
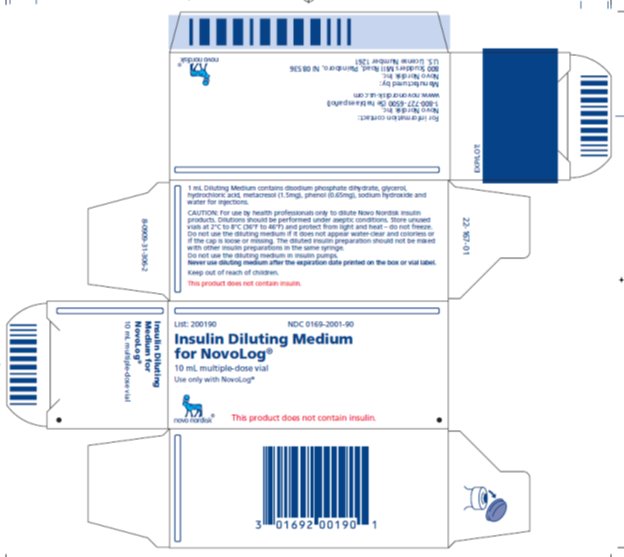
Insulin Diluting Medium for NovoLog water injection 1 mL/mL Injection, Solution
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Insulin Analog class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- It can seem a little odd at first. In these products, sterile water plays the essential role of carrying or dissolving the actual active medication — like insulin — so it can be sa...
- Why is 'water' listed as the active ingredient on my medicine?
- No — these are very different products that should never be used interchangeably. Sterile Water for Injection is used only as a diluent for other drugs given by needle, and it must...
- Is Sterile Water for Injection the same as the eye wash or the irrigation product?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
1.5 mg / 1 mL
UNII GGO4Y809LO
Metacresol is a preservative derived from coal tar or petroleum. It prevents bacterial and fungal growth in liquid medicines, helping keep the product safe and stable during storage.
-
0.65 mg / 1 mL
UNII 339NCG44TV
Phenol is a chemical compound derived from coal tar or petroleum. It serves as a preservative and antimicrobial agent in medicines, helping prevent bacterial and fungal growth to keep the product stable and safe during storage.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 94255I6E2T
Sodium phosphate dibasic dihydrate is a salt that helps control the acidity level of a medicine. It acts as a buffer and pH regulator to keep the medication stable and effective.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Insulin Diluting Medium for NovoLog 1 mL/mLthis 00169-2001-90 | Novo | 1 vial | — | — | FDA listed | — |
| Insulin Diluting Medium for Garzulys 1 mL/mL 71288-0909-10 | Meitheal | 1 vial | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00169-2001-90 You're viewing this | 1 VIAL, GLASS in 1 CARTON (0169-2001-90) / 10 mL in 1 VIAL, GLASS | 2018-08-01 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE NOVOLOG is indicated to improve glycemic control in adults and pediatric patients with diabetes mellitus. NOVOLOG is rapid acting human insulin analog indicated to improve glycemic control in adults and pediatric patients with diabetes mellitus ( 1 ).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION See Full Prescribing Information for important preparation, administration, and dosage instructions ( 2.1, 2.2, 2.3, 2.4, 2.5 ). • Subcutaneous injection ( 2.2 ): o Inject subcutaneously within 5-10 minutes before a meal into the abdominal area, thigh, buttocks or upper arm. o Rotate injection sites within the same region from one injection to the next to reduce risk of lipodystrophy and localized cutaneous amyloidosis. o Should generally be used in regimens with an intermediate- or long-acting insulin. • Continuous Subcutaneous Infusion (Insulin Pump) ( 2.2 ): o Refer to the insulin infusion pump user manual to see if NOVOLOG can be used.
Use in accordance with the insulin pump instructions for use. o Administer by continuous subcutaneous infusion using an insulin pump in a region recommended in the instructions from the pump manufacturer. o Rotate the injection sites within the same region from one injection to the next to reduce the risk of lipodystrophy and localized cutaneous amyloidosis. o Do not mix with other insulins or diluents in the pump. • Intravenous Administration ( 2.2 ) : o Dilute NOVOLOG to concentrations from 0.05 unit/mL to 1 unit/mL insulin aspart in infusion systems using polypropylene infusion bags. o NOVOLOG is stable in infusion fluids such as 0.9% Sodium Chloride Injection, USP. • Individualize and adjust the dosage of NOVOLOG based on route of administration, the individual's metabolic needs, blood glucose monitoring results and glycemic control goal ( 2.4 ). • Dosage adjustments may be needed with changes in physical activity, changes in meal patterns (i.e., macronutrient content or timing of food intake), changes in renal or hepatic function or during acute illness ( 2.4 ).
2.1Important Preparation and Administration Instructions • Always check insulin labels before administration [see Warnings and Precautions ( 5.4 )] . • Inspect NOVOLOG visually before use. It should appear clear and colorless. Do not use NOVOLOG if particulate matter or coloration is seen. • In patients with visual impairment, use: o NOVOLOG FlexPen and NOVOLOG FlexTouch with caution in those who may rely on audible clicks to dial their dose. o PenFill cartridges with caution. • Do not mix NOVOLOG with other insulins when administering using a continuous subcutaneous infusion pump.
2.2Preparation and Administration Instructions for the Approved Routes of Administration Subcutaneous Injection • Inject NOVOLOG subcutaneously within 5-10 minutes before a meal into the abdominal area, thigh, buttocks or upper arm. • Rotate injection sites within the same region from one injection to the next to reduce the risk of lipodystrophy and localized cutaneous amyloidosis. Do not inject into areas of lipodystrophy or localized cutaneous amyloidosis [see Warnings and Precautions ( 5.2 ) and Adverse Reactions ( 6.1 , 6.3 )]. • Dial the NOVOLOG FlexPen and FlexTouch in 1-unit increments. • Generally use NOVOLOG (administered by subcutaneous injection) in regimens with an intermediate- or long-acting insulin. • May dilute NOVOLOG with Insulin Diluting Medium for NOVOLOG for subcutaneous injection.
Diluting one part NOVOLOG to: o Nine parts diluent will yield a concentration one-tenth that of NOVOLOG (equivalent to U-10). o One part diluent will yield a concentration one-half that of NOVOLOG (equivalent to U-50). Continuous Subcutaneous Infusion (Insulin Pump) • Can use this NOVOLOG product with the continuous subcutaneous insulin infusion pumps labeled for use with NOVOLOG (insulin aspart). Refer to the insulin pump user manual to see if NOVOLOG can be used.
Use NOVOLOG in accordance with the insulin pump system’s instructions for use. • Train patients using continuous subcutaneous insulin infusion pump therapy to administer insulin by injection and have alternate insulin therapy available in case of pump failure. • Administer NOVOLOG by continuous subcutaneous infusion in a region recommended in the instructions fro…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: 100 units/mL (U-100) is a clear and colorless solution available as: • 10 mL multiple-dose vial • 3 mL single-patient-use PenFill prefilled cartridge for the 3 mL PenFill cartridge delivery device with NovoFine ® disposable needles • 3 mL single-patient-use FlexPen prefilled pen • 3 mL single-patient-use FlexTouch prefilled pen Injection: 100 units/mL (U-100) of insulin aspart available as: • 10 mL multiple-dose vial ( 3 ) • 3 mL single-patient-use PenFill prefilled cartridge for the 3 mL PenFill cartridge delivery device with NovoFine ® disposable needles ( 3 ) • 3 mL single-patient-use FlexPen ® prefilled pen ( 3 ) • 3 mL single-patient-use FlexTouch ® prefilled pen ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS NOVOLOG is contraindicated: • During episodes of hypoglycemia [see Warnings and Precautions ( 5.3 )] • In patients with hypersensitivity to NOVOLOG or one of its excipients, [see Warnings and Precautions ( 5.5 )] • During episodes of hypoglycemia ( 4 ). • Hypersensitivity to NOVOLOG or one of its excipients.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Never share a NOVOLOG FlexPen or a NOVOLOG FlexTouch, PenFill cartridge or PenFill cartridge device between patients, even if the needle is changed ( 5.1 ). • Hyperglycemia or hypoglycemia with changes in insulin regimen: Make changes to a patient’s insulin regimen (e.g., insulin strength, manufacturer, type, injection site or method of administration) under close medical supervision with increased frequency of blood glucose monitoring ( 5.2 ). • Hypoglycemia: May be life-threatening. Increase frequency of glucose monitoring with changes to: insulin dosage, concomitantly administered glucose lowering medications, meal pattern, physical activity; and in patients with renal or hepatic impairments and hypoglycemia unawareness ( 5.
3). • Medication Errors: Accidental mix-ups between insulin products can occur. Instruct patients to check insulin labels before injection ( 5. 4). • Hypersensitivity reactions: Severe, life-threatening, generalized allergy, including anaphylaxis, may occur.
Discontinue NOVOLOG, treat, and monitor, if indicated ( 5.5 ). • Hypokalemia: May be life-threatening. Monitor potassium levels in patients at risk of hypokalemia and treat if indicated ( 5. 6). • Fluid retention and heart failure with concomitant use of thiazolidinediones (TZDs): Observe for signs and symptoms of heart failure; consider dosage reduction or discontinuation if heart failure occurs ( 5.7 ). • Hyperglycemia and Ketoacidosis Due to Insulin Pump Device Malfunction: Monitor glucose and administer NOVOLOG by subcutaneous injection if pump malfunction occurs ( 5.8 ).
5.1Never Share a NOVOLOG FlexPen, NOVOLOG FlexTouch, PenFill Cartridge, or PenFill Cartridge Device between Patients NOVOLOG FlexPen, NOVOLOG FlexTouch, PenFill cartridge, and PenFill cartridge devices should never be shared between patients, even if the needle is changed. Patients using NOVOLOG vials must never share needles or syringes with another person. Sharing poses a risk for transmission of blood-borne pathogens.
5.2Hyperglycemia or Hypoglycemia with Changes in Insulin Regimen Changes in an insulin regimen (e.g., insulin strength, manufacturer, type, injection site or method of administration) may affect glycemic control and predispose to hypoglycemia [see Warnings and Precautions ( 5.3 )] or hyperglycemia. Repeated insulin injections into areas of lipodystrophy or localized cutaneous amyloidosis have been reported to result in hyperglycemia; and a sudden change in the injection site (to an unaffected area) has been reported to result in hypoglycemia [see Adverse Reactions ( 6.1 , 6.3 )].
Make any changes to a patient’s insulin regimen under close medical supervision with increased frequency of blood glucose monitoring. Advise patients who have repeatedly injected into areas of lipodystrophy or localized cutaneous amyloidosis to change the injection site to unaffected areas and closely monitor for hypoglycemia. For patients with type 2 diabetes, dosage adjustments of concomitant anti-diabetic products may be needed.
5.3Hypoglycemia Hypoglycemia is the most common adverse reaction of all insulins, including NOVOLOG. Severe hypoglycemia can cause seizures, may lead to unconsciousness, may be life threatening or cause death. Hypoglycemia can impair concentration ability and reaction time; this may place an individual and others at risk in situations where these abilities are important (e.g., driving or operating other machinery).
Hypoglycemia can happen suddenly and symptoms may differ in each individual and change over time in the same individual. Symptomatic awareness of hypoglycemia may be less pronounced in patients with longstanding diabetes in patients with diabetic nerve disease, in patients using medications that block the sympathetic nervous system (e.g., beta-blockers) [see Drug Interactions (7) ] , or in patients who experience recurrent hypoglycemia. Risk Factors for Hypoglycemia The risk of hypoglycemia after an injection is rel…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are also discussed elsewhere: • Hypoglycemia [see Warnings and Precautions ( 5.3 )] • Hypoglycemia Due to Medication Errors [see Warnings and Precautions (5.4 )] • Hypersensitivity reactions [see Warnings and Precautions ( 5.5 )] • Hypokalemia [see Warnings and Precautions ( 5.6 )] Adverse reactions observed with NOVOLOG include: hypoglycemia, allergic reactions, local injection site reactions, lipodystrophy, rash, and pruritus ( 6 ). To report SUSPECTED ADVERSE REACTIONS, contact Novo Nordisk Inc. at 1-800-727-6500 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying designs, the adverse reaction rates reported in one clinical trial may not be easily compared to those rates reported in another clinical trial, and may not reflect the rates actually observed in clinical practice. The safety of NOVOLOG was evaluated in two treat-to-target trials of 6 months duration, conducted in patients with type 1 diabetes or type 2 diabetes [see Clinical Studies (14) ]. The data in Table 1 reflect the exposure of 596 patients with type 1 diabetes to NOVOLOG in one clinical trial with a mean exposure duration to NOVOLOG of 24 weeks.
The mean age was 39 years. Fifty-one percent were male, 94% were Caucasian, 2% were Black and 4% were other races. The mean body mass index (BMI) was 25.6 kg/m 2 .
The mean duration of diabetes was 15.7 years and the mean HbA 1c at baseline was 7.9%. The data in Table 2 reflect the exposure of 91 patients with type 2 diabetes to NOVOLOG in one clinical trial with a mean exposure duration to NOVOLOG of 24 weeks. The mean age was 57 years.
Sixty-three percent were male, 76% were Caucasian, 9% were Black and 15% were other races. The mean BMI was 29.7 kg/m 2 . The mean duration of diabetes was 12.7 years and the mean HbA 1c at baseline was 8.1%.
Common adverse reactions were defined as events that occurred in ≥5%, excluding hypoglycemia, of the population studied. Common adverse events that occurred at the same rate or greater for NOVOLOG-treated patients than in comparator-treated patients during clinical trials in patients with type 1 diabetes mellitus and type 2 diabetes mellitus (other than hypoglycemia) are listed in Table 1 and Table 2, respectively. Table 1: Adverse reactions that occurred in ≥ 5% of Type 1 Diabetes Mellitus Adult Patients treated with NOVOLOG and at the same rate or greater on NOVOLOG than on comparator NOVOLOG + NPH (%) (n= 596) Regular Human Insulin + NPH (%) (n= 286) Headache 12 10 Injury accidental 11 10 Nausea 7 5 Diarrhea 5 3 Table 2: Adverse reactions that occurred in ≥ 5% of Type 2 Diabetes Mellitus Adult Patients treated with NOVOLOG and at the same rate or greater on NOVOLOG than on comparator NOVOLOG + NPH (%) (n= 91) Human Regular Insulin + NPH (%) (n= 91) Hyporeflexia 11 7 Onychomycosis 10 5 Sensory disturbance 9 7 Urinary tract infection 8 7 Chest pain 5 3 Headache 5 3 Skin disorder 5 2 Abdominal pain 5 1 Sinusitis 5 1 Severe Hypoglycemia Hypoglycemia is the most commonly observed adverse reaction in patients using insulin, including NOVOLOG .
The rates of reported hypoglycemia depend on the definition of hypoglycemia used, diabetes type, insulin dose, intensity of glucose control, background therapies, and other intrinsic and extrinsic patient factors. For these reasons, comparing rates of hypoglycemia in clinical trials for NOVOLOG with the incidence of hypoglycemia for other products may be misleading and also, may not be representative of hypoglycemia rates that will occur in clinical practice. Severe hypoglycemia was defined as hypoglycemia associated with central nervous system symptoms and requiring the intervention of another person or hospitalization.
The incidence of severe hypoglycemia in: • Adult and pediatric patients with type 1 diabetes mellitus who received subcutaneous NOVOLOG was 17% at 24 weeks and 6% at 24 weeks, respective…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS The table below presents clinically significant drug interactions with NOVOLOG. Drugs That May Increase the Risk of Hypoglycemia Drugs: Antidiabetic agents, ACE inhibitors, angiotensin II receptor blocking agents, disopyramide, fibrates, fluoxetine, monoamine oxidase inhibitors, pentoxifylline, pramlintide, salicylates, somatostatin analog (e.g., octreotide), and sulfonamide antibiotics. Intervention: Dose adjustment and increased frequency of glucose monitoring may be required when NOVOLOG is concomitantly administered with these drugs.
Drugs That May Decrease the Blood Glucose Lowering Effect of NOVOLOG Drugs: Atypical antipsychotics (e.g., olanzapine and clozapine), corticosteroids, danazol, diuretics, estrogens, glucagon, isoniazid, niacin, oral contraceptives, phenothiazines, progestogens (e.g., in oral contraceptives), protease inhibitors, somatropin, sympathomimetic agents (e.g., albuterol, epinephrine, terbutaline), and thyroid hormones. Intervention: Dose adjustment and increased frequency of glucose monitoring may be required when NOVOLOG is concomitantly administered with these drugs.
Drugs That May Increase or Decrease the Blood Glucose Lowering Effect of NOVOLOG Drugs: Alcohol, beta-blockers, clonidine, and lithium salts. Pentamidine may cause hypoglycemia, which may sometimes be followed by hyperglycemia. Pentamidine may cause hypoglycemia, which may sometimes be followed by hyperglycemia.
Intervention: Dose adjustment and increased frequency of glucose monitoring may be required when NOVOLOG is concomitantly administered with these drugs. Drugs That May Blunt Signs and Symptoms of Hypoglycemia Drugs: Beta-blockers, clonidine, guanethidine and reserpine Intervention: Increased frequency of glucose monitoring may be required when NOVOLOG is concomitantly administered with these drugs. • Drugs that may increase the risk of hypoglycemia: antidiabetic agents, ACE inhibitors, angiotensin II receptor blocking agents, disopyramide, fibrates, fluoxetine, monoamine oxidase inhibitors, pentoxifylline, pramlintide, salicylates, somatostatin analog (e.g., octreotide), and sulfonamide antibiotics ( 7 ). • Drugs that may decrease the blood glucose lowering effect: atypical antipsychotics, corticosteroids, danazol, diuretics, estrogens, glucagon, isoniazid, niacin, oral contraceptives, phenothiazines, progestogens (e.g., in oral contraceptives), protease inhibitors, somatropin, sympathomimetic agents (e.g., albuterol, epinephrine, terbutaline), and thyroid hormones ( 7 ). • Drugs that may increase or decrease the blood glucose lowering effect: alcohol, beta-blockers, clonidine, lithium salts, and pentamidine ( 7 ). • Drugs that may blunt the signs and symptoms of hypoglycemia: beta-blockers, clonidine, guanethidine, and reserpine ( 7 ).
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Available information from published randomized controlled trials with insulin aspart use during the second trimester of pregnancy have not reported an association with insulin aspart and major birth defects or adverse maternal or fetal outcomes [see Data] . There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy [see Clinical Considerations] . In animal reproduction studies, administration of subcutaneous insulin aspart to pregnant rats and rabbits during the period of organogenesis did not cause adverse developmental effects at exposures 8-times and equal to the human subcutaneous dose of 1 unit/kg/day, respectively.
Pre- and post-implantation losses and visceral/skeletal abnormalities were seen at higher exposures, which are considered secondary to maternal hypoglycemia. These effects were similar to those observed in rats administered regular human insulin [see Data] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
The estimated background risk of major birth defects is 6 to 10% in women with pre-gestational diabetes with a periconceptional HbA 1c >7% and has been reported to be as high as 20 to 25% in women with a periconceptional HbA 1c >10%. The estimated background risk of miscarriage for the indicated population is unknown. Clinical Considerations Disease-Associated Maternal and/or Embryo-Fetal Risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, preeclampsia, spontaneous abortions, preterm delivery, and delivery complications.
Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity. Data Human Data Published data from 5 randomized controlled trials of 441 pregnant women with diabetes mellitus treated with insulin aspart during the late 2 nd trimester of pregnancy did not identify an association of insulin aspart with major birth defects or adverse maternal or fetal outcomes. However, these studies cannot definitely establish the absence of any risk because of methodological limitations, including a variable duration of treatment and small size of the majority of the trials.
Animal Data Fertility, embryo-fetal and pre- and postnatal development studies have been performed with insulin aspart and regular human insulin in rats and rabbits. In a combined fertility and embryo-fetal development study in rats, insulin aspart was administered before mating, during mating, and throughout pregnancy. Further, in a pre- and postnatal development study insulin aspart was given throughout pregnancy and during lactation to rats.
In an embryo-fetal development study insulin aspart was given to female rabbits during organogenesis. The effects of insulin aspart did not differ from those observed with subcutaneous regular human insulin. Insulin aspart, like human insulin, caused pre- and post-implantation losses and visceral/skeletal abnormalities in rats at a dose of 200 units/kg/day (approximately 32 times the human subcutaneous dose of 1 unit/kg/day, based on human exposure equivalents) and in rabbits at a dose of 10 units/kg/day (approximately three times the human subcutaneous dose of 1 unit/kg/day, based on human exposure equivalents).
No significant effects were observed in rats at a dose of 50 units/kg/day and in rabbits at a dose of 3 units/kg/day. These doses are approximately 8 times the human subcutaneous dose of 1 unit/kg/day for rats and equal to the human subcutaneous dose of 1 unit/kg/day for rabbits, based on human exposure equivalents. The effects are considered secondary to maternal hypoglycemia.
8.2Lactation Risk Summary There are no data on the presence of NOVOLOG in human milk, the effects on the breastfed infant, or the effect on milk production. One small published study repor…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available information from published randomized controlled trials with insulin aspart use during the second trimester of pregnancy have not reported an association with insulin aspart and major birth defects or adverse maternal or fetal outcomes [see Data] . There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy [see Clinical Considerations] . In animal reproduction studies, administration of subcutaneous insulin aspart to pregnant rats and rabbits during the period of organogenesis did not cause adverse developmental effects at exposures 8-times and equal to the human subcutaneous dose of 1 unit/kg/day, respectively.
Pre- and post-implantation losses and visceral/skeletal abnormalities were seen at higher exposures, which are considered secondary to maternal hypoglycemia. These effects were similar to those observed in rats administered regular human insulin [see Data] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
The estimated background risk of major birth defects is 6 to 10% in women with pre-gestational diabetes with a periconceptional HbA 1c >7% and has been reported to be as high as 20 to 25% in women with a periconceptional HbA 1c >10%. The estimated background risk of miscarriage for the indicated population is unknown. Clinical Considerations Disease-Associated Maternal and/or Embryo-Fetal Risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, preeclampsia, spontaneous abortions, preterm delivery, and delivery complications.
Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity. Data Human Data Published data from 5 randomized controlled trials of 441 pregnant women with diabetes mellitus treated with insulin aspart during the late 2 nd trimester of pregnancy did not identify an association of insulin aspart with major birth defects or adverse maternal or fetal outcomes. However, these studies cannot definitely establish the absence of any risk because of methodological limitations, including a variable duration of treatment and small size of the majority of the trials.
Animal Data Fertility, embryo-fetal and pre- and postnatal development studies have been performed with insulin aspart and regular human insulin in rats and rabbits. In a combined fertility and embryo-fetal development study in rats, insulin aspart was administered before mating, during mating, and throughout pregnancy. Further, in a pre- and postnatal development study insulin aspart was given throughout pregnancy and during lactation to rats.
In an embryo-fetal development study insulin aspart was given to female rabbits during organogenesis. The effects of insulin aspart did not differ from those observed with subcutaneous regular human insulin. Insulin aspart, like human insulin, caused pre- and post-implantation losses and visceral/skeletal abnormalities in rats at a dose of 200 units/kg/day (approximately 32 times the human subcutaneous dose of 1 unit/kg/day, based on human exposure equivalents) and in rabbits at a dose of 10 units/kg/day (approximately three times the human subcutaneous dose of 1 unit/kg/day, based on human exposure equivalents).
No significant effects were observed in rats at a dose of 50 units/kg/day and in rabbits at a dose of 3 units/kg/day. These doses are approximately 8 times the human subcutaneous dose of 1 unit/kg/day for rats and equal to the human subcutaneous dose of 1 unit/kg/day for rabbits, based on human exposure equivalents. The effects are considered secondary to maternal hypoglycemia.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of NOVOLOG to improve glycemic control have been established in pediatric patients with diabetes mellitus. Use of NOVOLOG for this indication is supported by evidence from an adequate and well-controlled study in 283 pediatric patients with type 1 diabetes mellitus aged 6 to 18 years and from studies in adults with diabetes mellitus [see Adverse Reactions ( 6.1 ), Clinical Pharmacology ( 12.3 ), and Clinical Studies ( 14 )] .
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of patients (n=1,375) treated with NOVOLOG in 3 controlled clinical studies, 2.6% (n=36) were 65 years of age or over. One-half of these patients had type 1 diabetes (18/1285) and the other half had type 2 diabetes (18/90). The HbA 1c response to NOVOLOG, as compared to regular human insulin, did not differ by age.
🆘 Overdosage ▾
10 OVERDOSAGE Excess insulin administration may cause hypoglycemia and hypokalemia [see Warnings and Precautions ( 5.3 , 5.6 )] . Mild episodes of hypoglycemia usually can be treated with oral glucose. Adjustments in drug dosage, meal patterns, or exercise may be needed.
More severe episodes with coma, seizure, or neurologic impairment may be treated with intramuscular/subcutaneous glucagon or concentrated intravenous glucose. Sustained carbohydrate intake and observation may be necessary because hypoglycemia may recur after apparent clinical recovery. Hypokalemia must be corrected appropriately.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The primary activity of insulin, including NOVOLOG is the regulation of glucose metabolism. Insulin and its analogs lower blood glucose by stimulating peripheral glucose uptake, especially by skeletal muscle and fat, and by inhibiting hepatic glucose production. Insulin inhibits lipolysis and proteolysis, and enhances protein synthesis.
12.2Pharmacodynamics Pharmacodynamics of NOVOLOG After Subcutaneous Administration The pharmacodynamic profile of NOVOLOG given subcutaneously in 22 patients with type 1 diabetes is shown in Figure 2. The maximum glucose-lowering effect of NOVOLOG occurred between 1 and 3 hours after subcutaneous injection (0.15 units/kg). The duration of action for NOVOLOG is 3 to 5 hours.
The time course of action of insulin and insulin analogs such as NOVOLOG may vary considerably in different individuals or within the same individual. The parameters of NOVOLOG activity (time of onset, peak time and duration) as designated in Figure 2 should be considered only as general guidelines. The rate of insulin absorption and onset of activity is affected by the site of injection, exercise, and other variables [see Warnings and Precautions ( 5.3 )] .
Figure 2. Serial mean serum glucose collected up to 6 hours following a single 0.15 units/kg pre-meal dose of NOVOLOG (solid curve) or regular human insulin (hatched curve) injected immediately before a meal in 22 patients with type 1 diabetes. Pharmacodynamics of NOVOLOG After Intravenous Administration A double-blind, randomized, two-way crossover study in 16 patients with type 1 diabetes demonstrated that intravenous infusion of NOVOLOG resulted in a blood glucose profile that was similar to that after intravenous infusion with regular human insulin.
NOVOLOG or human insulin was infused until the patient’s blood glucose decreased to 36 mg/dL, or until the patient demonstrated signs of hypoglycemia (rise in heart rate and onset of sweating), defined as the time of autonomic reaction (R) (see Figure 3). Figure 3. Mean blood glucose profiles following intravenous infusion of NOVOLOG (hatched curve) and regular human insulin (solid curve) in 16 patients with type 1 diabetes.
R represents the time of autonomic reaction. Figure 2 Fig. 3 - Pharmacodynamics Graph - Time of Autonomic Reaction
12.3Pharmacokinetics Pharmacokinetics of subcutaneous administration of NOVOLOG is presented below. Absorption and Bioavailability In studies in healthy volunteers (total n=107) and patients with type 1 diabetes (total n=40), the median time to maximum concentration of NOVOLOG in these trials was 40 to 50 minutes versus 80 to 120 minutes, for regular human insulin respectively. The relative bioavailability of NOVOLOG (0.15 units/kg) compared to regular human insulin indicates that the two insulins are absorbed to a similar extent.
In a clinical trial in patients with type 1 diabetes, NOVOLOG and regular human insulin, both administered subcutaneously at a dose of 0.15 units/kg body weight, reached mean maximum concentrations of 82 and 36 mU/L , respectively. Distribution Insulin aspart has a low binding affinity to plasma proteins (<10%), similar to that seen with regular human insulin. Figure 4.
Serial mean serum free insulin concentration collected up to 6 hours following a single 0.15 units/kg pre-meal dose of NOVOLOG (solid curve) or regular human insulin (hatched curve) injected immediately before a meal in 22 patients with type 1 diabetes. Metabolism and Elimination In a randomized, double-blind, crossover study 17 healthy Caucasian male subjects between 18 and 40 years of age received an intravenous infusion of either NOVOLOG or regular human insulin at 1.5 mU/kg/min for 120 minutes. The mean insulin clearance was similar for the two groups with mean values of
1.2 L/h/kg for the NOVOLOG group and
1.2L/h/kg for the regular human insulin group. After subcutaneous administration in normal male volunteers (n=24), NOVOLOG was eliminat…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The primary activity of insulin, including NOVOLOG is the regulation of glucose metabolism. Insulin and its analogs lower blood glucose by stimulating peripheral glucose uptake, especially by skeletal muscle and fat, and by inhibiting hepatic glucose production. Insulin inhibits lipolysis and proteolysis, and enhances protein synthesis.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied NOVOLOG (insulin aspart) injection 100 units/mL (U-100) is available as a clear and colorless solution in: One 10 mL multiple-dose vial per carton NDC 0169-7501-11 ReliOn ® brand NDC 0169-2100-11 Five 3 mL single-patient-use FlexPen prefilled pens per carton NDC 0169-6339-10 ReliOn ® brand NDC 0169-2101-25 Five 3 mL single-patient-use PenFill prefilled cartridges* per carton NDC 0169-3303-12 Five 3 mL single-patient-use FlexTouch prefilled pens per carton NDC 0169-6338-10 *NOVOLOG PenFill cartridges are designed for use with compatible insulin delivery devices with NovoFine disposable needles.
FlexPen and FlexTouch can be used with NovoFine or NovoTwist disposable needles. The NOVOLOG FlexPen and FlexTouch dial in 1-unit increments.
16.2Recommended Storage Dispense in the original sealed carton with the enclosed Instructions for Use. Store unused NOVOLOG in a refrigerator between 2°C to 8°C (36°F to 46°F). Do not freeze NOVOLOG and do not use NOVOLOG if it has been frozen.
Do not expose NOVOLOG to excessive heat or light. Do not withdraw NOVOLOG into a syringe and store for later use. Always remove and discard the needle after each injection from the NOVOLOG FlexPen or NOVOLOG FlexTouch and store without a needle attached.
The storage conditions are summarized in the following table: Table 9. Storage Conditions for vial, PenFill cartridges, NOVOLOG FlexPen, and NOVOLOG FlexTouch NOVOLOG presentation Not in-use (unopened) Room Temperature (up to 30°C [86°F]) Not in-use (unopened) Refrigerated (2°C to 8°C [36°F to 46°F]) In-use (opened) Room Temperature (up to 30°C [86°F]) 10 mL multiple-dose vial 28 days Until expiration date 28 days* (refrigerated/room temperature) 3 mL single-patient-use PenFill cartridges 28 days Until expiration date 28 days (Do not refrigerate) 3 mL single-patient-use FlexPen 28 days Until expiration date 28 days (Do not refrigerate) 3 mL single-patient-use FlexTouch 28 days Until expiration date 28 days (Do not refrigerate) *For insulin pump use, the total in-use time is 19 days, including 7 days pump in-use time.
Storage in External Insulin Pump: Change the NOVOLOG in the pump reservoir at least every 7 days or according to the pump user manual, whichever is shorter, or after exposure to temperatures that exceed 37°C (98.6°F). Storage of Diluted NOVOLOG NOVOLOG diluted with Insulin Diluting Medium for NOVOLOG to a concentration equivalent to U-10 or equivalent to U-50 prepared as indicated under Dosage and Administration (2.2) may remain in patient use at temperatures up to 30°C (86°F) for 28 days. Storage of NOVOLOG in Intravenous Infusion Fluids Infusion bags prepared as indicated under Dosage and Administration (2.2) are stable at room temperature for 24 hours.
Some insulin will be initially adsorbed to the material of the infusion.
📦 Storage and Handling ▾
16.2Recommended Storage Dispense in the original sealed carton with the enclosed Instructions for Use. Store unused NOVOLOG in a refrigerator between 2°C to 8°C (36°F to 46°F). Do not freeze NOVOLOG and do not use NOVOLOG if it has been frozen.
Do not expose NOVOLOG to excessive heat or light. Do not withdraw NOVOLOG into a syringe and store for later use. Always remove and discard the needle after each injection from the NOVOLOG FlexPen or NOVOLOG FlexTouch and store without a needle attached.
The storage conditions are summarized in the following table: Table 9. Storage Conditions for vial, PenFill cartridges, NOVOLOG FlexPen, and NOVOLOG FlexTouch NOVOLOG presentation Not in-use (unopened) Room Temperature (up to 30°C [86°F]) Not in-use (unopened) Refrigerated (2°C to 8°C [36°F to 46°F]) In-use (opened) Room Temperature (up to 30°C [86°F]) 10 mL multiple-dose vial 28 days Until expiration date 28 days* (refrigerated/room temperature) 3 mL single-patient-use PenFill cartridges 28 days Until expiration date 28 days (Do not refrigerate) 3 mL single-patient-use FlexPen 28 days Until expiration date 28 days (Do not refrigerate) 3 mL single-patient-use FlexTouch 28 days Until expiration date 28 days (Do not refrigerate) *For insulin pump use, the total in-use time is 19 days, including 7 days pump in-use time.
Storage in External Insulin Pump: Change the NOVOLOG in the pump reservoir at least every 7 days or according to the pump user manual, whichever is shorter, or after exposure to temperatures that exceed 37°C (98.6°F). Storage of Diluted NOVOLOG NOVOLOG diluted with Insulin Diluting Medium for NOVOLOG to a concentration equivalent to U-10 or equivalent to U-50 prepared as indicated under Dosage and Administration (2.2) may remain in patient use at temperatures up to 30°C (86°F) for 28 days. Storage of NOVOLOG in Intravenous Infusion Fluids Infusion bags prepared as indicated under Dosage and Administration (2.2) are stable at room temperature for 24 hours.
Some insulin will be initially adsorbed to the material of the infusion.
📋 Description ▾
11 DESCRIPTION Insulin aspart is a rapid-acting human insulin analog homologous with regular human insulin with the exception of a single substitution of the amino acid proline by aspartic acid in position B28, and is produced by recombinant DNA technology utilizing Saccharomyces cerevisiae (baker's yeast). Insulin aspart has the empirical formula C 256 H 381 N 65 0 79 S 6 and a molecular weight of 5825.8 Da. Figure 1.
Structural formula of insulin aspart. NOVOLOG (insulin aspart) injection is a sterile, clear, and colorless solution for subcutaneous or intravenous use. Each mL contains 100 units of insulin aspart and the inactive ingredients: disodium hydrogen phosphate dihydrate (1.25 mg), glycerin (16.0 mg), metacresol (1.72 mg), phenol (1.50 mg), sodium chloride (0.58 mg), zinc (19.6 mcg), and Water for Injection, USP.
NOVOLOG has a pH of 7.2-7.6. Hydrochloric acid 10% and/or sodium hydroxide 10% may be added to adjust pH. Fig.
1 - Structural Formula of Insulin Aspart
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use). Never Share a NOVOLOG FlexPen or a NOVOLOG FlexTouch, PenFill Cartridge or PenFill Cartridge Device between Patients Advise patients that they must never share NOVOLOG FlexPen, NOVOLOG FlexTouch, PenFill cartridge or PenFill cartridge devices with another person even if the needle is changed, because doing so carries a risk for transmission of blood-borne pathogens. Advise patients using NOVOLOG vials not to share needles or syringes with another person.
Sharing poses a risk for transmission of blood-borne pathogens [see Warnings and Precautions ( 5.1 )] . Hyperglycemia or Hypoglycemia Inform patients that hypoglycemia is the most common adverse reaction with insulin. Instruct patients on self-management procedures including glucose monitoring, proper injection technique, and management of hypoglycemia and hyperglycemia, especially at initiation of NOVOLOG therapy.
Instruct patients on handling of special situations such as intercurrent conditions (illness, stress, or emotional disturbances), an inadequate or skipped insulin dose, inadvertent administration of an increased insulin dose, inadequate food intake, and skipped meals. Instruct patients on the management of hypoglycemia [see Warnings and Precautions ( 5.3 )] . Inform patients that their ability to concentrate and react may be impaired as a result of hypoglycemia.
Advise patients who have frequent hypoglycemia or reduced or absent warning signs of hypoglycemia to use caution when driving or operating machinery. Advise patients that changes in insulin regimen can predispose to hyperglycemia or hypoglycemia and that changes in insulin regimen should be made under close medical supervision [see Warnings and Precautions (5.2)] . Hypoglycemia with Medication Errors Instruct patients to always check the insulin label before each injection to avoid mix-ups between insulin products [see Warnings and Precautions ( 5.3 )] .
Hypersensitivity Reactions Advise patients that hypersensitivity reactions have occurred with NOVOLOG. Inform patients of the symptoms of hypersensitivity reactions [see Warnings and Precautions ( 5.4 )] . Patients Using Continuous Subcutaneous Insulin Pumps • Train patients in both intensive insulin therapy with multiple injections and in the function of their pump and pump accessories. • This NOVOLOG product can be used with continuous subcutaneous insulin infusion pumps labeled for use with NOVOLOG (insulin aspart) - refer to the insulin pump user manual to see if NOVOLOG can be used.
See recommended infusion sets in the insulin pump user manual. • Instruct patients to replace insulin in the reservoir at least every 7 days or according to the user manual, whichever is shorter; infusion sets and infusion set insertion sites should be changed according to the manufacturer’s user manual. By following this schedule, patients avoid insulin degradation, infusion set occlusion, and loss of the insulin preservative. • Instruct patients to discard insulin exposed to temperatures higher than 37°C (98.6°F). • Instruct patients to inform physician and select a new site for infusion if infusion site becomes erythematous, pruritic, or thickened. • Instruct patients of the risk of rapid hyperglycemia and ketosis due to pump malfunction, infusion set occlusion, leakage, disconnection or kinking, and degraded insulin.
If these problems cannot be promptly corrected, instruct patients to resume therapy with subcutaneous insulin injection and contact their physician [see Warnings and Precautions (5) and How Supplied/Storage and Handling ( 16.2 )] . • Instruct patients of the risk of hypoglycemia from pump malfunction. If these problems cannot be promptly corrected, instruct patients to resume therapy with subcutaneous insulin injection and contact their physician [see Warnings and Precautions (5) and How Supplied/Storage and Handling…