
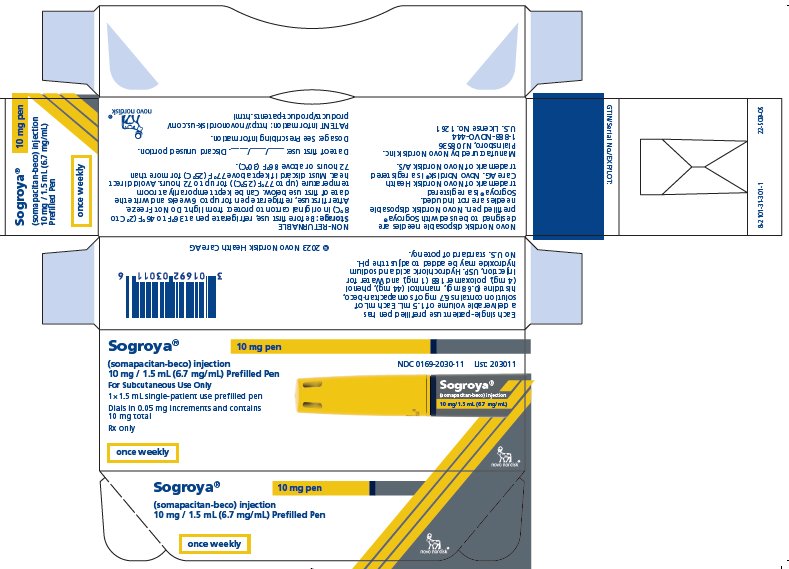
SOGROYA somapacitan-beco 6.7 mg/mL Injection, Solution, 1 syringe
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Somatropin and somatropin agonists class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Somapacitan-beco injection is used to replace growth hormone (a natural hormone produced by your body) in adults with growth hormone deficiency. Somapacitan-beco injection is also used to replace growth hormone and to increase growth in children 2.5 years of age or older with growth hormone deficiency. Somapacitan-beco is a human growth hormone (hGH) analog. It works by replacing growth hormones that are normally produced in the body.
Read the full MedlinePlus article ↗- Sogroya is specifically designed to last longer in the body. It attaches to a natural blood protein called albumin, which slows its breakdown so one weekly shot provides steady lev...
- Why does my doctor have me inject Sogroya only once a week instead of every day like older growth hormone shots?
- You can inject Sogroya into the upper arm, thigh, abdomen, or buttocks — all are approved injection sites. What really matters is rotating the spot each week. Using the same area r...
- Where exactly do I inject it, and does it matter if I use the same spot every week?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
0.68 mg / 1 mL
UNII 4QD397987E
An amino acid used as a buffer and stabilizer in medications. It helps maintain the pH balance and protects the active drug from breaking down during storage and use.
-
44 mg / 1 mL
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
4 mg / 1 mL
UNII 339NCG44TV
Phenol is a chemical compound derived from coal tar or petroleum. It serves as a preservative and antimicrobial agent in medicines, helping prevent bacterial and fungal growth to keep the product stable and safe during storage.
-
1 mg / 1 mL
UNII LQA7B6G8JG
A synthetic polymer made by combining water-soluble compounds. It acts as a surfactant and solubilizer to help mix oil and water-based ingredients, improving the medicine's texture and how active ingredients dissolve.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $1,925.93 | $2,888.90 / 1.5 ml |
| Medicare drug plans payPart D · Q2 2026 | $2,261.29 | $3,391.94 / 1.5 ml |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Sogroya 6.7 mg/mLthis 00169-2030-11 | Novo | 1 syringe | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Why the date isn’t exact: Biosimilar timing can change because patents may be challenged, settled, licensed, added or removed, and litigation can move the real date earlier or later.
🛈 What do these terms mean?
- Biologic patent
- A patent the reference product’s maker has publicly listed. A biosimilar generally can’t launch until these expire — unless they’re invalidated or resolved in a settlement.
- Reference-product exclusivity
- A flat 12 years of FDA market protection from the biologic’s first licensure (the BPCIA). No biosimilar can be licensed before it ends, regardless of patents.
- Interchangeable exclusivity
- The first interchangeable biosimilar can earn a period as the only interchangeable version (pharmacists can substitute it without the prescriber).
- Earliest biosimilar (LOE)
- The latest of all the dates above — the soonest a biosimilar can realistically reach the market. Litigation and settlements can move it earlier.
Biologics have no small-molecule “generics” — competition comes from FDA-licensed biosimilars, tracked in the FDA Purple Book.
| Code | What it grants | Expires |
|---|---|---|
| RefProduct | Reference-product exclusivity (12-year, BPCIA) — no biosimilar can be licensed before this date | Aug 28, 2032 |
Is there a biosimilar for SOGROYA 10 MG/1.5 ML PEN?
Why do different websites show different biosimilar dates?
Can a biosimilar launch before the last patent expires?
What does “current Purple Book estimate” mean?
What does “FDA listed” mean?
What does a patent or protection date mean here?
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00169-2030-11 You're viewing this | 1 SYRINGE, PLASTIC in 1 CARTON (0169-2030-11) / 1.5 mL in 1 SYRINGE, PLASTIC | 2023-05-01 | Active |
| 00169-2030-90 | 1 SYRINGE, PLASTIC in 1 CARTON (0169-2030-90) / 1.5 mL in 1 SYRINGE, PLASTIC | 2023-05-01 | Active |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 00169-2030-11?
What is the difference between NDC 00169-2030-11 and NDC 00169-2030-90?
What NDC number is used to bill for this package of SOGROYA somapacitan-beco 6.7 mg/mL Injection, Solution?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE SOGROYA is indicated for the treatment of pediatric patients aged 2.5 years and older with: • Growth failure due to inadequate secretion of endogenous growth hormone (GH). • Short stature born small for gestational age (SGA) and with no catch-up growth by 2 years of age. • Growth failure associated with Noonan syndrome (NS). • Idiopathic Short Stature (ISS). SOGROYA is indicated for the replacement of endogenous GH in adults with growth hormone deficiency (GHD). SOGROYA is a human growth hormone analog indicated for: Pediatric Patients: Treatment of pediatric patients aged 2.5 years and older with: • Growth failure due to inadequate secretion of endogenous growth hormone (GH).
( 1 ) • Short stature born small for gestational age (SGA) and with no catch-up growth by 2 years of age. ( 1 ) • Growth failure associated with Noonan syndrome (NS). ( 1 ) • Idiopathic Short Stature (ISS).
( 1 ) Adults: Replacement of endogenous growth hormone in adults with growth hormone deficiency (GHD). ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • SOGROYA treatment should be supervised by a healthcare provider who is experienced in the diagnosis and management of patients with growth hormone deficiency, pediatric patients born SGA, pediatric patients with NS, and pediatric patients with ISS. ( 2.1 ) • SOGROYA should be administered by subcutaneous injection once weekly, any time of the day, in the upper arms, thigh, abdomen or buttocks with regular rotation of injection site to avoid lipohypertrophy/lipoatrophy. ( 2.1 ) • See Full Prescribing Information for complete dosage, titration, and monitoring recommendations for pediatric and adult patients, including those aged 65 years and older, patients with hepatic impairment, and women receiving oral estrogen.
( 2.1 , 2.2 , 2.3 , 2.4 , 2.5 ) For pediatric patients : • GH deficiency: Initiate SOGROYA with a dosage of 0.16 mg/kg body weight once weekly for treatment-naïve patients and patients switching from daily growth hormone (somatropin). ( 2.3 ) • SGA/NS/ISS: Initiate SOGROYA with a dosage of 0.24 mg/kg body weight once weekly for treatment-naïve patients and patients switching from daily growth hormone (somatropin). ( 2.3 ) • Individualize dosage for each patient based on the growth response.
( 2.3 ) • Patients switching from daily human growth hormone to once-weekly SOGROYA should choose the preferred day for the weekly dose and stop final dose of daily treatment the day before (or at least 8 hours before) taking the first dose of once-weekly somapacitan-beco. ( 2.3 ) For adult patients with GHD : • Initiate SOGROYA with a dosage of 1.5 mg once weekly for treatment naïve patients and patients switching from daily growth hormone. ( 2.4 ) • Increase the weekly dosage every 2 to 4 weeks by approximately 0.5 mg to 1.5 mg until the desired response has been achieved.
( 2.4 ) • Titrate the dosage based on clinical response and serum insulin-like growth factor-1 (IGF-1) concentrations. ( 2.4 ) • The maximum recommended dosage for adult GHD is 8 mg once weekly. ( 2.4 )
2.1Important Dosing and Administration Information • SOGROYA treatment should be supervised by a healthcare provider who is experienced in the diagnosis and management of pediatric patients with growth failure due to GHD, pediatric patients born SGA, pediatric patients with NS, pediatric patients with ISS and/or adults with GHD [see Indications and Usage ( 1 )]. • SOGROYA should be administered by subcutaneous injection, once weekly, any time of the day, in the upper arms, thigh, abdomen or buttocks with weekly rotation of injection site. • Inspect visually for particulate matter and discoloration.
SOGROYA should be a clear to slightly opalescent and colorless to slightly yellow solution. If the solution is cloudy or contains particulate matter do not use. • Advise patients to read the PATIENT INFORMATION and INSTRUCTIONS FOR USE leaflets enclosed with the SOGROYA prefilled pen. • SOGROYA is available in 3 single-patient-use prefilled pens with 3 different dosing ranges ( Table 1 ). Table 1.
Strength and Dosing Range of SOGROYA Prefilled Pens Strength Dose increments (mg) Dose Delivery Range (mg) 5 mg/1.5 mL (3.3 mg/mL) 0.025 0.025 to 2 10 mg/1.5 mL (6.7 mg/mL) 0.05 0.05 to 4 15 mg/1.5 mL (10 mg/mL) 0.1 0.1 to 8
2.2Perform Fundoscopic Examination Prior to Initiation of SOGROYA • Perform fundoscopic examination before initiating treatment with SOGROYA to exclude preexisting papilledema. If papilledema is identified, evaluate the etiology and treat the underlying cause before initiating treatment with SOGROYA [see Warnings and Precautions ( 5.5 )].
2.3Recommended Dosage and Monitoring for Pediatric Patients • GH Deficiency: Recommended dosage of SOGROYA is 0.16 mg/kg based on actual body weight once weekly for treatment-naïve patients and patients switching from daily growth hormone (somatropin). • Small for Gestational Age (SGA), Noonan Syndrome (NS), and Idiopathic Short Stature (ISS): Recommended dosage of SOGROYA is 0.24 mg/kg…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS SOGROYA is a clear to slightly opalescent and colorless to slightly yellow solution available as follows: • Injection: 5 mg/1.5 mL (3.3 mg/mL) in a single-patient-use prefilled pen (teal) • Injection: 10 mg/1.5 mL (6.7 mg/mL) in a single-patient-use prefilled pen (yellow) • Injection: 15 mg/1.5 mL (10 mg/mL) in a single-patient-use prefilled pen (red) SOGROYA is a liquid solution available in a ready-to-use prefilled pen. Injection: 5 mg/1.5 mL (3.3 mg/mL) or 10 mg/1.5 mL (6.7 mg/mL) or 15 mg/1.5 mL (10 mg/mL) in a single-patient-use prefilled pen.
( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS SOGROYA is contraindicated in patients with: • Acute critical illness after open-heart surgery, abdominal surgery or multiple accidental trauma, or those with acute respiratory failure because of the risk of increased mortality with use of pharmacologic doses of SOGROYA [see Warnings and Precautions ( 5.1 )] . • Hypersensitivity to SOGROYA or any of its excipients. Systemic hypersensitivity reactions have been reported postmarketing with somatropin [see Warnings and Precautions ( 5.2 )] . • Pediatric patients with closed epiphyses. • Active malignancy [see Warnings and Precautions ( 5.3 )]. • Active proliferative or severe non-proliferative diabetic retinopathy. • Pediatric patients with Prader-Willi syndrome who are severely obese, have a history of upper airway obstruction or sleep apnea or have severe respiratory impairment due to risk of sudden death [see Warnings and Precautions ( 5.13 )] . • Acute critical illness ( 4 ) • Active malignancy ( 4 ) • Hypersensitivity to somapacitan-beco or excipients ( 4 ) • Active proliferative or severe non-proliferative diabetic retinopathy ( 4 ) • Closed epiphyses in children used for longitudinal growth promotion ( 4 ) • Children with Prader-Willi syndrome who are severely obese or have severe respiratory impairment due to risk of sudden death ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Severe Hypersensitivity : Serious hypersensitivity reactions, including anaphylactic reactions and angioedema, may occur. In the event of an allergic reaction, seek prompt medical attention. ( 5.2 ) • Increased Risk of Neoplasm : Monitor patients with preexisting tumors for progression or recurrence.
Increased risk of a second neoplasm in childhood cancer survivors treated with somatropin – in particular meningiomas in patients treated with radiation to the head for their first neoplasm. ( 5.3 ) • Glucose Intolerance and Diabetes Mellitus : SOGROYA may decrease insulin sensitivity, particularly at higher doses. Monitor glucose levels periodically in all patients receiving SOGROYA, especially in patients with existing diabetes mellitus or at risk for its development.
( 5.4 ) • Intracranial Hypertension (IH) : Perform fundoscopic examinations prior to initiation and periodically thereafter. If papilledema is identified prior to initiation, evaluate the etiology and treat the underlying cause before initiating. If papilledema occurs with SOGROYA, stop treatment.
( 5.5 ) • Fluid Retention : Was observed and may be dose dependent. Reduce dose as necessary. ( 5.6 ) • Hypoadrenalism : Monitor patients for reduced serum cortisol levels and/or need for glucocorticoid dose increases in those with known hypoadrenalism.
( 5.7 ) • Hypothyroidism : Monitor thyroid function periodically as hypothyroidism may occur or worsen after initiation of SOGROYA. ( 5.8 ) • Slipped Capital Femoral Epiphysis in Pediatric Patients : May develop. Evaluate children with the onset of a limp or persistent hip/knee pain.
( 5.9 ) • Progression of Preexisting Scoliosis in Pediatric Patients : May develop. ( 5.10 ) • Pancreatitis : Consider pancreatitis in patients with persistent severe abdominal pain. ( 5.11 ) • Lipohypertrophy/lipoatrophy : May occur if SOGROYA is administered in the same location over a long period of time.
Rotate injection sites on a regular basis. ( 5.12 )
5.1Increased Mortality in Patients with Acute Critical Illness Increased mortality has been reported after treatment with somatropin in patients with acute critical illness due to complications following open-heart surgery, abdominal surgery and multiple accidental trauma, as well as patients with acute respiratory failure [see Contraindications ( 4 )] . The safety of continuing SOGROYA treatment in patients receiving replacement doses for approved indications who concurrently develop these illnesses has not been established.
SOGROYA is not indicated for the treatment of non-GH deficient adults.
5.2Severe Hypersensitivity Serious systemic hypersensitivity reactions including anaphylactic reactions and angioedema have been reported with postmarketing use of somatropin. Inform patients and/or caregivers that such reactions are possible, and that prompt medical attention should be sought if an allergic reaction occurs. SOGROYA is contraindicated in patients with known hypersensitivity to somatropin or any excipients in SOGROYA [see Contraindications ( 4 )].
5.3Increased Risk of Neoplasms Active Malignancy There is an increased risk of malignancy progression with somatropin treatment in patients with active malignancy [see Contraindications ( 4 )] . Any preexisting malignancy should be inactive, and its treatment complete prior to instituting therapy with SOGROYA. Discontinue SOGROYA if there is evidence of recurrent activity.
Risk of Second Neoplasm in Pediatric Patients In childhood cancer survivors who were treated with radiation to the brain/head for their first neoplasm and who developed subsequent growth hormone deficiency (GHD) and were treated with somatropin, an increased risk of second neoplasm has been reported. Intracranial tumors, in particular meningiomas, were the most common of these second neoplasms. Monitor all patients with a history of GHD secondary to an intracranial neoplasm while on somatropin therapy for progression or recurrence of the…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse drug reactions are described elsewhere in the labeling: • Increased mortality in patients with acute critical illness [see Warnings and Precautions ( 5.1 )] • Severe hypersensitivity [see Warnings and Precautions ( 5.2 )] • Increased risk of neoplasms [see Warnings and Precautions ( 5.3 )] • Glucose intolerance and diabetes mellitus [see Warnings and Precautions ( 5.4 )] • Intracranial hypertension [see Warnings and Precautions ( 5.5 )] • Fluid retention [see Warnings and Precautions ( 5.6 )] • Hypoadrenalism [see Warnings and Precautions ( 5.7 )] • Hypothyroidism [see Warnings and Precautions ( 5.8 )] • Slipped capital femoral epiphysis in pediatric patients [see Warnings and Precautions ( 5.9 )] • Progression of preexisting scoliosis in pediatric patients [see Warnings and Precautions ( 5.10 )] • Pancreatitis [see Warnings and Precautions ( 5.11 )] • Lipohypertrophy/Lipoatrophy [see Warnings and Precautions ( 5.12 )] • Sudden death in pediatric patients with Prader-Willi syndrome [see Warnings and Precautions ( 5.13 )] • Common adverse reactions reported in pediatric patients treated with SOGROYA include: cough, diarrhea, ear infection, headache, injection site reaction, nasopharyngitis, pain in extremity, pyrexia, respiratory tract infection, and vomiting.
( 6.1 ) • Adult patients with GHD: Adverse reactions reported in >2% of patients treated with SOGROYA are: back pain, arthralgia, dyspepsia, sleep disorder, dizziness, tonsillitis, peripheral edema, vomiting, adrenal insufficiency, hypertension, blood creatine phosphokinase increase, weight increase, anemia. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Novo Nordisk Inc. at 1-800-727-6500 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Pediatric Patients with GHD SOGROYA 0.16 mg/kg/week was studied in a 52-week randomized, open-label, active-controlled, parallel-group clinical study in 200 treatment-naïve, prepubertal pediatric patients with growth hormone deficiency [see Clinical Studies ( 14.1 )] .
Table 2 shows common adverse reactions that occurred in ≥ 5% of patients treated with either SOGROYA or somatropin in this trial. Table 2. Adverse Reactions Occurring ≥5% in SOGROYA or Somatropin-treated Pediatric Patients (52 Weeks of Treatment) Somatropin (N=68) SOGROYA (N=132) Adverse Reactions % % Nasopharyngitis a 16.2
16.7Headache 8.8
12.1Pyrexia b 11.8
9.1Pain in extremity c 2.9
9.8Injection site reaction d 5.9
6.1Diarrhea e 5.9
4.5Nausea/vomiting f 5.9
4.5Bronchitis 7.4 3 a Nasopharyngitis in the SOGROYA treatment group included nasopharyngitis (11.4%), rhinitis (3.8%), pharyngitis streptococcal (0.8%), acute sinusitis (0.8%), nasal congestion (0.8%), pharyngitis (0.8%), and sinusitis (0.8%). b Pyrexia in the SOGROYA treatment group included pyrexia (8.3%) and hyperthermia (0.8%). c Pain in extremity in the SOGROYA treatment group included pain in extremity (9.1%) and growing pains (0.8%). d Injection site reaction in the SOGROYA treatment group included injection site bruising (1.5%), injection site pain (1.5%), injection site hematoma (1.5%), injection site reaction (0.8%), and injection site swelling (0.8%) e Diarrhea in the SOGROYA treatment group included diarrhea (2.3%), gastroenteritis viral (1.5%), and gastrointestinal viral infection (0.8%) f Nausea/vomiting in the SOGROYA treatment group included vomiting (4.5%) and nausea (1.5%) Pediatric Patients Born Small for Gestational Age and with no Catch-up Growth by 2 Years of Age SOGROYA 0.24 mg/kg/week was studied in a 52-week randomized, open-label, active-comparator, basket clinical study in GH treatment-naïve, pre-pubertal patients with sh…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 7 includes a list of drugs with clinically important drug interactions when administered concomitantly with SOGROYA and instructions for preventing or managing them. Table 7. Clinically Important Drug Interactions with SOGROYA Replacement Glucocorticoid Treatment Clinical Impact: Microsomal enzyme 11β-hydroxysteroid dehydrogenase type 1 (11βHSD-1) is required for conversion of cortisone to its active metabolite, cortisol, in hepatic and adipose tissue.
GH inhibits 11βHSD-1. Consequently, individuals with untreated GH deficiency have relative increases in 11βHSD-1 and serum cortisol. Initiation of SOGROYA may result in inhibition of 11βHSD-1 and reduced serum cortisol concentrations.
Intervention: Patients treated with glucocorticoid replacement for hypoadrenalism may require an increase in their maintenance or stress doses following initiation of SOGROYA [see Warnings and Precautions ( 5.7 )]. Examples: Cortisone acetate and prednisone may be affected more than others because conversion of these drugs to their biologically active metabolites is dependent on the activity of 11βHSD-1. Cytochrome P450-Metabolized Drugs Clinical Impact: Limited published data indicate that GH treatment increases cytochrome P450 (CP450)-mediated antipyrine clearance.
SOGROYA may alter the clearance of compounds known to be metabolized by CP450 liver enzymes. Intervention: Careful monitoring is advisable when SOGROYA is administered in combination with drugs metabolized by CP450 liver enzymes. Oral Estrogen Clinical Impact: Oral estrogens may reduce the serum IGF-1 response to SOGROYA.
Intervention: Patients receiving oral estrogen replacement may require higher SOGROYA dosages [see Dosage and Administration (2.5 )] . Insulin and/or Other Hypoglycemic Agents Clinical Impact: Treatment with SOGROYA may decrease insulin sensitivity, particularly at higher doses. Intervention: Patients with diabetes mellitus may require adjustment of their doses of insulin and/or other hypoglycemic agents [see Warnings and Precautions ( 5.4 )]. • Replacement Glucocorticoid Treatment : Patients treated with glucocorticoid for hypoadrenalism may require an increase in their maintenance or stress doses following initiation of SOGROYA.
( 7 ) • Cytochrome P450-Metabolized Drugs : SOGROYA may alter the clearance. Monitor carefully if used with SOGROYA. ( 7 ) • Oral Estrogen : Larger doses of SOGROYA may be required.
( 7 ) • Insulin and/or Other Antihyperglycemic Agents : Dose adjustment of insulin or antihyperglycemic agent may be required. ( 5.4 , 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no available data on the use of SOGROYA during pregnancy; however, published studies describing the use of short-acting recombinant growth hormone (rhGH) during pregnancy over several decades have not identified any drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal reproduction studies, subcutaneously administered somapacitan-beco was not teratogenic in rats or rabbits during organogenesis at doses approximately 12 times the clinical exposure at the maximum recommended human dose (MRHD) of 8 mg/week.
No adverse developmental outcomes were observed in a pre- and post-natal development study with administration of somapacitan-beco to pregnant rats from organogenesis through lactation at approximately 275 times the clinical exposure at the MRHD (see Data) . The background risk of birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data In an embryo-fetal development study in rats, somapacitan-beco was administered by subcutaneous injection at doses of 2, 6, and 18 mg/kg/day during the period of organogenesis from gestation day 6 to 17. Fetal viability and development were not affected at doses up to 6 mg/kg/day (31 times the MRHD, based on AUC). Transient, fetal skeletal variations (short/bent/thickened long bones) were observed at 18 mg/kg/day (261 times the MRHD, based on AUC).
In an embryo-fetal development study in rabbits, somapacitan-beco was administered by subcutaneous injection at doses of 1, 3, and 9 mg/kg every two days during the period of organogenesis from gestation day 6 to 18. Fetal viability and development were not adversely affected at somapacitan-beco dose of 1 mg/kg/every two days (12 times the MRHD, based on AUC). Reduced fetal growth was observed at doses ≥3 mg/kg/every two days (≥130 times the MRHD, based on C 12h ).
In a pre- and post-natal development study in pregnant rats, somapacitan-beco was administered by subcutaneous injection at doses of 4, 9, and 18 mg/kg twice a week from gestation day 6 through lactation day 18. No adverse developmental effects were observed in the offspring at doses up to 9 mg/kg (275 times the MRHD, based on AUC). Increased incidence of renal pelvic dilatation was observed on post-natal day 21 at 18 mg/kg (630 times the MRHD, based on AUC), but was not observed in the adult F1 generation.
8.2Lactation Risk Summary There is no information on the presence of somapacitan-beco in human milk, the effects on the breastfed infant, or the effects on milk production. Somapacitan-beco-related material was secreted into milk of lactating rats. When a substance is present in animal milk, it is likely that the substance will be present in human milk .
Available published data describing administration of short-acting recombinant growth hormone (rhGH) to lactating women for 7 days reported that short-acting rhGH did not increase the normal breastmilk concentration of growth hormone and no adverse effects were reported in breastfed infants. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for SOGROYA and any potential adverse effects on the breastfed infant from SOGROYA or from the underlying maternal condition.
8.4Pediatric Use The safety and effectiveness of SOGROYA have been established in pediatric patients 2.5 years of age and older for the treatment of: • Growth failure due to inadequate secretion of endogenous GH. The use of SOGROYA for this indication is supported by evidence from a 52-week randomized, multi-center, open-label, active-controlled, parallel-group phase 3 trial in 200 treatment-naïve, pediatric patients aged 2.5 to 11 years with GHD [see Clinical Studies (14.1)] . The safety…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no available data on the use of SOGROYA during pregnancy; however, published studies describing the use of short-acting recombinant growth hormone (rhGH) during pregnancy over several decades have not identified any drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal reproduction studies, subcutaneously administered somapacitan-beco was not teratogenic in rats or rabbits during organogenesis at doses approximately 12 times the clinical exposure at the maximum recommended human dose (MRHD) of 8 mg/week.
No adverse developmental outcomes were observed in a pre- and post-natal development study with administration of somapacitan-beco to pregnant rats from organogenesis through lactation at approximately 275 times the clinical exposure at the MRHD (see Data) . The background risk of birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data In an embryo-fetal development study in rats, somapacitan-beco was administered by subcutaneous injection at doses of 2, 6, and 18 mg/kg/day during the period of organogenesis from gestation day 6 to 17. Fetal viability and development were not affected at doses up to 6 mg/kg/day (31 times the MRHD, based on AUC). Transient, fetal skeletal variations (short/bent/thickened long bones) were observed at 18 mg/kg/day (261 times the MRHD, based on AUC).
In an embryo-fetal development study in rabbits, somapacitan-beco was administered by subcutaneous injection at doses of 1, 3, and 9 mg/kg every two days during the period of organogenesis from gestation day 6 to 18. Fetal viability and development were not adversely affected at somapacitan-beco dose of 1 mg/kg/every two days (12 times the MRHD, based on AUC). Reduced fetal growth was observed at doses ≥3 mg/kg/every two days (≥130 times the MRHD, based on C 12h ).
In a pre- and post-natal development study in pregnant rats, somapacitan-beco was administered by subcutaneous injection at doses of 4, 9, and 18 mg/kg twice a week from gestation day 6 through lactation day 18. No adverse developmental effects were observed in the offspring at doses up to 9 mg/kg (275 times the MRHD, based on AUC). Increased incidence of renal pelvic dilatation was observed on post-natal day 21 at 18 mg/kg (630 times the MRHD, based on AUC), but was not observed in the adult F1 generation.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of SOGROYA have been established in pediatric patients 2.5 years of age and older for the treatment of: • Growth failure due to inadequate secretion of endogenous GH. The use of SOGROYA for this indication is supported by evidence from a 52-week randomized, multi-center, open-label, active-controlled, parallel-group phase 3 trial in 200 treatment-naïve, pediatric patients aged 2.5 to 11 years with GHD [see Clinical Studies (14.1)] . The safety profile from the pediatric trial was similar to that reported in adults [see Adverse Reactions (6.1)] . • Short stature born SGA with no catch-up growth by 2 years of age.
The use of SOGROYA for this indication is supported by evidence from a multi-center, randomized open-label, active-comparator, phase 3 basket study in 142 pediatric patients aged 2.6 to 10.7 years with short stature born SGA with no catch-up growth by 2 years of age [see Clinical Studies (14.2)] . • Growth failure associated with NS. The use of SOGROYA for this indication is supported by evidence from a multi-center, randomized open-label, active-comparator, phase 3 basket study in 77 pediatric patients aged 2 to 11.1 years with growth failure associated with NS [see Clinical Studies (14.3)]. • ISS.
The use of SOGROYA for this indication is supported by evidence from a multi-center, randomized open-label, active-comparator, phase 3 basket study in 88 pediatric patients aged 2.8 to 10.8 years with ISS [see Clinical Studies (14.4)]. The safety and effectiveness of SOGROYA have not been established in pediatric patients less than 2.5 years of age for the treatment of growth failure due to inadequate secretion of endogenous GH, short stature born SGA with no catch-up growth, growth failure associated with NS, or with ISS.
Risks in pediatric patients associated with growth hormone use include: • Sudden death in pediatric patients with Prader-Willi Syndrome. SOGROYA is not indicated for the treatment of pediatric patients with growth failure secondary to genetically confirmed Prader-Willi syndrome. [see Warnings and Precautions (5.13)] • Increased risk of second neoplasm in pediatric cancer survivors treated with radiation to the brain and/or head [see Warnings and Precautions (5.3)] • Slipped capital femoral epiphysis in pediatric patients [see Warnings and Precautions (5.9)] • Progression of preexisting scoliosis in pediatric patients [see Warnings and Precautions (5.10)] • Pancreatitis [see Warnings and Precautions (5.11)]
🧓 Geriatric Use ▾
8.5Geriatric Use In clinical studies a total of 52 (15.6%) of the 333 SOGROYA-treated patients were 65 years or older and 3 (0.9%) were 75 years or older [see Clinical Studies ( 14 )] . Subjects older than 65 years appeared to have higher exposure than younger subjects at the same dose level. Elderly patients may be more sensitive to the action of somapacitan-beco and therefore may be at increased risk for adverse reactions.
Initiate SOGROYA with a dose of 1 mg once weekly and use smaller increments when increasing the dose [see Dosage and Administration ( 2.5 )].
🆘 Overdosage ▾
10 OVERDOSAGE Acute overdosage could lead initially to hypoglycemia and subsequently to hyperglycemia. Overdose with SOGROYA is likely to cause fluid retention. Long-term overdosage could result in signs and symptoms of gigantism and/or acromegaly consistent with the known effects of excess endogenous growth hormone.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Somapacitan-beco binds to a dimeric GH receptor in the cell membrane of target cells resulting in intracellular signal transduction and a host of pharmacodynamic effects. Some of these pharmacodynamic effects are primarily mediated by insulin-like growth factor-1 (IGF-1) produced in the liver, while others are primarily a consequence of the direct effects of somapacitan-beco.
12.2Pharmacodynamics IGF-1 was measured to assess the pharmacodynamic (PD) properties of somapacitan-beco. Somapacitan-beco normalizes the mean IGF-1 standard deviation score (SDS) level from a baseline value below -2 to a value within the reference range (-2 to +2) in treatment-naïve adult patients with GHD [see Clinical Studies ( 14 )] . In adult patients with GHD (n=26), somapacitan-beco induces a less than dose proportional IGF-1 response at steady state.
Maximum IGF-1 concentrations were observed within 2 to 4 days after dosing. Similar to the somapacitan-beco exposure time course, a steady state IGF-1 response was reached after 1 to 2 weekly doses with limited cumulative IGF-1 response. In pediatric patients with GHD aged 2.5 to 11 years, somapacitan-beco produces a dose linear IGF-1 response, with a change of 0.02 mg/kg on average resulting in a change in IGF-1 standard deviation score (SDS) of 0.32.
Approximately 97% of pediatric patients achieved an average IGF-1 SDS level within normal range after 52 weeks of treatment with once weekly SOGROYA in Study NCT03811535. IGF-1 SDS levels were -2.03 at baseline and the IGF-1 SDS level change from baseline was 2.36. In pediatric patients born SGA aged 2.6 to 10.1 years, somapacitan-beco produces a dose linear IGF-1 response, with a change of 0.02 mg/kg/week on average resulting in a change in IGF-1 SDS of 0.24 in the dosing range of 0.16 mg to 0.24 mg/kg/week.
IGF-1 SDS was normal at baseline and increased by 2.48 after 52 weeks of treatment with SOGROYA 0.24 mg/kg/week. In pediatric patients with NS aged 2.6 to 11.1 years, IGF-1 SDS was normal at baseline and increased by 2.35 after 52 weeks of treatment with SOGROYA 0.24 mg/kg/week. In pediatric patients with ISS aged 2.8 to 10.8 years, IGF-1 SDS was normal at baseline and increased by 2.44 after 52 weeks of treatment with SOGROYA 0.24 mg/kg/week.
12.3Pharmacokinetics Somapacitan-beco has pharmacokinetic properties compatible with once weekly administration. The reversible binding to endogenous albumin delays elimination of somapacitan and thereby prolongs the in vivo half-life and duration of action. The pharmacokinetics (PK) of somapacitan-beco following subcutaneous administration have been investigated at clinically relevant doses (e.g., 0.01 to 0.32 mg/kg in healthy adults, 0.02 to 0.12 mg/kg in adults with GHD, 0.02 to 0.16 mg/kg in pediatric patients with GHD, 0.16 to 0.24 mg/kg in pediatric patient born SGA, 0.24 mg/kg in pediatric patient with NS, and 0.24 mg/kg in pediatric patient with ISS).
Overall, somapacitan-beco displays non-linear pharmacokinetics, however in the clinically relevant dose range of somapacitan-beco in adults with GHD, somapacitan-beco pharmacokinetics are approximately linear. After subcutaneous administration of 0.02 – 0.16 mg/kg/week somapacitan-beco in pediatric patients with GHD, a non-linear dose-exposure relationship with a greater than dose proportional increase in exposure was observed. Absorption In adults and pediatric patients, steady state exposure is achieved following 1 to 2 weeks of once weekly administration of subcutaneous somapacitan-beco.
In adults with GHD, a maximum concentration of somapacitan-beco is reached 4 to 24 hours post dose. In pediatric patients with GHD, maximum somapacitan-beco concentrations occurred 8 to 25 hours after dosing at doses from 0.02 mg/kg/week to 0.16 mg/kg/week and increased with increasing dose level. In pediatric patients born SGA, a maximum concentration of somapacitan-beco is reached 22 hours post dose at doses from…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Somapacitan-beco binds to a dimeric GH receptor in the cell membrane of target cells resulting in intracellular signal transduction and a host of pharmacodynamic effects. Some of these pharmacodynamic effects are primarily mediated by insulin-like growth factor-1 (IGF-1) produced in the liver, while others are primarily a consequence of the direct effects of somapacitan-beco.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied SOGROYA (somapacitan-beco) injection is a clear to slightly opalescent and colorless to slightly yellow solution available as one 1.5 mL single-patient-use prefilled pen per carton: • SOGROYA 5 mg/1.5 mL (3.3 mg/mL) pen (teal) NDC 0169-2035-11 • SOGROYA 10 mg/1.5 mL (6.7 mg/mL) pen (yellow) NDC 0169-2030-11 • SOGROYA 15 mg/1.5 mL (10 mg/mL) pen (red) NDC 0169-2037-11 SOGROYA 5 mg/1.5 mL, 10 mg/1.5 mL, and 15 mg/1.5 mL pens are compatible with FlexPro ® PenMate ® . The FlexPro PenMate is an accessory device that is dispensed separately with its enclosed Instructions for Use.
Storage and Handling Before and during use: Store in a refrigerator at 2°C to 8°C (36°F to 46°F) with the cap on and in the original carton to protect from light. Do not freeze. Do not use SOGROYA if it has been frozen.
Discard prefilled pen if kept above 30°C (86°F). Avoid direct or excessive heat. Avoid sunlight.
Refer to storage conditions for SOGROYA ( Table 14 ). Write the date of first use in the space provided on the carton. Always remove and safely discard the needle after each injection and store the SOGROYA prefilled pen without an injection needle attached.
Always use a new needle for each injection to prevent contamination. Table 14. Storage Conditions for SOGROYA Before first use (unopened) After first use (opened) Refrigerated 2°C to 8°C (36°F to 46°F) Room Temperature up to 25°C (77°F) Refrigerated 2°C to 8°C (36°F to 46°F) Room Temperature up to 25°C (77°F) SOGROYA Until expiration date Maximum 72 hours (3 days)* up to 6 weeks Maximum 72 hours (3 days)* *The total time allowed at room temperature (up to 25°C [77°F]) is 72 hours (3 days) regardless of whether the product is in-use (opened) or before first use (unopened).
Must discard if kept above 30°C (86°F).
📋 Description ▾
11 DESCRIPTION Somapacitan-beco is a human growth hormone (hGH) analog with a single substitution in the amino acid backbone (L101C) to which an albumin-binding moiety has been attached. The albumin-binding moiety (side-chain) consists of an albumin binder and a hydrophilic spacer attached to position 101 of the protein. The protein part consists of 191 amino acids.
Somapacitan-beco is produced in Escherichia coli by recombinant DNA technology. The molecular formula (including the albumin-binding moiety) is C 1038 H 1609 N 273 O 319 S 9 and the molecular weight is 23305.10 g/mol, of which the albumin-binding moiety is 1191.39 g/mol. Structural Formula: SOGROYA (somapacitan-beco) injection is supplied as a sterile, clear to slightly opalescent and colorless to slightly yellow solution for subcutaneous use in a single-patient-use prefilled pen with a deliverable volume of 1.5 mL.
Each mL of SOGROYA 5 mg/1.5 mL prefilled pen contains 3.3 mg of somapacitan-beco, histidine (0.68 mg), mannitol (44 mg), phenol (4 mg), poloxamer 188 (1 mg), and Water for Injection, USP. The pH is approximately 6.8. Hydrochloric acid and sodium hydroxide may be added to adjust the pH.
Each mL of SOGROYA 10 mg/1.5 mL prefilled pen contains 6.7 mg of somapacitan-beco, histidine (0.68 mg), mannitol (44 mg), phenol (4 mg), poloxamer 188 (1 mg), and Water for Injection, USP. The pH is approximately 6.8. Hydrochloric acid and sodium hydroxide may be added to adjust the pH.
Each mL of SOGROYA 15 mg/1.5 mL prefilled pen contains 10 mg of somapacitan-beco, histidine (0.68 mg), mannitol (44 mg), phenol (4 mg), poloxamer 188 (1 mg), and Water for Injection, USP. The pH is approximately 6.8. Hydrochloric acid and sodium hydroxide may be added to adjust the pH. molecular-structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients and/or caregivers to read the FDA-approved patient labeling (Patient Information and Instructions for Use). • Advise patients and/or caregivers to administer SOGROYA once weekly. • Hypersensitivity - Advise patients and/or caregivers that severe and/or serious systemic hypersensitivity reactions (anaphylaxis and angioedema) have been reported, and to seek prompt medical attention should an allergic reaction occur [see Warnings and Precautions ( 5.2 )] . • Neoplasms – Advise patients to report marked changes in skin pigmentation or changes in the appearance of preexisting nevi. • Glucose Intolerance/ Diabetes Mellitus – Advise patients that new onset pre- /diabetes mellitus or exacerbation of preexisting diabetes mellitus can occur and monitoring of blood glucose during treatment with SOGROYA may be needed. • Intracranial Hypertension - Advise patients to report to their healthcare provider any visual changes, headache, and nausea and/or vomiting. • Fluid Retention - Advise patients that fluid retention during SOGROYA replacement therapy may frequently occur.
Inform patients of the clinical manifestations of fluid retention (e.g. edema, arthralgia, myalgia, nerve compression syndromes including carpal tunnel syndrome/paresthesia) and to report to their healthcare provider any of these signs or symptoms occur during treatment with SOGROYA. • Hypoadrenalism - Advise patients who have or who are at risk for corticotropin deficiency that hypoadrenalism may develop and to report to their healthcare provider if they experience hyperpigmentation, extreme fatigue, dizziness, weakness, or weight loss. • Hypothyroidism - Advise patients/caregivers that undiagnosed/untreated hypothyroidism may prevent an optimal response to SOGROYA.
Advise patients/caregivers they may require periodic thyroid function tests. • Pancreatitis - Advise patients that pancreatitis may develop and to report to their healthcare provider any new onset abdominal pain. • Lipohypertrophy/ Lipoatrophy – Advise patients that lipohypertrophy or lipoatrophy can occur if SOGROYA is administered subcutaneously at the same site over a long period of time. Advise patients to rotate injection sites when administering SOGROYA to reduce this risk. Novo Nordisk ® and PenMate ® are registered trademarks of Novo Nordisk A/S.
SOGROYA ® and FlexPro ® are registered trademarks of Novo Nordisk Health Care AG. © 2002-2026 Novo Nordisk Health Care AG Patent Information: http://novonordisk-us.com/products/product-patents.html For information about SOGROYA contact: Novo Nordisk Inc. 800 Scudders Mill Road Plainsboro, New Jersey 08536 1-888-668-6444 Manufactured by: Novo Nordisk Inc. 800 Scudders Mill Road Plainsboro, NJ 08536 U.S.
License No. 1261