
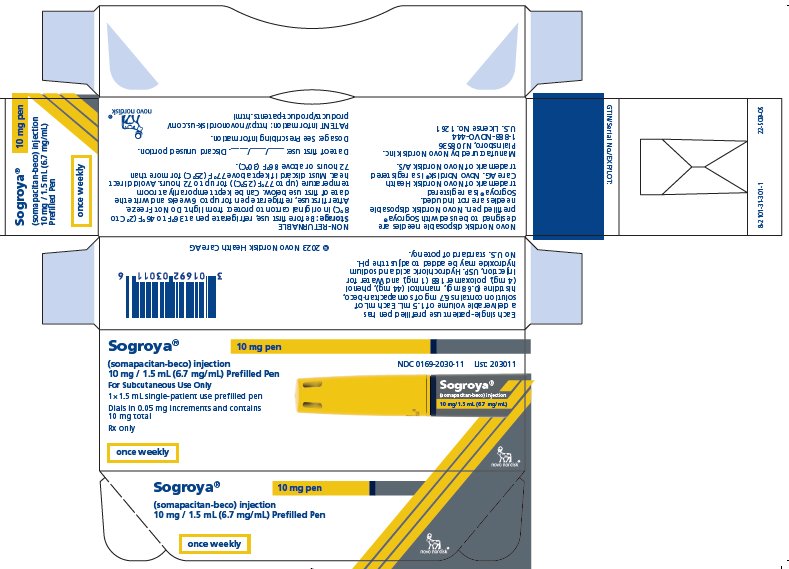
SOGROYA somapacitan-beco 6.7 mg/mL Injection, Solution, 1 syringe — NDC 0169-2030-90 (Billing 00169-2030-90)
This is a package of 1 syringe of SOGROYA somapacitan-beco 6.7 mg/mL Injection, Solution from Novo Nordisk, marketed since May 2023 and currently FDA-listed.
NDC database record
One package, one record: these facts belong to NDC 0169-2030-90 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0169 labeler · 2030 product · 90 package
- Package marketed since
- May 1, 2023
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 0169203090 1
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 081477
- GCN: 48603
- GPI-14 (Medi-Span): 3010000720D220
- HICL (First Databank): 046831
- AHFS class code: 68:28.00.00
- RxCUI (RxNorm): 2557398
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Somatropin and somatropin agonists class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It is a growth hormone given once a week. Children 2.5 and older use it for growth failure from low growth hormone, short stature after being born small for gestational age, Noonan...
- You inject it under the skin once a week using the prefilled pen, on any day and time. Rotate between the arms, thigh, abdomen and buttocks. If you miss a dose, take it within 3 da...
- How do I take it, and what if I miss a dose?
- Children often get colds, coughs, ear infections, fever or headaches. Adults may notice back or joint pain, indigestion or dizziness. Injection spots can bruise or be sore.
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $2,261.29 | $3,391.94 / 1.5 ml |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 8, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00169-2030-11 0169-2030-11 Main listing | 1 SYRINGE, PLASTIC in 1 CARTON / 1.5 mL in 1 SYRINGE, PLASTIC | 2023-05-01 | — | Active |
| 00169-2030-90 You're viewing this | 1 SYRINGE, PLASTIC in 1 CARTON / 1.5 mL in 1 SYRINGE, PLASTIC | 2023-05-01 | — | Active |
This pack shows little to no recent Medicaid volume — a different pack size carries most fills. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 00169-2030-11?
What NDC number is used to bill for this package of SOGROYA somapacitan-beco 6.7 mg/mL Injection, Solution?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Sogroya 6.7 mg/mLthis 00169-2030-90 | Novo | 1 syringe | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Purple Book · refreshed Oct 5, 2026
- CMS NADAC weekly file
Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Why the date isn’t exact: Biosimilar timing can change because patents may be challenged, settled, licensed, added or removed, and litigation can move the real date earlier or later.
🛈 What do these terms mean?
- Biologic patent
- A patent the reference product’s maker has publicly listed. A biosimilar generally can’t launch until these expire — unless they’re invalidated or resolved in a settlement.
- Reference-product exclusivity
- A flat 12 years of FDA market protection from the biologic’s first licensure (the BPCIA). No biosimilar can be licensed before it ends, regardless of patents.
- Interchangeable exclusivity
- The first interchangeable biosimilar can earn a period as the only interchangeable version (pharmacists can substitute it without the prescriber).
- Earliest biosimilar (LOE)
- The latest of all the dates above — the soonest a biosimilar can realistically reach the market. Litigation and settlements can move it earlier.
Biologics have no small-molecule “generics” — competition comes from FDA-licensed biosimilars, tracked in the FDA Purple Book.
| Code | What it grants | Expires |
|---|---|---|
| RefProduct | Reference-product exclusivity (12-year, BPCIA) — no biosimilar can be licensed before this date | Aug 28, 2032 |
Is there a biosimilar for SOGROYA 10 MG/1.5 ML PEN?
Why do different websites show different biosimilar dates?
Can a biosimilar launch before the last patent expires?
What does “current Purple Book estimate” mean?
What does “FDA listed” mean?
What does a patent or protection date mean here?
Where does this data come from?
- FDA Purple Book · refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Somapacitan-beco Injection inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
0.68 mg / 1 mL
UNII 4QD397987E
An amino acid used as a buffer and stabilizer in medications. It helps maintain the pH balance and protects the active drug from breaking down during storage and use.
-
44 mg / 1 mL
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
4 mg / 1 mL
UNII 339NCG44TV
Phenol is a chemical compound derived from coal tar or petroleum. It serves as a preservative and antimicrobial agent in medicines, helping prevent bacterial and fungal growth to keep the product stable and safe during storage.
-
1 mg / 1 mL
UNII LQA7B6G8JG
A synthetic polymer made by combining water-soluble compounds. It acts as a surfactant and solubilizer to help mix oil and water-based ingredients, improving the medicine's texture and how active ingredients dissolve.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Novo Nordisk labeler code 00169
- Novolin R Human Insulin 100 [iU]/mL Injection, Solution NDC 0169-1833-02
- Novolin N Human Insulin 100 [iU]/mL Injection, Suspension NDC 0169-1834-02
- Novolin 70/30 Human Insulin 100 [iU]/mL Injection, Suspension NDC 0169-1837-02
- Zegalogue dasiglucagon .6 mg/.6mL Injection, Solution NDC 0169-1912-01
- Zegalogue dasiglucagon .6 mg/.6mL Injection, Solution NDC 0169-1913-01
- Insulin Diluting Medium for NovoLog water injection 1 mL/mL Injection, Solution NDC 0169-2001-90
- SOGROYA somapacitan-beco 3.3 mg/mL Injection, Solution NDC 0169-2035-11
- SOGROYA somapacitan-beco 10 mg/mL Injection, Solution NDC 0169-2037-11
- Alhemo concizumab 100 mg/mL Injection, Solution NDC 0169-2080-15
- Alhemo concizumab 100 mg/mL Injection, Solution NDC 0169-2081-03
- Alhemo concizumab 40 mg/mL Injection, Solution NDC 0169-2084-15
- NOVOLOG insulin aspart 100 [iU]/mL Injection, Solution NDC 0169-2100-11
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE SOGROYA is indicated for the treatment of pediatric patients aged 2.5 years and older with: • Growth failure due to inadequate secretion of endogenous growth hormone (GH). • Short stature born small for gestational age (SGA) and with no catch-up growth by 2 years of age. • Growth failure associated with Noonan syndrome (NS). • Idiopathic Short Stature (ISS). SOGROYA is indicated for the replacement of endogenous GH in adults with growth hormone deficiency (GHD). SOGROYA is a human growth hormone analog indicated for: Pediatric Patients: Treatment of pediatric patients aged 2.5 years and older with: • Growth failure due to inadequate secretion of endogenous growth hormone (GH).
( 1 ) • Short stature born small for gestational age (SGA) and with no catch-up growth by 2 years of age. ( 1 ) • Growth failure associated with Noonan syndrome (NS). ( 1 ) • Idiopathic Short Stature (ISS).
( 1 ) Adults: Replacement of endogenous growth hormone in adults with growth hormone deficiency (GHD). ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • SOGROYA treatment should be supervised by a healthcare provider who is experienced in the diagnosis and management of patients with growth hormone deficiency, pediatric patients born SGA, pediatric patients with NS, and pediatric patients with ISS. ( 2.1 ) • SOGROYA should be administered by subcutaneous injection once weekly, any time of the day, in the upper arms, thigh, abdomen or buttocks with regular rotation of injection site to avoid lipohypertrophy/lipoatrophy. ( 2.1 ) • See Full Prescribing Information for complete dosage, titration, and monitoring recommendations for pediatric and adult patients, including those aged 65 years and older, patients with hepatic impairment, and women receiving oral estrogen.
( 2.1 , 2.2 , 2.3 , 2.4 , 2.5 ) For pediatric patients : • GH deficiency: Initiate SOGROYA with a dosage of 0.16 mg/kg body weight once weekly for treatment-naïve patients and patients switching from daily growth hormone (somatropin). ( 2.3 ) • SGA/NS/ISS: Initiate SOGROYA with a dosage of 0.24 mg/kg body weight once weekly for treatment-naïve patients and patients switching from daily growth hormone (somatropin). ( 2.3 ) • Individualize dosage for each patient based on the growth response.
( 2.3 ) • Patients switching from daily human growth hormone to once-weekly SOGROYA should choose the preferred day for the weekly dose and stop final dose of daily treatment the day before (or at least 8 hours before) taking the first dose of once-weekly somapacitan-beco. ( 2.3 ) For adult patients with GHD : • Initiate SOGROYA with a dosage of 1.5 mg once weekly for treatment naïve patients and patients switching from daily growth hormone. ( 2.4 ) • Increase the weekly dosage every 2 to 4 weeks by approximately 0.5 mg to 1.5 mg until the desired response has been achieved.
( 2.4 ) • Titrate the dosage based on clinical response and serum insulin-like growth factor-1 (IGF-1) concentrations. ( 2.4 ) • The maximum recommended dosage for adult GHD is 8 mg once weekly. ( 2.4 )
2.1Important Dosing and Administration Information • SOGROYA treatment should be supervised by a healthcare provider who is experienced in the diagnosis and management of pediatric patients with growth failure due to GHD, pediatric patients born SGA, pediatric patients with NS, pediatric patients with ISS and/or adults with GHD [see Indications and Usage ( 1 )]. • SOGROYA should be administered by subcutaneous injection, once weekly, any time of the day, in the upper arms, thigh, abdomen or buttocks with weekly rotation of injection site. • Inspect visually for particulate matter and discoloration.
SOGROYA should be a clear to slightly opalescent and colorless to slightly yellow solution. If the solution is cloudy or contains particulate matter do not use. • Advise patients to read the PATIENT INFORMATION and INSTRUCTIONS FOR USE leaflets enclosed with the SOGROYA prefilled pen. • SOGROYA is available in 3 single-patient-use prefilled pens with 3 different dosing ranges ( Table 1 ). Table 1.
Strength and Dosing Range of SOGROYA Prefilled Pens Strength Dose increments (mg) Dose Delivery Range (mg) 5 mg/1.5 mL (3.3 mg/mL) 0.025 0.025 to 2 10 mg/1.5 mL (6.7 mg/mL) 0.05 0.05 to 4 15 mg/1.5 mL (10 mg/mL) 0.1 0.1 to 8
2.2Perform Fundoscopic Examination Prior to Initiation of SOGROYA • Perform fundoscopic examination before initiating treatment with SOGROYA to exclude preexisting papilledema. If papilledema is identified, evaluate the etiology and treat the underlying cause before initiating treatment with SOGROYA [see Warnings and Precautions ( 5.5 )].
2.3Recommended Dosage and Monitoring for Pediatric Patients • GH Deficiency: Recommended dosage of SOGROYA is 0.16 mg/kg based on actual body weight once weekly for treatment-naïve patients and patients switching from daily growth hormone (somatropin). • Small for Gestational Age (SGA), Noonan Syndrome (NS), and Idiopathic Short Stature (ISS): Recommended dosage of SOGROYA is 0.24 mg/kg… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS SOGROYA is a clear to slightly opalescent and colorless to slightly yellow solution available as follows: • Injection: 5 mg/1.5 mL (3.3 mg/mL) in a single-patient-use prefilled pen (teal) • Injection: 10 mg/1.5 mL (6.7 mg/mL) in a single-patient-use prefilled pen (yellow) • Injection: 15 mg/1.5 mL (10 mg/mL) in a single-patient-use prefilled pen (red) SOGROYA is a liquid solution available in a ready-to-use prefilled pen. Injection: 5 mg/1.5 mL (3.3 mg/mL) or 10 mg/1.5 mL (6.7 mg/mL) or 15 mg/1.5 mL (10 mg/mL) in a single-patient-use prefilled pen.
( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS SOGROYA is contraindicated in patients with: • Acute critical illness after open-heart surgery, abdominal surgery or multiple accidental trauma, or those with acute respiratory failure because of the risk of increased mortality with use of pharmacologic doses of SOGROYA [see Warnings and Precautions ( 5.1 )] . • Hypersensitivity to SOGROYA or any of its excipients. Systemic hypersensitivity reactions have been reported postmarketing with somatropin [see Warnings and Precautions ( 5.2 )] . • Pediatric patients with closed epiphyses. • Active malignancy [see Warnings and Precautions ( 5.3 )]. • Active proliferative or severe non-proliferative diabetic retinopathy. • Pediatric patients with Prader-Willi syndrome who are severely obese, have a history of upper airway obstruction or sleep apnea or have severe respiratory impairment due to risk of sudden death [see Warnings and Precautions ( 5.13 )] . • Acute critical illness ( 4 ) • Active malignancy ( 4 ) • Hypersensitivity to somapacitan-beco or excipients ( 4 ) • Active proliferative or severe non-proliferative diabetic retinopathy ( 4 ) • Closed epiphyses in children used for longitudinal growth promotion ( 4 ) • Children with Prader-Willi syndrome who are severely obese or have severe respiratory impairment due to risk of sudden death ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Severe Hypersensitivity : Serious hypersensitivity reactions, including anaphylactic reactions and angioedema, may occur. In the event of an allergic reaction, seek prompt medical attention. ( 5.2 ) • Increased Risk of Neoplasm : Monitor patients with preexisting tumors for progression or recurrence.
Increased risk of a second neoplasm in childhood cancer survivors treated with somatropin – in particular meningiomas in patients treated with radiation to the head for their first neoplasm. ( 5.3 ) • Glucose Intolerance and Diabetes Mellitus : SOGROYA may decrease insulin sensitivity, particularly at higher doses. Monitor glucose levels periodically in all patients receiving SOGROYA, especially in patients with existing diabetes mellitus or at risk for its development.
( 5.4 ) • Intracranial Hypertension (IH) : Perform fundoscopic examinations prior to initiation and periodically thereafter. If papilledema is identified prior to initiation, evaluate the etiology and treat the underlying cause before initiating. If papilledema occurs with SOGROYA, stop treatment.
( 5.5 ) • Fluid Retention : Was observed and may be dose dependent. Reduce dose as necessary. ( 5.6 ) • Hypoadrenalism : Monitor patients for reduced serum cortisol levels and/or need for glucocorticoid dose increases in those with known hypoadrenalism.
( 5.7 ) • Hypothyroidism : Monitor thyroid function periodically as hypothyroidism may occur or worsen after initiation of SOGROYA. ( 5.8 ) • Slipped Capital Femoral Epiphysis in Pediatric Patients : May develop. Evaluate children with the onset of a limp or persistent hip/knee pain.
( 5.9 ) • Progression of Preexisting Scoliosis in Pediatric Patients : May develop. ( 5.10 ) • Pancreatitis : Consider pancreatitis in patients with persistent severe abdominal pain. ( 5.11 ) • Lipohypertrophy/lipoatrophy : May occur if SOGROYA is administered in the same location over a long period of time.
Rotate injection sites on a regular basis. ( 5.12 )
5.1Increased Mortality in Patients with Acute Critical Illness Increased mortality has been reported after treatment with somatropin in patients with acute critical illness due to complications following open-heart surgery, abdominal surgery and multiple accidental trauma, as well as patients with acute respiratory failure [see Contraindications ( 4 )] . The safety of continuing SOGROYA treatment in patients receiving replacement doses for approved indications who concurrently develop these illnesses has not been established.
SOGROYA is not indicated for the treatment of non-GH deficient adults.
5.2Severe Hypersensitivity Serious systemic hypersensitivity reactions including anaphylactic reactions and angioedema have been reported with postmarketing use of somatropin. Inform patients and/or caregivers that such reactions are possible, and that prompt medical attention should be sought if an allergic reaction occurs. SOGROYA is contraindicated in patients with known hypersensitivity to somatropin or any excipients in SOGROYA [see Contraindications ( 4 )].
5.3Increased Risk of Neoplasms Active Malignancy There is an increased risk of malignancy progression with somatropin treatment in patients with active malignancy [see Contraindications ( 4 )] . Any preexisting malignancy should be inactive, and its treatment complete prior to instituting therapy with SOGROYA. Discontinue SOGROYA if there is evidence of recurrent activity.
Risk of Second Neoplasm in Pediatric Patients In childhood cancer survivors who were treated with radiation to the brain/head for their first neoplasm and who developed subsequent growth hormone deficiency (GHD) and were treated with somatropin, an increased risk of second neoplasm has been reported. Intracranial tumors, in particular meningiomas, were the most common of these second neoplasms. Monitor all patients with a history of GHD secondary to an intracranial neoplasm while on somatropin therapy for progression or recurrence of the… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse drug reactions are described elsewhere in the labeling: • Increased mortality in patients with acute critical illness [see Warnings and Precautions ( 5.1 )] • Severe hypersensitivity [see Warnings and Precautions ( 5.2 )] • Increased risk of neoplasms [see Warnings and Precautions ( 5.3 )] • Glucose intolerance and diabetes mellitus [see Warnings and Precautions ( 5.4 )] • Intracranial hypertension [see Warnings and Precautions ( 5.5 )] • Fluid retention [see Warnings and Precautions ( 5.6 )] • Hypoadrenalism [see Warnings and Precautions ( 5.7 )] • Hypothyroidism [see Warnings and Precautions ( 5.8 )] • Slipped capital femoral epiphysis in pediatric patients [see Warnings and Precautions ( 5.9 )] • Progression of preexisting scoliosis in pediatric patients [see Warnings and Precautions ( 5.10 )] • Pancreatitis [see Warnings and Precautions ( 5.11 )] • Lipohypertrophy/Lipoatrophy [see Warnings and Precautions ( 5.12 )] • Sudden death in pediatric patients with Prader-Willi syndrome [see Warnings and Precautions ( 5.13 )] • Common adverse reactions reported in pediatric patients treated with SOGROYA include: cough, diarrhea, ear infection, headache, injection site reaction, nasopharyngitis, pain in extremity, pyrexia, respiratory tract infection, and vomiting.
( 6.1 ) • Adult patients with GHD: Adverse reactions reported in >2% of patients treated with SOGROYA are: back pain, arthralgia, dyspepsia, sleep disorder, dizziness, tonsillitis, peripheral edema, vomiting, adrenal insufficiency, hypertension, blood creatine phosphokinase increase, weight increase, anemia. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Novo Nordisk Inc. at 1-800-727-6500 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Pediatric Patients with GHD SOGROYA 0.16 mg/kg/week was studied in a 52-week randomized, open-label, active-controlled, parallel-group clinical study in 200 treatment-naïve, prepubertal pediatric patients with growth hormone deficiency [see Clinical Studies ( 14.1 )] .
Table 2 shows common adverse reactions that occurred in ≥ 5% of patients treated with either SOGROYA or somatropin in this trial. Table 2. Adverse Reactions Occurring ≥5% in SOGROYA or Somatropin-treated Pediatric Patients (52 Weeks of Treatment) Somatropin (N=68) SOGROYA (N=132) Adverse Reactions % % Nasopharyngitis a 16.2
16.7Headache 8.8
12.1Pyrexia b 11.8
9.1Pain in extremity c 2.9
9.8Injection site reaction d 5.9
6.1Diarrhea e 5.9
4.5Nausea/vomiting f 5.9
4.5Bronchitis 7.4 3 a Nasopharyngitis in the SOGROYA treatment group included nasopharyngitis (11.4%), rhinitis (3.8%), pharyngitis streptococcal (0.8%), acute sinusitis (0.8%), nasal congestion (0.8%), pharyngitis (0.8%), and sinusitis (0.8%). b Pyrexia in the SOGROYA treatment group included pyrexia (8.3%) and hyperthermia (0.8%). c Pain in extremity in the SOGROYA treatment group included pain in extremity (9.1%) and growing pains (0.8%). d Injection site reaction in the SOGROYA treatment group included injection site bruising (1.5%), injection site pain (1.5%), injection site hematoma (1.5%), injection site reaction (0.8%), and injection site swelling (0.8%) e Diarrhea in the SOGROYA treatment group included diarrhea (2.3%), gastroenteritis viral (1.5%), and gastrointestinal viral infection (0.8%) f Nausea/vomiting in the SOGROYA treatment group included vomiting (4.5%) and nausea (1.5%) Pediatric Patients Born Small for Gestational Age and with no Catch-up Growth by 2 Years of Age SOGROYA 0.24 mg/kg/week was studied in a 52-week randomized, open-label, active-comparator, basket clinical study in GH treatment-naïve, pre-pubertal patients with sh… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 7 includes a list of drugs with clinically important drug interactions when administered concomitantly with SOGROYA and instructions for preventing or managing them. Table 7. Clinically Important Drug Interactions with SOGROYA Replacement Glucocorticoid Treatment Clinical Impact: Microsomal enzyme 11β-hydroxysteroid dehydrogenase type 1 (11βHSD-1) is required for conversion of cortisone to its active metabolite, cortisol, in hepatic and adipose tissue.
GH inhibits 11βHSD-1. Consequently, individuals with untreated GH deficiency have relative increases in 11βHSD-1 and serum cortisol. Initiation of SOGROYA may result in inhibition of 11βHSD-1 and reduced serum cortisol concentrations.
Intervention: Patients treated with glucocorticoid replacement for hypoadrenalism may require an increase in their maintenance or stress doses following initiation of SOGROYA [see Warnings and Precautions ( 5.7 )]. Examples: Cortisone acetate and prednisone may be affected more than others because conversion of these drugs to their biologically active metabolites is dependent on the activity of 11βHSD-1. Cytochrome P450-Metabolized Drugs Clinical Impact: Limited published data indicate that GH treatment increases cytochrome P450 (CP450)-mediated antipyrine clearance.
SOGROYA may alter the clearance of compounds known to be metabolized by CP450 liver enzymes. Intervention: Careful monitoring is advisable when SOGROYA is administered in combination with drugs metabolized by CP450 liver enzymes. Oral Estrogen Clinical Impact: Oral estrogens may reduce the serum IGF-1 response to SOGROYA.
Intervention: Patients receiving oral estrogen replacement may require higher SOGROYA dosages [see Dosage and Administration (2.5 )] . Insulin and/or Other Hypoglycemic Agents Clinical Impact: Treatment with SOGROYA may decrease insulin sensitivity, particularly at higher doses. Intervention: Patients with diabetes mellitus may require adjustment of their doses of insulin and/or other hypoglycemic agents [see Warnings and Precautions ( 5.4 )]. • Replacement Glucocorticoid Treatment : Patients treated with glucocorticoid for hypoadrenalism may require an increase in their maintenance or stress doses following initiation of SOGROYA.
( 7 ) • Cytochrome P450-Metabolized Drugs : SOGROYA may alter the clearance. Monitor carefully if used with SOGROYA. ( 7 ) • Oral Estrogen : Larger doses of SOGROYA may be required.
( 7 ) • Insulin and/or Other Antihyperglycemic Agents : Dose adjustment of insulin or antihyperglycemic agent may be required. ( 5.4 , 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no available data on the use of SOGROYA during pregnancy; however, published studies describing the use of short-acting recombinant growth hormone (rhGH) during pregnancy over several decades have not identified any drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal reproduction studies, subcutaneously administered somapacitan-beco was not teratogenic in rats or rabbits during organogenesis at doses approximately 12 times the clinical exposure at the maximum recommended human dose (MRHD) of 8 mg/week.
No adverse developmental outcomes were observed in a pre- and post-natal development study with administration of somapacitan-beco to pregnant rats from organogenesis through lactation at approximately 275 times the clinical exposure at the MRHD (see Data) . The background risk of birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data In an embryo-fetal development study in rats, somapacitan-beco was administered by subcutaneous injection at doses of 2, 6, and 18 mg/kg/day during the period of organogenesis from gestation day 6 to 17. Fetal viability and development were not affected at doses up to 6 mg/kg/day (31 times the MRHD, based on AUC). Transient, fetal skeletal variations (short/bent/thickened long bones) were observed at 18 mg/kg/day (261 times the MRHD, based on AUC).
In an embryo-fetal development study in rabbits, somapacitan-beco was administered by subcutaneous injection at doses of 1, 3, and 9 mg/kg every two days during the period of organogenesis from gestation day 6 to 18. Fetal viability and development were not adversely affected at somapacitan-beco dose of 1 mg/kg/every two days (12 times the MRHD, based on AUC). Reduced fetal growth was observed at doses ≥3 mg/kg/every two days (≥130 times the MRHD, based on C 12h ).
In a pre- and post-natal development study in pregnant rats, somapacitan-beco was administered by subcutaneous injection at doses of 4, 9, and 18 mg/kg twice a week from gestation day 6 through lactation day 18. No adverse developmental effects were observed in the offspring at doses up to 9 mg/kg (275 times the MRHD, based on AUC). Increased incidence of renal pelvic dilatation was observed on post-natal day 21 at 18 mg/kg (630 times the MRHD, based on AUC), but was not observed in the adult F1 generation.
8.2Lactation Risk Summary There is no information on the presence of somapacitan-beco in human milk, the effects on the breastfed infant, or the effects on milk production. Somapacitan-beco-related material was secreted into milk of lactating rats. When a substance is present in animal milk, it is likely that the substance will be present in human milk .
Available published data describing administration of short-acting recombinant growth hormone (rhGH) to lactating women for 7 days reported that short-acting rhGH did not increase the normal breastmilk concentration of growth hormone and no adverse effects were reported in breastfed infants. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for SOGROYA and any potential adverse effects on the breastfed infant from SOGROYA or from the underlying maternal condition.
8.4Pediatric Use The safety and effectiveness of SOGROYA have been established in pediatric patients 2.5 years of age and older for the treatment of: • Growth failure due to inadequate secretion of endogenous GH. The use of SOGROYA for this indication is supported by evidence from a 52-week randomized, multi-center, open-label, active-controlled, parallel-group phase 3 trial in 200 treatment-naïve, pediatric patients aged 2.5 to 11 years with GHD [see Clinical Studies (14.1)] . The safety… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no available data on the use of SOGROYA during pregnancy; however, published studies describing the use of short-acting recombinant growth hormone (rhGH) during pregnancy over several decades have not identified any drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal reproduction studies, subcutaneously administered somapacitan-beco was not teratogenic in rats or rabbits during organogenesis at doses approximately 12 times the clinical exposure at the maximum recommended human dose (MRHD) of 8 mg/week.
No adverse developmental outcomes were observed in a pre- and post-natal development study with administration of somapacitan-beco to pregnant rats from organogenesis through lactation at approximately 275 times the clinical exposure at the MRHD (see Data) . The background risk of birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data In an embryo-fetal development study in rats, somapacitan-beco was administered by subcutaneous injection at doses of 2, 6, and 18 mg/kg/day during the period of organogenesis from gestation day 6 to 17. Fetal viability and development were not affected at doses up to 6 mg/kg/day (31 times the MRHD, based on AUC). Transient, fetal skeletal variations (short/bent/thickened long bones) were observed at 18 mg/kg/day (261 times the MRHD, based on AUC).
In an embryo-fetal development study in rabbits, somapacitan-beco was administered by subcutaneous injection at doses of 1, 3, and 9 mg/kg every two days during the period of organogenesis from gestation day 6 to 18. Fetal viability and development were not adversely affected at somapacitan-beco dose of 1 mg/kg/every two days (12 times the MRHD, based on AUC). Reduced fetal growth was observed at doses ≥3 mg/kg/every two days (≥130 times the MRHD, based on C 12h ).
In a pre- and post-natal development study in pregnant rats, somapacitan-beco was administered by subcutaneous injection at doses of 4, 9, and 18 mg/kg twice a week from gestation day 6 through lactation day 18. No adverse developmental effects were observed in the offspring at doses up to 9 mg/kg (275 times the MRHD, based on AUC). Increased incidence of renal pelvic dilatation was observed on post-natal day 21 at 18 mg/kg (630 times the MRHD, based on AUC), but was not observed in the adult F1 generation.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of SOGROYA have been established in pediatric patients 2.5 years of age and older for the treatment of: • Growth failure due to inadequate secretion of endogenous GH. The use of SOGROYA for this indication is supported by evidence from a 52-week randomized, multi-center, open-label, active-controlled, parallel-group phase 3 trial in 200 treatment-naïve, pediatric patients aged 2.5 to 11 years with GHD [see Clinical Studies (14.1)] . The safety profile from the pediatric trial was similar to that reported in adults [see Adverse Reactions (6.1)] . • Short stature born SGA with no catch-up growth by 2 years of age.
The use of SOGROYA for this indication is supported by evidence from a multi-center, randomized open-label, active-comparator, phase 3 basket study in 142 pediatric patients aged 2.6 to 10.7 years with short stature born SGA with no catch-up growth by 2 years of age [see Clinical Studies (14.2)] . • Growth failure associated with NS. The use of SOGROYA for this indication is supported by evidence from a multi-center, randomized open-label, active-comparator, phase 3 basket study in 77 pediatric patients aged 2 to 11.1 years with growth failure associated with NS [see Clinical Studies (14.3)]. • ISS.
The use of SOGROYA for this indication is supported by evidence from a multi-center, randomized open-label, active-comparator, phase 3 basket study in 88 pediatric patients aged 2.8 to 10.8 years with ISS [see Clinical Studies (14.4)]. The safety and effectiveness of SOGROYA have not been established in pediatric patients less than 2.5 years of age for the treatment of growth failure due to inadequate secretion of endogenous GH, short stature born SGA with no catch-up growth, growth failure associated with NS, or with ISS.
Risks in pediatric patients associated with growth hormone use include: • Sudden death in pediatric patients with Prader-Willi Syndrome. SOGROYA is not indicated for the treatment of pediatric patients with growth failure secondary to genetically confirmed Prader-Willi syndrome. [see Warnings and Precautions (5.13)] • Increased risk of second neoplasm in pediatric cancer survivors treated with radiation to the brain and/or head [see Warnings and Precautions (5.3)] • Slipped capital femoral epiphysis in pediatric patients [see Warnings and Precautions (5.9)] • Progression of preexisting scoliosis in pediatric patients [see Warnings and Precautions (5.10)] • Pancreatitis [see Warnings and Precautions (5.11)]
🧓 Geriatric Use ▾
8.5Geriatric Use In clinical studies a total of 52 (15.6%) of the 333 SOGROYA-treated patients were 65 years or older and 3 (0.9%) were 75 years or older [see Clinical Studies ( 14 )] . Subjects older than 65 years appeared to have higher exposure than younger subjects at the same dose level. Elderly patients may be more sensitive to the action of somapacitan-beco and therefore may be at increased risk for adverse reactions.
Initiate SOGROYA with a dose of 1 mg once weekly and use smaller increments when increasing the dose [see Dosage and Administration ( 2.5 )].
🆘 Overdosage ▾
10 OVERDOSAGE Acute overdosage could lead initially to hypoglycemia and subsequently to hyperglycemia. Overdose with SOGROYA is likely to cause fluid retention. Long-term overdosage could result in signs and symptoms of gigantism and/or acromegaly consistent with the known effects of excess endogenous growth hormone.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Somapacitan-beco binds to a dimeric GH receptor in the cell membrane of target cells resulting in intracellular signal transduction and a host of pharmacodynamic effects. Some of these pharmacodynamic effects are primarily mediated by insulin-like growth factor-1 (IGF-1) produced in the liver, while others are primarily a consequence of the direct effects of somapacitan-beco.
12.2Pharmacodynamics IGF-1 was measured to assess the pharmacodynamic (PD) properties of somapacitan-beco. Somapacitan-beco normalizes the mean IGF-1 standard deviation score (SDS) level from a baseline value below -2 to a value within the reference range (-2 to +2) in treatment-naïve adult patients with GHD [see Clinical Studies ( 14 )] . In adult patients with GHD (n=26), somapacitan-beco induces a less than dose proportional IGF-1 response at steady state.
Maximum IGF-1 concentrations were observed within 2 to 4 days after dosing. Similar to the somapacitan-beco exposure time course, a steady state IGF-1 response was reached after 1 to 2 weekly doses with limited cumulative IGF-1 response. In pediatric patients with GHD aged 2.5 to 11 years, somapacitan-beco produces a dose linear IGF-1 response, with a change of 0.02 mg/kg on average resulting in a change in IGF-1 standard deviation score (SDS) of 0.32.
Approximately 97% of pediatric patients achieved an average IGF-1 SDS level within normal range after 52 weeks of treatment with once weekly SOGROYA in Study NCT03811535. IGF-1 SDS levels were -2.03 at baseline and the IGF-1 SDS level change from baseline was 2.36. In pediatric patients born SGA aged 2.6 to 10.1 years, somapacitan-beco produces a dose linear IGF-1 response, with a change of 0.02 mg/kg/week on average resulting in a change in IGF-1 SDS of 0.24 in the dosing range of 0.16 mg to 0.24 mg/kg/week.
IGF-1 SDS was normal at baseline and increased by 2.48 after 52 weeks of treatment with SOGROYA 0.24 mg/kg/week. In pediatric patients with NS aged 2.6 to 11.1 years, IGF-1 SDS was normal at baseline and increased by 2.35 after 52 weeks of treatment with SOGROYA 0.24 mg/kg/week. In pediatric patients with ISS aged 2.8 to 10.8 years, IGF-1 SDS was normal at baseline and increased by 2.44 after 52 weeks of treatment with SOGROYA 0.24 mg/kg/week.
12.3Pharmacokinetics Somapacitan-beco has pharmacokinetic properties compatible with once weekly administration. The reversible binding to endogenous albumin delays elimination of somapacitan and thereby prolongs the in vivo half-life and duration of action. The pharmacokinetics (PK) of somapacitan-beco following subcutaneous administration have been investigated at clinically relevant doses (e.g., 0.01 to 0.32 mg/kg in healthy adults, 0.02 to 0.12 mg/kg in adults with GHD, 0.02 to 0.16 mg/kg in pediatric patients with GHD, 0.16 to 0.24 mg/kg in pediatric patient born SGA, 0.24 mg/kg in pediatric patient with NS, and 0.24 mg/kg in pediatric patient with ISS).
Overall, somapacitan-beco displays non-linear pharmacokinetics, however in the clinically relevant dose range of somapacitan-beco in adults with GHD, somapacitan-beco pharmacokinetics are approximately linear. After subcutaneous administration of 0.02 – 0.16 mg/kg/week somapacitan-beco in pediatric patients with GHD, a non-linear dose-exposure relationship with a greater than dose proportional increase in exposure was observed. Absorption In adults and pediatric patients, steady state exposure is achieved following 1 to 2 weeks of once weekly administration of subcutaneous somapacitan-beco.
In adults with GHD, a maximum concentration of somapacitan-beco is reached 4 to 24 hours post dose. In pediatric patients with GHD, maximum somapacitan-beco concentrations occurred 8 to 25 hours after dosing at doses from 0.02 mg/kg/week to 0.16 mg/kg/week and increased with increasing dose level. In pediatric patients born SGA, a maximum concentration of somapacitan-beco is reached 22 hours post dose at doses from… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Somapacitan-beco binds to a dimeric GH receptor in the cell membrane of target cells resulting in intracellular signal transduction and a host of pharmacodynamic effects. Some of these pharmacodynamic effects are primarily mediated by insulin-like growth factor-1 (IGF-1) produced in the liver, while others are primarily a consequence of the direct effects of somapacitan-beco.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied SOGROYA (somapacitan-beco) injection is a clear to slightly opalescent and colorless to slightly yellow solution available as one 1.5 mL single-patient-use prefilled pen per carton: • SOGROYA 5 mg/1.5 mL (3.3 mg/mL) pen (teal) NDC 0169-2035-11 • SOGROYA 10 mg/1.5 mL (6.7 mg/mL) pen (yellow) NDC 0169-2030-11 • SOGROYA 15 mg/1.5 mL (10 mg/mL) pen (red) NDC 0169-2037-11 SOGROYA 5 mg/1.5 mL, 10 mg/1.5 mL, and 15 mg/1.5 mL pens are compatible with FlexPro ® PenMate ® . The FlexPro PenMate is an accessory device that is dispensed separately with its enclosed Instructions for Use.
Storage and Handling Before and during use: Store in a refrigerator at 2°C to 8°C (36°F to 46°F) with the cap on and in the original carton to protect from light. Do not freeze. Do not use SOGROYA if it has been frozen.
Discard prefilled pen if kept above 30°C (86°F). Avoid direct or excessive heat. Avoid sunlight.
Refer to storage conditions for SOGROYA ( Table 14 ). Write the date of first use in the space provided on the carton. Always remove and safely discard the needle after each injection and store the SOGROYA prefilled pen without an injection needle attached.
Always use a new needle for each injection to prevent contamination. Table 14. Storage Conditions for SOGROYA Before first use (unopened) After first use (opened) Refrigerated 2°C to 8°C (36°F to 46°F) Room Temperature up to 25°C (77°F) Refrigerated 2°C to 8°C (36°F to 46°F) Room Temperature up to 25°C (77°F) SOGROYA Until expiration date Maximum 72 hours (3 days)* up to 6 weeks Maximum 72 hours (3 days)* *The total time allowed at room temperature (up to 25°C [77°F]) is 72 hours (3 days) regardless of whether the product is in-use (opened) or before first use (unopened).
Must discard if kept above 30°C (86°F).
📋 Description ▾
11 DESCRIPTION Somapacitan-beco is a human growth hormone (hGH) analog with a single substitution in the amino acid backbone (L101C) to which an albumin-binding moiety has been attached. The albumin-binding moiety (side-chain) consists of an albumin binder and a hydrophilic spacer attached to position 101 of the protein. The protein part consists of 191 amino acids.
Somapacitan-beco is produced in Escherichia coli by recombinant DNA technology. The molecular formula (including the albumin-binding moiety) is C 1038 H 1609 N 273 O 319 S 9 and the molecular weight is 23305.10 g/mol, of which the albumin-binding moiety is 1191.39 g/mol. Structural Formula: SOGROYA (somapacitan-beco) injection is supplied as a sterile, clear to slightly opalescent and colorless to slightly yellow solution for subcutaneous use in a single-patient-use prefilled pen with a deliverable volume of 1.5 mL.
Each mL of SOGROYA 5 mg/1.5 mL prefilled pen contains 3.3 mg of somapacitan-beco, histidine (0.68 mg), mannitol (44 mg), phenol (4 mg), poloxamer 188 (1 mg), and Water for Injection, USP. The pH is approximately 6.8. Hydrochloric acid and sodium hydroxide may be added to adjust the pH.
Each mL of SOGROYA 10 mg/1.5 mL prefilled pen contains 6.7 mg of somapacitan-beco, histidine (0.68 mg), mannitol (44 mg), phenol (4 mg), poloxamer 188 (1 mg), and Water for Injection, USP. The pH is approximately 6.8. Hydrochloric acid and sodium hydroxide may be added to adjust the pH.
Each mL of SOGROYA 15 mg/1.5 mL prefilled pen contains 10 mg of somapacitan-beco, histidine (0.68 mg), mannitol (44 mg), phenol (4 mg), poloxamer 188 (1 mg), and Water for Injection, USP. The pH is approximately 6.8. Hydrochloric acid and sodium hydroxide may be added to adjust the pH. molecular-structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients and/or caregivers to read the FDA-approved patient labeling (Patient Information and Instructions for Use). • Advise patients and/or caregivers to administer SOGROYA once weekly. • Hypersensitivity - Advise patients and/or caregivers that severe and/or serious systemic hypersensitivity reactions (anaphylaxis and angioedema) have been reported, and to seek prompt medical attention should an allergic reaction occur [see Warnings and Precautions ( 5.2 )] . • Neoplasms – Advise patients to report marked changes in skin pigmentation or changes in the appearance of preexisting nevi. • Glucose Intolerance/ Diabetes Mellitus – Advise patients that new onset pre- /diabetes mellitus or exacerbation of preexisting diabetes mellitus can occur and monitoring of blood glucose during treatment with SOGROYA may be needed. • Intracranial Hypertension - Advise patients to report to their healthcare provider any visual changes, headache, and nausea and/or vomiting. • Fluid Retention - Advise patients that fluid retention during SOGROYA replacement therapy may frequently occur.
Inform patients of the clinical manifestations of fluid retention (e.g. edema, arthralgia, myalgia, nerve compression syndromes including carpal tunnel syndrome/paresthesia) and to report to their healthcare provider any of these signs or symptoms occur during treatment with SOGROYA. • Hypoadrenalism - Advise patients who have or who are at risk for corticotropin deficiency that hypoadrenalism may develop and to report to their healthcare provider if they experience hyperpigmentation, extreme fatigue, dizziness, weakness, or weight loss. • Hypothyroidism - Advise patients/caregivers that undiagnosed/untreated hypothyroidism may prevent an optimal response to SOGROYA.
Advise patients/caregivers they may require periodic thyroid function tests. • Pancreatitis - Advise patients that pancreatitis may develop and to report to their healthcare provider any new onset abdominal pain. • Lipohypertrophy/ Lipoatrophy – Advise patients that lipohypertrophy or lipoatrophy can occur if SOGROYA is administered subcutaneously at the same site over a long period of time. Advise patients to rotate injection sites when administering SOGROYA to reduce this risk. Novo Nordisk ® and PenMate ® are registered trademarks of Novo Nordisk A/S.
SOGROYA ® and FlexPro ® are registered trademarks of Novo Nordisk Health Care AG. © 2002-2026 Novo Nordisk Health Care AG Patent Information: http://novonordisk-us.com/products/product-patents.html For information about SOGROYA contact: Novo Nordisk Inc. 800 Scudders Mill Road Plainsboro, New Jersey 08536 1-888-668-6444 Manufactured by: Novo Nordisk Inc. 800 Scudders Mill Road Plainsboro, NJ 08536 U.S.
License No. 1261
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Somapacitan-beco has pharmacokinetic properties compatible with once weekly administration. The reversible binding to endogenous albumin delays elimination of somapacitan and thereby prolongs the in vivo half-life and duration of action. The pharmacokinetics (PK) of somapacitan-beco following subcutaneous administration have been investigated at clinically relevant doses (e.g., 0.01 to 0.32 mg/kg in healthy adults, 0.02 to 0.12 mg/kg in adults with GHD, 0.02 to 0.16 mg/kg in pediatric patients with GHD, 0.16 to 0.24 mg/kg in pediatric patient born SGA, 0.24 mg/kg in pediatric patient with NS, and 0.24 mg/kg in pediatric patient with ISS).
Overall, somapacitan-beco displays non-linear pharmacokinetics, however in the clinically relevant dose range of somapacitan-beco in adults with GHD, somapacitan-beco pharmacokinetics are approximately linear. After subcutaneous administration of 0.02 – 0.16 mg/kg/week somapacitan-beco in pediatric patients with GHD, a non-linear dose-exposure relationship with a greater than dose proportional increase in exposure was observed. Absorption In adults and pediatric patients, steady state exposure is achieved following 1 to 2 weeks of once weekly administration of subcutaneous somapacitan-beco.
In adults with GHD, a maximum concentration of somapacitan-beco is reached 4 to 24 hours post dose. In pediatric patients with GHD, maximum somapacitan-beco concentrations occurred 8 to 25 hours after dosing at doses from 0.02 mg/kg/week to 0.16 mg/kg/week and increased with increasing dose level. In pediatric patients born SGA, a maximum concentration of somapacitan-beco is reached 22 hours post dose at doses from 0.16 mg/kg/week to 0.24 mg/kg/week and increased with increasing dose level.
In pediatric patients with NS, a maximum concentration of somapacitan-beco is reached 23 hours post dose at 0.24 mg/kg/week. In pediatric patients with ISS, a maximum concentration of somapacitan-beco is reached 23 hours post dose at 0.24 mg/kg/week. Distribution Somapacitan-beco is extensively bound (>99%) to plasma proteins.
Based on population PK analyses, the estimated volume of distribution (V/F) of somapacitan-beco in adult GHD patients is approximately
14.6 L,
1.7 L in pediatric patients with GHD,
2.97 L in pediatric patients born SGA,
3.23 L in pediatric patients with NS, and
2.99L in pediatric patients with ISS. Elimination The plasma elimination half-life of somapacitan-beco is approximately 2 to 3 days in adult patients with GHD. Following a dose of 0.16 mg/kg/week, the terminal half-life of somapacitan-beco was about 34 hours in pediatric patients with GHD.
Following a dose of 0.24 mg/kg/week, the mean terminal half-life of somapacitan-beco range from 36 to 37 hours in pediatric patients with SGA, NS, and ISS. Somapacitan-beco was cleared within one week after treatment discontinuation. Metabolism : Somapacitan-beco is metabolized via proteolytic cleavage of the linker sequence between the peptide backbone and albumin binder sidechain.
Excretion : The primary excretion routes of somapacitan-beco-related material are via the urine and feces. Approximately 81% of the dose is excreted in the urine and approximately 13% is excreted in the feces. No intact somapacitan-beco is excreted indicating full breakdown of somapacitan-beco prior to excretion.
Specific Populations Body weight : Adults with GHD – The exposure of somapacitan-beco decreases with increasing body weight. However, the somapacitan-beco dose range of 0.1 to 8 mg/week provides adequate systemic exposure to reach target IGF-1 levels over the weight range of 34.5-150.5 kg evaluated in the clinical trials. Pediatric patients with GHD : Based on pharmacokinetic analysis, gender and race do not have a clinically meaningful effect on the pharmacokinetics.
The exposure of somapacitan-beco decreases with increasing body weight. However, the somapacitan-beco dose of 0.16 mg/kg/week provides adequate systemic exposure for pediatrics to… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics IGF-1 was measured to assess the pharmacodynamic (PD) properties of somapacitan-beco. Somapacitan-beco normalizes the mean IGF-1 standard deviation score (SDS) level from a baseline value below -2 to a value within the reference range (-2 to +2) in treatment-naïve adult patients with GHD [see Clinical Studies ( 14 )] . In adult patients with GHD (n=26), somapacitan-beco induces a less than dose proportional IGF-1 response at steady state.
Maximum IGF-1 concentrations were observed within 2 to 4 days after dosing. Similar to the somapacitan-beco exposure time course, a steady state IGF-1 response was reached after 1 to 2 weekly doses with limited cumulative IGF-1 response. In pediatric patients with GHD aged 2.5 to 11 years, somapacitan-beco produces a dose linear IGF-1 response, with a change of 0.02 mg/kg on average resulting in a change in IGF-1 standard deviation score (SDS) of 0.32.
Approximately 97% of pediatric patients achieved an average IGF-1 SDS level within normal range after 52 weeks of treatment with once weekly SOGROYA in Study NCT03811535. IGF-1 SDS levels were -2.03 at baseline and the IGF-1 SDS level change from baseline was 2.36. In pediatric patients born SGA aged 2.6 to 10.1 years, somapacitan-beco produces a dose linear IGF-1 response, with a change of 0.02 mg/kg/week on average resulting in a change in IGF-1 SDS of 0.24 in the dosing range of 0.16 mg to 0.24 mg/kg/week.
IGF-1 SDS was normal at baseline and increased by 2.48 after 52 weeks of treatment with SOGROYA 0.24 mg/kg/week. In pediatric patients with NS aged 2.6 to 11.1 years, IGF-1 SDS was normal at baseline and increased by 2.35 after 52 weeks of treatment with SOGROYA 0.24 mg/kg/week. In pediatric patients with ISS aged 2.8 to 10.8 years, IGF-1 SDS was normal at baseline and increased by 2.44 after 52 weeks of treatment with SOGROYA 0.24 mg/kg/week.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Pediatric Patients with Growth Hormone Deficiency (GHD) A randomized, open-label, active-controlled, parallel-group phase 3 study was conducted in 200 treatment-naïve, pediatric patients with growth hormone deficiency (GHD) (NCT03811535). The primary efficacy endpoint was annualized height velocity at Week 52. One hundred thirty-two patients (132) received 0.16 mg/kg/week SOGROYA, and 68 received 0.034 mg/kg/day daily somatropin.
The patients ranged in age from 2.5 to 11 years with a mean of 6.4 years. Of these patients, 74.5% were male and 25.5% were female. Fifty-seven percent (57%) of patients were Caucasian, 37% of patients were Asian, 0.5% of patients were Black or African American, 5.0% were not reported, and 0.5% were categorized as “other.” The mean baseline height standard deviation score (SDS) of -2.99 (1.02) in SOGROYA group and -3.47 (1.52) in daily somatropin group.
Treatment with once-weekly SOGROYA for 52 weeks resulted in an annualized height velocity of 11.2 cm/year. Patients treated with daily somatropin achieved an annualized height velocity of 11.7 cm/year after 52 weeks of treatment. Refer to Table 8 .
Table 8. Annualized Height Velocity at Week 52 in Pediatric Patients with GHD Once-Weekly SOGROYA (N=132) Daily somatropin (N=68) Estimate of treatment difference (95% CI) (SOGROYA minus daily somatropin) Annualized Height Velocity (cm/year) 11.2 11.7 -0.5 [-1.1; 0.2] The mean increase in height SDS over the 52-week period was 1.25 and 1.30 in the once-weekly SOGROYA and daily somatropin groups, respectively.
14.2Pediatric Patients Born Small for Gestational Age (SGA) A multi-center, randomized, open-label, active-comparator, phase 3 basket study was conducted in GH treatment-naïve, pre-pubertal pediatric patients with short stature in small for gestational age (SGA), Noonan syndrome (NS) or idiopathic short stature (ISS) (NCT05330325). The primary efficacy endpoint was annualized height velocity at Week 52. One hundred forty-two pediatric patients with SGA were randomized to SOGROYA 0.24 mg/kg/week (n=70), daily somatropin 0.035 mg/kg/day (n=37), or daily somatropin 0.067 mg/kg/day (n=35).
Dose 0.035 mg/kg/day of daily somatropin is less than maximum dose (0.067 mg/kg/day) approved for use in pediatric patients with SGA in the United States. Patients ranged in age from 2.6 to 10.7 years with a mean of 5.5 years. Of these patients, 49% were male and 51% were female.
Fifty-nine percent of patients were Caucasian, 36% of patients were Asian, 1% of patients were Black or African American, and 4% were not reported. The mean baseline height SDS was -3, -3, and -3 in the SOGROYA, somatropin 0.035 mg/kg/day, and somatropin 0.067 mg/kg/day groups, respectively. The annualized height velocity at Week 52 for SOGROYA and somatropin are presented in Table 9 .
Table 9. Annualized Height Velocity at Week 52 in Pediatric Patients with SGA Once weekly SOGROYA 0.24 mg/kg/week (N=70) Daily somatropin 0.035 mg/kg/day (N=37) Daily somatropin 0.067 mg/kg/day (N=35) Estimated treatment difference (95% CI) * Annualized Height Velocity (cm/year) 11 9.4
11.1Once weekly SOGROYA 0.24 mg/kg/week vs. Daily somatropin 0.035 mg/kg/day: 1.6 # [0.91; 2.23] Once weekly SOGROYA 0.24 mg/kg/week vs. Daily somatropin 0.067 mg/kg/day: -0.1 # [-0.75; 0.60] *Estimated treatment difference (Height Velocity of SOGROYA - Daily Somatropin) # Height velocity at Week 52 is analyzed using an analysis of covariance model with treatment, gender, age group, region, baseline height SDS (<-3 or >=-3) and gender by age group by region interaction term as factors, and baseline height and baseline IGF-1 SDS as covariates.
There were no missing values at Week 52, so no multiple imputation was done. The mean increase in height SDS was 1.17, 0.85, and 1.21 following a 52-week treatment period with SOGROYA 0.24 mg/kg/week, daily somatropin 0.035 mg/kg/day, and daily somatropin 0.067 mg/kg/day, respectively.
14.3Pediatric Patients with Noon… [Excerpted — this section continues on DailyMed.]
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE
9.1Controlled Substance SOGROYA contains somapacitan-beco, which is not a controlled substance.
9.2Abuse Inappropriate use of SOGROYA may result in significant negative health consequences.
9.3Dependence SOGROYA is not associated with drug related withdrawal adverse reactions.
🔒 Controlled Substance ▾
9.1Controlled Substance SOGROYA contains somapacitan-beco, which is not a controlled substance.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Long term studies in animals with somapacitan-beco to evaluate carcinogenic potential have not been conducted. Somapacitan-beco was not mutagenic or clastogenic in a standard battery of genotoxicity tests (bacterial mutagenicity (Ames), human lymphocyte chromosome aberration, rat bone marrow micronucleus). In rat studies evaluating male and female fertility, somapacitan-beco was administered by subcutaneous injection at doses of 1, 2, and 4 mg/kg twice weekly.
Males were dosed from four weeks before pairing until termination and females were dosed beginning two weeks prior to mating through gestation day 7. No adverse effects were observed on male or female fertility in rats at doses up to 4 mg/kg (29 times the MRHD, based on AUC).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Long term studies in animals with somapacitan-beco to evaluate carcinogenic potential have not been conducted. Somapacitan-beco was not mutagenic or clastogenic in a standard battery of genotoxicity tests (bacterial mutagenicity (Ames), human lymphocyte chromosome aberration, rat bone marrow micronucleus). In rat studies evaluating male and female fertility, somapacitan-beco was administered by subcutaneous injection at doses of 1, 2, and 4 mg/kg twice weekly.
Males were dosed from four weeks before pairing until termination and females were dosed beginning two weeks prior to mating through gestation day 7. No adverse effects were observed on male or female fertility in rats at doses up to 4 mg/kg (29 times the MRHD, based on AUC).
📄 Patient Package Insert ▾
PATIENT INFORMATION PATIENT INFORMATION SOGROYA ® (suh-GROY-uh) (somapacitan-beco) injection, for subcutaneous use What is SOGROYA? • SOGROYA is a prescription medicine that contains human growth hormone, the same growth hormone made by the human body. SOGROYA is given by injection under the skin (subcutaneous). • SOGROYA is used to treat children 2.5 years of age and older who: o are not growing because of low or no growth hormone. o are short (in stature) and were born small (small for gestational age-SGA) and have not caught up in growth by age 2 years. o are not growing and have Noonan syndrome. o have Idiopathic Short Stature (ISS). • SOGROYA is used to treat adults who do not make enough growth hormone.
Do not use SOGROYA if: • you have a critical illness caused by certain types of heart or stomach surgery, trauma or breathing (respiratory) problems. • you have cancer or other tumors. • you are allergic to somapacitan-beco or any of the ingredients in SOGROYA. See the end of this Patient Information leaflet for a complete list of ingredients in SOGROYA. • your healthcare provider tells you that you have certain types of eye problems caused by diabetes (diabetic retinopathy). • you are a child with closed bone growth plates. • you are a child with Prader-Willi syndrome who is severely obese or has breathing problems including sleep apnea (briefly stop breathing during sleep).
Before taking SOGROYA, tell your healthcare provider about all of your medical conditions, including if you: • have had heart or stomach surgery, trauma or serious breathing (respiratory) problems. • have had cancer or any tumor. • have diabetes. • have adrenal gland problems. • are taking replacement therapy with glucocorticoids. • have thyroid gland problems. • have liver problems. • are a child with a history of worsening of curvature of the spine (scoliosis). • are pregnant or plan to become pregnant. It is not known if SOGROYA will harm your unborn baby.
Talk to your healthcare provider if you are pregnant or plan to become pregnant. • are breastfeeding or plan to breastfeed. It is not known if SOGROYA passes into your breast milk. You and your healthcare provider should decide if you will take SOGROYA while you breastfeed.
Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements. SOGROYA may affect how other medicines work, and other medicines may affect how SOGROYA works. How should I use SOGROYA? • Read the detailed Instructions for Use that come with SOGROYA. • SOGROYA comes in 3 strengths: 5 mg/1.5 mL (3.3 mg/mL) pen, 10 mg/1.5 mL (6.7 mg/mL) pen, and 15 mg/1.5 mL (10 mg/mL) pen.
Your healthcare provider will prescribe the dose that is right for you. • Your healthcare provider will show you how to inject SOGROYA. • Use SOGROYA exactly as your healthcare provider tells you to. • Use SOGROYA 1 time each week. • If you miss a dose of SOGROYA, the missed dose can be taken within 3 days (72 hours) after the scheduled dosing day. One-time weekly dosing for the next dose can be started again on the regularly scheduled dosing day. • If more than 3 days (72 hours) have passed, skip the missed dose and take your next dose on the regularly scheduled dosing day. • SOGROYA pens are for use by 1 person only. • Do not share your SOGROYA pens and needles with another person, even if the needle has been changed.
You may give another person an infection or get an infection from them. What are the possible side effects of SOGROYA? SOGROYA may cause serious side effects, including: • high risk of death in people who have critical illnesses because of heart or stomach surgery, trauma, or serious breathing (respiratory) problems. • increased risk of growth of cancer or a tumor that is already present and increased risk of the return of cancer or a tumor in people who were treated with radiation to the brain or head as children and who developed low growth hormone probl… [Excerpted — this section continues on DailyMed.]
📖 Instructions for Use ▾
Instructions for Use – 5 mg/1.5 mL (3.3 mg/mL) Instructions for Use SOGROYA ® 5 mg (suh-GROY-uh) (somapacitan-beco) injection 5 mg/1.5 mL (3.3 mg/mL) Supplies you will need: • SOGROYA prefilled Pen • new injection needle. SOGROYA prefilled Pen is designed to be used with all Novo Nordisk disposable needles up to a length of 8 mm. • sharps disposal container. See Step 5 for information on how to throw away (dispose of) used needles and Pens. • alcohol pad • gauze pad How to use your SOGROYA Pen 5 steps you should follow for a SOGROYA injection: Step 1 : Prepare your SOGROYA Pen Step 2 : Check the SOGROYA flow with each new Pen Step 3 : Select your dose Step 4 : Inject your dose Step 5 : After your injection For further information about your Pen see: Frequently Asked Questions and Important information Important information Pay special attention to these notes as they are important for safe use of the Pen.
Additional information SOGROYA is a prefilled growth hormone Pen. It contains 5 mg of somapacitan-beco and delivers doses from 0.025 mg to 2.0 mg, in increments of 0.025 mg. SOGROYA is for use under the skin only (subcutaneous) for injection 1 time each week.
Do not share your SOGROYA Pen and needles with another person. You may give another person an infection or get an infection from them. Do not use your Pen without proper training from your healthcare provider.
Make sure that you are confident in giving an injection with the Pen before you start your treatment. If you are blind or have poor eyesight and cannot read the dose counter on the Pen, do not use this Pen without help. Get help from a person with good eyesight who is trained to use the Pen.
Step 1. Prepare your SOGROYA Pen • Wash your hands with soap and water. • Check the name, strength, and colored label on your Pen to make sure that it contains SOGROYA in the right strength. • Pull off the Pen cap. • Turn the Pen upside down 1 or 2 times to check that the SOGROYA in your Pen is clear to almost clear and colorless to slightly yellow (See Figure A). If SOGROYA looks cloudy or you see particles, do not use the Pen. • When you are ready to give your injection, get a new disposable needle, and remove the paper tab. • Push the needle straight onto the Pen.
Turn the needle clockwise until it is on tight (See Figure B). Make sure the right pen is used. Especially if you use more than one type of injection medicine.
Using the wrong medicine could be harmful to your health. Always use a new needle for each injection. This reduces the risk of contamination, infection, leakage of SOGROYA, and blocked needles leading to incorrect dosing. • Pull off the outer needle cap and throw it away (dispose of) (See Figure C). • Pull off the inner needle cap and throw it away (dispose of) (See Figure D).
A drop of SOGROYA may appear at the needle tip. This is normal, but you must still check the SOGROYA flow with each new Pen (See Step 2). Never use a bent or damaged needle.
Step 2. Check the SOGROYA flow with each new Pen If your Pen is already in use , go to Step 3. • Before using a new Pen , check the SOGROYA flow to make sure the growth hormone can flow through the Pen and needle. • Turn the dose selector clockwise 1 marking on the dose counter to select 0.025 mg. You may hear a faint “click” when you turn the dose selector (See Figure E). • 1 marking on the dose counter equals 0.025 mg (See Figure F). • Hold the Pen with the needle pointing up.
Press and hold in the dose button until the dose counter returns to “0”. The “0” must line up with the dose pointer (See Figure G). • Check that a drop of SOGROYA appears at the needle tip (See Figure H). If no SOGROYA appears , repeat Step 2 up to 6 times.
If you still do not see a drop of SOGROYA, change the needle: • Carefully remove the needle from the Pen by turning the needle counterclockwise. Place the needle in a sharps disposal container immediately (See Step 5). • Repeat Step 2 again. Do not use the Pen if a drop of SOGROYA still… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Indication and Usage ( 1 )………………………………………….……2/2026 Dosage and Administration ( 2.1 , 2.3 )………………………………….2/2026 Warnings and Precautions ( 5.6 , 5.10 , 5.14 ) …………………….……..2/2026 Warnings and Precautions ( 5.9 )………………………………………..7/2025
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL – 5 mg Sogroya ® 5 mg pen NDC 0169-2035-11 (somapacitan-beco) injection List: 203511 5 mg / 1.5 mL (3.3 mg/mL) Prefilled Pen For subcutaneous Use Only 1x1.5 mL single-patient use prefilled pen Dials in 0.025 mg increments and contains 5 mg total Rx only once weekly 5mg-carton
PRINCIPAL DISPLAY PANEL – 10 mg Sogroya ® 10 mg pen NDC 0169-2030-11 (somapacitan-beco) injection List: 203011 10 mg / 1.5 mL (6.7 mg/mL) Prefilled Pen For subcutaneous Use Only 1x1.5 mL single-patient use prefilled pen Dials in 0.05 mg increments and contains 10 mg total Rx only once weekly 10mg-carton
PRINCIPAL DISPLAY PANEL – 15 mg Sogroya ® 15 mg pen NDC 0169-2037-11 (somapacitan-beco) injection List: 203711 15 mg / 1.5 mL (10 mg/mL) Prefilled Pen For subcutaneous Use Only 1x1.5 mL single-patient use prefilled pen Dials in 0.1 mg increments and contains 15 mg total Rx only once weekly 15mg-carton
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |