
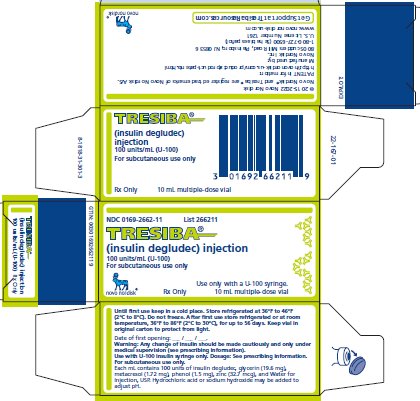
Tresiba insulin degludec 100 U/mL Injection, Solution — NDC 0169-2662-11 (Billing 00169-2662-11)
This is a package of Tresiba insulin degludec 100 U/mL Injection, Solution from Novo Nordisk, marketed since Nov 2018 and currently FDA-listed; retail pharmacies pay about $9.02 per mL (NADAC). It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 0169-2662-11 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0169 labeler · 2662 product · 11 package
- Package marketed since
- Feb 5, 2019
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 0169266211 9
- Medicaid fills, this package
- 2,903 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 079385
- GCN: 42785
- GPI-14 (Medi-Span): 27104007002020
- HICL (First Databank): 040844
- AHFS class code: 68:20.08.00
- RxCUI (RxNorm): 1670011
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Insulin Analog class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Insulin degludec is a long-acting insulin used to help control blood sugar in people with type 1 or type 2 diabetes — including children as young as 1 year old. It gives your body...
- What is insulin degludec (Tresiba) actually used for?
- If you're an adult, you have flexibility — you can take it at any time of day that works for you, as long as at least 8 hours pass between doses if you ever need to adjust the timi...
- When should I take it, and does it matter if I take it at different times each day?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Insulin Degludec — tap one for details:
Insulin Degludec may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $9.024 | $90.24 / 10 ml |
| Medicaid paysCMS SDUD · 12 mo | $32.63 | $326.33 / 10 ml |
| Medicare drug plans payPart D · Q2 2026 | $9.07 | $90.70 / 10 ml |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 00169-2662-11 You're viewing this Main listing | 1 VIAL, GLASS in 1 CARTON / 10 mL in 1 VIAL, GLASS | $9.02 / mL | $90.24 | 2019-02-05 | — | Active |
| 00169-2662-90 0169-2662-90 | 1 VIAL, GLASS in 1 CARTON / 10 mL in 1 VIAL, GLASS | — | — | 2019-02-05 | — | Active |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Tresiba insulin degludec 100 U/mL Injection, Solution?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Tresiba 100 U/mLthis 00169-2662-11 | Novo | 1 vial | $9.024 | — | Availability likely | — |
| Tresiba 100 U/mL 00169-2660-15 | Novo | 5 syringes | $9.036 | — | Availability likely | +0% |
| Insulin Degludec 100 U/mL 73070-0400-11 | Novo | 1 vial | $11.340 | — | Availability likely | +26% |
| Insulin Degludec 100 U/mL 73070-0403-15 | Novo | 5 syringes | $11.390 | — | Availability likely | +26% |
| Tresiba 100 U/mL 50090-7077-00 | A-S | 5 syringes | — | — | Discontinued | — |
| Insulin Degludec 100 U/mL 50090-7176-00 | A-S | 5 syringes | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Purple Book · refreshed Oct 5, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Why the date isn’t exact: Biosimilar timing can change because patents may be challenged, settled, licensed, added or removed, and litigation can move the real date earlier or later.
🛈 What do these terms mean?
- Biologic patent
- A patent the reference product’s maker has publicly listed. A biosimilar generally can’t launch until these expire — unless they’re invalidated or resolved in a settlement.
- Reference-product exclusivity
- A flat 12 years of FDA market protection from the biologic’s first licensure (the BPCIA). No biosimilar can be licensed before it ends, regardless of patents.
- Interchangeable exclusivity
- The first interchangeable biosimilar can earn a period as the only interchangeable version (pharmacists can substitute it without the prescriber).
- Earliest biosimilar (LOE)
- The latest of all the dates above — the soonest a biosimilar can realistically reach the market. Litigation and settlements can move it earlier.
Biologics have no small-molecule “generics” — competition comes from FDA-licensed biosimilars, tracked in the FDA Purple Book.
| Code | What it grants | Expires |
|---|---|---|
| RefProduct | Reference-product exclusivity (12-year, BPCIA) — no biosimilar can be licensed before this date | Sep 25, 2027 |
Is there a biosimilar for TRESIBA 100 UNIT/ML VIAL?
Why do different websites show different biosimilar dates?
Can a biosimilar launch before the last patent expires?
What does “current Purple Book estimate” mean?
What does “FDA listed” mean?
What does a patent or protection date mean here?
Where does this data come from?
- FDA Purple Book · refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Insulin Degludec (rDNA Origin) Injection inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
19.6 mg / 1 mL
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
1.72 mg / 1 mL
UNII GGO4Y809LO
Metacresol is a preservative derived from coal tar or petroleum. It prevents bacterial and fungal growth in liquid medicines, helping keep the product safe and stable during storage.
-
1.50 mg / 1 mL
UNII 339NCG44TV
Phenol is a chemical compound derived from coal tar or petroleum. It serves as a preservative and antimicrobial agent in medicines, helping prevent bacterial and fungal growth to keep the product stable and safe during storage.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
-
32.7 ug / 1 mL
UNII J41CSQ7QDS
A mineral element that strengthens tablet structure and acts as a processing aid. Zinc helps bind ingredients together and may improve the medicine's stability during manufacturing and storage.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Novo Nordisk labeler code 00169
- NOVOLOG insulin aspart 100 [iU]/mL Injection, Solution NDC 0169-2100-11
- NOVOLOG insulin aspart 100 [iU]/mL Injection, Solution NDC 0169-2101-25
- NovoLog Mix 70/30 insulin aspart 100 [iU]/mL Injection, Suspension NDC 0169-2200-11
- NovoLog Mix 70/30 insulin aspart 100 [iU]/mL Injection, Suspension NDC 0169-2201-25
- Tresiba insulin degludec 200 U/mL Injection, Solution NDC 0169-2550-13
- Tresiba insulin degludec 100 U/mL Injection, Solution NDC 0169-2660-15
- Saxenda liraglutide 6 mg/mL Injection, Solution NDC 0169-2800-15
- Xultophy 100/3.6 insulin degludec and liraglutide 100 [iU]/mL; 3.6 mg/mL Injection, Solution NDC 0169-2911-15
- Novolin R Human Insulin 100 [iU]/mL Injection, Solution NDC 0169-3003-15
- Novolin N Human Insulin 100 [iU]/mL Injection, Suspension NDC 0169-3004-15
- Novolin 70/30 Human Insulin 100 [iU]/mL Injection, Suspension NDC 0169-3007-15
- Awiqli Insulin icodec-abae 700 U/mL Injection, Solution NDC 0169-3105-11
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE TRESIBA is indicated to improve glycemic control in patients 1 year of age and older with diabetes mellitus. Limitations of Use • Not recommended for the treatment of diabetic ketoacidosis. TRESIBA is a long-acting human insulin analog indicated to improve glycemic control in patients 1 year of age and older with diabetes mellitus ( 1 ). Limitations of Use: • Not recommended for the treatment of diabetic ketoacidosis.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • See Full Prescribing Information for important administration instructions ( 2.1 ). • Inject TRESIBA subcutaneously into the thigh, upper arm, or abdomen ( 2.1 ). • Rotate injection sites to reduce risk of lipodystrophy and localized cutaneous amyloidosis ( 2.1 ). • For pediatric patients requiring less than 5 units of TRESIBA each day, use a TRESIBA U-100 vial ( 2.1 ). • In adults, inject subcutaneously once daily at any time of day ( 2.2 ). • In pediatric patients inject subcutaneously once daily at the same time every day ( 2.2 ). • Individualize dose based on type of diabetes, metabolic needs, blood glucose monitoring results and glycemic control goal ( 2.2 ). • The recommended days between dose increases are 3 to 4 days ( 2.2 ). • See Full Prescribing Information for recommended starting dose in insulin naïve patients and patients already on insulin therapy ( 2.3 , 2.4 ).
2.1Important Administration Instructions • Always check insulin labels before administration [see Warnings and Precautions ( 5.4 ) ] . • Inspect visually for particulate matter and discoloration. Only use TRESIBA if the solution appears clear and colorless. • Inject TRESIBA subcutaneously into the thigh, upper arm, or abdomen. • Rotate injection sites within the same region from one injection to the next to reduce the risk of lipodystrophy and localized cutaneous amyloidosis. Do not inject into areas of lipodystrophy or localized cutaneous amyloidosis [see Warnings and Precautions ( 5.2 ), Adverse Reactions ( 6.1 , 6.3 )]. • During changes to a patient’s insulin regimen, increase the frequency of blood glucose monitoring [see Warnings and Precautions ( 5.2 )]. • For pediatric patients requiring less than 5 units of TRESIBA each day, use the TRESIBA U-100 vial. • DO NOT administer TRESIBA intravenously or in an insulin infusion pump. • DO NOT dilute or mix TRESIBA with any other insulin or solution. • DO NOT transfer TRESIBA from the TRESIBA FlexTouch pen into a syringe for administration [see Warnings and Precautions ( 5.4 )]. • Use TRESIBA FlexTouch pens with caution in patients with visual impairment that may rely on audible clicks to dial their dose.
2.2General Dosing Instructions • TRESIBA is available in 2 concentrations (U-100 and U-200): o TRESIBA U-100 is available, as a single-patient use FlexTouch pen and multiple-dose vial. ▪ The FlexTouch pen delivers doses in 1 unit increments and can deliver up to 80 units in a single injection. o TRESIBA U-200 is available as a single-patient-use FlexTouch pen. ▪ The FlexTouch pen delivers doses in 2 unit increments and can deliver up to 160 units in a single injection. • DO NOT perform dose conversion when using the TRESIBA U-100 or U-200 FlexTouch pens.
The dose window shows the number of insulin units to be delivered and no conversion is needed. • In adults, inject TRESIBA subcutaneously once-daily at any time of day. • In pediatric patients inject TRESIBA subcutaneously once-daily at the same time every day. • Individualize and titrate the dose of TRESIBA based on the patient’s metabolic needs, blood glucose monitoring results, and glycemic control goal . • The recommended days between dose increases are 3 to 4 days. • Dose adjustments may be needed with changes in physical activity, changes in meal patterns (i.e., macronutrient content or timing of food intake), changes in renal or hepatic function or during acute illness to minimize the risk of hypoglycemia or hyperglycemia [see Warnings and Precautions ( 5.3 )] . • For adult patients, instruct patients who miss a dose of TRESIBA to inject their daily dose during waking hours upon discovering the missed dose.
Instruct patients to ensure that at least 8 hours have elapsed between consecutive TRESIBA injections. • For pediatric patients, instruct patients who miss a dose of TRESIBA to contact their healthcare provider for guidance and to monitor blood glucose levels more frequently until the next scheduled TRESIBA dose.… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: Available as a clear and colorless solution: • 100 units/mL (U-100): 3 mL single-patient-use FlexTouch prefilled pen • 100 units/mL (U-100): 10 mL multiple-dose vial • 200 units/mL (U-200): 3 mL single-patient-use FlexTouch prefilled pen Injection: Available as: • 100 units/mL (U-100): 3 mL single-patient-use FlexTouch ® prefilled pen ( 3 ). • 100 units/mL (U-100): 10 mL multiple-dose vial ( 3 ). • 200 units/mL (U-200): 3 mL single-patient-use FlexTouch ® prefilled pen ( 3 ).
⛔ Contraindications ▾
4 CONTRAINDICATIONS TRESIBA is contraindicated: • During episodes of hypoglycemia [see Warnings and Precautions ( 5.3 )] . • In patients with hypersensitivity to insulin degludec or any of the excipients in TRESIBA [see Warnings and Precautions ( 5.5 )] . • During episodes of hypoglycemia ( 4 ). • Hypersensitivity to insulin degludec or any of the excipients in TRESIBA ( 4 ).
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Never share a TRESIBA FlexTouch pen, insulin syringe, or needle between patients, even if the needle is changed ( 5.1 ). • Hyperglycemia or hypoglycemia with changes in insulin regimen: Make changes to a patient’s insulin regimen (e.g., insulin strength, manufacturer, type, injection site or method of administration) under close medical supervision with increased frequency of blood glucose monitoring ( 5.2 ). • Hypoglycemia : May be life-threatening. Increase monitoring with changes to: insulin dosage, concomitant drugs, meal pattern, physical activity; and in patients with renal impairment or hepatic impairment or hypoglycemia unawareness ( 5.3 , 5.4 , 6.1 ). • Hypoglycemia due to medication errors: Accidental mix-ups between insulin products can occur.
Instruct patients to check insulin labels before injection. DO NOT transfer TRESIBA from the TRESIBA pen into a syringe for administration as overdosage and severe hypoglycemia can result ( 5.4 ). • Hypersensitivity reactions : Severe, life-threatening, generalized allergy, including anaphylaxis, can occur. Discontinue TRESIBA, monitor and treat if indicated ( 5.5 ). • Hypokalemia: May be life-threatening.
Monitor potassium levels in patients at risk for hypokalemia and treat if indicated ( 5.6 ). • Fluid retention and heart failure with concomitant use of Thiazolidinediones (TZDs): Observe for signs and symptoms of heart failure; consider dosage reduction or discontinuation if heart failure occurs ( 5.7 ).
5.1Never Share a TRESIBA FlexTouch Pen, Needle, or Insulin Syringe Between Patients TRESIBA FlexTouch disposable prefilled pens should never be shared between patients, even if the needle is changed. Patients using TRESIBA vials should never share needles or syringes with another person. Sharing poses a risk for transmission of blood-borne pathogens.
5.2Hyperglycemia or Hypoglycemia with Changes in Insulin Regimen Changes in an insulin regimen (e.g., insulin strength, manufacturer, type, injection site or method of administration) may affect glycemic control and predispose to hypoglycemia [see Warnings and Precautions ( 5.3 )] or hyperglycemia. Repeated insulin injections into areas of lipodystrophy or localized cutaneous amyloidosis have been reported to result in hyperglycemia; and a sudden change in the injection site (to an unaffected area) has been reported to result in hypoglycemia [see Adverse Reactions ( 6.1 , 6.3 )].
Make any changes to a patient’s insulin regimen under close medical supervision with increased frequency of blood glucose monitoring. Advise patients who have repeatedly injected into areas of lipodystrophy or localized cutaneous amyloidosis to change the injection site to unaffected areas and closely monitor for hypoglycemia. For patients with type 2 diabetes, adjustments in concomitant anti-diabetic treatment may be needed [see Dosage and Administration ( 2.4 )].
5.3Hypoglycemia Hypoglycemia is the most common adverse reaction of insulin, including TRESIBA [see Adverse Reactions ( 6.1 )]. Severe hypoglycemia can cause seizures, may be life-threatening or cause death. Hypoglycemia can impair concentration ability and reaction time; this may place the patient and others at risk in situations where these abilities are important (e.g., driving or operating other machinery).
TRESIBA, or any insulin, should not be used during episodes of hypoglycemia [see Contraindications ( 4 )]. Hypoglycemia can happen suddenly and symptoms may differ in each patient and change over time in the same patient. Symptomatic awareness of hypoglycemia may be less pronounced in patients with longstanding diabetes, in patients with diabetic neuropathy, using drugs that block the sympathetic nervous system (e.g., beta-blockers) [see Drug Interactions ( 7 )], or who experience recurrent hypoglycemia.
The long-acting effect of TRESIBA may delay recovery from hypoglycemia compared to shorter-acting insulins. Risk Factors for Hypoglycemia The risk of h… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are also discussed elsewhere: • Hypoglycemia [see Warnings and Precautions ( 5.3 )] • Hypoglycemia due to Medication errors [see Warnings and Precautions ( 5.4 )] • Hypersensitivity reactions [see Warnings and Precautions ( 5.5 )] • Hypokalemia [see Warnings and Precautions ( 5.6 )] Adverse reactions commonly associated with TRESIBA are: • hypoglycemia, allergic reactions, injection site reactions, lipodystrophy, pruritus, rash, edema and weight gain ( 6.1 ). To report SUSPECTED ADVERSE REACTIONS, contact Novo Nordisk at 1-800-727-6500 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The safety of TRESIBA in subjects with type 1 diabetes or type 2 diabetes was evaluated in nine trials of 6-12 month duration in adults and in one trial of 12-month duration in pediatric patients 1 year of age and older with type 1 diabetes.
The cardiovascular safety of TRESIBA was evaluated in one double-blinded, event-driven trial of 2-year median duration in patients with type 2 diabetes at high risk of cardiovascular events [see Clinical Studies ( 14 )]. The data in Table 1 reflect the exposure of 1102 adults with type 1 diabetes to TRESIBA with a mean exposure duration to TRESIBA of 34 weeks in three open-label trials; Study A, B and C [see Clinical Studies (14.1)] . The mean age was 43 years and 1% were older than 75 years.
Fifty-seven percent were male, 81% were White, 2% were Black or African American and 4% were Hispanic. The mean body mass index (BMI) was 26 kg/m 2 . The mean duration of diabetes was 18 years and the mean HbA 1c at baseline was 7.8%.
A history of neuropathy, ophthalmopathy, nephropathy and cardiovascular disease at baseline was reported in 11%, 16%, 7% and 0.5% respectively. The mean eGFR at baseline was 87 mL/min/1.73 m 2 and 7% of the patients had an eGFR less than 60 mL/min/1.73 m 2 . The data in Table 2 reflect the exposure of 2713 adults with type 2 diabetes to TRESIBA with a mean exposure duration to TRESIBA of 36 weeks in six open-label trials; Study D, E, F, G, H and I [see Clinical Studies (14.3)] .
The mean age was 58 years and 3% were older than 75 years. Fifty-eight percent were male, 71% were White, 7% were Black or African American and 13% were Hispanic. The mean BMI was 30 kg/m 2 .
The mean duration of diabetes was 11 years and the mean HbA 1c at baseline was 8.3%. A history of neuropathy, ophthalmopathy, nephropathy and cardiovascular disease at baseline was reported for 14%, 10%, 6% and 0.6% of participants respectively. At baseline, the mean eGFR was 83 mL/min/1.73 m 2 and 9% had an eGFR less than 60 mL/min/1.73 m 2 .
Common adverse reactions (excluding hypoglycemia) occurring in TRESIBA treated subjects during clinical trials in adult patients with type 1 diabetes mellitus and adults with type 2 diabetes mellitus are listed in Table 1 and Table 2, respectively. Common adverse reactions were defined as reactions occurring in ≥5% of the population studied. Hypoglycemia is not shown in these tables but discussed in a dedicated subsection below.
174 pediatric patients 1 year of age and older with type 1 diabetes were exposed to TRESIBA with a mean exposure to TRESIBA of 48 weeks. The mean age was 10 years: 25% were ages 1-5 years, 40% were ages 6-11 years, and 35% were ages 12-17 years. 55% were male, 78% were White, 3% were Black or African American and 4% were Hispanic.
The mean body mass index (BMI) was 18.7 kg/m 2 . The mean duration of diabetes was 3.9 years and the mean HbA 1c at baseline was 8.2%. Common adverse reactions in TRESIBA treated pediatric patients with type 1 diabetes mellitus were similar to the adverse reactions listed in Table 1.
Table 1: Adver… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 5 includes clinically significant drug interactions with TRESIBA. Table 5: Clinically Significant Drug Interactions with TRESIBA Drugs That May Increase the Risk of Hypoglycemia Drugs: Antidiabetic agents, ACE inhibitors, angiotensin II receptor blocking agents, disopyramide, fibrates, fluoxetine, monoamine oxidase inhibitors, pentoxifylline, pramlintide, salicylates, somatostatin analogs (e.g., octreotide), and sulfonamide antibiotics, GLP-1 receptor agonists, DPP-4 inhibitors, SGLT-2 inhibitors.
Intervention: Dosage reductions and increased frequency of glucose monitoring may be required when TRESIBA is co-administered with these drugs. Drugs That May Decrease the Blood Glucose Lowering Effect of TRESIBA Drugs: Atypical antipsychotics (e.g., olanzapine and clozapine), corticosteroids, danazol, diuretics, estrogens, glucagon, isoniazid, niacin, oral contraceptives, phenothiazines, progestogens (e.g., in oral contraceptives), protease inhibitors, somatropin, sympathomimetic agents (e.g., albuterol, epinephrine, terbutaline), and thyroid hormones.
Intervention: Dosage increases and increased frequency of glucose monitoring may be required when TRESIBA is co-administered with these drugs. Drugs That May Increase or Decrease the Blood Glucose Lowering Effect of TRESIBA Drugs: Alcohol, beta-blockers, clonidine, and lithium salts. Pentamidine may cause hypoglycemia, which may sometimes be followed by hyperglycemia.
Intervention: Dosage adjustment and increased frequency of glucose monitoring may be required when TRESIBA is co-administered with these drugs. Drugs That May Blunt Signs and Symptoms of Hypoglycemia Drugs: Beta-blockers, clonidine, guanethidine, and reserpine Intervention: Increased frequency of glucose monitoring may be required when TRESIBA is co-administered with these drugs. • Drugs that Affect Glucose Metabolism: Adjustment of insulin dosage mey be needed. ( 7 ) • Antiandrenergic Drugs (e.g., beta-blockers, clonidine, guanethidine, and reserpine): Signs and symptoms of hypoglycemia may be reduced or absent.
( 5.3 , 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Available data from one unpublished trial and the published literature with TRESIBA use during pregnancy have not identified a drug-associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes. In a randomized, parallel-group, open-label actively controlled clinical trial that included 91 pregnant women with type 1 diabetes who were administered TRESIBA once daily and insulin aspart, beginning in gestational weeks 8 to 13 or prior to conception, no clear evidence of maternal or fetal risk associated with TRESIBA use was observed ( see Data ).
There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy ( see Clinical Considerations ). Rats and rabbits were exposed to insulin degludec in animal reproduction studies during organogenesis. Pre-and post-implantation losses and visceral/skeletal abnormalities were observed in rats at doses 5 times (rat) and at 10 times (rabbit) the human exposure at a dose of
0.75U/kg/day. These effects were similar to those observed in rats administered human insulin (NPH) (see Data) . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
The estimated background risk of major birth defects is 6 to 10% in women with pre-gestational diabetes with a peri-conceptional HbA 1c >7 and has been reported to be as high as 20 to 25% in women with a peri-conceptional HbA 1c >10. The estimated background risk of miscarriage for the indicated population is unknown. Clinical Considerations Disease-Associated Maternal and/or Embryo/fetal Risk Hypoglycemia and hyperglycemia occur more frequently during pregnancy in patients with pre-gestational diabetes.
Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, pre-eclampsia, spontaneous abortions, preterm delivery, and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, still birth, and macrosomia related morbidity. Data Human Data In an open-label clinical trial, 185 pregnant females with type 1 diabetes were treated with either TRESIBA (once daily) or insulin detemir (once or twice daily); both groups received insulin aspart 2 to 4 times daily with meals.
There were no significant drug-associated differences in pregnancy outcomes or the health of the fetus and newborn between the two groups. In this study, the proportion of subjects with severe hypoglycemia and hypoglycemia was similar between the two treatment arms; for the definitions of severe hypoglycemia and hypoglycemia [see Adverse Reactions (6.1)]. Poor glucose control during pregnancy in both groups and small sample size were limitations of the study.
In about two thirds of infants, insulin degludec was detected in the infant cord blood at levels above the lower level of quantification of the assay. Animal Data Insulin degludec was investigated in studies covering fertility, embryo-fetal development and pre- and post-natal development in rats and during the period of embryo-fetal development in rabbits. Human insulin (NPH insulin) was included as comparator.
In these studies, insulin degludec caused pre- and post-implantation losses and visceral/skeletal abnormalities when given subcutaneously at up to 21 U/kg/day in rats and
3.3U/kg/day in rabbits, resulting in 5 times (rat) and 10 times (rabbit) the human exposure (AUC) at a human subcutaneous dose of
0.75U/kg/day. Overall, the effects of insulin degludec were similar to those observed with human insulin, which were probably secondary to maternal hypoglycemia.
8.2Lactation Risk Summary There are no data on the presence of insulin degludec in human milk, the effects on the breastfed infant, or the effects on milk production. Insulin degludec is present in rat milk ( see Data) . The developmental and health benefits… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from one unpublished trial and the published literature with TRESIBA use during pregnancy have not identified a drug-associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes. In a randomized, parallel-group, open-label actively controlled clinical trial that included 91 pregnant women with type 1 diabetes who were administered TRESIBA once daily and insulin aspart, beginning in gestational weeks 8 to 13 or prior to conception, no clear evidence of maternal or fetal risk associated with TRESIBA use was observed ( see Data ).
There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy ( see Clinical Considerations ). Rats and rabbits were exposed to insulin degludec in animal reproduction studies during organogenesis. Pre-and post-implantation losses and visceral/skeletal abnormalities were observed in rats at doses 5 times (rat) and at 10 times (rabbit) the human exposure at a dose of
0.75U/kg/day. These effects were similar to those observed in rats administered human insulin (NPH) (see Data) . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
The estimated background risk of major birth defects is 6 to 10% in women with pre-gestational diabetes with a peri-conceptional HbA 1c >7 and has been reported to be as high as 20 to 25% in women with a peri-conceptional HbA 1c >10. The estimated background risk of miscarriage for the indicated population is unknown. Clinical Considerations Disease-Associated Maternal and/or Embryo/fetal Risk Hypoglycemia and hyperglycemia occur more frequently during pregnancy in patients with pre-gestational diabetes.
Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, pre-eclampsia, spontaneous abortions, preterm delivery, and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, still birth, and macrosomia related morbidity. Data Human Data In an open-label clinical trial, 185 pregnant females with type 1 diabetes were treated with either TRESIBA (once daily) or insulin detemir (once or twice daily); both groups received insulin aspart 2 to 4 times daily with meals.
There were no significant drug-associated differences in pregnancy outcomes or the health of the fetus and newborn between the two groups. In this study, the proportion of subjects with severe hypoglycemia and hypoglycemia was similar between the two treatment arms; for the definitions of severe hypoglycemia and hypoglycemia [see Adverse Reactions (6.1)]. Poor glucose control during pregnancy in both groups and small sample size were limitations of the study.
In about two thirds of infants, insulin degludec was detected in the infant cord blood at levels above the lower level of quantification of the assay. Animal Data Insulin degludec was investigated in studies covering fertility, embryo-fetal development and pre- and post-natal development in rats and during the period of embryo-fetal development in rabbits. Human insulin (NPH insulin) was included as comparator.
In these studies, insulin degludec caused pre- and post-implantation losses and visceral/skeletal abnormalities when given subcutaneously at up to 21 U/kg/day in rats and
3.3U/kg/day in rabbits, resulting in 5 times (rat) and 10 times (rabbit) the human exposure (AUC) at a human subcutaneous dose of
0.75U/kg/day. Overall, the effects of insulin degludec were similar to those observed with human insulin, which were probably secondary to maternal hypoglycemia.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of TRESIBA to improve glycemic control in pediatric patients 1 year of age and older with diabetes mellitus have been established. The use of TRESIBA for this indication is supported by evidence from an adequate and well-controlled trial and a pharmacokinetic study (trials included pediatric patients 1 year of age and older with type 1 diabetes mellitus) [ see Clinical Pharmacology ( 12.3 ) and Clinical Studies ( 14.2 )]. The use of TRESIBA in pediatric patients 1 year of age and older with type 2 diabetes mellitus is also supported by evidence from adequate and well-controlled trials in adults with type 2 diabetes mellitus [see Clinical Studies ( 14.3 )] .
In pediatric patients 1 year of age and older already on insulin therapy, start TRESIBA at a reduced dose to minimize the risk of hypoglycemia [see Dosage and Administration ( 2.4 )]. The safety and effectiveness of TRESIBA have not been established in pediatric patients less than 1-year-old.
🧓 Geriatric Use ▾
8.5Geriatric Use In controlled clinical trials [see Clinical Studies ( 14 )] a total of 77 (7%) of the 1102 TRESIBA-treated patients with type 1 diabetes were 65 years or older and 9 (1%) were 75 years or older. A total of 670 (25%) of the 2713 TRESIBA-treated patients with type 2 diabetes were 65 years or older and 80 (3%) were 75 years or older. Differences in safety or effectiveness were not suggested in subgroup analyses comparing subjects older than 65 years to younger subjects.
In the safety outcomes trial (DEVOTE), a total of 1983 (52%) of the 3818 TRESIBA-treated patients with type 2 diabetes were 65 years or older and 381 (10%) were 75 years or older. Differences in safety or effectiveness were not observed in these subgroup analyses. Nevertheless, greater caution should be exercised when TRESIBA is administered to geriatric patients since greater sensitivity of some older individuals to the effects of TRESIBA cannot be ruled out.
The initial dosing, dose increments, and maintenance dosage should be conservative to avoid hypoglycemia. Hypoglycemia may be more difficult to recognize in the geriatric patients.
🆘 Overdosage ▾
10 OVERDOSAGE An excess of insulin relative to food intake, energy expenditure, or both may lead to severe and sometimes prolonged and life-threatening hypoglycemia and hypokalemia [see Warnings and Precautions ( 5.3 , 5.6 )] . Mild episodes of hypoglycemia usually can be treated with oral glucose. Lowering the insulin dosage, and adjustment in meal patterns or exercise may be needed.
More severe episodes of hypoglycemia with coma, seizure, or neurologic impairment may be treated with a glucagon for emergency use or concentrated intravenous glucose. After apparent clinical recovery from hypoglycemia, continued observation and additional carbohydrate intake may be necessary to avoid reoccurrence of hypoglycemia. Hypokalemia must be corrected appropriately.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The primary activity of insulin, including TRESIBA, is regulation of glucose metabolism. Insulin and its analogs lower blood glucose by stimulating peripheral glucose uptake, especially by skeletal muscle and fat, and by inhibiting hepatic glucose production. Insulin also inhibits lipolysis and proteolysis, and enhances protein synthesis.
TRESIBA forms multi-hexamers when injected into the subcutaneous tissue resulting in a subcutaneous insulin degludec depot. The protracted time action profile of TRESIBA is predominantly due to delayed absorption of insulin degludec from the subcutaneous tissue to the systemic circulation and to a lesser extent due to binding of insulin degludec to circulating albumin.
12.2Pharmacodynamics The glucose-lowering effect of TRESIBA after 8 days of once-daily dosing was measured in a euglycemic glucose clamp study enrolling 21 patients with type 1 diabetes. Figure 2 shows the pharmacodynamic effect of TRESIBA over time following 8 once-daily subcutaneous injections of
0.4U/kg of TRESIBA in patients with type 1 diabetes. Figure 2: Mean GIR Profile for 0.4 units/kg Dose of TRESIBA (Steady State) in Patients with Type 1 Diabetes Mellitus The mean maximum glucose lowering effect (GIR max ) of a 0.4 units/kg dose of TRESIBA was 2.0 mg/kg/min, which was observed at a median of 12 hours post-dose. The glucose lowering effect of TRESIBA lasted at least 42 hours after the last of 8 once-daily injections.
In patients with type 1 diabetes mellitus, the steady-state, within subjects, day-to-day variability in total glucose lowering effect was 20% with TRESIBA (within-subject coefficient of variation for AUC GIR,τ,SS ). The total glucose-lowering effect of TRESIBA over 24 hours measured in a euglycemic clamp study after 8 days of once-daily administration in patients with type 1 diabetes increases approximately in proportion to the dose for doses between 0.4 units/kg to 0.8 units/kg. The total glucose-lowering effect of 0.4 units/kg of TRESIBA U-100 and 0.4 units/kg of TRESIBA U-200, administered at the same dose, and assessed over 24 hours in a euglycemic clamp study after 8 days of once-daily injection was comparable.
Figure 2: Mean GIR profile for
0.4 U/kg dose of TRESIBA (steady state) in patients with Type 1 diabetes mellitus
12.3Pharmacokinetics Absorption In patients with type 1 diabetes, after 8 days of once daily subcutaneous dosing with 0.4 units/kg of TRESIBA, maximum insulin degludec concentrations of 4472 pmol/L were attained at a median of 9 hours (t max ). After the first dose of TRESIBA, median onset of appearance was around one hour. Total insulin degludec concentration (i.e., exposure) increased in a dose proportional manner after subcutaneous administration of 0.4 units/kg to 0.8 units/kg TRESIBA.
Total and maximum insulin degludec exposure at steady state are comparable between TRESIBA U-100 and TRESIBA U-200 when each is administered at the same units/kg dose. Insulin degludec concentration reached steady state levels after 3-4 days of TRESIBA administration [see Dosage and Administration ( 2.2 )] . Distribution The affinity of insulin degludec to serum albumin corresponds to a plasma protein binding of >99% in human plasma.
The results of the in vitro protein binding studies demonstrate that there is no clinically relevant interaction between insulin degludec and other protein bound drugs. Elimination The half-life after subcutaneous administration is determined primarily by the rate of absorption from the subcutaneous tissue. On average, the half-life at steady state is approximately 25 hours independent of dose.
Degradation of TRESIBA is similar to that of insulin human; all metabolites formed are inactive. The mean apparent clearance of insulin degludec is
0.03L/kg (2.1 L/h in 70 kg patient) after single subcutaneous dose of 0.4 units/kg. Specific Populations Pediatrics- Population pharmacokinetic analysis was conducted for TRESIBA… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action The primary activity of insulin, including TRESIBA, is regulation of glucose metabolism. Insulin and its analogs lower blood glucose by stimulating peripheral glucose uptake, especially by skeletal muscle and fat, and by inhibiting hepatic glucose production. Insulin also inhibits lipolysis and proteolysis, and enhances protein synthesis.
TRESIBA forms multi-hexamers when injected into the subcutaneous tissue resulting in a subcutaneous insulin degludec depot. The protracted time action profile of TRESIBA is predominantly due to delayed absorption of insulin degludec from the subcutaneous tissue to the systemic circulation and to a lesser extent due to binding of insulin degludec to circulating albumin.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied TRESIBA (insulin degludec) injection is available as a clear and colorless solution as follows: Table 17: Presentations of TRESIBA TRESIBA Presentation Total volume Concentration Total units available in presentation NDC number Max dose per injection Dose increment Package Size U-100 single-patient-use FlexTouch Pen 3 mL 100 units/mL 300 Units 0169-2660-15 80 Units 1 Unit 5 pens/pack U-100 multiple-dose Vial 10 mL 100 units/mL 1,000 Units 0169-2662-11 _ _ 1 vial/pack U-200 single-patient-use FlexTouch Pen 3 mL 200 units/mL 600 Units 0169-2550-13 160 Units 2 Unit 3 pens/pack Additional Information about TRESIBA FlexTouch: • TRESIBA U-100 FlexTouch pen dials in 1 unit increments. • TRESIBA U-200 FlexTouch pen dials in 2 unit increments.
16.2Recommended Storage Dispense in the original sealed carton with the enclosed Instructions for Use. Store TRESIBA vials in the original carton to protect from light. Store unused TRESIBA in a refrigerator (36ºF to 46ºF [2ºC to 8ºC]).
Do not store in the freezer or directly adjacent to the refrigerator cooling element. Do not freeze. Do not use TRESIBA if it has been frozen.
The storage conditions are summarized in Table 18: Table 18: Storage Conditions for TRESIBA Not in-use (unopened) In-use (opened) Refrigerated (36°F to 46°F [2°C to 8°C]) Room Temperature (up to 86°F [30°C]) Room Temperature (up to 86°F [30°C]) Refrigerated (36°F to 46°F [2°C to 8°C]) 3 mL single-patient-use TRESIBA U-100 FlexTouch Until expiration date 56 days (8 weeks) 56 days (8 weeks) 56 days (8 weeks) 10 mL multiple-dose TRESIBA U-100 Vial Until expiration date 56 days (8 weeks) 56 days (8 weeks) 56 days (8 weeks) 3 mL single-patient-use TRESIBA U-200 FlexTouch Until expiration date 56 days (8 weeks) 56 days (8 weeks) 56 days (8 weeks)
📋 Description ▾
11 DESCRIPTION Insulin degludec is a long-acting basal human insulin analog for subcutaneous injection produced by a process that includes expression of recombinant DNA in Saccharomyces cerevisiae followed by chemical modification. Insulin degludec differs from human insulin in that the amino acid threonine in position B30 has been omitted and a side-chain consisting of glutamic acid and a C16 fatty acid has been attached (chemical name: LysB29(Nε-hexadecandioyl-γ-Glu) des(B30) human insulin). Insulin degludec has a molecular formula of C 274 H 411 N 65 O 81 S 6 and a molecular weight of 6.104 kDa.
It has the following structure: Figure 1: Structural Formula of Insulin Degludec TRESIBA (insulin degludec) injection is a sterile, aqueous, clear, and colorless solution available as 100 units/mL (U-100) or 200 units/mL (U-200) for subcutaneous use. For the 100 units/mL solution, each mL contains 100 units of insulin degludec and glycerin (19.6 mg), metacresol (1.72 mg), phenol (1.5 mg), zinc (32.7 mcg), and Water for Injection, USP. For the 200 units/mL solution, each mL contains 200 units of insulin degludec and glycerin (19.6 mg), metacresol (1.72 mg), phenol (1.5 mg), zinc (71.9 mcg), and Water for Injection, USP.
TRESIBA has a pH of approximately 7.6. Hydrochloric acid or sodium hydroxide may be added to adjust pH. Figure 1: Structural Formula of Tresiba
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient and/or caregiver to read the FDA-approved patient labeling (Patient Information and Instructions for Use). There are separate Instructions for Use for the Vials and FlexTouch Pens. Never Share a TRESIBA FlexTouch Pen, Needle, or Insulin Syringe Between Patients Advise patients that they should never share a TRESIBA FlexTouch pen device with another person, even if the needle is changed.
Advise patients using TRESIBA vials not to share needles or insulin syringes with another person. Sharing poses a risk for transmission of blood-borne pathogens [see Warnings and Precautions ( 5.1 )] . Hyperglycemia or Hypoglycemia Inform patients that hypoglycemia is the most common adverse reaction with insulin.
Inform patients of the symptoms of hypoglycemia(e.g., impaired ability to concentrate and react . This may present a risk in situations where these abilities are especially important, such as driving or operating other machinery. Advise patients who have frequent hypoglycemia or reduced or absent warning signs of hypoglycemia to use caution when driving or operating machinery [see Warnings and Precautions ( 5.3 )].
Advise patients that changes in insulin regimen can predispose to hyperglycemia or hypoglycemia and that changes in insulin regimen should be made under close medical supervision [see Warnings and Precautions ( 5.2 )] . Hypoglycemia Due to Medication Errors Inform patients to always check the insulin label before each injection to reduce the risk of medication error [see Warnings and Precautions ( 5.4 )] . Inform patients that the dose counter of TRESIBA FlexTouch pen shows the number of units of TRESIBA to be injected.
NO dose re-calculation is required [see Dosage and Administration ( 2.2 )] . Instruct patients to never use a syringe to remove TRESIBA from the FlexTouch disposable insulin prefilled pen. Hypersensitivity Reactions Advise patients that hypersensitivity reactions have occurred with TRESIBA.
Inform patients on the symptoms of hypersensitivity reactions [see Warnings and Precautions ( 5.5 )]. Version: 9 Novo Nordisk ® , TRESIBA ® , FlexTouch ® , LEVEMIR ® , NOVOLOG ® and NovoFine ® are registered trademarks of Novo Nordisk A/S. © 2015-2022 Novo Nordisk PATENT Information: http://novonordisk-us.com/products/product-patents.html Manufactured by: Novo Nordisk Inc. 800 Scudders Mill Road Plainsboro, NJ 08536 U.S.
License Number 1261 For information about TRESIBA contact: Novo Nordisk Inc. 800 Scudders Mill Road Plainsboro, NJ 08536 1-800-727-6500 www.novonordisk-us.com
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption In patients with type 1 diabetes, after 8 days of once daily subcutaneous dosing with 0.4 units/kg of TRESIBA, maximum insulin degludec concentrations of 4472 pmol/L were attained at a median of 9 hours (t max ). After the first dose of TRESIBA, median onset of appearance was around one hour. Total insulin degludec concentration (i.e., exposure) increased in a dose proportional manner after subcutaneous administration of 0.4 units/kg to 0.8 units/kg TRESIBA.
Total and maximum insulin degludec exposure at steady state are comparable between TRESIBA U-100 and TRESIBA U-200 when each is administered at the same units/kg dose. Insulin degludec concentration reached steady state levels after 3-4 days of TRESIBA administration [see Dosage and Administration ( 2.2 )] . Distribution The affinity of insulin degludec to serum albumin corresponds to a plasma protein binding of >99% in human plasma.
The results of the in vitro protein binding studies demonstrate that there is no clinically relevant interaction between insulin degludec and other protein bound drugs. Elimination The half-life after subcutaneous administration is determined primarily by the rate of absorption from the subcutaneous tissue. On average, the half-life at steady state is approximately 25 hours independent of dose.
Degradation of TRESIBA is similar to that of insulin human; all metabolites formed are inactive. The mean apparent clearance of insulin degludec is
0.03L/kg (2.1 L/h in 70 kg patient) after single subcutaneous dose of 0.4 units/kg. Specific Populations Pediatrics- Population pharmacokinetic analysis was conducted for TRESIBA using data from 199 pediatric subjects (1 to <18 years of age) with type 1 diabetes. Body weight was a significant covariate affecting the clearance of TRESIBA.
After adjusting for body weight, the total exposure of TRESIBA at steady state was independent of age. Geriatrics - Pharmacokinetic and pharmacodynamic response of TRESIBA was compared in 13 younger adult (18−35 years) and 14 geriatric (≥65 years) subjects with type 1 diabetes following two 6-day periods of once-daily subcutaneous dosing with 0.4 units/kg dose of TRESIBA or insulin glargine. On average, the pharmacokinetic and pharmacodynamic properties of TRESIBA at steady-state were similar in younger adult and geriatric subjects, albeit with greater between subject variability among the geriatric subjects.
Gender - The effect of gender on the pharmacokinetics of TRESIBA was examined in an across-trial analysis of the pharmacokinetic and pharmacodynamic studies conducted using unit/kg doses of TRESIBA. Overall, there were no clinically relevant differences in the pharmacokinetic properties of insulin degludec between female and male subjects. Obesity- The effect of BMI on the pharmacokinetics of TRESIBA was explored in a cross-trial analysis of pharmacokinetic and pharmacodynamic studies conducted using unit/kg doses of TRESIBA.
For subjects with type 1 diabetes, no relationship between exposure of TRESIBA and BMI was observed. For subjects with type 1 and type 2 diabetes a trend for decrease in glucose-lowering effect of TRESIBA with increasing BMI was observed. Race and Ethnicity - TRESIBA has been studied in a pharmacokinetic and pharmacodynamic study in Black or African American subjects not of Hispanic or Latino origin (N=18), White subjects of Hispanic or Latino origin (N=22) and White subjects not of Hispanic or Latino origin (N=23) with type 2 diabetes mellitus conducted using unit/kg doses of TRESIBA.
There were no statistically significant differences in the pharmacokinetic and pharmacodynamic properties of TRESIBA between the racial and ethnic groups investigated. Pregnancy- The effect of pregnancy on the pharmacokinetics and pharmacodynamics of TRESIBA has not been studied [see Use in Specific Populations ( 8.1 )] . Renal Impairment - TRESIBA pharmacokinetics was studied in 32 subjects (N=4-8/group) with normal or impaired rena… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics The glucose-lowering effect of TRESIBA after 8 days of once-daily dosing was measured in a euglycemic glucose clamp study enrolling 21 patients with type 1 diabetes. Figure 2 shows the pharmacodynamic effect of TRESIBA over time following 8 once-daily subcutaneous injections of
0.4U/kg of TRESIBA in patients with type 1 diabetes. Figure 2: Mean GIR Profile for 0.4 units/kg Dose of TRESIBA (Steady State) in Patients with Type 1 Diabetes Mellitus The mean maximum glucose lowering effect (GIR max ) of a 0.4 units/kg dose of TRESIBA was 2.0 mg/kg/min, which was observed at a median of 12 hours post-dose. The glucose lowering effect of TRESIBA lasted at least 42 hours after the last of 8 once-daily injections.
In patients with type 1 diabetes mellitus, the steady-state, within subjects, day-to-day variability in total glucose lowering effect was 20% with TRESIBA (within-subject coefficient of variation for AUC GIR,τ,SS ). The total glucose-lowering effect of TRESIBA over 24 hours measured in a euglycemic clamp study after 8 days of once-daily administration in patients with type 1 diabetes increases approximately in proportion to the dose for doses between 0.4 units/kg to 0.8 units/kg. The total glucose-lowering effect of 0.4 units/kg of TRESIBA U-100 and 0.4 units/kg of TRESIBA U-200, administered at the same dose, and assessed over 24 hours in a euglycemic clamp study after 8 days of once-daily injection was comparable.
Figure 2: Mean GIR profile for
0.4 U/kg dose of TRESIBA (steady state) in patients with Type 1 diabetes mellitus
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The efficacy of TRESIBA administered once-daily either at the same time each day or at any time each day in patients with type 1 diabetes and used in combination with a mealtime insulin was evaluated in three randomized, open-label, treat-to-target, active-controlled trials in adults and one randomized, open-label, treat-to-target, active-controlled trial in pediatric patients 1 year of age and older. The efficacy of TRESIBA administered once-daily either at the same time each day or at any time each day in adult patients with type 2 diabetes and used in combination with a mealtime insulin or in combination with common oral anti-diabetic agents was evaluated in six randomized, open-label, treat-to-target active-controlled trials.
Adult patients treated with TRESIBA achieved levels of glycemic control similar to those achieved with LANTUS (insulin glargine 100 units/mL) and LEVEMIR (insulin detemir) and achieved statistically significant improvements compared to sitagliptin.
14.1Type 1 Diabetes – Adult TRESIBA Administered at the Same Time Each Day in Combination with a Rapid-Acting Insulin Analog at Mealtimes in Adult Patients Study A The efficacy of TRESIBA was evaluated in a 52-week randomized, open-label, multicenter trial in 629 patients with type 1 diabetes mellitus (Study A). Patients were randomized to TRESIBA once-daily with the evening meal or insulin glargine U-100 once-daily according to the approved labeling. Insulin aspart was administered before each meal in both treatment arms.
The mean age of the trial population was 43 years and mean duration of diabetes was 19 years. 59% were male. 93% were White, 2% Black or African American.
5% were Hispanic. 9% of patients had eGFR<60 mL/min/1.73m 2 . The mean BMI was approximately 26.3 kg/m 2 .
At week 52, the difference in HbA 1c reduction from baseline between TRESIBA and insulin glargine U-100 was -0.01% with a 95% confidence interval of [-0.14%; 0.11%] and met the pre-specified non-inferiority margin (0.4%). See Table 6, Study A. Study B The efficacy of TRESIBA was evaluated in a 26-week randomized, open-label, multicenter trial in 455 patients with type 1 diabetes mellitus (Study B).
Patients were randomized to TRESIBA or insulin detemir once-daily in the evening. After 8 weeks, insulin detemir could be dosed twice-daily. 67% used insulin detemir once daily at end of trial.
33% used insulin detemir twice daily at end of trial. Insulin aspart was administered before each meal in both treatment arms. The mean age of the trial population was 41 years and mean duration of diabetes was 14 years.
52% were male. 45% were White, 0.4% Black or African American. 4% were Hispanic.
4% of patients had eGFR<60 mL/min/1.73m 2 . The mean BMI was approximately 23.9 kg/m 2 . At week 26, the difference in HbA 1c reduction from baseline between TRESIBA and insulin detemir was -0.09% with a 95% confidence interval of [-0.23%; 0.05%] and met the pre-specified non-inferiority margin (0.4%).
See Table 6, Study B. Table 6: Results at Week 52 in a Trial Comparing TRESIBA to Insulin Glargine U-100 (Study A) and Week 26 in a Trial Comparing TRESIBA to Insulin Detemir (Study B) in Adult Patients with Type 1 Diabetes Mellitus Receiving Insulin Aspart at Mealtimes Study A Study B TRESIBA + Insulin aspart Insulin glargine U-100 + Insulin aspart TRESIBA + Insulin aspart Insulin detemir + Insulin aspart N 472 157 302 153 HbA 1c (%) Baseline 7.7 7.7 8.0
8.0End of trial 7.3 7.3 7.3
7.3Adjusted mean change from baseline * -0.36 -0.34 -0.71 -0.61 Estimated treatment difference [95%CI] TRESIBA - basal insulin U-100 -0.01 [-0.14;0.11] -0.09 [-0.23;0.05] Proportion Achieving HbA 1c < 7% at Trial End 39.8% 42.7% 41.1% 37.3% FPG (mg/dL) Baseline 165 174 178 171 End of trial 141 149 131 161 Adjusted mean change from baseline -27.6 -21.6 -43.3 -13.5 Daily basal insulin dose Baseline mean 28 U 26 U 22 U 22 U Mean dose at end of study 29 U 1 31 U 1 25 U 2 29 U 2 Daily bolus insulin dose Bas… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Standard 2-year carcinogenicity studies in animals have not been performed to evaluate the carcinogenic potential of insulin degludec. In a 52-week study including human insulin (NPH insulin) as comparator (6.7 units/kg/day), Sprague-Dawley rats were dosed subcutaneously with insulin degludec at 3.3, 6.7, and 10 units/kg/day, resulting in 5 times the human exposure (AUC) when compared to a human subcutaneous dosage of 0.75 units/kg/day. Human insulin was dosed at 6.7 units/kg/day.
No treatment-related increases in incidences of hyperplasia, benign or malignant tumors were recorded in female mammary glands from rats dosed with insulin degludec and no treatment related changes in the female mammary gland cell proliferation were found using BrdU incorporation. Further, no treatment related changes in the occurrence of hyperplastic or neoplastic lesions were seen in other tissues in animals dosed with insulin degludec when compared to vehicle or human insulin. Genotoxicity testing of insulin degludec was not performed.
In a combined fertility and embryo-fetal study in male and female rats, treatment with insulin degludec up to 21 units/kg/day (approximately 5 times the human subcutaneous dose of 0.75 units/kg/day, based on units/body surface area) prior to mating and in female rats during gestation had no effect on mating performance and fertility.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Standard 2-year carcinogenicity studies in animals have not been performed to evaluate the carcinogenic potential of insulin degludec. In a 52-week study including human insulin (NPH insulin) as comparator (6.7 units/kg/day), Sprague-Dawley rats were dosed subcutaneously with insulin degludec at 3.3, 6.7, and 10 units/kg/day, resulting in 5 times the human exposure (AUC) when compared to a human subcutaneous dosage of 0.75 units/kg/day. Human insulin was dosed at 6.7 units/kg/day.
No treatment-related increases in incidences of hyperplasia, benign or malignant tumors were recorded in female mammary glands from rats dosed with insulin degludec and no treatment related changes in the female mammary gland cell proliferation were found using BrdU incorporation. Further, no treatment related changes in the occurrence of hyperplastic or neoplastic lesions were seen in other tissues in animals dosed with insulin degludec when compared to vehicle or human insulin. Genotoxicity testing of insulin degludec was not performed.
In a combined fertility and embryo-fetal study in male and female rats, treatment with insulin degludec up to 21 units/kg/day (approximately 5 times the human subcutaneous dose of 0.75 units/kg/day, based on units/body surface area) prior to mating and in female rats during gestation had no effect on mating performance and fertility.
📄 Patient Package Insert ▾
Patient Information TRESIBA® (tre–SI-bah) (insulin degludec) injection, for subcutaneous use Do not share your TRESIBA FlexTouch insulin delivery device with other people, even if the needle has changed. Do not share needles or syringes with another person. You may give other people a serious infection, or get a serious infection from them.
What is TRESIBA? • TRESIBA is a man-made insulin that is used to control high blood sugar in adults and children who are 1 year of age and older with diabetes mellitus. • TRESIBA is not for people with diabetic ketoacidosis (increased ketones in the blood or urine). • It is not known if TRESIBA is safe and effective in children under 1 year of age. • TRESIBA is available in 2 concentrations (U-100 and U-200): o U-100 concentration is available in pen and vial ▪ The 100 units/mL pen can be injected from 1 to 80 units in a single injection, in increments of 1 unit. ▪ The 100 units/mL vial should be used with a U-100 insulin syringe only. o U-200 concentration is only available in pen ▪ The 200 units/mL pen can be injected from 2 to 160 units in a single injection, in increments of 2 units.
Who should not take TRESIBA? Do not take TRESIBA if you: • are having an episode of low blood sugar (hypoglycemia). • have an allergy to TRESIBA or any of the ingredients in TRESIBA. Before taking TRESIBA, tell your healthcare provider about all your medical conditions including, if you are: • pregnant, planning to become pregnant, or are breastfeeding. • taking new prescription or over-the-counter medicines, vitamins, or herbal supplements.
Before you start taking TRESIBA, talk to your healthcare provider about low blood sugar and how to manage it. How should I take TRESIBA? • Read the Instructions for Use that come with your TRESIBA. • Take TRESIBA exactly as your healthcare provider tells you to. • Do not do any conversion of your dose. The dose counter always shows the selected dose in units.
Both the 100 units/mL and 200 units/mL TRESIBA FlexTouch pens are made to deliver your insulin dose in units. • Know the type and strength of insulin you take. Do not change the type of insulin you take unless your healthcare provider tells you to. The amount of insulin and the best time for you to take your insulin may need to change if you take different types of insulin. • For children who need less than 5 units of TRESIBA each day, use a TRESIBA U-100 vial. • Adults: If you miss or are delayed in taking your dose of TRESIBA: o Take your dose as soon as you remember then continue with your regular dosing schedule. o Make sure there are at least 8 hours between your doses. • If children miss a dose of TRESIBA: o Call the healthcare provider for information and instructions about checking blood sugar levels more often until the next scheduled dose of TRESIBA. • Check your blood sugar levels.
Ask your healthcare provider what your blood sugars should be and when you should check your blood sugar levels. • Do not reuse or share your needles with other people. You may give other people a serious infection or get a serious infection from them. • Never inject TRESIBA into a vein or muscle. • Never use a syringe to remove TRESIBA from the FlexTouch pen. • TRESIBA can be injected under the skin (subcutaneously) of your upper legs (thighs), upper arms, or stomach area (abdomen). • Change ( rotate) your injection sites within the area you choose with each dose to reduce your risk of getting lipodystrophy (pits in skin or thickened skin) and localized cutaneous amyloidosis (skin with lumps) at the injection sites. o Do not use the exact same spot for each injection. o Do not inject where the skin has pits, is thickened, or has lumps. o Do not inject where the skin is tender, bruised, scaly or hard, or into scars or damaged skin.
What should I avoid while taking TRESIBA? While taking TRESIBA do not: • Drive or operate heavy machinery, until you know how TRESIBA affects you. • Drink alcohol or use prescription or over-the-cou… [Excerpted — this section continues on DailyMed.]
📖 Instructions for Use ▾
INSTRUCTIONS FOR USE TRESIBA ® (tre–SI-bah) (insulin degludec) injection, for subcutaneous use 10 mL multiple-dose vial (100 units/mL, U-100) Read this Instructions for Use before you start taking TRESIBA and each time you get a refill. There may be new information. This information does not take the place of talking to your healthcare provider about your medical condition or your treatment.
The vial is not recommended for use by the blind or visually impaired without the assistance of a person trained in the proper use of the product and insulin syringe. Do not reuse or share syringes or needles with other people. You may give other people a serious infection or get a serious infection from them.
Supplies you will need to give your TRESIBA injection: • a 10 mL TRESIBA vial • a U-100 insulin syringe and needle • 2 alcohol swabs • 1 sharps container for throwing away used syringes and needles. See “Disposing of your used needles and syringes” at the end of these instructions. Preparing your TRESIBA dose: • Do not roll or shake the TRESIBA vial.
Shaking the TRESIBA vial right before the dose is drawn into the syringe may cause bubbles or foam. This can cause you to draw up the wrong dose of insulin. • The tamper-resistant cap should not be loose or damaged before the first use. Do not use if the tamper-resistant cap is loose or damaged before using TRESIBA for the first time. • Wash your hands with soap and water. • Before you start to prepare your injection, check the TRESIBA label to make sure that you are taking the right type of insulin.
This is especially important if you use more than 1 type of insulin. • Check that the TRESIBA vial is not cracked or damaged. Do not use if the TRESIBA vial is cracked or damaged. • TRESIBA should look clear and colorless. Do not use TRESIBA if it is thick, cloudy, or is colored. • Do not use TRESIBA past the expiration date printed on the label or 56 days after you start using the TRESIBA vial.
Step 1: Pull off the tamper-resistant cap (See Figure A). Step 2: Wipe the rubber stopper with an alcohol swab (See Figure B). (Figure A Figure B) Step 3: Hold the syringe with the needle pointing up.
Pull down on the plunger until the tip of the plunger reaches the line for the number of units for your prescribed dose (See Figure C). (Figure C) Step 4: Push the needle through the rubber stopper of the TRESIBA vial (See Figure D). (Figure D) Step 5: Push the plunger all the way in.
This puts air into the TRESIBA vial (See Figure E). (Figure E) Step 6: Turn the TRESIBA vial and syringe upside down and slowly pull the plunger down until the tip of the plunger is a few units past the line for your dose (See Figure F). If there are air bubbles, tap the syringe gently a few times to let any air bubbles rise to the top (See Figure G).
(Figure F) (Figure G) Step 7: Slowly push the plunger up until the tip of the plunger reaches the line for your prescribed TRESIBA dose (See Figure H). (Figure H) Step 8: Check the syringe to make sure you have the right dose of TRESIBA. Step 9: Pull the syringe out of the rubber stopper on the TRESIBA vial (See Figure I).
(Figure I) Giving your TRESIBA injection: • Inject your TRESIBA exactly as your healthcare provider has shown you. Your healthcare provider should tell you if you need to pinch the skin before injecting. • TRESIBA can be injected under the skin (subcutaneously) of your upper legs (thighs), upper arms, or stomach area (abdomen). Do not inject TRESIBA into your muscle. • Change (rotate) your injection sites within the area you choose for each dose to reduce your risk of getting lipodystrophy (pits in skin or thickened skin) and localized cutaneous amyloidosis (skin with lumps) at the injection sites.
Do not use the same injection site for each injection. Do not inject where the skin has pits, is thickened, or has lumps. Do not inject where the skin is tender, bruised, scaly or hard, or into scars or damaged skin. • Do not dilute or mix TRESIBA with any other… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL U-100 Vial NDC 0169-2662-11 List 266211 TRESIBA ® (insulin degludec) injection 100 units/mL (U-100) For subcutaneous use only Use only with a U-100 syringe. Rx Only 10 mL vial multiple-dose vial Vial carton
PRINCIPAL DISPLAY PANEL U-100 FlexTouch NDC 0169-2660-15 List: 266015 TRESIBA ® FlexTouch ® (insulin degludec) injection For Single Patient Use Only 100 units/mL (U-100) 5×3 mL Prefilled Pens For subcutaneous use only Recommended for use with NovoFine ® , NovoFine ® Plus or NovoTwist ® disposable needles. Keep in a cold place until first use. Store at 36°F to 46°F (2°C to 8°C).
Do not freeze. After first use, store between 36°F to 86°F (2°C to 30°C) for up to 56 days. Protect from light.
Rx Only Dispense in this sealed carton. U100 FT carton
PRINCIPAL DISPLAY PANEL U-200 FlexTouch NDC 0169-2550-13 List: 255013 TRESIBA ® FlexTouch ® (insulin degludec) injection For Single Patient Use Only 200 units/mL (U-200) 3×3 mL Prefilled Pens For subcutaneous use only Recommended for use with NovoFine ® , NovoFine ® Plus or NovoTwist ® disposable needles. disposable needles. Keep in a cold place until first use. Store at 36°F to 46°F (2°C to 8°C).
Do not freeze. After first use, store between 36°F to 86°F (2°C to 30°C) for up to 56 days. Protect from light.
Rx Only Dispense in this sealed carton. U200 FT carton