
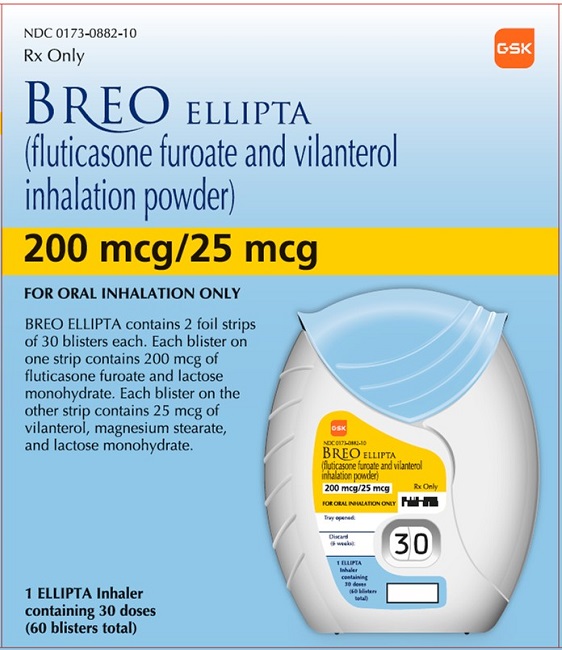
Breo Ellipta fluticasone furoate and vilanterol trifenatate 200 ug; 25 ug Powder
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the beta2-Adrenergic Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
The combination of fluticasone and vilanterol is used to control wheezing, shortness of breath, coughing, and chest tightness caused by asthma and chronic obstructive pulmonary (COPD; a group of diseases that affect the lungs and airways, that includes chronic bronchitis and emphysema) in adults. It is also used to control difficulty breathing, wheezing, shortness of breath, coughing, and chest tightness caused by asthma in adults and children 5 years of age or older. Fluticasone is in a class of medications called steroids. It works by reducing swelling in the airways. Vilanterol is in a clas...
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $6.502 | $195.07 / 30 powders |
| Medicaid paysCMS SDUD · 12 mo | $6.55 | $196.49 / 30 powders |
| Medicare drug plans payPart D · Q2 2026 | $6.52 | $195.73 / 30 powders |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Breo Ellipta 200 ug/1; 25 ugthis 00173-0882-10 | GlaxoSmithKline | 1 inhaler | $6.502 | — | Availability likely | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8511304 ↗ | Method of use | U-1691 | Jun 14, 2027 |
| US 8511304 ↗ | Method of use | U-1424 | Jun 14, 2027 |
| US 11116721 ↗ | Method of use | U-1401 | Feb 26, 2029 |
| US 8511304 ↗ | Method of use | U-3623 | Jun 14, 2027 |
| US 8511304 ↗ | Method of use | U-3623 | Jun 14, 2027 |
| US 11116721 ↗ | Method of use | U-3623 | Feb 26, 2029 |
| US 11116721 ↗ | Method of use | U-3623 | Feb 26, 2029 |
| US 8511304 ↗ | Method of use | U-1691 | Jun 14, 2027 |
| US 8511304 ↗ | Method of use | U-3623 | Jun 14, 2027 |
| US 11116721 ↗ | Method of use | U-3623 | Feb 26, 2029 |
| US 11116721 ↗ | Method of use | U-1691 | Feb 26, 2029 |
| US 11116721 ↗ | Method of use | U-1691 | Feb 26, 2029 |
| US 8746242 ↗ | Drug product | — | Oct 11, 2030 |
| US 8534281 ↗ | Drug product | — | Mar 8, 2030 |
| US 8534281 ↗ | Drug product | — | Mar 8, 2030 |
| US 8534281 ↗ | Drug product | — | Mar 8, 2030 |
| US 8746242 ↗ | Drug product | — | Oct 11, 2030 |
| US 8746242 ↗ | Drug product | — | Oct 11, 2030 |
| US 8746242*PED ↗ | Drug product | — | Apr 11, 2031 |
| US 8534281*PED ↗ | Drug product | — | Sep 8, 2030 |
| US 8511304*PED ↗ | Drug product | — | Dec 14, 2027 |
| US 8746242*PED ↗ | Drug product | — | Apr 11, 2031 |
| US 8534281*PED ↗ | Drug product | — | Sep 8, 2030 |
| US 8511304*PED ↗ | Drug product | — | Dec 14, 2027 |
| US 11116721*PED ↗ | Drug product | — | Aug 26, 2029 |
| US 8511304*PED ↗ | Drug product | — | Dec 14, 2027 |
| US 8746242*PED ↗ | Drug product | — | Apr 11, 2031 |
| US 8534281*PED ↗ | Drug product | — | Sep 8, 2030 |
| US 11116721*PED ↗ | Drug product | — | Aug 26, 2029 |
| US 11116721*PED ↗ | Drug product | — | Aug 26, 2029 |
| Code | What it grants | Expires |
|---|---|---|
| NPP | New Patient Population | May 13, 2026 |
| NS | New Strength | May 13, 2026 |
| PED | Pediatric Exclusivity (+6 months) | Nov 13, 2026 |
| PED | Pediatric Exclusivity (+6 months) | Nov 13, 2026 |
Is there a generic version of BREO ELLIPTA 200-25 MCG INHALR?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 00173-0882-10 You're viewing this | 1 TRAY in 1 CARTON (0173-0882-10) / 1 INHALER in 1 TRAY / 30 POWDER in 1 INHALER | $6.50 / ea | $195.07 | 2015-04-30 | Active |
| 00173-0882-14 | 1 TRAY in 1 CARTON (0173-0882-14) / 1 INHALER in 1 TRAY / 14 POWDER in 1 INHALER | $5.36 / ea | $75.00 | 2015-04-30 | Active |
| 00173-0882-61 | 1 TRAY in 1 CARTON (0173-0882-61) / 1 INHALER in 1 TRAY / 14 POWDER in 1 INHALER | — | — | 2015-04-30 | Active |
Per ea, this pack runs about 21% above the cheapest pack (NDC 00173-0882-14, $5.36 vs $6.50 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 00173-0882-10?
What NDC number is used to bill for this package of Breo Ellipta fluticasone furoate and vilanterol trifenatate 200 ug; 25 ug Powder?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE BREO ELLIPTA is a combination of fluticasone furoate, a corticosteroid, and vilanterol, a long-acting beta 2 -adrenergic agonist (LABA), indicated for: • the maintenance treatment of patients with chronic obstructive pulmonary disease (COPD). ( 1.1 ) • the maintenance treatment of asthma in patients aged 5 years and older. ( 1.2 ) Limitations of Use: Not indicated for relief of acute bronchospasm. ( 1.3 , 5.2 )
1.1Maintenance Treatment of Chronic Obstructive Pulmonary Disease BREO ELLIPTA is indicated for the maintenance treatment of patients with chronic obstructive pulmonary disease (COPD).
1.2Maintenance Treatment of Asthma BREO ELLIPTA is indicated for the maintenance treatment of asthma in patients aged 5 years and older.
1.3Limitations of Use BREO ELLIPTA is NOT indicated for the relief of acute bronchospasm.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • For oral inhalation only. ( 2.3 ) • Maintenance treatment of COPD: 1 actuation of BREO ELLIPTA 100/25 mcg once daily administered by oral inhalation. ( 2.1 ) • Maintenance treatment of asthma in adult patients aged 18 years and older: 1 actuation of BREO ELLIPTA 100/25 mcg or BREO ELLIPTA 200/25 mcg once daily administered by oral inhalation.
( 2.2 ) • Maintenance treatment of asthma in pediatric patients aged 12 to 17 years: 1 actuation of BREO ELLIPTA 100/25 mcg once daily administered by oral inhalation. ( 2.2 ) • Maintenance treatment of asthma in pediatric patients aged 5 to 11 years: 1 actuation of BREO ELLIPTA 50/25 mcg once daily administered by oral inhalation. ( 2.2 )
2.1Recommended Dosage for Maintenance Treatment of Chronic Obstructive Pulmonary Disease The recommended dosage of BREO ELLIPTA 100/25 mcg (containing fluticasone furoate 100 mcg and vilanterol 25 mcg) is 1 actuation once daily by oral inhalation. If shortness of breath occurs in the period between doses, an inhaled, short-acting beta 2 -agonist (rescue medicine, e.g., albuterol) should be used for immediate relief.
2.2Recommended Dosage for Maintenance Treatment of Asthma Adult Patients Aged 18 Years and Older The recommended dosage of BREO ELLIPTA 100/25 mcg (containing fluticasone furoate 100 mcg and vilanterol 25 mcg) is 1 actuation once daily by oral inhalation or BREO ELLIPTA 200/25 mcg (containing fluticasone furoate 200 mcg and vilanterol 25 mcg) is 1 actuation once daily by oral inhalation. • When choosing the starting dosage strength of BREO ELLIPTA, consider the patients’ disease severity, their previous asthma therapy, including the inhaled corticosteroid (ICS) dosage, as well as the patients’ current control of asthma symptoms and risk of future exacerbation. • The median time to onset, defined as a 100-mL increase from baseline in mean forced expiratory volume in 1 second (FEV1), was approximately 15 minutes after beginning treatment.
Individual patients will experience a variable time to onset and degree of symptom relief. • For patients who do not respond adequately to BREO ELLIPTA 100/25 mcg once daily, increasing the dose to BREO ELLIPTA 200/25 mcg once daily may provide additional improvement in asthma control. For patients who do not respond adequately to BREO ELLIPTA 200/25 mcg once daily, re-evaluate and consider other therapeutic regimens and additional therapeutic options. • The maximum recommended dosage is 1 inhalation of BREO ELLIPTA 200/25 mcg once daily. • If asthma symptoms arise in the period between doses, an inhaled, short-acting beta2-agonist (rescue medicine, e.g., albuterol) should be used for immediate relief.
Pediatric Patients Aged 12 to 17 Years The recommended dosage of BREO ELLIPTA 100/25 mcg (containing fluticasone furoate 100 mcg and vilanterol 25 mcg) is 1 actuation once daily by oral inhalation [see Warnings and Precautions ( 5.14 )] . Pediatric Patients Aged 5 to 11 Years The recommended dosage of BREO ELLIPTA 50/25 mcg (containing fluticasone furoate 50 mcg and vilanterol 25 mcg) is 1 actuation once daily by oral inhalation [see Warnings and Precautions ( 5.14 )] .
2.3Administration Information • After inhalation, the patient should rinse his/her mouth with water without swallowing to help reduce the risk of oropharyngeal candidiasis [see Warnings and Precautions ( 5.4)] . • BREO ELLIPTA should be used at the same time every day. Do not use BREO ELLIPTA more than 1 time every 24 hours. • More frequent administration or a greater number of inhalations (more than 1 inhalation daily) of the prescribed strength of BREO ELLIPTA is not recommended as some patients are more likely to experience adverse effects with higher doses.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Inhalation powder: • 50 mcg fluticasone furoate and 25 mcg vilanterol (50/25 mcg) per actuation • 100 mcg fluticasone furoate and 25 mcg vilanterol (100/25 mcg) per actuation • 200 mcg fluticasone furoate and 25 mcg vilanterol (200/25 mcg) per actuation Inhalation powder: • 50 mcg fluticasone furoate and 25 mcg vilanterol (50/25 mcg) per actuation ( 3 ) • 100 mcg fluticasone furoate and 25 mcg vilanterol (100/25 mcg) per actuation ( 3 ) • 200 mcg fluticasone furoate and 25 mcg vilanterol (200/25 mcg) per actuation ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS BREO ELLIPTA is contraindicated in the following conditions: • Primary treatment of status asthmaticus or other acute episodes of COPD or asthma where intensive measures are required [see Warnings and Precautions ( 5.2 )] . • Severe hypersensitivity to milk proteins or demonstrated hypersensitivity to fluticasone furoate, vilanterol, or any of the excipients [see Warnings and Precautions ( 5.11 ), Description ( 11 )] . • Primary treatment of status asthmaticus or acute episodes of COPD or asthma requiring intensive measures.
( 4 ) • Severe hypersensitivity to milk proteins or any ingredients. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • LABA monotherapy increases the risk of serious asthma-related events. ( 5.1 ) • Do not initiate in acutely deteriorating COPD or asthma. Do not use to treat acute symptoms.
( 5.2 ) • Do not use in combination with additional therapy containing a LABA because of risk of overdose. ( 5.3 ) • Candida albicans infection of the mouth and pharynx may occur. Monitor patients periodically.
Advise the patient to rinse his/her mouth with water without swallowing after inhalation to help reduce the risk. ( 5.4 ) • Increased risk of pneumonia in patients with COPD. Monitor patients for signs and symptoms of pneumonia.
( 5.5 ) • Potential worsening of infections (e.g., existing tuberculosis; fungal, bacterial, viral, or parasitic infections; ocular herpes simplex). Use with caution in patients with these infections. More serious or even fatal course of chickenpox or measles can occur in susceptible patients.
( 5.6 ) • Risk of impaired adrenal function when transferring from systemic corticosteroids. Wean patients slowly from systemic corticosteroids if transferring to BREO ELLIPTA. ( 5.7 ) • Hypercorticism and adrenal suppression may occur with very high dosages or at the regular dosage in susceptible individuals.
If such changes occur, discontinue BREO ELLIPTA slowly. ( 5.8 ) • If paradoxical bronchospasm occurs, discontinue BREO ELLIPTA and institute alternative therapy. ( 5.10 ) • Use with caution in patients with cardiovascular disorders because of beta-adrenergic stimulation.
( 5.12 ) • Assess for decrease in bone mineral density (BMD) initially and periodically thereafter. ( 5.13 ) • Monitor growth of pediatric patients ( 5.14 ) • Glaucoma and cataracts may occur with long-term use of Inhaled Corticosteroid (ICS). Consider referral to an ophthalmologist in patients who develop ocular symptoms or use BREO ELLIPTA long term.
( 5.15 ) • Use with caution in patients with convulsive disorders, thyrotoxicosis, diabetes mellitus, and ketoacidosis. ( 5.16 ) • Increased blood glucose levels have been reported. Also, be alert to hypokalemia.
( 5.17 )
5.1Serious Asthma-Related Events – Hospitalizations, Intubations, Death Use of Long-acting Beta 2 -adrenergic Agonist (LABA) as monotherapy (without ICS) for asthma is associated with an increased risk of asthma-related death [see Salmeterol Multicenter Asthma Research Trial (SMART)] . Available data from controlled clinical trials also suggest that use of LABA as monotherapy increases the risk of asthma-related hospitalization in pediatric patients. These findings are considered a class effect of LABA monotherapy.
When LABA are used in fixed-dose combination with ICS, data from large clinical trials do not show a significant increase in the risk of serious asthma‑related events (hospitalizations, intubations, death) compared with ICS alone (see Serious Asthma-Related Events with Inhaled Corticosteroid/Long-Acting Beta 2 -Adrenergic Agonists) . Serious Asthma-Related Events with Inhaled Corticosteroid/Long-Acting Beta 2 -Adrenergic Agonists Four (4) large, 26-week, randomized, double-blind, active-controlled clinical safety trials were conducted to evaluate the risk of serious asthma-related events when LABA were used in fixed-dose combination with ICS compared with ICS alone in patients with asthma.
Three (3) trials included adult and pediatric patients aged 12 years and older: 1 trial compared budesonide/formoterol with budesonide, 1 trial compared fluticasone propionate/salmeterol inhalation powder with fluticasone propionate inhalation powder, and 1 trial compared mometasone furoate/formoterol with mometasone furoate. The fourth trial included pediatric patients aged 4 to 11 years and compared fluticasone propionate/salmeterol inhalation powder with fluticasone propionate inhalation powder. The primary safety endpoint for all 4 trials was serious asthma-related events (hospitalizations, intubations, death).
A blinded adjudication committee determined whether events…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in labeling: • Serious Asthma-Related Events – Hospitalizations, Intubations, Death [see Warnings and Precautions ( 5.1 )] • Oropharyngeal Candidiasis [see Warnings and Precautions ( 5.4 )] • Pneumonia [see Warnings and Precautions ( 5.5 )] • Immunosuppression and Risk of Infections [see Warnings and Precautions ( 5.6 )] • Hypercorticism and Adrenal Suppression [see Warnings and Precautions ( 5.8 )] • Paradoxical Bronchospasm [see Warnings and Precautions ( 5.10 )] • Cardiovascular Effects [see Warnings and Precautions ( 5.12 )] • Reduction in Bone Mineral Density [see Warnings and Precautions ( 5.13 )] • Growth Effects [see Warnings and Precautions ( 5.14 )] • Glaucoma and Cataracts [see Warnings and Precautions ( 5.15 )] Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in practice. • COPD: Most common adverse reactions (incidence ≥3%) are nasopharyngitis, upper respiratory tract infection, headache, oral candidiasis, back pain, pneumonia, bronchitis, sinusitis, cough, oropharyngeal pain, arthralgia, hypertension, influenza, pharyngitis, and pyrexia.
( 6.1 ) • Asthma: Most common adverse reactions (incidence ≥2%) are nasopharyngitis, oral candidiasis, headache, influenza, upper respiratory tract infection, bronchitis, sinusitis, oropharyngeal pain, dysphonia, and cough. ( 6.2 ) To report SUSPECTED ADVERSE REACTIONS, contact GlaxoSmithKline at 1-888-825-5249 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience in Chronic Obstructive Pulmonary Disease The safety data described below are based on two 6-month and two 12-month trials and one long-term mortality trial. In these studies, 5,356 patients with COPD received at least 1 dose of BREO ELLIPTA 100/25 mcg. Adverse reactions observed in other studies of BREO ELLIPTA in COPD patients were similar to those observed in these 5 trials.
6-Month Trials The incidence of adverse reactions associated with BREO ELLIPTA 100/25 mcg in Table 2 is based on 2 placebo-controlled, 6-month clinical trials (Trials 1 and 2; n = 1,224 and n = 1,030, respectively). Of the 2,254 patients, 70% were male and 84% were White. They had a mean age of 62 years and an average smoking history of 44 pack years, with 54% identified as current smokers.
At screening, the mean postbronchodilator percent predicted FEV 1 was 48% (range: 14% to 87%), the mean postbronchodilator FEV 1 /forced vital capacity (FVC) ratio was 47% (range: 17% to 88%), and the mean percent reversibility was 14% (range: -41% to 152%). Patients received 1 inhalation once daily of the following: BREO ELLIPTA 100/25 mcg, BREO ELLIPTA 200/25 mcg, fluticasone furoate/vilanterol 50/25 mcg, fluticasone furoate 100 mcg, fluticasone furoate 200 mcg, vilanterol 25 mcg, or placebo. Table 2.
Adverse Reactions with BREO ELLIPTA 100/25 mcg with ≥3% Incidence and More Common than Placebo in Patients with Chronic Obstructive Pulmonary Disease a Includes oral candidiasis, oropharyngeal candidiasis, candidiasis, and fungal oropharyngitis. Adverse Reaction BREO ELLIPTA 100/25 mcg (n = 410) % Vilanterol 25 mcg (n = 408) % Fluticasone Furoate 100 mcg (n = 410) % Placebo (n = 412) % Infections and infestations Nasopharyngitis 9 10 8 8 Upper respiratory tract infection 7 5 4 3 Oropharyngeal candidiasis a 5 2 3 2 Nervous system disorders Headache 7 9 7 5 12-Month Trials Long-term safety data are based on two 12-month trials (Trials 3 and 4; n = 1,633 and n = 1,622, respectively).
Trials 3 and 4 included 3,255 patients, of which 57% were male and 85% were White. They had a mean age of 64 years and an average smoking history of 46 pack years, with 44% identified as current smokers. At screening, the mean postbronchodilator percent predicte…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Strong cytochrome P450 3A4 inhibitors (e.g., ketoconazole): Use with caution. May cause systemic corticosteroid and cardiovascular effects. ( 7.1 ) • Monoamine oxidase inhibitors and tricyclic antidepressants: Use with extreme caution.
May potentiate effect of vilanterol on cardiovascular system. ( 7.2 ) • Beta-blockers: Use with caution. May block bronchodilatory effects of beta-agonists and produce severe bronchospasm.
( 7.3 ) • Diuretics: Use with caution. Electrocardiographic changes and/or hypokalemia associated with non–potassium-sparing diuretics may worsen with concomitant beta-agonists. ( 7.4 )
7.1Inhibitors of Cytochrome P450 3A4 Fluticasone furoate and vilanterol are both substrates of CYP3A4. Concomitant administration of the strong CYP3A4 inhibitor ketoconazole increases the systemic exposure to fluticasone furoate and vilanterol. Caution should be exercised when considering the coadministration of BREO ELLIPTA with ketoconazole and other known strong CYP3A4 inhibitors [see Warnings and Precautions ( 5.9 ), Clinical Pharmacology ( 12.3 )] .
7.2Monoamine Oxidase Inhibitors, Tricyclic Antidepressants, and QTc Prolonging Drugs Vilanterol, like other beta 2 -agonists, should be administered with extreme caution to patients being treated with monoamine oxidase inhibitors, tricyclic antidepressants, or drugs known to prolong the QTc interval or within 2 weeks of discontinuation of such agents, because the effect of adrenergic agonists on the cardiovascular system may be potentiated by these agents. Drugs that are known to prolong the QTc interval have an increased risk of ventricular arrhythmias.
7.3Beta-Adrenergic Receptor Blocking Agents Beta-blockers not only block the pulmonary effect of beta-agonists, such as vilanterol, but may also produce severe bronchospasm in patients with COPD or asthma. Therefore, patients with COPD or asthma should not normally be treated with beta-blockers. However, under certain circumstances, there may be no acceptable alternatives to the use of beta-adrenergic blocking agents for these patients; cardioselective beta-blockers could be considered, although they should be administered with caution.
7.4Non–Potassium-Sparing Diuretics The electrocardiographic changes and/or hypokalemia that may result from the administration of non–potassium-sparing diuretics (such as loop or thiazide diuretics) can be acutely worsened by beta-agonists, especially when the recommended dose of the beta-agonist is exceeded. Although the clinical significance of these effects is not known, caution is advised in the coadministration of beta-agonists with non–potassium-sparing diuretics.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Hepatic impairment: Fluticasone furoate systemic exposure may increase in patients with moderate or severe impairment. Monitor for systemic corticosteroid effects. ( 8.6 , 12.3 )
8.1Pregnancy Risk Summary There are insufficient data on the use of BREO ELLIPTA or its individual components, fluticasone furoate and vilanterol, in pregnant women to inform a drug-associated risk. (See Clinical Considerations.) In an animal reproduction study, fluticasone furoate and vilanterol administered by inhalation alone or in combination to pregnant rats during the period of organogenesis produced no fetal structural abnormalities. The highest fluticasone furoate and vilanterol doses in this study were approximately 5 and 40 times the maximum recommended human daily inhalation doses (MRHDID) of 200 and 25 mcg, respectively.
(See Data.) The estimated risk of major birth defects and miscarriage for the indicated populations is unknown. In the U.S. general population, the estimated risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryofetal Risk: In women with poorly or moderately controlled asthma, there is an increased risk of several perinatal outcomes such as pre-eclampsia in the mother and prematurity, low birth weight, and small for gestational age in the neonate.
Pregnant women should be closely monitored, and medication adjusted as necessary to maintain optimal control of asthma. Labor or Delivery: BREO ELLIPTA should be used during late gestation and labor only if the potential benefit justifies the potential for risks related to beta-agonists interfering with uterine contractility. Data Animal Data: Fluticasone Furoate and Vilanterol: In an embryofetal developmental study, pregnant rats received fluticasone furoate and vilanterol during the period of organogenesis at doses up to approximately 5 and 40 times the MRHDID of 200 and 25 mcg, respectively, alone or in combination (on a mcg/m 2 basis at inhalation doses up to approximately 95 mcg/kg/day).
No evidence of structural abnormalities was observed. Fluticasone Furoate: In 2 separate embryofetal developmental studies, pregnant rats and rabbits received fluticasone furoate during the period of organogenesis at doses up to approximately 4 and 1 times, respectively, the MRHDID of 200 mcg (on a mcg/m 2 basis at maternal inhalation doses up to 91 and 8 mcg/kg/day, respectively). No evidence of structural abnormalities in fetuses was observed in either species.
In a perinatal and postnatal developmental study in rats, dams received fluticasone furoate during late gestation and lactation periods at doses up to approximately 1 time the MRHDID of 200 mcg (on a mcg/m 2 basis at maternal inhalation doses up to 27 mcg/kg/day). No evidence of effects on offspring development was observed. Vilanterol: In 2 separate embryofetal developmental studies, pregnant rats and rabbits received vilanterol during the period of organogenesis at doses up to approximately 13,000 and 1,000 times, respectively, the MRHDID (on a mcg/m 2 basis at maternal inhalation doses up to 33,700 mcg/kg/day in rats and on an AUC basis at maternal inhaled doses up to 5,740 mcg/kg/day in rabbits).
No evidence of structural abnormalities was observed at any dose in rats or in rabbits up to approximately 160 times the MRHDID (on an AUC basis at maternal doses up to 591 mcg/kg/day). However, fetal skeletal variations were observed in rabbits at approximately 1,000 times the MRHDID (on an AUC basis at maternal inhaled or subcutaneous doses of 5,740 or 300 mcg/kg/day, respectively). The skeletal variations included decreased or absent ossification in cervical vertebral centrum and metacarpals.
In a perinatal and postnatal developmental study in rats, dams received vilanterol during late gestation and the lactation periods at doses up to approximately 3,900 times the MRHDID…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are insufficient data on the use of BREO ELLIPTA or its individual components, fluticasone furoate and vilanterol, in pregnant women to inform a drug-associated risk. (See Clinical Considerations.) In an animal reproduction study, fluticasone furoate and vilanterol administered by inhalation alone or in combination to pregnant rats during the period of organogenesis produced no fetal structural abnormalities. The highest fluticasone furoate and vilanterol doses in this study were approximately 5 and 40 times the maximum recommended human daily inhalation doses (MRHDID) of 200 and 25 mcg, respectively.
(See Data.) The estimated risk of major birth defects and miscarriage for the indicated populations is unknown. In the U.S. general population, the estimated risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryofetal Risk: In women with poorly or moderately controlled asthma, there is an increased risk of several perinatal outcomes such as pre-eclampsia in the mother and prematurity, low birth weight, and small for gestational age in the neonate.
Pregnant women should be closely monitored, and medication adjusted as necessary to maintain optimal control of asthma. Labor or Delivery: BREO ELLIPTA should be used during late gestation and labor only if the potential benefit justifies the potential for risks related to beta-agonists interfering with uterine contractility. Data Animal Data: Fluticasone Furoate and Vilanterol: In an embryofetal developmental study, pregnant rats received fluticasone furoate and vilanterol during the period of organogenesis at doses up to approximately 5 and 40 times the MRHDID of 200 and 25 mcg, respectively, alone or in combination (on a mcg/m 2 basis at inhalation doses up to approximately 95 mcg/kg/day).
No evidence of structural abnormalities was observed. Fluticasone Furoate: In 2 separate embryofetal developmental studies, pregnant rats and rabbits received fluticasone furoate during the period of organogenesis at doses up to approximately 4 and 1 times, respectively, the MRHDID of 200 mcg (on a mcg/m 2 basis at maternal inhalation doses up to 91 and 8 mcg/kg/day, respectively). No evidence of structural abnormalities in fetuses was observed in either species.
In a perinatal and postnatal developmental study in rats, dams received fluticasone furoate during late gestation and lactation periods at doses up to approximately 1 time the MRHDID of 200 mcg (on a mcg/m 2 basis at maternal inhalation doses up to 27 mcg/kg/day). No evidence of effects on offspring development was observed. Vilanterol: In 2 separate embryofetal developmental studies, pregnant rats and rabbits received vilanterol during the period of organogenesis at doses up to approximately 13,000 and 1,000 times, respectively, the MRHDID (on a mcg/m 2 basis at maternal inhalation doses up to 33,700 mcg/kg/day in rats and on an AUC basis at maternal inhaled doses up to 5,740 mcg/kg/day in rabbits).
No evidence of structural abnormalities was observed at any dose in rats or in rabbits up to approximately 160 times the MRHDID (on an AUC basis at maternal doses up to 591 mcg/kg/day). However, fetal skeletal variations were observed in rabbits at approximately 1,000 times the MRHDID (on an AUC basis at maternal inhaled or subcutaneous doses of 5,740 or 300 mcg/kg/day, respectively). The skeletal variations included decreased or absent ossification in cervical vertebral centrum and metacarpals.
In a perinatal and postnatal developmental study in rats, dams received vilanterol during late gestation and the lactation periods at doses up to approximately 3,900 times the MRHDID (on a mcg/m 2 basis at maternal oral doses up to 10,000 mcg/kg/day). No evidence of effects in offspring development was observed.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of BREO ELLIPTA for the maintenance treatment of asthma in pediatric patients 5 years of age and older have been established. This indication is based on Trial 14, an adequate and well-controlled trial in pediatric patients aged 5 to 17 years [see Adverse Reactions ( 6.2 ), Clinical Studies ( 14.2 )] . The recommended dosage for pediatric patients is different than the adult dosage [see Dosage and Administration ( 2.2 )] .
The safety and efficacy of BREO ELLIPTA in pediatric patients aged younger than 5 years have not been established. In Trial 12, an exacerbation trial [see Clinical Studies ( 14.2 )] , pediatric patients aged 12 to 17 years (n = 281) were treated with BREO ELLIPTA 100/25 mcg (n = 151) or treated with fluticasone furoate 100 mcg (n = 130). Among these patients, 10% of patients treated with BREO ELLIPTA 100/25 mcg reported an asthma exacerbation compared with 7% for patients treated with fluticasone furoate 100 mcg.
Asthma-related hospitalizations occurred in 4 patients (2.6%) treated with BREO ELLIPTA 100/25 mcg compared with 0 patients treated with fluticasone furoate 100 mcg. Effects on Growth Orally inhaled corticosteroids may cause a reduction in growth velocity when administered to pediatric patients. A reduction of growth velocity in pediatric patients may occur as a result of poorly controlled asthma or from use of corticosteroids, including ICS.
The effects of long-term treatment of pediatric patients with ICS, including fluticasone furoate, on final adult height are not known. Controlled clinical trials have shown that ICS may cause a reduction in growth in children. In these trials, the mean reduction in growth velocity was approximately 1 cm/year (range: 0.3 to 1.8 cm/year) and appears to be related to dose and duration of exposure.
This effect has been observed in the absence of laboratory evidence of HPA axis suppression, suggesting that growth velocity is a more sensitive indicator of systemic corticosteroid exposure in children than some commonly used tests of HPA axis function. The long-term effects of this reduction in growth velocity associated with orally inhaled corticosteroids, including the impact on final adult height, are unknown. The potential for “catch-up” growth following discontinuation of treatment with orally inhaled corticosteroids has not been adequately studied.
The growth of pediatric patients receiving orally inhaled corticosteroids, including BREO ELLIPTA, should be monitored routinely (e.g., via stadiometry). The potential growth effects of prolonged treatment should be weighed against the clinical benefits obtained and the risks associated with alternative therapies. To minimize the systemic effects of orally inhaled corticosteroids, including BREO ELLIPTA, each patient should be titrated to the lowest dose that effectively controls his/her symptoms.
A randomized, double-blind, parallel-group, multicenter, 1-year, placebo-controlled trial evaluated the effect of once-daily treatment with orally inhaled fluticasone furoate 50 mcg on growth velocity assessed by stadiometry. The patients were 457 prepubertal children (girls aged 5 to <8 years and boys aged 5 to <9 years). Mean growth velocity over the 52-week treatment period was lower in the patients receiving orally inhaled fluticasone furoate (5.905 cm/year) compared with placebo (6.065 cm/year).
The mean reduction in growth velocity was 0.16 cm/year (95% CI: -0.14, 0.46) [see Warnings and Precautions ( 5.14 )] .
🧓 Geriatric Use ▾
8.5Geriatric Use Based on available data, no adjustment of the dosage of BREO ELLIPTA in geriatric patients is necessary, but greater sensitivity in some older individuals cannot be ruled out. Clinical trials of BREO ELLIPTA for COPD included 4,820 subjects aged 65 years and older and 1,118 subjects aged 75 years and older. Clinical trials of BREO ELLIPTA for asthma included 854 subjects aged 65 years and older.
No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE BREO ELLIPTA contains both fluticasone furoate and vilanterol; therefore, the risks associated with overdosage for the individual components described below apply to BREO ELLIPTA. Treatment of overdosage consists of discontinuation of BREO ELLIPTA together with institution of appropriate symptomatic and/or supportive therapy. The judicious use of a cardioselective beta-receptor blocker may be considered, bearing in mind that such medicine can produce bronchospasm.
Cardiac monitoring is recommended in cases of overdosage. Fluticasone Furoate Because of low systemic bioavailability (15.2%) and an absence of acute drug-related systemic findings in clinical trials, overdosage of fluticasone furoate is unlikely to require any treatment other than observation. If used at excessive doses for prolonged periods, systemic effects such as hypercorticism may occur [see Warnings and Precautions ( 5.8 )] .
Vilanterol The expected signs and symptoms with overdosage of vilanterol are those of excessive beta-adrenergic stimulation and/or occurrence or exaggeration of any of the signs and symptoms of beta-adrenergic stimulation (e.g., seizures, angina, hypertension or hypotension, tachycardia with rates up to 200 beats/min, arrhythmias, nervousness, headache, tremor, muscle cramps, dry mouth, palpitation, nausea, dizziness, fatigue, malaise, insomnia, hyperglycemia, hypokalemia, metabolic acidosis). As with all inhaled sympathomimetic medicines, cardiac arrest and even death may be associated with an overdose of vilanterol.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action BREO ELLIPTA BREO ELLIPTA contains both fluticasone furoate and vilanterol. The mechanisms of action described below for the individual components apply to BREO ELLIPTA. These drugs represent 2 different classes of medications (an ICS and a LABA), each having different effects on clinical and physiological indices.
Fluticasone Furoate Fluticasone furoate is a synthetic trifluorinated corticosteroid with anti-inflammatory activity. Fluticasone furoate has been shown in vitro to exhibit a binding affinity for the human glucocorticoid receptor that is approximately 29.9 times that of dexamethasone and 1.7 times that of fluticasone propionate. The clinical relevance of these findings is unknown.
The precise mechanism through which fluticasone furoate affects COPD and asthma symptoms is not known. Inflammation is an important component in the pathogenesis of COPD and asthma. Corticosteroids have been shown to have a wide range of actions on multiple cell types (e.g., mast cells, eosinophils, neutrophils, macrophages, lymphocytes) and mediators (e.g., histamine, eicosanoids, leukotrienes, cytokines) involved in inflammation.
Specific effects of fluticasone furoate demonstrated in in vitro and in vivo models included activation of the glucocorticoid response element, inhibition of pro-inflammatory transcription factors such as NFkB, and inhibition of antigen-induced lung eosinophilia in sensitized rats. These anti-inflammatory actions of corticosteroids may contribute to their efficacy. Vilanterol Vilanterol is a LABA.
In vitro tests have shown the functional selectivity of vilanterol was similar to salmeterol. The clinical relevance of this in vitro finding is unknown. Although beta 2 -receptors are the predominant adrenergic receptors in bronchial smooth muscle and beta 1 -receptors are the predominant receptors in the heart, there are also beta 2 -receptors in the human heart comprising 10% to 50% of the total beta-adrenergic receptors.
The precise function of these receptors has not been established, but they raise the possibility that even highly selective beta 2 -agonists may have cardiac effects. The pharmacologic effects of beta 2 -adrenergic agonist drugs, including vilanterol, are at least in part attributable to stimulation of intracellular adenyl cyclase, the enzyme that catalyzes the conversion of adenosine triphosphate (ATP) to cyclic-3′,5′-adenosine monophosphate (cyclic AMP). Increased cyclic AMP levels cause relaxation of bronchial smooth muscle and inhibition of release of mediators of immediate hypersensitivity from cells, especially from mast cells.
12.2Pharmacodynamics Cardiac Electrophysiology Healthy Subjects: QTc interval prolongation was studied in a double-blind, multiple-dose, placebo- and positive-controlled crossover study in 85 healthy volunteers. The maximum mean (95% upper confidence bound) difference in QTcF from placebo after baseline correction was 4.9 (7.5) milliseconds and 9.6 (12.2) milliseconds seen 30 minutes after dosing for fluticasone furoate/vilanterol 200/25 mcg and fluticasone furoate/vilanterol 800/100 mcg, respectively. A dose-dependent increase in heart rate was also observed.
The maximum mean (95% upper confidence bound) difference in heart rate from placebo after baseline-correction was 7.8 (9.4) beats/min and 17.1 (18.7) beats/min seen 10 minutes after dosing for fluticasone furoate/vilanterol 200/25 mcg and fluticasone furoate/vilanterol 800/100 mcg, respectively. Hypothalamic-Pituitary-Adrenal Axis Effects Healthy Subjects: Inhaled fluticasone furoate at repeat doses up to 400 mcg was not associated with statistically significant decreases in serum or urinary cortisol in healthy subjects.
Decreases in serum and urine cortisol levels were observed at fluticasone furoate exposures several-fold higher than exposures observed at the therapeutic dose. Patients with Chronic Obstructive Pulmonary Disease: In a trial with patients with CO…
🧬 Mechanism of Action ▾
12.1Mechanism of Action BREO ELLIPTA BREO ELLIPTA contains both fluticasone furoate and vilanterol. The mechanisms of action described below for the individual components apply to BREO ELLIPTA. These drugs represent 2 different classes of medications (an ICS and a LABA), each having different effects on clinical and physiological indices.
Fluticasone Furoate Fluticasone furoate is a synthetic trifluorinated corticosteroid with anti-inflammatory activity. Fluticasone furoate has been shown in vitro to exhibit a binding affinity for the human glucocorticoid receptor that is approximately 29.9 times that of dexamethasone and 1.7 times that of fluticasone propionate. The clinical relevance of these findings is unknown.
The precise mechanism through which fluticasone furoate affects COPD and asthma symptoms is not known. Inflammation is an important component in the pathogenesis of COPD and asthma. Corticosteroids have been shown to have a wide range of actions on multiple cell types (e.g., mast cells, eosinophils, neutrophils, macrophages, lymphocytes) and mediators (e.g., histamine, eicosanoids, leukotrienes, cytokines) involved in inflammation.
Specific effects of fluticasone furoate demonstrated in in vitro and in vivo models included activation of the glucocorticoid response element, inhibition of pro-inflammatory transcription factors such as NFkB, and inhibition of antigen-induced lung eosinophilia in sensitized rats. These anti-inflammatory actions of corticosteroids may contribute to their efficacy. Vilanterol Vilanterol is a LABA.
In vitro tests have shown the functional selectivity of vilanterol was similar to salmeterol. The clinical relevance of this in vitro finding is unknown. Although beta 2 -receptors are the predominant adrenergic receptors in bronchial smooth muscle and beta 1 -receptors are the predominant receptors in the heart, there are also beta 2 -receptors in the human heart comprising 10% to 50% of the total beta-adrenergic receptors.
The precise function of these receptors has not been established, but they raise the possibility that even highly selective beta 2 -agonists may have cardiac effects. The pharmacologic effects of beta 2 -adrenergic agonist drugs, including vilanterol, are at least in part attributable to stimulation of intracellular adenyl cyclase, the enzyme that catalyzes the conversion of adenosine triphosphate (ATP) to cyclic-3′,5′-adenosine monophosphate (cyclic AMP). Increased cyclic AMP levels cause relaxation of bronchial smooth muscle and inhibition of release of mediators of immediate hypersensitivity from cells, especially from mast cells.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING BREO ELLIPTA is supplied as a disposable light grey and pale blue plastic inhaler containing 2 foil strips, each with 30 blisters (or 14 blisters for the institutional pack). One strip contains fluticasone furoate (50, 100 or 200 mcg per blister), and the other strip contains vilanterol (25 mcg per blister). A blister from each strip is used to create 1 dose.
The inhaler is packaged within a moisture-protective foil tray with a desiccant and a peelable lid in the following packs: NDC 0173-0916-10 BREO ELLIPTA 50/25 mcg 30 inhalations (60 blisters) NDC 0173-0859-10 BREO ELLIPTA 100/25 mcg 30 inhalations (60 blisters) NDC 0173-0859-14 BREO ELLIPTA 100/25 mcg 14 inhalations (28 blisters), institutional pack NDC 0173-0882-10 BREO ELLIPTA 200/25 mcg 30 inhalations (60 blisters) NDC 0173-0882-14 BREO ELLIPTA 200/25 mcg 14 inhalations (28 blisters), institutional pack Store at room temperature between 68°F and 77°F (20°C and 25°C); excursions permitted from 59°F to 86°F (15°C to 30°C) [See USP Controlled Room Temperature].
Store in a dry place away from direct heat or sunlight. Keep out of reach of children. BREO ELLIPTA should be stored inside the unopened moisture-protective foil tray and only removed from the tray immediately before initial use.
Discard BREO ELLIPTA 6 weeks after opening the foil tray or when the counter reads “0” (after all blisters have been used), whichever comes first. The inhaler is not reusable. Do not attempt to take the inhaler apart.
📋 Description ▾
11 DESCRIPTION BREO ELLIPTA is an inhalation powder drug product for delivery of a combination of fluticasone furoate (an ICS) and vilanterol (a LABA) to patients by oral inhalation. Fluticasone furoate, a synthetic trifluorinated corticosteroid, has the chemical name (6α,11β,16α,17α)-6,9-difluoro-17-{[(fluoro-methyl)thio]carbonyl}-11-hydroxy-16-methyl-3-oxoandrosta-1,4-dien-17-yl 2-furancarboxylate and the following chemical structure: Fluticasone furoate is a white powder with a molecular weight of 538.6, and the empirical formula is C 27 H 29 F 3 O 6 S.
It is practically insoluble in water. Vilanterol trifenatate has the chemical name triphenylacetic acid-4-{(1 R )-2-[(6-{2-[2,6-dicholorobenzyl)oxy]ethoxy}hexyl)amino]-1-hydroxyethyl}-2-(hydroxymethyl)phenol (1:1) and the following chemical structure: Vilanterol trifenatate is a white powder with a molecular weight of 774.8, and the empirical formula is C 24 H 33 Cl 2 NO 5 •C 20 H 16 O 2 . It is practically insoluble in water.
BREO ELLIPTA is a light grey and pale blue plastic inhaler containing 2 foil blister strips. Each blister on one strip contains a white powder blend of micronized fluticasone furoate (50, 100, or 200 mcg) and lactose monohydrate (12.5, 12.4 or 12.3 mg, respectively), and each blister on the other strip contains a white powder blend of micronized vilanterol trifenatate (40 mcg equivalent to 25 mcg of vilanterol), magnesium stearate (125 mcg), and lactose monohydrate (12.34 mg). The lactose monohydrate contains milk proteins.
After the inhaler is activated, the powder within both blisters is exposed and ready for dispersion into the airstream created by the patient inhaling through the mouthpiece. Under standardized in vitro test conditions, BREO ELLIPTA delivers 46, 92 or 184 mcg of fluticasone furoate and 22 mcg of vilanterol per dose when tested at a flow rate of 60 L/min for 4 seconds. In adult patients with obstructive lung disease and severely compromised lung function (COPD with FEV 1 /FVC <70% and FEV 1 <30% predicted or FEV 1 <50% predicted plus chronic respiratory failure), mean peak inspiratory flow through the ELLIPTA inhaler was
66.5L/min (range: 43.5 to
81.0L/min). In adult patients with severe asthma, mean peak inspiratory flow through the ELLIPTA inhaler was
96.6L/min (range: 72.4 to 124.6 L/min). In pediatric patients with asthma aged 5 to 11 years, mean peak inspiratory flow through the ELLIPTA inhaler was
60.6L/min (range: 36.3 to
82.5L/min). The actual amount of drug delivered to the lung will depend on patient factors, such as inspiratory flow profile. fluticasone furoate chemical structure vilanterol trifenatate chemical structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use). Serious Asthma-Related Events Inform patients with asthma that LABA when used alone increases the risk of asthma-related hospitalization or asthma-related death. Available data show that when ICS and LABA are used together, such as with BREO ELLIPTA, there is not a significant increase in the risk of these events. [See Warnings and Precautions ( 5.1 ).] Not for Acute Symptoms Inform patients that BREO ELLIPTA is not meant to relieve acute symptoms of COPD or asthma and extra doses should not be used for that purpose.
Advise patients to treat acute symptoms with an inhaled, short-acting beta 2 -agonist such as albuterol. Provide patients with such medication and instruct them in how it should be used. Instruct patients to seek medical attention immediately if they experience any of the following: • Decreasing effectiveness of inhaled, short-acting beta 2 -agonists • Need for more inhalations than usual of inhaled, short-acting beta 2 -agonists • Significant decrease in lung function as outlined by the physician Tell patients they should not stop therapy with BREO ELLIPTA without physician/provider guidance since symptoms may recur after discontinuation. [See Warnings and Precautions ( 5.2 ).] Do Not Use Additional Long-Acting Beta 2 -Agonists Instruct patients not to use other LABA for COPD and asthma. [See Warnings and Precautions ( 5.3 ).] Oropharyngeal Candidiasis Inform patients that localized infections with Candida albicans occurred in the mouth and pharynx in some patients.
If oropharyngeal candidiasis develops, treat it with appropriate local or systemic (i.e., oral) antifungal therapy while still continuing therapy with BREO ELLIPTA, but at times therapy with BREO ELLIPTA may need to be temporarily interrupted under close medical supervision. Advise patients to rinse the mouth with water without swallowing after inhalation to help reduce the risk of thrush. [See Warnings and Precautions ( 5.4 ).] Pneumonia Patients with COPD have a higher risk of pneumonia; instruct them to contact their healthcare providers if they develop symptoms of pneumonia. [See Warnings and Precautions ( 5.5 ).] Immunosuppression and Risk of Infections Warn patients who are on immunosuppressant doses of corticosteroids to avoid exposure to chickenpox or measles and, if exposed, to consult their physicians without delay.
Inform patients of potential worsening of existing tuberculosis; fungal, bacterial, viral, or parasitic infections; or ocular herpes simplex. [See Warnings and Precautions ( 5.6 ).] Hypercorticism and Adrenal Suppression Advise patients that BREO ELLIPTA may cause systemic corticosteroid effects of hypercorticism and adrenal suppression. Additionally, inform patients that deaths due to adrenal insufficiency have occurred during and after transfer from systemic corticosteroids. Patients should taper slowly from systemic corticosteroids if transferring to BREO ELLIPTA. [See Warnings and Precautions ( 5.8 ).] Paradoxical Bronchospasm As with other inhaled medicines, BREO ELLIPTA can cause paradoxical bronchospasm.
If paradoxical bronchospasm occurs, instruct patients to discontinue BREO ELLIPTA and contact their healthcare provider right away. [See Warnings and Precautions ( 5.10 ).] Hypersensitivity Reactions, including Anaphylaxis Advise patients that hypersensitivity reactions (e.g., anaphylaxis, angioedema, rash, urticaria) may occur after administration of BREO ELLIPTA. Instruct patients to discontinue BREO ELLIPTA if such reactions occur. There have been reports of anaphylactic reactions in patients with severe milk protein allergy after inhalation of other powder medications containing lactose; therefore, patients with severe milk protein allergy should not use BREO ELLIPTA. [See Warnings and Precautions ( 5.11 ).] Reduction in Bone Mineral Density Advise patients who are at an increas…