
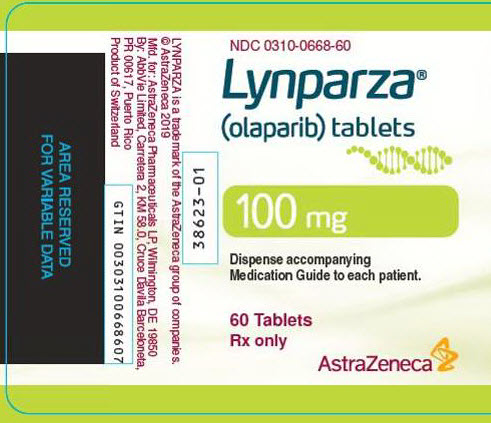
Lynparza olaparib 100 mg Tablet, Film Coated, 60-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Poly(ADP-Ribose) Polymerase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Olaparib (brand name Lynparza) is a targeted cancer medicine called a PARP inhibitor. It's designed for cancers in adults that carry certain DNA-repair gene mutations — most common...
- What exactly is olaparib and why did my doctor prescribe it for me?
- You take Lynparza tablets twice a day, and you can take them with or without food — whichever is easier for you. Swallow them whole; don't crush, chew, or break them. If you miss a...
- How do I take the tablets and what should I do if I miss a dose?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Olaparib — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII D9C330MD8B
Copovidone is a synthetic polymer made by combining two types of plastic-like molecules. It acts as a binder and film-former to help hold tablet ingredients together and improve how the medicine dissolves in your body.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII B697894SGQ
Polyethylene glycol 400 is a clear, thick liquid made from petroleum-derived polymers. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7CV7WJK4UI
Sodium stearyl fumarate is a synthetic compound made from stearyl alcohol and fumaric acid. It acts as a lubricant and glidant in tablets and capsules, helping ingredients flow smoothly during manufacturing and preventing sticking.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $142.14 | $8,528.35 / 60 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lynparza 100 mg 00310-0569-12 | AstraZeneca | 120 tablets | — | — | FDA listed | — |
| Lynparza 100 mgthis 00310-0668-95 | AstraZeneca | 60 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8143241 ↗ | Method of use | U-2482 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-2480 | Aug 12, 2027 |
| US 8859562 ↗ | Method of use | U-2101 | Aug 4, 2031 |
| US 8859562 ↗ | Method of use | U-2482 | Aug 4, 2031 |
| US 8143241 ↗ | Method of use | U-2480 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-2482 | Aug 12, 2027 |
| US 8859562 ↗ | Method of use | U-2101 | Aug 4, 2031 |
| US 8859562 ↗ | Method of use | U-2483 | Aug 4, 2031 |
| US 8859562 ↗ | Method of use | U-2482 | Aug 4, 2031 |
| US 8143241 ↗ | Method of use | U-2716 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-2716 | Aug 12, 2027 |
| US 8859562 ↗ | Method of use | U-2716 | Aug 4, 2031 |
| US 8859562 ↗ | Method of use | U-2716 | Aug 4, 2031 |
| US 8143241 ↗ | Method of use | U-2483 | Aug 12, 2027 |
| US 8859562 ↗ | Method of use | U-2480 | Aug 4, 2031 |
| US 8859562 ↗ | Method of use | U-2483 | Aug 4, 2031 |
| US 8143241 ↗ | Method of use | U-2483 | Aug 12, 2027 |
| US 8859562 ↗ | Method of use | U-3631 | Aug 4, 2031 |
| US 8143241 ↗ | Method of use | U-3631 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-3631 | Aug 12, 2027 |
| US 8859562 ↗ | Method of use | U-3631 | Aug 4, 2031 |
| US 8071579 ↗ | Method of use | U-3631 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-3631 | Aug 12, 2027 |
| US 8859562 ↗ | Method of use | U-2103 | Aug 4, 2031 |
| US 8859562 ↗ | Method of use | U-2833 | Aug 4, 2031 |
| US 8859562 ↗ | Method of use | U-2103 | Aug 4, 2031 |
| US 8859562 ↗ | Method of use | U-2833 | Aug 4, 2031 |
| US 8071579 ↗ | Method of use | U-2716 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-2483 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-2482 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-2482 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-2483 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-2716 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-2824 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-2823 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-2821 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-2819 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-2820 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-2822 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-2824 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-2820 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-2821 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-2823 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-2822 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-2819 | Aug 12, 2027 |
| US 8859562 ↗ | Method of use | U-2822 | Aug 4, 2031 |
| US 8859562 ↗ | Method of use | U-2821 | Aug 4, 2031 |
| US 8859562 ↗ | Method of use | U-2823 | Aug 4, 2031 |
| US 8859562 ↗ | Method of use | U-2824 | Aug 4, 2031 |
| US 8859562 ↗ | Method of use | U-2820 | Aug 4, 2031 |
| US 8859562 ↗ | Method of use | U-2819 | Aug 4, 2031 |
| US 8859562 ↗ | Method of use | U-2822 | Aug 4, 2031 |
| US 8859562 ↗ | Method of use | U-2820 | Aug 4, 2031 |
| US 8859562 ↗ | Method of use | U-2823 | Aug 4, 2031 |
| US 8859562 ↗ | Method of use | U-2824 | Aug 4, 2031 |
| US 8859562 ↗ | Method of use | U-2819 | Aug 4, 2031 |
| US 8859562 ↗ | Method of use | U-2821 | Aug 4, 2031 |
| US 11970530 ↗ | Method of use | U-3929 | Oct 25, 2041 |
| US 11970530 ↗ | Method of use | U-3929 | Oct 25, 2041 |
| US 11970530 ↗ | Method of use | U-3930 | Oct 25, 2041 |
| US 11970530 ↗ | Method of use | U-3930 | Oct 25, 2041 |
| US 11970530 ↗ | Method of use | U-3931 | Oct 25, 2041 |
| US 11970530 ↗ | Method of use | U-3931 | Oct 25, 2041 |
| US 8071579 ↗ | Method of use | U-3695 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-3695 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-3695 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-3695 | Aug 12, 2027 |
| US 8859562 ↗ | Method of use | U-3695 | Aug 4, 2031 |
| US 8859562 ↗ | Method of use | U-3695 | Aug 4, 2031 |
| US 8071579 ↗ | Method of use | U-2820 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-2824 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-2833 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-2823 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-2832 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-2480 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-2821 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-2819 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-2822 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-2832 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-2823 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-2819 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-2833 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-2821 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-2480 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-2824 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-2820 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-2832 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-2833 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-2833 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-2832 | Aug 12, 2027 |
| US 8859562 ↗ | Method of use | U-2832 | Aug 4, 2031 |
| US 8859562 ↗ | Method of use | U-2832 | Aug 4, 2031 |
| US 8143241 ↗ | Method of use | U-3333 | Aug 12, 2027 |
| US 8859562 ↗ | Method of use | U-3333 | Aug 4, 2031 |
| US 8071579 ↗ | Method of use | U-3333 | Aug 12, 2027 |
| US 8071579 ↗ | Method of use | U-3333 | Aug 12, 2027 |
| US 8143241 ↗ | Method of use | U-3333 | Aug 12, 2027 |
| US 8859562 ↗ | Method of use | U-3333 | Aug 4, 2031 |
| US 8071579 ↗ | Method of use | U-2822 | Aug 12, 2027 |
| US 8859562 ↗ | Method of use | U-2480 | Aug 4, 2031 |
| US 11975001 ↗ | Drug product | — | Oct 7, 2029 |
| US 11633396 ↗ | Drug product | — | Oct 7, 2029 |
| US 8475842 ↗ | Drug product | — | Dec 31, 2029 |
| US 12048695 ↗ | Drug product | — | Oct 7, 2029 |
| US 12178816 ↗ | Drug product | — | Oct 7, 2029 |
| US 11633396 ↗ | Drug product | — | Oct 7, 2029 |
| US 7449464 ↗ | Drug substance | — | Sep 8, 2027 |
| US 12178816 ↗ | Drug product | — | Oct 7, 2029 |
| US 12144810 ↗ | Drug product | — | Oct 7, 2029 |
| US 7449464 ↗ | Drug substance | — | Sep 8, 2027 |
| US 12048695 ↗ | Drug product | — | Oct 7, 2029 |
| US 12144810 ↗ | Drug product | — | Oct 7, 2029 |
| US 11975001 ↗ | Drug product | — | Oct 7, 2029 |
| US 8475842 ↗ | Drug product | — | Dec 31, 2029 |
| Code | What it grants | Expires |
|---|---|---|
| I-914 | New indication (3-year) | May 31, 2026 |
| ODE-283 | Orphan Drug Exclusivity (7-year) | Dec 27, 2026 |
| ODE-306 | Orphan Drug Exclusivity (7-year) | May 8, 2027 |
| I-914 | New indication (3-year) | May 31, 2026 |
| ODE-283 | Orphan Drug Exclusivity (7-year) | Dec 27, 2026 |
| ODE-306 | Orphan Drug Exclusivity (7-year) | May 8, 2027 |
Is there a generic version of LYNPARZA 100 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00310-0668-12 | 120 TABLET, FILM COATED in 1 BOTTLE (0310-0668-12) | 2017-08-17 | Active |
| 00310-0668-60 | 60 TABLET, FILM COATED in 1 BOTTLE (0310-0668-60) | 2017-08-17 | Active |
| 00310-0668-95 You're viewing this | 60 TABLET, FILM COATED in 1 BOTTLE (0310-0668-95) | 2022-09-01 | Active |
This pack shows little to no recent Medicaid volume — the 120 tablets pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 00310-0668-95?
What is the difference between NDC 00310-0668-95 and NDC 00310-0668-60?
What NDC number is used to bill for this package of Lynparza olaparib 100 mg Tablet, Film Coated?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Lynparza is a poly (ADP-ribose) polymerase (PARP) inhibitor indicated: Ovarian cancer • for the maintenance treatment of adult patients with deleterious or suspected deleterious germline or somatic BRCA -mutated advanced epithelial ovarian, fallopian tube or primary peritoneal cancer who are in complete or partial response to first-line platinum-based chemotherapy. Select patients for therapy based on an FDA-approved companion diagnostic for Lynparza. ( 1.1 , 2.1 ) • in combination with bevacizumab for the maintenance treatment of adult patients with advanced epithelial ovarian, fallopian tube or primary peritoneal cancer who are in complete or partial response to first-line platinum-based chemotherapy and whose cancer is associated with homologous recombination deficiency (HRD)-positive status defined by either: • a deleterious or suspected deleterious BRCA mutation, and/or • genomic instability.
Select patients for therapy based on an FDA-approved companion diagnostic for Lynparza. ( 1.2 , 2.1 ) • for the maintenance treatment of adult patients with deleterious or suspected deleterious germline or somatic BRCA-mutated recurrent epithelial ovarian, fallopian tube or primary peritoneal cancer, who are in complete or partial response to platinum-based chemotherapy. Select patients for therapy based on an FDA-approved companion diagnostic for Lynparza.
( 1.3 , 2.1 ) Breast cancer • for the adjuvant treatment of adult patients with deleterious or suspected deleterious g BRCA m human epidermal growth factor receptor 2 (HER2)-negative high risk early breast cancer who have been treated with neoadjuvant or adjuvant chemotherapy. Select patients for therapy based on an FDA-approved companion diagnostic for Lynparza. ( 1.4 , 2.1 ) • for the treatment of adult patients with deleterious or suspected deleterious gBRCA m, HER2-negative metastatic breast cancer who have been treated with chemotherapy in the neoadjuvant, adjuvant or metastatic setting.
Patients with hormone receptor (HR)-positive breast cancer should have been treated with a prior endocrine therapy or be considered inappropriate for endocrine therapy. Select patients for therapy based on an FDA-approved companion diagnostic for Lynparza. ( 1.5 , 2.1 ) Pancreatic cancer • for the maintenance treatment of adult patients with deleterious or suspected deleterious gBRCA m metastatic pancreatic adenocarcinoma whose disease has not progressed on at least 16 weeks of a first-line platinum-based chemotherapy regimen.
Select patients for therapy based on an FDA-approved companion diagnostic for Lynparza. ( 1.6 , 2.1 ) Prostate cancer • for the treatment of adult patients with deleterious or suspected deleterious germline or somatic homologous recombination repair (HRR) gene-mutated metastatic castration-resistant prostate cancer (mCRPC) who have progressed following prior treatment with enzalutamide or abiraterone. Select patients for therapy based on an FDA-approved companion diagnostic for Lynparza.
( 1.7 , 2.1 ) • in combination with abiraterone and prednisone or prednisolone for the treatment of adult patients with deleterious or suspected deleterious BRCA -mutated ( BRCA m) metastatic castration-resistant prostate cancer (mCRPC). Select patients for therapy based on an FDA-approved companion diagnostic for Lynparza. ( 1.8 , 2.1 )
1.1First-Line Maintenance Treatment of BRCA -mutated Advanced Ovarian Cancer Lynparza is indicated for the maintenance treatment of adult patients with deleterious or suspected deleterious germline or somatic BRCA -mutated advanced epithelial ovarian, fallopian tube or primary peritoneal cancer who are in complete or partial response to first-line platinum-based chemotherapy. Select patients for therapy based on an FDA-approved companion diagnostic for Lynparza [see Dosage and Administration (2.1) ] .
1.2First-line Maintenance Treatment of HRD-positive Advanced Ovarian Cancer in Combination with Bevacizumab Lynparza is indicate…
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Recommended dosage is 300 mg taken orally twice daily with or without food. See Full Prescribing Information for the recommended duration. (2.2) • Patients receiving Lynparza for mCRPC should also receive a gonadotropin-releasing hormone (GnRH) analog concurrently or should have had bilateral orchiectomy. (2.2) • For moderate renal impairment (CLcr 31-50 mL/min), reduce Lynparza dosage to 200 mg orally twice daily. (2.5)
2.1Patient Selection Information on FDA-approved tests for the detection of genetic mutations is available at http://www.fda.gov/companiondiagnostics . Select patients for treatment with Lynparza based on the presence of deleterious or suspected deleterious HRR gene mutations, including BRCA mutations, or genomic instability based on the indication, biomarker, and sample type (Table 1). Table 1 Biomarker Testing for Patient Selection Where testing fails or tissue sample is unavailable/insufficient, or when germline testing is negative, consider using an alternative test, if available.
Indication Biomarker Sample type Tumor Blood Plasma (ctDNA) First-line maintenance treatment of germline or somatic BRCAm advanced ovarian cancer BRCA1 m, BRCA2 m X X First-line maintenance treatment of HRD-positive advanced ovarian cancer in combination with bevacizumab BRCA1 m, BRC A2m and/or genomic instability X Maintenance treatment of germline or somatic BRCA m recurrent ovarian cancer BRCA1 m, BRCA2 m X X Adjuvant treatment of gBRCA m HER2-negative high risk early breast cancer gBRCA1 m , gBRCA2 m X g BRCA m HER2-negative metastatic breast cancer gBRCA1 m, gBRCA2 m X First-line maintenance treatment of germline BRCA -mutated metastatic pancreatic adenocarcinoma gBRCA1 m, gBRCA2 m X Germline or somatic HRR gene-mutated metastatic castration-resistant prostate cancer ATM m, BRCA1 m , BRCA2 m, BARD1 m, BRIP1 m, CDK12 m, CHEK1 m, CHEK2 m, FANCL m, PALB2 m, RAD51B m, RAD51C m, RAD51D m, RAD54L m X g BRCA1 m, g BRCA2 m X ATM m , BRCA1 m, BRCA2 m X BRCA -mutated metastatic castration-resistant prostate cancer in combination with abiraterone and prednisone or prednisolone BRCA1 m, BRCA2 m X X X
2.2Recommended Dosage The recommended dosage of Lynparza is 300 mg taken orally twice daily, with or without food. If a patient misses a dose of Lynparza, instruct patient to take their next dose at its scheduled time. Instruct patients to swallow tablets whole.
Do not chew, crush, dissolve, or divide tablet. First-Line Maintenance Treatment of BRCA -mutated Advanced Ovarian Cancer Continue treatment until disease progression, unacceptable toxicity, or completion of 2 years of treatment. Patients with a complete response (no radiological evidence of disease) at 2 years should stop treatment.
Patients with evidence of disease at 2 years, who in the opinion of the treating healthcare provider can derive further benefit from continuous treatment, can be treated beyond 2 years. First-Line Maintenance Treatment of HRD-positive Advanced Ovarian Cancer in Combination with Bevacizumab Continue Lynparza treatment until disease progression, unacceptable toxicity, or completion of 2 years of treatment. Patients with a complete response (no radiological evidence of disease) at 2 years should stop treatment.
Patients with evidence of disease at 2 years, who in the opinion of the treating healthcare provider can derive further benefit from continuous Lynparza treatment, can be treated beyond 2 years. When used with Lynparza, the recommended dose of bevacizumab is 15 mg/kg every three weeks. Bevacizumab should be given for a total of 15 months including the period given with chemotherapy and given as maintenance.
Refer to the Prescribing Information for bevacizumab when used in combination with Lynparza for more information. Adjuvant Treatment of Germline BRCA -mutated HER2-negative High Risk Early Breast Cancer Continue treatment for a total of 1 year, or until disease recurrence, or unacceptable toxicity, whichever occurs…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: • 150 mg: green to green/grey, oval, bi-convex, film-coated, with debossment ‘OP150’ on one side and plain on the reverse side. • 100 mg: yellow to dark yellow, oval, bi-convex, film-coated, with debossment ‘OP100’ on one side and plain on the reverse side. Tablets: 150 mg, 100 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Myelodysplastic Syndrome/Acute Myeloid Leukemia (MDS/AML): Occurred in approximately 1.2% of patients with various BRCA m, g BRCA m, HRR gene-mutated or HRD-positive cancers exposed to Lynparza and the majority of events had a fatal outcome. Monitor patients for hematological toxicity at baseline and monthly thereafter. Discontinue if MDS/AML is confirmed.
(5.1) • Pneumonitis: Occurred in 1.0% of patients exposed to Lynparza, and some cases were fatal. Interrupt treatment if pneumonitis is suspected. Discontinue if pneumonitis is confirmed.
(5.2) • Venous thromboembolism (VTE), including severe or fatal pulmonary embolism (PE), occurred in patients treated with Lynparza. VTE occurred in 8% of patients with mCRPC. Monitor patients for signs and symptoms of VTE and PE and treat as medically appropriate.
( 5.3 ) • Hepatotoxicity, Including Drug-induced liver injury (DILI): Occurred in patients treated with Lynparza. If DILI is suspected, interrupt Lynparza. If DILI is confirmed, discontinue treatment.
( 5.4 ) • Embryo-Fetal Toxicity: Can cause fetal harm. Advise of the potential risk to a fetus and to use effective contraception. ( 5.5 , 8.1 , 8.3 )
5.1Myelodysplastic Syndrome/Acute Myeloid Leukemia Myelodysplastic syndrome (MDS)/Acute Myeloid Leukemia (AML) has occurred in patients treated with Lynparza and some cases were fatal. In clinical studies, among 2219 patients with various BRCA m, g BRCA m, HRR gene-mutated or HRD-positive cancers who received Lynparza as a single agent or as part of combination regimen, consistent with approved indications, the cumulative incidence of MDS/AML was approximately 1.2% (26/2219) [see Adverse Reactions (6.1) ]. Of these, 54% (14/26) had a fatal outcome.
The median duration of therapy with Lynparza in patients who developed MDS/AML was approximately 2 years (range: < 6 months to > 4 years). All of these patients had received previous chemotherapy with platinum agents and/or other DNA damaging agents including radiotherapy. In SOLO1, patients with newly diagnosed advanced BRCA m ovarian cancer, the incidence of MDS/AML was 1.9% (5/260) in patients who received Lynparza and 0.8% (1/130) in patients who received placebo based on an updated analysis.
In PAOLA-1, of patients with newly diagnosed advanced ovarian cancer with HRD-positive status, the incidence of MDS/AML was 1.6% (4/255) in patients who received Lynparza and 2.3% (3/131) in the control arm. In SOLO2, patients with BRCA m platinum-sensitive relapsed ovarian cancer, the incidence of MDS/AML was 8% (15/195) in patients who received Lynparza and 4% (4/99) in patients who received placebo. The duration of Lynparza treatment prior to the diagnosis of MDS/AML ranged from 0.6 years to 4.5 years.
Do not start Lynparza until patients have recovered from hematological toxicity caused by previous chemotherapy (≤ Grade 1). Monitor complete blood count for cytopenia at baseline and monthly thereafter for clinically significant changes during treatment. For prolonged hematological toxicities, interrupt Lynparza and monitor blood counts weekly until recovery.
If the levels have not recovered to Grade 1 or less after 4 weeks, refer the patient to a hematologist for further investigations, including bone marrow analysis and blood sample for cytogenetics. If MDS/AML is confirmed, discontinue Lynparza.
5.2Pneumonitis Pneumonitis, including severe and fatal cases, has occurred in patients treated with Lynparza. In clinical studies, among patients who received Lynparza as a single agent or as part of a combination regimen [see Error! Hyperlink reference not valid. ] , the incidence of pneumonitis, including fatal cases, was 1.0% (29/2851).
If patients present with new or worsening respiratory symptoms such as dyspnea, cough and fever, or a radiological abnormality occurs, interrupt Lynparza treatment and promptly assess the source of the symptoms. If pneumonitis is confirmed, discontinue Lynparza treatment and treat the p…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed elsewhere in the labeling: • Myelodysplastic Syndrome/Acute Myeloid Leukemia [see Warnings and Precautions (5.1) ] • Pneumonitis [see Warnings and Precautions (5.2) ] • Venous Thromboembolism [see Warnings and Precautions (5.3) ] • Hepatotoxicity, Including Drug-Induced Liver Injury [see Warnings and Precautions (5.4) ] Most common adverse reactions (≥10%): • as a single agent were nausea, fatigue (including asthenia), anemia, vomiting, diarrhea, decreased appetite, headache, dysgeusia, cough, neutropenia, dyspnea, dizziness, dyspepsia, leukopenia, and thrombocytopenia.
(6.1) • in combination with bevacizumab were nausea, fatigue (including asthenia), anemia, lymphopenia, vomiting, diarrhea, neutropenia, leukopenia, urinary tract infection, and headache. ( 6.1 ) • in combination with abiraterone and prednisone or prednisolone were anemia, fatigue, nausea, diarrhea, decreased appetite, lymphopenia, dizziness, and abdominal pain. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact AstraZeneca at 1-800-236-9933 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Unless otherwise specified, the data described in the WARNINGS AND PRECAUTIONS reflect exposure to Lynparza as a single agent or as part of a combination regimen (SOLO-1, SOLO-2, PAOLA-1, OlympiA, OlympiAD, POLO, PROfound, and PROpel) in 2851 patients that were pooled to conduct safety analyses.
Additional data reflect exposure to Lynparza as a single agent in 2901 patients; 2135 patients with exposure to 300 mg twice daily tablet dose including five controlled, randomized, trials (SOLO-1, SOLO-2, OlympiAD, POLO, and PROfound) and to 400 mg twice daily capsule dose in 766 patients in other trials that were pooled to conduct safety analyses. In this pooled single agent safety population, 56% of patients were exposed for 6 months or longer and 28% were exposed for greater than one year in the Lynparza group. In this pooled single agent safety population, the most common adverse reactions in ≥10% of patients were nausea (60%), fatigue (55%), anemia (36%), vomiting (32%), diarrhea (24%), decreased appetite (22%), headache (16%), dysgeusia (15%), cough (15%), neutropenia (14%), dyspnea (14%), dizziness (12%), dyspepsia (12%), leukopenia (11%), and thrombocytopenia (10%).
First-Line Maintenance Treatment of BRCA -mutated Advanced Ovarian Cancer SOLO-1 The safety of Lynparza for the maintenance treatment of patients with BRCA-mutated advanced ovarian cancer following first-line treatment with platinum-based chemotherapy was investigated in SOLO- 1 [see Clinical Studies (14.1) ] . Patients received Lynparza tablets 300 mg orally twice daily (n=260) or placebo (n=130) until disease progression or unacceptable toxicity. The median duration of study treatment was 25 months for patients who received Lynparza and 14 months for patients who received placebo.
Among patients who received Lynparza, dose interruptions due to an adverse reaction of any grade occurred in 52% and dose reductions due to an adverse reaction occurred in 28%. The most frequent adverse reactions leading to dose interruption or reduction of Lynparza were anemia (23%), nausea (14%), and vomiting (10%). Discontinuation due to adverse reactions occurred in 12% of patients receiving Lynparza.
The most frequent adverse reactions that led to discontinuation of Lynparza were fatigue (3.1%), anemia (2.3%), and nausea (2.3%). Tables 2 and 3 summarize adverse reactions and laboratory abnormalities in SOLO-1. Table 2 Adverse Reactions Graded according to the National Cancer Institute Common Terminology Criteria for Adverse Events (NCI CTCAE), version 4.0. in SOLO-1 (≥10%…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Strong or moderate CYP3A inhibitors: Avoid concomitant use. If concomitant use cannot be avoided, reduce Lynparza dosage. ( 2.4 , 7.2 , 12.3 ) • Strong or moderate CYP3A inducers: Avoid concomitant use. ( 7.2 , 12.3 )
7.1Use with Anticancer Agents Clinical studies of Lynparza with other myelosuppressive anticancer agents, including DNA damaging agents, indicate a potentiation and prolongation of myelosuppressive toxicity.
7.2Effect of Other Drugs on Lynparza Strong and Moderate CYP3A Inhibitors Coadministration of CYP3A inhibitors can increase olaparib concentrations, which may increase the risk for adverse reactions [see Clinical Pharmacology (12.3) ] . Avoid coadministration of strong or moderate CYP3A inhibitors. If the strong or moderate inhibitor must be coadministered, reduce the dose of Lynparza [see Dosage and Administration (2.4) ].
Strong and Moderate CYP3A Inducers Concomitant use with a strong or moderate CYP3A inducer decreased olaparib exposure, which may reduce Lynparza efficacy [see Clinical Pharmacology (12.3) ] . Avoid coadministration of strong or moderate CYP3A inducers.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise women not to breastfeed. (8.2)
8.1Pregnancy Risk Summary Based on findings in animals and its mechanism of action [see Clinical Pharmacology (12.1) ] , Lynparza can cause fetal harm when administered to a pregnant woman. There are no available data on Lynparza use in pregnant women to inform the drug-associated risk. In an animal reproduction study, the administration of olaparib to pregnant rats during the period of organogenesis caused teratogenicity and embryo-fetal toxicity at exposures below those in patients receiving the recommended human dose of 300 mg twice daily (see Data ).
Apprise pregnant women of the potential hazard to the fetus and the potential risk for loss of the pregnancy. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. The estimated background risk in the U.S. general population of major birth defects is 2-4%; and the risk for spontaneous abortion is approximately 15-20% in clinically recognized pregnancies.
Data Animal Data In a fertility and early embryonic development study in female rats, olaparib was administered orally for 14 days before mating through to Day 6 of pregnancy, which resulted in increased post-implantation loss at a dose level of 15 mg/kg/day (with maternal systemic exposures approximately 7% of the human exposure (AUC 0-24h ) at the recommended dose). In an embryo-fetal development study, pregnant rats received oral doses of 0.05 and 0.5 mg/kg/day olaparib during the period of organogenesis. A dose of 0.5 mg/kg/day (with maternal systemic exposures approximately 0.18% of human exposure (AUC 0-24h ) at the recommended dose) caused embryo-fetal toxicities including increased post-implantation loss and major malformations of the eyes (anophthalmia, microphthalmia), vertebrae/ribs (extra rib or ossification center; fused or absent neural arches, ribs, and sternebrae), skull (fused exoccipital), and diaphragm (hernia).
Additional abnormalities or variants included incomplete or absent ossification (vertebrae/sternebrae, ribs, limbs) and other findings in the vertebrae/sternebrae, pelvic girdle, lung, thymus, liver, ureter, and umbilical artery. Some findings noted above in the eyes, ribs, and ureter were observed at a dose of 0.05 mg/kg/day olaparib at lower incidence.
8.2Lactation Risk Summary No data are available regarding the presence of olaparib in human milk, or on its effects on the breastfed infant or on milk production. Because of the potential for serious adverse reactions in the breastfed infants from Lynparza, advise a lactating woman not to breastfeed during treatment with Lynparza and for one month after receiving the last dose.
8.3Females and Males of Reproductive Potential Lynparza can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1) ] . Pregnancy Testing Verify pregnancy status in females of reproductive potential prior to initiating treatment with Lynparza. Contraception Females Advise females of reproductive potential to use effective contraception during treatment with Lynparza and for 6 months following the last dose.
Males Based on findings in genetic toxicity and animal reproduction studies, advise male patients with female partners of reproductive potential or who are pregnant to use effective contraception during treatment and for 3 months following the last dose of Lynparza. Advise male patients not to donate sperm during therapy and for 3 months following the last dose of Lynparza [see Use in Specific Populations (8.1) and Nonclinical Toxicology (13.1) ] .
8.4Pediatric Use Safety and effectiveness of Lynparza have not been established in pediatric patients.
8.5Geriatric Use Of the 2901 patients with advanced solid tumors who received Lynparza as a single agent, 680 (23%) patients were aged ≥65 years, and this included 206 (7%) patients who were aged ≥75 years. Thirteen (0.4%) patients were aged ≥85 years. O…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings in animals and its mechanism of action [see Clinical Pharmacology (12.1) ] , Lynparza can cause fetal harm when administered to a pregnant woman. There are no available data on Lynparza use in pregnant women to inform the drug-associated risk. In an animal reproduction study, the administration of olaparib to pregnant rats during the period of organogenesis caused teratogenicity and embryo-fetal toxicity at exposures below those in patients receiving the recommended human dose of 300 mg twice daily (see Data ).
Apprise pregnant women of the potential hazard to the fetus and the potential risk for loss of the pregnancy. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. The estimated background risk in the U.S. general population of major birth defects is 2-4%; and the risk for spontaneous abortion is approximately 15-20% in clinically recognized pregnancies.
Data Animal Data In a fertility and early embryonic development study in female rats, olaparib was administered orally for 14 days before mating through to Day 6 of pregnancy, which resulted in increased post-implantation loss at a dose level of 15 mg/kg/day (with maternal systemic exposures approximately 7% of the human exposure (AUC 0-24h ) at the recommended dose). In an embryo-fetal development study, pregnant rats received oral doses of 0.05 and 0.5 mg/kg/day olaparib during the period of organogenesis. A dose of 0.5 mg/kg/day (with maternal systemic exposures approximately 0.18% of human exposure (AUC 0-24h ) at the recommended dose) caused embryo-fetal toxicities including increased post-implantation loss and major malformations of the eyes (anophthalmia, microphthalmia), vertebrae/ribs (extra rib or ossification center; fused or absent neural arches, ribs, and sternebrae), skull (fused exoccipital), and diaphragm (hernia).
Additional abnormalities or variants included incomplete or absent ossification (vertebrae/sternebrae, ribs, limbs) and other findings in the vertebrae/sternebrae, pelvic girdle, lung, thymus, liver, ureter, and umbilical artery. Some findings noted above in the eyes, ribs, and ureter were observed at a dose of 0.05 mg/kg/day olaparib at lower incidence.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of Lynparza have not been established in pediatric patients.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 2901 patients with advanced solid tumors who received Lynparza as a single agent, 680 (23%) patients were aged ≥65 years, and this included 206 (7%) patients who were aged ≥75 years. Thirteen (0.4%) patients were aged ≥85 years. Of the 535 patients with advanced solid tumors who received Lynparza tablets 300 mg orally twice daily in combination with bevacizumab (PAOLA-1), 204 (38%) patients were aged ≥65 years, and this included 31 (6%) patients who were aged ≥75 years.
Of the 398 patients with advanced solid tumors who received Lynparza tablets 300 mg orally twice daily in combination with abiraterone and prednisone or prednisolone (PROpel), 268 (67%) patients were aged ≥65 years, and this included 95 (24%) patients who were aged ≥75 years. No overall differences in the safety or effectiveness of Lynparza were observed between these patients and younger patients.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Olaparib is an inhibitor of poly (ADP-ribose) polymerase (PARP) enzymes, including PARP1, PARP2, and PARP3. PARP enzymes are involved in normal cellular functions, such as DNA transcription and DNA repair. Olaparib has been shown to inhibit growth of select tumor cell lines in vitro and decrease tumor growth in mouse xenograft models of human cancer, both as monotherapy or following platinum-based chemotherapy.
Increased cytotoxicity and anti-tumor activity following treatment with olaparib were noted in cell lines and mouse tumor models with deficiencies in BRCA1/2 , ATM , or other genes involved in the homologous recombination repair (HRR) of DNA damage and correlated with platinum response. In vitro studies have shown that olaparib-induced cytotoxicity may involve inhibition of PARP enzymatic activity and increased formation of PARP-DNA complexes, resulting in DNA damage and cancer cell death. In prostate cancer models, PARP1 has been shown to contribute to androgen receptor (AR) activity regulation; the combination of olaparib and AR inhibition resulted in cytotoxicity in vitro and anti-tumor activity in mouse xenograft models.
12.2Pharmacodynamics Cardiac Electrophysiology The effect of olaparib on cardiac repolarization was assessed in 119 patients following a single dose of 300 mg and in 109 patients following multiple dosing of 300 mg twice daily. No clinically relevant effect of olaparib on QT interval was observed.
12.3Pharmacokinetics The area under the curve (AUC) of olaparib increases approximately proportionally following administration of single doses of 25 mg to 450 mg (0.08 to 1.5 times the recommended dose) and maximal concentrations (C max ) increased slightly less than proportionally for the same dose range. Olaparib showed time-dependent pharmacokinetics and an AUC mean accumulation ratio of 1.8 is observed at steady state following a dose of 300 mg twice daily. The mean (CV%) olaparib C max is 5.4 μg/mL (32%) and AUC is 39.2 μg*h/mL (44%) following a single 300 mg dose.
The mean steady state olaparib C max and AUC is 7.6 μg/mL (35%) and 49.2 μg*h/mL (44%), following a dose of 300 mg twice daily. Absorption Following oral administration of olaparib, the median time to peak plasma concentration is 1.5 hours. Effect of Food Co-administration of a high fat and high calorie meal (800-1000 kcal, 50% of the calorie content made up from fat) with olaparib slowed the rate (t max delayed by 2.5 hours) of absorption, but did not significantly alter the extent of olaparib absorption (mean AUC increased by approximately 8%).
Distribution The mean (± standard deviation) apparent volume of distribution of olaparib is 158 ± 136 L following a single 300 mg dose of Lynparza. The protein binding of olaparib is approximately 82% in vitro. Elimination The mean (± standard deviation) terminal plasma half-life of olaparib is 14.9 ± 8.2 hours and the apparent plasma clearance is 7.4 ±
3.9L/h following a single 300 mg dose of Lynparza. Metabolism Olaparib is metabolized by cytochrome P450 (CYP) 3A in vitro. Following an oral dose of radiolabeled olaparib to female patients, unchanged olaparib accounted for 70% of the circulating radioactivity in plasma.
It was extensively metabolized with unchanged drug accounting for 15% and 6% of radioactivity in urine and feces, respectively. The majority of the metabolism is attributable to oxidation reactions with a number of the components produced undergoing subsequent glucuronide or sulfate conjugation. Excretion Following a single dose of radiolabeled olaparib, 86% of the dosed radioactivity was recovered within a 7-day collection period, 44% via the urine and 42% via the feces.
The majority of the material was excreted as metabolites. Specific Populations Patients with Renal Impairment In a renal impairment trial, the mean AUC increased by 24% and C max by 15%, when olaparib was dosed in patients with mild renal impairment (CLcr=51-80…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Olaparib is an inhibitor of poly (ADP-ribose) polymerase (PARP) enzymes, including PARP1, PARP2, and PARP3. PARP enzymes are involved in normal cellular functions, such as DNA transcription and DNA repair. Olaparib has been shown to inhibit growth of select tumor cell lines in vitro and decrease tumor growth in mouse xenograft models of human cancer, both as monotherapy or following platinum-based chemotherapy.
Increased cytotoxicity and anti-tumor activity following treatment with olaparib were noted in cell lines and mouse tumor models with deficiencies in BRCA1/2 , ATM , or other genes involved in the homologous recombination repair (HRR) of DNA damage and correlated with platinum response. In vitro studies have shown that olaparib-induced cytotoxicity may involve inhibition of PARP enzymatic activity and increased formation of PARP-DNA complexes, resulting in DNA damage and cancer cell death. In prostate cancer models, PARP1 has been shown to contribute to androgen receptor (AR) activity regulation; the combination of olaparib and AR inhibition resulted in cytotoxicity in vitro and anti-tumor activity in mouse xenograft models.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Lynparza is available as 150 mg and 100 mg tablets. • 150 mg tablets: green to green/grey, oval, bi-convex, film-coated tablet, with debossment ‘OP150’ on one side and plain on the reverse, are available in: ∘ Bottles of 60 tablets (NDC 0310-0679-60) and ∘ Bottles of 120 tablets (NDC 0310-0679-12). • 100 mg tablets: yellow to dark yellow, oval, bi-convex, film-coated tablet, with debossment ‘OP100’ on one side and plain on the reverse, are available in: ∘ Bottles of 60 tablets (NDC 0310-0668-60) and ∘ Bottles of 120 tablets (NDC 0310-0668-12).
Store at 20ºC to 25ºC (68ºF to 77ºF), excursions permitted to 15ºC to 30ºC (59ºF to 86ºF) [see USP Controlled Room Temperature]. Store in original bottle to protect from moisture.
📋 Description ▾
11 DESCRIPTION Olaparib is a poly (ADP-ribose) polymerase (PARP) inhibitor. The chemical name is 4-[(3-{[4-(cyclopropylcarbonyl)piperazin-1-yl]carbonyl}-4-fluorophenyl)methyl]phthalazin-1(2H)-one. The empirical molecular formula for Lynparza is C 24 H 23 FN 4 O 3 and the relative molecular mass is 434.46.
It has the following chemical structure: Olaparib is a crystalline solid, is non-chiral and shows pH-independent low solubility across the physiological pH range. Lynparza (olaparib) tablets for oral use contain 100 mg or 150 mg of olaparib. Inactive ingredients in the tablet core are copovidone, mannitol, colloidal silicon dioxide, and sodium stearyl fumarate.
The tablet coating consists of hypromellose, polyethylene glycol 400, titanium dioxide, ferric oxide yellow, and ferrosoferric oxide (150 mg tablet only). chemical structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). MDS/AML Advise patients to contact their healthcare provider if they experience weakness, feeling tired, fever, weight loss, frequent infections, bruising, bleeding easily, breathlessness, blood in urine or stool, and/or laboratory findings of low blood cell counts, or a need for blood transfusions. This may be a sign of hematological toxicity or a more serious uncommon bone marrow problem called ‘myelodysplastic syndrome’ (MDS) or ‘acute myeloid leukemia’ (AML) which have been reported in patients treated with Lynparza [see Warnings and Precautions (5.1) ] .
Pneumonitis Advise patients to contact their healthcare provider if they experience any new or worsening respiratory symptoms including shortness of breath, fever, cough, or wheezing [see Warnings and Precautions (5.2) ] . Venous Thromboembolism Advise patients to immediately report any signs or symptoms of thromboembolism such as pain or swelling in an extremity, shortness of breath, chest pain, tachypnea, and tachycardia [see Warnings and Precautions (5.3) ] . Hepatotoxicity, Including Drug-Induced Liver Injury Inform patients that liver problems, including drug-induced liver injury and abnormalities in liver tests, may develop during Lynparza treatment.
Advise patients to contact their healthcare provider immediately if they experience abdominal discomfort, dark urine, or jaundice [see Warnings and Precautions (5.4) ] . Embryo-Fetal Toxicity Inform pregnant women of the risk to a fetus and potential loss of the pregnancy. Advise females to inform their healthcare provider of known or suspected pregnancy [see Use in Specific Populations (8.1) ] .
Advise females of reproductive potential to use effective contraception during treatment with Lynparza and for 6 months after the last dose [see Use in Specific Populations (8.3) ] . Advise male patients with female partners of reproductive potential or who are pregnant to use effective contraception during treatment and for 3 months after receiving the last dose of Lynparza. Advise male patients not to donate sperm during therapy and for 3 months following the last dose of Lynparza [see Warnings and Precautions (5.5) and Use in Specific Populations (8.3) ].
Lactation Advise patients not to breastfeed while taking Lynparza and for one month after receiving the last dose [see Use in Specific Populations (8.2) ] . Drug Interactions Advise patients and caregivers to inform their healthcare provider of all concomitant medications, including prescription medicines, over-the-counter drugs, vitamins, and herbal products. Inform patients to avoid grapefruit, grapefruit juice, Seville oranges, and Seville orange juice while taking Lynparza [see Drug Interactions (7.2) ] .
Nausea/Vomiting Advise patients that mild or moderate nausea and/or vomiting is very common in patients receiving Lynparza and that they should contact their healthcare provider who will advise on available antiemetic treatment options [see Adverse Reactions (6.1) ] . Distributed by: AstraZeneca Pharmaceuticals LP Wilmington, DE 19850 © AstraZeneca 2025
💬 Medication Guide ▾
Medication Guide Lynparza ® (Lin-par-zah) (olaparib) tablets What is the most important information I should know about Lynparza? Lynparza may cause serious side effects, including: • Bone marrow problems called Myelodysplastic Syndrome (MDS) or Acute Myeloid Leukemia (AML). Some people who have received previous treatment with chemotherapy, radiotherapy or certain other medicines for their cancer have developed MDS or AML during treatment with Lynparza.
MDS or AML may lead to death. Symptoms of low blood cell counts are common during treatment with Lynparza, but can be a sign of serious bone marrow problems, including MDS or AML. Symptoms may include: ∘ weakness ∘ weight loss ∘ fever ∘ frequent infections ∘ blood in urine or stool ∘ shortness of breath ∘ feeling very tired ∘ bruising or bleeding more easily Your healthcare provider will do blood tests to check your blood cell counts: ∘ before treatment with Lynparza ∘ every month during treatment with Lynparza ∘ weekly if you have low blood cell counts that last a long time. • Lung problems (Pneumonitis).
Lynparza can cause serious lung problems that can lead to death. Tell your healthcare provider if you have any new or worsening symptoms of lung problems, including shortness of breath, fever, cough, or wheezing. Your healthcare provider may do a chest x-ray if you have any of these symptoms. • Blood clots (Venous Thromboembolism, [VTE]).
Some people may develop a blood clot in a deep vein, usually in the leg (venous thrombosis), or a clot in the lungs (pulmonary embolism, [PE]) which may be severe or lead to death. Tell your healthcare provider right away if you have any symptoms such as pain or swelling in an extremity, shortness of breath, chest pain, breathing that is more rapid than normal (tachypnea), or heart beats faster than normal (tachycardia). Your healthcare provider will monitor you for these symptoms and may prescribe blood thinner medicine. • Liver problems, including Drug-Induced Liver Injury (DILI).
People taking Lynparza may develop liver problems which may be severe and can lead to death. Your healthcare provider should do blood tests before and during your treatment with Lynparza. Tell your healthcare provider right away if you notice discomfort on the right side of your stomach-area (abdominal), dark or “tea-colored” urine, or yellowing of your skin or the whites of your eyes (jaundice).
Your healthcare provide may change your dose, temporarily stop, or permanently stop treatment with Lynparza if you get certain side effects. See “What are the possible side effects of LYNPARZA?” for more information about side effects. What is Lynparza?
Lynparza is a prescription medicine used to treat adults who have: • ovarian, fallopian tube, or primary peritoneal cancer: ∘ that is advanced and has a certain type of inherited (germline) or acquired (somatic) abnormal BRCA gene. Lynparza is used as maintenance treatment after the cancer has responded to your first treatment with platinum-based chemotherapy. ∘ in combination with another anti-cancer medicine called bevacizumab when your cancer is advanced and homologous recombination deficiency (HRD) positive, which is identified by a certain type of abnormal BRCA gene or a positive laboratory tumor test for genomic instability.
Lynparza is used as maintenance treatment after the cancer has responded to your first treatment with platinum-based chemotherapy. ∘ that has come back and has a certain type of inherited or acquired abnormal BRCA gene. Lynparza is used as maintenance treatment after the cancer has responded to treatment with platinum-based chemotherapy. • human epidermal growth factor receptor 2 (HER2)-negative breast cancer with a certain type of inherited abnormal BRCA gene: ∘ with a high risk of recurrence. Lynparza is given after surgery (treatment after surgery is called adjuvant therapy).
You should have received chemotherapy medicines before or after surgery to remove the tumor. ∘ that has spread to oth…