
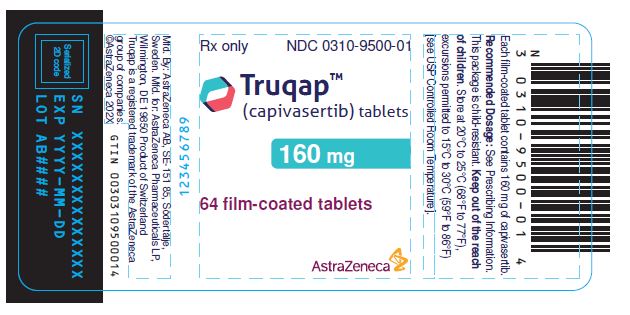
Truqap capivasertib 160 mg Tablet, Film Coated, 64-count — NDC 0310-9500-01 (Billing 00310-9500-01)
This is a package of 64 tablets of Truqap capivasertib 160 mg Tablet, Film Coated from AstraZeneca Pharmaceuticals LP, marketed since Nov 2023 and currently FDA-listed.
NDC database record
One package, one record: these facts belong to NDC 0310-9500-01 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0310 labeler · 9500 product · 01 package
- Package marketed since
- Nov 16, 2023
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Billing quantity
- 64 EA per package
- Barcode (UPC-A, from the NDC)
- 3 0310950001 4
- FDA record last changed
- Oct 1, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 085520
- GCN: 55025
- HICL (First Databank): 049313
- AHFS class code: 10:00.00.00
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
Clinical
Capivasertib is used to treat breast cancer or prostate cancer. Capivasertib is in a class of medications called kinase inhibitors. It works by blocking the action of an abnormal protein that signals cancer cells to multiply. This helps slow or stop the spread of cancer cells.
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Capivasertib — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $370.10 | $23,686.35 / 64 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 4, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00310-9500-01 You're viewing this | 64 TABLET, FILM COATED in 1 BOTTLE | 2023-11-16 | — | Active |
| 00310-9500-02 0310-9500-02 Main listing | 4 BLISTER PACK in 1 CARTON / 16 TABLET, FILM COATED in 1 BLISTER PACK | 2024-10-18 | — | Active |
This pack shows little to no recent Medicaid volume — a different pack size carries most fills. See all packs ↓
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Truqap capivasertib 160 mg Tablet, Film Coated?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Truqap 160 mgthis 00310-9500-01 | AstraZeneca | 64 tablets | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 11760760 ↗ | Method of use | U-3762 | Oct 10, 2028 |
| US 11760760 ↗ | Method of use | U-3762 | Oct 10, 2028 |
| US 10654855 ↗ | Method of use | U-3762 | Oct 10, 2028 |
| US 10654855 ↗ | Method of use | U-3762 | Oct 10, 2028 |
| US 10039766 ↗ | Method of use | U-3762 | Apr 16, 2033 |
| US 10039766 ↗ | Method of use | U-3762 | Apr 16, 2033 |
| US 8101623 ↗ | Drug substance | U-3762 | Mar 10, 2030 |
| US 8101623 ↗ | Drug substance | U-3762 | Mar 10, 2030 |
| US 12252495 ↗ | Method of use | U-3762 | Oct 10, 2028 |
| US 12252495 ↗ | Method of use | U-3762 | Oct 10, 2028 |
| US 11236095 ↗ | Method of use | U-4559 | Oct 10, 2028 |
| US 11236095 ↗ | Method of use | U-4559 | Oct 10, 2028 |
| US 10039766 ↗ | Method of use | U-4559 | Apr 16, 2033 |
| US 10039766 ↗ | Method of use | U-4559 | Apr 16, 2033 |
| US 9492453 ↗ | Method of use | U-4559 | Oct 10, 2028 |
| US 9492453 ↗ | Method of use | U-4559 | Oct 10, 2028 |
| US 10059714 ↗ | Drug substance | — | Oct 10, 2028 |
| US 10059714 ↗ | Drug substance | — | Oct 10, 2028 |
| US 9487525 ↗ | Drug substance | — | Apr 16, 2033 |
| US 9487525 ↗ | Drug substance | — | Apr 16, 2033 |
| Code | What it grants | Expires |
|---|---|---|
| I-991 | New indication (3-year) | Jun 12, 2029 |
| NCE | New Chemical Entity (5-year) | Nov 16, 2028 |
| I-991 | New indication (3-year) | Jun 12, 2029 |
| NCE | New Chemical Entity (5-year) | Nov 16, 2028 |
Is there a generic version of TRUQAP 160 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII L11K75P92J
A mineral salt made from calcium and phosphate. It acts as a filler and binder in tablets to add bulk and help hold the medicine together in solid form.
-
UNII D9C330MD8B
Copovidone is a synthetic polymer made by combining two types of plastic-like molecules. It acts as a binder and film-former to help hold tablet ingredients together and improve how the medicine dissolves in your body.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII C9H2L21V7U
A fat derived from coconut or palm oil containing shorter fatty acid chains. It serves as a solvent and carrier to help dissolve or suspend active ingredients, improving absorption and stability in liquid formulations.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII VH2XOU12IE
Polydextrose is a synthetic polymer made from dextrose (sugar) that acts as a bulking agent and filler in medicines. It helps give tablets and capsules proper volume and texture while often adding slight sweetness.
-
UNII G2M7P15E5P
Polyethylene glycol 3350 is a synthetic polymer used as a solvent, humectant, and thickening agent in medicines. It helps dissolve other ingredients, retain moisture in the product, and achieve the desired consistency.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
14 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from AstraZeneca Pharmaceuticals LP labeler code 00310
- Crestor Rosuvastatin 40 mg Tablet, Film Coated NDC 0310-7590-30
- Dapagliflozin 5 mg Tablet, Film Coated NDC 0310-8205-00
- Dapagliflozin 10 mg Tablet, Film Coated NDC 0310-8210-00
- AIRSUPRA Albuterol sulfate and budesonide 90 ug; 80 ug Aerosol, Metered NDC 0310-9080-12
- WAINUA EPLONTERSEN 45 mg/.8mL Injection, Solution NDC 0310-9400-01
- WAINUA EPLONTERSEN 45 mg/.8mL Injection, Solution NDC 0310-9420-01
- Truqap capivasertib 200 mg Tablet, Film Coated NDC 0310-9501-01
- Rilvegostomig 16.5 kg/16.5kg Liquid NDC 0310-9700-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE TRUQAP is a kinase inhibitor indicated: HR positive, HER2 negative locally advanced or metastatic breast cancer • in combination with fulvestrant for the treatment of adult patients with hormone receptor (HR)-positive, human epidermal growth factor receptor 2 (HER2)-negative, locally advanced or metastatic breast cancer with one or more PIK3CA/AKT1/PTEN -alterations as detected by an FDA-authorized test following progression on at least one endocrine-based regimen in the metastatic setting or recurrence on or within 12 months of completing adjuvant therapy.
( 1.1 ) PTEN-deficient metastatic androgen pathway modulation-naïve or -sensitive (mAPMN/S) prostate cancer • in combination with abiraterone and prednisone for the treatment of adult patients with metastatic androgen pathway modulation-naïve or -sensitive (mAPMN/S) prostate cancer that is PTEN-deficient as detected by an FDA-authorized test. ( 1.2 )
1.1HR-positive, HER2-negative locally advanced or metastatic breast cancer TRUQAP, in combination with fulvestrant, is indicated for the treatment of adult patients with hormone receptor (HR)-positive, human epidermal growth factor receptor 2 (HER2)-negative, locally advanced or metastatic breast cancer with one or more PIK3CA/AKT1/PTEN -alteration as detected by an FDA-authorized test following progression on at least one endocrine-based regimen in the metastatic setting or recurrence on or within 12 months of completing adjuvant therapy.
1.2PTEN-deficient metastatic androgen pathway modulation-naïve or -sensitive prostate cancer TRUQAP, in combination with abiraterone and prednisone, is indicated for treatment of adult patients with metastatic androgen pathway modulation-naïve or -sensitive (mAPMN/S) prostate cancer that is PTEN-deficient as detected by an FDA-authorized test.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Select patients for the treatment of HR-positive, HER2-negative advanced or metastatic breast cancer with TRUQAP based on the presence of one or more of the following genetic alterations in tumor tissue: PIK3CA/AKT1/PTEN . ( 2.1 ) • Select patients for the treatment of mAPMN/S prostate cancer with TRUQAP based on PTEN deficiency in tumor tissue. ( 2.1 ) • Recommended Dosage: 400 mg orally twice daily, with or without food, for 4 days followed by 3 days off.
( 2.3 )
2.1Patient Selection Select patients for the treatment of HR-positive, HER2-negative advanced or metastatic breast cancer with TRUQAP, based on the presence of one or more of the following genetic alterations in tumor tissue: PIK3CA/AKT1/PTEN [see Clinical Studies (14) ] . Select patients for the treatment of metastatic androgen pathway modulation-naïve or -sensitive (mAPMN/S) prostate cancer with TRUQAP based on PTEN deficiency in tumor tissue [see Clinical Studies (14) ] . Information on FDA-authorized tests for patient selection for the detection of PIK3CA, AKT1, and PTEN alterations or PTEN deficiency are available at: http://www.fda.gov/CompanionDiagnostics
2.2Recommended Evaluation Before Initiating TRUQAP Evaluate fasting blood glucose (FG) and hemoglobin A1C (HbA1C) prior to starting TRUQAP and at regular intervals during treatment [see Warnings and Precautions (5.1) ] .
2.3Recommended Dosage The HR positive, HER2 negative locally advanced or metastatic breast cancer The recommended dosage of TRUQAP, in combination with fulvestrant, is 400 mg orally twice daily (approximately 12 hours apart) with or without food, for 4 days followed by 3 days off. Continue TRUQAP until disease progression or unacceptable toxicity. For premenopausal and perimenopausal women, administer a luteinizing hormone releasing hormone (LHRH) agonist according to current clinical practice standards.
For men, consider administering a LHRH agonist according to current clinical practice standards. PTEN-deficient metastatic androgen pathway modulation-naïve or -sensitive (mAPMN/S) prostate cancer The recommended dosage of TRUQAP, in combination with abiraterone and prednisone, is 400 mg orally twice daily (approximately 12 hours apart) with or without food, for 4 days followed by 3 days off. Continue TRUQAP until disease progression or unacceptable toxicity.
Patients with mAPMN/S prostate cancer should also receive a gonadotropin-releasing hormone (GnRH) analog concurrently or should have had bilateral orchiectomy. Refer to the Prescribing Information of the individual therapeutic agents used in combination with TRUQAP for dosing and administration information.
2.4Administration TRUQAP dosing schedule for each week is provided in Table 1. Table 1: TRUQAP Dosing Schedule for Each Week Day 1 2 3 4 5 No dosing on day 5, 6 and 7 6 7 Morning 2 x 200 mg 2 x 200 mg 2 x 200 mg 2 x 200 mg Evening 2 x 200 mg 2 x 200 mg 2 x 200 mg 2 x 200 mg Swallow TRUQAP tablets whole. Do not chew, crush, or split tablets prior to swallowing.
Do not take tablets that are broken, cracked, or otherwise not intact. If a patient misses a dose within 4 hours of the scheduled time, instruct the patient to take the missed dose. If a patient misses a dose more than 4 hours of the scheduled time, instruct the patient to skip the dose and take the next dose at its usual scheduled time.
If a patient vomits a dose, instruct the patient not to take an additional dose and take the next dose at its usual scheduled time.
2.5Dosage Modification for Adverse Reactions The recommended dose reductions for adverse reactions are listed in Table 2. Permanently discontinue TRUQAP if unable to tolerate the second dose reduction. Table 2: Recommended Dose Reductions of TRUQAP for Adverse Reactions TRUQAP Dose and Schedule First dose reduction 320 mg twice daily for 4 days followed by 3 days off Second dose reduction 200 mg twice daily for 4 days followed by 3 days off The recommended dosage modifications for… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: • 160 mg: beige film-coated, round, biconvex tablets debossed with ‘CAV’ above ‘160’ on one side and plain on the reverse. • 200 mg: beige film-coated, capsule-shaped, biconvex tablets debossed with ‘CAV 200’ on one side and plain on the reverse. Tablets: 160 mg and 200 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS TRUQAP is contraindicated in patients with severe hypersensitivity to TRUQAP or any of its components. Severe hypersensitivity to TRUQAP or any of its components. (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Hyperglycemia: TRUQAP can cause severe hyperglycemia, including diabetic ketoacidosis and fatal outcomes. Evaluate blood glucose levels and hemoglobin A1C prior to starting and at regular intervals during treatment. Withhold, reduce dose, or permanently discontinue TRUQAP based on severity.
( 2.2 , 2.5 , 5.1 ) • Diarrhea: TRUQAP caused diarrhea in most patients. Advise patients to increase oral fluids, start antidiarrheal treatment, and consult with a healthcare provider if diarrhea occurs while taking TRUQAP. Withhold, reduce dose, or permanently discontinue TRUQAP based on severity.
( 2.5 , 5.2 ) • Cutaneous Adverse Reactions: Monitor for signs and symptoms of cutaneous adverse reactions. Withhold, reduce dose, or permanently discontinue TRUQAP based on severity. ( 2.5 , 5.3 ) • Embryo-Fetal Toxicity: TRUQAP can cause fetal harm.
Advise patients of potential risk to a fetus and to use effective contraception. Refer to the Full Prescribing Information of fulvestrant for pregnancy and contraception information. ( 5.4 , 8.1 , 8.3 )
5.1Hyperglycemia TRUQAP can cause severe hyperglycemia, including diabetic ketoacidosis and fatal outcomes. Withhold TRUQAP in clinical situations known to increase the risk of severe hyperglycemia or ketoacidosis (e.g., suspected serious infection or acute illness). Before initiating treatment with TRUQAP, test fasting glucose levels (FPG or FBG), HbA1C levels, and optimize fasting glucose.
After initiating treatment with TRUQAP, monitor or self-monitor fasting glucose levels on Day 3 or 4 of the dosing week during weeks 1, 2, 4, 6 and 8; then monthly while on treatment with TRUQAP; and as clinically indicated. Monitor HbA1C levels every 3 months during treatment with TRUQAP and as clinically indicated and manage changes as appropriate. Patients with a history of well-controlled Type 2 diabetes mellitus may require intensified anti-hyperglycemic treatment and require close monitoring of fasting glucose levels.
For patients who experience hyperglycemia during treatment with TRUQAP, monitor fasting glucose at least twice weekly, on days on and off TRUQAP, until fasting glucose decreases to baseline levels. During treatment with anti-diabetic medications, monitor fasting glucose at least once a week for 2 months, followed by once every 2 weeks, or as clinically indicated. Consider consultation with a healthcare practitioner with expertise in the treatment of hyperglycemia and initiation of fasting glucose monitoring at home for patients who have risk factors for hyperglycemia or who experience hyperglycemia.
Advise patients of the signs and symptoms of hyperglycemia and counsel patients on lifestyle changes. Withhold TRUQAP immediately when ketoacidosis is suspected. If ketoacidosis is confirmed, permanently discontinue TRUQAP.
The safety of TRUQAP has not been established in patients with Type 1 diabetes or Type 2 diabetes that is uncontrolled or requiring insulin at baseline as these patients were excluded from clinical studies [see Clinical Studies ( 14.1 , 14.2 )] . Based on the severity of the hyperglycemia, withhold, reduce dose, or permanently discontinue TRUQAP [see Dosage and Administration (2.5) ]. CAPItello 291 Increased fasting glucose from baseline occurred in 37% of patients treated with TRUQAP, including 11% of patients with Grade 2 (FG > 160 to 250 mg/dL), 2% with Grade 3 (FG > 250 to 500 mg/dL), and 1.1% with Grade 4 (FG > 500 mg/dL) events.
The median time to first occurrence of hyperglycemia was 15 days (range: 1 to 367). Dose reduction for hyperglycemia was required in 0.6% of patients and permanent discontinuation was required in 0.6% of patients. Diabetic metabolic decompensation occurred in 0.6% of patients, including diabetic ketoacidosis in 0.3%.
In CAPItello-291, 12% (43/355) of patients who received TRUQAP had an anti-hyperglycemic medication regimen either initiated or changed during the study, including treatment with insulin in 4.8% (17/355) o… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are also discussed in greater details in other sections of the labeling: • Hyperglycemia [see Warnings and Precautions (5.1) ] • Diarrhea [see Warnings and Precautions (5.2) ] • Cutaneous Adverse Reactions [see Warnings and Precautions (5.3) ] Most common adverse reactions (incidence ≥20%), including laboratory abnormalities, in patients with: • HR-positive, HER2-negative breast cancer were diarrhea, cutaneous adverse reactions, increased random glucose, decreased lymphocytes, decreased hemoglobin, increased fasting glucose, nausea, fatigue, decreased leukocytes, increased triglycerides, decreased neutrophils, increased creatinine, vomiting and stomatitis.
( 6.1 ) • PTEN-deficient mAPMN/S prostate cancer were increased fasting glucose, decreased hemoglobin, decreased lymphocytes, cutaneous adverse reactions, diarrhea, decreased potassium, increased creatinine, increased non-fasting glucose, increased alanine aminotransferase, increased triglycerides, increased aspartate aminotransferase, decreased sodium, and fatigue. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact AstraZeneca at 1-800-236-9933 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The safety population described in WARNINGS and PRECAUTIONS reflects exposure to TRUQAP 400 mg orally, twice a day for 4 days followed by 3 days off, in combination with fulvestrant, in 355 patients with metastatic breast cancer in CAPItello-291 until disease progression or unacceptable toxicity.
Among the 355 patients who received TRUQAP in combination with fulvestrant, 52% were exposed for 6 months or longer, and 27% were exposed for greater than one year. In this safety population, the most common (≥ 20%) adverse reactions including laboratory abnormalities were diarrhea (72%), cutaneous adverse reactions (58%), increased random glucose (57%), decreased lymphocytes (47%), decreased hemoglobin (45%), increased fasting glucose (37%), nausea and fatigue (35% each), decreased leukocytes (32%), increased triglycerides (27%), decreased neutrophils (23%), increased creatinine (22%), vomiting (21%), and stomatitis (20%).
The safety population described in WARNINGS and PRECAUTIONS also reflects exposure to TRUQAP 400 mg orally, twice a day for 4 days followed by 3 days off, in combination with abiraterone, in 503 patients with mAPMN/S prostate cancer with PTEN deficiency in CAPItello-281 until disease progression or unacceptable toxicity. CAPItello-291 The safety of TRUQAP was evaluated in CAPItello-291, a clinical trial including 288 adult patients (155 patients in TRUQAP with fulvestrant arm and 133 patients in placebo with fulvestrant arm) whose breast cancer had one or more PIK3CA/AKT1/PTEN -alterations [see Clinical Studies (14) ] .
Among patients who received TRUQAP, 61% were exposed for 6 months or longer and 30% were exposed for greater than one year. Of the 155 patients who received TRUQAP with fulvestrant, the median age was 58 years (range 36 to 84); female (99%); White (48%), Asian (31%), Black (1.3%), American Indian/Alaska Native (0.6%), and other races (19%). Serious adverse reactions occurred in 18% of patients receiving TRUQAP with fulvestrant.
The most common serious adverse reactions (≥ 1%) were cutaneous adverse reaction (3.9%), diarrhea and pneumonia (2.6% each), vomiting and pyrexia (1.9% each), hyperglycemia, hypersensitivity, fatigue, renal injury and second malignancy (1.3% each). Fatal adverse reactions occurred in 1.3% of patients who received TRUQAP with fulvestrant, including sepsis (0.6%), and acute myocardial infarction (0.6%). Permanent TRUQAP discontinuation due to an adverse reaction occurred in 10% of patients.… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Strong CYP3A Inhibitors: Avoid concomitant use. If concomitant use cannot be avoided, reduce TRUQAP dose. ( 2.6 , 7.1 ) • Moderate CYP3A Inhibitors: Reduce TRUQAP dose. ( 2.6 , 7.1 ) • Strong and Moderate CYP3A Inducers: Avoid concomitant use. ( 7.1 )
7.1Effects of Other Drugs on TRUQAP Table 8 describes drug interactions where concomitant use of another drug affects TRUQAP. Table 8: Drug Interactions with TRUQAP Strong CYP3A Inhibitors Clinical Impact • Capivasertib is a CYP3A substrate. Strong CYP3A inhibitors increase capivasertib exposure [see Clinical Pharmacology (12.3) ], which may increase the risk of TRUQAP adverse reactions.
Prevention or Management • Avoid concomitant use with a strong CYP3A inhibitor. If concomitant use cannot be avoided, reduce the dose of TRUQAP and monitor patients for adverse reactions [see Dosage and Administration (2.5) ] . Moderate CYP3A Inhibitors Clinical Impact • Capivasertib is a CYP3A substrate.
Moderate CYP3A inhibitors increase capivasertib exposure [see Clinical Pharmacology (12.3) ], which may increase the risk of TRUQAP adverse reactions. Prevention or Management • When concomitantly used with moderate CYP3A inhibitor, reduce the dose of TRUQAP and monitor patients for adverse reactions [see Dosage and Administration (2.5) ] . Strong and Moderate CYP3A Inducers Clinical Impact • Capivasertib is a CYP3A substrate.
Strong and moderate CYP3A inducers decrease capivasertib exposure [see Clinical Pharmacology (12.3) ], which may reduce the effectiveness of TRUQAP. Prevention or Management • Avoid concomitant use of TRUQAP with strong or moderate CYP3A inducers.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary TRUQAP is used in combination with fulvestrant. Refer to the Full Prescribing Information of fulvestrant for pregnancy information. Based on findings in animals and mechanism of action, TRUQAP can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] .
There are no available data on the use of TRUQAP in pregnant women. In an animal reproduction study, oral administration of capivasertib to pregnant rats during the period of organogenesis caused adverse developmental outcomes, including embryo-fetal mortality and reduced fetal weights at maternal exposures 0.7 times the human exposure (AUC) at the recommended dose of 400 mg twice daily ( see Data ). Advise pregnant women and females of reproductive potential of the potential risk to a fetus.
The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects is 2% to 4% and of miscarriage is 15% to 20% of clinically recognized pregnancies in the U.S. general population. Data Animal Data In an embryo-fetal development study, pregnant rats received oral doses of capivasertib up to 150 mg/kg/day during the period of organogenesis.
Administration of capivasertib resulted in maternal toxicities (reduced body weight gain and food consumption, increased blood glucose) and adverse developmental outcomes, including embryo-fetal deaths (post-implantation loss), reduced fetal weights, and minor fetal visceral variations at a dose of 150 mg/kg/day (0.7 times the human exposure at the recommended dose of 400 mg twice daily based on AUC). In a pre- and post-natal assessment, pregnant rats received oral doses of capivasertib up to 150 mg/kg/day from gestation day 6 through at least lactation day 6.
Administration of 150 mg/kg/day resulted in reduced litter and pup weights.
8.2Lactation Risk Summary TRUQAP is used in combination with fulvestrant. Refer to the Full Prescribing Information of fulvestrant for lactation information. There are no data on the presence of capivasertib or its metabolites in human milk or their effects on milk production or the breastfed child.
Capivasertib was detected in the plasma of suckling rat pups ( see Data ). Because of the potential for serious adverse reactions in a breastfed child, advise women not to breastfeed during treatment with TRUQAP. Data Animal Data In a pre- and post-natal assessment, when capivasertib was administered to maternal rats during the lactation period, capivasertib was detected in plasma of suckling rat pups on lactation day 7 to 8 [see Use in Specific Populations (8.1) ] .
Plasma concentrations in pups were up to 0.6% of concentrations in maternal plasma in the 150 mg/kg/day group.
8.3Females and Males of Reproductive Potential TRUQAP is used in combination with fulvestrant or abiraterone. Refer to the Full Prescribing Information of fulvestrant or abiraterone for contraception and infertility information. TRUQAP can cause fetal harm when administered to pregnant women [see Use in Specific Populations (8.1) ] .
Pregnancy Testing Verify pregnancy status of females of reproductive potential prior to initiating TRUQAP [see Use in Specific Populations (8.1) ] . Contraception Females Advise females of reproductive potential to use effective contraception during treatment with TRUQAP and for 1 month after the last dose. Males Advise male patients with female partners of reproductive potential to use effective contraception during treatment with TRUQAP and for 4 months after the last dose.
8.4Pediatric Use The safety and effectiveness of TRUQAP have not been established in pediatric patients.
8.5Geriatric Use Of the 355 patients who received TRUQAP in CAPItello-291, 115 (32%) patients were ≥ 65 years of age and 24 (7%) patients were ≥ 75 years of age. No overall differences in the effic… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary TRUQAP is used in combination with fulvestrant. Refer to the Full Prescribing Information of fulvestrant for pregnancy information. Based on findings in animals and mechanism of action, TRUQAP can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] .
There are no available data on the use of TRUQAP in pregnant women. In an animal reproduction study, oral administration of capivasertib to pregnant rats during the period of organogenesis caused adverse developmental outcomes, including embryo-fetal mortality and reduced fetal weights at maternal exposures 0.7 times the human exposure (AUC) at the recommended dose of 400 mg twice daily ( see Data ). Advise pregnant women and females of reproductive potential of the potential risk to a fetus.
The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects is 2% to 4% and of miscarriage is 15% to 20% of clinically recognized pregnancies in the U.S. general population. Data Animal Data In an embryo-fetal development study, pregnant rats received oral doses of capivasertib up to 150 mg/kg/day during the period of organogenesis.
Administration of capivasertib resulted in maternal toxicities (reduced body weight gain and food consumption, increased blood glucose) and adverse developmental outcomes, including embryo-fetal deaths (post-implantation loss), reduced fetal weights, and minor fetal visceral variations at a dose of 150 mg/kg/day (0.7 times the human exposure at the recommended dose of 400 mg twice daily based on AUC). In a pre- and post-natal assessment, pregnant rats received oral doses of capivasertib up to 150 mg/kg/day from gestation day 6 through at least lactation day 6.
Administration of 150 mg/kg/day resulted in reduced litter and pup weights.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of TRUQAP have not been established in pediatric patients.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 355 patients who received TRUQAP in CAPItello-291, 115 (32%) patients were ≥ 65 years of age and 24 (7%) patients were ≥ 75 years of age. No overall differences in the efficacy of TRUQAP were observed between patients ≥ 65 years of age and younger patients. Analysis of the safety of TRUQAP comparing patients ≥ 65 years of age to younger patients suggest a higher incidence of Grade 3 to 5 adverse reactions (57% versus 36%), dosage reductions (30% versus 15%), dose interruptions (57% versus 30%), and permanent discontinuations (23% versus 8%), respectively.
Of the 503 patients who received TRUQAP in CAPItello-281, 331 (66%) patients were ≥ 65 years of age and 85 (17%) patients were ≥ 75 years of age. No overall differences in the efficacy of TRUQAP were observed between patients ≥ 65 years of age and younger patients. Analysis of the safety of TRUQAP comparing patients ≥ 65 years of age to younger patients suggest a higher incidence of Grade 3 to 5 adverse reactions (77% versus 60%), dosage reductions (36% versus 24%), dose interruptions (72% versus 53%), and permanent discontinuations (27% versus 7%), respectively.
The differences in Grade 3 or 4 adverse reactions between patients ≥ 65 years of age and younger patients was primarily driven by an increased incidence of hyperglycemia and hypokalemia.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Capivasertib is an inhibitor of all 3 isoforms of serine/threonine kinase AKT (AKT1, AKT2 and AKT3) and inhibits phosphorylation of downstream AKT substrates. AKT activation in tumors is a result of activation of upstream signaling pathways, mutations in AKT1 , loss of phosphatase and tensin homolog (PTEN) function and mutations in the catalytic subunit alpha of phosphatidylinositol 3-kinase ( PIK3CA ). In vitro , capivasertib reduced growth of breast cancer cell lines including those with relevant PIK3CA or AKT1 mutations or PTEN alteration.
In vivo , capivasertib alone and in combination with fulvestrant inhibited tumor growth of mouse xenograft models including estrogen receptor positive breast cancer models with alterations in PIK3CA, AKT1 , and PTEN . In vitro , capivasertib reduced growth of AR-positive PTEN deficient prostate cancer cell lines. In vivo , capivasertib inhibited tumor growth in mouse xenograft models bearing PTEN-deficient prostate cancer cells and demonstrated increased antitumor activity when used in combination with abiraterone.
12.2Pharmacodynamics Exposure-Response Relationships The exposure-response relationship and time course of pharmacodynamic response for the effectiveness of capivasertib have not been fully characterized. An exposure-response relationship was observed where increased capivasertib exposure was associated with increased incidence of diarrhea (CTCAE Grades 3 or 4) at doses of 80 to 800 mg (0.2 to 2 times the approved recommended dosage). Cardiac Electrophysiology At the recommended TRUQAP dose, a mean increase in the QTc interval > 20 ms was not observed.
12.3Pharmacokinetics Capivasertib pharmacokinetic parameters are presented as the geometric mean [geometric % coefficient of variation (%CV)], unless otherwise specified. The capivasertib steady-state AUC is 7,356 h·ng/mL (38%) and C max is 1,247 ng/mL (28%). Steady-state concentrations are predicted to be attained on the 3rd and 4th dosing day of each week, starting week 2.
Capivasertib plasma concentrations are approximately 0.2% to 5.1% of the steady state Cmax during the off-dosing days. Capivasertib AUC and C max are proportional with dose over a range of 80 to 800 mg (0.2 to 2 times the approved recommended dosage). Absorption T max is approximately 1-2 hours.
The absolute bioavailability is 29%. Effect of Food No clinically meaningful differences in capivasertib pharmacokinetics were observed following administration of TRUQAP with a high-fat meal (approximately 1,000 kcal; fat 60%) or a low-fat meal (approximately 400 kcal; fat 26%). Distribution The steady state oral volume of distribution is 1,847 L (36%).
Capivasertib plasma protein binding is 78% and the plasma-to-blood ratio is 0.71. Elimination The half-life is 8.3 hours, and the steady-state oral clearance is 50 L/h (37% CV). Renal clearance was 21% of total clearance.
Metabolism Capivasertib is primarily metabolized by CYP3A4 and UGT2B7. Excretion Following a single radiolabeled oral dose of 400 mg, the mean total recovery was 45% from urine and 50% from feces. Specific Populations No clinically significant differences in capivasertib pharmacokinetics were observed based on race/ethnicity (including White, Asian, Black, American Indian or Alaskan Native, and Native Hawaiian or Other Pacific Islander), sex (88% females), body weight (32 to 150 kg), age (26 to 87 years), mild hepatic impairment (bilirubin ≤ ULN and AST > ULN or bilirubin > 1 to 1.5x ULN), or mild to moderate renal impairment (CLcr 30 to 89 mL/min).
The effect of moderate (bilirubin > 1.5 to 3x ULN and any AST) hepatic impairment is not fully characterized. TRUQAP has not been studied in patients with severe (bilirubin > 3x ULN and any AST) hepatic impairment or severe renal impairment (CLcr 15 to 29 mL/min). Drug Interaction Studies Clinical Studies and Model-Informed Approaches Effect of Strong and Moderate CYP3A Inhibitors on Capivasertib: Itraco… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Capivasertib is an inhibitor of all 3 isoforms of serine/threonine kinase AKT (AKT1, AKT2 and AKT3) and inhibits phosphorylation of downstream AKT substrates. AKT activation in tumors is a result of activation of upstream signaling pathways, mutations in AKT1 , loss of phosphatase and tensin homolog (PTEN) function and mutations in the catalytic subunit alpha of phosphatidylinositol 3-kinase ( PIK3CA ). In vitro , capivasertib reduced growth of breast cancer cell lines including those with relevant PIK3CA or AKT1 mutations or PTEN alteration.
In vivo , capivasertib alone and in combination with fulvestrant inhibited tumor growth of mouse xenograft models including estrogen receptor positive breast cancer models with alterations in PIK3CA, AKT1 , and PTEN . In vitro , capivasertib reduced growth of AR-positive PTEN deficient prostate cancer cell lines. In vivo , capivasertib inhibited tumor growth in mouse xenograft models bearing PTEN-deficient prostate cancer cells and demonstrated increased antitumor activity when used in combination with abiraterone.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied Table 11: TRUQAP 160 mg and 200 mg Tablets Strength Description Package Size and Type NDC Number TRUQAP 160 mg Beige film-coated, round, biconvex tablets debossed with ‘CAV’ above ‘160’ on one side and plain on the reverse. HPDE, child resistant, bottle of 64 tablets 0310-9500-01 TRUQAP 200 mg Beige film-coated, capsule-shaped, biconvex tablets debossed with ‘CAV 200’ on one side and plain on the reverse. HPDE, child resistant, bottle of 64 tablets 0310-9501-01 TRUQAP 160 mg Beige film-coated, round, biconvex tablets debossed with ‘CAV’ above ‘160’ on one side and plain on the reverse.
Each carton has 4 blister packs each blister pack containing 16 tablets (total 64 tablets). 0310-9500-02 TRUQAP 200 mg Beige film-coated, capsule-shaped, biconvex tablets debossed with ‘CAV 200’ on one side and plain on the reverse. Each carton has 4 blister packs each blister pack containing16 tablets (total 64 tablets).
0310-9501-02 TRUQAP 200 mg Beige film-coated, capsule-shaped, biconvex tablets debossed with ‘CAV 200’ on one side and plain on the reverse supplied in a blister with a child resistant closure. Each carton has 4 blister packs with each blister pack containing 8 tablets (total 32 tablets). 0310-9501-04 Storage and Handling Store TRUQAP at 20°C to 25°C (68°F to 77°F).
Excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Store tablets in the original package. Discard unused tablets after 45 days.
Dispense bottled TRUQAP tablets either in the original bottle or a USP equivalent tight container.
📋 Description ▾
11 DESCRIPTION TRUQAP (capivasertib) is a kinase inhibitor. The molecular formula for capivasertib is C 21 H 25 ClN 6 O 2 and the molecular weight is 428.92 g/mol. The chemical name of capivasertib is 4-amino- N -[(1S)-1-(4-chlorophenyl)-3-hydroxypropyl]-1-(7 H -pyrrolo[2,3- d ]pyrimidin-4-yl)-4-piperidinecarboxamide.
Capivasertib is freely soluble in water at pH values below 1.2 and practically insoluble at pH values above 6.8. Capivasertib has the following structural formula: TRUQAP film-coated tablets are supplied for oral administration with 160 mg or 200 mg capivasertib. The tablets also contain croscarmellose sodium, dibasic calcium phosphate, magnesium stearate, and microcrystalline cellulose.
The film coat contains the following inactive ingredients: copovidone, hypromellose, iron oxide black, iron oxide red, iron oxide yellow, medium chain triglycerides, polydextrose, polyethylene glycol 3350, and titanium dioxide. chemical structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Hyperglycemia Advise patients that TRUQAP can cause hyperglycemia and that they will need to monitor their fasting blood glucose and HbA1C periodically during therapy. Advise patients to withhold TRUQAP in clinical situations known to increase the risk of severe hyperglycemia or ketoacidosis (e.g., suspected serious infection or acute illness).
Advise patients to contact their healthcare provider immediately for signs and symptoms of hyperglycemia (e.g., excessive thirst, urinating more often, blurred vision, mental confusion, difficulty breathing, or increased appetite with weight loss) or ketoacidosis [see Warnings and Precautions (5.1) ] . Diarrhea Advise patients that TRUQAP can cause diarrhea and to start antidiarrheal treatment, increase oral fluids, and notify their healthcare provider if diarrhea occurs while taking TRUQAP [see Warnings and Precautions (5.2) ] .
Cutaneous Adverse Reactions Advise patients that TRUQAP can cause cutaneous adverse reactions and to contact their healthcare provider immediately to report new or worsening rash, erythematous and exfoliative skin reactions [see Warnings and Precautions (5.3) ] . Embryo-Fetal Toxicity • Advise females to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.4) and Use in Specific Populations (8.1) ] . Advise pregnant women and females of reproductive potential of the potential risk to a fetus. • Advise females of reproductive potential to use effective contraception during treatment with TRUQAP and for 1 month after the last dose [see Use in Specific Population (8.3) ] . • Advise male patients with female partners of reproductive potential to use effective contraception during treatment with TRUQAP and for 4 months after the last dose [see Use in Specific Populations (8.3) ] . • Refer to the Full Prescribing Information of fulvestrant or abiraterone for pregnancy and contraception information.
Lactation Advise women to not breastfeed during treatment with TRUQAP [see Use in Specific Populations (8.2) ] . Refer to the Full Prescribing Information of fulvestrant for lactation information. Dosing Instructions Instruct patients to take TRUQAP 2 times each day, at about the same times each day, for four days on and 3 days off, with or without food.
Swallow the tablet(s) whole with water. Tablets should not be chewed, crushed, or split prior to swallowing. [see Dosage and Administration (2.3) ] . Instruct patients that if the dose is missed, it can be taken within 4 hours after the time it is usually taken.
If more than 4 hours has passed, skip the dose. Take the next dose at the usual time. Instruct patients that if they vomit after taking the dose, an additional dose should not be taken.
The next dose of TRUQAP should be taken at the usual time [ see Dosage and Administration (2.3) ] . Drug Interactions Advise patients to inform their healthcare providers of all concomitant medications, including prescription medicines, over-the-counter medications, vitamins, and herbal products [see Drug Interactions (7.1) ] . Grapefruit may interact with TRUQAP.
Patients should not consume grapefruit products while taking TRUQAP. Distributed by: AstraZeneca Pharmaceuticals LP Wilmington, DE 19850 TRUQAP is a registered trademark of the AstraZeneca group of companies. ©AstraZeneca 2026
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Capivasertib pharmacokinetic parameters are presented as the geometric mean [geometric % coefficient of variation (%CV)], unless otherwise specified. The capivasertib steady-state AUC is 7,356 h·ng/mL (38%) and C max is 1,247 ng/mL (28%). Steady-state concentrations are predicted to be attained on the 3rd and 4th dosing day of each week, starting week 2.
Capivasertib plasma concentrations are approximately 0.2% to 5.1% of the steady state Cmax during the off-dosing days. Capivasertib AUC and C max are proportional with dose over a range of 80 to 800 mg (0.2 to 2 times the approved recommended dosage). Absorption T max is approximately 1-2 hours.
The absolute bioavailability is 29%. Effect of Food No clinically meaningful differences in capivasertib pharmacokinetics were observed following administration of TRUQAP with a high-fat meal (approximately 1,000 kcal; fat 60%) or a low-fat meal (approximately 400 kcal; fat 26%). Distribution The steady state oral volume of distribution is 1,847 L (36%).
Capivasertib plasma protein binding is 78% and the plasma-to-blood ratio is 0.71. Elimination The half-life is 8.3 hours, and the steady-state oral clearance is 50 L/h (37% CV). Renal clearance was 21% of total clearance.
Metabolism Capivasertib is primarily metabolized by CYP3A4 and UGT2B7. Excretion Following a single radiolabeled oral dose of 400 mg, the mean total recovery was 45% from urine and 50% from feces. Specific Populations No clinically significant differences in capivasertib pharmacokinetics were observed based on race/ethnicity (including White, Asian, Black, American Indian or Alaskan Native, and Native Hawaiian or Other Pacific Islander), sex (88% females), body weight (32 to 150 kg), age (26 to 87 years), mild hepatic impairment (bilirubin ≤ ULN and AST > ULN or bilirubin > 1 to 1.5x ULN), or mild to moderate renal impairment (CLcr 30 to 89 mL/min).
The effect of moderate (bilirubin > 1.5 to 3x ULN and any AST) hepatic impairment is not fully characterized. TRUQAP has not been studied in patients with severe (bilirubin > 3x ULN and any AST) hepatic impairment or severe renal impairment (CLcr 15 to 29 mL/min). Drug Interaction Studies Clinical Studies and Model-Informed Approaches Effect of Strong and Moderate CYP3A Inhibitors on Capivasertib: Itraconazole (strong CYP3A4 inhibitor) is predicted to increase capivasertib AUC by up to 1.7-fold and C max by up to 1.4-fold.
Erythromycin and verapamil (moderate CYP3A inhibitors) are predicted to increase capivasertib AUC by up to 1.5-fold and C max by up to 1.3-fold. Effect of Strong and Moderate CYP3A Inducers on Capivasertib: Rifampicin (strong CYP3A4 inducer) is predicted to decrease capivasertib AUC by 70% and C max by 60%. Efavirenz (moderate CYP3A4 inducer) is predicted to decrease capivasertib AUC by 60% and C max by 50%.
Effect of UGT2B7 Inhibitors on Capivasertib: Probenecid (UGT2B7 inhibitor) is not predicted to have a clinically meaningful effect on capivasertib pharmacokinetics. Effect of Acid Reducing Agents on Capivasertib: Rabeprazole (gastric acid reducing agent) did not have a clinically meaningful effect on capivasertib pharmacokinetics. Effect of Capivasertib on CYP3A Substrates: Concomitant use of TRUQAP increased midazolam (CYP3A substrate) AUC by 1.8-fold on day 4 and by 1.2-fold on day 7.
Effect of Capivasertib on CYP2D6 Substrates: TRUQAP is predicted to increase desipramine (CYP2D6 substrate) AUC by up to 2.1-fold on day 4. Effect of Capivasertib on CYP2C9 Substrates: Concomitant use of TRUQAP with warfarin (CYP2C9 substrate) is not predicted to have a clinically meaningful effect on warfarin pharmacokinetics. Effect of Capivasertib on UGT1A1 Substrates: TRUQAP is predicted to increase raltegravir (UGT1A1 substrate) AUC by up to 1.7-fold on day 4.
In-Vitro Studies CYP450 Enzymes: Capivasertib induces CYP1A2. Transporter Systems: Capivasertib inhibits BCRP, OATP1B1, OATP1B3, OAT3, MATE1, MATE2-K, and OCT2.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Exposure-Response Relationships The exposure-response relationship and time course of pharmacodynamic response for the effectiveness of capivasertib have not been fully characterized. An exposure-response relationship was observed where increased capivasertib exposure was associated with increased incidence of diarrhea (CTCAE Grades 3 or 4) at doses of 80 to 800 mg (0.2 to 2 times the approved recommended dosage). Cardiac Electrophysiology At the recommended TRUQAP dose, a mean increase in the QTc interval > 20 ms was not observed.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Metastatic HR-Positive, HER2-Negative Breast Cancer The efficacy of TRUQAP with fulvestrant was evaluated in CAPItello-291 (NCT04305496), a randomized, double-blind, placebo-controlled, multicenter trial that enrolled 708 adult patients with locally advanced (inoperable) or metastatic HR-positive, HER2-negative (defined as IHC 0 or 1+, or IHC 2+/ISH-) breast cancer of which 289 patients had tumors with eligible PIK3CA/AKT1/PTEN -alterations. Eligible PIK3CA/AKT1 activating mutations or PTEN loss of function alterations were identified in the majority of FFPE tumor specimens using FoundationOne®CDx next-generation sequencing (n=686).
All patients were required to have progression on an aromatase inhibitor (AI) based treatment in the metastatic setting or recurrence on or within 12 months of completing (neo)adjuvant treatment with an AI. Patients could have received up to two prior lines of endocrine therapy and up to 1 line of chemotherapy for locally advanced (inoperable) or metastatic disease. Patients were excluded if they had clinically significant abnormalities of glucose metabolism (defined as patients with diabetes mellitus Type 1, Type 2 requiring insulin treatment, or HbA1c ≥8%).
Patients were randomized (1:1) to receive either 400 mg of TRUQAP (n=355) or placebo (n=353), given orally twice daily for 4 days followed by 3 days off treatment each week of 28-day treatment cycle. Fulvestrant 500 mg intramuscular injection was administered on cycle 1 days 1 and 15, and then at day 1 of each subsequent 28-day cycle. Patients were treated until disease progression, or unacceptable toxicity.
Randomization was stratified by presence of liver metastases (yes vs. no), prior treatment with CDK4/6 inhibitors (yes vs. no) and geographical region (region 1: US, Canada, Western Europe, Australia, and Israel vs region 2: Latin America, Eastern Europe and Russia vs Region 3: Asia). The major efficacy outcomes were investigator-assessed progression-free survival (PFS) in the overall population, and in the population of patients whose tumors have PIK3CA/AKT1/PTEN -alterations evaluated according to Response Evaluation Criteria in Solid Tumors (RECIST), version 1.1.
Additional efficacy outcome measures were overall survival (OS), investigator assessed objective response rate (ORR) and duration of response (DoR). Of the 289 patients whose tumors were PIK3CA/AKT1/PTEN -altered, the median age was 59 years (range 34 to 90); female (99%); White (52%), Asian (29%), Black (1%), American Indian/Alaska Native (0.7%), other races (17%) and 9% were Hispanic/Latino. Eastern Cooperative Oncology Group (ECOG) performance status was 0 (66%) or 1 (34%), and 18% were premenopausal or perimenopausal.
Seventy-six percent of patients had an alteration in PIK3CA , 13% had an alteration in AKT1 , and 17% had an alteration in PTEN . All patients received prior endocrine-based therapy (100% AI based treatment and 44% received tamoxifen). Seventy-one percent of patients were previously treated with a CDK4/6 inhibitor and 18% received prior chemotherapy for locally advanced (inoperable) or metastatic disease.
A statistically significant difference in PFS was observed in the overall population and the population of patients whose tumors have PIK3CA/AKT1/PTEN -alteration. An exploratory analysis of PFS in the 313 (44%) patients whose tumors did not have a PIK3CA/AKT1/PTEN -alteration showed a HR of 0.79 (95% CI: 0.61, 1.02), indicating that the difference in the overall population was primarily attributed to the results seen in the population of patients whose tumors have PIK3CA/AKT1/PTEN -alteration. Efficacy results for PIK3CA/AKT1/PTEN -altered subgroup are presented in Table 9 and Figure 1.
Results from the blinded independent review committee (BICR) assessment were consistent with the investigator assessed PFS results. Overall survival results were immature at the time of the PFS analysis (30% of the patients died). Table 9: Efficacy Re… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In a 2-year rat carcinogenicity study, rats received oral doses up to 30 mg/kg/day in males and 75 mg/kg/day in females (approximately 0.2 times and 0.4 times the human exposure at the recommended dose based on AUC, respectively). While there were no statistically significant increases in tumors, there was an increase in malignant mesothelioma in the testis of male rats at 30 mg/kg/day, which is considered a rare tumor in the tested rat strain. Capivasertib was genotoxic in the in vivo rat bone marrow micronucleus assay through an aneugenic mechanism.
Capivasertib was not mutagenic in vitro in a bacterial reverse mutation (Ames) assay or mouse lymphoma gene mutation assay. In repeat-dose toxicity studies up to 26 weeks duration in rats and 39 weeks duration in dogs, tubular degeneration in the testes and cellular debris in the epididymides were observed at oral capivasertib doses of 100 mg/kg/day in rats and 15 mg/kg/day in dogs (approximately 1 time the human exposure at the recommended dose of 400 mg twice daily based on AUC). In a male fertility study, capivasertib had no effect on fertility in male rats at oral doses up to 100 mg/kg/day following 10 weeks of treatment.
Effects of capivasertib on female fertility have not been studied in animals.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In a 2-year rat carcinogenicity study, rats received oral doses up to 30 mg/kg/day in males and 75 mg/kg/day in females (approximately 0.2 times and 0.4 times the human exposure at the recommended dose based on AUC, respectively). While there were no statistically significant increases in tumors, there was an increase in malignant mesothelioma in the testis of male rats at 30 mg/kg/day, which is considered a rare tumor in the tested rat strain. Capivasertib was genotoxic in the in vivo rat bone marrow micronucleus assay through an aneugenic mechanism.
Capivasertib was not mutagenic in vitro in a bacterial reverse mutation (Ames) assay or mouse lymphoma gene mutation assay. In repeat-dose toxicity studies up to 26 weeks duration in rats and 39 weeks duration in dogs, tubular degeneration in the testes and cellular debris in the epididymides were observed at oral capivasertib doses of 100 mg/kg/day in rats and 15 mg/kg/day in dogs (approximately 1 time the human exposure at the recommended dose of 400 mg twice daily based on AUC). In a male fertility study, capivasertib had no effect on fertility in male rats at oral doses up to 100 mg/kg/day following 10 weeks of treatment.
Effects of capivasertib on female fertility have not been studied in animals.
📄 Recent Major Changes ▾
Indications and Usage ( 1.2 ) 06/2026 Dosage and Administration ( 2.1 , 2.3 ) 06/2026 Warnings and Precautions ( 5.1 , 5.2 , 5.3 ) 06/2026
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL – 160mg tablets Rx Only NDC 03109500-01 TRUQAP™ (capivasertib) tablets 160mg 64 film-coated tablets AstraZeneca 160mg_label
PRINCIPAL DISPLAY PANEL – 200mg tablet Rx only NDC 0310-9501-01 TRUQAP™ (capivasertib) tablets 200mg 64 film-coated tablets AstraZeneca 200mg_label
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |