
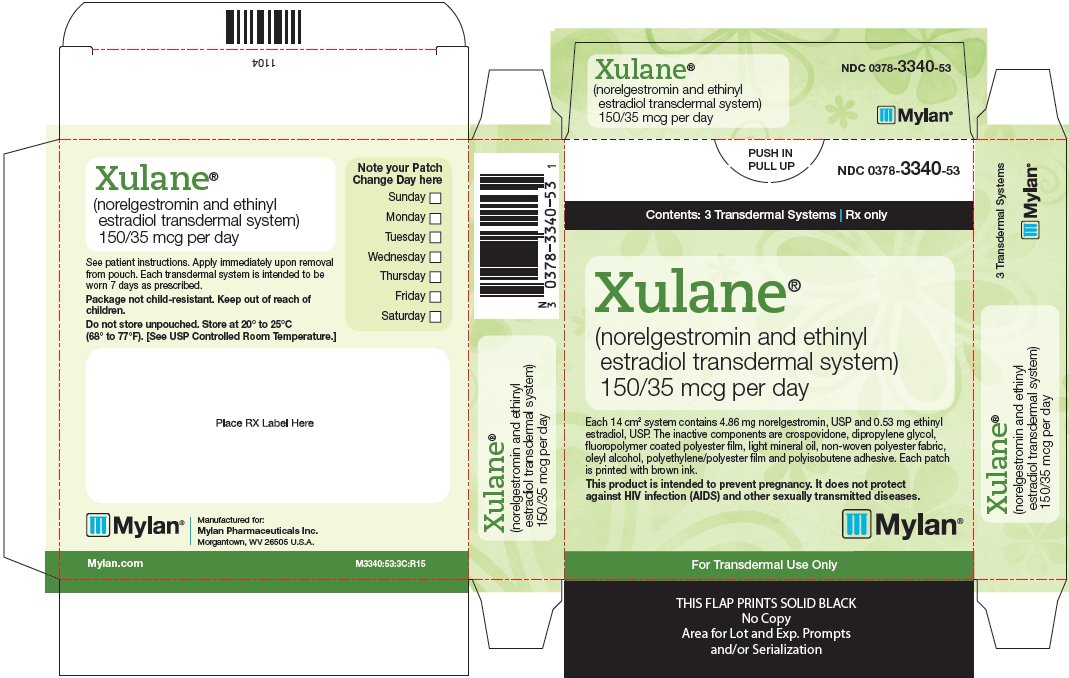
Xulane norelgestromin and ethinyl estradiol 150 ug/d; 35 ug/d Patch — NDC 0378-3340-53 (Billing 00378-3340-53)
This is a package of Xulane norelgestromin and ethinyl estradiol 150 ug/d; 35 ug/d Patch from Mylan Pharmaceuticals Inc., marketed since Apr 2014 and currently FDA-listed; retail pharmacies pay about $37.16 per unit (NADAC). It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 0378-3340-53 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0378 labeler · 3340 product · 53 package
- Package marketed since
- Apr 16, 2014
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 0378334053 1
- Medicaid fills, this package
- 243,432 prescriptions in the last four reported quarters
- FDA record last changed
- Aug 27, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 049828
- GCN: 15524
- GPI-14 (Medi-Span): 25960002508820
- HICL (First Databank): 023235
- AHFS class code: 68:12.00.00
- RxCUI (RxNorm): 1534809
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Progestin class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Estrogen and progestin transdermal (patch) contraceptives are used to prevent pregnancy. Estrogen (ethinyl estradiol) and progestin (levonorgestrel or norelgestromin) are two female sex hormones. Combinations of estrogen and progestin work by preventing ovulation (the release of eggs from the ovaries) and by changing the cervical mucus and the lining of the uterus. The contraceptive patch is a very effective method of birth control, but it does not prevent the spread of human immunodeficiency virus (HIV; the virus that causes acquired immunodeficiency syndrome [AIDS]) and other sexually transm...
Read the full MedlinePlus article ↗- Yes, exactly every week for 3 weeks in a row, then you skip week 4 entirely — no patch. Always change it on the same day each week (your 'Patch Change Day'). Only wear one patch at...
- How exactly do I use the patch — do I really have to change it every week?
- You can apply it to your upper outer arm, abdomen, buttock, or back. Just avoid the breast. Absorption is considered equivalent from all those spots, though the abdomen absorbs sli...
- Where should I put the patch on my body?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $37.155 | $111.47 / 3 patch |
| Medicaid paysCMS SDUD · 12 mo | $31.50 | $94.50 / 3 patch |
| Medicare drug plans payPart D · Q2 2026 | $30.39 | $91.17 / 3 patch |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 00378-3340-32 0378-3340-32 | 1 POUCH in 1 CARTON / 1 PATCH in 1 POUCH / 7 d in 1 PATCH | — | — | 2016-06-13 | — | Active |
| 00378-3340-53 You're viewing this Main listing | 3 POUCH in 1 CARTON / 1 PATCH in 1 POUCH / 7 d in 1 PATCH | $37.16 / ea | $111.47 | 2014-04-16 | — | Active |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Xulane norelgestromin and ethinyl estradiol 150 ug/d; 35 ug/d Patch?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Zafemy 150 ug/d; 35 ug/d 65162-0358-03 | Amneal | 3 patches | $31.908 | AB | Availability likely | save 14% |
| norelgestromin and ethinyl estradiol 150 ug/mg; 35 ug/mg 70710-1190-03 | Zydus | 3 pouches | $33.290 | AB | Availability likely | save 10% |
| Xulane 150 ug/d; 35 ug/dthis 00378-3340-53 | Mylan | 3 patches | $37.155 | AB | Availability likely | — |
| Zafemy 150 ug/d; 35 ug/d 42291-0930-03 | AvKARE | 3 patches | — | AB | FDA listed | — |
| Xulane 150 ug/d; 35 ug/d 50090-1683-00 | A-S | 3 pouches | — | AB | FDA listed | — |
| Norelgestromin and Ethinly Estradiol 150 ug/d; 35 ug/d 69238-1521-03 | Amneal | 3 patches | — | AB | FDA listed | — |
| norelgestromin and ethinyl estradiol 150 ug/mg; 35 ug/mg 70771-1777-03 | Zydus | 3 pouches | — | AB | FDA listed | — |
| Zafemy 150 ug/d; 35 ug/d 72162-2220-01 | Bryant | 3 patches | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Ethinyl Estradiol / Norelgestromin inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 68401960MK
Crospovidone is a synthetic polymer made from polyvinylpyrrolidone. It acts as a disintegrant, helping tablets break apart quickly in the stomach so the medicine dissolves and absorbs into the body.
-
UNII E107L85C40
Dipropylene glycol is a clear liquid made from propylene glycol. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII T5L8T28FGP
Mineral oil is a clear, odorless liquid derived from crude oil. It acts as a lubricant and emollient in medications, helping pills slide smoothly during manufacturing and aiding moisture retention in topical products.
-
UNII 172F2WN8DV
A fatty alcohol derived from animal or plant oils. It acts as an emollient and helps stabilize emulsions, allowing oil and water to mix evenly in the medication.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Mylan Pharmaceuticals Inc. labeler code 00378
- Prazosin Hydrochloride 5 mg Capsule NDC 0378-3205-01
- candesartan cilexetil 4 mg Tablet NDC 0378-3224-77
- candesartan cilexetil 8 mg Tablet NDC 0378-3225-77
- candesartan cilexetil 16 mg Tablet NDC 0378-3231-77
- candesartan cilexetil 32 mg Tablet NDC 0378-3232-77
- Etoposide 50 mg Capsule NDC 0378-3266-94
- Estradiol .025 mg/d Patch NDC 0378-3349-99
- Estradiol .05 mg/d Patch NDC 0378-3350-99
- Estradiol .075 mg/d Patch NDC 0378-3351-99
- Estradiol .1 mg/d Patch NDC 0378-3352-99
- Estradiol .0375 mg/d Patch NDC 0378-3360-99
- Estradiol .06 mg/d Patch NDC 0378-3361-99
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: CIGARETTE SMOKING AND SERIOUS CARDIOVASCULAR EVENTS and CONTRAINDICATED IN WOMEN WITH A BMI ≥ 30 kg/m 2 • Cigarette Smoking and Serious Cardiovascular Events Cigarette smoking increases the risk of serious cardiovascular events from hormonal contraceptive use. This risk increases with age, particularly in women over 35 years of age, and with the number of cigarettes smoked. For this reason, CHCs, including Xulane, are contraindicated in women who are over 35 years of age and smoke [see Contraindications (4) and Warnings and Precautions (5.1) ] . • Contraindicated in Women with a BMI ≥ 30 kg/m 2 Xulane is contraindicated in women with a BMI ≥ 30 kg/m 2 .
The risk of VTE may be greater with Xulane in women with a BMI > 30 kg/m 2 compared to women with a lower BMI. [see Contraindications (4) and Warnings and Precautions (5.1 )] . WARNING: CIGARETTE SMOKING AND SERIOUS CARDIOVASCULAR EVENTS and CONTRAINDICATED IN WOMEN WITH A BMI ≥ 30 kg/m 2 See full prescribing information for complete boxed warning. • Xulane is contraindicated in women over 35 years old who smoke. Cigarette smoking increases the risk of serious cardiovascular events from combination hormonal contraceptive (CHC) use.
( 4 , 5.1 ) • Xulane is contraindicated for use in women with a BMI ≥ 30 kg/m 2 . Women with a BMI ≥ 30 kg/m 2 who use Xulane may have a higher risk of venous thromboembolic events compared with women with a lower BMI. ( 4 , 5.1 , 8.8 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Xulane is indicated for the prevention of pregnancy in women with a body mass index (BMI) < 30 kg/m 2 for whom a combined hormonal contraceptive is appropriate. Limitations of Use: Xulane may be less effective in preventing pregnancy in women who weigh 198 lbs. (90 kg) or more.
Xulane is contraindicated for use in women with BMI ≥ 30 kg/m 2 [see Contraindications (4) , Warnings and Precautions (5.1) and Clinical Studies (14) ] . Xulane is an estrogen/progestin combination hormonal contraceptive (CHC), indicated for the prevention of pregnancy in women with a BMI < 30 kg/m 2 for whom a combined hormonal contraceptive is appropriate. ( 1 ) Limitations of Use: Xulane may be less effective in preventing pregnancy in women at or above 198 lbs.
(90 kg). ( 1 , 4 , 14 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION To achieve maximum contraceptive effectiveness, Xulane must be used exactly as directed. Complete instructions to facilitate patient counseling on proper system usage may be found in the FDA-Approved Patient Labeling. • Xulane uses a 28-day (4-week) cycle. Apply a new patch to the upper outer arm, abdomen, buttock or back each week for 3 weeks (21 total days).
Week 4 is patch-free. ( 2.1 , 2.3 ) • Apply each new patch on the same day of the week. Wear only one patch at a time.
( 2.1 ) • Do not cut or alter the patch in any way. ( 2.1 )
2.1How to Use Xulane The Xulane transdermal system uses a 28-day (4-week) cycle. A new patch is applied each week for 3 weeks (21 total days). Week 4 is patch-free.
Withdrawal bleeding is expected during this time. Every new patch should be applied on the same day of the week. This day is known as the “Patch Change Day.” For example, if the first patch is applied on a Monday, all subsequent patches should be applied on a Monday.
Only one patch should be worn at a time. Do not cut, damage or alter the Xulane patch in any way. If the Xulane patch is cut, damaged or altered in size, contraceptive efficacy may be impaired.
On the day after Week 4 ends, a new 4-week cycle is started by applying a new patch. Under no circumstances should there be more than a 7-day patch-free interval between dosing cycles.
2.2How to Start Using Xulane There are multiple options for starting the Xulane patch, and the woman should choose the option that is most appropriate (see Table 1): Table 1: Instructions for Administration Starting Xulane in women with no current use of hormonal contraception The woman has two options for starting the patch and she should choose the option that is right for her: First Day Start • The woman should apply her first patch during the first 24 hours of her menstrual period. If a patch is applied after the first 24 hours of menstruation, non-hormonal back-up contraception (such as condoms and spermicide, or diaphragm and spermicide) is needed for the first 7 days of the first cycle only. • The woman should apply a new patch each week for three weeks (21 total days).
Every new patch should be applied on the same day of the week. This day is known as the “Patch Change Day.” For example, if the first patch is applied on a Monday, all subsequent patches should be applied on a Monday. Only one patch should be worn at a time. • No patch is worn during Week Four (the “Patch-Free Week”).
Withdrawal bleeding is expected during this time. • On the day after Week 4 ends, a new 4-week cycle is started by applying a new patch. Under no circumstances should there be more than a 7-day patch-free interval between dosing cycles. Sunday Start • The woman should apply her first patch on the first Sunday after her menstrual period begins. • With this option, a non-hormonal backup method of birth control, such as a condom and spermicide or diaphragm and spermicide, is needed for the first 7 days of the first cycle only. • If her period starts on a Sunday, the first patch should be applied that day, and no backup contraception is needed.
Switching from another contraceptive method Oral combination hormonal contraception (oral CHC) • If the woman is switching from the pill to Xulane, she should complete her current pill cycle and apply the first Xulane patch on the day she would normally start her next pill • If she does not get her period within a week after taking the last active pill, she should check with her healthcare professional to be sure that she is not pregnant, but she may go ahead and start Xulane for contraception. • If the patch is applied more than a week after taking the last active pill, she should use a non-hormonal back-up contraception (such as condoms and spermicide, or diaphragm and spermicide) concurrently for the first 7 days of patch use.
Transdermal system • If the woman is switching from another contraceptive transdermal system to Xulane, she should comp… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Xulane ® (norelgestromin and ethinyl estradiol transdermal system) is available in one strength of 150 mcg/day norelgestromin (NGMN) and 35 mcg/day ethinyl estradiol (EE). Xulane ® is a 14 cm² peach, transdermal system printed with “Xulane ® (norelgestromin and ethinyl estradiol) 150/35 mcg per day” in brown ink. Each system contains 4.86 mg norelgestromin, USP and 0.53 mg ethinyl estradiol, USP.
Transdermal system: 150 mcg/day norelgestromin and 35 mcg/day ethinyl estradiol. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Xulane is contraindicated in females who are known to have or develop the following conditions: • At high risk of arterial or venous thromboembolic events. Examples include women who: o Smoke, if over age 35 [see Boxed Warning , and Warnings and Precautions (5.1) ] o Have deep vein thrombosis or pulmonary embolism, now or in the past [see Warnings and Precautions (5.1) ] o Have inherited or acquired hypercoagulopathies [see Warnings and Precautions (5.1) ] o Have cerebrovascular disease [see Warnings and Precautions (5.1) ] o Have coronary artery disease [see Warnings and Precautions (5.1) ] o Have thrombogenic valvular or thrombogenic rhythm diseases of the heart (for example, subacute bacterial endocarditis with valvular disease, or atrial fibrillation) [see Warnings and Precautions (5.1) ] o Have uncontrolled hypertension [see Warnings and Precautions (5.5) ] o Have diabetes mellitus with vascular disease [see Warnings and Precautions (5.7) ] o Have headaches with focal neurological symptoms or have migraine headaches with aura ▪ Women over age 35 with any migraine headaches [see Warnings and Precautions (5.8) ] • Body Mass Index ≥ 30 kg/m 2 [see Warnings and Precautions (5.1) ] • Liver tumors, benign or malignant, or liver disease [see Warnings and Precautions (5.3) , Use in Specific Populations (8.6) and Clinical Pharmacology (12.3) ] • Undiagnosed abnormal uterine bleeding [see Warnings and Precautions (5.9) ] • Pregnancy, because there is no reason to use hormonal contraceptives during pregnancy [see Warnings and Precautions (5.10) and Use in Specific Populations (8.1) ] • Current diagnosis of, or history of, breast cancer, which may be hormone-sensitive [See Warnings and Precautions (5.12) ] • Use of Hepatitis C drug combinations containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir, due to the potential for alanine aminotransferase (ALT) elevations [see Warnings and Precautions (5.4) ] • At high risk of arterial or venous thromboembolic events ( 4 ) • BMI ≥ 30 kg/m 2 ( 4 ) • Breast cancer or other estrogen- or progestin-sensitive cancer ( 4 ) • Liver tumors or liver disease ( 4 ) • Undiagnosed abnormal uterine bleeding ( 4 ) • Pregnancy ( 4 ) • Co-administration with Hepatitis C drug combinations containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Vascular risks: Stop Xulane if a thrombotic event occurs. Stop at least 4 weeks before and through 2 weeks after major surgery. Start no earlier than 4 weeks after delivery, in women who are not breastfeeding.
Consider cardiovascular risk factors before initiating in all women, particularly those over 35 years. ( 5.1 ) • Liver disease: Discontinue Xulane if jaundice occurs. ( 5.3 ) • High blood pressure: Do not prescribe Xulane for women with uncontrolled hypertension or hypertension with vascular disease.
( 5.5 ) • Carbohydrate and lipid metabolic effects: Monitor prediabetic and diabetic women taking Xulane. Consider an alternate contraceptive method for women with uncontrolled dyslipidemia. ( 5.7 ) • Headache: Evaluate significant change in headaches and discontinue Xulane if indicated.
( 5.8 ) • Uterine bleeding: Evaluate irregular bleeding or amenorrhea. ( 5.9 )
5.1Thromboembolic Disorders and Other Vascular Conditions • Stop Xulane if an arterial or venous thromboembolic event (VTE) occurs. • Stop Xulane if there is unexplained loss of vision, proptosis, diplopia, papilledema, or retinal vascular lesions. Evaluate for retinal vein thrombosis immediately. • If feasible, stop Xulane at least 4 weeks before and through 2 weeks after major surgery or other surgeries known to have an elevated risk of VTE. Discontinue use of Xulane during prolonged immobilization and resume treatment based on clinical judgment. • Start Xulane no earlier than 4 weeks after delivery, in women who are not breastfeeding.
The risk of postpartum VTE decreases after the third postpartum week, whereas the risk of ovulation increases after the third postpartum week. • Before starting Xulane, evaluate any past medical history or family history of thrombotic or thromboembolic disorders and consider whether the history suggests an inherited or acquired hypercoagulopathy. [see Contraindications (4) ] . Arterial Events The use of CHCs increases the risk of cardiovascular events and cerebrovascular events, such as myocardial infarction and stroke.
The risk is greater among older women (> 35 years of age), smokers, and women with hypertension, dyslipidemia, diabetes, or obesity. Xulane is contraindicated in women over 35 years of age who smoke [see Contraindications (4) ] . Cigarette smoking increases the risk of serious cardiovascular events from CHC use.
This risk increases with age, particularly in women over 35 years of age, and with the number of cigarettes smoked. Venous Events The use of CHCs increases the risk of venous thromboembolic events (VTEs), such as deep vein thrombosis and pulmonary embolism. Risk factors for VTEs include smoking, obesity, and family history of VTE, in addition to other factors that contraindicate use of CHCs.
The risk of VTE may be greater with Xulane in women with a BMI ≥ 30 kg/m 2 compared to women with a lower BMI [see Contraindications (4) ] . While the increased risk of VTE associated with use of CHCs is well-established, the rates of VTE are even greater during pregnancy, and especially during the postpartum period (see Figure 1). The frequency of VTE in women using CHCs has been estimated to be 3 to 12 cases per 10,000 woman-years.
The risk of VTE is highest during the first year of use of CHCs and when restarting hormonal contraception after a break of 4 weeks or longer. This initial higher risk declines during the first year, but users of CHCs remain at an increased risk of VTE compared to non-users of CHCs. Based on results from a few studies, there is some evidence that this is true for non-oral products as well.
The risk of thromboembolic disease due to CHCs gradually disappears after CHC use is discontinued. Figure 1 shows the risk of developing a VTE for women who are not pregnant and do not use CHCs, for women who use CHCs with a range of doses and routes of administration, for pregnant women, and for women in the postpartum period. To put the risk of developing a VTE into perspec… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions with the use of combination hormonal contraceptives, including Xulane, are discussed elsewhere in the labeling: • Serious cardiovascular events and stroke [see Boxed Warning and Warnings and Precautions (5.1) ] • Vascular events, including venous and arterial thromboembolic events [see Warnings and Precautions (5.1) ] • Liver disease [see Warnings and Precautions (5.3) ] Adverse reactions commonly reported by users of combination hormonal contraceptives are: • Irregular uterine bleeding • Nausea • Breast tenderness • Headache The most frequent adverse reactions reported during clinical trials (≥ 5%) were breast symptoms, nausea/vomiting, headache, application site disorder, abdominal pain, dysmenorrhea, vaginal bleeding and menstrual disorders, and mood, affect and anxiety disorders.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Mylan at 1-877-446-3679 (1-877-4-INFO-RX) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. The data described below reflect exposure to norelgestromin and ethinyl estradiol transdermal system in 3330 sexually active women (3322 of whom had safety data) who participated in three Phase 3 clinical trials designed to evaluate contraceptive efficacy and safety.
These subjects received six or 13 cycles of contraception (norelgestromin and ethinyl estradiol transdermal system or an oral contraceptive comparator in 2 of the trials). The women ranged in age from 18 to 45 years and were predominantly white (91%). The most common adverse reactions (≥ 5%) reported during clinical trials were breast symptoms, nausea/vomiting, headache, application site disorder, abdominal pain, dysmenorrhea, vaginal bleeding and menstrual disorders, and mood, affect and anxiety disorders.
The most common events leading to discontinuation were application site reaction, breast symptoms (including breast discomfort, engorgement and pain), nausea and/or vomiting, headache and emotional lability. Adverse drug reactions reported by ≥ 2.5% of norelgestromin and ethinyl estradiol transdermal system-treated subjects in these trials are shown in Table 3. Table 3: Adverse Drug Reactions Reported by ≥ 2.5% of Norelgestromin and Ethinyl Estradiol Transdermal System-treated Subjects in Three Phase 3 Clinical Trials System/Organ Class MedDRA version
10.0Adverse reaction Norelgestromin and Ethinyl Estradiol Transdermal System (n = 3322) Reproductive system and breast disorders Breast symptoms Represents a bundle of similar terms 22.4% Dysmenorrhea 7.8% Vaginal bleeding and menstrual disorders 6.4% Gastrointestinal disorders Nausea 16.6% Abdominal pain 8.1% Vomiting 5.1% Diarrhea 4.2% Nervous system disorders Headache 21.0% Dizziness 3.3% Migraine 2.7% General disorders and administration site conditions Application site disorder 17.1% Fatigue 2.6% Psychiatric disorders Mood, affect and anxiety disorders 6.3% Skin and subcutaneous tissue disorders Acne 2.9% Pruritus 2.5% Infections and infestations Vaginal yeast infection 3.9% Investigations Weight increased 2.7% Additional adverse drug reactions that occurred in < 2.5% of norelgestromin and ethinyl estradiol transdermal system-treated subjects in the above clinical trials datasets are: • Gastrointestinal disorders: Abdominal distension • General disorders and administration site conditions: Fluid retention 1 , malaise • Hepatobiliary disorders: Cholecystitis • Investigations: Blood pressure increased, lipid disorders 1 • Musculoskeletal and connective tissue disorders: Muscle spasms • Psychiatric disorders: Insomnia, libido decreased, libido increased • Reproductive system and breast disorders: Galactorrhea, genital discharge, p… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Consult the labeling of concurrently-used drugs to obtain further information about interactions with hormonal contraceptives or the potential for enzyme alterations. Drugs or herbal products that induce certain enzymes (for example CYP3A4) may decrease the effectiveness of CHCs or increase breakthrough bleeding. Counsel patients to use a back-up or alternative method of contraception when enzyme inducers are used with CHCs. ( 7.1 )
7.1Effects of Other Drugs on Combined Hormonal Contraceptives Substances Decreasing the Plasma Concentrations of CHCs and Potentially Diminishing the Efficacy of CHCs Drugs or herbal products that induce certain enzymes, including cytochrome P450 3A4 (CYP3A4), may decrease the plasma concentrations of CHCs and potentially diminish the effectiveness of CHCs or increase breakthrough bleeding. Some drugs or herbal products that may decrease the effectiveness of hormonal contraceptives include phenytoin, barbiturates, carbamazepine, bosentan, felbamate, griseofulvin, oxcarbazepine, rifampicin, topiramate, rifabutin, rufinamide, aprepitant, and products containing St.
John’s wort. Interactions between hormonal contraceptives and other drugs may lead to breakthrough bleeding and/or contraceptive failure. Counsel women to use an alternative method of contraception or a back-up method when enzyme inducers are used with CHCs, and to continue back-up contraception for 28 days after discontinuing the enzyme inducer to ensure contraceptive reliability.
Substances Increasing the Plasma Concentrations of CHCs Co-administration of atorvastatin or rosuvastatin and certain CHCs containing EE increase AUC values for EE by approximately 20% to 25%. Ascorbic acid and acetaminophen may increase plasma EE concentrations, possibly by inhibition of conjugation. CYP3A4 inhibitors such as itraconazole, voriconazole, fluconazole, grapefruit juice, or ketoconazole may increase plasma hormone concentrations.
Human Immunodeficiency Virus (HIV)/Hepatitis C Virus (HCV) Protease Inhibitors and Non-Nucleoside Reverse Transcriptase Inhibitors Significant changes (increase or decrease) in the plasma concentrations of estrogen and/or progestin have been noted in some cases of co-administration with HIV protease inhibitors (decrease [e.g., nelfinavir, ritonavir, darunavir/ritonavir, (fos)amprenavir/ritonavir, lopinavir/ritnoavir, and tipranavir/ritonavir] or increase [e.g., indinavir and atazanavir/ritonavir])/HCV protease inhibitors or with non-nucleoside reverse transcriptase inhibitors (decrease [e.g., nevirapine] or increase [e.g., etravirine]).
7.2Effects of Combined Hormonal Contraceptives on Other Drugs CHCs containing EE may inhibit the metabolism of other compounds (e.g., cyclosporine, prednisolone, theophylline, tizanidine, and voriconazole) and increase their plasma concentrations. CHCs have been shown to decrease plasma concentrations of acetaminophen, clofibric acid, morphine, salicylic acid, and temazepam. Significant decrease in plasma concentration of lamotrigine has been shown, likely due to induction of lamotrigine glucuronidation.
This may reduce seizure control; therefore, dosage adjustments of lamotrigine may be necessary. Women on thyroid hormone replacement therapy may need increased doses of thyroid hormone because serum concentration of thyroid-binding globulin increases with use of CHCs [see Warnings and Precautions (5.13) ] .
7.3Concomitant Use with HCV Combination Therapy – Liver Enzyme Elevation Do not co-administer Xulane with HCV drug combinations containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir, due to potential for ALT elevations [see Warnings and Precautions (5.4) ] .
7.4Interference with Laboratory Tests The use of contraceptive steroids may influence the results of certain laboratory tests, such as coagulation factors, lipids, glucose tolerance, and binding proteins.
Drug Interactions In a PK drug interaction study, oral administration of tetracycline H… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Nursing mothers: Not recommended; can decrease milk production. ( 8.3 )
8.1Pregnancy There is little or no increased risk of birth defects in women who inadvertently use hormonal contraceptives during early pregnancy. Epidemiologic studies and meta-analyses have not found an increased risk of genital or non-genital birth defects (including cardiac anomalies and limb reduction defects) following exposure to low dose hormonal contraceptives prior to conception or during early pregnancy. The administration of hormonal contraceptives to induce withdrawal bleeding should not be used as a test for pregnancy.
Hormonal contraceptives should not be used during pregnancy to treat threatened or habitual abortion.
8.3Nursing Mothers The effects of Xulane in nursing mothers have not been evaluated and are unknown. When possible, advise the nursing mother to use other forms of contraception until she has completely weaned her child. Estrogen-containing CHCs can reduce milk production in breastfeeding mothers.
This is less likely to occur once breastfeeding is well-established; however, it can occur at any time in some women. Small amounts of contraceptive steroids and/or metabolites are present in breast milk.
8.4Pediatric Use Safety and efficacy of norelgestromin and ethinyl estradiol transdermal system have been established in women of reproductive age. Efficacy is expected to be the same for post-pubertal adolescents under the age of 18 and for users 18 years and older. Use of this product before menarche is not indicated.
8.5Geriatric Use Xulane has not been studied in postmenopausal women and is not indicated in this population.
8.6Hepatic Impairment No studies with Xulane have been conducted in women with hepatic impairment. However, steroid hormones may be poorly metabolized in patients with impaired liver function. Acute or chronic disturbances of liver function may necessitate the discontinuation of combined hormonal contraceptive use until markers of liver function return to normal and combined hormonal contraceptive causation has been excluded. [See Contraindications (4) and Warnings and Precautions (5.3) .]
8.7Renal Impairment No studies with Xulane have been conducted in women with renal impairment.
8.8BMI and Weight Considerations Xulane is contraindicated in women with a BMI ≥ 30 kg/m 2 because of the potential increased risk of VTE [see Contraindications (4) and Warnings and Precautions (5.1) ]. Xulane may be less effective in preventing pregnancy in women who weigh 198 lbs. or more [see Clinical Studies (14) ].
Use in Specific Populations Effects of Age, Body Weight, Body Surface Area and Race The effects of age, body weight, body surface area and race on the PK of NGMN and EE were evaluated in 230 healthy women from nine pharmacokinetic studies of single 7-day applications of norelgestromin and ethinyl estradiol transdermal system. For both NGMN and EE, increasing age, body weight and body surface area each were associated with slight decreases in C ss and AUC values. However, only a small fraction (10% to 25%) of the overall variability in the PK of NGMN and EE following application of norelgestromin and ethinyl estradiol transdermal system may be associated with any or all of the above demographic parameters.
There was no significant effect of race with respect to Caucasians, Hispanics and Blacks.
🤰 Pregnancy ▾
8.1Pregnancy There is little or no increased risk of birth defects in women who inadvertently use hormonal contraceptives during early pregnancy. Epidemiologic studies and meta-analyses have not found an increased risk of genital or non-genital birth defects (including cardiac anomalies and limb reduction defects) following exposure to low dose hormonal contraceptives prior to conception or during early pregnancy. The administration of hormonal contraceptives to induce withdrawal bleeding should not be used as a test for pregnancy.
Hormonal contraceptives should not be used during pregnancy to treat threatened or habitual abortion.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and efficacy of norelgestromin and ethinyl estradiol transdermal system have been established in women of reproductive age. Efficacy is expected to be the same for post-pubertal adolescents under the age of 18 and for users 18 years and older. Use of this product before menarche is not indicated.
🧓 Geriatric Use ▾
8.5Geriatric Use Xulane has not been studied in postmenopausal women and is not indicated in this population.
🆘 Overdosage ▾
10 OVERDOSAGE Overdosage may cause nausea and vomiting, and withdrawal bleeding may occur in women. In case of suspected overdose, all Xulane patches should be removed and symptomatic treatment given.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action NGMN is the active progestin largely responsible for the progestational activity that occurs in women following application of norelgestromin and ethinyl estradiol transdermal system. NGMN is also the primary active metabolite produced following oral administration of NGM, the progestin component of some oral contraceptive products. Combination hormonal contraceptives act by suppression of gonadotropins.
Although the primary mechanism of this action is inhibition of ovulation, other alterations include changes in the cervical mucus (which increase the difficulty of sperm entry into the uterus) and the endometrium (which reduce the likelihood of implantation).
12.2Pharmacodynamics One clinical trial assessed the return of hypothalamic-pituitary-ovarian axis function post-therapy and found that follicle-stimulating hormone (FSH), luteinizing hormone (LH), and estradiol mean values, though suppressed during therapy, returned to near baseline values during the 6 weeks post-therapy.
12.3Pharmacokinetics Absorption The systemic delivery rate of NGMN and EE from norelgestromin and ethinyl estradiol transdermal system is approximately 150 mcg of NGMN and 35 mcg of EE per day based on a comparative analysis with intravenous (IV) data. Following a single application of norelgestromin and ethinyl estradiol transdermal system, both NGMN and EE reach a plateau by approximately 48 hours. Pooled data from the 3 clinical studies have demonstrated that steady state is reached within 2 weeks of application.
In one of the clinical studies, C ss concentrations across all subjects ranged from 0.305 to 1.53 ng/mL for NGMN and from 23 to 137 pg/mL for EE. Absorption of NGMN and EE following application of norelgestromin and ethinyl estradiol transdermal system to the buttock, upper outer arm, abdomen and upper torso (excluding breast) was examined. While absorption from the abdomen was slightly lower than from other sites, absorption from these anatomic sites was considered to be therapeutically equivalent.
The mean (%CV) PK parameters C ss and AUC 0-168 for NGMN and EE following a single buttock application of norelgestromin and ethinyl estradiol transdermal system are summarized in Table 5. In multiple dose studies, AUC 0-168 for NGMN and EE was found to increase over time (Table 5). In a three-cycle study, these PK parameters reached steady state conditions during Cycle 3 (Figures 3 and 4) .
Upon removal of the patch, serum levels of EE and NGMN reach very low or non-measurable levels within 3 days. Table 5: Mean (%CV * ) PK Parameters of NGMN and EE Following Three Consecutive Cycles of Norelgestromin and Ethinyl Estradiol Transdermal System Wear on the Buttock nc = not calculated, * %CV is % of Coefficient of variation = 100 (standard deviation/mean) Analyte Parameter Cycle 1 Cycle 3 Cycle 3 Cycle 3 Week 1 Week 1 Week 2 Week 3 NGMN C ss (ng/mL) 0.70 (39.4) 0.70 (41.8) 0.80 (28.7) 0.70 (45.3) AUC 0-168 (ng·h/mL) 107 (44.2) 105 (43.2) 132 (43.4) 120 (43.9) t 1/2 (h) nc nc nc 32.1 (40.3) EE C ss (pg/mL) 46.4 (38.5) 47.6 (36.4) 59.0 (42.5) 49.6 (54.4) AUC 0-168 (pg·h/mL) 6796 (39.3) 7160 (40.4) 10054 (41.8) 8840 (58.6) t 1/2 (h) nc nc nc 21.0 (43.2) Figure 3: Mean Serum NGMN Concentrations (ng/mL) in Healthy Female Volunteers Following Application of Norelgestromin and Ethinyl Estradiol Transdermal System on the Buttock for Three Consecutive Cycles (Vertical arrow indicates time of patch removal) Figure 4: Mean Serum EE Concentrations (pg/mL) in Healthy Female Volunteers Following Application of Norelgestromin and Ethinyl Estradiol Transdermal System on the Buttock for Three Consecutive Cycles (Vertical arrow indicates time of patch removal.) The absorption of NGMN and EE following application of norelgestromin and ethinyl estradiol transdermal system was studied under conditions encountered in a health club (sauna, whirlpool and treadmill) and in a cold water bath.
The results indicated that for… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action NGMN is the active progestin largely responsible for the progestational activity that occurs in women following application of norelgestromin and ethinyl estradiol transdermal system. NGMN is also the primary active metabolite produced following oral administration of NGM, the progestin component of some oral contraceptive products. Combination hormonal contraceptives act by suppression of gonadotropins.
Although the primary mechanism of this action is inhibition of ovulation, other alterations include changes in the cervical mucus (which increase the difficulty of sperm entry into the uterus) and the endometrium (which reduce the likelihood of implantation).
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Xulane ® (norelgestromin and ethinyl estradiol transdermal system) is available in one strength of 150 mcg/day NGMN and 35 mcg/day EE. Xulane ® is a 14 cm² peach, transdermal system printed with “Xulane ® (norelgestromin and ethinyl estradiol) 150/35 mcg per day” in brown ink. Each system contains 4.86 mg norelgestromin, USP and 0.53 mg ethinyl estradiol, USP.
Each transdermal system is packaged in a protective pouch. Xulane ® (norelgestromin and ethinyl estradiol transdermal system) is available in folding cartons of one cycle each (NDC 0378-3340-53); each cycle contains 3 systems.
16.2Special Precautions for Storage and Disposal Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Store patches in their protective pouches. Apply immediately upon removal from the protective pouch. Do not store in the refrigerator or freezer.
Used patches still contain some active hormones. The sticky sides of the patch should be folded together and the folded patch placed in a sturdy container, preferably with a child-resistant cap, and the container thrown in the trash. Used patches should not be flushed down the toilet.
📋 Description ▾
11 DESCRIPTION Xulane is a transdermal system with a contact surface area of 14 cm². It contains 4.86 mg norelgestromin, USP (NGMN) and 0.53 mg ethinyl estradiol, USP (EE), and its delivery rate is approximately 150 mcg of NGMN and 35 mcg of EE per day. Systemic exposures (as measured by area under the curve [AUC] and steady state concentration [C ss ]) of NGMN and EE during use of norelgestromin and ethinyl estradiol transdermal system are higher and the C max is lower than those produced by an oral contraceptive containing NGM 250 mcg / EE 35 mcg. [See Boxed Warning and Clinical Pharmacology (12.3) . ] Xulane is a thin, matrix-type transdermal system consisting of three layers.
The backing layer is composed of a peach flexible film consisting of a pigmented polyethylene outer layer and a polyester inner layer. It provides structural support and protects the middle adhesive layer from the environment. The middle layer contains polyisobutene adhesive, crospovidone, mineral oil, non-woven polyester fabric, oleyl alcohol and dipropylene glycol as inactive components.
The active components in this layer are the hormones, NGMN and EE. The third layer is the release liner , which protects the adhesive layer during storage and is removed just prior to application. It is a transparent polyester film with a fluoropolymer coating on the side that is in contact with the middle adhesive layer.
The outside of the backing layer is printed with “Xulane ® (norelgestromin and ethinyl estradiol) 150/35 mcg per day” in brown ink. Xulane transdermal systems are packaged with additional pieces of protective film above and below the system within each pouch. These pieces of protective film are removed and discarded at the time of use.
The structural formulas of the components are: Molecular weight, NGMN: 327.47 Molecular weight, EE: 296.41 Chemical name for NGMN: 18, 19-dinorpregn-4-en-20-yn-3-one, 13-ethyl-, 17-hydroxy, 3-oxime, (17 α )- Chemical name for EE: 19-Norpregna-1,3,5(10)-trien-20-yne-3, 17β-diol, (17 α )- Norelgestromin and Ethinyl Estradiol Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See FDA-approved patient labeling ( Patient Information and Instructions for Use )
17.1General Counsel patients about the following information: • Cigarette smoking increases the risk of serious cardiovascular events from combined hormonal contraceptive use, and that women who are over 35 years old and smoke should not use combined hormonal contraceptives. • The use of CHCs increases the risk of VTE. However, pregnancy increases the risk of VTE as much or more than the use of CHCs. The risk of VTE in women using CHCs is 3 to 12 cases per 10,000 woman-years.
The risk of VTE is highest during the first year of use of CHCs and when restarting hormonal contraception after a break of 4 weeks or longer. The risk of thromboembolic disease due to CHCs gradually disappears after use is discontinued. • Xulane does not protect against HIV infection (AIDS) and other sexually transmitted infections. • The Warnings and Precautions associated with combined hormonal contraceptives. • Xulane is not to be used during pregnancy; if pregnancy occurs during use of Xulane, instruct the patient to stop further use. • Apply a single patch the same day every week (Weeks 1 through 3).
Instruct patients what to do in the event a patch is missed. See “WHAT IF I FORGET TO CHANGE MY PATCH?” section in FDA-Approved Patient Labeling. • Use a back-up or alternative method of contraception when enzyme inducers are used with Xulane. • Combined hormonal contraceptives may reduce breast milk production; this is less likely to occur if breastfeeding is well established. • Women who start combined hormonal contraceptives postpartum, and who have not yet had a period, should use an additional method of contraception until they have used a patch for 7 consecutive days. • Amenorrhea may occur.
Consider pregnancy in the event of amenorrhea. Rule out pregnancy in the event of amenorrhea in two or more consecutive cycles, amenorrhea in one cycle if the woman has not adhered to the dosing schedule, or if associated with symptoms of pregnancy, such as morning sickness or unusual breast tenderness. • If the Xulane patch becomes partially or completely detached and remains detached, insufficient drug delivery occurs. o A patch should not be re-applied if it is no longer sticky, becomes stuck to itself or another surface, has other material stuck to it, or has become loose or fallen off before.
If a patch cannot be re-applied, a new patch should be applied immediately. Supplemental adhesives or wraps should not be used. o A woman may not be protected from pregnancy if a patch is partially or completely detached for ≥ 24 hours (or if the woman is not sure how long the patch has been detached). She should start a new cycle immediately by applying a new patch.
Back-up contraception, such as a condom and spermicide or diaphragm and spermicide, must be used for the first week of the new cycle. The brands listed are trademarks of their respective owners.
🍼 Nursing Mothers ▾
8.3Nursing Mothers The effects of Xulane in nursing mothers have not been evaluated and are unknown. When possible, advise the nursing mother to use other forms of contraception until she has completely weaned her child. Estrogen-containing CHCs can reduce milk production in breastfeeding mothers.
This is less likely to occur once breastfeeding is well-established; however, it can occur at any time in some women. Small amounts of contraceptive steroids and/or metabolites are present in breast milk.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption The systemic delivery rate of NGMN and EE from norelgestromin and ethinyl estradiol transdermal system is approximately 150 mcg of NGMN and 35 mcg of EE per day based on a comparative analysis with intravenous (IV) data. Following a single application of norelgestromin and ethinyl estradiol transdermal system, both NGMN and EE reach a plateau by approximately 48 hours. Pooled data from the 3 clinical studies have demonstrated that steady state is reached within 2 weeks of application.
In one of the clinical studies, C ss concentrations across all subjects ranged from 0.305 to 1.53 ng/mL for NGMN and from 23 to 137 pg/mL for EE. Absorption of NGMN and EE following application of norelgestromin and ethinyl estradiol transdermal system to the buttock, upper outer arm, abdomen and upper torso (excluding breast) was examined. While absorption from the abdomen was slightly lower than from other sites, absorption from these anatomic sites was considered to be therapeutically equivalent.
The mean (%CV) PK parameters C ss and AUC 0-168 for NGMN and EE following a single buttock application of norelgestromin and ethinyl estradiol transdermal system are summarized in Table 5. In multiple dose studies, AUC 0-168 for NGMN and EE was found to increase over time (Table 5). In a three-cycle study, these PK parameters reached steady state conditions during Cycle 3 (Figures 3 and 4) .
Upon removal of the patch, serum levels of EE and NGMN reach very low or non-measurable levels within 3 days. Table 5: Mean (%CV * ) PK Parameters of NGMN and EE Following Three Consecutive Cycles of Norelgestromin and Ethinyl Estradiol Transdermal System Wear on the Buttock nc = not calculated, * %CV is % of Coefficient of variation = 100 (standard deviation/mean) Analyte Parameter Cycle 1 Cycle 3 Cycle 3 Cycle 3 Week 1 Week 1 Week 2 Week 3 NGMN C ss (ng/mL) 0.70 (39.4) 0.70 (41.8) 0.80 (28.7) 0.70 (45.3) AUC 0-168 (ng·h/mL) 107 (44.2) 105 (43.2) 132 (43.4) 120 (43.9) t 1/2 (h) nc nc nc 32.1 (40.3) EE C ss (pg/mL) 46.4 (38.5) 47.6 (36.4) 59.0 (42.5) 49.6 (54.4) AUC 0-168 (pg·h/mL) 6796 (39.3) 7160 (40.4) 10054 (41.8) 8840 (58.6) t 1/2 (h) nc nc nc 21.0 (43.2) Figure 3: Mean Serum NGMN Concentrations (ng/mL) in Healthy Female Volunteers Following Application of Norelgestromin and Ethinyl Estradiol Transdermal System on the Buttock for Three Consecutive Cycles (Vertical arrow indicates time of patch removal) Figure 4: Mean Serum EE Concentrations (pg/mL) in Healthy Female Volunteers Following Application of Norelgestromin and Ethinyl Estradiol Transdermal System on the Buttock for Three Consecutive Cycles (Vertical arrow indicates time of patch removal.) The absorption of NGMN and EE following application of norelgestromin and ethinyl estradiol transdermal system was studied under conditions encountered in a health club (sauna, whirlpool and treadmill) and in a cold water bath.
The results indicated that for NGMN, there were no significant treatment effects on C ss or AUC when compared to normal wear. For EE, increased exposures were observed due to sauna, whirlpool and treadmill. There was no significant effect of cold water on these parameters.
Results from a study of consecutive norelgestromin and ethinyl estradiol transdermal system wear for 7 days and 10 days indicated that serum concentrations of NGMN and EE dropped slightly during the first 6 hours after the patch replacement, and recovered within 12 hours. By Day 10 of patch administration, both NGMN and EE concentrations had decreased by approximately 25% when compared to Day 7 concentrations. Figure 2: Mean Serum NGMN Concentrations (ng/mL) in Healthy Female Volunteers Following Application of Norelgestromin and Ethinyl Estradiol Transdermal System on the Buttock for Three Consecutive Cycles (Vertical arrow indicates time of patch removal) Figure 3: Mean Serum EE Concentrations (pg/mL) in Healthy Female Volunteers Following Application of Norelgestromin and Ethinyl Estradi… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics One clinical trial assessed the return of hypothalamic-pituitary-ovarian axis function post-therapy and found that follicle-stimulating hormone (FSH), luteinizing hormone (LH), and estradiol mean values, though suppressed during therapy, returned to near baseline values during the 6 weeks post-therapy.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES In 3 large clinical trials lasting 12 months, in North America, Europe and South Africa, 3,330 women (ages 18 to 45) completed 22,155 cycles of norelgestromin and ethinyl estradiol transdermal system use, the pregnancy rate in women aged 18 to 35 years was 1.07 (95% confidence interval 0.60, 1.76) per 100 woman-years of norelgestromin and ethinyl estradiol transdermal system use. The racial distribution was 91% Caucasian, 4.9% Black, 1.6% Asian, and 2.4% Other. With respect to weight, 5 of the 15 pregnancies reported with norelgestromin and ethinyl estradiol transdermal system use were among women with a baseline body weight ≥ 198 lbs., which constituted < 3% of the study population.
The greater proportion of pregnancies among women at or above 198 lbs. was statistically significant and suggests that norelgestromin and ethinyl estradiol transdermal system may be less effective in these women. Patch Adhesion In the clinical trials with norelgestromin and ethinyl estradiol transdermal system, approximately 2% of the cumulative number of patches completely detached and 3% partially detached. The proportion of subjects with at least one patch that completely detached ranged from 2% to 6%, with a reduction from Cycle 1 (6%) to Cycle 13 (2%).
For instructions on how to manage detachment of patches, refer to Dosage and Administration (2) .
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility See Warnings and Precautions (5.3 , 5.12) and Use in Specific Populations (8.1) . Norelgestromin was tested in in vitro mutagenicity assays (bacterial plate incorporation mutation assay, CHO/HGPRT mutation assay, chromosomal aberration assay using cultured human peripheral lymphocytes) and in one in vivo test (rat micronucleus assay) and found to have no genotoxic potential.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility See Warnings and Precautions (5.3 , 5.12) and Use in Specific Populations (8.1) . Norelgestromin was tested in in vitro mutagenicity assays (bacterial plate incorporation mutation assay, CHO/HGPRT mutation assay, chromosomal aberration assay using cultured human peripheral lymphocytes) and in one in vivo test (rat micronucleus assay) and found to have no genotoxic potential.
📄 Patient Package Insert ▾
PATIENT INFORMATION XULANE ® [zooʹ lane] (norelgestromin and ethinyl estradiol transdermal system) What is the most important information I should know about XULANE? Do not use XULANE if you smoke cigarettes and are over 35 years old. Smoking increases your risk of serious cardiovascular side effects from hormonal birth control methods, including death from heart attack, blood clots or stroke.
This risk increases with age and the number of cigarettes you smoke. Do not use XULANE if you have an increased risk for blood clots. Do not use XULANE if your Body Mass Index (BMI) is 30 kg/m 2 or more.
Women with a BMI of 30 kg/m 2 or more who use Xulane may be at a higher risk for developing blood clots compared to women with a BMI lower than 30 kg/m 2 . Hormonal birth control methods help to lower the chances of becoming pregnant. They do not protect against HIV infection (AIDS) and other sexually transmitted infections.
What is XULANE? XULANE is a birth control patch for women with a BMI less than 30 kg/m 2 . It contains two female hormones, an estrogen called ethinyl estradiol, and a progestin called norelgestromin.
Hormones from XULANE get into the blood stream and are processed by the body differently than hormones from birth control pills. You will be exposed to about 60% more estrogen if you use XULANE than if you use a typical birth control pill containing 35 micrograms of estrogen. In general, increased estrogen may increase the risk of side effects.
How well does XULANE work? Your chance of getting pregnant depends on how well you follow the directions for using XULANE. The better you follow the directions, the less chance you have of getting pregnant.
In clinical studies, 1 to 2 out of 100 women got pregnant during the first year that they used the norelgestromin and ethinyl estradiol transdermal system. XULANE may not be as effective in women weighing more than 198 lbs. (90 kg).
If you weigh more than 198 lbs. (90 kg), talk to your healthcare provider about which method of birth control is right for you. The following chart shows the chance of getting pregnant for women who use different methods of birth control.
Each box on the chart contains a list of birth control methods that are similar in effectiveness. The most effective methods are at the top of the chart. The box on the bottom of the chart shows the chance of getting pregnant for women who do not use birth control and are trying to get pregnant.
Do not use XULANE if you: • smoke and are over 35 years old • have or have had blood clots in your arms, legs, eyes or lungs • have an inherited problem that makes your blood clot more than normal • have had a stroke • have had a heart attack • have certain heart valve problems or heart rhythm problems that can cause blood clots to form in the heart • have high blood pressure that medicine cannot control • have diabetes with kidney, eye, nerve, or blood vessel damage • have had certain kinds of severe migraine headaches with aura, numbness, weakness or changes in vision, or have any migraine headaches if you are over age 35 • have a BMI of 30 or more • have liver disease, including liver tumors, take any Hepatitis C drug combination containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir.
This may increase levels of the liver enzyme “alanine aminotransferase” (ALT) in the blood. • have unexplained vaginal bleeding • are pregnant or think you may be pregnant. However, XULANE is not known to cause birth defects when used by accident during pregnancy. • have had breast cancer or any cancer that is sensitive to female hormones Hormonal birth control methods may not be a good choice for you if you have ever had jaundice (yellowing of the skin or eyes) caused by pregnancy or related to previous use of hormonal birth control.
Tell your healthcare provider if you have ever had any of the above conditions. Your healthcare provider may recommend another method of birth control. Before you use XULANE tell your healthc… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Warnings and Precautions ( 5.12 ) 3/2022
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL – 150/35 mcg per day NDC 0378-3340-53 Contents: 3 Transdermal Systems | Rx only Xulane® (norelgestromin and ethinyl estradiol transdermal system) 150/35 mcg per day Each 14 cm 2 system contains 4.86 mg norelgestromin, USP and 0.53 mg ethinyl estradiol, USP. The inactive components are crospovidone, dipropylene glycol, fluoropolymer coated polyester film, light mineral oil, non-woven polyester fabric, oleyl alcohol, polyethylene/polyester film and polyisobutene adhesive. Each patch is printed with brown ink.
This product is intended to prevent pregnancy. It does not protect against HIV infection (AIDS) and other sexually transmitted diseases. For Transdermal Use Only See patient instructions.
Apply immediately upon removal from pouch. Each transdermal system is intended to be worn 7 days as prescribed. Package not child-resistant.
Keep out of reach of children. Do not store unpouched. Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Manufactured for: Mylan Pharmaceuticals Inc.
Morgantown, WV 26505 U.S.A. Mylan.com M3340:53:3C:R15 Xulane Transdermal System 150/35 mcg per day Carton