
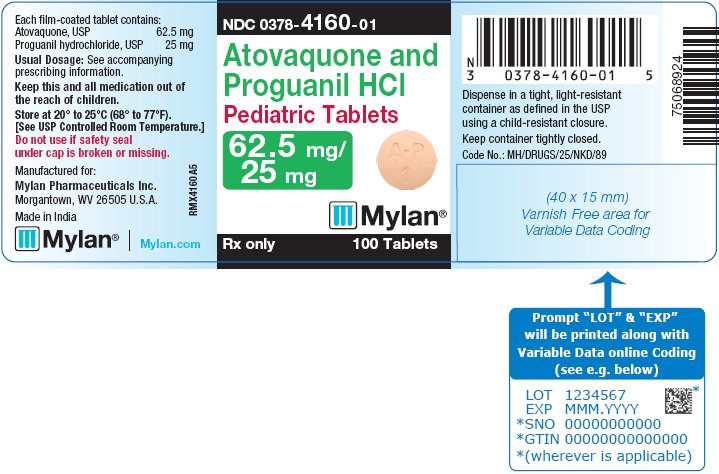
Atovaquone and Proguanil Hydrochloride 62.5 mg; 25 mg Tablet, Film Coated, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Antimalarial class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Atovaquone and proguanil is used to prevent or treat certain kinds of malaria infections (a serious infection that is spread by mosquitoes in certain parts of the world). Atovaquone and proguanil is in a class of medications called antimalarials. It works by killing the organisms that cause malaria.
Read the full MedlinePlus article ↗- It actually does both, depending on why your doctor prescribed it. If you're traveling to an area where malaria is common, you take it starting a day or two before you leave, every...
- What exactly does this medicine do — does it prevent malaria or treat it?
- Yes, it genuinely matters. One of the two ingredients, atovaquone, is barely absorbed on an empty stomach — fat in food dramatically increases how much gets into your bloodstream,...
- Why do I have to take it with food? Does it really matter?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII LQA7B6G8JG
A synthetic polymer made by combining water-soluble compounds. It acts as a surfactant and solubilizer to help mix oil and water-based ingredients, improving the medicine's texture and how active ingredients dissolve.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $1.040 | $104.00 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $1.40 | $139.70 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $2.82 | $282.02 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Atovaquone and Proguanil Hydrochloride 62.5 mg/1; 25 mgthis 00378-4160-01 | Mylan | 100 tablets | $1.040 | AB | Availability likely | — |
| Atovaquone and Proguanil Hydrochloride Pediatric 62.5 mg/1; 25 mg 68462-0402-01 | Glenmark | 100 tablets | $1.040 | AB | Availability likely | — |
| Malarone 62.5 mg/1; 25 mg 00173-0676-01 | GlaxoSmithKline | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00378-4160-01 You're viewing this | 100 TABLET, FILM COATED in 1 BOTTLE, PLASTIC (0378-4160-01) | 2014-05-28 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Atovaquone and proguanil hydrochloride tablets are an antimalarial indicated for: • prophylaxis of Plasmodium falciparum malaria, including in areas where chloroquine resistance has been reported. ( 1.1 ) • treatment of acute, uncomplicated P. falciparum malaria. ( 1.2 )
1.1Prevention of Malaria Atovaquone and proguanil hydrochloride tablets are indicated for the prophylaxis of Plasmodium falciparum malaria, including in areas where chloroquine resistance has been reported.
1.2Treatment of Malaria Atovaquone and proguanil hydrochloride tablets are indicated for the treatment of acute, uncomplicated P. falciparum malaria. Atovaquone and proguanil hydrochloride tablets have been shown to be effective in regions where the drugs chloroquine, halofantrine, mefloquine, and amodiaquine may have unacceptable failure rates, presumably due to drug resistance.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The daily dose should be taken at the same time each day with food or a milky drink. In the event of vomiting within 1 hour after dosing, a repeat dose should be taken. Atovaquone and proguanil hydrochloride tablets may be crushed and mixed with condensed milk just prior to administration to patients who may have difficulty swallowing tablets. • Atovaquone and proguanil hydrochloride tablets should be taken with food or a milky drink.
Prophylaxis ( 2.1 ) : • Start prophylaxis 1 or 2 days before entering a malaria-endemic area and continue daily during the stay and for 7 days after return. • Adults: One adult strength tablet per day. • Pediatric Patients: Dosage based on body weight (see Table 1). Treatment ( 2.2 ) : • Adults: Four adult strength tablets as a single daily dose for 3 days. • Pediatric Patients: Dosage based on body weight (see Table 2). Renal Impairment ( 2.3 ) : • Do not use for prophylaxis of malaria in patients with severe renal impairment. • Use with caution for treatment of malaria in patients with severe renal impairment.
2.1Prevention of Malaria Start prophylactic treatment with atovaquone and proguanil hydrochloride tablets 1 or 2 days before entering a malaria-endemic area and continue daily during the stay and for 7 days after return. Adults One atovaquone and proguanil hydrochloride tablet (adult strength = 250 mg atovaquone/100 mg proguanil hydrochloride) per day. Pediatric Patients The dosage for prevention of malaria in pediatric patients is based upon body weight (Table 1).
Table 1. Dosage for Prevention of Malaria in Pediatric Patients Weight (kg) Atovaquone/ Proguanil HCl Total Daily Dose Dosage Regimen 11-20 62.5 mg/25 mg 1 atovaquone and proguanil hydrochloride pediatric tablet daily 21-30 125 mg/50 mg 2 atovaquone and proguanil hydrochloride pediatric tablets as a single daily dose 31-40 187.5 mg/75 mg 3 atovaquone and proguanil hydrochloride pediatric tablets as a single daily dose > 40 250 mg/100 mg 1 atovaquone and proguanil hydrochloride tablet (adult strength) as a single daily dose
2.2Treatment of Acute Malaria Adults Four atovaquone and proguanil hydrochloride tablets (adult strength; total daily dose 1 g atovaquone/400 mg proguanil hydrochloride) as a single daily dose for 3 consecutive days. Pediatric Patients The dosage for treatment of acute malaria in pediatric patients is based upon body weight (Table 2). Table 2.
Dosage for Treatment of Acute Malaria in Pediatric Patients Weight (kg) Atovaquone/ Proguanil HCl Total Daily Dose Dosage Regimen 5-8 125 mg/50 mg 2 atovaquone and proguanil hydrochloride pediatric tablets daily for 3 consecutive days 9-10 187.5 mg/75 mg 3 atovaquone and proguanil hydrochloride pediatric tablets daily for 3 consecutive days 11-20 250 mg/100 mg 1 atovaquone and proguanil hydrochloride tablet (adult strength) daily for 3 consecutive days 21-30 500 mg/200 mg 2 atovaquone and proguanil hydrochloride tablets (adult strength) as a single daily dose for 3 consecutive days 31-40 750 mg/300 mg 3 atovaquone and proguanil hydrochloride tablets (adult strength) as a single daily dose for 3 consecutive days > 40 1 g/400 mg 4 atovaquone and proguanil hydrochloride tablets (adult strength) as a single daily dose for 3 consecutive days
2.3Renal Impairment Do not use atovaquone and proguanil hydrochloride tablets for malaria prophylaxis in patients with severe renal impairment (creatinine clearance < 30 mL/min) [see Contraindications (4) ] . Use with caution for the treatment of malaria in patients with severe renal impairment, only if the benefits of the 3-day treatment regimen outweigh the potential risks associated with increased drug exposure. No dosage adjustments are needed in patients with mild (creatinine clearance 50 to 80 mL/min) or moderate (creatinine clearance 30 to 50 mL/min) renal impairment. [See Clinical Pharmacology (12.3) .]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Atovaquone and Proguanil Hydrochloride Tablets are available containing 250 mg of atovaquone, USP and 100 mg of proguanil hydrochloride, USP. • The 250 mg/100 mg tablets are buff, film-coated, round, unscored tablets debossed with A-P over 2 on one side of the tablet and M on the other side. Atovaquone and Proguanil Hydrochloride Pediatric Tablets are available containing 62.5 mg of atovaquone, USP and 25 mg of proguanil hydrochloride, USP. • The 62.5 mg/25 mg tablets are buff, film-coated, round, unscored tablets debossed with A-P over 1 on one side of the tablet and M on the other side. • Tablets (adult strength): 250 mg atovaquone and 100 mg proguanil hydrochloride.
( 3 ) • Pediatric tablets: 62.5 mg atovaquone and 25 mg proguanil hydrochloride. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS • Atovaquone and proguanil hydrochloride tablets are contraindicated in individuals with known hypersensitivity reactions (e.g., anaphylaxis, erythema multiforme or Stevens-Johnson syndrome, angioedema, vasculitis) to atovaquone or proguanil hydrochloride or any component of the formulation. • Atovaquone and proguanil hydrochloride tablets are contraindicated for prophylaxis of P. falciparum malaria in patients with severe renal impairment (creatinine clearance < 30 mL/min) because of pancytopenia in patients with severe renal impairment treated with proguanil [see Use in Specific Populations (8.6) , Clinical Pharmacology (12.3) ] . • Known serious hypersensitivity reactions to atovaquone or proguanil hydrochloride or any component of the formulation.
( 4 ) • Prophylaxis of P. falciparum malaria in patients with severe renal impairment (creatinine clearance < 30 mL/min). ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Atovaquone absorption may be reduced in patients with diarrhea or vomiting. If used in patients who are vomiting, parasitemia should be closely monitored and the use of an antiemetic considered. In patients with severe or persistent diarrhea or vomiting, alternative antimalarial therapy may be required.
( 5.1 ) • In mixed P. falciparum and Plasmodium vivax infection, P. vivax relapse occurred commonly when patients were treated with atovaquone and proguanil hydrochloride tablets alone. ( 5.2 ) • In the event of recrudescent P. falciparum infections after treatment or prophylaxis failure, patients should be treated with a different blood schizonticide. ( 5.2 ) • Elevated liver laboratory tests and cases of hepatitis and hepatic failure requiring liver transplantation have been reported with prophylactic use.
( 5.3 ) • Atovaquone and proguanil hydrochloride tablets have not been evaluated for the treatment of cerebral malaria or other severe manifestations of complicated malaria. Patients with severe malaria are not candidates for oral therapy. ( 5.4 )
5.1Vomiting and Diarrhea Absorption of atovaquone may be reduced in patients with diarrhea or vomiting. If atovaquone and proguanil hydrochloride tablets are used in patients who are vomiting, parasitemia should be closely monitored and the use of an antiemetic considered [see Dosage and Administration (2) ]. Vomiting occurred in up to 19% of pediatric patients given treatment doses of atovaquone and proguanil hydrochloride tablets.
In the controlled clinical trials, 15.3% of adults received an antiemetic when they received atovaquone/proguanil and 98.3% of these patients were successfully treated. In patients with severe or persistent diarrhea or vomiting, alternative antimalarial therapy may be required.
5.2Relapse of Infection In mixed P. falciparum and Plasmodium vivax infections, P. vivax parasite relapse occurred commonly when patients were treated with atovaquone and proguanil hydrochloride tablets alone. In the event of recrudescent P. falciparum infections after treatment with atovaquone and proguanil hydrochloride tablets or failure of chemoprophylaxis with atovaquone and proguanil hydrochloride tablets, patients should be treated with a different blood schizonticide.
5.3Hepatotoxicity Elevated liver laboratory tests and cases of hepatitis and hepatic failure requiring liver transplantation have been reported with prophylactic use of atovaquone and proguanil hydrochloride tablets.
5.4Severe or Complicated Malaria Atovaquone and proguanil hydrochloride tablets have not been evaluated for the treatment of cerebral malaria or other severe manifestations of complicated malaria, including hyperparasitemia, pulmonary edema, or renal failure. Patients with severe malaria are not candidates for oral therapy.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS • Prophylaxis: Common adverse reactions (≥ 4%) in adults were diarrhea, dreams, oral ulcers, and headache; these events occurred in a similar or lower proportion of subjects receiving atovaquone and proguanil hydrochloride tablets than an active comparator. Common adverse reactions (≥ 5%) in pediatric patients included abdominal pain, headache, cough, and vomiting. ( 6.1 ) • Treatment: Common adverse reactions (≥ 5%) in adolescents and adults were abdominal pain, nausea, vomiting, headache, diarrhea, asthenia, anorexia, and dizziness.
Common adverse reactions (≥ 6%) in pediatric patients included vomiting, pruritus, and diarrhea. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Mylan at 1-877-446-3679 (1-877-4-INFO-RX) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in practice. Because atovaquone and proguanil hydrochloride tablets contain atovaquone and proguanil hydrochloride, the type and severity of adverse reactions associated with each of the compounds may be expected. The lower prophylactic doses of atovaquone and proguanil hydrochloride tablets were better tolerated than the higher treatment doses.
Prophylaxis of P.falciparum Malaria In 3 clinical trials (2 of which were placebo-controlled) 381 adults (mean age: 31 years) received atovaquone and proguanil hydrochloride tablets for the prophylaxis of malaria; the majority of adults were black (90%) and 79% were male. In a clinical trial for the prophylaxis of malaria, 125 pediatric patients (mean age: 9 years) received atovaquone and proguanil hydrochloride tablets; all subjects were black and 52% were male. Adverse experiences reported in adults and pediatric patients considered attributable to therapy occurred in similar proportions of subjects receiving atovaquone and proguanil hydrochloride tablets or placebo in all studies.
Prophylaxis with atovaquone and proguanil hydrochloride tablets was discontinued prematurely due to a treatment-related adverse experience in 3 of 381 (0.8%) adults and 0 of 125 pediatric patients. In a placebo-controlled study of malaria prophylaxis with atovaquone and proguanil hydrochloride tablets involving 330 pediatric patients (aged 4 to 14 years) in Gabon, a malaria-endemic area, the safety profile of atovaquone and proguanil hydrochloride tablets was consistent with that observed in the earlier prophylactic studies in adults and pediatric patients.
The most common treatment-emergent adverse events with atovaquone and proguanil hydrochloride tablets were abdominal pain (13%), headache (13%), and cough (10%). Abdominal pain (13% vs. 8%) and vomiting (5% vs.
3%) were reported more often with atovaquone and proguanil hydrochloride tablets than with placebo. No patient withdrew from the study due to an adverse experience with atovaquone and proguanil hydrochloride tablets. No routine laboratory data were obtained during this study.
Non-immune travelers visiting a malaria-endemic area received atovaquone and proguanil hydrochloride tablets (n = 1,004) for prophylaxis of malaria in 2 active-controlled clinical trials. In one study (n = 493), the mean age of subjects was 33 years and 53% were male; 90% of subjects were white, 6% of subjects were black, and the remaining were of other racial/ethnic groups. In the other study (n = 511), the mean age of subjects was 36 years and 51% were female; the majority of subjects (97%) were white.
Adverse experiences occurred in a similar or lower proportion of subjects receiving atovaquone and proguanil hydrochloride tablets than an active comparator (Table 3). Fewer neuropsychiatric adverse experiences occurred in subjects who received atovaquone and proguanil hydrochloride tablets than mefloquine.…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Administration with rifampin or rifabutin is known to reduce atovaquone concentrations; concomitant use with atovaquone and proguanil hydrochloride tablets is not recommended. ( 7.1 ) • Proguanil may potentiate anticoagulant effect of warfarin and other coumarin-based anticoagulants. Caution advised when initiating or withdrawing atovaquone and proguanil hydrochloride tablets in patients on anticoagulants; coagulation tests should be closely monitored.
( 7.2 ) • Tetracycline may reduce atovaquone concentrations; parasitemia should be closely monitored. ( 7.3 )
7.1Rifampin/Rifabutin Concomitant administration of rifampin or rifabutin is known to reduce atovaquone concentrations [see Clinical Pharmacology (12.3) ] . The concomitant administration of atovaquone and proguanil hydrochloride tablets and rifampin or rifabutin is not recommended.
7.2Anticoagulants Proguanil may potentiate the anticoagulant effect of warfarin and other coumarin-based anticoagulants. The mechanism of this potential drug interaction has not been established. Caution is advised when initiating or withdrawing malaria prophylaxis or treatment with atovaquone and proguanil hydrochloride tablets in patients on continuous treatment with coumarin-based anticoagulants.
When these products are administered concomitantly, coagulation tests should be closely monitored.
7.3Tetracycline Concomitant treatment with tetracycline has been associated with a reduction in plasma concentrations of atovaquone [see Clinical Pharmacology (12.3) ] . Parasitemia should be closely monitored in patients receiving tetracycline.
7.4Metoclopramide While antiemetics may be indicated for patients receiving atovaquone and proguanil hydrochloride tablets, metoclopramide may reduce the bioavailability of atovaquone and should be used only if other antiemetics are not available [see Clinical Pharmacology (12.3) ] .
7.5Indinavir Concomitant administration of atovaquone and indinavir did not result in any change in the steady-state AUC and C max of indinavir but resulted in a decrease in the C trough of indinavir [see Clinical Pharmacology (12.3) ] . Caution should be exercised when prescribing atovaquone with indinavir due to the decrease in trough concentrations of indinavir.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Renal impairment: contraindicated for prophylaxis of P. falciparum malaria in patients with severe renal impairment. ( 8.6 )
8.1Pregnancy Risk Summary Available data from published literature and postmarketing experience with use of atovaquone and proguanil hydrochloride tablets in pregnant women are insufficient to identify a drug-associated risk for major birth defects, miscarriage, or adverse maternal or fetal outcomes. The proguanil component of atovaquone and proguanil hydrochloride tablets acts to inhibit parasitic dihydrofolate reductase; however, pregnant women and females of reproductive potential should continue folate supplementation to prevent neural tube defects [see Clinical Pharmacology (12.4) ] .
Pregnant women with malaria are at increased risk for adverse pregnancy outcomes (see Clinical Considerations ) . Atovaquone administered by oral gavage to pregnant rats and rabbits during the period of organogenesis was not associated with fetal malformations at plasma exposures approximately 7 times and equal to, respectively, the estimated human exposure for the treatment of malaria based on AUC. Proguanil administered to pregnant rats and rabbits during the period of organogenesis was not associated with embryo-fetal toxicity at maternally toxic plasma exposures approximately 0.07 and 0.8 times, respectively, the estimated human exposure for treatment of malaria based on AUC (see Data ) .
The combination of atovaquone and proguanil hydrochloride given orally by gavage during the period of organogenesis was not associated with embryo-fetal developmental effects in pregnant rats or rabbits at atovaquone:proguanil hydrochloride doses of 50:20 mg/kg/day and 100:40 mg/kg/day, respectively (1.7 and 0.1 times and 0.3 and 0.5 times, respectively, the estimated human exposure for treatment of malaria). In a pre- and post-natal study with atovaquone and another pre- and post-natal study with proguanil, neither compound impaired the growth, development, or reproductive ability of first generation offspring at maternal AUC exposures of approximately 7.3 and 0.04 times, respectively, the estimated human AUC exposure for treatment of malaria (see Data ) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Malaria during pregnancy increases the risk for adverse pregnancy outcomes, including maternal anemia, prematurity, spontaneous abortion, and stillbirth. Data Animal Data Atovaquone Atovaquone administered in oral doses of 250, 500, and 1,000 mg/kg/day during organogenesis (Gestation Day [GD] 6 to GD15) in pregnant rats did not cause maternal or embryo-fetal toxicity at doses up to 1,000 mg/kg/day corresponding to maternal plasma exposures up to 7.3 times the estimated human exposure for the treatment of malaria based on AUC.
In pregnant rabbits, atovaquone administered in oral doses of 300, 600, and 1,200 mg/kg/day by gavage during organogenesis (GD6 to GD18) was associated with decreased fetal body length at a maternally toxic dose of 1,200 mg/kg/day corresponding to plasma exposures that were approximately 1.3 times the estimated human exposure during treatment of malaria based on AUC. In a pre- and post-natal study in rats, atovaquone administered in oral doses of 250, 500, and 1,000 mg/kg/day from GD15 until Lactation Day (LD) 20 did not impair the growth or developmental effects in first generation offspring at doses up to 1,000 mg/kg/day corresponding to AUC exposures of approximately 7.3 times the estimated human exposure during treatment of malaria.
Atovaquone crossed the placenta and was present in f…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from published literature and postmarketing experience with use of atovaquone and proguanil hydrochloride tablets in pregnant women are insufficient to identify a drug-associated risk for major birth defects, miscarriage, or adverse maternal or fetal outcomes. The proguanil component of atovaquone and proguanil hydrochloride tablets acts to inhibit parasitic dihydrofolate reductase; however, pregnant women and females of reproductive potential should continue folate supplementation to prevent neural tube defects [see Clinical Pharmacology (12.4) ] .
Pregnant women with malaria are at increased risk for adverse pregnancy outcomes (see Clinical Considerations ) . Atovaquone administered by oral gavage to pregnant rats and rabbits during the period of organogenesis was not associated with fetal malformations at plasma exposures approximately 7 times and equal to, respectively, the estimated human exposure for the treatment of malaria based on AUC. Proguanil administered to pregnant rats and rabbits during the period of organogenesis was not associated with embryo-fetal toxicity at maternally toxic plasma exposures approximately 0.07 and 0.8 times, respectively, the estimated human exposure for treatment of malaria based on AUC (see Data ) .
The combination of atovaquone and proguanil hydrochloride given orally by gavage during the period of organogenesis was not associated with embryo-fetal developmental effects in pregnant rats or rabbits at atovaquone:proguanil hydrochloride doses of 50:20 mg/kg/day and 100:40 mg/kg/day, respectively (1.7 and 0.1 times and 0.3 and 0.5 times, respectively, the estimated human exposure for treatment of malaria). In a pre- and post-natal study with atovaquone and another pre- and post-natal study with proguanil, neither compound impaired the growth, development, or reproductive ability of first generation offspring at maternal AUC exposures of approximately 7.3 and 0.04 times, respectively, the estimated human AUC exposure for treatment of malaria (see Data ) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Malaria during pregnancy increases the risk for adverse pregnancy outcomes, including maternal anemia, prematurity, spontaneous abortion, and stillbirth. Data Animal Data Atovaquone Atovaquone administered in oral doses of 250, 500, and 1,000 mg/kg/day during organogenesis (Gestation Day [GD] 6 to GD15) in pregnant rats did not cause maternal or embryo-fetal toxicity at doses up to 1,000 mg/kg/day corresponding to maternal plasma exposures up to 7.3 times the estimated human exposure for the treatment of malaria based on AUC.
In pregnant rabbits, atovaquone administered in oral doses of 300, 600, and 1,200 mg/kg/day by gavage during organogenesis (GD6 to GD18) was associated with decreased fetal body length at a maternally toxic dose of 1,200 mg/kg/day corresponding to plasma exposures that were approximately 1.3 times the estimated human exposure during treatment of malaria based on AUC. In a pre- and post-natal study in rats, atovaquone administered in oral doses of 250, 500, and 1,000 mg/kg/day from GD15 until Lactation Day (LD) 20 did not impair the growth or developmental effects in first generation offspring at doses up to 1,000 mg/kg/day corresponding to AUC exposures of approximately 7.3 times the estimated human exposure during treatment of malaria.
Atovaquone crossed the placenta and was present in fetal rat and rabbit tissue. Proguanil Proguanil administered orally to pregnant rats during organogenesis (GD6 to GD17) was not associated with fetal malfo…
🧒 Pediatric Use ▾
8.4Pediatric Use Prophylaxis of Malaria Safety and effectiveness have not been established in pediatric patients who weigh less than 11 kg. The efficacy and safety of atovaquone and proguanil hydrochloride tablets have been established for the prophylaxis of malaria in controlled trials involving pediatric patients weighing 11 kg or more [see Clinical Studies (14.1) ] . Treatment of Malaria Safety and effectiveness have not been established in pediatric patients who weigh less than 5 kg.
The efficacy and safety of atovaquone and proguanil hydrochloride tablets for the treatment of malaria have been established in controlled trials involving pediatric patients weighing 5 kg or more [see Clinical Studies (14.2) ] .
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of atovaquone and proguanil hydrochloride tablets did not include sufficient numbers of subjects aged 65 years and older to determine whether they respond differently from younger subjects. In general, dose selection for an elderly patient should be cautious, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, the higher systemic exposure to cycloguanil, and the greater frequency of concomitant disease or other drug therapy [see Clinical Pharmacology (12.3) ].
🆘 Overdosage ▾
10 OVERDOSAGE There is no information on overdoses of atovaquone and proguanil hydrochloride tablets substantially higher than the doses recommended for treatment. There is no known antidote for atovaquone, and it is currently unknown if atovaquone is dialyzable. Overdoses up to 31,500 mg of atovaquone have been reported.
In one such patient who also took an unspecified dose of dapsone, methemoglobinemia occurred. Rash has also been reported after overdose. Overdoses of proguanil hydrochloride as large as 1,500 mg have been followed by complete recovery, and doses as high as 700 mg twice daily have been taken for over 2 weeks without serious toxicity.
Adverse experiences occasionally associated with proguanil hydrochloride doses of 100 to 200 mg/day, such as epigastric discomfort and vomiting, would be likely to occur with overdose. There are also reports of reversible hair loss and scaling of the skin on the palms and/or soles, reversible aphthous ulceration, and hematologic side effects.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Atovaquone and proguanil hydrochloride tablets, a fixed-dose combination of atovaquone and proguanil hydrochloride, are an antimalarial agent [see Microbiology (12.4) ] .
12.2Pharmacodynamics Cardiac Effects The effect of atovaquone and proguanil hydrochloride tablets on the QT interval is unknown in humans.
12.3Pharmacokinetics Absorption Atovaquone is a highly lipophilic compound with low aqueous solubility. The bioavailability of atovaquone shows considerable inter-individual variability. Effect of Food Atovaquone and proguanil hydrochloride tablets should be taken with food or a milky drink.
Dietary fat taken with atovaquone increases the rate and extent of absorption, increasing AUC 2 to 3 times and C max 5 times over fasting. The absolute bioavailability of the tablet formulation of atovaquone when taken with food is 23%. Distribution Atovaquone is highly protein bound (> 99%) over the concentration range of 1 to 90 mcg/mL.
A population pharmacokinetic analysis demonstrated that the apparent volume of distribution of atovaquone (V/F) in adult and pediatric patients after oral administration is approximately
8.8L/kg. Proguanil is 75% protein bound. A population pharmacokinetic analysis demonstrated that the apparent V/F of proguanil in adult and pediatric patients older than 15 years with body weights from 31 to 110 kg ranged from 1,617 to 2,502 L.
In pediatric patients 15 years and younger with body weights from 11 to 56 kg, the V/F of proguanil ranged from 462 to 966 L. In human plasma, the binding of atovaquone and proguanil was unaffected by the presence of the other. Elimination The elimination half-life of atovaquone is about 2 to 3 days in adult patients.
The elimination half-life of proguanil is 12 to 21 hours in both adult patients and pediatric patients, but may be longer in individuals who are slow metabolizers. The main routes of elimination are hepatic biotransformation and renal excretion. Metabolism In a study where 14 C-labeled atovaquone was administered to healthy volunteers, greater than 94% of the dose was recovered as unchanged atovaquone in the feces over 21 days.
There was little or no excretion of atovaquone in the urine (less than 0.6%). There is indirect evidence that atovaquone may undergo limited metabolism; however, a specific metabolite has not been identified. Between 40% to 60% of proguanil is excreted by the kidneys.
Proguanil is metabolized to cycloguanil (primarily via cytochrome P450 2C19 [CYP2C19] and 4-chlorophenylbiguanide. Excretion A population pharmacokinetic analysis in adult and pediatric patients showed that the apparent clearance (CL/F) of both atovaquone and proguanil is related to body weight. The values CL/F for both atovaquone and proguanil in subjects with body weight ≥ 11 kg are shown in Table 4.
Table 4. Apparent Clearance for Atovaquone and Proguanil in Patients as a Function of Body Weight Body Weight (kg) Atovaquone Proguanil n CL/F (L/hr) Mean ± SD SD = standard deviation. (range) n CL/F (L/hr) Mean ± SD (range) 11-20 kg 159 1.34 ± 0.63 (0.52-4.26) 146 29.5 ± 6.5 (10.3-48.3) 21-30 kg 117 1.87 ± 0.81 (0.52-5.38) 113 40.0 ± 7.5 (15.9-62.7) 31-40 kg 95 2.76 ± 2.07 (0.97-12.5) 91 49.5 ± 8.30 (25.8-71.5) > 40 kg 368 6.61 ± 3.92 (1.32-20.3) 282 67.9 ± 19.9 (14.0-145) The pharmacokinetics of atovaquone and proguanil in patients with body weight less than 11 kg have not been adequately characterized.
Special Populations Pediatric Patients The pharmacokinetics of proguanil and cycloguanil are similar in adult patients and pediatric patients. However, the elimination half-life of atovaquone is shorter in pediatric patients (1 to 2 days) than in adult patients (2 to 3 days). In clinical trials, plasma trough concentrations of atovaquone and proguanil in pediatric patients weighing 5 to 40 kg were within the range observed in adults after dosing by body weight.
Geriatric Patients In a single-dose study, the pharmacokinetics o…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Atovaquone and proguanil hydrochloride tablets, a fixed-dose combination of atovaquone and proguanil hydrochloride, are an antimalarial agent [see Microbiology (12.4) ] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Atovaquone and Proguanil Hydrochloride Tablets are available containing 250 mg of atovaquone, USP and 100 mg of proguanil hydrochloride, USP. The 250 mg/100 mg tablets are buff, film-coated, round, unscored tablets debossed with A-P over 2 on one side of the tablet and M on the other side. They are available as follows: NDC 0378-4162-01 bottles of 100 tablets Atovaquone and Proguanil Hydrochloride Pediatric Tablets are available containing 62.5 mg of atovaquone, USP and 25 mg of proguanil hydrochloride, USP.
The 62.5 mg/25 mg tablets are buff, film-coated, round, unscored tablets debossed with A-P over 1 on one side of the tablet and M on the other side. They are available as follows: NDC 0378-4160-01 bottles of 100 tablets Storage Conditions: Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure.
📋 Description ▾
11 DESCRIPTION Atovaquone and proguanil hydrochloride tablets (adult strength) and atovaquone and proguanil hydrochloride pediatric tablets, for oral administration, contain a fixed-dose combination of the antimalarial agents atovaquone and proguanil hydrochloride. The chemical name of atovaquone is 2-[ trans -4-( p -Chlorophenyl)cyclohexyl]-3-hydroxy-1,4-naphthoquinone. Atovaquone, USP is a yellow powder that is practically insoluble in water.
It has a molecular weight of 366.84 and the molecular formula C 22 H 19 ClO 3 . The compound has the following structural formula: The chemical name of proguanil hydrochloride is 1-(4-chlorophenyl)-5-(1-methylethyl)biguanide hydrochloride. Proguanil hydrochloride, USP is a white or almost white crystalline powder that is sparingly soluble in water.
It has a molecular weight of 290.19 and the molecular formula C 11 H 16 ClN 5 •HCl. The compound has the following structural formula: Each atovaquone and proguanil hydrochloride tablet (adult strength) contains 250 mg of atovaquone and 100 mg of proguanil hydrochloride and each atovaquone and proguanil hydrochloride pediatric tablet contains 62.5 mg of atovaquone and 25 mg of proguanil hydrochloride. The inactive ingredients in both tablets are black iron oxide, crospovidone, hypromellose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, poloxamer 188, polyethylene glycol, povidone, red iron oxide, titanium dioxide and yellow iron oxide.
Atovaquone Structural Formula Proguanil Hydrochloride Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Patients should be instructed: • to take atovaquone and proguanil hydrochloride tablets at the same time each day with food or a milky drink. • to take a repeat dose of atovaquone and proguanil hydrochloride tablets if vomiting occurs within 1 hour after dosing. • to take a dose as soon as possible if a dose is missed, then return to their normal dosing schedule. However, if a dose is skipped, the patient should not double the next dose. • that rare serious adverse events such as hepatitis, severe skin reactions, neurological events, and hematological events have been reported when atovaquone and proguanil hydrochloride tablets were used for the prophylaxis or treatment of malaria. • to consult a healthcare professional regarding alternative forms of prophylaxis if prophylaxis with atovaquone and proguanil hydrochloride tablets is prematurely discontinued for any reason. • that protective clothing, insect repellents, and bed nets are important components of malaria prophylaxis. • that no chemoprophylactic regimen is 100% effective; therefore, patients should seek medical attention for any febrile illness that occurs during or after return from a malaria-endemic area and inform their healthcare professional that they may have been exposed to malaria. • that falciparum malaria carries a higher risk of death and serious complications in pregnant women than in the general population.
Pregnant women anticipating travel to malarious areas should discuss the risks and benefits of such travel with their physicians. Manufactured for: Mylan Pharmaceuticals Inc. Morgantown, WV 26505 U.S.A.
Manufactured by: Mylan Laboratories Limited Hyderabad — 500 096, India Revised: 3/2019 75067629 MX:ATPRO:R4