
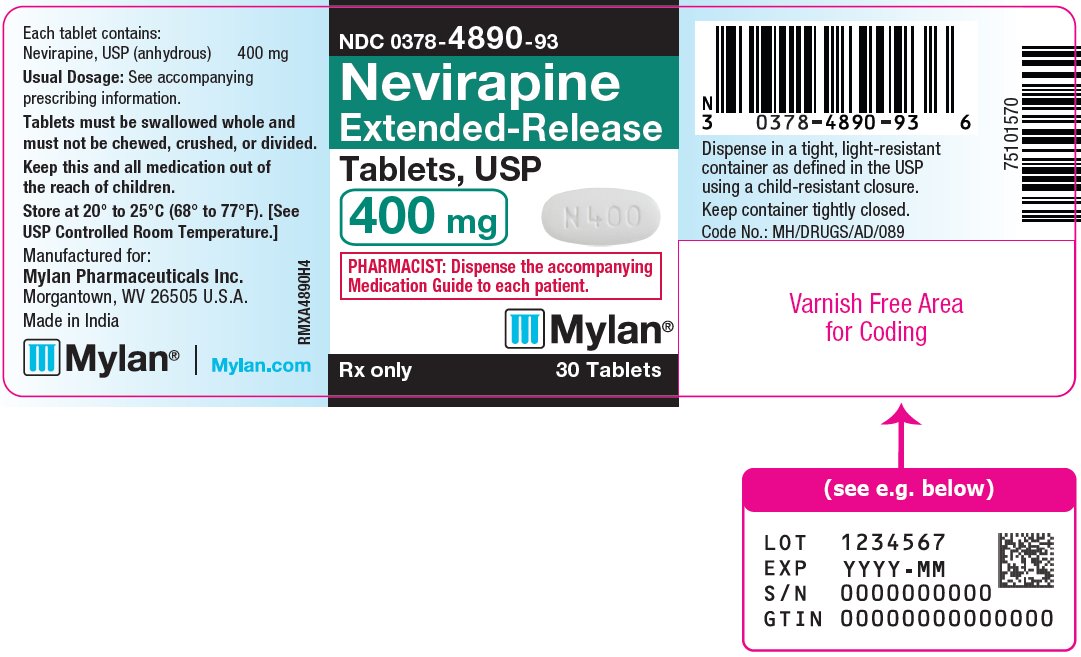
Nevirapine 400 mg Tablet, Extended Release, 30-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Human Immunodeficiency Virus 1 Non-Nucleoside Analog Reverse Transcriptase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Nevirapine is used to treat human immunodeficiency virus (HIV) infection. Nevirapine is in a class of medications called non-nucleoside reverse transcriptase inhibitors (NNRTIs). It works by decreasing the amount of HIV in the blood. Although nevirapine does not cure HIV, it may decrease your chance of developing acquired immunodeficiency syndrome (AIDS) and HIV-related illnesses. Taking these medications and making other life-style changes may decrease the risk of giving the HIV virus to other people.
Read the full MedlinePlus article ↗- Nevirapine is an antiviral drug that belongs to a class called NNRTIs — it works by blocking a key enzyme HIV needs to copy itself. But HIV is clever: if you only take one drug, th...
- What exactly is nevirapine and why do I need to take it with other HIV medicines?
- That first 14-day period at a once-daily lower dose is called the lead-in period, and it's actually really important — it's been shown to significantly reduce the chance of develop...
- Why do I have to start at a lower dose for the first two weeks?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Nevirapine — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 7CV7WJK4UI
Sodium stearyl fumarate is a synthetic compound made from stearyl alcohol and fumaric acid. It acts as a lubricant and glidant in tablets and capsules, helping ingredients flow smoothly during manufacturing and preventing sticking.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $1.521 | $45.64 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $5.07 | $152.12 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Nevirapine 400 mgthis 00378-4890-93 | Mylan | 30 tablets | $1.521 | AB | Availability likely | — |
| Nevirapine 400 mg 33342-0238-07 | Macleods | 30 tablets | $1.521 | AB | Availability likely | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00378-4890-93 You're viewing this | 30 TABLET, EXTENDED RELEASE in 1 BOTTLE, PLASTIC (0378-4890-93) | 2014-10-29 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: LIFE-THREATENING (INCLUDING FATAL) HEPATOTOXICITY and SKIN REACTIONS HEPATOTOXICITY: Severe, life-threatening, and in some cases fatal hepatotoxicity, particularly in the first 18 weeks, has been reported in patients treated with nevirapine. In some cases, patients presented with non-specific prodromal signs or symptoms of hepatitis and progressed to hepatic failure. These events are often associated with rash.
Female sex and higher CD4 + cell counts at initiation of therapy place patients at increased risk; women with CD4 + cell counts greater than 250 cells/mm 3 , including pregnant women receiving nevirapine in combination with other antiretrovirals for the treatment of HIV-1 infection, are at the greatest risk. However, hepatotoxicity associated with nevirapine use can occur in both sexes, all CD4 + cell counts and at any time during treatment. Hepatic failure has also been reported in patients without HIV taking nevirapine for post-exposure prophylaxis (PEP).
Use of nevirapine for occupational and non-occupational PEP is contraindicated [see Contraindications (4) ]. Patients with signs or symptoms of hepatitis, or with increased transaminases combined with rash or other systemic symptoms, must discontinue nevirapine and seek medical evaluation immediately [see Warnings and Precautions (5.1) ]. SKIN REACTIONS: Severe, life-threatening skin reactions, including fatal cases, have occurred in patients treated with nevirapine.
These have included cases of Stevens-Johnson syndrome, toxic epidermal necrolysis, and hypersensitivity reactions characterized by rash, constitutional findings, and organ dysfunction. Patients developing signs or symptoms of severe skin reactions or hypersensitivity reactions must discontinue nevirapine and seek medical evaluation immediately. Transaminase levels should be checked immediately for all patients who develop a rash in the first 18 weeks of treatment.
The 14-day lead-in period with immediate-release nevirapine 200 mg daily dosing has been observed to decrease the incidence of rash and must be followed [see Warnings and Precautions (5.2) ]. MONITORING FOR HEPATOTOXICITY AND SKIN REACTIONS: Patients must be monitored intensively during the first 18 weeks of therapy with nevirapine to detect potentially life-threatening hepatotoxicity or skin reactions. Extra vigilance is warranted during the first 6 weeks of therapy, which is the period of greatest risk of these events.
Do not restart nevirapine following clinical hepatitis, or transaminase elevations combined with rash or other systemic symptoms, or following severe skin rash or hypersensitivity reactions. In some cases, hepatic injury has progressed despite discontinuation of treatment. WARNING: LIFE-THREATENING (INCLUDING FATAL) HEPATOTOXICITY and SKIN REACTIONS See full prescribing information for complete boxed warning. • Fatal and non-fatal hepatotoxicity have been reported in patients taking nevirapine extended-release tablets.
Discontinue immediately if clinical hepatitis or transaminase elevations combined with rash or other systemic symptoms occur. Do not restart nevirapine extended-release tablets after recovery. (5.1) • Fatal and non-fatal skin reactions, including Stevens-Johnson syndrome, toxic epidermal necrolysis, and hypersensitivity reactions, have been reported.
Discontinue immediately if severe skin reactions, hypersensitivity reactions, or any rash with systemic symptoms occur. Check transaminase levels immediately for all patients who develop a rash in the first 18 weeks of treatment. Do not restart nevirapine extended-release tablets after recovery.
( 5.2 ) • Monitoring during the first 18 weeks of therapy is essential. Extra vigilance is warranted during the first 6 weeks of therapy, which is the period of greatest risk of these events. ( 5.1 , 5.2 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Nevirapine extended-release tablets are indicated in combination with other antiretroviral agents for the treatment of human immunodeficiency virus (HIV-1) infection in adults and pediatric patients 6 years of age or older with a body surface area (BSA) of 1.17 m 2 or greater [see Clinical Studies (14.1 , 14.2) ] . Limitations of Use: Based on serious and life-threatening hepatotoxicity observed in controlled and uncontrolled trials, nevirapine extended-release tablets are not recommended to be initiated, unless the benefit outweighs the risk, in: • adult females with CD4 + cell counts greater than 250 cells/mm 3 or • adult males with CD4 + cell counts greater than 400 cells/mm 3 [see Warnings and Precautions (5.1) ] .
Nevirapine extended-release tablets are an NNRTI indicated in combination with other antiretroviral agents for the treatment of human immunodeficiency virus (HIV-1) infection in adults and pediatric patients 6 years of age or older with a BSA of 1.17 m 2 or greater. ( 1 ) Limitations of Use: Based on serious and life-threatening hepatotoxicity observed in controlled and uncontrolled trials, nevirapine extended-release tablets are not recommended to be initiated, unless the benefit outweighs the risk, in: • adult females with CD4 + cell counts greater than 250 cells/mm 3 • adult males with CD4 + cell counts greater than 400 cells/mm 3 ( 1 , 5.1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • The 14-day lead-in period with immediate-release nevirapine (200 mg once daily) must be strictly followed; it has been demonstrated to reduce the frequency of rash. ( 2.5 , 5.2 ) • Must be swallowed whole and must not be chewed, crushed, or divided. ( 2.1 ) • Adult patients must initiate therapy with one 200 mg immediate-release nevirapine tablet once daily for the first 14 days, followed by one 400 mg tablet of nevirapine extended-release once daily.
( 2.2 ) • Adult patients already on a regimen of immediate-release nevirapine twice daily can be switched to nevirapine extended-release tablets 400 mg once daily without the 14-day lead-in period of immediate-release nevirapine. ( 2.2 ) • Pediatric patients (ages 6 to less than 18 years with a BSA of 1.17 m 2 or greater) must initiate therapy with immediate-release nevirapine (as 150 mg/m 2 of nevirapine oral suspension or as nevirapine tablet) at a dose not to exceed 200 mg per day administered once daily for the first 14 days, followed by nevirapine extended-release tablets 400 mg once daily.
( 2.3 ) • Pediatric patients with a BSA of 1.17 m 2 or greater already on a regimen of twice daily nevirapine oral suspension or immediate-release nevirapine tablets can be switched to nevirapine extended-release tablets 400 mg once daily without the 14-day lead-in period of nevirapine oral suspension or immediate-release nevirapine tablets. ( 2.3 ) • If any patient experiences rash during the 14-day lead-in period with immediate-release nevirapine do not initiate nevirapine extended-release tablets until the rash has resolved.
Do not continue the immediate-release nevirapine lead-in dosing regimen beyond 28 days. ( 2.5 ) • If dosing is interrupted for greater than 7 days, restart 14-day lead-in dosing. ( 2.5 )
2.1General Dosing Considerations • Nevirapine extended-release tablets must be swallowed whole and must not be chewed, crushed, or divided. • Pediatric patients should be assessed for their ability to swallow the extended-release tablets before prescribing nevirapine extended-release tablets. • Nevirapine extended-release tablets can be taken with or without food.
2.2Recommended Dosage in Adult Patients Patients not currently taking immediate-release nevirapine Patients must initiate therapy with one 200-mg tablet of immediate-release nevirapine daily for the first 14 days in combination with other antiretroviral agents. The 14-day lead-in period with nevirapine 200 mg daily dosing must be strictly followed (the lead-in period has been observed to decrease the incidence of rash), followed by one 400-mg tablet of nevirapine extended-release once daily [see Dosage and Administration (2.5) and Warnings and Precautions (5.2) ] .
If rash persists beyond the 14-day lead-in period with immediate-release nevirapine, do not begin dosing with nevirapine extended-release tablets. The lead-in dosing with 200 mg once daily immediate-release nevirapine should not be continued beyond 28 days, at which point an alternative regimen should be sought . Switching patients from immediate-release nevirapine to nevirapine extended-release tablets Patients already on a regimen of immediate-release nevirapine twice daily in combination with other antiretroviral agents can be switched to nevirapine extended-release tablets 400 mg once daily without the 14-day lead-in period.
Patients already on a regimen of immediate-release nevirapine twice daily who switch to nevirapine extended-release tablet therapy should continue with their ongoing clinical and laboratory monitoring .
2.3Recommended Dosage in Pediatric Patients Nevirapine extended-release tablets in pediatric patients are dosed based on body surface area (BSA) calculated using the Mosteller formula. All pediatric patients must initiate therapy with immediate-release nevirapine (as 150 mg/m 2 of nevirapine oral suspension or as nevirapine tablets), at a dose not to exceed 200 mg per day, administered once daily for the…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Nevirapine Extended-Release Tablets, USP are available containing 400 mg of nevirapine, USP. • The 400 mg tablets are white to off-white, oval, unscored tablets debossed with M on one side of the tablet and N400 on the other side. 400 mg extended-release tablets ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Nevirapine extended-release tablets are contraindicated: • in patients with moderate or severe (Child-Pugh Class B or C, respectively) hepatic impairment [see Warnings and Precautions (5.1) and Use in Specific Populations (8.7) ] . • for use as part of occupational and non-occupational post-exposure prophylaxis (PEP) regimens [see Warnings and Precautions (5.1) ] . • Patients with moderate or severe (Child-Pugh Class B or C, respectively) hepatic impairment. ( 4 , 5.1 , 8.7 ) • Use as part of occupational and non-occupational post-exposure prophylaxis (PEP) regimens, an unapproved use.
( 4 , 5.1 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Monitor patients for immune reconstitution syndrome and fat redistribution. ( 5.5 , 5.6 )
5.1Hepatotoxicity and Hepatic Impairment Severe, life-threatening, and in some cases fatal hepatotoxicity, including fulminant and cholestatic hepatitis, hepatic necrosis and hepatic failure, have been reported in patients treated with nevirapine. The risk of symptomatic hepatic events regardless of severity is greatest in the first 6 weeks of therapy. The risk continued to be greater in the nevirapine groups in controlled clinical trials through 18 weeks of treatment.
However, hepatic events may occur at any time during treatment. In some cases, patients presented with non-specific, prodromal signs or symptoms of fatigue, malaise, anorexia, nausea, jaundice, liver tenderness or hepatomegaly, with or without initially abnormal serum transaminase levels. Rash was observed in approximately half of the patients with symptomatic hepatic adverse events.
Fever and flu-like symptoms accompanied some of these hepatic events. Some events, particularly those with rash and other symptoms, have progressed to hepatic failure with transaminase elevation, with or without hyperbilirubinemia, hepatic encephalopathy, prolonged partial thromboplastin time, or eosinophilia. Rhabdomyolysis has been observed in some patients experiencing skin and/or liver reactions associated with nevirapine use.
Hepatitis/hepatic failure may be associated with signs of hypersensitivity which can include severe rash or rash accompanied by fever, general malaise, fatigue, muscle or joint aches, blisters, oral lesions, conjunctivitis, facial edema, eosinophilia, granulocytopenia, lymphadenopathy, or renal dysfunction. Patients with signs or symptoms of hepatitis must be advised to discontinue nevirapine and immediately seek medical evaluation, which should include liver enzyme tests. The first 18 weeks of therapy with nevirapine extended-release tablets are a critical period during which intensive clinical and laboratory monitoring of patients is required to detect potentially life-threatening hepatic events.
The optimal frequency of monitoring during this period has not been established. Some experts recommend clinical and laboratory monitoring more often than once per month, and in particular, include monitoring of liver enzyme tests at baseline, prior to dose escalation and at two weeks post-dose escalation. After the initial 18-week period, frequent clinical and laboratory monitoring should continue throughout nevirapine extended-release tablet treatment.
Transaminases should be checked immediately if a patient experiences signs or symptoms suggestive of hepatitis and/or hypersensitivity reaction. Transaminases should also be checked immediately for all patients who develop a rash in the first 18 weeks of treatment. Physicians and patients should be vigilant for the appearance of signs or symptoms of hepatitis, such as fatigue, malaise, anorexia, nausea, jaundice, bilirubinuria, acholic stools, liver tenderness, or hepatomegaly.
The diagnosis of hepatotoxicity should be considered in this setting, even if transaminases are initially normal or alternative diagnoses are possible [see Dosage and Administration (2.4) ] . If clinical hepatitis or transaminase elevations combined with rash or other systemic symptoms occur, permanently discontinue nevirapine. Do not restart nevirapine after recovery.
In some cases, hepatic injury progresses despite discontinuation of treatment. The patients at greatest risk of hepatic events, including potentially fatal events, are women with high CD4 + cell counts. In a retrospective analysis of pooled clinical trials with immediate-release nevirapine, during the first 6 weeks of treatment women had a 3-fold higher risk than men for symptomatic, often rash-associated, hepatic events (6% versus 2%).
Patients with higher CD4 + cell counts at initiation of nevirapine therapy are at higher risk for symptomatic hepatic eve…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS • Adult patients: The most common adverse reaction is rash. During the lead-in period with immediate-release nevirapine, the incidence of Grade 2 or higher drug-related rash in adults is 3%. After the lead-in period the incidence of Grade 2 or higher drug-related rash in subjects taking nevirapine extended-release tablets is 3%.
The incidence of Grade 2 or higher drug-related clinical hepatitis after the lead-in phase was 2%. ( 6.1 ) • Pediatric patients: The incidence of Grade 2 or higher drug-related rash was 1%. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Mylan at 1-877-446-3679 (1-877-4-INFO-RX) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Clinical Trial Experience in Adult Patients The most serious adverse reactions associated with nevirapine are hepatitis, hepatic failure, Stevens-Johnson syndrome, toxic epidermal necrolysis, and hypersensitivity reactions.
Hepatitis/hepatic failure may be isolated or associated with signs of hypersensitivity which may include severe rash or rash accompanied by fever, general malaise, fatigue, muscle or joint aches, blisters, oral lesions, conjunctivitis, facial edema, eosinophilia, granulocytopenia, lymphadenopathy, or renal dysfunction [see Boxed Warning and Warnings and Precautions (5.1 , 5.2) ]. The most common clinical toxicity of nevirapine is rash, which can be severe or life-threatening [see Boxed Warning and Warnings and Precautions (5.2) ].
Rash occurs most frequently within the first 6 weeks of therapy. Rashes are usually mild to moderate, maculopapular erythematous cutaneous eruptions, with or without pruritus, located on the trunk, face and extremities. The safety database in nevirapine extended-release tablet clinical trials contains data from 800 subjects treated with nevirapine extended-release tablets and 654 subjects treated with immediate-release nevirapine.
Trial 1100.1486 (VERxVE) In Trial 1100.1486 (VERxVE), treatment-naïve subjects received a lead-in dose of immediate-release nevirapine 200 mg once daily for 14 days (n = 1,068) and then were randomized to receive either immediate-release nevirapine 200 mg twice daily (n = 506) or nevirapine extended-release tablets 400 mg once daily (n = 505). All subjects received tenofovir + emtricitabine as background therapy. Subjects were enrolled with CD4 + counts less than 250 cells/mm 3 for women and less than 400 cells/mm 3 for men [see Indications and Usage (1) ].
Data on potential symptoms of hepatic events were prospectively collected in this trial. The safety data include all subject visits up to the time of the last subject’s completion of the 96-week endpoint in the trial (mean observation period 98 weeks). After the lead-in period, the incidence of any hepatic event was 9% in the immediate-release nevirapine group and 6% in the nevirapine extended-release tablets group; the incidence of symptomatic hepatic events (anorexia, jaundice, vomiting) was 3% and 2%, respectively.
The incidence of GRADE 3 or 4 ALT/AST elevation was 8% in both the immediate-release nevirapine group and nevirapine extended-release tablets group. Overall, there was a comparable incidence of symptomatic hepatic events among men and women enrolled in VERxVE. Severe or life-threatening rash considered to be related to nevirapine treatment occurred in 1% of subjects during the lead-in phase with immediate-release nevirapine, and in 1% of subjects in either treatment group during the randomized phase.
In addition, six cases of Stevens-Johnson syndrome were reported; all but one occurred within the first 30 days of nevirapine treatment. No Grade 2 or above adverse reactions judged to be related to treatment by the in…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Nevirapine is principally metabolized by the liver via the cytochrome P450 isoenzymes, 3A and 2B6. Nevirapine is known to be an inducer of these enzymes. As a result, drugs that are metabolized by these enzyme systems may have lower than expected plasma levels when co-administered with nevirapine.
The results of drug interactions studies with immediate-release nevirapine are expected to also apply to nevirapine extended-release tablets. The specific pharmacokinetic changes that occur with co-administration of nevirapine and other drugs are listed in Clinical Pharmacology , Table 4. Clinical comments about possible dosage modifications based on established drug interactions are listed in Table 3.
The data in Tables 3 and 4 are based on the results of drug interaction studies conducted in HIV-1 seropositive subjects unless otherwise indicated. In addition to established drug interactions, there may be potential pharmacokinetic interactions between nevirapine and other drug classes that are metabolized by the cytochrome P450 system. These potential drug interactions are also listed in Table 3.
Although specific drug interaction studies in HIV-1 seropositive subjects have not been conducted for some classes of drugs listed in Table 3, additional clinical monitoring may be warranted when co-administering these drugs. The in vitro interaction between nevirapine and the antithrombotic agent warfarin is complex. As a result, when giving these drugs concomitantly, plasma warfarin levels may change with the potential for increases in coagulation time.
When warfarin is co-administered with nevirapine, anticoagulation levels should be monitored frequently. Table 3 Established and Potential Drug Interactions: Use with Caution, Alteration in Dose or Regimen May Be Needed Due to Drug Interaction Established Drug Interactions: See Clinical Pharmacology (12.3) , Table 4 for Magnitude of Interaction. Drug Name Effect on Concentration of Nevirapine or Concomitant Drug Clinical Comment HIV Antiviral Agents: Protease Inhibitors (PIs) Atazanavir/Ritonavir The interaction between immediate-release nevirapine and the drug was evaluated in a clinical study.
The results of drug interaction studies with immediate-release nevirapine are expected to also apply to nevirapine extended-release tablets. ↓ Atazanavir ↑ Nevirapine Do not co-administer nevirapine with atazanavir because nevirapine substantially decreases atazanavir exposure and there is a potential risk for nevirapine-associated toxicity due to increased nevirapine exposures. Fosamprenavir ↓ Amprenavir ↑ Nevirapine Co-administration of nevirapine and fosamprenavir without ritonavir is not recommended. Fosamprenavir/Ritonavir ↓ Amprenavir ↑ Nevirapine No dosing adjustments are required when nevirapine is co-administered with 700/100 mg of fosamprenavir/ritonavir twice daily.
The combination of nevirapine administered with fosamprenavir/ritonavir once daily has not been studied. Indinavir ↓ Indinavir The appropriate doses of this combination of indinavir and nevirapine with respect to efficacy and safety have not been established. Lopinavir/Ritonavir ↓ Lopinavir Dosing in adult patients: A dose adjustment of lopinavir/ritonavir to 500/125 mg tablets twice daily or 533/133 mg (6.5 mL) oral solution twice daily is recommended when used in combination with nevirapine.
Neither lopinavir/ritonavir tablets nor oral solution should be administered once daily in combination with nevirapine. Dosing in pediatric patients: Please refer to the Kaletra ® prescribing information for dosing recommendations based on body surface area and body weight. Neither lopinavir/ritonavir tablets nor oral solution should be administered once daily in combination with nevirapine.
Nelfinavir ↓ Nelfinavir M8 Metabolite ↓ Nelfinavir C min The appropriate doses of the combination of nevirapine and nelfinavir with respect to safety and efficacy have not been established. Saquinavir/Ritonavir The interaction be…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • No dose adjustment is required for patients with renal impairment with a creatinine clearance greater than or equal to 20 mL per min. Patients on dialysis receive an additional dose of immediate-release nevirapine (200 mg) following each dialysis treatment. ( 2.5 , 8.6 ) • Monitor patients with hepatic fibrosis or cirrhosis carefully for evidence of drug-induced toxicity.
Do not administer nevirapine extended-release tablets to patients with Child-Pugh B or C. ( 5.1 , 8.7 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to nevirapine during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Available data from the APR show no difference in the risk of overall major birth defects for nevirapine compared with the background rate for major birth defects of 2.7% in a U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP) [see Data ] .
The rate of miscarriage is not reported in the APR. The estimated background rate of miscarriage in clinically recognized pregnancies in the U.S. general population is 15-20%. The background risk of birth defects and miscarriage for the indicated population is unknown.
Methodological limitations of the APR include the use of MACDP as the external comparator group. The MACDP population is not disease-specific, evaluates women and infants from a limited geographic area, and does not include outcomes for births that occurred at < 20 weeks gestation. There is a risk for severe hepatic events in pregnant women exposed to nevirapine extended-release tablets [see Clinical Considerations ] .
In animal reproduction studies, no evidence of adverse developmental outcomes was observed following oral administration of nevirapine during organogenesis in the rat and rabbit, at systemic exposures (AUC) to nevirapine approximately equal (rats) and 50% higher (rabbits) than the exposure in humans at the recommended 400 mg daily dose [see Data ] . Clinical Considerations Maternal adverse reactions Severe hepatic events, including fatalities, have been reported in pregnant women receiving chronic nevirapine therapy as part of combination treatment of HIV-1 infection.
Regardless of pregnancy status, women with CD4 + cell counts greater than 250 cells/mm 3 should not initiate nevirapine unless the benefit outweighs the risk. It is unclear if pregnancy augments the risk observed in non-pregnant women [see Warnings and Precautions (5.1) ] . Data Human Data Based on prospective reports to the APR of exposures to nevirapine during pregnancy resulting in live births (including over 1,100 exposed in the first trimester and over 1,500 exposed in the second/third trimester), the prevalence of birth defects in live births was 3.0% (95% CI: 2.1%, 4.1%) and 3.3% (95% CI: 2.4%, 4.3%) following first and second/third-trimester exposure, respectively, to nevirapine-containing regimens, compared with the background birth defect rate of 2.7% in a U.S. reference population of the MACDP.
Animal Data Nevirapine was administered orally to pregnant rats (at 0, 12.5, 25, and 50 mg/kg/day), and rabbits (at 0, 30, 100, and 300 mg/kg/day) through organogenesis (on gestation days 7 through 16 and 6 through 18, respectively). No adverse developmental effects were observed at doses producing systemic exposures (AUC) approximately equivalent to (rats) or approximately 50% higher (rabbits) than human exposure at the recommended daily dose. In rats, decreased fetal body weights were observed at a maternally toxic dose at an exposure approximately 50% higher than the recommended daily dose.
8.2Lactation Risk Summary Published data report that immediate-release nevirapine is present in human milk. There are limited data on the effects of nevirapine on the breastfed infant. There is no information on the…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to nevirapine during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Available data from the APR show no difference in the risk of overall major birth defects for nevirapine compared with the background rate for major birth defects of 2.7% in a U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP) [see Data ] .
The rate of miscarriage is not reported in the APR. The estimated background rate of miscarriage in clinically recognized pregnancies in the U.S. general population is 15-20%. The background risk of birth defects and miscarriage for the indicated population is unknown.
Methodological limitations of the APR include the use of MACDP as the external comparator group. The MACDP population is not disease-specific, evaluates women and infants from a limited geographic area, and does not include outcomes for births that occurred at < 20 weeks gestation. There is a risk for severe hepatic events in pregnant women exposed to nevirapine extended-release tablets [see Clinical Considerations ] .
In animal reproduction studies, no evidence of adverse developmental outcomes was observed following oral administration of nevirapine during organogenesis in the rat and rabbit, at systemic exposures (AUC) to nevirapine approximately equal (rats) and 50% higher (rabbits) than the exposure in humans at the recommended 400 mg daily dose [see Data ] . Clinical Considerations Maternal adverse reactions Severe hepatic events, including fatalities, have been reported in pregnant women receiving chronic nevirapine therapy as part of combination treatment of HIV-1 infection.
Regardless of pregnancy status, women with CD4 + cell counts greater than 250 cells/mm 3 should not initiate nevirapine unless the benefit outweighs the risk. It is unclear if pregnancy augments the risk observed in non-pregnant women [see Warnings and Precautions (5.1) ] . Data Human Data Based on prospective reports to the APR of exposures to nevirapine during pregnancy resulting in live births (including over 1,100 exposed in the first trimester and over 1,500 exposed in the second/third trimester), the prevalence of birth defects in live births was 3.0% (95% CI: 2.1%, 4.1%) and 3.3% (95% CI: 2.4%, 4.3%) following first and second/third-trimester exposure, respectively, to nevirapine-containing regimens, compared with the background birth defect rate of 2.7% in a U.S. reference population of the MACDP.
Animal Data Nevirapine was administered orally to pregnant rats (at 0, 12.5, 25, and 50 mg/kg/day), and rabbits (at 0, 30, 100, and 300 mg/kg/day) through organogenesis (on gestation days 7 through 16 and 6 through 18, respectively). No adverse developmental effects were observed at doses producing systemic exposures (AUC) approximately equivalent to (rats) or approximately 50% higher (rabbits) than human exposure at the recommended daily dose. In rats, decreased fetal body weights were observed at a maternally toxic dose at an exposure approximately 50% higher than the recommended daily dose.
🧒 Pediatric Use ▾
8.4Pediatric Use Nevirapine extended-release tablets are indicated for use in combination with other antiretroviral agents for the treatment of HIV-1 infection in children 6 years of age or older with a BSA of 1.17 m 2 or greater [see Indications and Usage (1) and Dosage and Administration (2.3) ]. The use of nevirapine extended-release tablets for the treatment of HIV-1 infection in pediatric patients 6 to less than 18 years of age is based on pharmacokinetic, safety, and antiviral activity data from an open-label trial with nevirapine extended-release tablets.
The results of this trial were supported by previous demonstration of efficacy in adult patients [see Adverse Reactions (6.1) , Clinical Pharmacology (12.3) , and Clinical Studies (14.2) ]. Nevirapine extended-release tablets are not recommended for children less than 6 years of age. Trial 1100.1518 did not provide sufficient pharmacokinetic data for children 3 to less than 6 years of age to support the use of nevirapine extended-release tablets in this age group.
Furthermore, nevirapine extended-release tablets are not recommended for children less than 3 years of age because they are not able to swallow tablets.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of nevirapine extended-release tablets did not include sufficient numbers of subjects aged 65 and older to determine whether elderly subjects respond differently from younger subjects. In general, dose selection for an elderly patient should be cautious, reflecting the greater frequency of decreased hepatic, renal or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE There is no known antidote for nevirapine overdosage. Cases of immediate-release nevirapine overdose at doses ranging from 800 to 1,800 mg per day for up to 15 days have been reported. Patients have experienced events including edema, erythema nodosum, fatigue, fever, headache, insomnia, nausea, pulmonary infiltrates, rash, vertigo, vomiting and weight decrease. All events subsided following discontinuation of immediate-release nevirapine.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Nevirapine is an antiretroviral drug [see Microbiology (12.4) ].
12.3Pharmacokinetics Adults Absorption and Bioavailability The single-dose pharmacokinetics of nevirapine extended-release tablets was studied in 17 healthy volunteers. Nevirapine was absorbed with a median t max of approximately 24 hrs. The mean C max and AUC 0-∞ of nevirapine were 2060 ng per mL and 161,000 ng*hr/mL, respectively.
The bioavailability of 400 mg of nevirapine extended-release tablets, relative to 400 mg of immediate-release nevirapine, was approximately 75%. The multiple-dose pharmacokinetics of nevirapine extended-release tablets was studied in 24 HIV-1 infected subjects who switched from chronic immediate-release nevirapine to nevirapine extended-release tablets. The mean nevirapine AUC 0-24,ss and C min,ss after 19 days of nevirapine extended-release tablet dosing under fasted conditions were 82,000 ng*hr/mL and 2,920 ng per mL, respectively.
When nevirapine extended-release tablets were administered under fed conditions, the mean nevirapine AUC 0-24,ss and C min,ss were 96,700 ng*hr/mL and 3,150 ng per mL, respectively. The bioavailability of 400 mg of nevirapine extended-release tablets, relative to 400 mg of immediate-release nevirapine, under fasted and fed conditions, was 80% and 94%, respectively. The difference in the bioavailability of nevirapine, when nevirapine extended-release tablets are dosed under fasted or fed conditions, is not considered clinically relevant.
Nevirapine extended-release tablets can be taken with or without food. Distribution Nevirapine is highly lipophilic and is essentially nonionized at physiologic pH. Following intravenous administration to healthy adults, the apparent volume of distribution (Vdss) of nevirapine was 1.21 ±
0.09L/kg, suggesting that nevirapine is widely distributed in humans. Nevirapine readily crosses the placenta and is also found in breast milk [see Use in Specific Populations (8.2) ] . Nevirapine is about 60% bound to plasma proteins in the plasma concentration range of 1-10 mcg per mL.
Nevirapine concentrations in human cerebrospinal fluid (n = 6) were 45% (± 5%) of the concentrations in plasma; this ratio is approximately equal to the fraction not bound to plasma protein. Metabolism/Elimination In vivo studies in humans and in vitro studies with human liver microsomes have shown that nevirapine is extensively biotransformed via cytochrome P450 (oxidative) metabolism to several hydroxylated metabolites. In vitro studies with human liver microsomes suggest that oxidative metabolism of nevirapine is mediated primarily by cytochrome P450 (CYP) isozymes from the CYP3A and CYP2B6 families, although other isozymes may have a secondary role.
In a mass balance/excretion trial in eight healthy male volunteers dosed to steady-state with immediate-release nevirapine 200 mg given twice daily followed by a single 50 mg dose of 14 C-nevirapine, approximately 91.4 ± 10.5% of the radiolabeled dose was recovered, with urine (81.3 ± 11.1%) representing the primary route of excretion compared to feces (10.1 ± 1.5%). Greater than 80% of the radioactivity in urine was made up of glucuronide conjugates of hydroxylated metabolites. Thus, cytochrome P450 metabolism, glucuronide conjugation, and urinary excretion of glucuronidated metabolites represent the primary route of nevirapine biotransformation and elimination in humans.
Only a small fraction (less than 5%) of the radioactivity in urine (representing less than 3% of the total dose) was made up of parent compound; therefore, renal excretion plays a minor role in elimination of the parent compound. Nevirapine is an inducer of hepatic cytochrome P450 (CYP) metabolic enzymes 3A and 2B6. Nevirapine induces CYP3A and CYP2B6 by approximately 20-25%, as indicated by erythromycin breath test results and urine metabolites.
Autoinduction of CYP3A and CYP2B6 mediated metabolism leads to an approximately 1.5- to 2-fo…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Nevirapine is an antiretroviral drug [see Microbiology (12.4) ].
Mechanism of Action Nevirapine is a non-nucleoside reverse transcriptase inhibitor (NNRTI) of HIV-1. Nevirapine binds directly to reverse transcriptase (RT) and blocks the RNA-dependent and DNA-dependent DNA polymerase activities by causing a disruption of the enzyme’s catalytic site. The activity of nevirapine does not compete with template or nucleoside triphosphates.
HIV-2 RT and eukaryotic DNA polymerases (such as human DNA polymerases α, ß, γ, or δ) are not inhibited by nevirapine.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Nevirapine Extended-Release Tablets, USP are available containing 400 mg of nevirapine, USP. The 400 mg tablets are white to off-white, oval, unscored tablets debossed with M on one side of the tablet and N400 on the other side. They are available as follows: NDC 0378-4890-93 bottles of 30 tablets Storage Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Store in a safe place out of the reach of children.
Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure. PHARMACIST: Dispense a Medication Guide with each prescription.
📋 Description ▾
11 DESCRIPTION Nevirapine is a non-nucleoside reverse transcriptase inhibitor (NNRTI) with activity against Human Immunodeficiency Virus Type 1 (HIV-1). Nevirapine is structurally a member of the dipyridodiazepinone chemical class of compounds. The chemical name of nevirapine is 11-Cyclopropyl-5,11-dihydro-4-methyl-6 H -dipyrido[3,2- b :2’,3’- e ][1, 4]diazepin-6-one.
Nevirapine, USP (anhydrous) is a white to off-white, odorless to nearly odorless crystalline powder with the molecular weight of 266.30 and the molecular formula C 15 H 14 N 4 O. Nevirapine has the following structural formula: Nevirapine extended-release tablets, USP are for oral administration. Each tablet contains 400 mg of nevirapine and the inactive ingredients hypromellose, lactose monohydrate and sodium stearyl fumarate.
Nevirapine Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Medication Guide ). Hepatotoxicity and Skin Reactions Inform patients of the possibility of severe liver disease or skin reactions associated with nevirapine that may result in death. Instruct patients developing signs or symptoms of liver disease or severe skin reactions to discontinue nevirapine and seek medical attention immediately, including performance of laboratory monitoring.
Symptoms of liver disease include fatigue, malaise, anorexia, nausea, jaundice, acholic stools, liver tenderness or hepatomegaly. Symptoms of severe skin or hypersensitivity reactions include rash accompanied by fever, general malaise, fatigue, muscle or joint aches, blisters, oral lesions, conjunctivitis, facial edema, and/or hepatitis. Intensive clinical and laboratory monitoring, including liver enzymes, is essential during the first 18 weeks of therapy with nevirapine to detect potentially life-threatening hepatotoxicity and skin reactions.
However, liver disease can occur after this period; therefore, monitoring should continue at frequent intervals throughout nevirapine treatment. Extra vigilance is warranted during the first 6 weeks of therapy, which is the period of greatest risk of hepatic events. Advise patients with signs and symptoms of hepatitis to discontinue nevirapine and seek medical evaluation immediately.
If nevirapine is discontinued due to hepatotoxicity, do not restart it. Patients, particularly women, with increased CD4 + cell count at initiation of nevirapine therapy (greater than 250 cells/mm 3 in women and greater than 400 cells/mm 3 in men) are at substantially higher risk for development of symptomatic hepatic events, often associated with rash. Advise patients that co-infection with hepatitis B or C or increased transaminases at the start of therapy with nevirapine are associated with a greater risk of later symptomatic events (6 weeks or more after starting nevirapine) and asymptomatic increases in AST or ALT [see Warnings and Precautions (5.1) ].
The majority of rashes associated with nevirapine occur within the first 6 weeks of initiation of therapy. Instruct patients that if any rash occurs during the two-week lead-in period with immediate-release nevirapine, do not initiate nevirapine extended-release tablets until the rash resolves. The total duration of the lead-in dosing period with immediate-release nevirapine should not exceed 28 days, at which point an alternative regimen may need to be started.
Any patient experiencing a rash should have their liver enzymes (AST, ALT) evaluated immediately. Patients with severe rash or hypersensitivity reactions should discontinue nevirapine immediately and consult a physician. Nevirapine should not be restarted following severe skin rash or hypersensitivity reaction.
Women tend to be at higher risk for development of nevirapine-associated rash. For patients who interrupt nevirapine extended-release tablet dosing for more than 7 days and for whom restarting nevirapine therapy is not contraindicated, restart the recommended lead-in dosing with immediate-release nevirapine using one 200 mg tablet daily (150 mg/m 2 /day in pediatric patients) for the first 14 days [see Warnings and Precautions (5.2) ]. Administration and Missed Dosage Inform patients to take nevirapine extended-release tablets every day as prescribed.
Advise patients not to alter the dose without consulting their doctor. If a dose is missed, patients should take the next dose as soon as possible. However, if a dose is skipped, the patient should not double the next dose.
Inform patients that they may occasionally see soft remnants of nevirapine extended-release tablets in their stool, which sometimes resemble intact tablets. These occurrences have not been shown to affect drug levels or response. Instruct patients to swallow nevirapine extended-release tablets whole.
They must not be chewed, crushed, or divided. To…
💬 Medication Guide ▾
Medication Guide Nevirapine Extended-Release Tablets, USP (ne vir′ a peen) What is the most important information I should know about nevirapine? Nevirapine can cause severe liver and skin problems that may lead to death. These problems can happen at any time during treatment, but your risk is higher during the first 18 weeks of treatment.
Nevirapine can cause serious side effects, including: • Severe liver problems. Some people taking nevirapine may develop severe liver problems that can lead to liver failure and the need for a liver transplant, or death. If you have liver problems, you may get a rash. o Women have a higher risk of developing liver problems during treatment with nevirapine than men. o People who have abnormal liver test results before starting nevirapine and people with hepatitis B or C also have a greater risk of getting liver problems.
People who have higher CD4 + cell counts when they begin nevirapine have a higher risk of liver problems, especially: o Women with CD4 + counts higher than 250 cells/mm 3 . This group has the highest risk. o Men with CD4 + counts higher than 400 cells/mm 3 . Stop taking nevirapine and call your doctor right away if you have any of the following symptoms of liver problems with or without a skin rash: • dark (tea colored) urine • light-colored bowel movements (stools) • feeling sick to your stomach (nausea) • pain or tenderness on your right side below your ribs • loss of appetite • yellowing of your skin or whites of your eyes • fever • feel unwell or like you have the flu • tiredness • Severe skin reactions and rash .
Some skin reactions and rashes may be severe, life-threatening, and in some people, may lead to death. Most severe skin reactions and rashes happen in the first 6 weeks of treatment with nevirapine. o Women have a higher risk of developing a rash during treatment with nevirapine than men. Stop taking nevirapine and call your doctor right away if you get a rash with any of the following symptoms: • blisters • red or inflamed eyes, like “pink eye” (conjunctivitis) • swelling of your face • feel unwell or like you have the flu • muscle or joint aches • mouth sores • fever • tiredness • Your doctor should do blood tests often to check your liver function and check for severe skin reactions during the first 18 weeks of treatment with nevirapine.
You should continue to see your doctor and have your liver checked regularly during your treatment with nevirapine. It is important for you to keep all of your doctor appointments. • If your doctor tells you to stop treatment with nevirapine because you have had any of the severe liver or skin symptoms listed above, you should never take nevirapine again. See “What are the possible side effects of nevirapine?” for more information about side effects.
What is nevirapine? Nevirapine oral suspension is a prescription HIV-1 medicine used with other HIV-1 medicines to treat HIV-1 (Human Immunodeficiency Virus 1) in adults and in children 15 days of age or older. HIV-1 is the virus that causes AIDS (Acquired Immune Deficiency Syndrome).
Nevirapine extended-release tablets are a prescription medicine used with other HIV-1 medicines to treat HIV-1 (Human Immunodeficiency Virus 1) in adults and in children 6 years of age or older based on the child’s weight and height. • If you are a woman with CD4 + counts higher than 250 cells/mm 3 or a man with CD4 + counts higher than 400 cells/mm 3 , you and your doctor will decide if starting nevirapine is right for you. • Nevirapine extended-release tablets are not recommended for use in children less than 6 years of age.
Do not take nevirapine: • if you have liver problems. • as part of occupational and non-occupational post-exposure prophylaxis (PEP) regimens. Nevirapine is only for people diagnosed with HIV-1. If you have not been diagnosed as HIV positive, then do not take nevirapine.
Before taking nevirapine, tell your doctor about all your or your child’s medical conditions, including if…