
Saxagliptin and Metformin 5 mg; 1000 mg Tablet, Film Coated, Extended Release, 30-count
🆔 Identity & classification
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Metformin is used alone or with other medications, including insulin, to treat type 2 diabetes (condition in which the body does not use insulin normally and, therefore, cannot control the amount of sugar in the blood). Metformin is in a class of drugs called biguanides. Metformin helps to control the amount of glucose (sugar) in your blood. It decreases the amount of glucose you absorb from your food and the amount of glucose made by your liver. Metformin also increases your body's response to insulin, a natural substance that controls the amount of glucose in the blood. Metformin is not used...
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 5138Q19F1X
Ammonia is a colorless gas made from nitrogen and hydrogen. It's used in medicines as a pH buffer to maintain the correct acidity level and help keep the product stable.
-
UNII F68VH75CJC
A synthetic polymer made from acrylic acid that thickens and stabilizes liquid or gel formulations. It's used as a gelling agent and emulsifier to create the desired texture and consistency in topical medicines.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII VM7F0B23ZI
Hypromellose 2208 is a plant-derived thickening agent that forms a protective coating on tablets and capsules. It slows down how quickly the medicine dissolves, controlling drug release into your body.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII G2M7P15E5P
Polyethylene glycol 3350 is a synthetic polymer used as a solvent, humectant, and thickening agent in medicines. It helps dissolve other ingredients, retain moisture in the product, and achieve the desired consistency.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII RDH86HJV5Z
Povidone K90 is a synthetic polymer made from a chemical called vinyl pyrrolidone. It acts as a binder to hold pill ingredients together and as a dispersant to help the medicine break down and dissolve properly in your body.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 4ELV7Z65AP
Stearic acid is a fatty acid derived from plant or animal sources. It acts as a binder and lubricant in tablets and capsules, helping them hold together and flow smoothly during manufacturing.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
15 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $9.912 | $297.35 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $4.75 | $142.57 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Saxagliptin and Metformin 5 mg/1; 1000 mgthis 00378-8177-93 | Mylan | 30 tablets | $9.912 | AB | Availability likely | — |
| Saxagliptin and Metformin Hydrochloride 5 mg/1; 1000 mg 43598-0619-30 | Dr.Reddys | 30 tablets | $9.912 | AB | Availability likely | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00378-8177-93 You're viewing this | 30 TABLET, FILM COATED, EXTENDED RELEASE in 1 BOTTLE, PLASTIC (0378-8177-93) | 2023-08-08 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: LACTIC ACIDOSIS • Post-marketing cases of metformin-associated lactic acidosis have resulted in death, hypothermia, hypotension, and resistant bradyarrhythmias. The onset of metformin-associated lactic acidosis is often subtle, accompanied only by nonspecific symptoms such as malaise, myalgias, respiratory distress, somnolence, and abdominal pain. Metformin-associated lactic acidosis was characterized by elevated blood lactate levels (> 5 mmol/Liter), anion gap acidosis (without evidence of ketonuria or ketonemia), an increased lactate/pyruvate ratio; and metformin plasma levels generally > 5 mcg/mL [ see Warnings and Precautions (5.1) ]. • Risk factors for metformin-associated lactic acidosis include renal impairment, concomitant use of certain drugs (e.g., carbonic anhydrase inhibitors such as topiramate), age 65 years old or greater, having a radiological study with contrast, surgery and other procedures, hypoxic states (e.g., acute congestive heart failure ), excessive alcohol intake, hepatic impairment, and mitochondrial diseases [ see Warnings and Precautions (5.1) ]. • Steps to reduce the risk of and manage metformin-associated lactic acidosis in these high risk groups are provided in the full prescribing information [ see Dosage and Administration (2.2) , Contraindications (4) , Warnings and Precautions (5.1) , Drug Interactions (7) , and Use in Specific Populations (8.6 , 8.7) ]. • If metformin-associated lactic acidosis is suspected, immediately discontinue saxagliptin and metformin hydrochloride extended-release tablets and institute general supportive measures in a hospital setting.
Prompt hemodialysis is recommended [ see Warnings and Precautions (5.1) ]. WARNING: LACTIC ACIDOSIS See full prescribing information for complete boxed warning. • Post-marketing cases of metformin-associated lactic acidosis have resulted in death, hypothermia, hypotension, and resistant bradyarrhythmias. Symptoms included malaise, myalgias, respiratory distress, somnolence, and abdominal pain.
Laboratory abnormalities included elevated blood lactate levels, anion gap acidosis, increased lactate/pyruvate ratio; and metformin plasma levels generally > 5 mcg/mL. ( 5.1 ) • Risk factors include renal impairment, concomitant use of certain drugs, age > 65 years old, radiological studies with contrast, surgery and other procedures, hypoxic states, excessive alcohol intake, hepatic impairment, and mitochondrial diseases. Steps to reduce the risk of and manage metformin-associated lactic acidosis in these high risk groups are provided in the Full Prescribing Information.
( 5.1 ) • If lactic acidosis is suspected, discontinue saxagliptin and metformin hydrochloride extended-release tablets and institute general supportive measures in a hospital setting. Prompt hemodialysis is recommended. ( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Saxagliptin and metformin hydrochloride extended-release tablets are indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus [ see Clinical Studies (14) ]. Saxagliptin and metformin hydrochloride extended-release tablets are a combination of saxagliptin, a dipeptidyl peptidase-4 (DPP4) inhibitor, and metformin hydrochloride (HCl), a biguanide, indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus.
( 1 ) Limitations of Use: • Not recommended for the treatment of type 1 diabetes mellitus or diabetic ketoacidosis. ( 1.1 )
1.1Limitations of Use Saxagliptin and metformin hydrochloride extended-release tablets are not recommended for the treatment of type 1 diabetes mellitus or diabetic ketoacidosis.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Administer once daily with the evening meal. ( 2.1 ) • Individualize the starting dosage based on the patient’s current regimen then adjust the dosage based on effectiveness and tolerability. ( 2.1 ) • Do not exceed a daily dosage of 5 mg saxagliptin/2,000 mg metformin HCl extended-release.
( 2.1 ) • Swallow whole. Never crush, cut, or chew. ( 2.1 ) • Limit the saxagliptin dosage to 2.5 mg daily for patients also taking strong cytochrome P450 3A4/5 inhibitors (e.g., ketoconazole).
( 2.3 , 7.1 ) • Assess renal function prior to initiation of saxagliptin and metformin hydrochloride extended-release tablets and periodically thereafter. ( 2.2 ) o Do not use in patients with eGFR below 30 mL/min/1.73 m 2 . o Initiation is not recommended in patients with eGFR between 30 - 45 mL/min/1.73 m 2 . o Assess risk/benefit of continuing if eGFR falls below 45 mL/min/1.73 m 2 . o Limit the saxagliptin component to 2.5 mg daily if eGFR is less than 45 mL/min/1.73 m 2 . o Discontinue if eGFR falls below 30 mL/min/1.73 m 2 . • Saxagliptin and metformin hydrochloride extended-release tablets may need to be discontinued at time of, or prior to, iodinated contrast imaging procedures.
( 2.4 )
2.1Recommended Dosage and Administration Individualize the starting dosage of saxagliptin and metformin hydrochloride extended-release tablets based on the patient’s current regimen and the available strengths of saxagliptin and metformin hydrochloride extended-release tablets [ see Dosage Forms and Strengths (3) ]. Administer saxagliptin and metformin hydrochloride extended-release tablets once daily with the evening meal, with gradual dose titration to reduce the gastrointestinal side effects associated with metformin HCl [ see Adverse Reactions (6.1) ].
The recommended starting dosage of saxagliptin and metformin hydrochloride extended-release tablets in patients who need 5 mg of saxagliptin and who are not currently treated with metformin HCl is one saxagliptin and metformin hydrochloride extended-release tablet containing 5 mg saxagliptin and 500 mg metformin HCl extended-release once daily with gradual dose escalation to reduce the gastrointestinal side effects due to metformin HCl. In patients treated with metformin HCl, the recommended starting dosage of saxagliptin and metformin hydrochloride extended-release tablets should provide metformin HCl at the dose already being taken, or the nearest therapeutically appropriate dose.
Following a switch from metformin HCl immediate-release to saxagliptin and metformin hydrochloride extended-release tablets, closely monitor glycemic control and adjust the dosage accordingly. Patients who need 2.5 mg saxagliptin in combination with metformin HCl extended-release may be treated with saxagliptin and metformin hydrochloride extended-release tablets 2.5 mg/1,000 mg. Patients who need 2.5 mg saxagliptin who are either metformin HCl naive or who require a dose of metformin HCl higher than 1,000 mg should use the individual components.
Gradually titrate the dosage of saxagliptin and metformin hydrochloride extended-release tablets, as needed, after assessing therapeutic response and tolerability, up to a maximum recommended dosage of saxagliptin and metformin hydrochloride extended-release tablets (5 mg for saxagliptin and 2,000 mg for metformin HCl extended-release orally once daily). Inform patients that saxagliptin and metformin hydrochloride extended-release tablets must be swallowed whole and never crushed, cut, or chewed. Occasionally, the inactive ingredients of saxagliptin and metformin hydrochloride extended-release tablets will be eliminated in the feces as a soft, hydrated mass that may resemble the original tablet.
If a dose is missed, advise patients not to take an extra dose. Resume treatment with the next dose.
2.2Recommendations for Dosage and Administration in Renal Impairment Assess renal function prior to initiation of saxagliptin and metformin hydrochloride extended-r…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Extended-Release Tablets: • Saxagliptin and Metformin Hydrochloride Extended-Release Tablets, 5 mg/500 mg, are pink, film-coated, round, unscored tablets imprinted with SM3 over M in black ink on one side of the tablet and blank on the other side. • Saxagliptin and Metformin Hydrochloride Extended-Release Tablets, 5 mg/1000 mg, are pink, film-coated, capsule shaped, unscored tablets imprinted with SM6 over M in black ink on one side of the tablet and blank on the other side. • Saxagliptin and Metformin Hydrochloride Extended-Release Tablets, 2.5 mg/1000 mg, are light peach, film-coated, capsule shaped, unscored tablets imprinted with SM4 over M in black ink on one side of the tablet and blank on the other side. • 5 mg saxagliptin/500 mg metformin HCl extended-release ( 3 ) • 5 mg saxagliptin/1000 mg metformin HCl extended-release ( 3 ) • 2.5 mg saxagliptin/1000 mg metformin HCl extended-release ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Saxagliptin and metformin hydrochloride extended-release tablets are contraindicated in patients with: • Severe renal impairment (eGFR below 30 mL/min/1.73 m 2 ). • Acute or chronic metabolic acidosis, including diabetic ketoacidosis. Diabetic ketoacidosis should be treated with insulin. • A history of a serious hypersensitivity reaction to saxagliptin, metformin HCl, or any of the ingredients in saxagliptin and metformin hydrochloride extended-release tablets. Reactions such as anaphylaxis, angioedema, or exfoliative skin conditions have been reported [ see Warnings and Precautions (5.6) and Adverse Reactions (6.2) ]. • Severe renal impairment (eGFR below 30 mL/min/1.73 m 2 ).
( 4 ) • Metabolic acidosis, including diabetic ketoacidosis. ( 4 ) • History of a serious hypersensitivity reaction (e.g., anaphylaxis, angioedema, exfoliative skin conditions) to saxagliptin, metformin HCl, or any of the ingredients in saxagliptin and metformin hydrochloride extended-release tablets. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Pancreatitis: There have been postmarketing reports of acute pancreatitis. If pancreatitis is suspected, promptly discontinue saxagliptin and metformin hydrochloride extended-release tablets. ( 5.2 ) • Heart Failure: Consider the risks and benefits of saxagliptin and metformin hydrochloride extended-release tablets in patients who have known risk factors for heart failure.
Monitor patients for signs and symptoms. ( 5.3 ) • Vitamin B 12 Deficiency: Metformin may lower vitamin B 12 levels. Measure hematological parameters annually.
( 5.4 ) • Hypoglycemia with Concomitant Use of Insulin or Insulin Secretagogues: Consider a lower dosage of insulin or insulin secretagogue when used in combination with saxagliptin and metformin hydrochloride extended-release tablets. ( 5.5 ) • Hypersensitivity-Related Events: There have been post-marketing reports of serious hypersensitivity reactions, such as anaphylaxis, angioedema, and exfoliative skin conditions in patients treated with saxagliptin. If hypersensitivity reactions occur, discontinue saxagliptin and metformin hydrochloride extended-release tablets, treat promptly, and monitor until signs and symptoms resolve.
( 5.6 ) • Arthralgia: Severe and disabling arthralgia has been reported in patients taking DPP4 inhibitors. Consider as a possible cause for severe joint pain and discontinue drug if appropriate. ( 5.7 ) • Bullous Pemphigoid: There have been postmarketing reports of bullous pemphigoid requiring hospitalization in patients taking DPP-4 inhibitors.
Tell patients to report development of blisters or erosions. If bullous pemphigoid is suspected, discontinue saxagliptin and metformin hydrochloride extended-release tablets ( 5.8 ).
5.1Lactic Acidosis There have been postmarketing cases of metformin-associated lactic acidosis, including fatal cases. These cases had a subtle onset and were accompanied by nonspecific symptoms such as malaise, myalgias, abdominal pain, respiratory distress, or increased somnolence; however, hypothermia, hypotension and resistant bradyarrhythmias have occurred with severe acidosis. Metformin-associated lactic acidosis was characterized by elevated blood lactate concentrations (> 5 mmol/Liter), anion gap acidosis (without evidence of ketonuria or ketonemia), and an increased lactate: pyruvate ratio; metformin plasma levels generally > 5 mcg/mL.
Metformin decreases liver uptake of lactate increasing lactate blood levels which may increase the risk of lactic acidosis, especially in patients at risk. If metformin-associated lactic acidosis is suspected, general supportive measures should be instituted promptly in a hospital setting, along with immediate discontinuation of saxagliptin and metformin hydrochloride extended-release tablets. In saxagliptin and metformin hydrochloride extended-release tablet-treated patients with a diagnosis or strong suspicion of lactic acidosis, prompt hemodialysis is recommended to correct the acidosis and remove accumulated metformin (metformin HCl is dialyzable, with a clearance of up to 170 mL/minute under good hemodynamic conditions).
Hemodialysis has often resulted in reversal of symptoms and recovery. Educate patients and their families about the symptoms of lactic acidosis and if these symptoms occur instruct them to discontinue saxagliptin and metformin hydrochloride extended-release tablets and report these symptoms to their health care provider. For each of the known and possible risk factors for metformin-associated lactic acidosis, recommendations to reduce the risk of and manage metformin-associated lactic acidosis are provided below: Renal Impairment The post-marketing metformin-associated lactic acidosis cases primarily occurred in patients with significant renal impairment.
The risk of metformin accumulation and metformin-associated lactic acidosis increases with the severity of renal impairment because metformin is substantially excreted by the kidney. Clinical recommendations base…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described below or elsewhere in the prescribing information: • Lactic Acidosis [ see Boxed Warning and Warnings and Precautions (5.1) ] • Pancreatitis [ see Warnings and Precautions (5.2) ] • Heart Failure [ see Warnings and Precautions (5.3) ] • Vitamin B 12 Deficiency [ see Warnings and Precautions (5.4) ] • Hypoglycemia with Concomitant Use of Insulin or Insulin Secretagogues [ see Warnings and Precautions (5.5) ] • Hypersensitivity Reactions [ see Warnings and Precautions (5.6) ] • Severe and disabling arthralgia [ see Warnings and Precautions (5.7) ] • Bullous pemphigoid [ see Warnings and Precautions (5.8) ] • Most common adverse reactions with metformin HCl extended-release (incidence > 5% and more often than placebo) are: diarrhea and nausea/vomiting.
( 6.1 ) • Most common adverse reactions with saxagliptin (incidence ≥ 5% and more often than placebo) are: upper respiratory tract infection, urinary tract infection, and headache. ( 6.1 ) • Adverse reactions with coadministered saxagliptin and metformin HCl (incidence ≥ 5% and more often than placebo) are: headache and nasopharyngitis. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Mylan at 1-877-446-3679 (1-877-4-INFO-RX) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse Reactions in Placebo-Controlled Trials in Adults with Type 2 Diabetes Mellitus Metformin HCl In placebo-controlled monotherapy trials of metformin HCl extended-release, diarrhea and nausea/vomiting were reported in > 5% of metformin-treated patients and more commonly than in placebo-treated patients (9.6% versus 2.6% for diarrhea and 6.5% versus 1.5% for nausea/vomiting).
Diarrhea led to discontinuation of trial medication in 0.6% of the patients treated with metformin HCl extended-release. Saxagliptin The data in Table 1 are derived from a pool of 5 placebo-controlled clinical trials [ see Clinical Studies (14) ]. These data shown in the table reflect exposure of 882 patients to saxagliptin and a mean duration of exposure to saxagliptin of 21 weeks.
The mean age of these patients was 55 years, 1.4% were 75 years or older and 48.4% were male. The population was 67.5% White, 4.6% Black or African American, 17.4% Asian, 10.5% other races and 9.8% were of Hispanic or Latino ethnicity. At baseline the population had diabetes for an average of 5.2 years and a mean HbA1c of 8.2%.
Baseline estimated renal function was normal or mildly impaired (eGFR ≥ 60 mL/min/1.73 m 2 ) in 91% of these patients. Table 1 shows common adverse reactions, excluding hypoglycemia, associated with the use of saxagliptin. These adverse reactions occurred more commonly on saxagliptin than on placebo and occurred in at least 5% of patients treated with saxagliptin.
Table 1: Adverse Reactions in Placebo-Controlled Trials The 5 placebo-controlled trials include two monotherapy trials and one add-on combination therapy trial with each of the following: metformin HCl, thiazolidinedione, or glyburide. Table shows 24-week data regardless of glycemic rescue. Reported in ≥ 5% of Patients Treated with Saxagliptin 5 mg and More Commonly than in Patients Treated with Placebo % of Patients Saxagliptin 5 mg N = 882 Placebo N = 799 Upper respiratory tract infection 7.7
7.6Urinary tract infection 6.8
6.1Headache 6.5
5.9In patients treated with saxagliptin 2.5 mg, headache (6.5%) was the only adverse reaction reported at a rate ≥ 5% and more commonly than in patients treated with placebo. In the add-on to TZD trial, the incidence of peripheral edema was higher for saxagliptin 5 mg versus placebo (8.1% and 4.3%, respectively). The incidence of peripheral edema for saxagliptin 2.5…
🔄 Drug Interactions ▾
Drug Interactions The concomitant use of saxagliptin and metformin hydrochloride extended-release tablets with specific drugs may increase the risk of metformin-associated lactic acidosis: those that impair renal function, result in significant hemodynamic change, interfere with acid-base balance or increase metformin accumulation [ see Drug Interactions (7) ]. Therefore, consider more frequent monitoring of patients.
7 DRUG INTERACTIONS • Strong CYP3A4/5 inhibitors (e.g., ketoconazole): Coadministration with saxagliptin and metformin hydrochloride extended-release tablets significantly increases saxagliptin concentrations. Limit saxagliptin and metformin hydrochloride extended-release tablets dosage to 2.5 mg/1,000 mg once daily when coadministered with a strong CYP3A4/5 inhibitor. ( 2.3 , 7.1 ) • Carbonic anhydrase inhibitors: May increase risk of lactic acidosis.
Consider more frequent monitoring. ( 7.2 ) • Drugs that reduce metformin clearance : May increase risk of lactic acidosis. Consider benefits and risks of concomitant use.
( 7.3 ) • See full prescribing information for additional drug interactions. ( 7 )
7.1Strong Inhibitors of CYP3A4/5 Enzymes Ketoconazole significantly increased saxagliptin exposure. Similar significant increases in plasma concentrations of saxagliptin are anticipated with other strong CYP3A4/5 inhibitors (e.g., atazanavir, clarithromycin, indinavir, itraconazole, nefazodone, nelfinavir, ritonavir, saquinavir, and telithromycin). The dose of saxagliptin and metformin hydrochloride extended-release tablets should be limited to 2.5 mg of saxagliptin when coadministered with a strong CYP3A4/5 inhibitor [ see Dosage and Administration (2.3) and Clinical Pharmacology (12.3) ].
7.2Carbonic Anhydrase Inhibitors Topiramate or other carbonic anhydrase inhibitors (e.g., zonisamide, acetazolamide or dichlorphenamide) frequently causes a decrease in serum bicarbonate and induce non-anion gap, hyperchloremic metabolic acidosis. Concomitant use of these drugs with saxagliptin and metformin hydrochloride extended-release tablets may increase the risk for lactic acidosis.
7.3Drugs that Reduce Metformin Clearance Concomitant use of drugs that interfere with common renal tubular transport systems involved in the renal elimination of metformin (e.g., organic cationic transporter-2 [OCT2]/multidrug and toxin extrusion [MATE] inhibitors such as ranolazine, vandetanib, dolutegravir, and cimetidine) could increase systemic exposure to metformin and may increase the risk for lactic acidosis [ see Clinical Pharmacology (12.3) ]. Consider the benefits and risks of concomitant use.
7.4Alcohol Alcohol is known to potentiate the effect of metformin on lactate metabolism. Warn patients against excessive alcohol intake while receiving saxagliptin and metformin hydrochloride extended-release tablets.
7.5Insulin or Insulin Secretagogues Insulin and insulin secretagogues are known to cause hypoglycemia. Concomitant use of saxagliptin and metformin hydrochloride extended-release tablets with insulin or an insulin secretagogue may require lower dosages of insulin or the insulin secretagogue to reduce the risk of hypoglycemia [ see Warnings and Precautions (5.5) ].
7.6Drugs Affecting Glycemic Control Certain drugs tend to produce hyperglycemia and may lead to loss of glycemic control. These medications include the thiazides and other diuretics, corticosteroids, phenothiazines, thyroid products, estrogens, oral contraceptives, phenytoin, nicotinic acid, sympathomimetics, calcium channel blocking drugs, and isoniazid. When such drugs are administered to a patient receiving saxagliptin and metformin hydrochloride extended-release tablets, observe the patient closely for loss of blood glucose control.
When such drugs are withdrawn from a patient receiving saxagliptin and metformin hydrochloride extended-release tablets, observe the patient closely for hypoglycemia.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Geriatric Use: Assess renal function more frequently. ( 8.5 ) • Hepatic Impairment: Avoid use in patients with hepatic impairment. ( 8.7 )
8.1Pregnancy Risk Summary Limited available data with saxagliptin and metformin hydrochloride extended-release tablets or saxagliptin in pregnant women are not sufficient to determine a drug-associated risk for major birth defects and miscarriage. Published trials with metformin use during pregnancy have not reported a clear association with metformin and major birth defect or miscarriage risk [ see Data ]. No adverse developmental effects independent of maternal toxicity were observed when saxagliptin and metformin were administered separately or in combination to pregnant rats and rabbits during the period of organogenesis [ see Data ].
The estimated background risk of major birth defects is 6 to 10% in women with pre-gestational diabetes with an HbA1c greater than 7 and has been reported to be as high as 20 to 25% in women with an HbA1c greater than 10. The estimated background risk of miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, preeclampsia, spontaneous abortions, preterm delivery, still birth and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity. Data Animal Data Saxagliptin In embryo-fetal development studies, saxagliptin was administered to pregnant rats and rabbits during the period of organogenesis, corresponding to the first trimester of human pregnancy.
No adverse developmental effects were observed in either species at exposures 1503- and 152-times the 5 mg clinical dose in rats and rabbits, respectively, based on AUC. Saxagliptin crosses the placenta into the fetus following dosing in pregnant rats. In a prenatal and postnatal development study, no adverse developmental effects were observed in maternal rats administered saxagliptin from gestation day 6 through lactation day 21 at exposures up to 470-times the 5 mg clinical dose, based on AUC.
Metformin HCl Metformin HCl did not cause adverse developmental effect when administered to pregnant Sprague Dawley rats and rabbits up to 600 mg/kg/day during the period of organogenesis. This represents an exposure of about 2- and 6-times a 2,000 mg clinical dose based on body surface area (mg/m 2 ) for rats and rabbits, respectively. Saxagliptin and Metformin Saxagliptin and metformin coadministered to pregnant rats and rabbits during the period of organogenesis did not result in adverse developmental effects considered clinically relevant in either species.
Doses tested in rats provided exposure up to 100- and 10-times clinical exposure, and doses tested in rabbits provided exposure up to 249- and 1-times clinical exposure relative to the clinical dose of 5 mg saxagliptin and 2,000 mg metformin. Minor skeletal abnormalities associated with maternal toxicity were observed in rats. In rabbits, coadministration was poorly tolerated in a subset of mothers (12 of 30), resulting in death, moribundity, or abortion.
However, among surviving mothers with evaluable litters, maternal toxicity was limited to marginal reductions in body weight over the course of gestation days 21 to 29, associated with fetal body weight decrements of 7%, and a low incidence of delayed ossification of the fetal hyoid bone.
8.2Lactation Risk Summary There is no information regarding the presence of saxagliptin and metformin or saxagliptin in human milk, the effects on the breastfed infant, or the effects on milk production. Limited published studies report that metformin is present in h…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Limited available data with saxagliptin and metformin hydrochloride extended-release tablets or saxagliptin in pregnant women are not sufficient to determine a drug-associated risk for major birth defects and miscarriage. Published trials with metformin use during pregnancy have not reported a clear association with metformin and major birth defect or miscarriage risk [ see Data ]. No adverse developmental effects independent of maternal toxicity were observed when saxagliptin and metformin were administered separately or in combination to pregnant rats and rabbits during the period of organogenesis [ see Data ].
The estimated background risk of major birth defects is 6 to 10% in women with pre-gestational diabetes with an HbA1c greater than 7 and has been reported to be as high as 20 to 25% in women with an HbA1c greater than 10. The estimated background risk of miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, preeclampsia, spontaneous abortions, preterm delivery, still birth and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity. Data Animal Data Saxagliptin In embryo-fetal development studies, saxagliptin was administered to pregnant rats and rabbits during the period of organogenesis, corresponding to the first trimester of human pregnancy.
No adverse developmental effects were observed in either species at exposures 1503- and 152-times the 5 mg clinical dose in rats and rabbits, respectively, based on AUC. Saxagliptin crosses the placenta into the fetus following dosing in pregnant rats. In a prenatal and postnatal development study, no adverse developmental effects were observed in maternal rats administered saxagliptin from gestation day 6 through lactation day 21 at exposures up to 470-times the 5 mg clinical dose, based on AUC.
Metformin HCl Metformin HCl did not cause adverse developmental effect when administered to pregnant Sprague Dawley rats and rabbits up to 600 mg/kg/day during the period of organogenesis. This represents an exposure of about 2- and 6-times a 2,000 mg clinical dose based on body surface area (mg/m 2 ) for rats and rabbits, respectively. Saxagliptin and Metformin Saxagliptin and metformin coadministered to pregnant rats and rabbits during the period of organogenesis did not result in adverse developmental effects considered clinically relevant in either species.
Doses tested in rats provided exposure up to 100- and 10-times clinical exposure, and doses tested in rabbits provided exposure up to 249- and 1-times clinical exposure relative to the clinical dose of 5 mg saxagliptin and 2,000 mg metformin. Minor skeletal abnormalities associated with maternal toxicity were observed in rats. In rabbits, coadministration was poorly tolerated in a subset of mothers (12 of 30), resulting in death, moribundity, or abortion.
However, among surviving mothers with evaluable litters, maternal toxicity was limited to marginal reductions in body weight over the course of gestation days 21 to 29, associated with fetal body weight decrements of 7%, and a low incidence of delayed ossification of the fetal hyoid bone.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of saxagliptin and metformin hydrochloride extended-release tablets as an adjunct to diet and exercise to improve glycemic control in patients with type 2 diabetes mellitus have not been established in pediatric patients. Effectiveness of saxagliptin was not demonstrated in a 26-week, placebo-controlled, double-blind randomized clinical trial with a 26-week safety extension (NCT03199053) in 164 pediatric patients aged 10 to 17 years with inadequately controlled type 2 diabetes mellitus.
🧓 Geriatric Use ▾
8.5Geriatric Use Saxagliptin and Metformin Hydrochloride Extended-Release Tablets Elderly patients are more likely to have decreased renal function. Assess renal function more frequently in the elderly [ see Warnings and Precautions (5.1) and Clinical Pharmacology (12.3) ]. Saxagliptin In the seven, double-blind, controlled clinical safety and efficacy trials of saxagliptin, a total of 4751 (42.0%) of the 11301 patients randomized to saxagliptin were 65 years and over, and 1210 (10.7%) were 75 years and over.
No overall differences in safety or effectiveness were observed between patients 65 years of age and older and younger adult patients. Metformin HCl Controlled clinical trials of metformin did not include sufficient numbers of elderly patients to determine whether they respond differently than younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy and the higher risk of lactic acidosis.
Assess renal function more frequently in elderly patients [ see Warnings and Precautions (5.1) ].
🆘 Overdosage ▾
10 OVERDOSAGE Saxagliptin In a controlled clinical trial, once-daily, orally administered saxagliptin in healthy subjects at doses up to 400 mg daily for 2 weeks (80-times the MRHD) had no dose-related clinical adverse reactions and no clinically meaningful effect on QTc interval or heart rate. In the event of an overdose, initiate appropriate supportive treatment as dictated by the patient’s clinical status. Saxagliptin and its active metabolite are removed by hemodialysis (23% of dose over 4 hours).
Contact the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdosage management recommendations. Metformin HCl Overdose of metformin HCl has occurred, including ingestion of amounts greater than 50 grams. Hypoglycemia was reported in approximately 10% of cases, but no causal association with metformin HCl has been established.
Lactic acidosis has been reported in approximately 32% of metformin overdose cases [ see Warnings and Precautions (5.1) ]. Metformin is dialyzable with a clearance of up to 170 mL/min under good hemodynamic conditions. Therefore, hemodialysis may be useful for removal of accumulated drug from patients in whom metformin overdosage is suspected.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Saxagliptin and Metformin Hydrochloride Extended-Release Tablets Saxagliptin and metformin hydrochloride extended-release tablets contain two antihyperglycemic medications: saxagliptin, a dipeptidyl-peptidase-4 (DPP4) inhibitor, and metformin HCl, a biguanide. Saxagliptin Increased concentrations of the incretin hormones such as glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP) are released into the bloodstream from the small intestine in response to meals.
These hormones cause insulin release from the pancreatic beta cells in a glucose-dependent manner but are inactivated by the DPP4 enzyme within minutes. GLP-1 also lowers glucagon secretion from pancreatic alpha cells, reducing hepatic glucose production. In patients with type 2 diabetes mellitus, concentrations of GLP-1 are reduced but the insulin response to GLP-1 is preserved.
Saxagliptin is a competitive DPP4 inhibitor that slows the inactivation of the incretin hormones, thereby increasing their bloodstream concentrations and reducing fasting and postprandial glucose concentrations in a glucose-dependent manner in patients with type 2 diabetes mellitus. Metformin HCl Metformin improves glucose tolerance in patients with type 2 diabetes mellitus, lowering both basal and postprandial plasma glucose. Metformin decreases hepatic glucose production, decreases intestinal absorption of glucose, and improves insulin sensitivity by increasing peripheral glucose uptake and utilization.
Unlike sulfonylureas, metformin does not produce hypoglycemia in patients with type 2 diabetes mellitus or in healthy subjects except in unusual circumstances [ see Warnings and Precautions (5.5) ] and does not cause hyperinsulinemia. With metformin therapy, insulin secretion remains unchanged while fasting insulin levels and day-long plasma insulin response may actually decrease.
12.2Pharmacodynamics Saxagliptin In patients with type 2 diabetes mellitus, administration of saxagliptin inhibits DPP4 enzyme activity for a 24-hour period. After an oral glucose load or a meal, this DPP4 inhibition resulted in a 2- to 3-fold increase in circulating levels of active GLP-1 and GIP, decreased glucagon concentrations, and increased glucose-dependent insulin secretion from pancreatic beta cells. The rise in insulin and decrease in glucagon were associated with lower fasting glucose concentrations and reduced glucose excursion following an oral glucose load or a meal.
Cardiac Electrophysiology Saxagliptin In a randomized, double-blind, placebo-controlled, 4-way crossover, active comparator trial using moxifloxacin in 40 healthy subjects, saxagliptin was not associated with clinically meaningful prolongation of the QTc interval or heart rate at daily doses up to 40 mg (8-times the MRHD).
12.3Pharmacokinetics Saxagliptin and Metformin Hydrochloride Extended-Release Tablets Bioequivalence and food effect of saxagliptin and metformin hydrochloride extended-release tablets were characterized under low calorie diet. The low calorie diet consisted of 324 kcal with meal composition that contained 11.1% protein, 10.5% fat, and 78.4% carbohydrate. The results of bioequivalence studies in healthy subjects demonstrated that saxagliptin and metformin hydrochloride extended-release combination tablets are bioequivalent to coadministration of corresponding doses of saxagliptin (ONGLYZA ® ) and metformin HCl extended-release as individual tablets under fed conditions.
Saxagliptin The pharmacokinetics of saxagliptin and its active metabolite, 5-hydroxy saxagliptin were similar in healthy subjects and in patients with type 2 diabetes mellitus. The C max and AUC values of saxagliptin and its active metabolite increased proportionally in the 2.5 to 400 mg dose range. Following a 5 mg single oral dose of saxagliptin to healthy subjects, the mean plasma AUC values for saxagliptin and its active metabolite were 78 ng•h/mL and 214 ng•h/mL, resp…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Saxagliptin and Metformin Hydrochloride Extended-Release Tablets Saxagliptin and metformin hydrochloride extended-release tablets contain two antihyperglycemic medications: saxagliptin, a dipeptidyl-peptidase-4 (DPP4) inhibitor, and metformin HCl, a biguanide. Saxagliptin Increased concentrations of the incretin hormones such as glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP) are released into the bloodstream from the small intestine in response to meals.
These hormones cause insulin release from the pancreatic beta cells in a glucose-dependent manner but are inactivated by the DPP4 enzyme within minutes. GLP-1 also lowers glucagon secretion from pancreatic alpha cells, reducing hepatic glucose production. In patients with type 2 diabetes mellitus, concentrations of GLP-1 are reduced but the insulin response to GLP-1 is preserved.
Saxagliptin is a competitive DPP4 inhibitor that slows the inactivation of the incretin hormones, thereby increasing their bloodstream concentrations and reducing fasting and postprandial glucose concentrations in a glucose-dependent manner in patients with type 2 diabetes mellitus. Metformin HCl Metformin improves glucose tolerance in patients with type 2 diabetes mellitus, lowering both basal and postprandial plasma glucose. Metformin decreases hepatic glucose production, decreases intestinal absorption of glucose, and improves insulin sensitivity by increasing peripheral glucose uptake and utilization.
Unlike sulfonylureas, metformin does not produce hypoglycemia in patients with type 2 diabetes mellitus or in healthy subjects except in unusual circumstances [ see Warnings and Precautions (5.5) ] and does not cause hyperinsulinemia. With metformin therapy, insulin secretion remains unchanged while fasting insulin levels and day-long plasma insulin response may actually decrease.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied Saxagliptin and Metformin Hydrochloride Extended-Release Tablets, 5 mg/500 mg, are pink, film-coated, round, unscored tablets imprinted with SM3 over M in black ink on one side of the tablet and blank on the other side. They are available as follows: NDC 0378-8175-93 bottles of 30 tablets Saxagliptin and Metformin Hydrochloride Extended-Release Tablets, 5 mg/1000 mg, are pink, film-coated, capsule shaped, unscored tablets imprinted with SM6 over M in black ink on one side of the tablet and blank on the other side.
They are available as follows: NDC 0378-8177-93 bottles of 30 tablets Saxagliptin and Metformin Hydrochloride Extended-Release Tablets, 2.5 mg/1000 mg, are light peach, film-coated, capsule shaped, unscored tablets imprinted with SM4 over M in black ink on one side of the tablet and blank on the other side. They are available as follows: NDC 0378-8176-91 bottles of 60 tablets Storage and Handling Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure.
PHARMACIST: Dispense a Medication Guide with each prescription.
📋 Description ▾
11 DESCRIPTION Saxagliptin and metformin hydrochloride extended-release tablets contain two oral antihyperglycemic medications used in the management of type 2 diabetes mellitus: saxagliptin and metformin HCl. Saxagliptin Saxagliptin is an orally active inhibitor of the dipeptidyl-peptidase-4 (DPP4) enzyme. Saxagliptin hydrochloride dihydrate is described chemically as (1S,3S,5S)-2-[(2S)-Amino-(3-hydroxytricyclo[3.3.1.1 3,7 ]dec-1-yl)acetyl]-2-azabicyclo[3.1.0]hexane-3-carbonitrile hydrochloride dihydrate or (1S,3S,5S)-2-[(2S)-2-Amino-2-(3-hydroxyadamantan-1-yl)acetyl]-2-azabicyclo[3.1.0]hexane-3-carbonitrile hydrochloride dihydrate.
The empirical formula is C 18 H 25 N 3 O 2 •HCl•2 H 2 O and the molecular weight is 387.92. The structural formula is: Saxagliptin hydrochloride dihydrate is a white to off white, non-hygroscopic, crystalline powder. It is sparingly soluble in water at 24°C ± 3°C, slightly soluble in ethyl acetate, and soluble in methanol, ethanol, isopropyl alcohol, acetonitrile, acetone, and polyethylene glycol 400 (PEG 400).
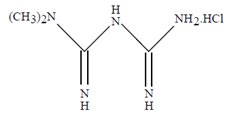
Metformin HCl Metformin hydrochloride, USP (1,1-Dimethylbiguanide monohydrochloride) is a white, crystalline powder with a molecular formula of C 4 H 11 N 5 •HCl and a molecular weight of 165.62. Metformin HCl is freely soluble in water, slightly soluble in alcohol, and is practically insoluble in acetone, ether, and chloroform. The pKa of metformin is 12.4.
The pH of a 1% aqueous solution of metformin HCl is 6.36. The structural formula is: Saxagliptin and Metformin Hydrochloride Extended-Release Tablets Saxagliptin and metformin hydrochloride extended-release tablets are available for oral administration as tablets containing either 6.149 mg saxagliptin hydrochloride dihydrate equivalent to 5 mg saxagliptin and 500 mg metformin hydrochloride (saxagliptin and metformin hydrochloride extended-release tablets 5 mg/500 mg), or 6.149 mg saxagliptin hydrochloride dihydrate equivalent to 5 mg saxagliptin and 1000 mg metformin hydrochloride (saxagliptin and metformin hydrochloride extended-release tablets 5 mg/1000 mg), or 3.075 mg saxagliptin hydrochloride dihydrate equivalent to 2.5 mg saxagliptin and 1000 mg metformin hydrochloride (saxagliptin and metformin hydrochloride extended-release tablets 2.5 mg/1000 mg).
Each film-coated tablet of saxagliptin and metformin hydrochloride extended-release contains the following inactive ingredients: carbomer homopolymer type A, colloidal silicon dioxide, hypromellose, magnesium stearate, polyethylene glycol, polyvinyl alcohol, povidone, red iron oxide, stearic acid, talc and titanium dioxide. The 2.5 mg/1000 mg tablets also contain yellow iron oxide. In addition, the black imprinting ink contains ammonium hydroxide, black iron oxide, propylene glycol and shellac glaze.
The biologically inert components of the tablet may occasionally remain intact during gastrointestinal transit and will be eliminated in the feces as a soft, hydrated mass. Saxagliptin Hydrochloride Dihydrate Structural Formula Metformin Hydrochloride Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Lactic Acidosis The risks of lactic acidosis due to the metformin component, its symptoms and conditions that predispose to its development, as noted in Warnings and Precautions (5.1) , should be explained to patients. Patients should be advised to discontinue saxagliptin and metformin hydrochloride extended-release tablets immediately and to promptly notify their health care provider if unexplained hyperventilation, myalgia, malaise, unusual somnolence, dizziness, slow or irregular heartbeat, sensation of feeling cold (especially in the extremities), or other nonspecific symptoms occur.
Gastrointestinal symptoms are common during initiation of metformin treatment and may occur during initiation of saxagliptin and metformin hydrochloride extended-release tablet therapy; however, patients should consult their physician if they develop unexplained symptoms. Although gastrointestinal symptoms that occur after stabilization are unlikely to be drug related, such an occurrence of symptoms should be evaluated to determine if it may be due to lactic acidosis or other serious disease. Patients should be counseled against excessive alcohol intake while receiving saxagliptin and metformin hydrochloride extended-release tablets.
Patients should be informed about the importance of regular testing of renal function and hematological parameters when receiving treatment with saxagliptin and metformin hydrochloride extended-release tablets. Instruct patients to inform their doctor that they are taking saxagliptin and metformin hydrochloride extended-release tablets prior to any surgical or radiological procedure, as temporary discontinuation of saxagliptin and metformin hydrochloride extended-release tablets may be required until renal function has been confirmed to be normal [ see Warnings and Precautions (5.1) ].
Pancreatitis Inform patients that acute pancreatitis has been reported during post-marketing use of saxagliptin. Educate patients that persistent severe abdominal pain, sometimes radiating to the back, which may or may not be accompanied by vomiting, is the hallmark symptom of acute pancreatitis. Instruct patients to promptly discontinue saxagliptin and metformin hydrochloride extended-release tablets and contact their health care provider if persistent severe abdominal pain occurs [ see Warnings and Precautions (5.2) ].
Heart Failure Inform patients of the signs and symptoms of heart failure. Before initiating saxagliptin and metformin hydrochloride extended-release tablets, ask patients if they have a history of heart failure or other risk factors for heart failure including moderate to severe renal impairment. Instruct patients to contact their health care provider as soon as possible if they experience symptoms of heart failure, including increasing shortness of breath, rapid increase in weight or swelling of the feet [ see Warnings and Precautions (5.3) ].
Hypoglycemia with Concomitant Use with Insulin or Insulin Secretagogues Inform patients that hypoglycemia can occur, particularly when insulin or an insulin secretagogue is used in combination with saxagliptin and metformin hydrochloride extended-release tablets. Educate patients about the risks, symptoms and appropriate management of hypoglycemia [ see Warnings and Precautions (5.5) ]. Hypersensitivity Reactions Patients should be informed that serious allergic (hypersensitivity) reactions, such as angioedema, anaphylaxis, and exfoliative skin conditions, have been reported during post-marketing use of saxagliptin.
If symptoms of these allergic reactions (such as rash, skin flaking or peeling, urticaria, swelling of the skin, or swelling of the face, lips, tongue, and throat that may cause difficulty in breathing or swallowing) occur, patients must stop taking saxagliptin and metformin hydrochloride extended-release tablets and seek medical advice promptly [ see…
💬 Medication Guide ▾
Medication Guide Saxagliptin and Metformin Hydrochloride Extended-Release Tablets, for oral use (sax″ a glip′ tin met for′ min hye″ droe klor′ ide) What is the most important information I should know about saxagliptin and metformin hydrochloride extended-release tablets? Serious side effects can happen in people taking saxagliptin and metformin hydrochloride extended-release tablets, including: 1. Lactic acidosis.
Metformin, one of the medicines in saxagliptin and metformin hydrochloride extended-release tablets, can cause a rare but serious condition called lactic acidosis (a build-up of an acid in the blood) that can cause death. Lactic acidosis is a medical emergency and must be treated in the hospital. Stop taking saxagliptin and metformin hydrochloride extended-release tablets and call your healthcare provider right away or go to the nearest hospital emergency room if you have any of the following symptoms of lactic acidosis: • feel very weak or tired • you have unusual (not normal) muscle pain • you have trouble breathing • you have stomach pains, nausea, vomiting or diarrhea • have unusual sleepiness or sleep longer than usual • feel cold, especially in your arms and legs • feel dizzy or lightheaded • have a slow or irregular heartbeat Most people who have had lactic acidosis with metformin have other things that, combined with the metformin, led to the lactic acidosis.
Tell your doctor if you have any of the following, because you have a higher chance for getting lactic acidosis with saxagliptin and metformin hydrochloride extended-release tablets if you: • have severe kidney problems or your kidneys are affected by certain x-ray tests that use injectable dye • have liver problems • drink alcohol very often, or drink a lot of alcohol in short-term "binge" drinking • get dehydrated (lose a large amount of body fluids). This can happen if you are sick with a fever, vomiting, or diarrhea.
Dehydration can also happen when you sweat a lot with activity or exercise and do not drink enough fluids • are 65 years of age or older • have surgery • have a heart attack, severe infection, or stroke • have a genetically inherited disease affecting mitochondria (the energy-producing parts within cells) such as mitochondrial encephalomyopathy with lactic acidosis, and stroke-like episodes (MELAS) syndrome and maternally inherited diabetes and deafness (MIDD). The best way to keep from having a problem with lactic acidosis from metformin is to tell your doctor if you have any of the problems in the list above.
Your doctor may decide to stop your saxagliptin and metformin hydrochloride extended-release tablets for a while if you have any of these things. Saxagliptin and metformin hydrochloride extended-release tablets can have other serious side effects. See “What are the possible side effects of saxagliptin and metformin hydrochloride extended-release tablets?” .
2. Inflammation of the pancreas (pancreatitis) which may be severe and lead to death. Certain medical problems make you more likely to get pancreatitis.
Before you start taking saxagliptin and metformin hydrochloride extended-release tablets: Tell your healthcare provider if you have ever had: • inflammation of your pancreas (pancreatitis) • a history of alcoholism • stones in your gallbladder (gallstones) • high blood triglyceride levels Stop taking saxagliptin and metformin hydrochloride extended-release tablets and contact your healthcare provider right away if you have pain in your stomach area (abdomen) that is severe and will not go away. The pain may be felt going from your abdomen through to your back.
The pain may happen with or without vomiting. These may be symptoms of pancreatitis. 3.
Heart failure. Heart failure means your heart does not pump blood well enough. Before you start taking saxagliptin and metformin hydrochloride extended-release tablets: Tell your healthcare provider if you: • have ever had heart failure or have problems with your kidneys.
Contact your…