
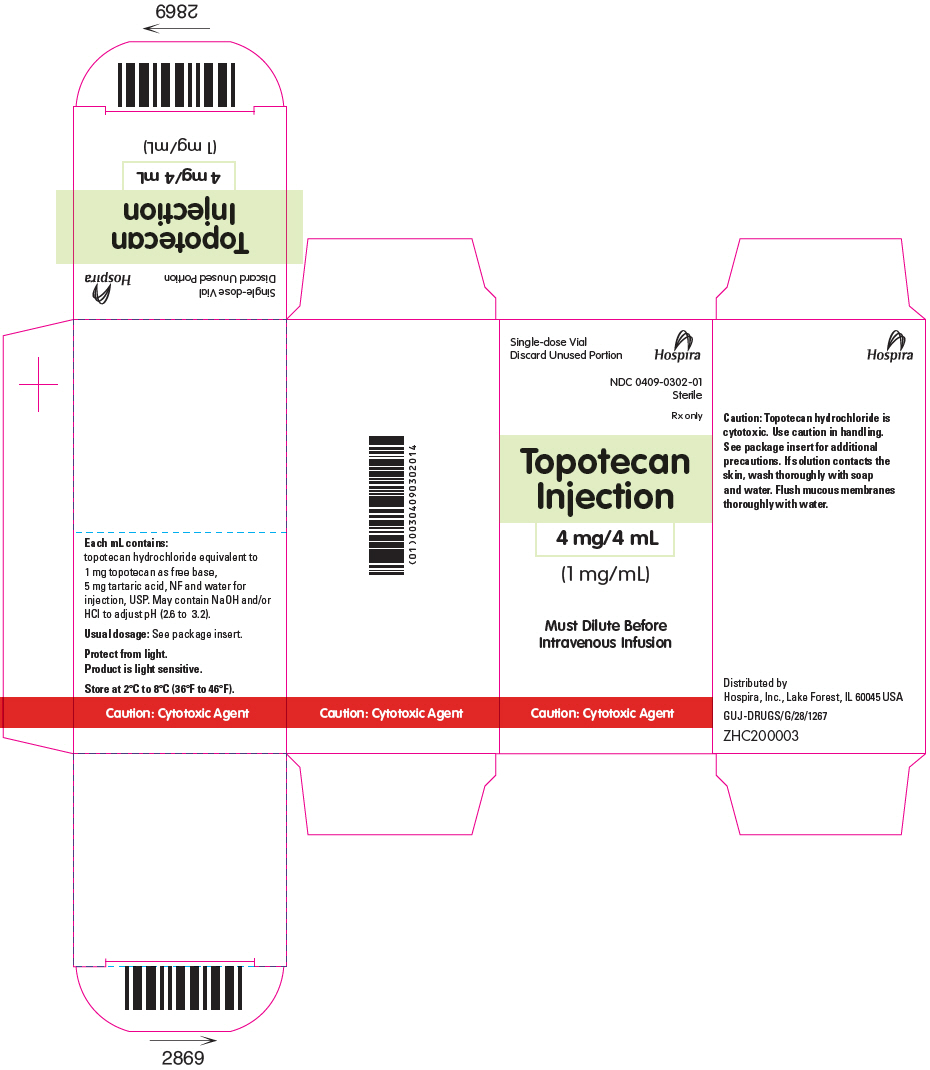
Topotecan 1 mg/mL Injection, Solution, Concentrate — NDC 0409-0302-01 (Billing 00409-0302-01)
This is a package of Topotecan 1 mg/mL Injection, Solution, Concentrate from Hospira, Inc., marketed since Feb 2011 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0409-0302-01 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0409 labeler · 0302 product · 01 package
- Package marketed since
- Feb 21, 2011
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 0409030201 4
- Medicaid fills, this package
- 1,078 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 067043
- GCN: 29519
- GPI-14 (Medi-Span): 21550080102020
- HICL (First Databank): 011381
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 1799424
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Topoisomerase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Topotecan injection is used to treat ovarian cancer (cancer that begins in the female reproductive organs where eggs are formed) and small cell lung cancer (a type of cancer that begins in the lungs) that have spread and did not improve after treatment with other medications. It is also used together with other medications to treat cervical cancer (cancer that begins in the opening of the uterus [womb]) that has not improved or has come back after other treatments. Topotecan is in a class of medications called topoisomerase type I inhibitors. It works by killing cancer cells.
Read the full MedlinePlus article ↗- It’s a chemotherapy medicine. Depending on the product, it treats small cell lung cancer, metastatic ovarian cancer, and, with cisplatin, advanced or recurrent cervical cancer. Hyc...
- The injection is given into a vein by your care team over about 30 minutes, in repeated 21-day courses. Hycamtin capsules are taken by mouth. Your team sets the schedule, so follow...
- Low blood counts are the most common, along with nausea, vomiting, hair loss, diarrhea or constipation, tiredness and fever. Your blood will be checked often to keep an eye on this...
- Call right away for fever, chills or other signs of infection, since low white blood cells can lead to serious infection. Also call for severe belly pain or diarrhea, new cough or...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Topotecan — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $19.65 | $78.62 / 4 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J9351 | $2.759 / J9351 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00409-0302-01 You're viewing this Main listing | 1 VIAL, SINGLE-DOSE in 1 CARTON / 4 mL in 1 VIAL, SINGLE-DOSE | 2011-02-21 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Topotecan 1 mg/mLthis 00409-0302-01 | Hospira, | 1 vial | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Topotecan inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
5 mg / 1 mL
UNII W4888I119H
Tartaric acid is a natural organic acid found in grapes and tamarinds. In medicines, it works as a buffer to control acidity, an antioxidant to prevent spoilage, and sometimes a flavoring or binding agent.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Hospira, Inc. labeler code 00409
- Gemcitabine 38 mg/mL Injection, Powder, Lyophilized, For Solution NDC 0409-0185-01
- Gemcitabine 38 mg/mL Injection, Powder, Lyophilized, For Solution NDC 0409-0186-01
- GEMCITABINE 38 mg/mL Injection, Powder, Lyophilized, For Solution NDC 0409-0187-01
- Docetaxel 10 mg/mL Injection, Solution NDC 0409-0201-02
- MILRINONE LACTATE 1 mg/mL Injection, Solution NDC 0409-0212-01
- Meropenem 500 mg/10mL Injection, Powder, For Solution NDC 0409-0222-10
- Bleomycin 30 [USP'U]/1 Injection, Powder, Lyophilized, For Solution NDC 0409-0323-20
- Bleomycin 15 [USP'U]/1 Injection, Powder, Lyophilized, For Solution NDC 0409-0332-20
- Docetaxel 20 mg/mL Injection, Solution NDC 0409-0365-01
- Docetaxel 20 mg/mL Injection, Solution NDC 0409-0366-01
- Docetaxel 20 mg/mL Injection, Solution NDC 0409-0367-01
- Docetaxel 20 mg/mL Injection, Solution NDC 0409-0368-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: MYELOSUPPRESSION Topotecan can cause severe myelosuppression. Administer first cycle only to patients with baseline neutrophil counts of greater than or equal to 1,500/mm 3 and platelet counts greater than or equal to 100,000/mm 3 . Monitor blood cell counts [see Warnings and Precautions (5.1) ] .
WARNING: MYELOSUPPRESSION See full prescribing information for complete boxed warning. Topotecan can cause severe myelosuppression. Administer first cycle only to patients with baseline neutrophil counts greater than or equal to 1,500/mm 3 and platelet count greater than or equal to 100,000/mm 3 .
Monitor blood cell counts. ( 2.2 , 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Topotecan Injection is indicated for the treatment of patients with small cell lung cancer (SCLC) with platinum-sensitive disease who progressed at least 60 days after initiation of first-line chemotherapy. Topotecan Injection is a topoisomerase inhibitor indicated for treatment of small cell lung cancer (SCLC) platinum-sensitive disease in patients who progressed at least 60 days after initiation of first-line chemotherapy. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Recommended dosage : 1.5 mg/m 2 by intravenous infusion over 30 minutes daily for 5 consecutive days, starting on Day 1 of a 21-day cycle. ( 2.2 ) Renal impairment : Reduce dose for creatinine clearance (CLcr) of 20 to 39 mL/min. ( 2.4 )
2.1Important Safety Information Verify dosage using body surface area. Do not exceed a single dose of 4 mg intravenously.
2.2Recommended Dosage for Small Cell Lung Cancer The recommended dosage of Topotecan Injection is 1.5 mg/m 2 by intravenous infusion over 30 minutes daily for 5 consecutive days, starting on Day 1 of a 21-day cycle.
2.3Dosage Modifications for Adverse Reactions Hematologic Do not administer subsequent cycles of Topotecan Injection until neutrophils recover to greater than 1,000/mm 3 , platelets recover to greater than 100,000/mm 3 , and hemoglobin levels recover to greater than or equal to 9 g/dL (with transfusion if necessary). Reduce the dose of Topotecan Injection to 1.25 mg/m 2 /day for: neutrophil counts of less than 500/mm 3 or administer granulocyte-colony stimulating factor (G-CSF) starting no sooner than 24 hours following the last dose platelet counts less than 25,000/mm 3 during previous cycle
2.4Dosage Modification for Renal Impairment Reduce the dose of Topotecan Injection to 0.75 mg/m 2 /day for patients with creatinine clearance (CLcr) of 20 to 39 mL/min (calculated with the Cockcroft-Gault method using ideal body weight) [see Clinical Pharmacology (12.3) ] .
2.5Preparation and Administration Topotecan Injection is a cytotoxic drug. Follow applicable special handling and disposable procedures. 1 Withdraw the appropriate volume from the vial and discard any unused portion.
Dilute Topotecan Injection in a minimum of 50 mL of 0.9% Sodium Chloride Injection, USP or 5% Dextrose Injection, USP prior to administration. Infuse diluted Topotecan Injection over 30 minutes. Store diluted Topotecan Injection at 20°C and 25°C (68°F and 77°F) in ambient lighting conditions for no more than 24 hours.
Discard unused portion after 24 hours. Visually inspect for particulate matter and discoloration prior to administration, whenever solution and container permit. Discard if particulate matter or discoloration is observed.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: 4 mg/4 mL (1 mg/mL topotecan free base) clear, yellow to yellow-green solution in single-dose vial. Injection : 4 mg/4 mL (1 mg/mL topotecan free base) solution in single-dose vial. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Topotecan Injection is contraindicated in patients who have a history of severe hypersensitivity reactions to topotecan. Reactions have included anaphylactoid reactions [see Adverse Reactions (6.2) ] . History of severe hypersensitivity reactions to topotecan. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Interstitial lung disease (ILD): Fatal cases have occurred. Permanently discontinue if ILD confirmed. ( 5.2 ) Extravasation and tissue injury : Severe cases have occurred. If extravasation occurs, immediately stop administration and institute recommended management procedures. ( 5.3 ) Embryo-fetal toxicity : Can cause fetal harm. Advise women of potential risk to the fetus. ( 5.4 , 8.1 , 8.3 )
5.1Myelosuppression Topotecan can cause severe myelosuppression. Grade 4 neutropenia occurred in 78% of 879 patients, with a median duration of 7 days and was most common during Cycle 1 (58% of patients). Grade 4 neutropenia associated with infection occurred in 13% and febrile neutropenia occurred in 5%.
Sepsis occurred in 4% and was fatal in 1%. Grade 4 thrombocytopenia occurred in 27%, with a median duration of 5 days. Grade 3 or 4 anemia occurred in 37% of patients.
Topotecan can cause fatal typhlitis (neutropenic enterocolitis). Consider the possibility of typhlitis in patients presenting with fever, neutropenia, and abdominal pain. Administer the first cycle of Topotecan Injection only to patients with a baseline neutrophil count of greater than or equal to 1,500/mm 3 and a platelet count greater than or equal to 100,000/mm 3 .
Monitor blood counts frequently during treatment. Withhold and reduce dose of Topotecan Injection based on neutrophil counts, platelet counts and hemoglobin levels [see Dosage and Administration (2.3) ] .
5.2Interstitial Lung Disease Interstitial lung disease (ILD), including fatalities, has occurred with topotecan [see Adverse Reactions (6.2) ] . Underlying risk factors include history of ILD, pulmonary fibrosis, lung cancer, thoracic radiation, and use of pneumotoxic drugs and/or colony stimulating factors. Monitor patients for pulmonary symptoms indicative of ILD (e.g., cough, fever, dyspnea, and/or hypoxia), and discontinue Topotecan Injection if a new diagnosis of ILD is confirmed.
5.3Extravasation and Tissue Injury Extravasation with topotecan has been observed; severe cases have been reported. If signs or symptoms of extravasation occur, immediately stop administration of Topotecan Injection and institute recommended management procedures [see Adverse Reactions (6.2) ] .
5.4Embryo-Fetal Toxicity Based on animal data, topotecan can cause fetal harm when administered to a pregnant woman. Topotecan caused embryolethality, fetotoxicity, and teratogenicity in rats and rabbits when administered during organogenesis. Advise women of the potential risk to a fetus.
Advise females of reproductive potential to use effective contraception during treatment and for 6 months after the last dose of Topotecan Injection. Advise males with a female partner of reproductive potential to use effective contraception during treatment with Topotecan Injection and for 3 months after the last dose [see Use in Specific Populations (8.1 , 8.3) , Nonclinical Toxicology (13.1) ] .
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described elsewhere in the labeling: Myelosuppression [see Warnings and Precautions (5.1) ] Interstitial Lung Disease [see Warnings and Precautions (5.2) ] Extravasation and Tissue Injury [see Warnings and Precautions (5.3) ] The most common Grade 3 or 4 hematologic adverse reactions (incidence >5%) were: neutropenia , anemia , thrombocytopenia, and febrile neutropenia. ( 6.1 ) The most common non-hematologic adverse reactions (incidence >5%) (all grades) were asthenia, dyspnea, nausea, pneumonia, abdominal pain, and fatigue.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Hospira, Inc. at 1-800-441-4100 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in practice. The data in Warnings and Precautions reflect exposure to topotecan from 8 trials in which 879 patients with small cell lung cancer (SCLC) and other solid tumors received topotecan 1.5 mg/m 2 by intravenous infusion daily for 5 consecutive days, starting on Day 1 of a 21-day cycle.
Small Cell Lung Cancer (SCLC) The safety of topotecan was evaluated in randomized, comparative trial in patients with recurrent or progressive SCLC (Study 090) [see Clinical Studies (14.1) ]. Table 1 shows the Grade 3 or 4 hematologic and non-hematologic adverse reactions in patients with SCLC. Table 1.
Adverse Reactions Occurring in ≥5% of Patients with Small Cell Lung Cancer in Study 090 Adverse Reactions Topotecan (n = 107) CAV CAV = cyclophosphamide, doxorubicin and vincristine. (n = 104) Grade 3–4 (%) Grade 3–4 (%) Hematologic Grade 4 neutropenia (< 500/mm 3 ) 70 72 Grade 3 or 4 anemia (Hgb < 8 g/dL) 42 20 Grade 4 thrombocytopenia (< 25,000/mm 3 ) 29 5 Febrile neutropenia 28 26 Non-Hematologic Respiratory, thoracic, and mediastinal Dyspnea 9 14 Pneumonia 8 6 General and administrative site conditions Asthenia 9 7 Fatigue 6 10 Pain Pain includes body pain, skeletal pain, and back pain.
5 7 Gastrointestinal Nausea 8 6 Abdominal pain 6 4 Infections Sepsis Death related to sepsis occurred in 3% of patients receiving topotecan and 1% of patients receiving CAV. 5 5 Hepatobiliary Disorders Based on 879 patients with small cell lung cancer or another solid tumor who were treated with topotecan, Grade 3 or 4 elevated aspartate (AST) or alanine transaminase (ALT) occurred in 4% and Grade 3 or 4 elevated bilirubin occurred in less than 2% of patients.
6.2Postmarketing Experience The following reactions have been identified during postapproval use of topotecan. Because these reactions are reported voluntarily from a population of unknown size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Blood and Lymphatic System Severe bleeding (in association with thrombocytopenia) Hypersensitivity Allergic manifestations, anaphylactoid reactions, angioedema Gastrointestinal Abdominal pain potentially associated with neutropenic enterocolitis, gastrointestinal perforation Pulmonary Interstitial lung disease Skin and Subcutaneous Tissue Severe dermatitis, severe pruritus General and Administration Site Conditions Extravasation, mucosal inflammation
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation : Advise not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary Based on animal data and its mechanism of action, Topotecan Injection can cause fetal harm when administered to a pregnant woman. There are no available clinical data on the use of topotecan in pregnancy. Topotecan caused embryolethality, fetotoxicity, and teratogenicity in rats and rabbits when administered during organogenesis at doses similar to the clinical dose (see Data ).
Advise pregnant women of the potential risk to a fetus. In the U.S. general population, the background risk of major birth defects is 2% to 4% and of miscarriage is 15% to 20% of clinically recognized pregnancies. Data Animal Data In rabbits, an intravenous dose of 0.10 mg/kg/day [(about equal to the 1.5 mg/m 2 clinical dose based on body surface area (BSA)] given on Days 6 through 20 of gestation caused maternal toxicity, embryolethality, and reduced fetal body weight.
In the rat, an intravenous dose of 0.23 mg/kg/day (about equal to the 1.5 mg/m 2 clinical dose based on BSA) given for 14 days before mating through gestation Day 6 caused fetal resorption, microphthalmia, pre-implant loss, and mild maternal toxicity. Administration of an intravenous dose of 0.10 mg/kg/day (about half the 1.5 mg/m 2 clinical dose based on BSA) given to rats on Days 6 through 17 of gestation caused an increase in post-implantation mortality. This dose also caused an increase in total fetal malformations.
The most frequent malformations were of the eye (microphthalmia, anophthalmia, rosette formation of the retina, coloboma of the retina, ectopic orbit), brain (dilated lateral and third ventricles), skull, and vertebrae.
8.2Lactation Risk Summary There are no data on the presence of topotecan or its metabolites in human milk or their effects on the breastfed infant or on milk production. Lactating rats excrete high concentrations of topotecan in milk (see Data ). Because of the potential for serious adverse reactions in breastfed infants, advise women not to breastfeed during treatment with Topotecan Injection and for 1 week after the last dose.
Data Following intravenous administration of topotecan to lactating rats at a dose of 4.72 mg/m 2 (about twice the 1.5 mg/m 2 clinical dose based on BSA), topotecan was excreted into milk at concentrations up to 48-fold higher than those in plasma.
8.3Females and Males of Reproductive Potential Pregnancy Testing Verify pregnancy status of females of reproductive potential prior to initiating Topotecan Injection [see Use in Specific Populations (8.1) ] . Contraception Topotecan can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1) ] . Females Advise female patients of reproductive potential to use effective contraception during treatment with Topotecan Injection and for 6 months after the last dose.
Males Topotecan may damage spermatozoa, resulting in possible genetic and fetal abnormalities. Advise males with a female partner of reproductive potential to use effective contraception during treatment with Topotecan Injection and for 3 months after the last dose [see Nonclinical Toxicology (13.1) ] . Infertility Females Topotecan may have both acute and long-term effects on fertility [see Nonclinical Toxicology (13.1) ] .
Males Effects on spermatogenesis occurred in animals administered topotecan [see Nonclinical Toxicology (13.1) ] .
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
8.5Geriatric Use Of the 879 patients with SCLC or another solid tumor who received topotecan in clinical trials, 32% were aged 65 years and older, while 3.8% were aged 75 years and older. No overall differences in effectiveness or safety were observed between these patients and younger patients and other reported clinical experience has not identified differences in responses between the elderly and younger patients.
8.6Renal Impairment Reduce the dose of Topotecan… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on animal data and its mechanism of action, Topotecan Injection can cause fetal harm when administered to a pregnant woman. There are no available clinical data on the use of topotecan in pregnancy. Topotecan caused embryolethality, fetotoxicity, and teratogenicity in rats and rabbits when administered during organogenesis at doses similar to the clinical dose (see Data ).
Advise pregnant women of the potential risk to a fetus. In the U.S. general population, the background risk of major birth defects is 2% to 4% and of miscarriage is 15% to 20% of clinically recognized pregnancies. Data Animal Data In rabbits, an intravenous dose of 0.10 mg/kg/day [(about equal to the 1.5 mg/m 2 clinical dose based on body surface area (BSA)] given on Days 6 through 20 of gestation caused maternal toxicity, embryolethality, and reduced fetal body weight.
In the rat, an intravenous dose of 0.23 mg/kg/day (about equal to the 1.5 mg/m 2 clinical dose based on BSA) given for 14 days before mating through gestation Day 6 caused fetal resorption, microphthalmia, pre-implant loss, and mild maternal toxicity. Administration of an intravenous dose of 0.10 mg/kg/day (about half the 1.5 mg/m 2 clinical dose based on BSA) given to rats on Days 6 through 17 of gestation caused an increase in post-implantation mortality. This dose also caused an increase in total fetal malformations.
The most frequent malformations were of the eye (microphthalmia, anophthalmia, rosette formation of the retina, coloboma of the retina, ectopic orbit), brain (dilated lateral and third ventricles), skull, and vertebrae.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 879 patients with SCLC or another solid tumor who received topotecan in clinical trials, 32% were aged 65 years and older, while 3.8% were aged 75 years and older. No overall differences in effectiveness or safety were observed between these patients and younger patients and other reported clinical experience has not identified differences in responses between the elderly and younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE Overdoses (up to 10-fold of the recommended dose) have occurred in patients receiving intravenous topotecan. The primary complication of overdosage is myelosuppression. Elevated hepatic enzymes, mucositis, gastrointestinal toxicity and skin toxicity have occurred with overdosages. If an overdose is suspected, monitor the patient closely for myelosuppression and institute supportive-care measures as appropriate.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Topoisomerase I relieves torsional strain in DNA by inducing reversible single-strand breaks. Topotecan binds to the topoisomerase I-DNA complex and prevents re-ligation of these single-strand breaks. The cytotoxicity of topotecan is thought to be due to double-strand DNA damage produced during DNA synthesis, when replication enzymes interact with the ternary complex formed by topotecan, topoisomerase I, and DNA.
Mammalian cells cannot efficiently repair these double-strand breaks.
12.3Pharmacokinetics Following administration of topotecan at doses of 0.5 to 1.5 mg/m 2 (0.3 to 1 times the recommended dose) administered as a 30-minute infusion, area under the curve (AUC) increases approximately proportional with dose. Distribution Protein binding of topotecan is approximately 35%. Elimination The terminal half-life of topotecan is 2 to 3 hours following intravenous administration.
Metabolism Topotecan undergoes a reversible pH-dependent hydrolysis of its pharmacologically active lactone moiety. At pH ≤ 4, the lactone is exclusively present, whereas the ring-opened hydroxy-acid form predominates at physiologic pH. Topotecan is metabolized to an N-demethylated metabolite in vitro.
The mean metabolite: parent AUC ratio was about 3% for total topotecan and topotecan lactone following intravenous administration. Excretion The overall recovery of total topotecan and its N-desmethyl metabolite in urine and feces over 9 days averaged 73% ± 2% following an intravenous dose. Mean values of 51% ± 3% as total topotecan and 3% ± 1% as N-desmethyl topotecan were excreted in the urine.
Fecal elimination of total topotecan accounted for 18% ± 4% while fecal elimination of N-desmethyl topotecan was 1.7% ± 0.6%. An O-glucuronidation metabolite of topotecan and N-desmethyl topotecan has been identified in the urine. Specific Populations No clinically significant differences in the pharmacokinetics of topotecan were observed based on age, sex, or hepatic impairment following intravenous administration.
Patients with Renal Impairment Compared to patients with CLcr > 60 mL/min (calculated by the Cockcroft-Gault method using ideal body weight), plasma clearance of topotecan lactone decreased by 33% in patients with CLcr 40 to 60 mL/min and decreased by 65% in patients with CLcr 20 to 39 mL/min. The effect on topotecan pharmacokinetics in patients with CLcr < 20 mL/min is unknown [see Dosage and Administration (2.4) ] . Drug Interaction Studies Clinical Studies No clinically significant changes in topotecan pharmacokinetics were observed when coadministered cisplatin.
No clinically significant changes in the pharmacokinetics of free platinum were observed in patients coadministered cisplatin with topotecan. In Vitro Studies Topotecan does not inhibit CYP1A2, CYP2A6, CYP2C8/9, CYP2C19, CYP2D6, CYP2E, CYP3A, or CYP4A or dihydropyrimidine dehydrogenase.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Topoisomerase I relieves torsional strain in DNA by inducing reversible single-strand breaks. Topotecan binds to the topoisomerase I-DNA complex and prevents re-ligation of these single-strand breaks. The cytotoxicity of topotecan is thought to be due to double-strand DNA damage produced during DNA synthesis, when replication enzymes interact with the ternary complex formed by topotecan, topoisomerase I, and DNA.
Mammalian cells cannot efficiently repair these double-strand breaks.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Topotecan Injection is supplied in 4 mg/4 mL (1 mg/mL topotecan free base) single-dose vials. Each vial contains 4 mL of the sterile, clear, yellow to yellow-green solution. NDC 0409-0302-01 (Package of 1 single-dose vial) Store refrigerated between 2°C and 8°C (36°F and 46°F) in the original carton to protect from light.
Discard unused portion. Topotecan Injection is a cytotoxic drug. Follow applicable handling and disposal procedures.
1
📦 Storage and Handling ▾
Store refrigerated between 2°C and 8°C (36°F and 46°F) in the original carton to protect from light. Discard unused portion. Topotecan Injection is a cytotoxic drug. Follow applicable handling and disposal procedures. 1
📋 Description ▾
11 DESCRIPTION Topotecan is a semi-synthetic derivative of camptothecin and a topoisomerase inhibitor. The chemical name for topotecan hydrochloride is (S)-10-[(dimethylamino)methyl]-4-ethyl-4,9-dihydroxy-1 H -pyrano[3',4':6,7]indolizino[1,2- b ]quinoline-3,14-(4 H ,12 H )-dione 1.25 hydrochloride. It has the molecular formula C 23 H 23 N 3 O 5 ∙xHCl (x=1.25) and a molecular weight of 467.02.
It is soluble in water and melts with decomposition at 213°C to 218°C. Topotecan hydrochloride has the following structural formula: Topotecan Injection for intravenous use is supplied as a sterile, non-pyrogenic, clear, yellow to yellow-green solution in single-dose vial at a topotecan free base concentration of 4 mg/4 mL (1 mg/mL). Each mL contains 1 mg topotecan free base (equivalent to 1.11 mg of topotecan hydrochloride), 5 mg tartaric acid, NF and water for injection, USP.
It may also contain hydrochloric acid and/or sodium hydroxide to adjust the pH. The solution pH ranges from 2.6 to 3.2. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Myelosuppression Inform patients that topotecan decreases blood cell counts such as white blood cells, platelets, and red blood cells. Advise patients to notify their healthcare provider promptly for fever, other signs of infection, or bleeding [see Warnings and Precautions (5.1) ] . Interstitial Lung Disease (ILD) Inform patients of the risks of severe ILD.
Advise patients to contact their healthcare provider immediately to report new or worsening respiratory symptoms [see Warnings and Precautions (5.2) ] . Embryo-Fetal Toxicity Advise females of reproductive potential and males with female partners of reproductive potential of the potential risk to a fetus. Advise women to contact their healthcare provider if they become pregnant, or if pregnancy is suspected during treatment with Topotecan Injection [see Warnings and Precautions (5.4) , Use in Specific Populations (8.1 , 8.3) ] .
Advise females of reproductive potential to use effective contraception during treatment with Topotecan Injection and for 6 months after the last dose [see Use in Specific Populations (8.1 , 8.3) ] . Advise males with a female sexual partner of reproductive potential to use effective contraception during treatment with Topotecan Injection and for 3 months after the last dose [see Use in Specific Populations (8.1 , 8.3) , Nonclinical Toxicology (13.1) ]. Lactation Advise women to discontinue breastfeeding during treatment with Topotecan Injection and for at least 1 week after the last dose [see Use in Specific Populations (8.2) ] .
Infertility Advise male and female patients of the potential risk for impaired fertility [see Use in Specific Populations (8.3) , Nonclinical Toxicology (13.1) ] . Asthenia and Fatigue Advise patients that topotecan may cause asthenia or fatigue. These symptoms may impair the ability to safely drive or operate machinery.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Following administration of topotecan at doses of 0.5 to 1.5 mg/m 2 (0.3 to 1 times the recommended dose) administered as a 30-minute infusion, area under the curve (AUC) increases approximately proportional with dose. Distribution Protein binding of topotecan is approximately 35%. Elimination The terminal half-life of topotecan is 2 to 3 hours following intravenous administration.
Metabolism Topotecan undergoes a reversible pH-dependent hydrolysis of its pharmacologically active lactone moiety. At pH ≤ 4, the lactone is exclusively present, whereas the ring-opened hydroxy-acid form predominates at physiologic pH. Topotecan is metabolized to an N-demethylated metabolite in vitro.
The mean metabolite: parent AUC ratio was about 3% for total topotecan and topotecan lactone following intravenous administration. Excretion The overall recovery of total topotecan and its N-desmethyl metabolite in urine and feces over 9 days averaged 73% ± 2% following an intravenous dose. Mean values of 51% ± 3% as total topotecan and 3% ± 1% as N-desmethyl topotecan were excreted in the urine.
Fecal elimination of total topotecan accounted for 18% ± 4% while fecal elimination of N-desmethyl topotecan was 1.7% ± 0.6%. An O-glucuronidation metabolite of topotecan and N-desmethyl topotecan has been identified in the urine. Specific Populations No clinically significant differences in the pharmacokinetics of topotecan were observed based on age, sex, or hepatic impairment following intravenous administration.
Patients with Renal Impairment Compared to patients with CLcr > 60 mL/min (calculated by the Cockcroft-Gault method using ideal body weight), plasma clearance of topotecan lactone decreased by 33% in patients with CLcr 40 to 60 mL/min and decreased by 65% in patients with CLcr 20 to 39 mL/min. The effect on topotecan pharmacokinetics in patients with CLcr < 20 mL/min is unknown [see Dosage and Administration (2.4) ] . Drug Interaction Studies Clinical Studies No clinically significant changes in topotecan pharmacokinetics were observed when coadministered cisplatin.
No clinically significant changes in the pharmacokinetics of free platinum were observed in patients coadministered cisplatin with topotecan. In Vitro Studies Topotecan does not inhibit CYP1A2, CYP2A6, CYP2C8/9, CYP2C19, CYP2D6, CYP2E, CYP3A, or CYP4A or dihydropyrimidine dehydrogenase.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Small Cell Lung Cancer The efficacy of topotecan was studied in 426 patients with recurrent or progressive SCLC in a randomized, comparative trial and in 3 single-arm trials. Randomized Comparative Trial In a randomized, comparative trial, 211 patients were randomized 1:1 to received topotecan (1.5 mg/m 2 once daily intravenously for 5 days starting on Day 1 of a 21-day cycle) or CAV (cyclophosphamide 1,000 mg/m 2 , doxorubicin 45 mg/m 2 , vincristine 2 mg administered sequentially on Day 1 of a 21-day cycle). All patients were considered sensitive to first-line chemotherapy (responders who then subsequently progressed greater than or equal to 60 days after completion of first-line therapy).
A total of 77% of patients treated with topotecan and 79% of patients treated with CAV received platinum/etoposide with or without other agents as first-line chemotherapy. The efficacy outcome measures were overall response rate, response duration, time to progression and overall survival (OS). The results of the trial did not show statistically significant improvements in response rates, response duration, time to progression, and OS as shown in Table 2.
Table 2. Efficacy Results in Patients with Small Cell Lung Cancer Sensitive to First-Line Chemotherapy in Study 090 Parameter Topotecan (n = 107) CAV CAV = cyclophosphamide, doxorubicin and vincristine. (n = 104) Abbreviations: CI = confidence interval.
Overall response rate (95% CI) 24% (16% to 32%) 18% (11% to 26%) Complete response rate 0% 1% Partial response rate 24% 17% Response duration The calculation for duration of response was based on the interval between first response and time to progression. (months) Median (95% CI) 3.3 (3.0 to 4.1) 3.5 (3.0 to 5.3) Time to progression (months) Median (95% CI) 3.1 (2.6 to 4.1) 2.8 (2.5 to 3.2) Hazard ratio (95% CI) 0.92 (0.69 to 1.22) Overall survival (months) Median (95% CI) 5.8 (4.7 to 6.8) 5.7 (5.0 to 7.0) Hazard ratio (95% CI) 1.04 (0.78 to 1.39) The median time to response was similar in both arms: topotecan 6 weeks (2.4 weeks to 3.6 months) versus CAV 6 weeks (5.1 weeks to 4.2 months).
Changes on a disease-related symptom scale are presented in Table 3. It should be noted that not all patients had all symptoms, nor did all patients respond to all questions. Each symptom was rated on a 4-category scale with an improvement defined as a change in 1 category from baseline sustained over 2 cycles.
Limitations in interpretation of the rating scale and responses preclude formal statistical analysis. Table 3. Symptom Improvement Defined as improvement sustained over at least 2 cycles compared with baseline. in Patients with Small Cell Lung Cancer in Study 090 Symptom Topotecan (n = 107) CAV CAV = cyclophosphamide, doxorubicin and vincristine.
(n = 104) n Number of patients with baseline and at least 1 post-baseline assessment. % n % Shortness of breath 68 28 61 7 Interference with daily activity 67 27 63 11 Fatigue 70 23 65 9 Hoarseness 40 33 38 13 Cough 69 25 61 15 Insomnia 57 33 53 19 Anorexia 56 32 57 16 Chest pain 44 25 41 17 Hemoptysis 15 27 12 33 Single-Arm Trials Topotecan was also studied in 3 open-label, non-comparative trials (Studies 014, 092 and 053) in a total of 319 patients with recurrent or progressive SCLC after treatment with first-line chemotherapy.
In all 3 trials, patients were stratified as either sensitive (responders who then subsequently progressed greater than or equal to 90 days after completion of first-line therapy) or refractory (no response to first-line chemotherapy or who responded to first-line therapy and then progressed within 90 days of completing first-line therapy). Response rates ranged from 11% to 31% for sensitive patients and 2% to 7% for refractory patients. Median time to progression and median survival were similar in all 3 trials and the comparative trial.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity testing of topotecan has not been performed. Topotecan is known to be genotoxic to mammalian cells and is a probable carcinogen. Topotecan was mutagenic to L5178Y mouse lymphoma cells and clastogenic to cultured human lymphocytes with and without metabolic activation.
It was also clastogenic to mouse bone marrow. Topotecan did not cause mutations in bacterial cells. Topotecan given to female rats prior to mating at an intravenous dose of 1.4 mg/m 2 (about equal to the 1.5 mg/m 2 clinical dose based on BSA) caused superovulation possibly related to inhibition of follicular atresia.
This dose given to pregnant female rats also caused increased pre-implantation loss. A one month study in dogs given a daily intravenous topotecan dose of 0.4 mg/m 2 (about 0.25 times the 1.5 mg/m 2 clinical dose based on BSA) suggests that treatment may cause an increase in the incidence of multinucleated spermatogonial giant cells in the testes.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity testing of topotecan has not been performed. Topotecan is known to be genotoxic to mammalian cells and is a probable carcinogen. Topotecan was mutagenic to L5178Y mouse lymphoma cells and clastogenic to cultured human lymphocytes with and without metabolic activation.
It was also clastogenic to mouse bone marrow. Topotecan did not cause mutations in bacterial cells. Topotecan given to female rats prior to mating at an intravenous dose of 1.4 mg/m 2 (about equal to the 1.5 mg/m 2 clinical dose based on BSA) caused superovulation possibly related to inhibition of follicular atresia.
This dose given to pregnant female rats also caused increased pre-implantation loss. A one month study in dogs given a daily intravenous topotecan dose of 0.4 mg/m 2 (about 0.25 times the 1.5 mg/m 2 clinical dose based on BSA) suggests that treatment may cause an increase in the incidence of multinucleated spermatogonial giant cells in the testes.
📚 References ▾
15 REFERENCES 1. "OSHA Hazardous Drugs." OSHA . http://www.osha.gov/SLTC/hazardousdrugs/index.html.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 4 mg/4 mL Vial Label Topotecan Injection 4 mg/4 mL (1 mg/mL) Must Dilute Before Intravenous Infusion Caution: Cytotoxic agent PRINCIPAL DISPLAY PANEL - 4 mg/4 mL Vial Label
PRINCIPAL DISPLAY PANEL - 4 mg/4 mL Vial Carton Single-dose Vial Discard Unused Portion Hospira NDC 0409-0302-01 Sterile Rx only Topotecan Injection 4 mg/4 mL (1 mg/mL) Must Dilute Before Intravenous Infusion Caution: Cytotoxic Agent PRINCIPAL DISPLAY PANEL - 4 mg/4 mL Vial Carton
Medicaid utilization & spend
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |