
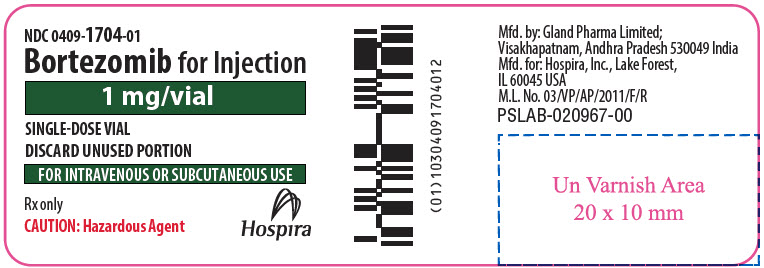
Bortezomib 1 mg Injection, Powder, Lyophilized, For Solution, 1 vial — NDC 0409-1704-01 (Billing 00409-1704-01)
This is a package of 1 vial of Bortezomib 1 mg Injection, Powder, Lyophilized, For Solution from Hospira, Inc., marketed since May 2022 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0409-1704-01 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0409 labeler · 1704 product · 01 package
- Package marketed since
- May 16, 2022
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 1 EA per package
- Barcode (UPC-A, from the NDC)
- 3 0409170401 5
- Medicaid fills, this package
- 124 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 071060
- GCN: 34747
- GPI-14 (Medi-Span): 21536015002110
- HICL (First Databank): 025202
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 2601542
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Proteasome Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Bortezomib is used to treat multiple myeloma (a type of cancer of the bone marrow). Bortezomib is also used to treat mantle cell lymphoma (a fast-growing cancer that begins in the cells of the immune system). Bortezomib is in a class of medications called proteasome inhibitors. It works by killing cancer cells.
Read the full MedlinePlus article ↗- It treats adults with multiple myeloma and mantle cell lymphoma. These are both cancers affecting blood-forming cells. Your oncology team decides how it fits into your plan.
- A healthcare professional gives it as an injection, into a vein or under the skin depending on the product. Your team sets the dose and schedule for you. You do not take it at home...
- Nausea, diarrhea, constipation, tiredness, low blood counts and numbness or tingling are common. Tell your team about them, since medicines can often help. Do not wait if the nerve...
- Call for fainting or severe dizziness, new shortness of breath or swelling, seizures, confusion, vision changes, unusual bleeding, or severe vomiting or diarrhea. These can signal...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Bortezomib — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $34.09 | — |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J9049 | $1.712 / J9049 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00409-1704-01 You're viewing this Main listing | 1 VIAL, SINGLE-DOSE in 1 CARTON / 1 INJECTION, POWDER, LYOPHILIZED, FOR SOLUTION in 1 VIAL, SINGLE-DOSE | 2022-05-16 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Bortezomib 1 mgthis 00409-1704-01 | Hospira, | 1 vial | — | AP | FDA listed | — |
| Bortezomib 1 mg 68083-0650-01 | Gland | 1 vial | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Hospira, Inc. labeler code 00409
- Atropine Sulfate .1 mg/mL Injection, Solution NDC 0409-1630-10
- Calcium Chloride 100 mg/mL Injection, Solution NDC 0409-1631-10
- Precedex DEXMEDETOMIDINE HYDROCHLORIDE 100 ug/mL Injection, Solution, Concentrate NDC 0409-1638-02
- Precedex DEXMEDETOMIDINE HYDROCHLORIDE 4 ug/mL Injection, Solution NDC 0409-1660-10
- Bortezomib 3.5 mg Injection, Powder, Lyophilized, For Solution NDC 0409-1700-01
- Bortezomib 2.5 mg Injection, Powder, Lyophilized, For Solution NDC 0409-1703-01
- Docetaxel 10 mg/mL Injection, Solution NDC 0409-1732-01
- Marcaine with Epinephrine BUPIVACAINE HYDROCHLORIDE AND EPINEPHRINE BITARTRATE 2.5 mg/mL; .0091 mg/mL Injection, Solution NDC 0409-1746-10
- Marcaine with Epinephrine BUPIVACAINE HYDROCHLORIDE AND EPINEPHRINE BITARTRATE 5 mg/mL; .0091 mg/mL Injection, Solution NDC 0409-1749-10
- Marcaine with Epinephrine BUPIVACAINE HYDROCHLORIDE AND EPINEPHRINE BITARTRATE 2.5 mg/mL; .0091 mg/mL Injection, Solution NDC 0409-1752-50
- Magnesium Sulfate 500 mg/mL Injection, Solution NDC 0409-1754-10
- Marcaine with Epinephrine BUPIVACAINE HYDROCHLORIDE AND EPINEPHRINE BITARTRATE 5 mg/mL; .0091 mg/mL Injection, Solution NDC 0409-1755-50
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Bortezomib for Injection is a proteasome inhibitor indicated for: • Treatment of adult patients with multiple myeloma. ( 1.1 ) • Treatment of adult patients with mantle cell lymphoma. ( 1.2 )
1.1Multiple Myeloma Bortezomib for Injection is indicated for the treatment of adult patients with multiple myeloma.
1.2Mantle Cell Lymphoma Bortezomib for Injection is indicated for the treatment of adult patients with mantle cell lymphoma.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • For subcutaneous or intravenous use only. Each route of administration has a different reconstituted concentration; Exercise caution when calculating the volume to be administered. ( 2.1 , 2.10 ) • The recommended starting dose of Bortezomib for Injection is 1.3 mg/m 2 administered either as a 3 to 5 second bolus intravenous injection or subcutaneous injection.
( 2.2 , 2.4 , 2.6 ) • Retreatment for multiple myeloma: May retreat starting at the last tolerated dose. ( 2.6 ) • Hepatic Impairment: Use a lower starting dose for patients with moderate or severe hepatic impairment. ( 2.8 ) • Dose must be individualized to prevent overdose.
( 2.10 )
2.1Important Dosing Guidelines Bortezomib for Injection is for intravenous or subcutaneous use only. Do not administer Bortezomib for Injection by any other route. Because each route of administration has a different reconstituted concentration, use caution when calculating the volume to be administered.
The recommended starting dose of Bortezomib for Injection is 1.3 mg/m 2 . Bortezomib for Injection is administered intravenously at a concentration of 1 mg/mL, or subcutaneously at a concentration of 2.5 mg/mL [see Dosage and Administration (2.10) ]. Bortezomib for Injection retreatment may be considered for patients with multiple myeloma who had previously responded to treatment with Bortezomib for Injection and who have relapsed at least six months after completing prior Bortezomib for Injection treatment.
Treatment may be started at the last tolerated dose [see Dosage and Administration (2.6) ] . When administered intravenously, administer Bortezomib for Injection as a 3 to 5 second bolus intravenous injection.
2.2Dosage in Previously Untreated Multiple Myeloma Bortezomib for Injection is administered in combination with oral melphalan and oral prednisone for 9, six-week treatment cycles as shown in Table 1 . In Cycles 1 to 4, Bortezomib for Injection is administered twice weekly (Days 1, 4, 8, 11, 22, 25, 29 and 32). In Cycles 5 to 9, Bortezomib for Injection is administered once weekly (Days 1, 8, 22 and 29).
At least 72 hours should elapse between consecutive doses of Bortezomib for Injection. Table 1: Dosage Regimen for Patients with Previously Untreated Multiple Myeloma Twice Weekly Bortezomib for Injection (Cycles 1 to 4) Week 1 2 3 4 5 6 Bortezomib for Injection (1.3 mg/m 2 ) Day 1 -- -- Day 4 Day 8 Day 11 rest period Day 22 Day 25 Day 29 Day 32 rest period Melphalan (9 mg/m 2 ) Prednisone (60 mg/m 2 ) Day 1 Day 2 Day 3 Day 4 -- -- rest period -- -- -- -- rest period Once Weekly Bortezomib for Injection (Cycles 5 to 9 when used in combination with Melphalan and Prednisone) Week 1 2 3 4 5 6 Bortezomib for Injection (1.3 mg/m 2 ) Day 1 -- -- Day 8 rest period Day 22 Day 29 rest period Melphalan (9 mg/m 2 ) Prednisone (60 mg/m 2 ) Day 1 Day 2 Day 3 Day 4 -- -- rest period -- -- -- -- rest period
2.3Dose Modification Guidelines for Bortezomib for Injection When Given in Combination with Melphalan and Prednisone Prior to initiating any cycle of therapy with Bortezomib for Injection in combination with melphalan and prednisone: • Platelet count should be at least 70 × 10 9 /L and the absolute neutrophil count (ANC) should be at least 1 × 10 9 /L • Non-hematological toxicities should have resolved to Grade 1 or baseline Table 2: Dose Modifications During Cycles of Combination Bortezomib for Injection, Melphalan and Prednisone Therapy Toxicity Dose Modification or Delay Hematological toxicity during a cycle: If prolonged Grade 4 neutropenia or thrombocytopenia, or thrombocytopenia with bleeding is observed in the previous cycle Consider reduction of the melphalan dose by 25% in the next cycle If platelet count is not above 30 × 10 9 /L or ANC is not above 0.75 × 10 9 /L on a Bortezomib for Injection dosing day (other than Day 1) Withhold Bortezomib for Injection dose If several Bortezomib for Injection doses in consecutive cycles are withheld due to toxic… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS For injection: Each single-dose vial of Bortezomib for Injection contains 1 mg or 2.5 mg of bortezomib as a sterile lyophilized white to off-white powder for reconstitution and withdrawal of the appropriate individual patient dose [see Dosage and Administration (2.10) ] . For injection: 1 mg or 2.5 mg of bortezomib as a lyophilized powder in a single-dose vial for reconstitution and withdrawal of the appropriate individual patient dose. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Bortezomib for Injection is contraindicated in patients with hypersensitivity (not including local reactions) to bortezomib, boron, or mannitol. Reactions have included anaphylactic reactions [see Adverse Reactions (6.1) ] . Bortezomib for Injection is contraindicated for intrathecal administration.
Fatal events have occurred with intrathecal administration of bortezomib products. • Patients with hypersensitivity (not including local reactions) to bortezomib, boron, or mannitol, including anaphylactic reactions. ( 4 ) • Contraindicated for intrathecal administration. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Peripheral Neuropathy: Manage with dose modification or discontinuation. ( 2.7 ) Patients with pre-existing severe neuropathy should be treated with Bortezomib for Injection only after careful risk-benefit assessment. ( 2.7 , 5.1 ) • Hypotension: Use caution when treating patients taking antihypertensives, with a history of syncope, or with dehydration.
( 5.2 ) • Cardiac Toxicity: Worsening of and development of cardiac failure has occurred. Closely monitor patients with existing heart disease or risk factors for heart disease. ( 5.3 ) • Pulmonary Toxicity: Acute respiratory syndromes have occurred.
Monitor closely for new or worsening symptoms and consider interrupting Bortezomib for Injection therapy. ( 5.4 ) • Posterior Reversible Encephalopathy Syndrome: Consider MRI imaging for onset of visual or neurological symptoms; discontinue Bortezomib for Injection if suspected. ( 5.5 ) • Gastrointestinal Toxicity: Nausea, diarrhea, constipation, and vomiting may require use of antiemetic and antidiarrheal medications or fluid replacement.
( 5.6 ) • Thrombocytopenia/Neutropenia: Monitor complete blood counts regularly throughout treatment. ( 5.7 ) • Tumor Lysis Syndrome: Closely monitor patients with high tumor burden. ( 5.8 ) • Hepatic Toxicity: Monitor hepatic enzymes during treatment.
Interrupt Bortezomib for Injection therapy to assess reversibility. ( 5.9 ) • Thrombotic Microangiopathy: Monitor for signs and symptoms. Discontinue Bortezomib for Injection if suspected.
( 5.10 ) • Embryo-Fetal Toxicity: Bortezomib for Injection can cause fetal harm. Advise females of reproductive potential and males with female partners of reproductive potential of the potential risk to a fetus and to use effective contraception. ( 5.11 )
5.1Peripheral Neuropathy Bortezomib treatment causes a peripheral neuropathy that is predominantly sensory; however, cases of severe sensory and motor peripheral neuropathy have been reported. Patients with pre-existing symptoms (numbness, pain or a burning feeling in the feet or hands) and/or signs of peripheral neuropathy may experience worsening peripheral neuropathy (including ≥Grade 3) during treatment with Bortezomib for Injection. Patients should be monitored for symptoms of neuropathy, such as a burning sensation, hyperesthesia, hypoesthesia, paresthesia, discomfort, neuropathic pain or weakness.
In the Phase 3 relapsed multiple myeloma trial comparing bortezomib subcutaneous vs intravenous, the incidence of Grade ≥2 peripheral neuropathy was 24% for subcutaneous and 39% for intravenous. Grade ≥3 peripheral neuropathy occurred in 6% of patients in the subcutaneous treatment group, compared with 15% in the intravenous treatment group [see Adverse Reactions (6.1) ] . Starting Bortezomib for Injection subcutaneously may be considered for patients with pre-existing or at high risk of peripheral neuropathy.
Patients experiencing new or worsening peripheral neuropathy during Bortezomib for Injection therapy may require a decrease in the dose and/or a less dose-intense schedule [see Dosage and Administration (2.7) ] . In the bortezomib vs dexamethasone Phase 3 relapsed multiple myeloma study, improvement in or resolution of peripheral neuropathy was reported in 48% of patients with ≥Grade 2 peripheral neuropathy following dose adjustment or interruption. Improvement in or resolution of peripheral neuropathy was reported in 73% of patients who discontinued due to Grade 2 neuropathy or who had ≥Grade 3 peripheral neuropathy in the Phase 2 multiple myeloma studies.
The long-term outcome of peripheral neuropathy has not been studied in mantle cell lymphoma.
5.2Hypotension The incidence of hypotension (postural, orthostatic, and hypotension NOS) was 8% [see Adverse Reactions (6.1) ] . These events are observed throughout therapy. Patients with a history of syncope, patients receiving medications known to be associated with hypotension, and patients who are dehydrated may be at increas… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are also discussed in other sections of the labeling: • Peripheral Neuropathy [see Warnings and Precautions (5.1) ] • Hypotension [see Warnings and Precautions (5.2) ] • Cardiac Toxicity [see Warnings and Precautions (5.3) ] • Pulmonary Toxicity [see Warnings and Precautions (5.4) ] • Posterior Reversible Encephalopathy Syndrome (PRES) [see Warnings and Precautions (5.5) ] • Gastrointestinal Toxicity [see Warnings and Precautions (5.6) ] • Thrombocytopenia/Neutropenia [see Warnings and Precautions (5.7) ] • Tumor Lysis Syndrome [see Warnings and Precautions (5.8) ] • Hepatic Toxicity [see Warnings and Precautions (5.9) ] • Thrombotic Microangiopathy [see Warnings and Precautions (5.10) ] Most commonly reported adverse reactions (incidence ≥20%) in clinical studies include nausea, diarrhea, thrombocytopenia, neutropenia, peripheral neuropathy, fatigue, neuralgia, anemia, leukopenia, constipation, vomiting, lymphopenia, rash, pyrexia, and anorexia.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Pfizer Inc., at 1-800-438-1985 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Summary of Clinical Trial in Patients with Previously Untreated Multiple Myeloma Table 9 describes safety data from 340 patients with previously untreated multiple myeloma who received bortezomib (1.3 mg/m 2 ) administered intravenously in combination with melphalan (9 mg/m 2 ) and prednisone (60 mg/m 2 ) in a prospective randomized study.
The safety profile of bortezomib in combination with melphalan/prednisone is consistent with the known safety profiles of both bortezomib and melphalan/prednisone. Table 9: Most Commonly Reported Adverse Reactions (≥10% in the Bortezomib, Melphalan and Prednisone Arm) with Grades 3 and ≥4 Intensity in the Previously Untreated Multiple Myeloma Study Bortezomib, Melphalan and Prednisone (n = 340) Melphalan and Prednisone (n = 337) Body System Total Toxicity Grade, n (%) Total Toxicity Grade, n (%) Adverse Reaction n (%) 3 ≥4 n (%) 3 ≥4 Blood and Lymphatic System Disorders Thrombocytopenia 164 (48) 60 (18) 57 (17) 140 (42) 48 (14) 39 (12) Neutropenia 160 (47) 101 (30) 33 (10) 143 (42) 77 (23) 42 (12) Anemia 109 (32) 41 (12) 4 (1) 156 (46) 61 (18) 18 (5) Leukopenia 108 (32) 64 (19) 8 (2) 93 (28) 53 (16) 11 (3) Lymphopenia 78 (23) 46 (14) 17 (5) 51 (15) 26 (8) 7 (2) Gastrointestinal Disorders Nausea 134 (39) 10 (3) 0 70 (21) 1 (<1) 0 Diarrhea 119 (35) 19 (6) 2 (1) 20 (6) 1 (<1) 0 Vomiting 87 (26) 13 (4) 0 41 (12) 2 (1) 0 Constipation 77 (23) 2 (1) 0 14 (4) 0 0 Abdominal pain upper 34 (10) 1 (<1) 0 20 (6) 0 0 Nervous System Disorders Peripheral neuropathy Represents High Level Term Peripheral Neuropathies NEC 156 (46) 42 (12) 2 (1) 4 (1) 0 0 Neuralgia 117 (34) 27 (8) 2 (1) 1 (<1) 0 0 Paresthesia 42 (12) 6 (2) 0 4 (1) 0 0 General Disorders and Administration Site Conditions Fatigue 85 (25) 19 (6) 2 (1) 48 (14) 4 (1) 0 Asthenia 54 (16) 18 (5) 0 23 (7) 3 (1) 0 Pyrexia 53 (16) 4 (1) 0 19 (6) 1 (<1) 1 (<1) Infections and Infestations Herpes Zoster 39 (11) 11 (3) 0 9 (3) 4 (1) 0 Metabolism and Nutrition Disorders Anorexia 64 (19) 6 (2) 0 19 (6) 0 0 Skin and Subcutaneous Tissue Disorders Rash 38 (11) 2 (1) 0 7 (2) 0 0 Psychiatric Disorders Insomnia 35 (10) 1 (<1) 0 21 (6) 0 0 Relapsed Multiple Myeloma Randomized Study of Bortezomib vs Dexamethasone The safety data described below and in Table 10 reflect exposure to either bortezomib (n=331) or dexamethasone (n=332) in a study of patients with relapsed multiple myeloma.
Bortezomib was administered intravenously at doses of 1.3 mg/m 2 twice weekly for two out of three weeks (21 day cycle). After eight 21 day… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Strong CYP3A4 Inhibitors: Closely monitor patients with concomitant use. ( 7.1 ) • Strong CYP3A4 Inducers: Avoid concomitant use. ( 7.1 )
7.1Effects of Other Drugs on Bortezomib Strong CYP3A4 Inducers Coadministration with a strong CYP3A4 inducer decreases the exposure of bortezomib [see Clinical Pharmacology (12.3) ] which may decrease Bortezomib for Injection efficacy. Avoid coadministration with strong CYP3A4 inducers. Strong CYP3A4 Inhibitors Coadministration with a strong CYP3A4 inhibitor increases the exposure of bortezomib [see Clinical Pharmacology (12.3) ] which may increase the risk of Bortezomib for Injection toxicities.
Monitor patients for signs of bortezomib toxicity and consider a bortezomib dose reduction if bortezomib must be given in combination with strong CYP3A4 inhibitors.
7.2Drugs Without Clinically Significant Interactions with Bortezomib No clinically significant drug interactions have been observed when Bortezomib for Injection was coadministered with dexamethasone, omeprazole, or melphalan in combination with prednisone [see Clinical Pharmacology (12.3) ] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Patients with diabetes may require close monitoring of blood glucose and adjustment of antidiabetic medication. ( 8.8 )
8.1Pregnancy Risk Summary Based on its mechanism of action [see Clinical Pharmacology (12.1) ] and findings in animals, Bortezomib for Injection can cause fetal harm when administered to a pregnant woman. There are no studies with the use of bortezomib in pregnant women to inform drug-associated risks. Bortezomib caused embryo-fetal lethality in rabbits at doses lower than the clinical dose (see Data ) .
Advise pregnant women of the potential risk to the fetus. Adverse outcomes in pregnancy occur regardless of the health of the mother or the use of medications. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data Bortezomib was not teratogenic in nonclinical developmental toxicity studies in rats and rabbits at the highest dose tested (0.075 mg/kg; 0.5 mg/m 2 in the rat and 0.05 mg/kg; 0.6 mg/m 2 in the rabbit) when administered during organogenesis. These dosages are approximately 0.5 times the clinical dose of 1.3 mg/m 2 based on body surface area.
Bortezomib caused embryo-fetal lethality in rabbits at doses lower than the clinical dose (approximately 0.5 times the clinical dose of 1.3 mg/m 2 based on body surface area). Pregnant rabbits given bortezomib during organogenesis at a dose of 0.05 mg/kg (0.6 mg/m 2 ) experienced significant post-implantation loss and decreased number of live fetuses. Live fetuses from these litters also showed significant decreases in fetal weight.
8.2Lactation Risk Summary There are no data on the presence of bortezomib or its metabolites in human milk, the effects of the drug on the breastfed child, or the effects of the drug on milk production. Because many drugs are excreted in human milk and because the potential for serious adverse reactions in a breastfed child from bortezomib is unknown, advise nursing women not to breastfeed during treatment with Bortezomib for Injection and for two months after treatment.
8.3Females and Males of Reproductive Potential Based on its mechanism of action and findings in animals, Bortezomib for Injection can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1) ] . Pregnancy Testing Conduct pregnancy testing in females of reproductive potential prior to initiating Bortezomib for Injection treatment. Contraception Females Advise females of reproductive potential to use effective contraception during treatment with Bortezomib for Injection and for seven months after the last dose.
Males Males with female partners of reproductive potential should use effective contraception during treatment with Bortezomib for Injection and for four months after the last dose. Infertility Based on the mechanism of action and findings in animals, Bortezomib for Injection may have an effect on either male or female fertility [see Nonclinical Toxicology (13.1) ] .
8.4Pediatric Use Safety and effectiveness have not been established in pediatric patients. The activity and safety of bortezomib in combination with intensive reinduction chemotherapy was evaluated in pediatric and young adult patients with lymphoid malignancies (pre-B cell ALL 77%, 16% with T-cell ALL, and 7% T-cell lymphoblastic lymphoma (LL)), all of whom relapsed within 36 months of initial diagnosis in a single-arm multicenter, nonrandomized cooperative group trial. An effective reinduction multiagent chemotherapy regimen was administered in three blocks.
Block 1 included vincristine, prednisone, doxorubicin and pegaspargase; Block 2 included cyclophosphamide, etoposide and methotrexate; Block 3 included high-dose cytosine arabinoside and asparaginase. Bortezomib was administe… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on its mechanism of action [see Clinical Pharmacology (12.1) ] and findings in animals, Bortezomib for Injection can cause fetal harm when administered to a pregnant woman. There are no studies with the use of bortezomib in pregnant women to inform drug-associated risks. Bortezomib caused embryo-fetal lethality in rabbits at doses lower than the clinical dose (see Data ) .
Advise pregnant women of the potential risk to the fetus. Adverse outcomes in pregnancy occur regardless of the health of the mother or the use of medications. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data Bortezomib was not teratogenic in nonclinical developmental toxicity studies in rats and rabbits at the highest dose tested (0.075 mg/kg; 0.5 mg/m 2 in the rat and 0.05 mg/kg; 0.6 mg/m 2 in the rabbit) when administered during organogenesis. These dosages are approximately 0.5 times the clinical dose of 1.3 mg/m 2 based on body surface area.
Bortezomib caused embryo-fetal lethality in rabbits at doses lower than the clinical dose (approximately 0.5 times the clinical dose of 1.3 mg/m 2 based on body surface area). Pregnant rabbits given bortezomib during organogenesis at a dose of 0.05 mg/kg (0.6 mg/m 2 ) experienced significant post-implantation loss and decreased number of live fetuses. Live fetuses from these litters also showed significant decreases in fetal weight.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness have not been established in pediatric patients. The activity and safety of bortezomib in combination with intensive reinduction chemotherapy was evaluated in pediatric and young adult patients with lymphoid malignancies (pre-B cell ALL 77%, 16% with T-cell ALL, and 7% T-cell lymphoblastic lymphoma (LL)), all of whom relapsed within 36 months of initial diagnosis in a single-arm multicenter, nonrandomized cooperative group trial. An effective reinduction multiagent chemotherapy regimen was administered in three blocks.
Block 1 included vincristine, prednisone, doxorubicin and pegaspargase; Block 2 included cyclophosphamide, etoposide and methotrexate; Block 3 included high-dose cytosine arabinoside and asparaginase. Bortezomib was administered at a dose of 1.3 mg/m 2 as a bolus intravenous injection on Days 1, 4, 8, and 11 of Block 1 and Days 1, 4, and 8 of Block 2. There were 140 patients with ALL or LL enrolled and evaluated for safety.
The median age was ten years (range: 1 to 26), 57% were male, 70% were white, 14% were black, 4% were Asian, 2% were American Indian/Alaska Native, 1% were Pacific Islander. The activity was evaluated in a prespecified subset of the first 60 evaluable patients enrolled on the study with pre-B ALL ≤21 years and relapsed <36 months from diagnosis. The complete remission (CR) rate at Day 36 was compared to that in a historical control set of patients who had received the identical backbone therapy without bortezomib.
There was no evidence that the addition of bortezomib had any impact on the CR rate. No new safety concerns were observed when bortezomib was added to a chemotherapy backbone regimen as compared with a historical control group in which the backbone regimen was given without bortezomib. The BSA-normalized clearance of bortezomib in pediatric patients was similar to that observed in adults.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 669 patients enrolled in the relapsed multiple myeloma study, 245 (37%) were 65 years of age or older: 125 (38%) on the bortezomib arm and 120 (36%) on the dexamethasone arm. Median time to progression and median duration of response for patients ≥65 were longer on bortezomib compared to dexamethasone [5.5 mo vs 4.3 mo, and 8.0 mo vs 4.9 mo, respectively]. On the bortezomib arm, 40% (n=46) of evaluable patients aged ≥65 experienced response (CR + PR) vs 18% (n=21) on the dexamethasone arm.
The incidence of Grade 3 and 4 events was 64%, 78% and 75% for bortezomib patients ≤50, 51 to 64 and ≥65 years old, respectively [see Adverse Reactions (6.1) , Clinical Studies (14.1) ] . No overall differences in safety or effectiveness were observed between patients ≥age 65 and younger patients receiving bortezomib; but greater sensitivity of some older individuals cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE There is no known specific antidote for Bortezomib for Injection overdosage. In humans, fatal outcomes following the administration of more than twice the recommended therapeutic dose have been reported, which were associated with the acute onset of symptomatic hypotension (5.2) and thrombocytopenia (5.7). In the event of an overdosage, the patient's vital signs should be monitored and appropriate supportive care given.
Studies in monkeys and dogs showed that intravenous bortezomib doses as low as two times the recommended clinical dose on a mg/m 2 basis were associated with increases in heart rate, decreases in contractility, hypotension, and death. In dog studies, a slight increase in the corrected QT interval was observed at doses resulting in death. In monkeys, doses of 3 mg/m 2 and greater (approximately twice the recommended clinical dose) resulted in hypotension starting at one hour post-administration, with progression to death in 12 to 14 hours following drug administration.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Bortezomib is a reversible inhibitor of the chymotrypsin-like activity of the 26S proteasome in mammalian cells. The 26S proteasome is a large protein complex that degrades ubiquitinated proteins. The ubiquitin-proteasome pathway plays an essential role in regulating the intracellular concentration of specific proteins, thereby maintaining homeostasis within cells.
Inhibition of the 26S proteasome prevents this targeted proteolysis, which can affect multiple signaling cascades within the cell. This disruption of normal homeostatic mechanisms can lead to cell death. Experiments have demonstrated that bortezomib is cytotoxic to a variety of cancer cell types in vitro.
Bortezomib causes a delay in tumor growth in vivo in nonclinical tumor models, including multiple myeloma.
12.2Pharmacodynamics Following twice weekly administration of 1 mg/m 2 and 1.3 mg/m 2 bortezomib doses, the maximum inhibition of 20S proteasome activity (relative to baseline) in whole blood was observed five minutes after drug administration. Comparable maximum inhibition of 20S proteasome activity was observed between 1 mg/m 2 and 1.3 mg/m 2 doses. Maximal inhibition ranged from 70% to 84% and from 73% to 83% for the 1 mg/m 2 and 1.3 mg/m 2 dose regimens, respectively.
12.3Pharmacokinetics Following intravenous administration of 1 mg/m 2 and 1.3 mg/m 2 doses, the mean maximum plasma concentrations of bortezomib (C max ) after the first dose (Day 1) were 57 ng/mL and 112 ng/mL, respectively. When administered twice weekly, the mean maximum observed plasma concentrations ranged from 67 ng/mL to 106 ng/mL for the 1 mg/m 2 dose and 89 ng/mL to 120 ng/mL for the 1.3 mg/m 2 dose. Following an intravenous bolus or subcutaneous injection of a 1.3 mg/m 2 dose to patients with multiple myeloma, the total systemic exposure after repeat dose administration (AUC last ) was equivalent for subcutaneous and intravenous administration.
The AUC last geometric mean ratio (90% confidence interval) was 0.99 (0.80 to 1.23). The C max after subcutaneous administration (20.4 ng/mL) was lower than after intravenous administration (223 ng/mL) with repeat dose administration. Distribution The mean distribution volume of bortezomib ranged from approximately 498 L/m 2 to 1884 L/m 2 following single- or repeat-dose administration of 1 mg/m 2 or 1.3 mg/m 2 to patients with multiple myeloma.
The binding of bortezomib to human plasma proteins averaged 83% over the concentration range of 100 ng/mL to 1000 ng/mL. Elimination The mean elimination half-life of bortezomib upon multiple dosing ranged from 40 hours to 193 hours after the 1 mg/m 2 dose and 76 hours to 108 hours after the 1.3 mg/m 2 dose. The mean total body clearance were 102 L/h and 112 L/h following the first dose for doses of 1 mg/m 2 and 1.3 mg/m 2 , respectively, and ranged from 15 L/h to 32 L/h following subsequent doses for doses of 1 mg/m 2 and 1.3 mg/m 2 , respectively.
Metabolism Bortezomib is primarily oxidatively metabolized to several inactive metabolites in vitro via cytochrome P450 (CYP) enzymes 3A4, CYP2C19, and CYP1A2, and to a lesser extent by CYP2D6 and CYP2C9. Excretion The pathways of elimination of bortezomib have not been characterized in humans. Specific Populations No clinically significant differences in the pharmacokinetics of bortezomib were observed based on age, sex, or renal impairment (including patients administered bortezomib after dialysis).
The effect of race on bortezomib pharmacokinetics is unknown. Patients with Hepatic Impairment Following administration of bortezomib doses ranging from 0.5 mg/m 2 to 1.3 mg/m 2 , mild (total bilirubin ≤1× ULN and AST >ULN, or total bilirubin >1× to 1.5× ULN and any AST) hepatic impairment did not alter dose-normalized bortezomib AUC when compared to patients with normal hepatic function. Dose-normalized mean bortezomib AUC increased by approximately 60% in patients with moderate (total bilirubin >1.5× to 3×… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Bortezomib is a reversible inhibitor of the chymotrypsin-like activity of the 26S proteasome in mammalian cells. The 26S proteasome is a large protein complex that degrades ubiquitinated proteins. The ubiquitin-proteasome pathway plays an essential role in regulating the intracellular concentration of specific proteins, thereby maintaining homeostasis within cells.
Inhibition of the 26S proteasome prevents this targeted proteolysis, which can affect multiple signaling cascades within the cell. This disruption of normal homeostatic mechanisms can lead to cell death. Experiments have demonstrated that bortezomib is cytotoxic to a variety of cancer cell types in vitro.
Bortezomib causes a delay in tumor growth in vivo in nonclinical tumor models, including multiple myeloma.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Bortezomib for Injection is supplied as individually cartoned 5 mL or 10 mL vials containing 1 mg or 2.5 mg of bortezomib, respectively, as a white to off-white cake or powder. Unit of Sale Strength NDC 0409-1704-01 1 Single-dose vial in a carton 1 mg/vial NDC 0409-1703-01 1 Single-dose vial in a carton 2.5 mg/vial Unopened vials may be stored at controlled room temperature 20°C to 25°C (68°F to 77°F); excursions permitted from 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
Retain in original package to protect from light. Follow guidelines for handling and disposal for hazardous drugs, including the use of gloves and other protective clothing to prevent skin contact 1 .
📦 Storage and Handling ▾
Unopened vials may be stored at controlled room temperature 20°C to 25°C (68°F to 77°F); excursions permitted from 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Retain in original package to protect from light. Follow guidelines for handling and disposal for hazardous drugs, including the use of gloves and other protective clothing to prevent skin contact 1 .
📋 Description ▾
11 DESCRIPTION Bortezomib for Injection, a proteasome inhibitor, is an antineoplastic agent. Bortezomib is a modified dipeptidyl boronic acid. The chemical name for bortezomib, the monomeric boronic acid, is [(1R)-3-methyl-1-[[(2S)-1-oxo-3-phenyl-2[(pyrazinylcarbonyl) amino]propyl]amino]butyl] boronic acid.
Bortezomib has the following chemical structure: The molecular weight is 384.24 g/mol. The molecular formula is C 19 H 25 BN 4 O 4 . The solubility of bortezomib, as the monomeric boronic acid, in water is 3.3 to 3.8 mg/mL in a pH range of 2 to 6.5.
Bortezomib for Injection is available for intravenous injection or subcutaneous use. Each single-dose vial contains 1 mg or 2.5 mg of bortezomib as a sterile lyophilized powder. It also contains the inactive ingredient: 10 mg or 25 mg mannitol, USP for the 1 mg and 2.5 mg single-dose vial, respectively.
The product is provided as a mannitol boronic ester which, in reconstituted form, consists of the mannitol ester in equilibrium with its hydrolysis product, the monomeric boronic acid. The drug substance exists in its monohydrate form. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Discuss the following with patients prior to treatment with Bortezomib for Injection: Peripheral Neuropathy Advise patients to report the development or worsening of sensory and motor peripheral neuropathy to their healthcare provider [see Warnings and Precautions (5.1) ]. Hypotension Advise patients to drink adequate fluids to avoid dehydration and to report symptoms of hypotension to their healthcare provider [see Warnings and Precautions (5.2) ]. Instruct patients to seek medical advice if they experience symptoms of dizziness, light headedness or fainting spells, or muscle cramps.
Cardiac Toxicity Advise patients to report signs or symptoms of heart failure to their healthcare provider [see Warnings and Precautions (5.3) ] . Pulmonary Toxicity Advise patients to report symptoms of ARDS, pulmonary hypertension, pneumonitis, and pneumonia immediately to their healthcare provider [see Warnings and Precautions (5.4) ] . Posterior Reversible Encephalopathy Syndrome (PRES) Advise patients to seek immediate medical attention for signs or symptoms of PRES [see Warnings and Precautions (5.5) ].
Gastrointestinal Toxicity Advise patients to report symptoms of gastrointestinal toxicity to their healthcare provider and to drink adequate fluids to avoid dehydration. Instruct patients to seek medical advice if they experience symptoms of dizziness, light headedness or fainting spells, or muscle cramps [see Warnings and Precautions (5.6) ]. Thrombocytopenia/Neutropenia Advise patients to report signs or symptoms of bleeding or infection immediately to their healthcare provider [see Warnings and Precautions (5.7) ] .
Tumor Lysis Syndrome Advise patients of the risk of tumor lysis syndrome and to drink adequate fluids to avoid dehydration [see Warnings and Precautions (5.8) ]. Hepatic Toxicity Advise patients to report signs or symptoms of hepatic toxicity to their healthcare provider [see Warnings and Precautions (5.9) ]. Thrombotic Microangiopathy Advise patients to seek immediate medical attention if any signs or symptoms of thrombotic microangiopathy occur [see Warnings and Precautions (5.10) ].
Ability to Drive or Operate Machinery or Impairment of Mental Ability Bortezomib for Injection may cause fatigue, dizziness, syncope, orthostatic/postural hypotension. Advise patients not to drive or operate machinery if they experience any of these symptoms [see Warnings and Precautions (5.2 , 5.5) ]. Embryo-Fetal Toxicity Advise females of the potential risk to the fetus and to use effective contraception during treatment with Bortezomib for Injection and for seven months following the last dose.
Advise male patients with female partners of reproductive potential to use effective contraception during treatment with Bortezomib for Injection and for four months following the last dose. Instruct patients to report pregnancy to their physicians immediately if they or their female partner becomes pregnant during treatment or within seven months following last dose [see Warnings and Precautions (5.11) ] . Lactation Advise women not to breastfeed while receiving Bortezomib for Injection and for two months after last dose [see Use in Specific Populations (8.2) ].
Concomitant Medications Advise patients to speak with their physicians about any other medication they are currently taking. Diabetic Patients Advise patients to check their blood sugar frequently if using an oral antidiabetic medication and to notify their physicians of any changes in blood sugar level . Dermal Advise patients to contact their physicians if they experience rash, severe injection site reactions [see Dosage and Administration (2.9) ] , or skin pain.
Discuss with patients the option for antiviral prophylaxis for herpes virus infection [see Adverse Reactions (6.1) ] . Other Instruct patients to contact their physicians if they develop an increase in blood pressure, bleeding, fever, constipation, or decreased appetite.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Following intravenous administration of 1 mg/m 2 and 1.3 mg/m 2 doses, the mean maximum plasma concentrations of bortezomib (C max ) after the first dose (Day 1) were 57 ng/mL and 112 ng/mL, respectively. When administered twice weekly, the mean maximum observed plasma concentrations ranged from 67 ng/mL to 106 ng/mL for the 1 mg/m 2 dose and 89 ng/mL to 120 ng/mL for the 1.3 mg/m 2 dose. Following an intravenous bolus or subcutaneous injection of a 1.3 mg/m 2 dose to patients with multiple myeloma, the total systemic exposure after repeat dose administration (AUC last ) was equivalent for subcutaneous and intravenous administration.
The AUC last geometric mean ratio (90% confidence interval) was 0.99 (0.80 to 1.23). The C max after subcutaneous administration (20.4 ng/mL) was lower than after intravenous administration (223 ng/mL) with repeat dose administration. Distribution The mean distribution volume of bortezomib ranged from approximately 498 L/m 2 to 1884 L/m 2 following single- or repeat-dose administration of 1 mg/m 2 or 1.3 mg/m 2 to patients with multiple myeloma.
The binding of bortezomib to human plasma proteins averaged 83% over the concentration range of 100 ng/mL to 1000 ng/mL. Elimination The mean elimination half-life of bortezomib upon multiple dosing ranged from 40 hours to 193 hours after the 1 mg/m 2 dose and 76 hours to 108 hours after the 1.3 mg/m 2 dose. The mean total body clearance were 102 L/h and 112 L/h following the first dose for doses of 1 mg/m 2 and 1.3 mg/m 2 , respectively, and ranged from 15 L/h to 32 L/h following subsequent doses for doses of 1 mg/m 2 and 1.3 mg/m 2 , respectively.
Metabolism Bortezomib is primarily oxidatively metabolized to several inactive metabolites in vitro via cytochrome P450 (CYP) enzymes 3A4, CYP2C19, and CYP1A2, and to a lesser extent by CYP2D6 and CYP2C9. Excretion The pathways of elimination of bortezomib have not been characterized in humans. Specific Populations No clinically significant differences in the pharmacokinetics of bortezomib were observed based on age, sex, or renal impairment (including patients administered bortezomib after dialysis).
The effect of race on bortezomib pharmacokinetics is unknown. Patients with Hepatic Impairment Following administration of bortezomib doses ranging from 0.5 mg/m 2 to 1.3 mg/m 2 , mild (total bilirubin ≤1× ULN and AST >ULN, or total bilirubin >1× to 1.5× ULN and any AST) hepatic impairment did not alter dose-normalized bortezomib AUC when compared to patients with normal hepatic function. Dose-normalized mean bortezomib AUC increased by approximately 60% in patients with moderate (total bilirubin >1.5× to 3× ULN and any AST) or severe (total bilirubin >3× ULN and any AST) hepatic impairment.
A lower starting dose is recommended in patients with moderate or severe hepatic impairment. Drug Interaction Studies Clinical Studies No clinically significant differences in bortezomib pharmacokinetics were observed when coadministered with dexamethasone (weak CYP3A4 inducer), omeprazole (strong CYP2C19 inhibitor), or melphalan in combination with prednisone. Strong CYP3A4 Inhibitor Coadministration with ketoconazole (strong CYP3A4 inhibitor) increased bortezomib exposure by 35%.
Strong CYP3A4 Inducer Coadministration with rifampin (strong CYP3A4 inducer) decreased bortezomib exposure by approximately 45%. In Vitro Studies Bortezomib may inhibit CYP2C19 activity and increase exposure to drugs that are substrates for this enzyme.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Following twice weekly administration of 1 mg/m 2 and 1.3 mg/m 2 bortezomib doses, the maximum inhibition of 20S proteasome activity (relative to baseline) in whole blood was observed five minutes after drug administration. Comparable maximum inhibition of 20S proteasome activity was observed between 1 mg/m 2 and 1.3 mg/m 2 doses. Maximal inhibition ranged from 70% to 84% and from 73% to 83% for the 1 mg/m 2 and 1.3 mg/m 2 dose regimens, respectively.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Multiple Myeloma Randomized, Open-Label Clinical Study in Patients with Previously Untreated Multiple Myeloma A prospective, international, randomized (1:1), open-label clinical study (NCT00111319) of 682 patients was conducted to determine whether bortezomib administered intravenously (1.3 mg/m 2 ) in combination with melphalan (9 mg/m 2 ) and prednisone (60 mg/m 2 ) resulted in improvement in time to progression (TTP) when compared to melphalan (9 mg/m 2 ) and prednisone (60 mg/m 2 ) in patients with previously untreated multiple myeloma.
Treatment was administered for a maximum of nine cycles (approximately 54 weeks) and was discontinued early for disease progression or unacceptable toxicity. Antiviral prophylaxis was recommended for patients on the bortezomib study arm. The median age of the patients in the study was 71 years (48;91), 50% were male, 88% were Caucasian and the median Karnofsky performance status score for the patients was 80 (60;100).
Patients had IgG/IgA/Light chain myeloma in 63%/25%/8% instances, a median hemoglobin of 105 g/L (64;165), and a median platelet count of 221,500/microliter (33,000;587,000). Efficacy results for the trial are presented in Table 14 . At a pre-specified interim analysis (with median follow-up of 16.3 months), the combination of bortezomib, melphalan and prednisone therapy resulted in significantly superior results for time to progression, progression-free survival, overall survival and response rate.
Further enrollment was halted, and patients receiving melphalan and prednisone were offered bortezomib in addition. A later, pre-specified analysis of overall survival (with median follow-up of 36.7 months with a hazard ratio of 0.65, 95% CI: 0.51, 0.84) resulted in a statistically significant survival benefit for the bortezomib, melphalan and prednisone treatment arm despite subsequent therapies including bortezomib based regimens. In an updated analysis of overall survival based on 387 deaths (median follow-up 60.1 months), the median overall survival for the bortezomib, melphalan and prednisone treatment arm was 56.4 months and for the melphalan and prednisone treatment arm was 43.1 months, with a hazard ratio of 0.695 (95% CI: 0.57, 0.85).
Table 14: Summary of Efficacy Analyses in the Previously Untreated Multiple Myeloma Study Efficacy Endpoint Bortezomib, Melphalan and Prednisone (n=344) Melphalan and Prednisone (n=338) Note: All results are based on the analysis performed at a median follow-up duration of 16.3 months except for the overall survival analysis. Time to Progression Events n (%) 101 (29) 152 (45) Median Kaplan-Meier estimate (months) 20.7 15.0 (95% CI) (17.6, 24.7) (14.1, 17.9) Hazard ratio Hazard ratio estimate is based on a Cox proportional-hazard model adjusted for stratification factors: beta 2 -microglobulin, albumin, and region.
A hazard ratio less than one indicates an advantage for bortezomib, melphalan and prednisone 0.54 (95% CI) (0.42, 0.70) p-value p-value based on the stratified log-rank test adjusted for stratification factors: beta 2 -microglobulin, albumin, and region 0.000002 Progression-Free Survival Events n (%) 135 (39) 190 (56) Median (months) 18.3 14.0 (95% CI) (16.6, 21.7) (11.1, 15.0) Hazard ratio 0.61 (95% CI) (0.49, 0.76) p-value 0.00001 Response Rate CR EBMT criteria n (%) 102 (30) 12 (4) PR n (%) 136 (40) 103 (30) nCR n (%) 5 (1) 0 CR + PR n (%) 238 (69) 115 (34) p-value p-value for Response Rate (CR + PR) from the Cochran-Mantel-Haenszel chi-square test adjusted for the stratification factors <10 -10 Overall Survival at Median Follow-Up of
36.7Months Events (deaths) n (%) 109 (32) 148 (44) Median (months) Not Reached 43.1 (95% CI) (46.2, NR) (34.8, NR) Hazard ratio 0.65 (95% CI) (0.51, 0.84) p-value 0.00084 TTP was statistically significantly longer on the bortezomib, melphalan and prednisone arm (see Figure 1 ) (median follow-up 16.3 months). Figure 1: Time to Progression Bortezomib, Melphalan, and Prednison… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies have not been conducted with bortezomib. Bortezomib showed clastogenic activity (structural chromosomal aberrations) in the in vitro chromosomal aberration assay using Chinese hamster ovary cells. Bortezomib was not genotoxic when tested in the in vitro mutagenicity assay (Ames test) and in vivo micronucleus assay in mice.
Fertility studies with bortezomib were not performed but evaluation of reproductive tissues has been performed in the general toxicity studies. In the six-month rat toxicity study, degenerative effects in the ovary were observed at doses ≥0.3 mg/m 2 (one-fourth of the recommended clinical dose), and degenerative changes in the testes occurred at 1.2 mg/m 2 .
13.2Animal Toxicology and/or Pharmacology Cardiovascular Toxicity Studies in monkeys showed that administration of dosages approximately twice the recommended clinical dose resulted in heart rate elevations, followed by profound progressive hypotension, bradycardia, and death 12 to 14 hours postdose. Doses ≥1.2 mg/m 2 induced dose-proportional changes in cardiac parameters. Bortezomib has been shown to distribute to most tissues in the body, including the myocardium.
In a repeated dosing toxicity study in the monkey, myocardial hemorrhage, inflammation, and necrosis were also observed. Chronic Administration In animal studies at a dose and schedule similar to that recommended for patients (twice weekly dosing for two weeks followed by one-week rest), toxicities observed included severe anemia and thrombocytopenia, and gastrointestinal, neurological and lymphoid system toxicities. Neurotoxic effects of bortezomib in animal studies included axonal swelling and degeneration in peripheral nerves, dorsal spinal roots, and tracts of the spinal cord.
Additionally, multifocal hemorrhage and necrosis in the brain, eye, and heart were observed.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies have not been conducted with bortezomib. Bortezomib showed clastogenic activity (structural chromosomal aberrations) in the in vitro chromosomal aberration assay using Chinese hamster ovary cells. Bortezomib was not genotoxic when tested in the in vitro mutagenicity assay (Ames test) and in vivo micronucleus assay in mice.
Fertility studies with bortezomib were not performed but evaluation of reproductive tissues has been performed in the general toxicity studies. In the six-month rat toxicity study, degenerative effects in the ovary were observed at doses ≥0.3 mg/m 2 (one-fourth of the recommended clinical dose), and degenerative changes in the testes occurred at 1.2 mg/m 2 .
📚 References ▾
15 REFERENCES 1. "OSHA Hazardous Drugs" (refer to antineoplastic weblinks including OSHA Technical Manual). OSHA. http://www.osha.gov/SLTC/hazardousdrugs/index.html
📄 Recent Major Changes ▾
Indications and Usage, Mantle Cell Lymphoma ( 1.2 ), Removed phrase “who have received at least 1 prior therapy” 12/2022 Dosage and Administration ( 2.4 , 2.5 , 2.6 , 2.7 , 2.8 , 2.9 , 2.10 ) 12/2022 Warnings and Precautions, Thrombocytopenia/Neutropenia ( 5.7 ) 12/2022
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 2.5 mg Vial Label NDC 0409-1703-01 Bortezomib for Injection 2.5 mg/vial SINGLE-DOSE VIAL DISCARD UNUSED PORTION FOR INTRAVENOUS OR SUBCUTANEOUS USE Rx ONLY CAUTION: Hazardous Agent Hospira CONTENTS: Lyophilized vial contains 2.5 mg bortezomib and 25 mg mannitol. Recommended Dosage: See Prescribing Information. PRINCIPAL DISPLAY PANEL - 2.5 mg Vial Label
PRINCIPAL DISPLAY PANEL - 2.5 mg Vial Carton 1 x 2.5 mg Single-dose Vial NDC 0409-1703-01 Bortezomib for Injection 2.5 mg/vial SINGLE-DOSE VIAL DISCARD UNUSED PORTION FOR INTRAVENOUS OR SUBCUTANEOUS USE See Reconstitution Information on Back CAUTION: Hazardous Agent Hospira PRINCIPAL DISPLAY PANEL - 2.5 mg Vial Carton
PRINCIPAL DISPLAY PANEL - 1 mg Vial Label NDC 0409-1704-01 Bortezomib for Injection 1 mg/vial SINGLE-DOSE VIAL DISCARD UNUSED PORTION FOR INTRAVENOUS OR SUBCUTANEOUS USE Rx only CAUTION: Hazardous Agent Hospira PRINCIPAL DISPLAY PANEL - 1 mg Vial Label
PRINCIPAL DISPLAY PANEL - 1 mg Vial Carton 1 x 1 mg Single-Dose Vial NDC 0409-1704-01 Bortezomib for Injection 1 mg/vial SINGLE-DOSE VIAL DISCARD UNUSED PORTION FOR INTRAVENOUS OR SUBCUTANEOUS USE See Reconstitution Information on Back CAUTION: Hazardous Agent Hospira PRINCIPAL DISPLAY PANEL - 1 mg Vial Carton
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |