
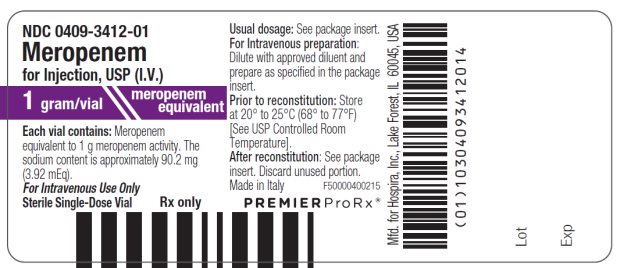
Meropenem 1 g/20mL Injection, Powder, For Solution
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Penem Antibacterial class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Meropenem injection is used to treat certain infections caused by bacteria. Meropenem injection is in a class of medications called carbapenem antibiotics. It works by killing bacteria. Antibiotics such as meropenem injection will not work for colds, flu, or other viral infections. Taking antibiotics when they are not needed increases your risk of getting an infection later that resists antibiotic treatment.
Read the full MedlinePlus article ↗- Meropenem is reserved for serious, hard-to-treat bacterial infections where a strong, broad-coverage antibiotic is needed fast. It can only be given by IV because it isn't absorbed...
- Why am I getting meropenem instead of a regular antibiotic pill?
- The most common ones — diarrhea, nausea, headache, and some redness or discomfort at your IV site — are generally manageable. What's more important to report right away: any troubl...
- What side effects should I actually watch out for?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Meropenem — tap one for details:
Meropenem may be associated with lower levels of 7 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $4.669 | $46.69 / 10 vials |
| Medicaid paysCMS SDUD · 12 mo | $9.23 | $92.28 / 10 vials |
| Medicare drug plans payPart D · Q2 2026 | $3.77 | $37.66 / 10 vials |
| Medicare Part B allowsASP · J2185 | $0.325 / J2185 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Meropenem 1 g/30mL 00143-9431-10 | Hikma | 10 vials | $4.669 | AP | Availability likely | — |
| Meropenem 1 g/20mL 00409-1391-22 | Hospira, | 10 vials | $4.669 | AP | Availability likely | — |
| Meropenem 1 g/20mLthis 00409-3412-10 | Hospira, | 10 vials | $4.669 | AP | Availability likely | — |
| Meropenem 1 g/30mL 00781-3098-95 | Sandoz | 10 vials | $4.669 | AP | Availability likely | — |
| Meropenem 1 g 44567-0146-10 | WG | 10 vials | $4.669 | AP | Availability likely | — |
| Meropenem 1 g 44567-0401-10 | WG | 10 vials | $4.669 | AP | Availability likely | — |
| Meropenem 1 g 55150-0208-30 | Eugia | 10 vials | $4.669 | AP | Availability likely | — |
| Meropenem 1 g/20mL 63323-0508-31 | Fresenius | 10 vials | $4.669 | AP | Availability likely | — |
| Meropenem 1 g/30mL 70121-1453-07 | Amneal | 10 vials | $4.669 | AP | Availability likely | — |
| Meropenem 1 g 70594-0076-02 | Xellia | 10 vials | $4.669 | AP | Availability likely | — |
| Meropenem 1 g/30mL 72572-0416-10 | Civica, | 10 vials | $4.669 | AP | Availability likely | — |
| Meropenem and Sodium Chloride 1 g/50mL 00264-3185-11 | B. | 50 ml | — | — | FDA listed | — |
| Meropenem 1 g/30mL 25021-0161-30 | Sagent | 10 vials | — | AP | FDA listed | — |
| Meropenem 1 g/30mL 44647-0033-10 | Savior | 10 vials | — | AP | FDA listed | — |
| Meropenem 1 g/30mL 51810-0503-02 | Qilu | 10 vials | — | AP | FDA listed | — |
| Meropenem 1 g/30mL 68083-0147-10 | Gland | 10 vials | — | AP | FDA listed | — |
| Meropenem 1 g/20mL 72485-0412-01 | ARMAS | 1 vial | — | AP | FDA listed | — |
| Meropenem 1 g/20mL 72572-0410-10 | Civica, | 10 vials | — | AP | FDA listed | — |
| Meropenem 1 g/20mL 81962-0001-01 | BROOKS | 1 vial | — | AP | FDA listed | — |
| Meropenem 1 g/20mL 00143-9486-10 | Hikma | 10 vials | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00409-3412-10 You're viewing this | 10 VIAL in 1 CARTON (0409-3412-10) / 20 mL in 1 VIAL (0409-3412-01) | 2022-12-06 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Meropenem for injection (I.V.) is a penem antibacterial indicated for the treatment of: 4. Complicated skin and skin structure infections (adult patients and pediatric patients 3 months of age and older only). ( 1.1 ) 5.
Complicated intra-abdominal infections (adult and pediatric patients). ( 1.2 ) 6. Bacterial meningitis (pediatric patients 3 months of age and older only).
( 1.3 ) To reduce the development of drug-resistant bacteria and maintain the effectiveness of Meropenem for injection (I.V.) and other antibacterial drugs, Meropenem for injection (I.V.) should only be used to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria.
1.1Complicated Skin and Skin Structure Infections (Adult Patients and Pediatric Patients 3 Months of Age and Older Only) Meropenem for injection, USP (I.V.) is indicated for the treatment of complicated skin and skin structure infections (cSSSI) due to Staphylococcus aureus (methicillin-susceptible isolates only), Streptococcus pyogenes, Streptococcus agalactiae, viridans group streptococci , Enterococcus faecalis (vancomycin-susceptible isolates only), Pseudomonas aeruginosa, Escherichia coli, Proteus mirabilis, Bacteroides fragilis, and Peptostreptococcus species.
1.2Complicated Intra-abdominal Infections (Adult and Pediatric Patients) Meropenem for injection, USP (I.V.) is indicated for the treatment of complicated appendicitis and peritonitis caused by viridans group streptococci, Escherichia coli , Klebsiella pneumoniae , Pseudomonas aeruginosa , Bacteroides fragilis , B. thetaiotaomicron , and Peptostreptococcus species.
1.3Bacterial Meningitis (Pediatric Patients 3 Months of Age and Older Only) Meropenem for injection, USP (I.V.) is indicated for the treatment of bacterial meningitis caused by Haemophilus influenzae , Neisseria meningitidis and penicillin-susceptible isolates of Streptococcus pneumoniae . Meropenem for injection, USP (I.V.) has been found to be effective in eliminating concurrent bacteremia in association with bacterial meningitis.
1.4Usage To reduce the development of drug-resistant bacteria and maintain the effectiveness of Meropenem for injection, USP (I.V.) and other antibacterial drugs, Meropenem for injection, USP (I.V.) should only be used to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION 5. 500 mg every 8 hours by intravenous infusion over 15 to 30 minutes for complicated skin and skin structure infections (cSSSI) for adult patients. When treating infections caused by Pseudomonas aeruginosa , a dose of 1 gram every 8 hours is recommended ( 2.1 ) 6.
1 gram every 8 hours by intravenous infusion over 15 minutes to 30 minutes for intra-abdominal infections for adult patients. ( 2.1 ) 7. 1 gram every 8 hours by intravenous bolus injection (5 mL to 20 mL) over 3 minutes to 5 minutes for adult patients.
( 2.1 ) 8. Dosage should be reduced in adult patients with renal impairment. ( 2.2 ) Recommended Meropenem for injection (I.V.) Dosage Schedule for Adult Patients with Renal Impairment Creatinine Clearance (mL/min) Dose (dependent on type of infection) Dosing Interval Greater than 50 Recommended dose (500 mg cSSSI and 1 gram Intra-abdominal) Every 8 hours 26 to 50 Recommended dose Every 12 hours 10 to 25 One-half recommended dose Every 12 hours Less than 10 One-half recommended dose Every 24 hours 2.
Pediatric patients 3 months of age and older. Recommended Meropenem for injection (I.V.) Dosage Schedule for Pediatric Patients 3 Months of Age and Older with Normal Renal Function ( 2.3 ) Type of Infection Dose (mg/kg) Up to a Maximum Dose Dosing Interval Complicated skin and skin structure* 10 500 mg Every 8 hours Intra-abdominal 20 1 gram Every 8 hours Meningitis 40 2 gram Every 8 hours - Intravenous infusion is to be given over approximately 15 minutes to 30 minutes. - Intravenous bolus injection (5 mL to 20 mL) is to be given over approximately 3 minutes to 5 minutes. - There is no experience in pediatric patients with renal impairment. *20 mg/kg (or 1 gram for pediatric patients weighing over 50 kg) every 8 hours is recommended when treating complicated skin and skin structure infections caused by P. aeruginosa ( 2.3 ). • Pediatric patients less than 3 months of age Recommended Meropenem for injection (I.V.) Dosage Schedule for Pediatric Patients Less than 3 Months of Age with Complicated Intra-Abdominal Infections and Normal Renal Function ( 2.3 ) Age Group Dose (mg/kg) Dose Interval Infants less than 32 weeks GA and PNA less than 2 weeks 20 Every 12 hours Infants less than 32 weeks GA and PNA 2 weeks and older 20 Every 8 hours Infants 32 weeks and older GA and PNA less than 2 weeks 20 Every 8 hours Infants 32 weeks and older GA and PNA 2 weeks and older 30 Every 8 hours Intravenous infusion is to be given over 30 minutes.
There is no experience in pediatric patients with renal impairment. GA: gestational age and PNA: postnatal age
2.1Adult Patients The recommended dose of Meropenem for injection (I.V.) is 500 mg given every 8 hours for skin and skin structure infections and 1 gram given every 8 hours for intra-abdominal infections. When treating complicated skin and skin structure infections caused by P. aeruginosa , a dose of 1 gram every 8 hours is recommended. Meropenem for injection (I.V.) should be administered by intravenous infusion over approximately 15 minutes to 30 minutes.
Doses of 1 gram may also be administered as an intravenous bolus injection (5 mL to 20 mL) over approximately 3 minutes to 5 minutes.
2.2Use in Adult Patients with Renal Impairment Dosage should be reduced in patients with creatinine clearance of 50 mL/min or less. (See dosing table below.) When only serum creatinine is available, the following formula (Cockcroft and Gault equation) 1 may be used to estimate creatinine clearance. Males: Creatinine Clearance (mL/min) = Weight (kg) x (140 - age) __ 72 x serum creatinine (mg/dL) Females: 0.85 x above value Table 1: Recommended Meropenem for injection (I.V.) Dosage Schedule for Adult Patients with Renal Impairment Creatinine Clearance (mL/min) Dose (dependent on type of infection) Dosing Interval Greater than 50 Recommended dose (500 mg cSSSI and 1 gram Intra-abdominal) Every 8 hours 26 to 50 Recommended dose Every 12 hours 10 to 25 One-half recommended dose…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Single dose clear glass vials of Meropenem for injection (I.V.) containing 500 mg or 1 gram (as the trihydrate blended with anhydrous sodium carbonate for re-constitution) of sterile meropenem powder. 500 mg meropenem for Injection Vial ( 3 ) 1 gram meropenem for Injection Vial ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Meropenem for injection (I.V.) is contraindicated in patients with known hypersensitivity to any component of this product or to other drugs in the same class or in patients who have demonstrated anaphylactic reactions to beta (β)-lactams. 2. Known hypersensitivity to product components or anaphylactic reactions to β-lactams. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS 7. Serious and occasionally fatal hypersensitivity (anaphylactic) reactions have been reported in patients receiving β-lactams. ( 5.1 ) 8.
Severe cutaneous adverse reactions have been reported in patients receiving Meropenem for injection (I.V.). (5.2) 9. Seizures and other adverse CNS experiences have been reported during treatment.
( Error! Hyperlink reference not valid. ) 10. Co-administration of Meropenem for injection (I.V.) with valproic acid or divalproex sodium reduces the serum concentration of valproic acid potentially increasing the risk of breakthrough seizures.
( 5.4 , 7.2 ) 11. Clostridium difficile- associated diarrhea (ranging from mild diarrhea to fatal colitis) has been reported. Evaluate if diarrhea occurs.
( 5.5 ) 12. In patients with renal dysfunction, thrombocytopenia has been observed. ( 5.8 )
5.1Hypersensitivity Reactions Serious and occasionally fatal hypersensitivity (anaphylactic) reactions have been reported in patients receiving therapy with β-lactams. These reactions are more likely to occur in individuals with a history of sensitivity to multiple allergens. There have been reports of individuals with a history of penicillin hypersensitivity who have experienced severe hypersensitivity reactions when treated with another β-lactam.
Before initiating therapy with Meropenem for injection (I.V.), it is important to inquire about previous hypersensitivity reactions to penicillins, cephalosporins, other β-lactams, and other allergens. If an allergic reaction to Meropenem for injection (I.V.) occurs, discontinue the drug immediately.
5.2Severe Cutaneous Adverse Reactions Severe cutaneous adverse reactions (SCAR) such as Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS), erythema multiforme (EM) and acute generalized exanthematous pustulosis (AGEP) have been reported in patients receiving Meropenem for injection (I.V.) [ see AdverseReactions(6.2) ]. If signs and symptoms suggestive of these reactions appear, meropenem should be withdrawn immediately and an alternative treatment should be considered.
5.3Seizure Potential Seizures and other adverse CNS experiences have been reported during treatment with Meropenem for injection (I.V.). These experiences have occurred most commonly in patients with CNS disorders (e.g., brain lesions or history of seizures) or with bacterial meningitis and/or compromised renal function [ see Adverse Reactions( 6.1 )and Drug Interactions( 7.2 ) ]. During clinical investigations, 2904 immunocompetent adult patients were treated for non-CNS infections with the overall seizure rate being 0.7% (based on 20 patients with this adverse event).
All meropenem-treated patients with seizures had pre-existing contributing factors. Among these are included prior history of seizures or CNS abnormality and concomitant medications with seizure potential. Dosage adjustment is recommended in patients with advanced age and/or adult patients with creatinine clearance of 50 mL/min or less [ see Dosage and Administration ( 2.2 ) ].
Close adherence to the recommended dosage regimens is urged, especially in patients with known factors that predispose to convulsive activity. Continue anti-convulsant therapy in patients with known seizure disorders. If focal tremors, myoclonus, or seizures occur, evaluate neurologically, placed on anti-convulsant therapy if not already instituted, and re-examine the dosage of Meropenem for injection (I.V.) to determine whether it should be decreased or discontinued.
5.4Risk of Breakthrough Seizures Due to Drug Interaction with Valproic Acid The concomitant use of meropenem and valproic acid or divalproex sodium is generally not recommended. Case reports in the literature have shown that co-administration of carbapenems, including meropenem, to patients receiving valproic acid or divalproex sodium results in a reduction in valproic acid concentrations. The valpro…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following are discussed in greater detail in other sections of labeling: 1. Hypersensitivity Reactions [ see Warnings and Precautions( 5.1 ) ] 2. Severe Cutaneous Adverse Reactions [ see Warnings and Precautions(5.2) ] 3.
Seizure Potential [ see Warnings and Precautions( Error! Hyperlink reference not valid. ) ] 4. Risk of Breakthrough Seizures Due to Drug Interaction with Valproic Acid [ see Warnings and Precautions ( 5.4 ) ] 5.
Clostridium difficile – associated Diarrhea [ see Warnings and Precautions( 5.5 ) ] 6. Development of Drug-Resistant Bacteria [ see Warnings and Precautions( 5.6 ) ] 7. Overgrowth of Nonsusceptible Organisms [ see Warnings and Precautions( 5.7 ) ] 8.
Thrombocytopenia [ see Warnings and Precautions( 5.8 ) ] 9. Potential for Neuromotor Impairment [ see Warnings and Precautions( Error! Hyperlink reference not valid. ) ] Most common adverse reactions (2% or less) are: headache, nausea, constipation, diarrhea, anemia, vomiting, and rash ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Hospira, Inc. at 1-800-441-4100 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Adverse Reactions from Clinical Trials Because clinical trials are conducted under widely varying conditions, adverse reactions rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adult Patients: During clinical investigations, 2904 immunocompetent adult patients were treated for non-CNS infections with Meropenem for injection (I.V.) (500 mg or 1 gram every 8 hours). Deaths in 5 patients were assessed as possibly related to meropenem; 36 (1.2%) patients had meropenem discontinued because of adverse events.
Many patients in these trials were severely ill and had multiple background diseases, physiological impairments and were receiving multiple other drug therapies. In the seriously ill patient population, it was not possible to determine the relationship between observed adverse events and therapy with Meropenem for injection (I.V.). The following adverse reaction frequencies were derived from the clinical trials in the 2904 patients treated with Meropenem for injection (I.V.) Local Adverse Reactions Local adverse events that were reported with Meropenem for injection (I.V.) were as follows: Inflammation at the injection site 2.4% Injection site reaction 0.9% Phlebitis/thrombophlebitis 0.8% Pain at the injection site 0.4% Edema at the injection site 0.2% Systemic Adverse Reactions Systemic adverse events that were reported with Meropenem for injection (I.V.) occurring in greater than 1% of the patients were diarrhea (4.8%), nausea/vomiting (3.6%), headache (2.3%), rash (1.9%), sepsis (1.6%), constipation (1.4%), apnea (1.3%), shock (1.2%), and pruritus (1.2%).
Additional systemic adverse events that were reported with Meropenem for injection (I.V.) and occurring in less than or equal to 1% but greater than 0.1% of the patients are listed below within each body system in order of decreasing frequency: Bleeding events were seen as follows: gastrointestinal hemorrhage (0.5%), melena (0.3%), epistaxis (0.2%), hemoperitoneum (0.2%). Body as a Whole: pain, abdominal pain, chest pain, fever, back pain, abdominal enlargement, chills, pelvic pain Cardiovascular: heart failure, heart arrest, tachycardia, hypertension, myocardial infarction, pulmonary embolus, bradycardia, hypotension, syncope Digestive System: oral moniliasis, anorexia, cholestatic jaundice/jaundice, flatulence, ileus, hepatic failure, dyspepsia, intestinal obstruction Hemic/Lymphatic: anemia, hypochromic anemia, hypervolemia Metabolic/Nutritional: peripheral edema, hypoxia Nervous System: insomnia, agitation, delirium, confusion, dizziness, seizure, nervousness, paresthesia, hallucinations, somnolence, anxiety, depression, asthenia [ see Warnings and Precautions( Error!
Hyperlink reference not valid. ) and ( Error! Hyperlink refere…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS 3. Co-administration of Meropenem for injection (I.V.) with probenecid inhibits renal excretion of meropenem and is therefore not recommended ( 7.1 ) 4. The concomitant use of Meropenem for injection (I.V.) and valproic acid or divalproex sodium is generally not recommended.
Antibacterial drugs other than carbapenems should be considered to treat infections in patients whose seizures are well controlled on valproic acid or divalproex sodium. ( 5.4 , 7.2 )
7.1Probenecid Probenecid competes with meropenem for active tubular secretion, resulting in increased plasma concentrations of meropenem. Co-administration of probenecid with meropenem is not recommended.
7.2Valproic Acid Case reports in the literature have shown that co-administration of carbapenems, including meropenem, to patients receiving valproic acid or divalproex sodium results in a reduction in valproic acid concentrations. The valproic acid concentrations may drop below the therapeutic range as a result of this interaction, therefore increasing the risk of breakthrough seizures. Although the mechanism of this interaction is unknown, data from in vitro and animal studies suggest that carbapenems may inhibit the hydrolysis of valproic acid’s glucuronide metabolite (VPA-g) back to valproic acid, thus decreasing the serum concentrations of valproic acid.
If administration of Meropenem for injection (I.V.) is necessary, then supplemental anti-convulsant therapy should be considered [ see Warnings and Precautions( 5.4 ) ].
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS 2. Renal Impairment: Dose adjustment is necessary, if creatinine clearance is 50 mL/min or less. ( 2.2 , 8.6 )
8.1Pregnancy Risk Summary There are insufficient human data to establish whether there is a drug-associated risk of major birth defects or miscarriages with meropenem in pregnant women. No fetal toxicity or malformations were observed in pregnant rats and Cynomolgus monkeys administered intravenous meropenem during organogenesis at doses up to 2.4 and 2.3 times the maximum recommended human dose (MRHD) based on body surface area comparison, respectively. In rats administered intravenous meropenem in late pregnancy and during the lactation period, there were no adverse effects on offspring at doses equivalent to approximately 3.2 times the MRHD based on body surface area comparison (see Data).
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Meropenem administered to pregnant rats during organogenesis (Gestation Day 6 to Gestation Day 17) in intravenous doses of 240, 500, and 750 mg/kg/day was associated with mild maternal weight loss at all doses, but did not produce malformations or fetal toxicity. The no-observed-adverse-effect-level (NOAEL) for fetal toxicity in this study was considered to be the high dose of 750 mg/kg/day (equivalent to approximately 2.4 times the MRHD of 1 gram every 8 hours based on body surface area comparison). Meropenem administered intravenously to pregnant Cynomolgus monkeys during organogenesis from Day 20 to 50 after mating at doses of 120, 240, and 360 mg/kg/day did not produce maternal or fetal toxicity at the NOAEL dose of 360 mg/kg/day (approximately 2.3 times the MRHD based on body surface area comparison).
In a peri-postnatal study in rats described in the published literature 2 , intravenous meropenem was administered to dams from Gestation Day 17 until Lactation Day 21 at doses of 240, 500, and 1000 mg/kg/day. There were no adverse effects in the dams and no adverse effects in the first generation offspring (including developmental, behavioral, and functional assessments and reproductive parameters) except that female offspring exhibited lowered body weights which continued during gestation and nursing of the second generation offspring.
Second generation offspring showed no meropenem-related effects. The NOAEL value was considered to be 1000 mg/kg/day (approximately 3.2 times the MRHD based on body surface area comparisons).
8.2Lactation Risk Summary Meropenem has been reported to be excreted in human milk. No information is available on the effects of meropenem on the breast-fed child or on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for Meropenem for Injection (I.V.) and any potential adverse effects on the breast-fed child from Meropenem for Injection (I.V.) or from the underlying maternal conditions.
8.4Pediatric Use The safety and effectiveness of Meropenem for injection (I.V.) have been established for pediatric patients 3 months of age and older with complicated skin and skin structure infections and bacterial meningitis, and for pediatric patients of all ages with complicated intra-abdominal infections. Skin and Skin Structure Infections Use of Meropenem for injection (I.V.) in pediatric patients 3 months of age and older with complicated skin and skin structure infections is supported by evidence from an adequate and well-controlled study in adults and additional data from pediatric pharmacokinetics studies [ see Indications and Usage( 1.3 ) , Dosage and Administration( 2.3 ) , Adverse Reactions( 6.1 ) , Clinical Pharmacology( 12.3 )…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are insufficient human data to establish whether there is a drug-associated risk of major birth defects or miscarriages with meropenem in pregnant women. No fetal toxicity or malformations were observed in pregnant rats and Cynomolgus monkeys administered intravenous meropenem during organogenesis at doses up to 2.4 and 2.3 times the maximum recommended human dose (MRHD) based on body surface area comparison, respectively. In rats administered intravenous meropenem in late pregnancy and during the lactation period, there were no adverse effects on offspring at doses equivalent to approximately 3.2 times the MRHD based on body surface area comparison (see Data).
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Meropenem administered to pregnant rats during organogenesis (Gestation Day 6 to Gestation Day 17) in intravenous doses of 240, 500, and 750 mg/kg/day was associated with mild maternal weight loss at all doses, but did not produce malformations or fetal toxicity. The no-observed-adverse-effect-level (NOAEL) for fetal toxicity in this study was considered to be the high dose of 750 mg/kg/day (equivalent to approximately 2.4 times the MRHD of 1 gram every 8 hours based on body surface area comparison). Meropenem administered intravenously to pregnant Cynomolgus monkeys during organogenesis from Day 20 to 50 after mating at doses of 120, 240, and 360 mg/kg/day did not produce maternal or fetal toxicity at the NOAEL dose of 360 mg/kg/day (approximately 2.3 times the MRHD based on body surface area comparison).
In a peri-postnatal study in rats described in the published literature 2 , intravenous meropenem was administered to dams from Gestation Day 17 until Lactation Day 21 at doses of 240, 500, and 1000 mg/kg/day. There were no adverse effects in the dams and no adverse effects in the first generation offspring (including developmental, behavioral, and functional assessments and reproductive parameters) except that female offspring exhibited lowered body weights which continued during gestation and nursing of the second generation offspring.
Second generation offspring showed no meropenem-related effects. The NOAEL value was considered to be 1000 mg/kg/day (approximately 3.2 times the MRHD based on body surface area comparisons).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of Meropenem for injection (I.V.) have been established for pediatric patients 3 months of age and older with complicated skin and skin structure infections and bacterial meningitis, and for pediatric patients of all ages with complicated intra-abdominal infections. Skin and Skin Structure Infections Use of Meropenem for injection (I.V.) in pediatric patients 3 months of age and older with complicated skin and skin structure infections is supported by evidence from an adequate and well-controlled study in adults and additional data from pediatric pharmacokinetics studies [ see Indications and Usage( 1.3 ) , Dosage and Administration( 2.3 ) , Adverse Reactions( 6.1 ) , Clinical Pharmacology( 12.3 ) and Clinical Studies( 14.1 ) ].
Intra-abdominal Infections Use of Meropenem for injection (I.V.) in pediatric patients 3 months of age and older with intra-abdominal infections is supported by evidence from adequate and well-controlled studies in adults with additional data from pediatric pharmacokinetics studies and controlled clinical trials in pediatric patients. Use of Meropenem for injection (I.V.) in pediatric patients less than 3 months of age with intra-abdominal infections is supported by evidence from adequate and well-controlled studies in adults with additional data from a pediatric pharmacokinetic and safety study [ see Indications and Usage ( 1.2 ) , Dosage and Administration ( 2.3 ) , Adverse Reactions ( 6.1 ) , Clinical Pharmacology ( 12.3 ) and Clinical Studies ( 14.2 ) ].
Bacterial Meningitis Use of Meropenem for injection (I.V.) in pediatric patients 3 months of age and older with bacterial meningitis is supported by evidence from adequate and well-controlled studies in the pediatric population [ see Indications and Usage ( 1.3 ) , Dosage and Administration ( 2.3 ) , Adverse Reactions ( 6.1 ) , Clinical Pharmacology ( 12.3 ) and Clinical Studies ( 14.3 ) ].
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of subjects in clinical studies of Meropenem for injection (I.V.), approximately 1100 (30%) were 65 years of age and older, while 400 (11%) were 75 years and older. Additionally, in a study of 511 patients with complicated skin and skin structure infections, 93 (18%) were 65 years of age and older, while 38 (7%) were 75 years and older. No overall differences in safety or effectiveness were observed between these subjects and younger subjects; spontaneous reports and other reported clinical experience have not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
Meropenem is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with renal impairment. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function. A pharmacokinetic study with Meropenem for injection (I.V.) in elderly patients has shown a reduction in the plasma clearance of meropenem that correlates with age-associated reduction in creatinine clearance [ see Clinical Pharmacology ( 12.3 ) ].
🆘 Overdosage ▾
10 OVERDOSAGE In mice and rats, large intravenous doses of meropenem (2200 mg/kg to 4000 mg/kg) have been associated with ataxia, dyspnea, convulsions, and mortalities. Intentional overdosing of Meropenem for injection (I.V.) is unlikely, although accidental overdosing might occur if large doses are given to patients with reduced renal function. The largest dose of meropenem administered in clinical trials has been 2 grams given intravenously every 8 hours.
At this dosage, no adverse pharmacological effects or increased safety risks have been observed. Limited postmarketing experience indicates that if adverse events occur following overdosage, they are consistent with the adverse event profile described in the Adverse Reactions section and are generally mild in severity and resolve on withdrawal or dose reduction. Consider symptomatic treatments.
In individuals with normal renal function, rapid renal elimination takes place. Meropenem and its metabolite are readily dialyzable and effectively removed by hemodialysis; however, no information is available on the use of hemodialysis to treat overdosage.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Meropenem is an antibacterial drug [ see Microbiology( 12.4 ) ].
12.2Pharmacodynamics The percentage of time of a dosing interval that unbound plasma concentration of meropenem exceeds the meropenem minimum inhibitory concentration (MIC) against the infecting organism has been shown to best correlate with efficacy in animal and in vitro models of infection.
12.3Pharmacokinetics Plasma Concentrations At the end of a 30-minute intravenous infusion of a single dose of Meropenem for injection (I.V.) in healthy volunteers, mean peak plasma concentrations of meropenem are approximately 23 mcg/mL (range 14 to 26) for the 500 mg dose and 49 mcg/mL (range 39 to 58) for the 1 gram dose. A 5-minute intravenous bolus injection of Meropenem for injection (I.V.) in healthy volunteers results in mean peak plasma concentrations of approximately 45 mcg/mL (range 18 to 65) for the 500 mg dose and 112 mcg/mL (range 83 to 140) for the 1 gram dose.
Following intravenous doses of 500 mg, mean plasma concentrations of meropenem usually decline to approximately 1 mcg/mL at 6 hours after administration. No accumulation of meropenem in plasma was observed with regimens using 500 mg administered every 8 hours or 1 gram administered every 6 hours in healthy volunteers with normal renal function. Distribution The plasma protein binding of meropenem is approximately 2%.
After a single intravenous dose of Meropenem for injection (I.V.), the highest mean concentrations of meropenem were found in tissues and fluids at 1 hour (0.5 hours to 1.5 hours) after the start of infusion, except where indicated in the tissues and fluids listed in Table 5 below. Table 5: Meropenem Concentrations in Selected Tissues (Highest Concentrations Reported) Tissue Intravenous Dose (gram) Number of Samples Mean [mcg/mL or mcg/(gram)] at 1 hour unless otherwise noted Range [mcg/mL or mcg/(gram)] Endometrium 0.5 7 4.2 1.7 to
10.2Myometrium 0.5 15 3.8 0.4 to
8.1Ovary 0.5 8 2.8 0.8 to
4.8Cervix 0.5 2 7 5.4 to
8.5Fallopian tube 0.5 9 1.7 0.3 to
3.4Skin 0.5 22 3.3 0.5 to
12.6Interstitial fluid obtained from blister fluid 0.5 9 5.5 3.2 to
8.6Skin 1 10 5.3 1.3 to
16.7Interstitial fluid 1 5 26.3 20.9 to
37.4Colon 1 2 2.6 2.5 to
2.7Bile 1 7 14.6 (3 hours) 4 to
25.7 Gall bladder 1 1 -
3.9Peritoneal fluid 1 9 30.2 7.4 to
54.6Lung 1 2 4.8 (2 hours) 1.4 to
8.2Bronchial mucosa 1 7 4.5 1.3 to
11.1Muscle 1 2 6. 1 (2 hours) 5.3 to
6.9Fascia 1 9 8.8 1.5 to 20 Heart valves 1 7 9.7 6.4 to
12.1Myocardium 1 10 15.5 5.2 to
25.5CSF (inflamed) 20 mg/kg in pediatric patients of age 5 months to 8 years 40 mg/kg in pediatric patients of age 1 month to 15 years 8 5 1.1 (2 hours) 3.3 (3 hours) 0.2 to 2.8 0.9 to
6.5CSF (uninflamed) 1 4 0.2 (2 hours) 0.1 to
0.3Elimination In subjects with normal renal function, the elimination half-life of meropenem is approximately 1 hour. Metabolism There is one metabolite of meropenem that is microbiologically inactive. Excretion Meropenem is primarily excreted unchanged by the kidneys.
Approximately 70% (50% to 75%) of the dose is excreted unchanged within 12 hours. A further 28% is recovered as the microbiologically inactive metabolite. Fecal elimination represents only approximately 2% of the dose.
The measured renal clearance and the effect of probenecid show that meropenem undergoes both filtration and tubular secretion.Urinary concentrations of meropenem in excess of 10 mcg/mL are maintained for up to 5 hours after a 500 mg dose. Specific Populations Patients with Renal Impairment Pharmacokinetic studies with Meropenem for injection (I.V.) in patients with renal impairment have shown that the plasma clearance of meropenem correlates with creatinine clearance. Dosage adjustments are necessary in subjects with renal impairment (creatinine clearance 50 mL/min or less) [ see Dosage and Administration( 2.2 )and Use in Specific Populations( 8.6 ) ].
Meropenem I.V. is hemodialyzable. However, there is no inf…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Meropenem is an antibacterial drug [ see Microbiology( 12.4 ) ].
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Meropenem for injection, USP (I.V.) is supplied in 20 mL and 30 mL injection single-dose vials containing sufficient meropenem to deliver 500 mg or 1 gram for intravenous administration, respectively. The dry powder should be stored at controlled room temperature 20º to 25ºC (68º to 77ºF) [see USP]. Strength Unit of Sale Each 500 mg/vial 0409-0222-10 Unit of 10 0409-0222-01 1 g/vial 0409-3412-10 Unit of 10 0409-3412-01 The container closure is not made with natural rubber latex.
📋 Description ▾
11 DESCRIPTION Meropenem for injection, USP (I.V.) is a sterile, pyrogen-free, synthetic, carbapenem antibacterial for intravenous administration. It is (4R,5S,6S)-3-[[(3S,5S)-5-(Dimethylcarbamoyl)-3-pyrrolidinyl]thio]-6-[(1R)-1-hydroxyethyl]-4-methyl-7-oxo-1-azabicyclo[3.2.0]hept-2-ene-2-carboxylic acid trihydrate. Its empirical formula is C 17 H 25 N 3 O 5 S•3H 2 O with a molecular weight of 437.52.
Its structural formula is: Meropenem for injection, USP (I.V.) is a white to pale yellow crystalline powder. The solution varies from colorless to yellow depending on the concentration. The pH of freshly constituted solutions is between 7.3 and 8.3.
Meropenem is soluble in 5% monobasic potassium phosphate solution, sparingly soluble in water, very slightly soluble in hydrated ethanol, and practically insoluble in acetone or ether. When re-constituted as instructed, each 500 mg Meropenem for injection, USP (I.V.) vial will deliver 500 mg meropenem and 45.1 mg of sodium as sodium carbonate (1.96 mEq). Each 1 gram Meropenem for injection, USP (I.V.) vial will deliver 1 gram of meropenem and 90.2 mg of sodium as sodium carbonate (3.92 mEq) [ see Dosage and Administration ( 2.4 ) ].
Structural formula Meropenem
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION 1. Counsel patients that antibacterial drugs including Meropenem for injection (I.V.) should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold).
When Meropenem for injection (I.V.) is prescribed to treat a bacterial infection, tell patients that although it is common to feel better early in the course of therapy, take the medication exactly as directed. Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by Meropenem for injection (I.V.) or other antibacterial drugs in the future. 2.
Counsel patients that diarrhea is a common problem caused by antibacterial drugs which usually ends when the antibacterial drug is discontinued. Sometimes after starting treatment with antibacterial drugs, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibacterial drug. If this occurs, patients should contact their physician as soon as possible [ see Warnings and Precautions( 5.5 ) ].
3. Counsel patients to inform their physician if they are taking valproic acid or divalproex sodium. Valproic acid concentrations in the blood may drop below the therapeutic range upon co-administration with Meropenem for injection (I.V.).
If treatment with Meropenem for injection (I.V.) is necessary and continued, alternative or supplemental anti-convulsant medication to prevent and/or treat seizures may be needed [ see Warnings and Precautions ( 5.4 ) ]. 4. Patients receiving Meropenem for injection (I.V.) on an outpatient basis must be alerted of adverse events such as seizures, delirium, headaches and/or paresthesias that could interfere with mental alertness and/or cause motor impairment.
Until it is reasonably well established that Meropenem for injection (I.V.) is well tolerated, patients should not operate machinery or motorized vehicles [ see Warnings and Precautions (5.9) ]. Manufactured for Hospira Inc. Lake Forest, IL 60045, USA Made in Italy PremierProRx ® is a registered trademark of Premier Healthcare Alliance, L.P., used under license.
Revised: May 2022