
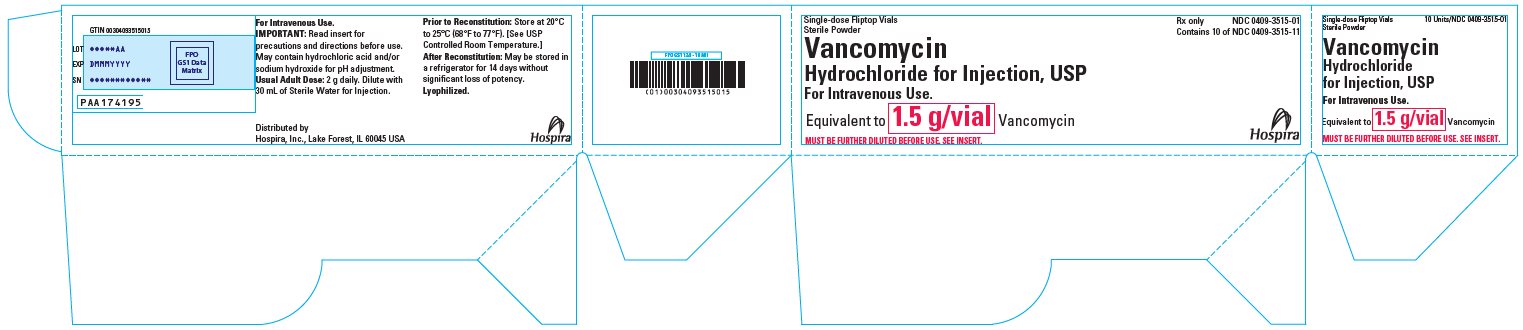
Vancomycin Hydrochloride 1.5 g Injection, Powder, Lyophilized, For Solution, 10 vials
Past resolved recalls for this product (1)
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Glycopeptide Antibacterial class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- It depends on what you're being treated for. If you have a serious infection like a bloodstream infection, heart valve infection, or bone infection, the oral form of vancomycin sim...
- Why do I need an IV antibiotic — can't I just take a pill?
- The two biggest things to watch for are changes in your hearing and changes in your urination. If you notice ringing in your ears, muffled hearing, or dizziness, let your doctor kn...
- What should I watch out for while taking vancomycin?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Vancomycin Hydrochloride — tap one for details:
Vancomycin Hydrochloride may be associated with lower levels of 7 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $55.03 | — |
| Medicare drug plans payPart D · Q2 2026 | $4.68 | — |
| Medicare Part B allowsASP · J3373 | $0.033 / J3373 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Vancomycin Hydrochloride 1.5 g 00143-9153-10 | Hikma | 10 vials | — | AP | FDA listed | — |
| Vancomycin Hydrochloride 1540 mg/mg 00143-9475-10 | HIKMA | 10 vials | — | — | FDA listed | — |
| Vancomycin Hydrochloride 1.5 gthis 00409-3515-01 | Hospira, | 10 vials | — | AP | FDA listed | — |
| Vancomycin Hydrochloride 1.5 g/30mL 25021-0149-30 | Sagent | 10 vials | — | AP | FDA listed | — |
| Vancomycin Hydrochloride 1.5 g 39822-0470-02 | XGen | 10 vials | — | AP | FDA listed | — |
| Vancomycin hydrochloride 1.5 g/30mL 55150-0472-10 | Eugia | 10 vials | — | AP | FDA listed | — |
| Vancomycin Hydrochloride 1.5 g/30mL 67457-0824-99 | Mylan | 10 vials | — | AP | FDA listed | — |
| Vancomycin Hydrochloride 1.5 g 68083-0597-10 | Gland | 10 vials | — | AP | FDA listed | — |
| Vancomycin Hydrochloride 1.5 g 68462-0479-84 | GLENMARK | 10 vials | — | AP | FDA listed | — |
| Vancomycin Hydrochloride 1.5 g/30mL 82449-0007-02 | STERISCIENCE | 10 vials | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00409-3515-01 You're viewing this | 10 VIAL in 1 TRAY (0409-3515-01) / 1 INJECTION, POWDER, LYOPHILIZED, FOR SOLUTION in 1 VIAL (0409-3515-11) | 2021-05-28 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Vancomycin hydrochloride for injection is indicated for the treatment of serious or severe infections caused by susceptible strains of methicillin-resistant (β-lactam-resistant) staphylococci. It is indicated for penicillin-allergic patients, for patients who cannot receive or who have failed to respond to other drugs, including the penicillins or cephalosporins, and for infections caused by vancomycin-susceptible organisms that are resistant to other antimicrobial drugs. Vancomycin hydrochloride for injection is indicated for initial therapy when methicillin-resistant staphylococci are suspected, but after susceptibility data are available, therapy should be adjusted accordingly.
Vancomycin hydrochloride for injection is effective in the treatment of staphylococcal endocarditis. Its effectiveness has been documented in other infections due to staphylococci, including septicemia, bone infections, lower respiratory tract infections, skin and skin structure infections. When staphylococcal infections are localized and purulent, antibiotics are used as adjuncts to appropriate surgical measures.
Vancomycin hydrochloride for injection has been reported to be effective alone or in combination with an aminoglycoside for endocarditis caused by S. viridans or S. bovis . For endocarditis caused by enterococci (e.g., E. faecalis ), vancomycin has been reported to be effective only in combination with an aminoglycoside. Vancomycin hydrochloride for injection has been reported to be effective for the treatment of diphtheroid endocarditis.
Vancomycin hydrochloride for injection has been used successfully in combination with either rifampin, an aminoglycoside, or both in early-onset prosthetic valve endocarditis caused by S. epidermidis or diphtheroids. Specimens for bacteriologic cultures should be obtained in order to isolate and identify causative organisms and to determine their susceptibilities to vancomycin. To reduce the development of drug-resistant bacteria and maintain the effectiveness of vancomycin hydrochloride for injection and other antibacterial drugs, vancomycin hydrochloride for injection should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria.
When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy. The parenteral form of vancomycin hydrochloride may be administered orally for treatment of antibiotic-associated pseudomembranous colitis produced by C. difficile and for staphylococcal enterocolitis.
Parenteral administration of vancomycin hydrochloride alone is of unproven benefit for these indications. Vancomycin is not effective by the oral route for other types of infections.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Infusion-related events are related to both the concentration and the rate of administration of vancomycin. Concentrations of no more than 5 mg/mL and rates of no more than 10 mg/min are recommended in adults (see also age-specific recommendations). In selected patients in need of fluid restriction, a concentration up to 10 mg/mL may be used; use of such higher concentrations may increase the risk of infusion-related events.
An infusion rate of 10 mg/min or less is associated with fewer infusion-related events (see ADVERSE REACTIONS ). Infusion-related events may occur, however, at any rate or concentration. Patients with Normal Renal Function Adults The usual daily intravenous dose is 2 g divided either as 500 mg every 6 hours or 1 g every 12 hours.
Each dose should be administered at no more than 10 mg/min or over a period of at least 60 minutes, whichever is longer. Other patient factors, such as age or obesity, may call for modification of the usual intravenous daily dose. Pediatric patients The usual intravenous dosage of vancomycin is 10 mg/kg per dose given every 6 hours.
Each dose should be administered over a period of at least 60 minutes. Close monitoring of serum concentrations of vancomycin may be warranted in these patients. Neonates In pediatric patients up to the age of 1 month, the total daily intravenous dosage may be lower.
In neonates, an initial dose of 15 mg/kg is suggested, followed by 10 mg/kg every 12 hours for neonates in the 1st week of life and every 8 hours thereafter up to the age of 1 month. Each dose should be administered over 60 minutes. In premature infants, vancomycin clearance decreases as postconceptional age decreases.
Therefore, longer dosing intervals may be necessary in premature infants. Close monitoring of serum concentrations of vancomycin is recommended in these patients. Patients with Impaired Renal Function and Elderly Patients Dosage adjustment must be made in patients with impaired renal function.
In premature infants and the elderly, greater dosage reductions than expected may be necessary because of decreased renal function. Measurement of vancomycin serum concentrations can be helpful in optimizing therapy, especially in seriously ill patients with changing renal function. Vancomycin serum concentrations can be determined by use of microbiologic assay, radioimmunoassay, fluorescence polarization immunoassay, fluorescence immunoassay, or high-pressure liquid chromatography.
If creatinine clearance can be measured or estimated accurately, the dosage for most patients with renal impairment can be calculated using the following table. The dosage of vancomycin hydrochloride for injection per day in mg is about 15 times the glomerular filtration rate in mL/min (see following table). DOSAGE TABLE FOR VANCOMYCIN IN PATIENTS WITH IMPAIRED RENAL FUNCTION (Adapted from Moellering et al 1 ) Creatinine Clearance mL/min Vancomycin Dose mg/24 h 100 1,545 90 1,390 80 1,235 70 1,080 60 925 50 770 40 620 30 465 20 310 10 155 The initial dose should be no less than 15 mg/kg, even in patients with mild to moderate renal insufficiency.
The table is not valid for functionally anephric patients. For such patients, an initial dose of 15 mg/kg of body weight should be given to achieve prompt therapeutic serum concentrations. The dose required to maintain stable concentrations is 1.9 mg/kg/24 h.
In patients with marked renal impairment, it may be more convenient to give maintenance doses of 250 to 1,000 mg once every several days rather than administering the drug on a daily basis. In anuria, a dose of 1,000 mg every 7 to 10 days has been recommended. When only serum creatinine is known, the following formula (based on sex, weight, and age of the patient) may be used to calculate creatinine clearance.
Calculated creatinine clearances (mL/min) are only estimates. The creatinine clearance should be measured promptly. Men: [Weight (kg) × (140 – age in years)] 72 × serum creatini…
⛔ Contraindications ▾
CONTRAINDICATIONS Vancomycin hydrochloride for injection is contraindicated in patients with known hypersensitivity to this antibiotic.
⚠️ Warnings ▾
WARNINGS Infusion Reactions Rapid bolus administration (e.g., over several minutes) may be associated with exaggerated hypotension, including shock and rarely cardiac arrest. Vancomycin hydrochloride for injection should be administered in a diluted solution over a period of not less than 60 minutes to avoid rapid-infusion-related reactions. Stopping the infusion usually results in prompt cessation of these reactions.
Nephrotoxicity Systemic vancomycin exposure may result in acute kidney injury (AKI). The risk of AKI increases as systemic exposure/serum levels increase. Monitor renal function in all patients, especially patients with underlying renal impairment, patients with co-morbidities that predispose to renal impairment, and patients receiving concomitant therapy with a drug known to be nephrotoxic.
Ototoxicity Ototoxicity has occurred in patients receiving vancomycin hydrochloride for injection. It may be transient or permanent. It has been reported mostly in patients who have been given excessive doses, who have an underlying hearing loss, or who are receiving concomitant therapy with another ototoxic agent, such as an aminoglycoside.
Vancomycin should be used with caution in patients with renal insufficiency because the risk of toxicity is appreciably increased by high, prolonged blood concentrations. Dosage of vancomycin hydrochloride for injection must be adjusted for patients with renal dysfunction (see PRECAUTIONS and DOSAGE AND ADMINISTRATION ). Severe Dermatologic Reactions Severe dermatologic reactions such as toxic epidermal necrolysis (TEN), Stevens-Johnson syndrome (SJS), drug reaction with eosinophilia and systemic symptoms (DRESS), acute generalized exanthematous pustulosis (AGEP), and linear IgA bullous dermatosis (LABD) have been reported in association with the use of vancomycin.
Cutaneous signs or symptoms reported include skin rashes, mucosal lesions, and blisters. Discontinue vancomycin hydrochloride for injection at the first appearance of signs and symptoms of TEN, SJS, DRESS, AGEP, or LABD. Clostridioides difficile Associated Diarrhea (CDAD) Clostridioides difficile associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including vancomycin hydrochloride for injection, and may range in severity from mild diarrhea to fatal colitis.
Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C. difficile . C. difficile produces toxins A and B which contribute to the development of CDAD. Hypertoxin producing strains of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy.
CDAD must be considered in all patients who present with diarrhea following antibiotic use. Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents. If CDAD is suspected or confirmed, ongoing antibiotic use not directed against C. difficile may need to be discontinued.
Appropriate fluid and electrolyte management, protein supplementation, antibiotic treatment of C. difficile , and surgical evaluation should be instituted as clinically indicated. Hemorrhagic Occlusive Retinal Vasculitis (HORV) Hemorrhagic occlusive retinal vasculitis, including permanent loss of vision, occurred in patients receiving intracameral or intravitreal administration of vancomycin during or after cataract surgery. The safety and efficacy of vancomycin administered by the intracameral or the intravitreal route have not been established by adequate and well-controlled trials.
Vancomycin is not indicated for the prophylaxis of endophthalmitis.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Infusion-Related Events During or soon after rapid infusion of vancomycin hydrochloride for injection, patients may develop anaphylactoid reactions, including hypotension (see ANIMAL PHARMACOLOGY ), wheezing, dyspnea, urticaria, or pruritus. Rapid infusion may also cause flushing of the upper body ("red neck") or pain and muscle spasm of the chest and back. These reactions usually resolve within 20 minutes but may persist for several hours.
Such events are infrequent if vancomycin hydrochloride for injection is given by a slow infusion over 60 minutes. In studies of normal volunteers, infusion-related events did not occur when vancomycin hydrochloride for injection was administered at a rate of 10 mg/min or less. Nephrotoxicity Systemic vancomycin exposure may result in acute kidney injury (AKI).
The risk of AKI increases as systemic exposure/serum levels increase. Additional risk factors for AKI in patients receiving vancomycin include receipt of concomitant drugs known to be nephrotoxic, in patients with pre-existing renal impairment, or with co-morbidities that predispose to renal impairment. Interstitial nephritis has also been reported in patients receiving vancomycin.
Gastrointestinal Onset of pseudomembranous colitis symptoms may occur during or after antibiotic treatment (see WARNINGS ). Ototoxicity A few dozen cases of hearing loss associated with vancomycin have been reported. Most of these patients had kidney dysfunction or a preexisting hearing loss or were receiving concomitant treatment with an ototoxic drug.
Vertigo, dizziness, and tinnitus have been reported rarely. Hematopoietic Reversible neutropenia, usually starting 1 week or more after onset of therapy with vancomycin or after a total dosage of more than 25 g, has been reported for several dozen patients. Neutropenia appears to be promptly reversible when vancomycin is discontinued.
Thrombocytopenia has rarely been reported. Although a causal relationship has not been established, reversible agranulocytosis (granulocytes <500/mm 3 ) has been reported rarely. Phlebitis Inflammation at the injection site has been reported.
Miscellaneous Patients have been reported to have had anaphylaxis, drug fever, nausea, chills, eosinophilia, rashes including exfoliative dermatitis, Stevens-Johnson syndrome (see WARNINGS, Severe Dermatologic Reactions ), and vasculitis in association with the administration of vancomycin. Chemical peritonitis has been reported following intraperitoneal administration (see PRECAUTIONS ). Post Marketing Reports The following adverse reactions have been identified during post-approval use of vancomycin.
Because these reactions are reported voluntarily from a population of uncertain size, it is not possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Skin and Subcutaneous Tissue Disorders Severe dermatologic reactions such as toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS), acute generalized exanthematous pustulosis (AGEP), and linear IgA bullous dermatosis (LABD) (see WARNINGS, Severe Dermatologic Reactions ). To report SUSPECTED ADVERSE EVENTS, contact FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug Interactions ▾
Drug Interactions Concomitant administration of vancomycin and anesthetic agents has been associated with erythema and histamine-like flushing (see Pediatric Use - PRECAUTIONS ) and anaphylactoid reactions (see ADVERSE REACTIONS ). Monitor renal function in patients receiving vancomycin and concurrent and/or sequential systemic or topical use of other potentially neurotoxic and/or nephrotoxic drugs, such as amphotericin B, aminoglycosides, bacitracin, polymixin B, colistin, viomycin, or cisplatin.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects Animal reproduction studies have not been conducted with vancomycin. It is not known whether vancomycin can affect reproduction capacity. In a controlled clinical study, the potential ototoxic and nephrotoxic effects of vancomycin on infants were evaluated when the drug was administered to pregnant women for serious staphylococcal infections complicating intravenous drug abuse.
Vancomycin was found in cord blood. No sensorineural hearing loss or nephrotoxicity attributable to vancomycin was noted. One infant whose mother received vancomycin in the third trimester experienced conductive hearing loss that was not attributed to the administration of vancomycin.
Because the number of patients treated in this study was limited and vancomycin was administered only in the second and third trimesters, it is not known whether vancomycin causes fetal harm. Vancomycin should be given to a pregnant woman only if clearly needed.
🧒 Pediatric Use ▾
Pediatric Use In pediatric patients, it may be appropriate to confirm desired vancomycin serum concentrations. Concomitant administration of vancomycin and anesthetic agents has been associated with erythema and histamine-like flushing in pediatric patients (see PRECAUTIONS ).
🧓 Geriatric Use ▾
Geriatric Use The natural decrement of glomerular filtration with increasing age may lead to elevated vancomycin serum concentrations if dosage is not adjusted. Vancomycin dosage schedules should be adjusted in elderly patients (see DOSAGE AND ADMINISTRATION ).
🆘 Overdosage ▾
OVERDOSAGE Supportive care is advised, with maintenance of glomerular filtration. Vancomycin is poorly removed by dialysis. Hemofiltration and hemoperfusion with polysulfone resin have been reported to result in increased vancomycin clearance.
The median lethal intravenous dose is 319 mg/kg in rats and 400 mg/kg in mice. To obtain up-to-date information about the treatment of overdose, a good resource is your certified Regional Poison Control Center. Telephone numbers of certified poison control centers are listed in the Physicians' Desk Reference (PDR) .
In managing overdosage, consider the possibility of multiple drug overdoses, interaction among drugs, and unusual drug kinetics in your patient.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Vancomycin is poorly absorbed after oral administration. In subjects with normal kidney function, multiple intravenous dosing of 1 g of vancomycin (15 mg/kg) infused over 60 minutes produces mean plasma concentrations of approximately 63 mcg/mL immediately after the completion of infusion, mean plasma concentrations of approximately 23 mcg/mL 2 hours after infusion, and mean plasma concentrations of approximately 8 mcg/mL 11 hours after the end of the infusion. Multiple dosing of 500 mg infused over 30 minutes produces mean plasma concentrations of about 49 mcg/mL at the completion of infusion, mean plasma concentrations of about 19 mcg/mL 2 hours after infusion, and mean plasma concentrations of about 10 mcg/mL 6 hours after infusion.
The plasma concentrations during multiple dosing are similar to those after a single dose. The mean elimination half-life of vancomycin from plasma is 4 to 6 hours in subjects with normal renal function. In the first 24 hours, about 75% of an administered dose of vancomycin is excreted in urine by glomerular filtration.
Mean plasma clearance is about 0.058 L/kg/h, and mean renal clearance is about 0.048 L/kg/h. Renal dysfunction slows excretion of vancomycin. In anephric patients, the average half-life of elimination is 7.5 days.
The distribution coefficient is from 0.3 to
0.43L/kg. There is no apparent metabolism of the drug. About 60% of an intraperitoneal dose of vancomycin administered during peritoneal dialysis is absorbed systemically in 6 hours.
Serum concentrations of about 10 mcg/mL are achieved by intraperitoneal injection of 30 mg/kg of vancomycin. However, the safety and efficacy of the intraperitoneal use of vancomycin has not been established in adequate and well-controlled trials (see PRECAUTIONS ). Total systemic and renal clearance of vancomycin may be reduced in the elderly.
Vancomycin is approximately 55% serum protein bound as measured by ultrafiltration at vancomycin serum concentrations of 10 to 100 mcg/mL. After IV administration of vancomycin, inhibitory concentrations are present in pleural, pericardial, ascitic, and synovial fluids; in urine; in peritoneal dialysis fluid; and in atrial appendage tissue. Vancomycin does not readily diffuse across normal meninges into the spinal fluid; but, when the meninges are inflamed, penetration into the spinal fluid occurs.
MICROBIOLOGY The bactericidal action of vancomycin results primarily from inhibition of cell-wall biosynthesis. In addition, vancomycin alters bacterial-cell-membrane permeability and RNA synthesis. There is no cross-resistance between vancomycin and other antibiotics.
Vancomycin is not active in vitro against gram-negative bacilli, mycobacteria, or fungi. Synergy The combination of vancomycin and an aminoglycoside acts synergistically in vitro against many strains of Staphylococcus aureus , Streptococcus bovis , enterococci, and the viridans group streptococci. Vancomycin has been shown to be active against most strains of the following microorganisms, both in vitro and in clinical infections as described in the INDICATIONS AND USAGE section.
Aerobic gram-positive microorganisms Diphtheroids Enterococci (e.g., Enterococcus faecalis ) Staphylococci, including Staphylococcus aureus and Staphylococcus epidermidis (including heterogeneous methicillin-resistant strains) Streptococcus bovis Viridans group streptococci The following in vitro data are available, but their clinical significance is unknown . Vancomycin exhibits in vitro MIC's of 1 mcg/mL or less against most (≥ 90%) strains of streptococci listed below and MIC's of 4 mcg/mL or less against most (≥ 90%) strains of other listed microorganisms; however, the safety and effectiveness of vancomycin in treating clinical infections due to these microorganisms have not been established in adequate and well-controlled clinical trials.
Aerobic gram-positive microorganisms Listeria monocytogenes Streptococcus pyogenes Streptococcus pneumoniae (…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED/STORAGE AND HANDLING Vancomycin Hydrochloride for Injection, USP is supplied as a sterile powder in single-dose fliptop vials that contain the vancomycin equivalent of either 500 mg, 750 mg, 1 g or 1.5 g. Unit of Sale Fill NDC 0409-4332-01 Tray of 10 Single-dose Fliptop Vials 500 mg/vial NDC 0409-6531-02 Tray of 10 Single-dose Fliptop Vials 750 mg/vial NDC 0409-6533-01 Tray of 10 Single-dose Fliptop Vials 1 g/vial NDC 0409-6533-21 Carton of 10 Single-dose Fliptop Vials 1 g/vial NDC 0409-3515-01 Tray of 10 Single-dose Fliptop Vials 1.5 g/vial Prior to reconstitution, store at 20 to 25°C (68 to 77°F). [See USP Controlled Room Temperature.]
📦 Storage and Handling ▾
Prior to reconstitution, store at 20 to 25°C (68 to 77°F). [See USP Controlled Room Temperature.]
📋 Description ▾
DESCRIPTION Vancomycin hydrochloride for injection, USP is a lyophilized powder, for preparing intravenous (IV) infusions, in vials each containing the equivalent of 500 mg, 750 mg, 1 g or 1.5 g vancomycin base. 500 mg of the base are equivalent to 0.34 mmol, 750 mg of the base are equivalent to 0.51 mmol, 1 g of the base are equivalent to 0.67 mmol and 1.5 g of the base are equivalent to 1.01 mmol. When reconstituted with Sterile Water for Injection to a concentration of 50 mg/mL, the pH of the solution is between 2.5 and 4.5.
This product is oxygen sensitive. Vancomycin Hydrochloride for Injection, USP should be administered intravenously in diluted solution (see DOSAGE AND ADMINISTRATION ), AFTER RECONSTITUTION FURTHER DILUTION IS REQUIRED BEFORE USE. Vancomycin is a tricyclic glycopeptide antibiotic derived from Amycolatopsis orientalis (formerly Nocardia orientalis ).
The chemical name for vancomycin hydrochloride is 3S- [3 R *,6 S *( S *),7 S *,22 S *,23 R *,26 R *,36 S *,38a S *]]-3-(2-Amino-2-oxoethyl)-44-[[2-O-(3-amino-2,3,6-trideoxy-3-C-methyl-α-L-lyxo-hexopyranosyl)-β-D-glucopyranosyl]oxy]-10,19-dichloro-2,3,4,5,6,7,23,24,25,26,36,37,38,38a-tetradecahydro-7,22,28,30,32-pentahydroxy-6-[[4-methyl-2-(methylamino)-1-oxopentyl]amino]-2,5,24,38,39-pentaoxo-22 H -8,11:18,21-dietheno-23,36- (iminomethano)-13,16:31,35-dimetheno-1 H ,16 H -[1,6,9]oxadiazacyclohexadecino[4,5- m ][10,2,16]-benzoxadiazacyclotetracosine-26-carboxylic acid, monohydrochloride.
The molecular formula is C 66 H 75 Cl 2 N 9 O 24 ∙ HCl and the molecular weight is 1,485.74. Vancomycin hydrochloride has the following structural formula: Chemical Structure
💬 Information for Patients ▾
Information for Patients Severe Dermatologic Reactions Advise patients about the signs and symptoms of serious skin manifestations. Instruct patients to stop vancomycin hydrochloride for injection immediately and promptly seek medical attention at the first signs or symptoms of skin rash, mucosal lesions, and blisters (see WARNINGS ). Patients should be counseled that antibacterial drugs including vancomycin hydrochloride for injection should only be used to treat bacterial infections.
They do not treat viral infections (e.g., the common cold). When vancomycin hydrochloride for injection is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed. Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by vancomycin hydrochloride for injection or other antibacterial drugs in the future.
Diarrhea is a common problem caused by antibiotics which usually ends when the antibiotic is discontinued. Sometimes after starting treatment with antibiotics, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibiotic. If this occurs, patients should contact their physician as soon as possible.
Severe Dermatologic Reactions Advise patients about the signs and symptoms of serious skin manifestations. Instruct patients to stop vancomycin hydrochloride for injection immediately and promptly seek medical attention at the first signs or symptoms of skin rash, mucosal lesions, and blisters (see WARNINGS ). Patients should be counseled that antibacterial drugs including vancomycin hydrochloride for injection should only be used to treat bacterial infections.
They do not treat viral infections (e.g., the common cold). When vancomycin hydrochloride for injection is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed. Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by vancomycin hydrochloride for injection or other antibacterial drugs in the future.
Diarrhea is a common problem caused by antibiotics which usually ends when the antibiotic is discontinued. Sometimes after starting treatment with antibiotics, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibiotic. If this occurs, patients should contact their physician as soon as possible.