
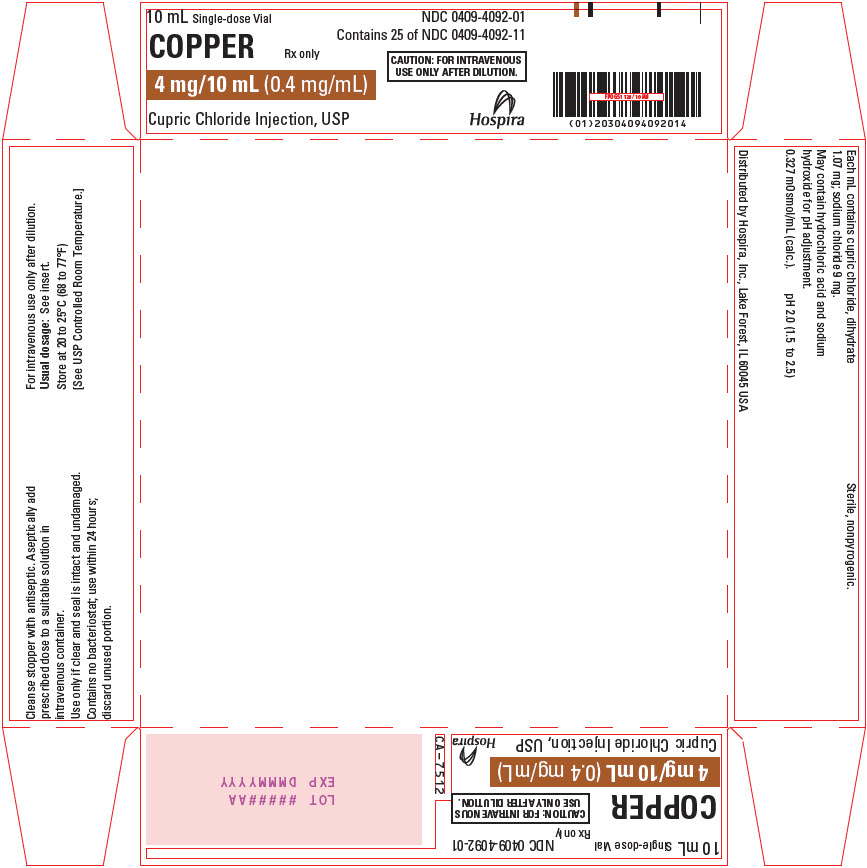
COPPER CUPRIC CHLORIDE .4 mg/mL Injection, Solution
🆔 Identity & classification
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
9 mg / 1 mL
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $45.99 | $11,496.95 / 250 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Copper .4 mg/mLthis 00409-4092-01 | Hospira, | 25 vials | — | AP | FDA listed | — |
| Cupric Chloride .4 mg/mL 51754-0103-03 | Exela | 10 vials | — | AP | FDA listed | — |
| Cupric Chloride .4 mg/mL 70069-0506-25 | Somerset | 25 vials | — | AP | FDA listed | — |
| Cupric Chloride .4 mg/mL 72603-0351-25 | Northstar | 25 vials | — | AP | FDA listed | — |
| Cupric Chloride .4 mg/mL 72819-0234-99 | Archis | 25 vials | — | AP | FDA listed | — |
| Cupric Chloride .4 mg/mL 80830-2301-05 | Amneal | 25 vials | — | — | FDA listed | — |
| Cupric Chloride .4 mg/mL 84897-0013-25 | Renova | 25 vials | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
🗺️ Medicaid utilization & spend
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00409-4092-01 You're viewing this | 25 VIAL, SINGLE-DOSE in 1 TRAY (0409-4092-01) / 10 mL in 1 VIAL, SINGLE-DOSE (0409-4092-11) | 2005-02-28 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Copper (Cupric Chloride Injection) is indicated for use as a supplement to intravenous solutions given for TPN. Administration helps to maintain copper serum levels and to prevent depletion of endogenous stores and subsequent deficiency symptoms.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION • Copper (Cupric Chloride Injection) contains 0.4 mg of copper per mL and is administered intravenously only after dilution. The additive should be diluted in a volume of fluid not less than 100 mL. • For the adult receiving TPN, the suggested additive dosage of copper is 0.3 to 0.5 mg/day. • For pediatric patients, the suggested additive dosage of copper is 20 mcg/kg/day (0.05 mL/kg/day) up to a maximum of 500 mcg/day. • This product is not appropriate for patients weighing less than 4 kg due to the inability to measure the appropriate amount of the product. • Do not administer Copper (Cupric Chloride Injection) intramuscularly because the acidic pH of the solution may cause considerable tissue irritation.
Copper (Cupric Chloride Injection) should only be used in conjunction with a pharmacy directed admixture program using aseptic technique in a laminar flow environment; it should be used promptly and in a single operation without any repeated penetrations. The solution contains no preservatives; discard the unused portion immediately after the admixture procedure is completed. Copper (Cupric Chloride Injection) should be inspected visually for particulate matter and discoloration prior to administration.
Do not use unless the solution is clear, and the seal is intact. Cupric ion may degrade ascorbic acid in TPN solutions. In order to avoid this loss of ascorbate, multivitamin additives should be added to TPN solutions immediately prior to infusion.
Alternatively, the multivitamin additive may be added to one container of TPN solution, followed by copper in a subsequent container.
⛔ Contraindications ▾
CONTRAINDICATIONS Copper (Cupric Chloride Injection) is contraindicated in patients with hypersensitivity to copper (see WARNINGS: Hypersensitivity Reactions ).
⚠️ Warnings ▾
WARNINGS Hepatic Accumulation Copper is primarily eliminated in the bile and excretion is decreased in patients with cholestasis and/or cirrhosis. Hepatic accumulation of copper has been reported in autopsies of patients receiving long-term parenteral nutrition containing copper at dosages higher than recommended. Administration of copper to patients with cholestasis and/or cirrhosis may cause hepatic accumulation of copper.
Administration of copper to patients with Wilson disease, an inborn error of copper metabolism with a defect in hepatocellular copper transport, may cause both increased hepatic accumulation of copper and aggravation of the underlying hepatocellular degeneration. For patients with cholestasis, biliary dysfunction, or cirrhosis, monitor hepatic and biliary function during long-term administration of Cupric Chloride Injection. If a patient develops signs or symptoms of hepatobiliary disease during the use of Cupric Chloride Injection, obtain serum concentrations of copper and ceruloplasmin, and adjust the dose as indicated (see PRECAUTIONS: Hepatic Impairment ).
Hypersensitivity Reactions Postmarket safety reporting has identified copper hypersensitivity in women receiving copper-containing intrauterine devices, providing evidence that patients may experience hypersensitivity reactions when exposed to this metal. If hypersensitivity reactions (e.g., pruritis, angioedema, dyspnea, rash, urticaria) occur in patients receiving Cupric Chloride Injection in parenteral nutrition, discontinue the product, and initiate appropriate medical treatment (see CONTRAINDICATIONS ). Aluminum Toxicity This product contains aluminum that may be toxic.
Aluminum may reach toxic levels with prolonged parenteral administration if kidney function is impaired. Premature neonates are particularly at risk because their kidneys are immature, and they require large amounts of calcium and phosphate solutions, which contain aluminum. Research indicates that patients with impaired kidney function, including premature neonates, who receive parenteral levels of aluminum at greater than 4 to 5 mcg/kg/day accumulate aluminum at levels associated with central nervous system and bone toxicity.
Tissue loading may occur at even lower rates of administration.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS None known.
🤰 Pregnancy ▾
Pregnancy Animal reproduction studies have not been conducted with cupric chloride. It is also not known whether cupric chloride can cause fetal harm when administered to a pregnant woman or can affect reproductive capacity. Cupric chloride should be given to a pregnant woman only if clearly indicated.
🧒 Pediatric Use ▾
Pediatric Use The safety and effectiveness of Cupric Chloride Injection have been established in pediatric patients receiving parenteral nutrition (see DOSAGE AND ADMINISTRATION ).
🧓 Geriatric Use ▾
Geriatric Use An evaluation of current literature revealed no clinical experience identifying differences in response between elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy. Hepatic Impairment Copper is primarily excreted in the bile.
Excretion is decreased in patients with cholestasis and/or cirrhosis (see CLINICAL PHARMACOLOGY ). Hepatic accumulation of copper has been reported with long-term administration of parenteral nutrition at dosages higher than recommended ( see WARNINGS: Hepatic Accumulation ). For patients with cholestasis or cirrhosis, monitor hepatic and biliary function during long-term administration of Cupric Chloride Injection.
If a patient develops signs or symptoms of hepatobiliary disease during use of Cupric Chloride Injection, obtain serum concentrations of copper and ceruloplasmin.
🆘 Overdosage ▾
OVERDOSAGE Acute copper toxicity has been reported in patients with oral, intravenous, or subcutaneous administration. Clinical manifestations included metallic taste, nausea, vomiting, diarrhea, abdominal pain, neurological signs, such as encephalopathy, and multi-organ failure involving kidney, liver, blood, and cardiovascular systems, which may be fatal. Chelating agents, such as D-penicillamine, can be used for treatment of acute toxicity.
Long-term administration of parenteral copper above the recommended dosage may result in significant accumulation of copper in the liver, brain, and other tissues with possible organ damage (see WARNINGS: Hepatic Accumulation ).
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Copper is an essential nutrient which serves as a cofactor for serum ceruloplasmin, an oxidase necessary for proper formation of the iron carrier protein, transferrin. Copper also helps maintain normal rates of red and white blood cell formation. Providing copper during TPN helps prevent development of the following deficiency symptoms: Leukopenia, neutropenia, anemia, depressed ceruloplasmin levels, impaired transferrin formation, secondary iron deficiency and osteoporosis.
Normal serum copper values range from 80 to 163 mcg/dl (mean, approximately 110 mcg/dl). The serum copper level at which deficiency symptoms appear is not precisely defined. In the plasma, about 7% of copper is bound to albumin and amino acids.
In the liver, about 93% of copper is bound to ceruloplasmin and released to the serum. The daily turnover of copper through ceruloplasmin is approximately 0.5 mg. Copper is primarily excreted through the bile and into the gastrointestinal tract where it is not reabsorbed.
Copper is also eliminated through the kidneys.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Copper 0.4 mg/mL (Cupric Chloride Injection, USP) is supplied as follows: Unit of Sale Concentration NDC 0409-4092-01 Tray containing 25 - 10 mL Single-dose Plastic Vials 4 mg/10 mL (0.4 mg/mL) Store at 20 to 25°C (68 to 77°F). [See USP Controlled Room Temperature.] Distributed by Hospira, Inc., Lake Forest, IL 60045 USA LAB-1067-3.0 Revised: 06/2025 Hospira Logo
📋 Description ▾
DESCRIPTION Copper (Cupric Chloride Injection, USP) 0.4 mg/mL is a sterile, nonpyrogenic solution intended for use as an additive to intravenous solutions for total parenteral nutrition (TPN). Each mL of solution contains 1.07 mg cupric chloride, dihydrate and 9 mg sodium chloride. The solution contains no bacteriostat, antimicrobial agent or added buffer.
The pH is 2.0 (1.5 to 2.5); product may contain hydrochloric acid and sodium hydroxide for pH adjustment. The osmolarity is 0.327 mOsmol/mL (calc.). Cupric chloride, USP is chemically designated cupric chloride, dihydrate (CuCl 2 • 2H 2 O), a crystalline compound freely soluble in water.
Sodium Chloride, USP is chemically designated NaCl, a white crystalline compound freely soluble in water. The semi-rigid vial is fabricated from a specially formulated polyolefin. It is a copolymer of ethylene and propylene.
The safety of the plastic has been confirmed by tests in animals according to USP biological standards for plastic containers. The small amount of water vapor that can pass through the plastic container wall will not significantly alter the drug concentration.