
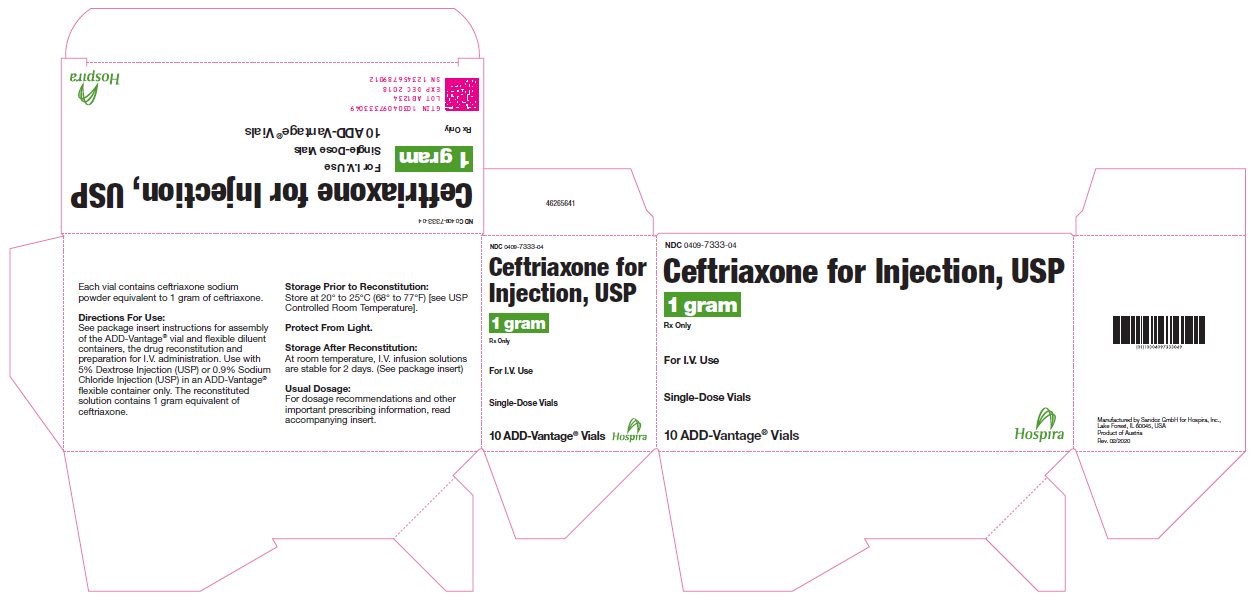
Ceftriaxone Sodium 1 g Injection, Powder, For Solution, 10 vials
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Cephalosporin Antibacterial class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Ceftriaxone injection is used to treat certain infections caused by bacteria. Ceftriaxone injection is also given before certain types of surgery to prevent infections that may develop after an operation. Ceftriaxone injection is in a class of medications called cephalosporin antibiotics. It works by killing bacteria. Antibiotics such as ceftriaxone injection will not work for colds, flu, or other viral infections.Using antibiotics when they are not needed increases your risk of getting an infection later that resists antibiotic treatment.
Read the full MedlinePlus article ↗- Ceftriaxone is only available as an injection — there's no pill form. The good news is that it works fast and reaches very high levels throughout the body, including areas that are...
- Why am I getting an injection instead of a pill?
- It depends on the type of infection. Some infections — like uncomplicated gonorrhea or an ear infection in a child — are treated with just a single dose. For more serious infection...
- How long will I need to take ceftriaxone?
Patient education
Supplement & herbal interactions
Ceftriaxone may be associated with lower levels of 7 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $53.20 | — |
| Medicare drug plans payPart D · Q2 2026 | $2.17 | — |
| Medicare Part B allowsASP · J0696 | $0.404 / J0696 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ceftriaxone Sodium 1 g 00409-7332-01 | Hospira, | 10 vials | $1.195 | AP | Availability likely | — |
| Ceftriaxone 1 g 00143-9857-25 | Hikma | 25 vials | $1.443 | AP | Availability likely | — |
| ceftriaxone 1 g 25021-0106-10 | Sagent | 25 vials | $1.443 | AP | Availability likely | — |
| Ceftriaxone 1 g 44567-0701-25 | WG | 25 vials | $1.443 | AP | Availability likely | — |
| Ceftriaxone 1 g 63323-0346-10 | Fresenius | 25 vials | $1.443 | AP | Availability likely | — |
| Ceftriaxone 1 g 72572-0061-25 | Civica, | 25 vials | $1.443 | AP | Availability likely | — |
| Ceftriaxone Sodium 1 g 00781-3208-85 | Sandoz | 1 vial | $3.450 | AP | Availability likely | — |
| Ceftriaxone Sodium 1 g 60505-6148-00 | Apotex | 1 vial | $3.450 | AP | Availability likely | — |
| Ceftriaxone And Dextrose 1 g/50mL 00264-3153-11 | B. | 50 ml | — | AP | FDA listed | — |
| Ceftriaxone 1 g/50mL 00338-5002-41 | Baxter | 50 ml | — | — | FDA listed | — |
| Ceftriaxone Sodium 1 gthis 00409-7333-04 | Hospira, | 10 vials | — | — | FDA listed | — |
| Ceftriaxone Sodium 1 g 67184-1007-01 | Qilu | 10 vials | — | AP | FDA listed | — |
| Ceftriaxone Sodium 1 g 70518-2499-00 | REMEDYREPACK | 10 vials | — | AP | FDA listed | — |
| Ceftriaxone Sodium 1 g 71205-0545-01 | Proficient | 1 vial | — | AP | FDA listed | — |
| Ceftriaxone Sodium 1 g 85766-0069-01 | Sportpharm | 1 vial | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00409-7333-04 You're viewing this | 10 VIAL, SINGLE-USE in 1 CARTON (0409-7333-04) / 1 INJECTION, POWDER, FOR SOLUTION in 1 VIAL, SINGLE-USE (0409-7333-11) | 2005-07-20 | Active |
| 00409-7333-49 | 10 VIAL, SINGLE-USE in 1 CARTON (0409-7333-49) / 1 INJECTION, POWDER, FOR SOLUTION in 1 VIAL, SINGLE-USE (0409-7333-31) | 2005-07-20 | Active |
In Medicaid, this is the most-dispensed pack of this product — about 88% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 00409-7333-04?
What is the difference between NDC 00409-7333-04 and NDC 00409-7333-49?
What NDC number is used to bill for this package of Ceftriaxone Sodium 1 g Injection, Powder, For Solution?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Before instituting treatment with ceftriaxone for injection, USP, appropriate specimens should be obtained for isolation of the causative organism and for determination of its susceptibility to the drug. Therapy may be instituted prior to obtaining results of susceptibility testing. To reduce the development of drug-resistant bacteria and maintain the effectiveness of ceftriaxone for injection, USP and other antibacterial drugs, ceftriaxone for injection, USP should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria.
When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy. Ceftriaxone for injection, USP is indicated for the treatment of the following infections when caused by susceptible organisms: Lower Respiratory Tract Infections Caused by Streptococcus pneumoniae, Staphylococcus aureus, Haemophilus influenzae, Haemophilus parainfluenzae, Klebsiella pneumoniae, Escherichia coli, Enterobacter aerogenes, Proteus mirabilis or Serratia marcescens.
Acute Bacterial Otitis Media Caused by Streptococcus pneumoniae, Haemophilus influenzae (including beta-lactamase producing strains) or Moraxella catarrhalis (including beta-lactamase producing strains). NOTE: In one study lower clinical cure rates were observed with a single dose of ceftriaxone compared to 10 days of oral therapy. In a second study comparable cure rates were observed between single dose ceftriaxone and the comparator.
The potentially lower clinical cure rate of ceftriaxone should be balanced against the potential advantages of parenteral therapy (see CLINICAL STUDIES ). Skin and Skin Structure Infections Caused by Staphylococcus aureus, Staphylococcus epidermidis, Streptococcus pyogenes , Viridans group streptococci , Escherichia coli, Enterobacter cloacae, Klebsiella oxytoca, Klebsiella pneumoniae, Proteus mirabilis, Morganella morganii*, Pseudomonas aeruginosa, Serratia marcescens, Acinetobacter calcoaceticus, Bacteroides fragilis* or Peptostreptococcus species.
Urinary Tract Infections (complicated and uncomplicated) Caused by Escherichia coli, Proteus mirabilis, Proteus vulgaris, Morganella morganii or Klebsiella pneumoniae. Uncomplicated Gonorrhea (cervical/urethral and rectal) Caused by Neisseria gonorrhoeae , including both penicillinase- and nonpenicillinase-producing strains, and pharyngeal gonorrhea caused by nonpenicillinase-producing strains of Neisseria gonorrhoeae . Pelvic Inflammatory Disease Caused by Neisseria gonorrhoeae .
Ceftriaxone sodium, like other cephalosporins, has no activity against Chlamydia trachomatis . Therefore, when cephalosporins are used in the treatment of patients with pelvic inflammatory disease and Chlamydia trachomatis is one of the suspected pathogens, appropriate antichlamydial coverage should be added. Bacterial Septicemia Caused by Staphylococcus aureus, Streptococcus pneumoniae, Escherichia coli, Haemophilus influenzae or Klebsiella pneumoniae.
Bone and Joint Infections Caused by Staphylococcus aureus, Streptococcus pneumoniae, Escherichia coli, Proteus mirabilis, Klebsiella pneumoniae or Enterobacter species. Intra-abdominal Infections Caused by Escherichia coli, Klebsiella pneumoniae, Bacteroides fragilis, Clostridium species (Note: most strains of Clostridium difficile are resistant) or Peptostreptococcus species. Meningitis Caused by Haemophilus influenzae, Neisseria meningitidis or Streptococcus pneumoniae .
Ceftriaxone has also been used successfully in a limited number of cases of meningitis and shunt infection caused by Staphylococcus epidermidis* and Escherichia coli* . *Efficacy for this organism in this organ system was studied in fewer than ten infections. Surgical Prophylaxis The preoperative administration of a single…
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Ceftriaxone in the ADD-Vantage ® Vial is intended for intravenous infusion only, after dilution with appropriate volume of ADD-Vantage ® diluent solution. Do not use diluents containing calcium, such as Ringer’s solution or Hartmann’s solution, to reconstitute ceftriaxone vials or to further dilute a reconstituted vial for IV administration because a precipitate can form. Precipitation of ceftriaxone-calcium can also occur when ceftriaxone is mixed with calcium-containing solutions in the same IV administration line.
Ceftriaxone must not be administered simultaneously with calcium-containing IV solutions, including continuous calcium-containing infusions such as parenteral nutrition via a Y-site. However, in patients other than neonates, ceftriaxone and calcium-containing solutions may be administered sequentially of one another if the infusion lines are thoroughly flushed between infusions with a compatible fluid (see WARNINGS ). There have been no reports of an interaction between ceftriaxone and oral calcium-containing products or interaction between intramuscular ceftriaxone and calcium-containing products (IV or oral).
Neonates Hyperbilirubinemic neonates, especially prematures, should not be treated with ceftriaxone for injection. Ceftriaxone is contraindicated in premature neonates (see CONTRAINDICATIONS ). Ceftriaxone is contraindicated in neonates (≤ 28 days) if they require (or are expected to require) treatment with calcium-containing IV solutions, including continuous calcium-containing infusions such as parenteral nutrition because of the risk of precipitation of ceftriaxone-calcium (see CONTRAINDICATIONS ).
Intravenous doses should be given over 60 minutes in neonates to reduce the risk of bilirubin encephalopathy. Pediatric Patients For the treatment of skin and skin structure infections, the recommended total daily dose is 50 to 75 mg/kg given once a day (or in equally divided doses twice a day). The total daily dose should not exceed 2 grams.
For the treatment of acute bacterial otitis media, a single intramuscular dose of 50 mg/kg (not to exceed 1 gram) is recommended (see INDICATIONS AND USAGE ). (The above is for informational purposes only. Ceftriaxone in ADD-Vantage ® vials is not intended for intramuscular use.) For the treatment of serious miscellaneous infections other than meningitis, the recommended total daily dose is 50 to 75 mg/kg, given in divided doses every 12 hours.
The total daily dose should not exceed 2 grams. In the treatment of meningitis, it is recommended that the initial therapeutic dose be 100 mg/kg (not to exceed 4 grams). Thereafter, a total daily dose of 100 mg/kg/day (not to exceed 4 grams daily) is recommended.
The daily dose may be administered once a day (or in equally divided doses every 12 hours). The usual duration of therapy is 7 to 14 days. Adults The usual adult daily dose is 1 to 2 grams given once a day (or in equally divided doses twice a day) depending on the type and severity of infection.
The total daily dose should not exceed 4 grams. If Chlamydia trachomatis is a suspected pathogen, appropriate antichlamydial coverage should be added, because ceftriaxone sodium has no activity against this organism. For the treatment of uncomplicated gonococcal infections, a single intramuscular dose of 250 mg is recommended.
(The above is for informational purposes only. Ceftriaxone in ADD-Vantage ® vials is not intended for intramuscular use.) For preoperative use (surgical prophylaxis), a single dose of 1 gram administered intravenously ½ to 2 hours before surgery is recommended. Generally, ceftriaxone therapy should be continued for at least 2 days after the signs and symptoms of infection have disappeared.
The usual duration of therapy is 4 to 14 days; in complicated infections, longer therapy may be required. When treating infections caused by Streptococcus pyogenes, therapy should be continued for at least 10 days. No dosage adjustment is necessary…
⛔ Contraindications ▾
CONTRAINDICATIONS Hypersensitivity Ceftriaxone for injection is contraindicated in patients with known hypersensitivity to ceftriaxone, any of its excipients or to any other cephalosporin. Patients with previous hypersensitivity reactions to penicillin and other beta lactam antibacterial agents may be at greater risk of hypersensitivity to ceftriaxone (see WARNINGS – Hypersensitivity Reactions ). Neonates Premature neonates Ceftriaxone for injection is contraindicated in premature neonates up to a postmenstrual age of 41 weeks (gestational age + chronological age).
Hyperbilirubinemic neonates Hyperbilirubinemic neonates should not be treated with ceftriaxone for injection. Ceftriaxone can displace bilirubin from its binding to serum albumin, leading to a risk of bilirubin encephalopathy in these patients. Neonates Requiring Calcium Containing IV Solutions Ceftriaxone for injection is contraindicated in neonates (≤ 28 days) if they require (or are expected to require) treatment with calcium-containing IV solutions, including continuous calcium-containing infusions such as parenteral nutrition because of the risk of precipitation of ceftriaxone-calcium (see CLINICAL PHARMACOLOGY , WARNINGS and DOSAGE AND ADMINISTRATION ).
Cases of fatal outcomes in which a crystalline material was observed in the lungs and kidneys at autopsy have been reported in neonates receiving ceftriaxone for injection and calcium-containing fluids. In some of these cases, the same intravenous infusion line was used for both ceftriaxone for injection and calcium-containing fluids and in some a precipitate was observed in the intravenous infusion line. There have been no similar reports in patients other than neonates.
Lidocaine Intravenous administration of ceftriaxone solutions containing lidocaine is contraindicated. When lidocaine solution is used as a solvent with ceftriaxone for intramuscular injection, exclude all contraindications to lidocaine. Refer to the prescribing information of lidocaine.
⚠️ Warnings ▾
WARNINGS Hypersensitivity Reactions Before therapy with ceftriaxone for injection is instituted, careful inquiry should be made to determine whether the patient has had previous hypersensitivity reactions to cephalosporins, penicillins and other beta-lactam agents or other drugs. This product should be given cautiously to penicillin and other beta-lactam agent-sensitive patients. Antibacterial drugs should be administered with caution to any patient who has demonstrated some form of allergy, particularly to drugs.
Serious acute hypersensitivity reactions may require the use of subcutaneous epinephrine and other emergency measures. As with all beta-lactam antibacterial agents, serious and occasionally fatal hypersensitivity reactions (i.e., anaphylaxis) have been reported. In case of severe hypersensitivity reactions, treatment with ceftriaxone must be discontinued immediately and adequate emergency measures must be initiated.
Interaction with Calcium-Containing Products Do not use diluents containing calcium, such as Ringer’s solution or Hartmann’s solution, to reconstitute ceftriaxone vials or to further dilute a reconstituted vial for IV administration because a precipitate can form. Precipitation of ceftriaxone-calcium can also occur when ceftriaxone is mixed with calcium-containing solutions in the same IV administration line. Ceftriaxone must not be administered simultaneously with calcium-containing IV solutions, including continuous calcium-containing infusions such as parenteral nutrition via a Y-site.
However, in patients other than neonates, ceftriaxone and calcium-containing solutions may be administered sequentially of one another if the infusion lines are thoroughly flushed between infusions with a compatible fluid. In vitro studies using adult and neonatal plasma from umbilical cord blood demonstrated that neonates have an increased risk of precipitation of ceftriaxone-calcium (see CLINICAL PHARMACOLOGY , CONTRAINDICATIONS and DOSAGE AND ADMINISTRATION ). Neurological Adverse Reactions Serious neurological adverse reactions have been reported during postmarketing surveillance with ceftriaxone use.
These reactions include encephalopathy (disturbance of consciousness including somnolence, lethargy, and confusion), seizures, myoclonus, and non-convulsive status epilepticus (see ADVERSE REACTIONS ). Some cases occurred in patients with severe renal impairment who did not receive appropriate dosage adjustment. However, in other cases, neurological adverse reactions occurred in patients receiving an appropriate dosage adjustment.
The neurological adverse reactions were reversible and resolved after discontinuation. If neurological adverse reactions associated with ceftriaxone for injection therapy occur, discontinue ceftriaxone for injection and institute appropriate supportive measures. Make appropriate dosage adjustments in patients with severe renal impairment (see DOSAGE AND ADMINISTRATION ).
Clostridium difficile -Associated Diarrhea Clostridium difficile associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including ceftriaxone, and may range in severity from mild diarrhea to fatal colitis. Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C. difficile. C. difficile produces toxins A and B which contribute to the development of CDAD.
Hypertoxin producing strains of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy. CDAD must be considered in all patients who present with diarrhea following antibiotic use. Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents.
If CDAD is suspected or confirmed, ongoing antibiotic use not directed against C. difficile may need to be discontinued. Appropriate fluid and electrolyte management, protein supplementation, antibi…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Ceftriaxone is generally well tolerated. In clinical trials, the following adverse reactions, which were considered to be related to ceftriaxone therapy or of uncertain etiology, were observed: Local Reactions Pain, induration and tenderness was 1% overall. Phlebitis was reported in <1% after IV administration.
The incidence of warmth, tightness or induration was 17% (3/17) after IM administration of 350 mg/mL and 5% (1/20) after IM administration of 250 mg/mL. General Disorders and Administration Site Conditions Injection site pain (0.6%) Hypersensitivity Rash (1.7%). Less frequently reported (<1%) were pruritus, fever or chills.
Infections and Infestations Genital fungal infection (0.1%) Hematologic Eosinophilia (6%), thrombocytosis (5.1%) and leukopenia (2.1%). Less frequently reported (<1%) were anemia, hemolytic anemia, neutropenia, lymphopenia, thrombocytopenia and prolongation of the prothrombin time. Blood and Lymphatic Disorders Granulocytopenia (0.9%), coagulopathy (0.4%) Gastrointestinal Diarrhea/loose stools (2.7%).
Less frequently reported (<1%) were nausea or vomiting, and dysgeusia. The onset of pseudomembranous colitis symptoms may occur during or after antibacterial treatment (see WARNINGS ). Hepatic Elevations of aspartate aminotransferase (AST) (3.1%) or alanine aminotransferase (ALT) (3.3%).
Less frequently reported (<1%) were elevations of alkaline phosphatase and bilirubin. Renal Elevations of the BUN (1.2%). Less frequently reported (<1%) were elevations of creatinine and the presence of casts in the urine.
Central Nervous System Headache or dizziness were reported occasionally (<1%). Genitourinary Moniliasis or vaginitis were reported occasionally (<1%). Miscellaneous Diaphoresis and flushing were reported occasionally (<1%).
Investigations Blood creatinine increased (0.6%). Other rarely observed adverse reactions (<0.1%) include abdominal pain, agranulocytosis, allergic pneumonitis, anaphylaxis, basophilia, biliary lithiasis, bronchospasm, colitis, dyspepsia, epistaxis, flatulence, gallbladder sludge, glycosuria, hematuria, jaundice, leukocytosis, lymphocytosis, monocytosis, nephrolithiasis, palpitations, a decrease in the prothrombin time, renal precipitations, seizures, and serum sickness. Post-Marketing Experience In addition to the adverse reactions reported during clinical trials, the following adverse experiences have been reported during clinical practice in patients treated with ceftriaxone.
Data are generally insufficient to allow an estimate of incidence or to establish causation. A small number of cases of fatal outcomes in which a crystalline material was observed in the lungs and kidneys at autopsy have been reported in neonates receiving ceftriaxone and calcium-containing fluids. In some of these cases, the same intravenous infusion line was used for both ceftriaxone and calcium-containing fluids and in some a precipitate was observed in the intravenous infusion line.
At least one fatality has been reported in a neonate in whom ceftriaxone and calcium-containing fluids were administered at different time points via different intravenous lines; no crystalline material was observed at autopsy in this neonate. There have been no similar reports in patients other than neonates. Gastrointestinal Pancreatitis, stomatitis and glossitis.
Genitourinary Oliguria, ureteric obstruction, post-renal acute renal failure. Dermatologic Exanthema, allergic dermatitis, urticaria, edema; acute generalized exanthematous pustulosis (AGEP) and isolated cases of severe cutaneous adverse reactions (erythema multiforme, Stevens-Johnson syndrome or Lyell’s syndrome/toxic epidermal necrolysis) have been reported. Hematological Changes Isolated cases of agranulocytosis (< 500/mm 3 ) have been reported, most of them after 10 days of treatment and following total doses of 20 g or more.
Neurologic Encephalopathy, seizures, myoclonus, and non-convulsive status epilepticus (see WARNINGS and PRECAUTIONS )…
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects Reproductive studies have been performed in mice and rats at doses up to 20 times the usual human dose and have no evidence of embryotoxicity, fetotoxicity or teratogenicity. In primates, no embryotoxicity or teratogenicity was demonstrated at a dose approximately 3 times the human dose. There are, however, no adequate and well-controlled studies in pregnant women.
Because animal reproductive studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed. Nonteratogenic Effects In rats, in the Segment I (fertility and general reproduction) and Segment III (perinatal and postnatal) studies with intravenously administered ceftriaxone, no adverse effects were noted on various reproductive parameters during gestation and lactation, including postnatal growth, functional behavior and reproductive ability of the offspring, at doses of 586 mg/kg/day or less.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness of ceftriaxone in neonates, infants and pediatric patients have been established for the dosages described in the DOSAGE AND ADMINISTRATION section. In vitro studies have shown that ceftriaxone, like some other cephalosporins, can displace bilirubin from serum albumin. Ceftriaxone should not be administered to hyperbilirubinemic neonates, especially prematures (see CONTRAINDICATIONS ).
🆘 Overdosage ▾
OVERDOSAGE Ceftriaxone overdosage has been reported in patients with severe renal impairment. Reactions have included neurological outcomes, including encephalopathy, seizures, myoclonus, and non-convulsive status epilepticus. In the event of overdosage, discontinue ceftriaxone for injection therapy and provide general supportive treatment (see DOSAGE AND ADMINISTRATION , WARNINGS and PRECAUTIONS ).
In the case of overdosage, drug concentration would not be reduced by hemodialysis or peritoneal dialysis. There is no specific antidote. Treatment of overdosage should be symptomatic.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Average plasma concentrations of ceftriaxone following a single 30-minute intravenous (IV) infusion of a 0.5, 1 or 2 g dose and intramuscular (IM) administration of a single 0.5 (250 mg/mL or 350 mg/mL concentrations) or 1 g dose in healthy subjects are presented in Table 1 . Table 1. Ceftriaxone Plasma Concentrations after Single Dose Administration Dose/Route Average Plasma Concentrations (mcg/mL) 0.5 hour 1 hour 2 hour 4 hour 6 hour 8 hour 12 hour 16 hour 24 hour 0.5 g IV* 82 59 48 37 29 23 15 10 5 0.5 g IM 250 mg/mL 22 33 38 35 30 26 16 ND 5 0.5 g IM 350 mg/mL 20 32 38 34 31 24 16 ND 5 1 g IV* 151 111 88 67 53 43 28 18 9 1 g IM 40 68 76 68 56 44 29 ND ND 2 g IV* 257 192 154 117 89 74 46 31 15 ND = Not determined. * IV doses were infused at a constant rate over 30 minutes.
Ceftriaxone was completely absorbed following IM administration with mean maximum plasma concentrations occurring between 2 and 3 hours post-dose. Multiple IV or IM doses ranging from 0.5 to 2 g at 12 to 24 hour intervals resulted in 15% to 36% accumulation of ceftriaxone above single dose values. Ceftriaxone concentrations in urine are shown in Table 2 .
Table 2. Urinary Concentrations of Ceftriaxone after Single Dose Administration Dose/Route Average Urinary Concentrations (mcg/mL) 0 to 2 hour 2 to 4 hour 4 to 8 hour 8 to 12 hour 12 to 24 hour 24 to 48 hour 0.5 g IV 526 366 142 87 70 15 0.5 g IM 115 425 308 127 96 28 1 g IV 995 855 293 147 132 32 1 g IM 504 628 418 237 ND ND 2 g IV 2692 1976 757 274 198 40 ND = Not determined. Thirty-three percent to 67% of a ceftriaxone dose was excreted in the urine as unchanged drug and the remainder was secreted in the bile and ultimately found in the feces as microbiologically inactive compounds.
After a 1 g IV dose, average concentrations of ceftriaxone, determined from 1 to 3 hours after dosing, were 581 mcg/mL in the gallbladder bile, 788 mcg/mL in the common duct bile, 898 mcg/mL in the cystic duct bile, 78.2 mcg/g in the gallbladder wall and 62.1 mcg/mL in the concurrent plasma. Over a 0.15 to 3 g dose range in healthy adult subjects, the values of elimination half-life ranged from 5.8 to 8.7 hours; apparent volume of distribution from 5.78 to
13.5L; plasma clearance from 0.58 to
1.45L/hour; and renal clearance from 0.32 to
0.73L/hour. Ceftriaxone is reversibly bound to human plasma proteins, and the binding decreased from a value of 95% bound at plasma concentrations of <25 mcg/mL to a value of 85% bound at 300 mcg/mL. Ceftriaxone crosses the blood placenta barrier.
The average values of maximum plasma concentration, elimination half-life, plasma clearance and volume of distribution after a 50 mg/kg IV dose and after a 75 mg/kg IV dose in pediatric patients suffering from bacterial meningitis are shown in Table 3 . Ceftriaxone penetrated the inflamed meninges of infants and pediatric patients; CSF concentrations after a 50 mg/kg IV dose and after a 75 mg/kg IV dose are also shown in Table 3 . Table 3.
Average Pharmacokinetic Parameters of Ceftriaxone in Pediatric Patients with Meningitis 50 mg/kg IV 75 mg/kg IV Maximum Plasma Concentrations (mcg/mL) 216 275 Elimination Half-life (hour) 4.6
4.3Plasma Clearance (mL/hour/kg) 49 60 Volume of Distribution (mL/kg) 338 373 CSF Concentration – inflamed meninges (mcg/mL) 5.6
6.4Range (mcg/mL) 1.3 to 18.5 1.3 to 44 Time after dose (hour) 3.7 (± 1.6) 3.3 (± 1.4) Compared to that in healthy adult subjects, the pharmacokinetics of ceftriaxone were only minimally altered in elderly subjects and in patients with renal impairment or hepatic dysfunction ( Table 4 ); therefore, dosage adjustments are not necessary for these patients with ceftriaxone dosages up to 2 g per day. Ceftriaxone was not removed to any significant extent from the plasma by hemodialysis; in six of 26 dialysis patients, the elimination rate of ceftriaxone was markedly reduced.
Table 4. Average Pharmacokinetic Parameters of Ceftriaxone in Humans Subject Group Elimination Half-Li…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Ceftriaxone for injection, USP is supplied as a sterile, white to yellowish crystalline powder in ADD-Vantage ® Vials as follows: ADD-Vantage ® Vials containing 1 g equivalent to ceftriaxone. Box of 10 (NDC 0409-7333-04). ADD-Vantage ® Vials containing 2 g equivalent to ceftriaxone. Box of 10 (NDC 0409-7336-04). Storage Prior to Reconstitution Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature]. Protect from light.
📋 Description ▾
DESCRIPTION Ceftriaxone for injection, USP is a sterile, semisynthetic, broad-spectrum cephalosporin antibiotic for intravenous or intramuscular administration. Ceftriaxone sodium is (6 R ,7 R )-7-[2-(2-Amino-4-thiazolyl)glyoxylamido]-8-oxo-3-[[(1,2,5,6-tetrahydro-2-methyl-5,6-dioxo- as -triazin-3-yl)thio]methyl]-5-thia-1-azabicyclo[4.2.0]oct-2-ene-2-carboxylic acid, 7 2 -( Z )-(O-methyloxime), disodium salt, sesquaterhydrate. The chemical formula of ceftriaxone sodium is C 18 H 16 N 8 Na 2 O 7 S 3 •3.5H 2 O.
It has a calculated molecular weight of 661.60 and the following structural formula: Ceftriaxone sodium is a white to yellowish crystalline powder which is readily soluble in water, sparingly soluble in methanol and very slightly soluble in ethanol. The pH of a 1% aqueous solution is approximately 6.7. The color of ceftriaxone sodium solutions ranges from light yellow to amber, depending on the length of storage, concentration and diluent used.
Ceftriaxone sodium contains approximately 83 mg (3.6 mEq) of sodium per gram of ceftriaxone activity. Ceftriaxone Chemical Structure
💬 Information for Patients ▾
Information for Patients • Patients should be counseled that antibacterial drugs including ceftriaxone for injection should only be used to treat bacterial infections. They do not treat viral infections (e.g., common cold). • When ceftriaxone for injection is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed. Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by ceftriaxone for injection or other antibacterial drugs in the future. • Diarrhea is a common problem caused by antibiotics which usually ends when the antibiotic is discontinued.
Sometimes after starting treatment with antibiotics, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibiotic. If this occurs, patients should contact their physician as soon as possible.