
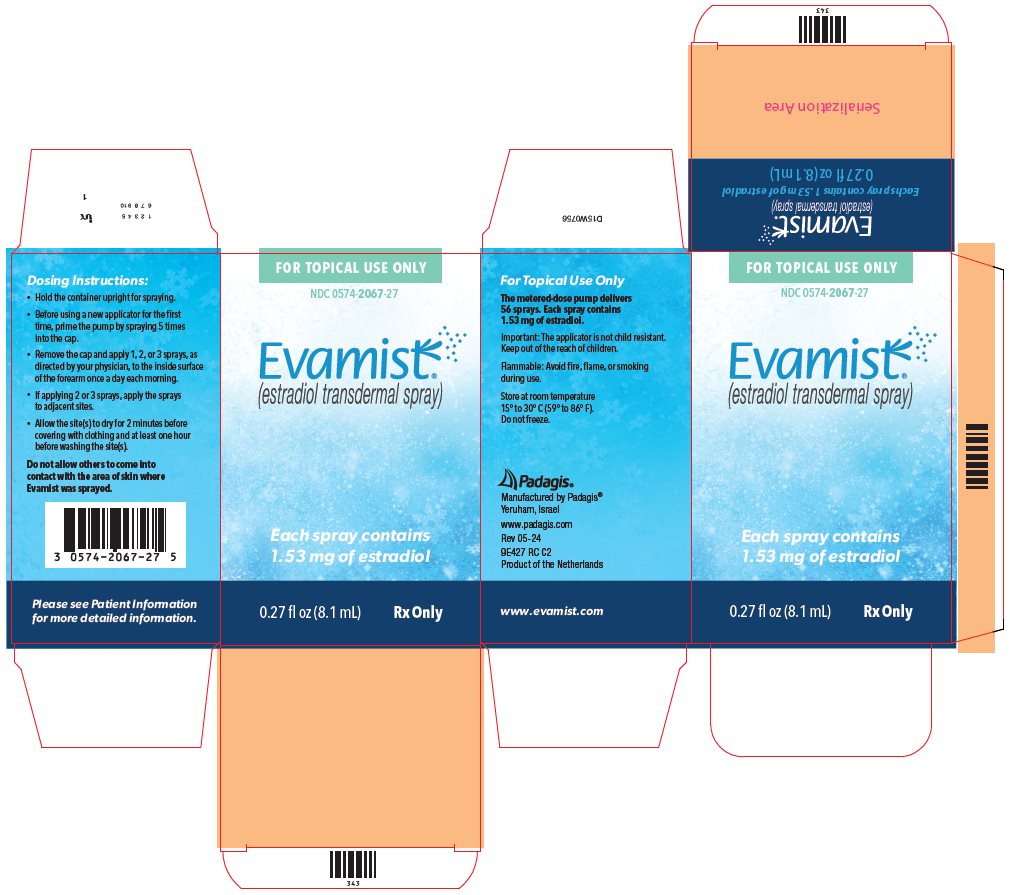
Evamist Estradiol 1.53 mg Spray, 56-count
Other active recalls for Estradiol (different manufacturers) — 3 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Radioactive Diagnostic Agent class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Estradiol topical may be used for the following: to treat and prevent hot flushes (hot flashes; sudden strong feelings of heat and sweating) in women who are experiencing menopause (change of life; the end of monthly menstrual periods). to treat vaginal dryness, itching, and burning Estradiol is in a class of medications called estrogen hormones. It works by replacing estrogen that is normally produced by the body.
Read the full MedlinePlus article ↗- Estradiol is a form of estrogen — the main female sex hormone. When estrogen levels fall after menopause (or due to other conditions like ovarian failure), you can get symptoms lik...
- What exactly is estradiol and why has my doctor prescribed it?
- Apply the patch to a clean, dry area of skin — usually the lower abdomen. Never put it on your breasts. Press it firmly in place and leave it on for the full wear period — once a w...
- How do I use my estradiol patch correctly?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Estradiol — tap one for details:
Estradiol may be associated with lower levels of 5 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII 4X49Y0596W
Ethylhexyl salicylate is a synthetic organic compound used as a UV filter and penetration enhancer in topical formulations. It helps protect the product and skin from ultraviolet light damage.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $16.73 | — |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Evamist 1.53 mgthis 00574-2067-00 | Padagis | 56 sprays | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 00574-2067-00 You're viewing this | 56 SPRAY in 1 VIAL, MULTI-DOSE (0574-2067-00) | — | — | 2015-04-11 | Active |
| 00574-2067-27 | 56 SPRAY in 1 VIAL, MULTI-DOSE (0574-2067-27) | $18.22 / mL | — | 2015-04-11 | Active |
This pack shows little to no recent Medicaid volume — the 56 sprays pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 00574-2067-00?
What is the difference between NDC 00574-2067-00 and NDC 00574-2067-27?
What NDC number is used to bill for this package of Evamist Estradiol 1.53 mg Spray?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: ENDOMETRIAL CANCER, CARDIOVASCULAR DISORDERS, PROBABLE DEMENTIA, BREAST CANCER, and UNINTENTIONAL SECONDARY EXPOSURE TO ESTROGEN Estrogen-Alone Therapy Endometrial Cancer There is an increased risk of endometrial cancer in a woman with a uterus who uses unopposed estrogens. Adding a progestogen to estrogen therapy has been shown to reduce the risk of endometrial hyperplasia, which may be a precursor to endometrial cancer. Perform adequate diagnostic measures, including directed and random endometrial sampling when indicated, to rule out malignancy in all cases of undiagnosed persistent or recurring abnormal genital bleeding [see Warnings and Precautions ( 5.2 )] .
Cardiovascular Disorders and Probable Dementia The Women’s Health Initiative (WHI) estrogen-alone substudy reported increased risks of stroke and deep vein thrombosis (DVT) in postmenopausal women (50 to 79 years of age) during 7.1 years of treatment with daily oral conjugated estrogens (CE) [0.625 mg]-alone, relative to placebo [see Warnings and Precautions ( 5.1 ), and Clinical Studies ( 14.2 )] . The WHI Memory Study (WHIMS) estrogen-alone ancillary study of WHI reported an increased risk of developing probable dementia in postmenopausal women 65 years of age and older during 5.2 years of treatment with daily CE (0.625 mg)-alone, relative to placebo.
It is unknown whether this finding applies to younger postmenopausal women [see Warnings and Precautions ( 5.3 ), Use in Specific Populations ( 8.5 ), and Clinical Studies ( 14.3 )]. Do not use estrogen-alone therapy for the prevention of cardiovascular disease or dementia [see Warnings and Precautions ( 5.1 , 5.3 ), and Clinical Studies ( 14.2 , 14.3 )]. Only daily oral 0.625 mg CE was studied in the estrogen-alone substudy of the WHI.
Therefore, the relevance of the WHI findings regarding adverse cardiovascular events and dementia to lower CE doses, other routes of administration, or other estrogen-alone products is not known. Without such data, it is not possible to definitively exclude these risks or determine the extent of these risks for other products. Discuss with your patient the benefits and risks of estrogen-alone therapy, taking into account her individual risk profile.
Prescribe estrogens with or without progestogens at the lowest effective doses and for the shortest duration consistent with treatment goals and risks for the individual woman. Estrogen Plus Progestin Therapy Cardiovascular Disorders and Probable Dementia The WHI estrogen plus progestin substudy reported increased risks of pulmonary embolism (PE), DVT, stroke and myocardial infarction (MI) in postmenopausal women (50 to 79 years of age) during 5.6 years of treatment with daily oral CE (0.625 mg) combined with medroxyprogesterone acetate (MPA) [2.5 mg], relative to placebo [see Warnings and Precautions ( 5.1 ), and Clinical Studies ( 14.2 )] .
The WHIMS estrogen plus progestin ancillary study of WHI reported an increased risk of developing probable dementia in postmenopausal women 65 years of age and older during 4 years of treatment with daily CE (0.625mg) combined with MPA (2.5 mg), relative to placebo. It is unknown whether this finding applies to younger postmenopausal women [see Warnings and Precautions (5.3), Use in Specific Populations ( 8.5 ), and Clinical Studies ( 14.3 )] . Do not use estrogen plus progestogen therapy for the prevention of cardiovascular disease or dementia [see Warning and Precautions ( 5.1 , 5.3 ), and Clinical Studies ( 14.2 )] .
Breast Cancer The WHI estrogen plus progestin substudy demonstrated an increased risk of invasive breast cancer [see Warnings and Precautions ( 5.2 ), and Clinical Studies ( 14.2 )] . Only daily oral 0.625 mg CE and 2.5 mg MPA were studied in the estrogen plus progestin substudy of the WHI. Therefore, the relevance of the WHI findings regarding adverse cardiovascular events, dementia and breast cancer to lower CE plus other MPA doses, other routes of administration, or other es…
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Evamist is an estrogen indicated for the treatment of moderate to severe vasomotor symptoms due to menopause ( 1.1 )
1.1Treatment of Moderate to Severe Vasomotor Symptoms due to Menopause.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Generally, when estrogen is prescribed for a postmenopausal woman with a uterus, consider addition of a progestogen to reduce the risk of endometrial cancer. Generally, a woman without a uterus does not need to use a progestogen in addition to her estrogen therapy. In some cases, however, hysterectomized women who have a history of endometriosis may need a progestogen [see Warnings and Precautions ( 5.2 , 5.15 )] .
Use estrogen-alone, or in combination with a progestogen, at the lowest effective dose and for the shortest duration consistent with treatment goals and risks for the individual woman. Re-evaluate postmenopausal women periodically as clinically appropriate to determine whether treatment is still necessary. • Start therapy with one spray of Evamist once daily each morning to forearm ( 2.1 ) • Dosage adjustment to two or three sprays of Evamist should be guided by the clinical response ( 2.1 )
2.1Treatment of Moderate to Severe Vasomotor Symptoms due to Menopause Start Evamist therapy with one spray of Evamist per day. Make dosage adjustment based on the clinical response. Prime the Evamist container by spraying 5 sprays with the cover on before applying the first dose from a new applicator.
Hold the container upright and vertical for spraying. Apply one, two or three sprays each morning to adjacent, non-overlapping areas on the inner surface of the forearm, starting near the elbow. Allow the sprays to dry for approximately 2 minutes before covering the site with clothing.
Do not wash the application site for at least one hour. Application of Evamist to other skin surfaces has not been adequately studied. Evamist should not be applied to skin surfaces other than the forearm.
Strict adherence to the following precautions is advised in order to minimize the potential for secondary exposure to estradiol from Evamist-treated skin. Cover the Evamist application site with clothing if another person may come into contact with that area of skin after the spray dries. Additional precautions to minimize unintentional secondary exposure are outlined in Patient Counseling Information [see Patient Counseling Information] and in the Patient Information Leaflet at the end of the prescribing information.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Evamist is an estradiol transdermal spray. One spray consists of 90 mcL that contains 1.53 mg of estradiol. • Spray: One spray consists of 90 mcL which contains 1.53 mg estradiol ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Evamist is contraindicated in women with any of the following conditions: • Undiagnosed abnormal genital bleeding [see Warnings and Precautions ( 5.2 )]. • Breast cancer or a history of breast cancer [see Warnings and Precautions ( 5.2 )]. • Estrogen-dependent neoplasia [see Warnings and Precautions ( 5.2 )]. • Active DVT, PE, or history of these conditions [see Warnings and Precautions ( 5.1 )]. • Active arterial thromboembolic disease (for example, stroke or MI), or a history of these conditions [see Warnings and Precautions ( 5.1 )]. • Known anaphylactic reaction, angioedema, or hypersensitivity to Evamist. • Hepatic impairment or disease. • Protein C, protein S, or antithrombin deficiency, or other known thrombophilic disorders. • Undiagnosed abnormal genital bleeding ( 4 , 5.2 ) • Breast cancer or a history of breast cancer ( 4 , 5.2 ) • Estrogen-dependent neoplasia ( 4 , 5.2 ) • Active DVT, PE, or history of these conditions ( 4 , 5.1 ) • Active arterial thromboembolic disease (for example, stroke and MI), or history of these conditions ( 4 , 5.1 ) • Known anaphylactic reaction, angioedema, or hypersensitivity to Evamist ( 4 ) • Hepatic impairment or disease ( 4 , 5.10 ) • Protein C, protein S, or antithrombin deficiency, or other known thrombophilic disorders ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Estrogens increase the risk of gallbladder disease ( 5.5 ) • Discontinue estrogens if severe hypercalcemia, loss of vision, severe hypertriglyceridemia or cholestatic jaundice occurs ( 5.6 , 5.7 , 5.10 , 5.11 ) • Monitor thyroid function in women on thyroid hormone replacement therapy ( 5.12 , 5.21 )
5.1Cardiovascular Disorders Increased risks of stroke and DVT are reported with estrogen-alone therapy. Increased risks of PE, DVT, stroke, and MI are reported with estrogen plus progestin therapy. Should any of these occur or be suspected, estrogen with or without progestin therapy should be discontinued.
Immediately discontinue estrogen with or without progestogen therapy if any of these occur or are suspected. Manage appropriately any risk factors for arterial vascular disease (for example, hypertension, diabetes mellitus, tobacco use, hypercholesterolemia, and obesity) and/or venous thromboembolism (VTE) (for example, personal history or family history of VTE, obesity, and systemic lupus erythematosus). Stroke The WHI estrogen-alone substudy reported a statistically significant increased risk of stroke in women 50 to 79 years of age receiving daily CE (0.625 mg)-alone compared to women in the same age group receiving placebo (45 versus 33 strokes per 10,000 women-years, respectively).
The increase in risk was demonstrated in year 1 and persisted [see Clinical Studies ( 14.2 )] . Immediately discontinue estrogen-alone therapy if a stroke occurs or is suspected. Subgroup analyses of women 50 to 59 years of age suggest no increased risk of stroke for those women receiving CE (0.625 mg)-alone versus those receiving placebo (18 versus 21 per 10,000 women-years).
1 The WHI estrogen plus progestin substudy reported a statistically significant increased risk of stroke in women 50 to 79 years of age receiving daily CE (0.625 mg) plus MPA (2.5 mg) compared to women in the same age group receiving placebo (33 versus 25 strokes per 10,000 women-years, respectively) [see Clinical Studies ( 14.2 )] . The increase in risk was demonstrated after the first year and persisted. 1 Immediately discontinue estrogen plus progestogen therapy if a stroke occurs or is suspected.
Coronary Heart Disease The WHI estrogen-alone substudy reported no overall effect on coronary heart disease (CHD) events (defined as non-fatal MI, silent MI, or CHD death) in women receiving estrogen-alone compared to placebo 2 [see Clinical Studies ( 14.2 )] . Subgroup analysis of women 50 to 59 years of age, who were less than 10 years since menopause, suggest a reduction (not statistically significant) of CHD events in those women receiving daily CE (0.635 mg)-alone compared to placebo) (8 versus 16 per 10,000 women-years) 1 .
The WHI estrogen plus progestin substudy reported an increased risk (not statistically significant) of CHD events in women receiving daily CE (0.625 mg) plus MPA (2.5 mg) compared to women receiving placebo (41 versus 34 per 10,000 women-years) 1 . An increase in relative risk was demonstrated in year 1, and a trend toward decreasing relative risk was reported in years 2 through 5 [see Clinical Studies ( 14.2 )] . In postmenopausal women with documented heart disease (n = 2,763), average 66.7 years of age, in a controlled clinical trial of secondary prevention of cardiovascular disease (Heart and Estrogen/Progestin Replacement Study; (HERS), treatment with daily CE (0.625 mg) plus MPA (2.5 mg) demonstrated no cardiovascular benefit.
During an average follow-up of 4.1 years, treatment with CE plus MPA did not reduce the overall rate of CHD events in postmenopausal women with established CHD. There were more CHD events in the CE plus MPA-treated group than in the placebo group in year 1, but not during the subsequent years. Two thousand, three hundred and twenty-one (2,321) women from the original HERS trial agreed to participate in an open label extension of the original HERS, HERS II.
Average follow-up in HERS II was an ad…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed elsewhere in the labeling: • Cardiovascular Disorders [see Boxed Warning, Warnings and Precautions ( 5.1 )] • Malignant Neoplasms [see Boxed Warning, Warnings and Precautions ( 5.2 )] The most common adverse reactions (≥ 5 percent) with Evamist are: headache, breast tenderness and nipple pain, nausea, back pain, and nasopharyngitis. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Padagis ® at 1-866-634-9120 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. In a 12-week, randomized, placebo-controlled trial of Evamist in 454 women, 80 to 90 percent of women randomized to active drug received at least 70 days of therapy and 75 to 85 percent randomized to placebo received at least 70 days of therapy.
The adverse reactions that occurred in at least 5 percent of women in any treatment group are shown in Table 1. Table 1. Frequency of Adverse Reactions (≥5%) in Any Treatment Group in a Controlled Study of Evamist Frequency n (%) System Organ Class Preferred Term 1 Spray 2 Sprays 3 Sprays Placebo (N = 77) Evamist (N = 76) Placebo (N = 76) Evamist (N = 74) Placebo (N = 75) Evamist (N = 76) Reproductive System and Breast Disorders Breast tenderness 0 (0) 4 (5) 4 (5) 5 (7) 0 (0) 4 (5) Nipple pain 0 (0) 2 (3) 0 (0) 5 (7) 0 (0) 1 (1) Gastrointestinal Disorders Nausea 5 (7) 1 (1) 1 (1) 2 (3) 4 (5) 2 (3) Infections and Infestations Nasopharyngitis 1 (1) 4 (5) 2 (3) 3 (4) 1 (1) 1 (1) Musculoskeletal and Connective Tissue Disorders Back pain 1 (1) 2 (3) 2 (3) 4 (5) 1 (1) 2 (3) Arthralgia 1 (1) 1 (1) 4 (5) 1 (1) 0 (0) 3 (4) Nervous system Headache 4 (5) 7 (9) 5 (7) 9 (12) 7 (9) 8 (11) Application site reactions were reported in 3 out of 226 (1.3%) women treated with Evamist.
6.2Postmarketing Experience The following additional adverse reactions have been identified during post-approval use of Evamist. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Breasts: Breast swelling, breast mass, breast enlargement Cardiovascular: Heart rate increased Central nervous system: Dizziness, dysgeusia, paresthesia, lethargy, hypoesthesia Eyes: Eye irritation, ocular hyperemia Gastrointestinal: Abdominal pain, diarrhea, constipation, abdominal distension, dry mouth, decreased appetite Genitourinary system: Vaginal bleeding Musculoskeletal: Muscle spasms, arthritis Psychiatric: Insomnia, mood swings, anxiety, irritability, mood altered, depression Respiratory tract: Cough, dyspnea, dry throat Skin: Nipple and areola discoloration, usually on the same side of the body as the inner forearm on which Evamist is applied, rash, pruritus, alopecia, urticaria, dry skin, skin discoloration, chloasma Miscellaneous: Weight increased, malaise, fatigue, asthenia
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS In vitro and in vivo studies have shown that estrogens are metabolized partially by cytochrome P450 3A4 (CYP3A4). Therefore, inducers or inhibitors of CYP3A4 may affect estrogen drug metabolism. Inducers of CYP3A4 such as St.
John's wort (Hypericum perforatum) preparations, phenobarbital, carbamazepine, and rifampin may reduce plasma concentrations of estrogens, possibly resulting in a decrease in therapeutic effects and/or changes in the uterine bleeding profile. Inhibitors of CYP3A4 such as erythromycin, clarithromycin, ketoconazole, itraconazole, ritonavir and grapefruit juice may increase plasma concentrations of estrogens and may result in adverse reactions. • Inducers and inhibitors of CYP3A4 may affect estrogen drug metabolism and decrease or increase the estrogen plasma concentration.
( 7.1 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Evamist is not indicated for use in pregnancy. There are no data with the use of Evamist in pregnant women; however, epidemiologic studies and meta-analyses have not found an increased risk of genital or nongenital birth defects (including cardiac anomalies and limb-reduction defects) following exposure to combined hormonal contraceptives (estrogens and progestins) before conception or during early pregnancy. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
8.2Lactation Risk Summary Estrogens are present in human milk and can reduce milk production in breast-feeding females. This reduction can occur at any time but is less likely to occur once breast-feeding is well-established. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for Evamist and any potential adverse effects on the breastfed child from Evamist or from the underlying maternal condition.
8.4Pediatric Use Evamist is not indicated for use in pediatric patients. Clinical studies have not been conducted in the pediatric population.
8.5Geriatric Use There have not been sufficient numbers of geriatric women involved in clinical studies utilizing Evamist to determine whether those over 65 years of age differ from younger subjects in their response to Evamist. The Women’s Health Initiative Studies In the WHI estrogen-alone substudy (daily CE [0.625 mg]-alone versus placebo), there was a higher relative risk of stroke in women greater than 65 years of age [see Clinical Studies ( 14.2 )] . In the WHI estrogen plus progestin substudy (daily CE [0.625 mg] plus MPA [2.5 mg] versus placebo), there was a higher relative risk of nonfatal stroke and invasive breast cancer in women greater than 65 years of age [see Clinical Studies ( 14.2 )] .
The Women’s Health Initiative Memory Study In the WHIMS ancillary studies of postmenopausal women 65 to 79 years of age, there was an increased risk of developing probable dementia in women receiving estrogen-alone or estrogen plus progestin when compared to placebo [see Warnings and Precautions ( 5.3 ), and Clinical Studies ( 14.3 )] . Since both ancillary studies were conducted in women 65 to 79 years of age, it is unknown whether these findings apply to younger postmenopausal women 8 [see Warnings and Precautions ( 5.3 ), and Clinical Studies ( 14.3 )].
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Evamist is not indicated for use in pregnancy. There are no data with the use of Evamist in pregnant women; however, epidemiologic studies and meta-analyses have not found an increased risk of genital or nongenital birth defects (including cardiac anomalies and limb-reduction defects) following exposure to combined hormonal contraceptives (estrogens and progestins) before conception or during early pregnancy. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
🧒 Pediatric Use ▾
8.4Pediatric Use Evamist is not indicated for use in pediatric patients. Clinical studies have not been conducted in the pediatric population.
🧓 Geriatric Use ▾
8.5Geriatric Use There have not been sufficient numbers of geriatric women involved in clinical studies utilizing Evamist to determine whether those over 65 years of age differ from younger subjects in their response to Evamist. The Women’s Health Initiative Studies In the WHI estrogen-alone substudy (daily CE [0.625 mg]-alone versus placebo), there was a higher relative risk of stroke in women greater than 65 years of age [see Clinical Studies ( 14.2 )] . In the WHI estrogen plus progestin substudy (daily CE [0.625 mg] plus MPA [2.5 mg] versus placebo), there was a higher relative risk of nonfatal stroke and invasive breast cancer in women greater than 65 years of age [see Clinical Studies ( 14.2 )] .
The Women’s Health Initiative Memory Study In the WHIMS ancillary studies of postmenopausal women 65 to 79 years of age, there was an increased risk of developing probable dementia in women receiving estrogen-alone or estrogen plus progestin when compared to placebo [see Warnings and Precautions ( 5.3 ), and Clinical Studies ( 14.3 )] . Since both ancillary studies were conducted in women 65 to 79 years of age, it is unknown whether these findings apply to younger postmenopausal women 8 [see Warnings and Precautions ( 5.3 ), and Clinical Studies ( 14.3 )].
🆘 Overdosage ▾
10 OVERDOSAGE Overdosage of estrogen may cause nausea and vomiting, breast tenderness, abdominal pain, drowsiness and fatigue, and withdrawal bleeding may occur in women. Treatment of overdose consists of discontinuation of Evamist therapy with institution of appropriate symptomatic care.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Endogenous estrogens are largely responsible for the development and maintenance of the female reproductive system and secondary sexual characteristics. Although circulating estrogens exist in a dynamic equilibrium of metabolic interconversions, estradiol is the principal intracellular human estrogen and is substantially more potent than its metabolites, estrone and estriol, at the receptor level. The primary source of estrogen in normally cycling adult women is the ovarian follicle, which secretes 70 to 500 mcg of estradiol daily, depending on the phase of the menstrual cycle.
After menopause, most endogenous estrogen is produced by conversion of androstenedione, secreted by the adrenal cortex, to estrone in the peripheral tissues. Thus, estrone and the sulfate conjugated form, estrone sulfate, are the most abundant circulating estrogens in postmenopausal women. Estrogens act through binding to nuclear receptors in estrogen-responsive tissues.
To date, two estrogen receptors have been identified. These vary in proportion from tissue to tissue. Circulating estrogens modulate the pituitary secretion of the gonadotropins, luteinizing hormone (LH) and FSH, through a negative feedback mechanism.
Estrogens act to reduce the elevated levels of these hormones seen in postmenopausal women.
12.2Pharmacodynamics Generally, a serum estrogen concentration does not predict an individual woman’s therapeutic response to Evamist nor her risk for adverse outcomes. Likewise, exposure comparisons across different estrogen products to infer efficacy or safety for the individual woman may not be valid.
12.3Pharmacokinetics Absorption In a multiple-dose study, 72 postmenopausal women were treated for 14 days with Evamist to the inner forearm. Serum concentrations of estradiol appeared to reach steady state after 7 to 8 days of application of one, two, or three 90 mcL sprays of Evamist per day (Figure 1). Figure 1.
Mean (±SD) Serum Estradiol Concentrations on Day 14 Following Topical Application for 14 Days of One, Two or Three Sprays of Evamist (Unadjusted for Baseline) Pharmacokinetics parameters for estradiol from one, two, or three 90 mcL sprays of Evamist, as assessed on Day 14 of this study, are described in Table 2. Table 2. Estradiol Pharmacokinetic Parameters on Day 14 (Unadjusted for Baseline) PK Parameter Number of Daily Sprays of Evamist 1 Spray (N = 24) 2 Sprays (N = 23) 3 Sprays (N = 24) C max (pg/mL) a C min (pg/mL) a C avg (pg/mL) a AUC 0-24 (pg*hr/mL) a T max (hours) b 36.4 (62) 11.3 (52) 19.6 (49) 471 (49) 20 (0-24) 57.4 (94) 18.1 (51) 30.7 (43) 736 (43) 18 (0-24) 54.1 (50) 19.6 (27) 30.9 (30) 742 (30) 20 (0-24) a Values expressed are arithmetic means (%CV) b Values expressed are medians (minimum-maximum) Distribution The distribution of exogenous estrogens is similar to that of endogenous estrogens.
Estrogens are widely distributed in the body and are generally found in higher concentrations in the sex hormone target organs. Estrogens circulate in blood largely bound to SHBG and albumin. Metabolism Exogenous estrogens are metabolized in the same manner as endogenous estrogens.
Circulating estrogens exist in a dynamic equilibrium of metabolic interconversions. These transformations take place mainly in the liver. Estradiol is converted reversibly to estrone, and both can be converted to estriol, which is a major urinary metabolite.
Estrogens also undergo enterohepatic recirculation via sulfate and glucuronide conjugation in the liver, biliary secretion of conjugates into the intestine, and hydrolysis in the intestine followed by reabsorption. In postmenopausal women, a significant proportion of the circulating estrogens exist as sulfate conjugates, especially estrone sulfate, which serves as a circulating reservoir for the formation of more active estrogens. Excretion Estradiol, estrone and estriol are excreted in the urine along with glucuronide and sulfate conjugates.
Potential…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Endogenous estrogens are largely responsible for the development and maintenance of the female reproductive system and secondary sexual characteristics. Although circulating estrogens exist in a dynamic equilibrium of metabolic interconversions, estradiol is the principal intracellular human estrogen and is substantially more potent than its metabolites, estrone and estriol, at the receptor level. The primary source of estrogen in normally cycling adult women is the ovarian follicle, which secretes 70 to 500 mcg of estradiol daily, depending on the phase of the menstrual cycle.
After menopause, most endogenous estrogen is produced by conversion of androstenedione, secreted by the adrenal cortex, to estrone in the peripheral tissues. Thus, estrone and the sulfate conjugated form, estrone sulfate, are the most abundant circulating estrogens in postmenopausal women. Estrogens act through binding to nuclear receptors in estrogen-responsive tissues.
To date, two estrogen receptors have been identified. These vary in proportion from tissue to tissue. Circulating estrogens modulate the pituitary secretion of the gonadotropins, luteinizing hormone (LH) and FSH, through a negative feedback mechanism.
Estrogens act to reduce the elevated levels of these hormones seen in postmenopausal women.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Evamist (NDC 0574-2067-27) is supplied as a homogeneous solution of estradiol USP, octisalate USP and alcohol USP. The liquid formulation of Evamist is packaged in a glass vial fitted with a metered-dose pump. The unit is encased in a plastic housing with a conical bell opening that controls the distance, angle, and area of application of the metered-dose spray.
Each metered-dose pump contains 8.1 mL and is designed to deliver 56 sprays of 90 mcL after priming. One spray contains 1.53 mg estradiol.
16.2Storage and Handling Keep out of reach of children. Alcohol and alcohol-based liquids are flammable. Avoid fire, flame or smoking until the spray has dried. Store at room temperature 20°C to 25°C (68°F to 77°F); excursion permitted between 15°C to 30°C (59°F to 86°F). Do not freeze.
📋 Description ▾
11 DESCRIPTION Evamist (estradiol transdermal spray) is designed to deliver estradiol to the blood circulation following topical application to the skin of a rapidly drying solution from a metered-dose pump. Evamist is a homogeneous solution of 1.7% estradiol USP (active ingredient) in alcohol USP and octisalate USP formulated to provide sustained release of the active ingredient into the systemic circulation. Estradiol USP is a white crystalline powder, chemically described as estra-1,3,5(10)-triene- 3,17β-diol.
It has an empirical formula of C 18 H 24 O 2 •1/2 H 2 O and molecular weight of 281.4. The structural formula is: Each metered-dose pump contains 8.1 mL and is designed to deliver 56 sprays of 90 mcL each after priming. One spray of Evamist contains 1.53 mg estradiol.
The metered-dose pump should be held upright and vertical for spraying. Before a new applicator is used for the first time, the pump should be primed by spraying 5 times with the cover on. One, two or three sprays are applied daily each morning to adjacent non-overlapping 20 cm 2 areas on the inner surface of the arm between the elbow and the wrist and allowed to dry.
Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise women to read the FDA-approved patient labeling (Patient Information and Instructions for Use). Vaginal Bleeding Inform postmenopausal women to report any vaginal bleeding to their healthcare provider as soon as possible [see Warnings and Precautions ( 5.2 )] . Unintentional Secondary Exposure to Evamist Provide the following information about secondary exposure to Evamist: • Apply Evamist as directed and keep children from contacting exposed application site(s).
If direct contact with the application site occurs, the contact area should be washed thoroughly with soap and water. Women should cover the Evamist application site, after the 2 minute drying period, with clothing if another person may come in contact with that area of skin. [See FDA-Approved Patient Information Leaflet at the end of the prescribing information.] • Look for signs of unexpected sexual development, such as breast mass or increased breast size in prepubertal children. • If signs of unintentional secondary exposure are noticed: o Have children evaluated by a healthcare provider. o Discontinue Evamist until the cause(s) is identified for any unexpected sexual development in children under their care. o Women should contact their healthcare provider and discuss the appropriate use and handling of Evamist when around children. o If conditions for safe use cannot be met, Evamist should be discontinued and alternative treatments for menopausal signs and symptoms should be considered. • Pets may also be unintentionally exposed to Evamist if above precautions are not followed.
Possible Serious Adverse Reactions with Estrogen-Alone Therapy Inform postmenopausal women of the possible serious adverse reactions of estrogen-alone therapy including Cardiovascular Disorders, Malignant Neoplasms, and Probable Dementia [see Warnings and Precautions ( 5.1 , 5.2 , 5.3 )] . Possible Common Adverse Reactions with Estrogen-Alone Therapy Inform postmenopausal women of possible less serious but common adverse reactions of estrogen-alone therapy such as headache, breast pain and tenderness, nausea and vomiting.
Manufactured by Padagis ® Yeruham, Israel www.padagis.com Rev 10-2024 9E400 RC PH3