
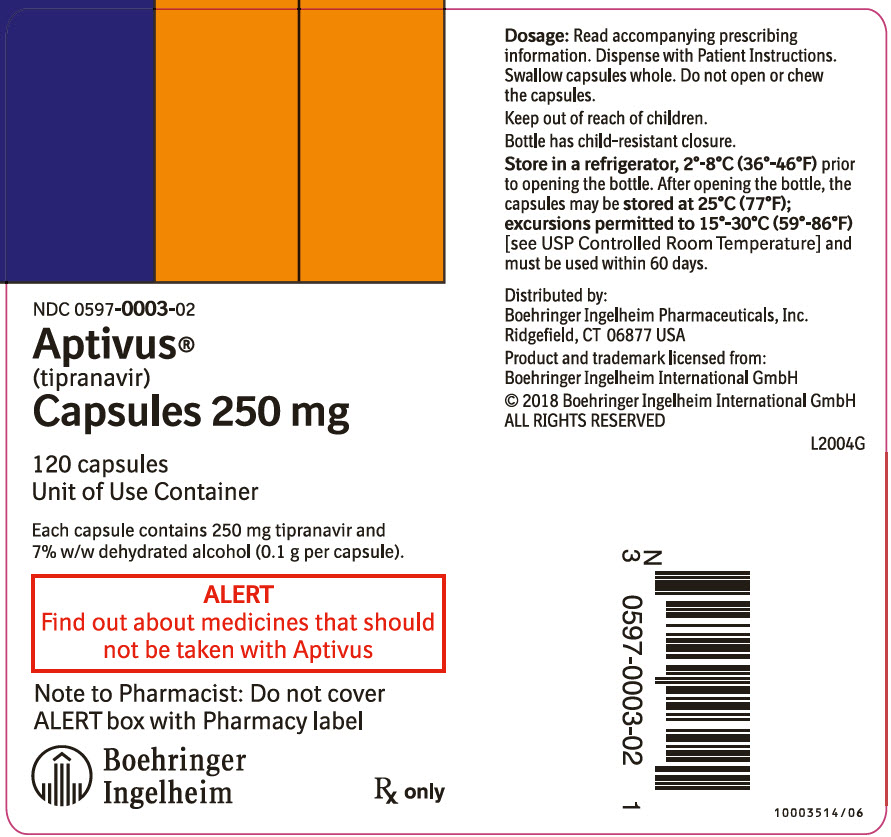
Aptivus tipranavir 250 mg Capsule, Liquid Filled, 120-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Protease Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Tipranavir is used to treat human immunodeficiency virus infection (HIV). Tipranavir is in a class of medications called protease inhibitors. It works by decreasing the amount of HIV in the blood. Although tipranavir does not cure HIV, it may decrease your chance of developing acquired immunodeficiency syndrome (AIDS) and HIV-related illnesses. Taking these medications and making other lifestyle changes may decrease the risk of giving the HIV virus to other people.
Read the full MedlinePlus article ↗- No — tipranavir on its own is broken down so fast by the liver that it never reaches the blood levels needed to fight HIV. Ritonavir acts as a booster: it slows down that breakdown...
- Why do I have to take this medication with ritonavir? Can't I just take tipranavir alone?
- It depends on which form of ritonavir you're using. If your ritonavir comes as tablets, then yes — you must take Aptivus with a meal every time. If you're using ritonavir capsules,...
- Do I need to eat when I take Aptivus capsules?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with tipranavir — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $16.457 | $1,974.82 / 120 capsules |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $17.82 | $2,138.82 / 120 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Aptivus 250 mgthis 00597-0003-02 | Boehringer | 120 capsules | $16.457 | — | Discontinued | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00597-0003-02 You're viewing this | 120 CAPSULE, LIQUID FILLED in 1 BOTTLE, PLASTIC (0597-0003-02) | 2005-07-01 | Inactivated by FDA |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
What does the discontinued status mean for this NDC?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: HEPATOTOXICITY and INTRACRANIAL HEMORRHAGE WARNING: HEPATOTOXICITY and INTRACRANIAL HEMORRHAGE See full prescribing information for complete boxed warning. Clinical hepatitis and hepatic decompensation including some fatalities. Extra vigilance is warranted in patients with chronic hepatitis B or hepatitis C co-infection.
( 5.2 ) Fatal and non-fatal intracranial hemorrhage ( 5.3 ) Hepatotoxicity: Clinical hepatitis and hepatic decompensation, including some fatalities, have been reported. Extra vigilance is warranted in patients with chronic hepatitis B or hepatitis C co-infection, as these patients have an increased risk of hepatotoxicity [ see Warnings and Precautions (5.2) ] . Intracranial Hemorrhage: Both fatal and non-fatal intracranial hemorrhage have been reported [ see Warnings and Precautions (5.3) ] .
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE APTIVUS, co-administered with ritonavir, is indicated for combination antiretroviral treatment of HIV-1 infected adults and pediatric patients weighing 36 kg or higher who are treatment-experienced and infected with HIV-1 strains resistant to more than one protease inhibitor (PI) [see Use in Specific Populations (8.4) ] . This indication is based on analyses of plasma HIV-1 RNA levels in two controlled studies of APTIVUS/ritonavir of 48 weeks duration in treatment-experienced adults and one open-label 48-week study in pediatric patients.
The adult studies were conducted in clinically advanced, 3-class antiretroviral (NRTI, NNRTI, PI) treatment-experienced adults with evidence of HIV-1 replication despite ongoing antiretroviral therapy. The following points should be considered when initiating therapy with APTIVUS/ritonavir: The use of APTIVUS/ritonavir in treatment-naïve patients is not recommended [ see Warnings and Precautions (5.2) ]. The use of other active agents with APTIVUS/ritonavir is associated with a greater likelihood of treatment response [ see Microbiology (12.4) and Clinical Studies (14) ].
Genotypic or phenotypic testing and/or treatment history should guide the use of APTIVUS/ritonavir [ see Microbiology (12.4) ]. The number of baseline primary protease inhibitor mutations affects the virologic response to APTIVUS/ritonavir [ see Microbiology (12.4) ]. Use caution when prescribing APTIVUS/ritonavir to patients with elevated transaminases, hepatitis B or C co-infection or patients with mild hepatic impairment [ see Warnings and Precautions (5.2) ].
Liver function tests should be performed at initiation of therapy with APTIVUS/ritonavir and monitored frequently throughout the duration of treatment [ see Warnings and Precautions (5.2) ]. The drug-drug interaction potential of APTIVUS/ritonavir when co-administered with other drugs must be considered prior to and during APTIVUS/ritonavir use [ see Contraindications (4) and Drug Interactions (7) ]. Use caution when prescribing APTIVUS/ritonavir in patients who may be at risk for increased bleeding or who are receiving medications known to increase the risk of bleeding [ see Warnings and Precautions (5.5) ].
There are no study results demonstrating the effect of APTIVUS/ritonavir on clinical progression of HIV-1. APTIVUS, a protease inhibitor, co-administered with ritonavir, is indicated for combination antiretroviral treatment of HIV-1 infected adult and pediatric patients weighing 36 kg or higher who are treatment-experienced and infected with HIV-1 strains resistant to more than one protease inhibitor ( 1 ) Do not use APTIVUS/ritonavir in treatment-naïve patients ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Adults: 500 mg APTIVUS, co-administered with 200 mg ritonavir, twice daily ( 2.2 ) Pediatric patients (weighing 36 kg or higher): 500 mg APTIVUS, co-administered with 200 mg ritonavir twice daily. ( 2.2 ) APTIVUS taken with ritonavir tablets must be taken with meals ( 2.1 ) APTIVUS capsules must be swallowed whole and must not be opened or chewed ( 2.1 ) Children should be assessed for their ability to swallow capsules before prescribing APTIVUS capsules. ( 2.1 ) Store unopened bottles of APTIVUS capsules in the refrigerator.
( 16 )
2.1Dosage and Administration Overview APTIVUS must be co-administered with ritonavir to exert its therapeutic effect. Failure to correctly co-administer APTIVUS with ritonavir will result in plasma levels of tipranavir that will be insufficient to achieve the desired antiviral effect and will alter some drug interactions [see Warnings and Precautions (5.1) ] . Children should be assessed for their ability to swallow capsules before prescribing APTIVUS capsules [see Use in Specific Populations (8.4) ] .
APTIVUS co-administered with ritonavir tablets must only be taken with meals [see Clinical Pharmacology (12.3) ] . APTIVUS is supplied as capsules. APTIVUS capsules must be swallowed whole and must not be opened or chewed.
Due to the need for co-administration of APTIVUS with ritonavir, please refer to the ritonavir prescribing information.
2.2Recommended Dosage in Adults and Pediatric Patients Weighing 36 kg or Higher The recommended dosage in adults and pediatric patients weighing 36 kg or higher is 500 mg (two 250 mg capsules) of APTIVUS co-administered with 200 mg of ritonavir, twice daily.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Capsules: 250 mg, pink, oblong capsules imprinted with "TPV 250" Capsules: 250 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS APTIVUS is contraindicated in patients with moderate or severe (Child-Pugh Class B or C, respectively) hepatic impairment [ see Warnings and Precautions (5.2) ]. APTIVUS/ritonavir is contraindicated when co-administered with drugs that are highly dependent on CYP3A for clearance or are potent CYP3A inducers (see Table 1 ) [ see Drug Interactions (7.2) ]. Table 1 Drugs that are Contraindicated with APTIVUS Co-Administered with Ritonavir Drug Class Drugs within Class that are Contraindicated with APTIVUS Co-administered with Ritonavir Clinical Comments: Alpha 1-adrenoreceptor antagonist Alfuzosin Potentially increased alfuzosin concentrations can result in hypotension.
Antiarrhythmics Amiodarone, bepridil, flecainide, propafenone, quinidine Potential for serious and/or life-threatening reactions such as cardiac arrhythmias secondary to increases in plasma concentrations of antiarrhythmics. Antimycobacterials Rifampin May lead to loss of virologic response and possible resistance to APTIVUS or to the class of protease inhibitors or other co-administered antiretroviral agents. Ergot derivatives Dihydroergotamine, ergonovine, ergotamine, methylergonovine Potential for acute ergot toxicity characterized by peripheral vasospasm and ischemia of the extremities and other tissues.
GI motility agent Cisapride Potential for cardiac arrhythmias. Herbal products St. John's wort (hypericum perforatum) May lead to loss of virologic response and possible resistance to APTIVUS or to the class of protease inhibitors.
HMG CoA reductase inhibitors Lovastatin, simvastatin Potential for myopathy including rhabdomyolysis. Antipsychotics Pimozide Potential for cardiac arrhythmias. Lurasidone Potential for serious and/or life-threatening reactions.
PDE-5 inhibitors Sildenafil (Revatio) [for treatment of pulmonary arterial hypertension] A safe and effective dose has not been established when used with APTIVUS/ritonavir. There is increased potential for sildenafil-associated adverse events (which include visual disturbances, hypotension, prolonged erection, and syncope). Sedatives/hypnotics Oral midazolam, triazolam Prolonged or increased sedation or respiratory depression.
Due to the need for co-administration of APTIVUS with ritonavir, please refer to the ritonavir prescribing information for a description of ritonavir contraindications. Patients with moderate or severe (Child-Pugh Class B or C) hepatic impairment ( 4 , 5.2 ) Use with drugs highly dependent on CYP3A for clearance or are potent CYP3A inducers ( 4 , 5.4 , 7 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Co-administration with Ritonavir: APTIVUS must be co-administered with ritonavir and food to achieve the desired antiviral effect. Failure to administer APTIVUS with ritonavir and food may result in a loss of efficacy of tipranavir. ( 5.1 ) Hepatic Impairment: Discontinue for signs and symptoms of clinical hepatitis or asymptomatic increases in ALT/AST >10 times ULN or asymptomatic increases in ALT/AST 5-10 times ULN with concomitant increases in total bilirubin.
Monitor liver function tests prior to therapy and frequently thereafter. ( 5.2 ) Intracranial Hemorrhage/Platelet Aggregation and Coagulation: Use with caution in patients at risk for increased bleeding or who are receiving medications that increase the risk of bleeding. ( 5.3 , 5.5 ) The concomitant use of APTIVUS/ritonavir and certain other drugs may result in known or potentially significant drug interactions.
Consult the full prescribing information prior to and during treatment for potential drug interactions. ( 5.4 , 7.2 ) Rash: Discontinue and initiate appropriate treatment if severe skin reaction occurs or is suspected. ( 5.6 ) Use with caution in patients with a known sulfonamide allergy.
( 5.7 ) Patients may develop new onset or exacerbations of diabetes mellitus, hyperglycemia ( 5.8 ), immune reconstitution syndrome ( 5.9 ), redistribution/accumulation of body fat ( 5.10 ), and elevated lipids. ( 5.11 ) Monitor cholesterol and triglycerides prior to therapy and periodically thereafter. Hemophilia: Spontaneous bleeding may occur, and additional factor VIII may be required.
( 5.12 )
5.1Importance of Co-administration with Ritonavir APTIVUS must be co-administered with ritonavir and food to achieve the desired antiviral effect. Failure to administer APTIVUS with ritonavir and food may result in a loss of efficacy of tipranavir. Please refer to the ritonavir prescribing information for additional information on precautionary measures.
5.2Hepatic Impairment and Toxicity Clinical hepatitis and hepatic decompensation, including some fatalities, were reported with APTIVUS co-administered with 200 mg of ritonavir. These have generally occurred in subjects with advanced HIV-1 disease taking multiple concomitant medications. A causal relationship to APTIVUS/ritonavir could not be established.
Physicians and patients should be vigilant for the appearance of signs or symptoms of hepatitis, such as fatigue, malaise, anorexia, nausea, jaundice, bilirubinuria, acholic stools, liver tenderness or hepatomegaly. Patients with signs or symptoms of clinical hepatitis should discontinue APTIVUS/ritonavir treatment and seek medical evaluation. All patients should be followed closely with clinical and laboratory monitoring, especially those with chronic hepatitis B or C co-infection, as these patients have an increased risk of hepatotoxicity.
Liver function tests should be performed prior to initiating therapy with APTIVUS/ritonavir, and frequently throughout the duration of treatment. If asymptomatic elevations in AST or ALT greater than 10 times the upper limit of normal occur, APTIVUS/ritonavir therapy should be discontinued. If asymptomatic elevations in AST or ALT between 5 – 10 times the upper limit of normal and increases in total bilirubin greater than 2.5 times the upper limit of normal occur, APTIVUS/ritonavir therapy should be discontinued.
Treatment-experienced patients with chronic hepatitis B or hepatitis C co-infection or elevated transaminases are at approximately 2-fold risk for developing Grade 3 or 4 transaminase elevations or hepatic decompensation. In two large, randomized, open-label, controlled clinical trials with an active comparator (1182.12 and 1182.48) of treatment-experienced subjects, Grade 3 and 4 increases in hepatic transaminases were observed in 10.3% (10.9/100 PEY) receiving APTIVUS/ritonavir through week 48. In a study of treatment-naïve subjects, 20.3% (21/100 PEY) experienced Grade 3 or 4 hepatic transaminase eleva…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are described, in greater detail, in other sections: Hepatic Impairment and Toxicity [ see Warnings and Precautions (5.2) ] Intracranial Hemorrhage [ see Warnings and Precautions (5.3) ] Rash [ see Warnings and Precautions (5.6) ] Due to the need for co-administration of APTIVUS with ritonavir, please refer to ritonavir prescribing information for ritonavir-associated adverse reactions. Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice.
In adults the most frequent adverse reactions (incidence >4%) were diarrhea, nausea, pyrexia, vomiting, fatigue, headache, and abdominal pain. ( 6.1 ) In pediatric subjects the most frequent adverse reactions were generally similar to those seen in adults. However, rash was more frequent in pediatric subjects than in adults.
( 6.2 ) To report SUSPECTED ADVERSE REACTIONS, contact Boehringer Ingelheim Pharmaceuticals, Inc. at 1-800-542-6257 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials in Adults APTIVUS, co-administered with ritonavir, has been studied in a total of 6308 HIV-1 positive adults as combination therapy in clinical studies. Of these, 1299 treatment-experienced subjects received the dose of 500 mg/200 mg BID. Nine hundred nine (909) adults, including 541 in the 1182.12 and 1182.48 controlled clinical trials, have been treated for at least 48 weeks [ see Clinical Studies (14) ].
In 1182.12 and 1182.48 in the APTIVUS/ritonavir arm, the most frequent adverse reactions were diarrhea, nausea, pyrexia, vomiting, fatigue, headache, and abdominal pain. The 48-Week Kaplan-Meier rates of adverse reactions leading to discontinuation were 13.3% for APTIVUS/ritonavir-treated subjects and 10.8% for the comparator arm subjects. Adverse reactions reported in the controlled clinical trials 1182.12 and 1182.48, based on treatment-emergent clinical adverse reactions of moderate to severe intensity (Grades 2 - 4) in at least 2% of treatment-experienced subjects in either treatment group are summarized in Table 2 below.
Table 2 Adverse Reactions Reported in Randomized, Controlled Clinical Trials (1182.12 and 1182.48) Based on Treatment-Emergent Clinical Adverse Reactions of Moderate to Severe Intensity (Grades 2 - 4) in at least 2% of Treatment-Experienced Subjects in either Treatment Group a (48-week Analyses) Percentage of patients (rate per 100 patient-exposure years) APTIVUS/ritonavir (500/200 mg BID) + OBR c (n=749; 757.4 patient-exposure years) Comparator PI/ritonavir b + OBR (n=737; 503.9 patient-exposure years) a Excludes laboratory abnormalities that were Adverse Events b Comparator PI/ritonavir: lopinavir/ritonavir 400/100 mg BID, indinavir/ritonavir 800/100 mg BID, saquinavir/ritonavir 1000/100 mg BID, amprenavir/ritonavir 600/100 mg BID c Optimized Background Regimen Blood and Lymphatic Disorders Anemia 3.3% (3.4) 2.3% (3.4) Neutropenia 2.0% (2.0) 1.0% (1.4) Gastrointestinal Disorders Diarrhea 15.0% (16.5) 13.4% (21.6) Nausea 8.5% (9.0) 6.4% (9.7) Vomiting 5.9% (6.0) 4.1% (6.1) Abdominal pain 4.4% (4.5) 3.4% (5.1) Abdominal pain upper 1.5% (1.5) 2.3% (3.4) General Disorders Pyrexia 7.5% (7.7) 5.4% (8.2) Fatigue 5.7% (5.9) 5.6% (8.4) Investigations Weight decreased 3.1% (3.1) 2.2% (3.2) ALT increased 2.0% (2.0) 0.5% (0.8) GGT increased 2.0% (2.0) 0.4% (0.6) Metabolism and Nutrition Disorders Hypertriglyceridemia 3.9% (4.0) 2.0% (3.0) Hyperlipidemia 2.5% (2.6) 0.8% (1.2) Dehydration 2.1% (2.1) 1.1% (1.6) Musculoskeletal and Connective Tissue Disorders Myalgia 2.3% (2.3) 1.8% (2.6) Nervous System Disorders Headache 5.2% (5.3) 4.2% (6.3) Peripheral neuropathy 1.5% (1.5) 2.0% (3.0) Psychiatric Disorders Insomnia 1.7% (1.7) 3.7% (5.5) Respiratory, Thoracic and Mediastinal Disorders Dyspnea 2.1% (2.1) 1.0% (…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Co-administration of APTIVUS can alter the concentrations of other drugs and other drugs may alter the concentration of tipranavir. The potential for drug-drug interactions must be considered prior to and during therapy. ( 4 , 5.4 , 7 )
7.1Potential for APTIVUS/ritonavir to Affect Other Drugs APTIVUS co-administered with ritonavir at the recommended dose is a net inhibitor of CYP3A and may increase plasma concentrations of agents that are primarily metabolized by CYP3A. Thus, co-administration of APTIVUS/ritonavir with drugs highly dependent on CYP3A for clearance and for which elevated plasma concentrations are associated with serious and/or life-threatening events is contraindicated [see Contraindications (4) ] . Co-administration with other CYP3A substrates may require a dose adjustment or additional monitoring [see Drug Interactions (7) ] .
Clinically significant drug-drug interactions of APTIVUS co-administered with ritonavir are summarized in Table 4 below. A phenotypic cocktail study was conducted with 16 healthy volunteers to quantify the influence of 10 days of APTIVUS/ritonavir capsule administration on the activity of hepatic CYP1A2 (caffeine), 2C9 (warfarin), 2C19 (omeprazole), 2D6 (dextromethorphan) and the activity of intestinal and hepatic CYP3A4/5 (midazolam) and P-glycoprotein (P-gp) (digoxin). This study determined the first-dose and steady-state effects of 500 mg of APTIVUS co-administered with 200 mg of ritonavir twice daily in capsule form.
There was no net effect on CYP2C9 or hepatic P-gp at first dose or steady state. There was no net effect after first dose on CYP1A2, but there was moderate induction at steady state. There was modest inhibition of CYP2C19 at the first dose, but there was marked induction at steady state.
Potent inhibition of CYP2D6 and both hepatic and intestinal CYP3A4/5 activities were observed after first dose and steady state. Intestinal and hepatic P-gp activity was assessed by administering oral and intravenous digoxin, respectively. The digoxin results indicate P-gp was inhibited after the first dose of APTIVUS/ritonavir followed by induction of P-gp over time.
Thus, it is difficult to predict the net effect of APTIVUS administered with ritonavir on oral bioavailability and plasma concentrations of drugs that are dual substrates of CYP3A and P-gp. The net effect will vary depending on the relative affinity of the co-administered drugs for CYP3A and P-gp, and the extent of intestinal first-pass metabolism/efflux. An in vitro induction study in human hepatocytes showed an increase in UGT1A1 by tipranavir similar to that evoked by rifampin.
The clinical consequences of this finding have not been established.
7.2Potential for Other Drugs to Affect Tipranavir Tipranavir is a CYP3A substrate and a P-gp substrate. Co-administration of APTIVUS/ritonavir and drugs that induce CYP3A and/or P-gp may decrease tipranavir plasma concentrations. Co-administration of APTIVUS/ritonavir and drugs that inhibit P-gp may increase tipranavir plasma concentrations.
Co-administration of APTIVUS/ritonavir with drugs that inhibit CYP3A may not further increase tipranavir plasma concentrations, because the level of metabolites is low following steady-state administration of APTIVUS/ritonavir 500 mg/200 mg twice daily. Clinically significant drug-drug interactions of APTIVUS co-administered with ritonavir are summarized in Table 4 below [see Contraindications (4) , Warnings and Precautions (5.4) , and Clinical Pharmacology (12.3) ] . Table 4 Established and Other Potentially Significant Drug Interactions: Alterations in Dose or Regimen May be Recommended Based on Drug Interaction Studies or Predicted Interaction Concomitant Drug Class: Drug name Effect on Concentration of Tipranavir or Concomitant Drug Clinical Comment ↑ increase, ↓ decrease, ↔ no change, ↕ unable to predict HIV-1 Antiviral Agents Fusion Inhibitors: Enfuvirtide ↑ Tipranavir At steady state, tipranavir trough concentrat…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to APTIVUS during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Prospective pregnancy data from the APR and an Expanded Access program are not sufficient to adequately assess the risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes.
Tipranavir use during pregnancy has been evaluated in a limited number of women as reported by the APR and an Expanded Access program, and available data show no birth defects in 13 first trimester exposures (see Data ) compared with the background rate for major birth defects of 2.7% in the US reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP). The rate of miscarriage is not reported in the APR. The estimated background rate of miscarriage in clinically recognized pregnancies in the U.S. general population is 15-20%.
The background risk of birth defects and miscarriage for the indicated population is unknown. Methodological limitations of the APR include the use of MACDP as the external comparator group. The MACDP population is not disease-specific, evaluates women and infants from a limited geographic area, and does not include outcomes for births that occurred at <20 weeks gestation.
In animal reproduction studies, fetal toxicities were observed with tipranavir at maternally toxic doses with systemic exposures (AUC) less than those in humans at the recommended human dose (RHD) (see Data ) . Data Human Data Based on prospective reports to the APR and an Expanded Access program for approximately 17 live births following exposure to tipranavir-containing regimens (including 13 live births exposed in the first trimester and 4 live births exposed in the second/third trimester), there were no birth defects reported in live-born infants.
Tipranavir has been shown to cross the placenta. Animal Data Tipranavir was administered orally to pregnant rats (at 0, 40, 400, or 1000 mg/kg/day from gestation day 6 to 17) and rabbits (at 0, 75, 150, or 375 mg/kg/day from gestation day 6 to 20). In rats, fetal toxicities including decreased body weight and sternebrae ossification occurred at maternally toxic doses (≥400 mg/kg/day) (approximately 0.8 times human exposure at the RHD).
In rabbits, fetal toxicities including decreased fetal body weights, wavy ribs, and bent femurs occurred at a maternally toxic dose (375 mg/kg/day) (approximately 0.05 times human exposure at the RHD). Maternal toxicity included an increased incidence of abortions at doses ≥150 mg/kg/day (approximately 0.05 times human exposure at the RHD). In the pre/post-natal development study, tipranavir was administered orally to rats at 0, 40, 400, 1000 mg/kg/day from gestation day 6 to lactation day 21.
The only significant effect observed was growth inhibition of the offspring at maternally toxic doses (≥400 mg/kg/day) (approximately 0.8 times human exposure at the RHD).
8.2Lactation Risk Summary There is no information regarding the presence of tipranavir in human milk, the effects on the breastfed infant, or the effects on milk production. Tipranavir is present in rat milk (see Data ) . Potential risks of breastfeeding include: (1) HIV-1 transmission (in HIV-1 negative infants), (2) developing viral resistance (in HIV-1-positive patients), and (3) adverse reactions in a breastfed infant similar to those seen in adults.
Data In a lactation study, tipranavir was excreted into the milk of lactating rats following a single oral dose of tipranavir (10 mg/kg) on lactation/postpartum day 14, with a maximal milk concentration achieved 2 hours post-administration (milk concentration 0.13 times that of maternal plasma concentration).
8.3Females and Males of Reproductive Potential Contraception Use of APTIVUS may reduce the effic…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to APTIVUS during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Prospective pregnancy data from the APR and an Expanded Access program are not sufficient to adequately assess the risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes.
Tipranavir use during pregnancy has been evaluated in a limited number of women as reported by the APR and an Expanded Access program, and available data show no birth defects in 13 first trimester exposures (see Data ) compared with the background rate for major birth defects of 2.7% in the US reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP). The rate of miscarriage is not reported in the APR. The estimated background rate of miscarriage in clinically recognized pregnancies in the U.S. general population is 15-20%.
The background risk of birth defects and miscarriage for the indicated population is unknown. Methodological limitations of the APR include the use of MACDP as the external comparator group. The MACDP population is not disease-specific, evaluates women and infants from a limited geographic area, and does not include outcomes for births that occurred at <20 weeks gestation.
In animal reproduction studies, fetal toxicities were observed with tipranavir at maternally toxic doses with systemic exposures (AUC) less than those in humans at the recommended human dose (RHD) (see Data ) . Data Human Data Based on prospective reports to the APR and an Expanded Access program for approximately 17 live births following exposure to tipranavir-containing regimens (including 13 live births exposed in the first trimester and 4 live births exposed in the second/third trimester), there were no birth defects reported in live-born infants.
Tipranavir has been shown to cross the placenta. Animal Data Tipranavir was administered orally to pregnant rats (at 0, 40, 400, or 1000 mg/kg/day from gestation day 6 to 17) and rabbits (at 0, 75, 150, or 375 mg/kg/day from gestation day 6 to 20). In rats, fetal toxicities including decreased body weight and sternebrae ossification occurred at maternally toxic doses (≥400 mg/kg/day) (approximately 0.8 times human exposure at the RHD).
In rabbits, fetal toxicities including decreased fetal body weights, wavy ribs, and bent femurs occurred at a maternally toxic dose (375 mg/kg/day) (approximately 0.05 times human exposure at the RHD). Maternal toxicity included an increased incidence of abortions at doses ≥150 mg/kg/day (approximately 0.05 times human exposure at the RHD). In the pre/post-natal development study, tipranavir was administered orally to rats at 0, 40, 400, 1000 mg/kg/day from gestation day 6 to lactation day 21.
The only significant effect observed was growth inhibition of the offspring at maternally toxic doses (≥400 mg/kg/day) (approximately 0.8 times human exposure at the RHD).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of APTIVUS, co-administered with ritonavir have been established in pediatric patients for combination antiretroviral treatment of HIV-1 infected pediatric patients weighing 36 kg or higher who are treatment-experienced and infected with HIV-1 strains resistant to more than one protease inhibitor (PI) [see Indications and Usage (1) and Dosage and Administration (2.2) ] . The safety, pharmacokinetic profile, and virologic and immunologic responses of APTIVUS in those weighing 36 kg or higher were similar to those observed in adults.
However, rash was reported more frequently in pediatric subjects than in adults [ see Warnings and Precautions (5.6) , Adverse Reactions (6.2) , Clinical Pharmacology (12.3) , and Clinical Studies (14.2) ]. The safety and effectiveness of APTIVUS, co-administered with ritonavir have been established in pediatric patients greater than 2 years of age or weighing less than 36 kg, but not recommended due to lack of a suitable pediatric formulation.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of APTIVUS/ritonavir did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently than younger subjects. In general, caution should be exercised in the administration and monitoring of APTIVUS in elderly patients reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE There is no known antidote for APTIVUS overdose. Treatment of overdose should consist of general supportive measures, including monitoring of vital signs and observation of the patient's clinical status. If indicated, elimination of unabsorbed tipranavir should be achieved by emesis or gastric lavage.
Administration of activated charcoal may also be used to aid in removal of unabsorbed drug. Since tipranavir is highly protein bound, dialysis is unlikely to provide significant removal of the drug.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Tipranavir is an antiretroviral drug [ see Microbiology (12.4) ].
12.2Pharmacodynamics ECG Evaluation The effect of APTIVUS/ritonavir on the QTcF interval was measured in a study in which 81 healthy subjects received the following treatments twice daily for 2.5 days: APTIVUS/ritonavir (500 mg/200 mg), APTIVUS/ritonavir at a supra-therapeutic dose (750 mg/200 mg), and placebo/ritonavir (-/200 mg). After baseline and placebo adjustment, the maximum mean QTcF change was 3.2 ms (1-sided 95% Upper CI: 5.6 ms) for the 500 mg/200 mg dose and 8.3 ms (1-sided 95% Upper CI: 10.9 ms) for the supra-therapeutic 750 mg/200 mg dose.
Antiviral Activity in vivo The median Inhibitory Quotient (IQ) determined from 264 treatment-experienced adult subjects was about 80 (inter-quartile range: 31-226), from the controlled clinical trials 1182.12 and 1182.48. The IQ is defined as the tipranavir trough concentration divided by the viral EC 50 value, corrected for protein binding. There was a relationship between the proportion of subjects with a ≥1 log 10 reduction of viral load from baseline at week 48 and their IQ value.
Among the 198 subjects receiving APTIVUS/ritonavir with no new enfuvirtide use (e.g., new enfuvirtide, defined as initiation of enfuvirtide for the first time), the response rate was 23% in those with an IQ value <80 and 59% in those with an IQ value ≥80. Among the 66 subjects receiving APTIVUS/ritonavir with new enfuvirtide, the response rates in subjects with an IQ value <80 versus those with an IQ value ≥80 were 55% and 71%, respectively. These IQ groups are derived from a select population and are not meant to represent clinical breakpoints.
12.3Pharmacokinetics In order to achieve effective tipranavir plasma concentrations and a twice-daily dosing regimen, co-administration of APTIVUS with ritonavir is essential [ see Dosage and Administration (2) ]. Ritonavir inhibits hepatic cytochrome P450 3A (CYP3A), the intestinal P-gp efflux pump and possibly intestinal CYP3A. In a dose-ranging evaluation in 113 HIV-1 negative male and female volunteers, there was a 29-fold increase in the geometric mean morning steady-state trough plasma concentrations of tipranavir following APTIVUS co-administered with low-dose ritonavir (500 mg/200 mg twice daily) compared to APTIVUS 500 mg twice daily without ritonavir.
In adults the mean systemic ritonavir concentration when 200 mg of ritonavir was given with 500 mg of APTIVUS was similar to the concentrations observed when 100 mg was given with the other protease inhibitors. Figure 1 displays mean plasma concentrations of tipranavir and ritonavir at steady state for 30 HIV-1 infected adult subjects dosed with 500 mg/200 mg tipranavir/ritonavir for 14 days. Figure 1 Mean Steady State Tipranavir Plasma Concentrations (95% CI) with Ritonavir Co-administration (tipranavir/ritonavir 500 mg/200 mg BID) Figure 1 Absorption and Bioavailability Absorption of tipranavir in humans is limited, although no absolute quantification of absorption is available.
Tipranavir is a P-gp substrate, a weak P-gp inhibitor, and appears to be a potent P-gp inducer as well. In vivo data suggest that tipranavir/ritonavir, at the dose of 500 mg/200 mg, is a P-gp inhibitor after the first dose and induction of P-gp occurs over time. Tipranavir trough concentrations at steady-state are about 70% lower than those on Day 1, presumably due to intestinal P-gp induction.
Steady state is attained in most subjects after 7-10 days of dosing. Dosing APTIVUS 500 mg with 200 mg ritonavir capsules twice daily for greater than 2 weeks and without meal restriction produced the pharmacokinetic parameters for male and female HIV-1 positive subjects presented in Table 5. Table 5 Pharmacokinetic Parameters a of tipranavir/ritonavir 500 mg/200 mg for HIV-1 Positive Subjects by Gender Parameter Females (n=14) Males (n=106) a Population pharmacokinetic parameters reported as mean ± standard deviatio…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Tipranavir is an antiretroviral drug [ see Microbiology (12.4) ].
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING APTIVUS capsules 250 mg are pink, oblong soft gelatin capsules imprinted in black with "TPV 250". They are packaged in HDPE unit-of-use bottles with a child resistant closure and 120 capsules. (NDC 0597-0003-02).
Storage APTIVUS capsules should be stored in a refrigerator 2°C-8°C (36°F-46°F) prior to opening the bottle. After opening the bottle, the capsules may be stored at 20°C-25°C (68°F-77°F); excursions permitted to 15°C-30°C (59°F-86°F ) [see USP Controlled Room Temperature] and must be used within 60 days after first opening of the bottle. Store in a safe place out of the reach of children.
📦 Storage and Handling ▾
Storage APTIVUS capsules should be stored in a refrigerator 2°C-8°C (36°F-46°F) prior to opening the bottle. After opening the bottle, the capsules may be stored at 20°C-25°C (68°F-77°F); excursions permitted to 15°C-30°C (59°F-86°F ) [see USP Controlled Room Temperature] and must be used within 60 days after first opening of the bottle. Store in a safe place out of the reach of children.
📋 Description ▾
11 DESCRIPTION APTIVUS is a protease inhibitor of HIV-1 belonging to the class of 4-hydroxy-5,6-dihydro-2-pyrone sulfonamides. The chemical name of tipranavir is 2-Pyridinesulfonamide, N-[3-[(1R)-1-[(6R)-5,6-dihydro-4-hydroxy-2-oxo-6-(2-phenylethyl)-6-propyl-2H-pyran-3-yl]propyl]phenyl]-5-(trifluoromethyl). It has a molecular formula of C 31 H 33 F 3 N 2 O 5 S and a molecular weight of 602.7.
Tipranavir has the following structural formula and is a single stereoisomer with the 1R, 6R configuration. Tipranavir is a white to off-white to slightly yellow solid. It is freely soluble in dehydrated alcohol and propylene glycol, and insoluble in aqueous buffer at pH 7.5.
APTIVUS soft gelatin capsules are for oral administration. Each capsule contains 250 mg tipranavir. The major inactive ingredients in the capsule are dehydrated alcohol (7% w/w or 0.1 g per capsule), polyoxyl 35 castor oil, propylene glycol, mono/diglycerides of caprylic/capric acid and gelatin.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Hepatic Impairment and Toxicity Inform patients that APTIVUS co-administered with 200 mg of ritonavir, has been associated with severe liver disease, including some deaths. Patients with signs or symptoms of clinical hepatitis should discontinue APTIVUS/ritonavir treatment and seek medical evaluation.
Symptoms of hepatitis include fatigue, malaise, anorexia, nausea, jaundice, bilirubinuria, acholic stools, liver tenderness or hepatomegaly. Extra vigilance is needed for patients with chronic hepatitis B or C co-infection, as these patients have an increased risk of developing hepatotoxicity. Liver function tests should be performed prior to initiating therapy with APTIVUS and 200 mg of ritonavir, and frequently throughout the duration of treatment.
Patients with chronic hepatitis B or C co-infection or elevations in liver enzymes prior to treatment are at increased risk (approximately 2-fold) for developing further liver enzyme elevations or severe liver disease. Caution should be exercised when administering APTIVUS/ritonavir to patients with liver enzyme abnormalities or history of chronic liver disease. Increased liver function testing is warranted in these patients.
APTIVUS should not be given to patients with moderate to severe hepatic impairment. Intracranial Hemorrhage Inform patients that APTIVUS co-administered with 200 mg of ritonavir has been associated with reports of both fatal and non-fatal intracranial hemorrhage. Patients should report any unusual or unexplained bleeding to their physician.
Drug Interactions APTIVUS may interact with some drugs; therefore, advise patients to report to their healthcare provider the use of any other prescription or non-prescription medications or herbal products, particularly St. John's wort. Rash Rash, including flat or raised rashes or sensitivity to the sun, have been reported in approximately 10% of subjects receiving APTIVUS.
Some patients who developed rash also had one or more of the following symptoms: joint pain or stiffness, throat tightness, generalized itching, muscle aches, fever, redness, blisters, or peeling of the skin. Women taking birth control pills may get a skin rash. Tell patients to discontinue use of APTIVUS and call their physician right away if any of these symptoms develop.
Sulfa Allergy Tell patients to report any history of sulfonamide allergy to the physician. Contraceptives Instruct women receiving estrogen-based hormonal contraceptives that additional or alternative contraceptive measures should be used during therapy with APTIVUS. There may be an increased risk of rash when APTIVUS is given with hormonal contraceptives [ see Use in Specific Populations (8.3) ].
Fat Redistribution Inform patients that redistribution or accumulation of body fat may occur in patients receiving antiretroviral therapy and that the cause and long-term health effects of these conditions are not known at this time. Administration Inform patients that APTIVUS must be co-administered with ritonavir to ensure its therapeutic effect. Failure to correctly co-administer APTIVUS with ritonavir will result in reduced plasma levels of tipranavir that may be insufficient to achieve the desired antiviral effect.
APTIVUS co-administered with ritonavir tablets must only be taken with meals Instruct patients to swallow APTIVUS capsules whole. They must not be opened or chewed. Tell patients that sustained decreases in plasma HIV-1 RNA have been associated with a reduced risk of progression to AIDS and death.
Patients should remain under the care of a physician while using APTIVUS. Advise patients to take APTIVUS and other concomitant antiretroviral therapy every day as prescribed. APTIVUS, co-administered with ritonavir, must be given in combination with other antiretroviral drugs.
Patients should not alter the dose or discontinue therapy without consulting with their he…