
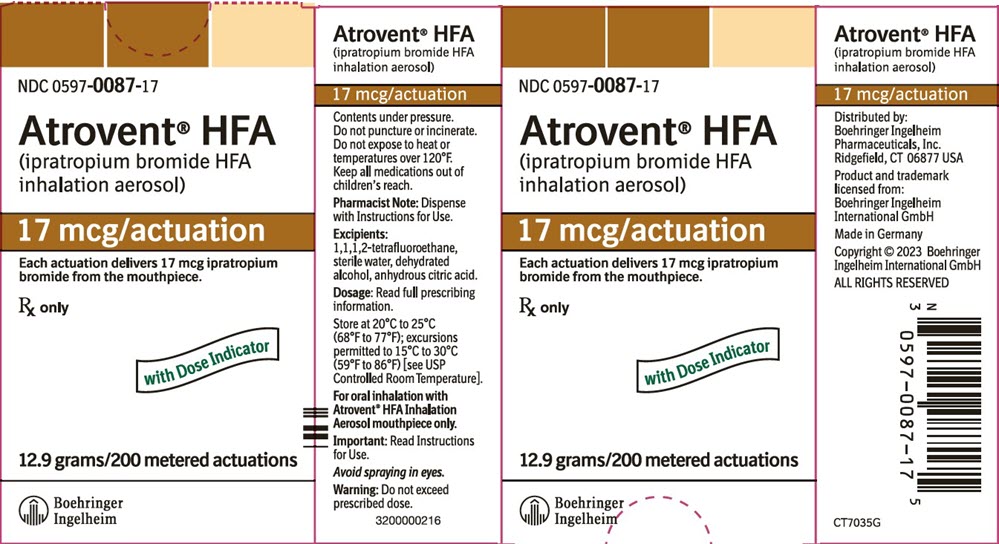
NDC 00597-0087-17: Atrovent HFA ipratropium bromide 17 ug Aerosol, Metered
This is a package of Atrovent HFA ipratropium bromide 17 ug Aerosol, Metered from Boehringer Ingelheim Pharmaceuticals, Inc., first listed with the FDA May 2005 and currently FDA-listed; retail pharmacies pay about $22.76 per g (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0597-0087-17 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0597 labeler · 0087 product · 17 package
- Package marketed since
- May 1, 2005
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 0597008717 5
- Medicaid fills, this package
- 88,974 prescriptions in the last four reported quarters
- FDA record last changed
- Nov 19, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 059081
- GCN: 24621
- GPI-14 (Medi-Span): 44100030123420
- HICL (First Databank): 000057
- AHFS class code: 12:08.08.00
- RxCUI (RxNorm): 836343
Where does this data come from?
- FDA openFDA NDC Directory · synced Nov 19, 2026
- FDA label on DailyMed · label index refreshed Nov 21, 2026
- RxNorm (NLM RxNav) · catalog refreshed Nov 19, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Nov 19, 2026
RxNorm drug class
This medicine belongs to the Anticholinergic class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Nov 19, 2026
Clinical
Ipratropium oral inhalation is used to prevent wheezing, shortness of breath, coughing, and chest tightness in people with chronic obstructive pulmonary disease (COPD; a group of diseases that affect the lungs and airways) such as chronic bronchitis (swelling of the air passages that lead to the lungs) and emphysema (damage to the air sacs in the lungs). Ipratropium is in a class of medications called bronchodilators. It works by relaxing and opening the air passages to the lungs to make breathing easier.
Read the full MedlinePlus article ↗- It's a daily maintenance medicine, not a rescue inhaler. You use it on a regular schedule every day to keep your airways open and prevent breathing problems — not to treat a sudden...
- Is this my rescue inhaler, or do I use it every day?
- That's called paradoxical bronchospasm, and it's rare but serious. If your breathing tightens up immediately after using ipratropium, stop using it right away and seek medical help...
- What should I do if my breathing gets worse right after I use it?
Patient education
Drug interactions
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Nov 19, 2026
- FDA label on DailyMed · label index refreshed Nov 21, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per g | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $22.759 | — |
| Medicaid paysCMS SDUD · 12 mo | $23.30 | — |
| Medicare drug plans payPart D · Q2 2026 | $22.79 | — |
Where does this data come from?
- CMS NADAC weekly file · file of Nov 18, 2026
- CMS ASP pricing files · refreshed Nov 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Oct 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00597-0087-17 You're viewing this Main listing | 1 CANISTER in 1 CARTON / 200 AEROSOL, METERED in 1 CANISTER | 2005-05-01 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ipratropium Bromide Inhalation 17 ug 17270-0401-00 | Armstrong | 1 canister | $21.626 | AB | Availability likely | save 5% |
| Atrovent HFA 17 ugthis 00597-0087-17 | Boehringer | 1 canister | $22.759 | AB | Availability likely | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Nov 19, 2026
- FDA Orange Book · refreshed Nov 6, 2026
- CMS NADAC weekly file · file of Nov 18, 2026
Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8474447 ↗ delist req. | Drug product | — | Jan 17, 2030 |
Is there a generic version of ATROVENT 17 MCG HFA INHALER?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Nov 6, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Ipratropium Oral Inhalation inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Nov 21, 2026
- FDA openFDA NDC Directory · synced Nov 19, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Boehringer Ingelheim Pharmaceuticals, Inc. labeler code 00597
- Micardis telmisartan 40 mg Tablet NDC 0597-0040-37
- Micardis telmisartan 80 mg Tablet NDC 0597-0041-37
- Micardis HCT telmisartan and hydrochlorothiazide 80 mg; 25 mg Tablet NDC 0597-0042-37
- Micardis HCT telmisartan and hydrochlorothiazide 40 mg; 12.5 mg Tablet NDC 0597-0043-37
- Micardis HCT telmisartan and hydrochlorothiazide 80 mg; 12.5 mg Tablet NDC 0597-0044-37
- Spiriva HandiHaler TIOTROPIUM BROMIDE 18 ug Capsule NDC 0597-0075-41
- Spiriva Respimat tiotropium bromide inhalation spray 3.124 ug Spray, Metered NDC 0597-0100-28
- Pradaxa dabigatran etexilate mesylate 110 mg Capsule NDC 0597-0108-54
- Gilotrif afatinib 30 mg Tablet, Film Coated NDC 0597-0137-30
- Gilotrif afatinib 40 mg Tablet, Film Coated NDC 0597-0138-30
- Tradjenta linagliptin 5 mg Tablet, Film Coated NDC 0597-0140-30
- Gilotrif afatinib 20 mg Tablet, Film Coated NDC 0597-0141-30
Where does this data come from?
- FDA openFDA NDC Directory · synced Nov 19, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ATROVENT HFA Inhalation Aerosol is indicated as a bronchodilator for maintenance treatment of bronchospasm associated with chronic obstructive pulmonary disease (COPD), including chronic bronchitis and emphysema. ATROVENT HFA is an anticholinergic indicated for the maintenance treatment of bronchospasm associated with chronic obstructive pulmonary disease (COPD), including chronic bronchitis and emphysema ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The usual starting dosage of ATROVENT HFA is two inhalations four times a day. Patients may take additional inhalations as required; however, the total number of inhalations should not exceed 12 in 24 hours. ATROVENT HFA is a solution aerosol that does not require shaking.
However, as with any other metered-dose inhaler, some coordination is required between actuating the canister and inhaling the medication. Patients should "prime" or actuate ATROVENT HFA before using for the first time by releasing 2 test sprays into the air away from the face. In cases where the inhaler has not been used for more than 3 days, prime the inhaler again by releasing 2 test sprays into the air away from the face.
Patients should avoid spraying ATROVENT HFA into their eyes. Each inhaler provides sufficient medication for 200 actuations. The inhaler should be discarded after the labeled number of actuations has been used.
The amount of medication in each actuation cannot be assured after this point, even though the canister is not completely empty. Patients should be instructed on the proper use of their inhaler [ see Patient Counseling Information (17) ]. For oral inhalation only Two inhalations four times a day, not to exceed 12 inhalations in 24 hours ( 2 )
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS ATROVENT HFA is an inhalation aerosol supplied in a pressurized stainless steel canister as a metered-dose inhaler with a white mouthpiece that has a clear, colorless sleeve and a green protective cap. Each pressurized metered-dose aerosol unit for oral inhalation contains a 12.9 g solution of ipratropium bromide (monohydrate) that provides sufficient medication for 200 actuations. After priming, each actuation of the inhaler delivers 21 mcg of ipratropium bromide (monohydrate) from the valve and delivers 17 mcg of ipratropium bromide (monohydrate) from the mouthpiece.
Inhalation Aerosol: Each actuation of ATROVENT HFA Inhalation Aerosol delivers 17 mcg of ipratropium bromide (monohydrate) from the mouthpiece ( 3 ) Supplied in a 12.9 g canister containing 200 actuations ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS ATROVENT HFA is contraindicated in the following conditions [ see Warnings and Precautions (5.2) ]. Hypersensitivity to ipratropium bromide or other ATROVENT HFA components Hypersensitivity to atropine or any of its derivatives Hypersensitivity to ipratropium bromide or other ATROVENT HFA components ( 4 ) Hypersensitivity to atropine or any of its derivatives ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Not indicated for the initial treatment of acute episodes of bronchospasm where rescue therapy is required for rapid response ( 5.1 ) Hypersensitivity reactions including anaphylaxis: Discontinue ATROVENT HFA at once and consider alternative treatments ( 5.2 ) Paradoxical bronchospasm: Discontinue ATROVENT HFA and consider other treatments if paradoxical bronchospasm occurs ( 5.3 ) Ocular effects: Use with caution in patients with narrow-angle glaucoma and instruct patients to consult a physician immediately if signs or symptoms of narrow-angle glaucoma develop ( 5.4 ) Urinary retention: Use with caution in patients with prostatic hyperplasia or bladder-neck obstruction and instruct patients to consult a physician immediately if signs or symptoms of urinary retention develop ( 5.5 )
5.1Use for Maintenance Treatment Only ATROVENT HFA is a bronchodilator for the maintenance treatment of bronchospasm associated with COPD and is not indicated for the initial treatment of acute episodes of bronchospasm where rescue therapy is required for rapid response.
5.2Hypersensitivity Reactions, Including Anaphylaxis Hypersensitivity reactions including urticaria, angioedema, rash, bronchospasm, anaphylaxis, and oropharyngeal edema may occur after the administration of ATROVENT HFA. In clinical trials and postmarketing experience with ipratropium-containing products, hypersensitivity reactions such as skin rash, pruritus, angioedema of tongue, lips and face, urticaria (including giant urticaria), laryngospasm and anaphylactic reactions have been reported [ see Adverse Reactions (6.1 , 6.2) ].
If such a reaction occurs, therapy with ATROVENT HFA should be stopped at once and alternative treatment should be considered [ see Contraindications (4) ] .
5.3Paradoxical Bronchospasm ATROVENT HFA can produce paradoxical bronchospasm that can be life threatening. If this occurs, treatment with ATROVENT HFA should be stopped and other treatments considered.
5.4Ocular Effects ATROVENT HFA is an anticholinergic and its use may increase intraocular pressure. This may result in precipitation or worsening of narrow-angle glaucoma. Therefore, ATROVENT HFA should be used with caution in patients with narrow-angle glaucoma [ see Drug Interactions (7.1) ].
Patients should avoid spraying ATROVENT HFA into their eyes. If a patient sprays ATROVENT HFA into their eyes, they may cause eye pain or discomfort, temporary blurring of vision, mydriasis, visual halos or colored images in association with red eyes from conjunctival and corneal congestion. Advise patients to consult their physician immediately if any of these symptoms develop while using ATROVENT HFA Inhalation Aerosol.
5.5Urinary Retention ATROVENT HFA is an anticholinergic and may cause urinary retention. Therefore, caution is advised when administering ATROVENT HFA Inhalation Aerosol to patients with prostatic hyperplasia, or bladder-neck obstruction [ see Drug Interactions (7.1) ].
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are described, or described in greater detail, in other sections: Hypersensitivity Reactions, Including Anaphylaxis [ see Contraindications (4) and Warnings and Precautions (5.2) ] Paradoxical Bronchospasm [ see Warnings and Precautions (5.3) ] Ocular Effects [ see Warnings and Precautions (5.4) ] Urinary Retention [ see Warnings and Precautions (5.5) ] Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in patients.
Most common adverse reactions (>5% incidence in the 12-week placebo-controlled trials) were bronchitis, COPD exacerbation, dyspnea, and headache ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Boehringer Ingelheim Pharmaceuticals, Inc. at 1-800-542-6257 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience The adverse reaction information concerning ATROVENT HFA is derived from two 12-week, double-blind, parallel-group studies and one 1-year open-label, parallel group study. These studies compared ATROVENT HFA Inhalation Aerosol, ATROVENT CFC Inhalation Aerosol, and placebo (in one study only) in 1,010 COPD patients. The following table lists the incidence of adverse reactions that occurred at a rate of greater than or equal to 3% in any ipratropium bromide group and greater than placebo in the 12-week study.
The frequency of corresponding reactions in the 1-year open label study is included for comparison. TABLE 1 Adverse Reactions (% Patients) in ATROVENT HFA Clinical Trials Placebo-controlled 12-week Study 244.1405 and Active-controlled 12-week Study 244.1408 Active-controlled 1-year Study 244.2453 ATROVENT HFA (N=243) % ATROVENT CFC (N=183) % Placebo (N=128) % ATROVENT HFA (N=305) % ATROVENT CFC (N=151) % BODY AS A WHOLE - GENERAL DISORDERS Back pain 2 3 2 7 3 Headache 6 9 8 7 5 Influenza-like symptoms 4 2 2 8 5 CENTRAL & PERIPHERAL NERVOUS SYSTEM DISORDERS Dizziness 3 3 2 3 1 GASTROINTESTINAL SYSTEM DISORDERS Dyspepsia 1 3 1 5 3 Mouth dry 4 2 2 2 3 Nausea 4 1 2 4 4 RESPIRATORY SYSTEM DISORDERS Bronchitis 10 11 6 23 19 COPD exacerbation 8 14 13 23 23 Dyspnea 8 8 4 7 4 Sinusitis 1 4 3 11 14 URINARY SYSTEM DISORDERS Urinary tract infection 2 3 1 10 8 Cough, rhinitis, and upper respiratory infection occurred in greater than or equal to 3% of patients in either ipratropium treatment group but not greater than placebo in the 12-week study.
In the one open-label controlled study in 456 COPD patients, the overall incidence of adverse events was also similar between ATROVENT HFA and ATROVENT CFC formulations. Overall, in the above mentioned studies, 9.3% of the patients taking 42 mcg ATROVENT HFA and 8.7% of the patients taking 42 mcg ATROVENT CFC reported at least one adverse event that was considered by the investigator to be related to the study drug. The most common drug-related adverse events were dry mouth (1.6% of ATROVENT HFA and 0.9% of ATROVENT CFC patients), and taste perversion (bitter taste) (0.9% of ATROVENT HFA and 0.3% of ATROVENT CFC patients).
As an anticholinergic drug, cases of precipitation or worsening of narrow-angle glaucoma, glaucoma, halo vision, conjunctival hyperemia, corneal edema, mydriasis, acute eye pain, dry throat, hypotension, palpitations, urinary retention, tachycardia, constipation, bronchospasm, including paradoxical bronchospasm have been reported with the use of ATROVENT. Additional adverse reactions identified for ATROVENT seen in clinical trials include throat irritation, stomatitis, mouth edema, and vision blurred. Allergic-type reactions such as skin rash, pruritus, angioedema including that of tongue, lips and face, urticaria (including giant urticaria), laryngospasm and anaphylactic reactions have been reported [ see Warnings and Precautions (5.2) ].
6.2Postmarketing Experience In a 5-year,… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS ATROVENT HFA has been used concomitantly with other drugs, including sympathomimetic bronchodilators, methylxanthines, oral and inhaled steroids commonly used in the treatment of COPD. With the exception of albuterol, there are no formal studies fully evaluating the interaction effects of ATROVENT HFA and these drugs with respect to safety and effectiveness. Anticholinergics: May interact additively with concomitantly used anticholinergic medications.
Avoid administration of ATROVENT HFA with other anticholinergic-containing drugs ( 7.1 )
7.1Anticholinergic Agents There is potential for an additive interaction with concomitantly used anticholinergic medications. Therefore, avoid coadministration of ATROVENT HFA with other anticholinergic-containing drugs as this may lead to an increase in anticholinergic adverse effects [ see Warnings and Precautions (5.4 , 5.5) ].
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Ipratropium is negligibly absorbed systemically following oral inhalation; therefore, maternal use is not expected to result in fetal exposure to the drug [ see Clinical Pharmacology (12.3) ]. There is limited experience with ipratropium bromide use in pregnant women. Published literature, including cohort studies, case control studies and case series, over several decades have not identified a drug associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes.
Based on animal reproduction studies, no evidence of structural alterations was observed when ipratropium bromide was administered to pregnant mice, rats and rabbits during organogenesis at doses up to approximately 200, 40,000, and 10,000 times, respectively, the maximum recommended human daily inhalation dose (MRHDID) in adults (see Data ) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data In animal reproduction studies, oral and inhalation administration of ipratropium bromide to pregnant mice, rats and rabbits during the period of organogenesis did not show evidence of fetal structural alterations. The ipratropium bromide dose in oral studies in mice, rats, and rabbits was up to approximately 200, 40,000, and 10,000 times, respectively, the MRHDID in adults (on a mg/m 2 basis at maternal doses of 10, 1,000, and 125 mg/kg/day, respectively).
The ipratropium bromide dose in inhalation studies in rats and rabbits was up to approximately 60 and 140 times, respectively, the MRHDID in adults (on a mg/m 2 basis at maternal doses of 1.5 and 1.8 mg/kg/day, respectively). Embryotoxicity was observed as increased resorption in rats at oral doses approximately 3,600 times the MRHDID in adults (on a mg/m 2 basis at maternal doses of 90 mg/kg/day and above). This effect is not considered relevant to human use due to the large doses at which it was observed and the difference in route of administration.
8.2Lactation Risk Summary There are no data on the presence of ipratropium in either human or animal milk, the effects on the breastfed infant, or the effects on milk production. Although lipid-insoluble quaternary cations pass into breast milk, ipratropium concentrations in plasma after inhaled therapeutic doses are low, therefore, ipratropium levels in human breast milk are expected to be low [ see Clinical Pharmacology (12.3) ]. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for ATROVENT HFA and any potential adverse effects on the breastfed child from ATROVENT HFA or from the underlying maternal condition.
8.4Pediatric Use Safety and effectiveness in the pediatric population have not been established.
8.5Geriatric Use In the pivotal 12-week study, both ATROVENT HFA and ATROVENT CFC formulations were equally effective in patients over 65 years of age and under 65 years of age. Of the total number of subjects in clinical studies of ATROVENT HFA, 57% were ≥65 years of age. No overall differences in safety or effectiveness were observed between these subjects and younger subjects.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Ipratropium is negligibly absorbed systemically following oral inhalation; therefore, maternal use is not expected to result in fetal exposure to the drug [ see Clinical Pharmacology (12.3) ]. There is limited experience with ipratropium bromide use in pregnant women. Published literature, including cohort studies, case control studies and case series, over several decades have not identified a drug associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes.
Based on animal reproduction studies, no evidence of structural alterations was observed when ipratropium bromide was administered to pregnant mice, rats and rabbits during organogenesis at doses up to approximately 200, 40,000, and 10,000 times, respectively, the maximum recommended human daily inhalation dose (MRHDID) in adults (see Data ) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data In animal reproduction studies, oral and inhalation administration of ipratropium bromide to pregnant mice, rats and rabbits during the period of organogenesis did not show evidence of fetal structural alterations. The ipratropium bromide dose in oral studies in mice, rats, and rabbits was up to approximately 200, 40,000, and 10,000 times, respectively, the MRHDID in adults (on a mg/m 2 basis at maternal doses of 10, 1,000, and 125 mg/kg/day, respectively).
The ipratropium bromide dose in inhalation studies in rats and rabbits was up to approximately 60 and 140 times, respectively, the MRHDID in adults (on a mg/m 2 basis at maternal doses of 1.5 and 1.8 mg/kg/day, respectively). Embryotoxicity was observed as increased resorption in rats at oral doses approximately 3,600 times the MRHDID in adults (on a mg/m 2 basis at maternal doses of 90 mg/kg/day and above). This effect is not considered relevant to human use due to the large doses at which it was observed and the difference in route of administration.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in the pediatric population have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use In the pivotal 12-week study, both ATROVENT HFA and ATROVENT CFC formulations were equally effective in patients over 65 years of age and under 65 years of age. Of the total number of subjects in clinical studies of ATROVENT HFA, 57% were ≥65 years of age. No overall differences in safety or effectiveness were observed between these subjects and younger subjects.
🆘 Overdosage ▾
10 OVERDOSAGE Acute overdose by inhalation is unlikely since ipratropium bromide is not well absorbed systemically after inhalation or oral administration.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Ipratropium bromide is an anticholinergic (parasympatholytic) agent which, based on animal studies, appears to inhibit vagally-mediated reflexes by antagonizing the action of acetylcholine, the transmitter agent released at the neuromuscular junctions in the lung. Anticholinergics prevent the increases in intracellular concentration of Ca++ which is caused by interaction of acetylcholine with the muscarinic receptors on bronchial smooth muscle.
12.2Pharmacodynamics Cardiovascular effects At recommended dosages, ipratropium bromide does not produce clinically significant changes in pulse rate or blood pressure. Ocular effects In studies without a positive control, ipratropium bromide did not alter pupil size, accommodation, or visual acuity. Mucociliary clearance and respiratory secretions Controlled clinical studies have demonstrated that ipratropium bromide does not alter either mucociliary clearance or the volume or viscosity of respiratory secretions.
12.3Pharmacokinetics Following administration by oral inhalation from a metered-dose inhaler, the majority of the delivered dose is deposited in the gastrointestinal tract and, to a lesser extent, in the lung, the intended site of action. Ipratropium bromide is a quaternary amine and hence is not readily absorbed into the systemic circulation either from the surface of the lung or from the gastrointestinal tract as confirmed by blood level and renal excretion studies. The half-life of elimination is about 2 hours after inhalation or intravenous administration.
Ipratropium bromide is minimally bound (0% to 9% in vitro ) to plasma albumin and α 1 -acid glycoprotein. It is partially metabolized to inactive ester hydrolysis products. Following intravenous administration, approximately one-half of the dose is excreted unchanged in the urine.
A pharmacokinetic study with 29 chronic obstructive pulmonary disease (COPD) patients (48-79 years of age) demonstrated that mean peak plasma ipratropium concentrations of 59±20 pg/mL were obtained following a single administration of 4 inhalations of ATROVENT HFA (84 mcg). Plasma ipratropium concentrations declined to 24±15 pg/mL by six hours. When these patients were administered 4 inhalations QID (16 inhalations/day=336 mcg) for one week, the mean peak plasma ipratropium concentration increased to 82±39 pg/mL with a trough (6 hour) concentration of 28±12 pg/mL at steady state.
Specific Populations Geriatric Patients In the pharmacokinetic study with 29 COPD patients, a subset of 14 patients were >65 years of age. Mean peak plasma ipratropium concentrations of 56±24 pg/mL were obtained following a single administration of 4 inhalations (21 mcg/puff) of ATROVENT HFA (84 mcg). When these 14 patients were administered 4 inhalations four times a day (16 inhalations/day) for one week, the mean peak plasma ipratropium concentration only increased to 84±50 pg/mL indicating that the pharmacokinetic behavior of ipratropium bromide in the geriatric population is consistent with younger patients.
Renally Impaired Patients The pharmacokinetics of ATROVENT HFA have not been studied in patients with renal insufficiency. Hepatically Impaired Patients The pharmacokinetics of ATROVENT HFA have not been studied in patients with hepatic insufficiency. Drug-Drug Interaction No specific pharmacokinetic studies were conducted to evaluate potential drug-drug interactions with other medications.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Ipratropium bromide is an anticholinergic (parasympatholytic) agent which, based on animal studies, appears to inhibit vagally-mediated reflexes by antagonizing the action of acetylcholine, the transmitter agent released at the neuromuscular junctions in the lung. Anticholinergics prevent the increases in intracellular concentration of Ca++ which is caused by interaction of acetylcholine with the muscarinic receptors on bronchial smooth muscle.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING ATROVENT HFA is supplied in a pressurized stainless steel canister as a metered-dose inhaler with a white mouthpiece that has a clear, colorless sleeve and a green protective cap (NDC 0597-0087-17). The mouthpiece has an actuation indicator visible through a small window. The indicator typically moves during every 5 to 7 actuations.
It displays the approximate number of actuations remaining in increments of 20, starting at "200" and decreasing until it reaches "0". The ATROVENT HFA canister is to be used only with the accompanying ATROVENT HFA mouthpiece. This mouthpiece should not be used with other aerosol medications.
Similarly, the canister should not be used with other mouthpieces. After priming, each actuation of ATROVENT HFA delivers 21 mcg of ipratropium bromide (monohydrate) from the valve and 17 mcg from the mouthpiece. Each canister has a net weight of 12.9 grams and provides sufficient medication for 200 actuations.
The inhaler should be discarded after the labeled number of actuations has been used when the indicator displays "0". The amount of medication in each actuation cannot be assured after this point, even though the canister is not completely empty. Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
For optimal results, the canister should be at room temperature before use. Contents Under Pressure: Do not puncture. Do not use or store near heat or open flame.
Exposure to temperatures above 120°F may cause bursting. Never throw the inhaler into a fire or incinerator. Keep out of reach of children.
Avoid spraying in eyes .
📦 Storage and Handling ▾
Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. For optimal results, the canister should be at room temperature before use. Contents Under Pressure: Do not puncture.
Do not use or store near heat or open flame. Exposure to temperatures above 120°F may cause bursting. Never throw the inhaler into a fire or incinerator.
Keep out of reach of children. Avoid spraying in eyes .
📋 Description ▾
11 DESCRIPTION The active ingredient in ATROVENT HFA is ipratropium bromide (monohydrate). It is an anticholinergic bronchodilator chemically described as 8-azoniabicyclo[3.2.1]octane, 3-(3-hydroxy-1-oxo-2-phenylpropoxy)-8-methyl-8-(1-methylethyl)-,bromide monohydrate, (3-endo, 8-syn)-: a synthetic quaternary ammonium compound, chemically related to atropine. The structural formula for ipratropium bromide is: C 20 H 30 BrNO 3 ∙H 2 O ipratropium bromide Mol.
Wt. 430.4 Ipratropium bromide is a white to off-white crystalline substance, freely soluble in water and methanol, sparingly soluble in ethanol, and insoluble in lipophilic solvents such as ether, chloroform, and fluorocarbons. ATROVENT HFA is a pressurized metered-dose aerosol unit for oral inhalation that contains a solution of ipratropium bromide.
The 200 inhalation unit has a net weight of 12.9 grams. After priming, each actuation of the inhaler delivers 21 mcg of ipratropium bromide (monohydrate) from the valve in 56 mg of solution and delivers 17 mcg of ipratropium bromide (monohydrate) from the mouthpiece. The actual amount of drug delivered to the lung may depend on patient factors, such as the coordination between the actuation of the device and inspiration through the delivery system.
The excipients are anhydrous citric acid, dehydrated alcohol, HFA-134a (1,1,1,2-tetrafluoroethane) as propellant, and sterile water for irrigation. This product does not contain chlorofluorocarbons (CFCs) as propellants. ATROVENT HFA should be primed before using for the first time by releasing 2 test sprays into the air away from the face.
In cases where the inhaler has not been used for more than 3 days, prime the inhaler again by releasing 2 test sprays into the air away from the face. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Instructions for Use). Appropriate and safe use of ATROVENT HFA includes providing the patient with the information listed below and an understanding of the way it should be administered. Advise patients that ATROVENT HFA is a bronchodilator for the maintenance treatment of bronchospasm associated with COPD and is not indicated for the initial treatment of acute episodes of bronchospasm where rescue therapy is required for rapid response.
Hypersensitivity Reactions Inform patients that hypersensitivity reactions, including urticaria, angioedema, rash, bronchospasm, anaphylaxis, and oropharyngeal edema, may occur after the administration of ATROVENT HFA. Advise patients to immediately discontinue ATROVENT HFA and consult a physician [ see Warnings and Precautions (5.2) ] . Paradoxical Bronchospasm Inform patients that ATROVENT HFA can produce paradoxical bronchospasm that can be life-threatening.
If paradoxical bronchospasm occurs, patients should discontinue using ATROVENT HFA. Ocular Effects Caution patients to avoid spraying the aerosol into their eyes and be advised that this may result in precipitation or worsening of narrow-angle glaucoma, mydriasis, increased intraocular pressure, acute eye pain or discomfort, temporary blurring of vision, visual halos or colored images in association with red eyes from conjunctival and corneal congestion. Patients should also be advised that should any combination of these symptoms develop, they should consult their physician immediately.
Since dizziness, accommodation disorder, mydriasis, and blurred vision may occur with use of ATROVENT HFA, patients should be cautioned about engaging in activities requiring balance and visual acuity such as driving a car or operating appliances or machinery. Urinary Retention Inform patients that ATROVENT HFA may cause urinary retention and should be advised to consult their physicians if they experience difficulty with urination. Frequency of Use The action of ATROVENT HFA should last 2 to 4 hours.
Advise patients not to increase the dose or frequency of ATROVENT HFA without patients consulting their physician. Advise patients to seek immediate medical attention if treatment with ATROVENT HFA becomes less effective for symptomatic relief, their symptoms become worse, and/or patients need to use the product more frequently than usual. Concomitant Drug Use Advise patients on the use of ATROVENT HFA in relation to other inhaled drugs [ see Drug Interactions (7.1) ].
Use Only as Prescribed Remind patients that ATROVENT HFA should be used consistently as prescribed throughout the course of therapy. Preparation for Use and Priming Instruct patients that priming ATROVENT HFA is essential to ensure appropriate content of the medication in each actuation. Patients do not have to shake the ATROVENT HFA canister before use .
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Following administration by oral inhalation from a metered-dose inhaler, the majority of the delivered dose is deposited in the gastrointestinal tract and, to a lesser extent, in the lung, the intended site of action. Ipratropium bromide is a quaternary amine and hence is not readily absorbed into the systemic circulation either from the surface of the lung or from the gastrointestinal tract as confirmed by blood level and renal excretion studies. The half-life of elimination is about 2 hours after inhalation or intravenous administration.
Ipratropium bromide is minimally bound (0% to 9% in vitro ) to plasma albumin and α 1 -acid glycoprotein. It is partially metabolized to inactive ester hydrolysis products. Following intravenous administration, approximately one-half of the dose is excreted unchanged in the urine.
A pharmacokinetic study with 29 chronic obstructive pulmonary disease (COPD) patients (48-79 years of age) demonstrated that mean peak plasma ipratropium concentrations of 59±20 pg/mL were obtained following a single administration of 4 inhalations of ATROVENT HFA (84 mcg). Plasma ipratropium concentrations declined to 24±15 pg/mL by six hours. When these patients were administered 4 inhalations QID (16 inhalations/day=336 mcg) for one week, the mean peak plasma ipratropium concentration increased to 82±39 pg/mL with a trough (6 hour) concentration of 28±12 pg/mL at steady state.
Specific Populations Geriatric Patients In the pharmacokinetic study with 29 COPD patients, a subset of 14 patients were >65 years of age. Mean peak plasma ipratropium concentrations of 56±24 pg/mL were obtained following a single administration of 4 inhalations (21 mcg/puff) of ATROVENT HFA (84 mcg). When these 14 patients were administered 4 inhalations four times a day (16 inhalations/day) for one week, the mean peak plasma ipratropium concentration only increased to 84±50 pg/mL indicating that the pharmacokinetic behavior of ipratropium bromide in the geriatric population is consistent with younger patients.
Renally Impaired Patients The pharmacokinetics of ATROVENT HFA have not been studied in patients with renal insufficiency. Hepatically Impaired Patients The pharmacokinetics of ATROVENT HFA have not been studied in patients with hepatic insufficiency. Drug-Drug Interaction No specific pharmacokinetic studies were conducted to evaluate potential drug-drug interactions with other medications.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Cardiovascular effects At recommended dosages, ipratropium bromide does not produce clinically significant changes in pulse rate or blood pressure. Ocular effects In studies without a positive control, ipratropium bromide did not alter pupil size, accommodation, or visual acuity. Mucociliary clearance and respiratory secretions Controlled clinical studies have demonstrated that ipratropium bromide does not alter either mucociliary clearance or the volume or viscosity of respiratory secretions.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Conclusions regarding the efficacy of ATROVENT HFA were derived from two randomized, double-blind, controlled clinical studies. These studies enrolled males and females ages 40 years and older, with a history of COPD, a smoking history of >10 pack-years, an FEV 1 <65% and an FEV 1 /FVC <70%. One of the studies was a 12-week randomized, double-blind active, and placebo-controlled study in which 505 of the 507 randomized COPD patients were evaluated for the safety and efficacy of 42 mcg (n=124) and 84 mcg (n=126) ATROVENT HFA in comparison to 42 mcg (n=127) ATROVENT CFC and their respective placebos (HFA n=62, CFC n=66).
Data for both placebo HFA and placebo CFC were combined in the evaluation. Serial FEV 1 (shown in Figure 1, below, as means adjusted for center and baseline effects on test day 1 and test day 85 (primary endpoint)) demonstrated that 1 dose (2 inhalations/21 mcg each) of ATROVENT HFA produced significantly greater improvement in pulmonary function than placebo. During the six hours immediately post-dose on day 1, the average hourly improvement in adjusted mean FEV 1 was 0.148 liters for ATROVENT HFA (42 mcg) and 0.013 liters for placebo.
The mean peak improvement in FEV 1 , relative to baseline, was 0.295 liters, compared to 0.138 liters for placebo. During the six hours immediately post-dose on day 85, the average hourly improvement in adjusted mean FEV 1 was 0.141 liters for ATROVENT HFA (42 mcg) and 0.014 liters for placebo. The mean peak improvement in FEV 1 , relative to baseline, was 0.295 liters, compared to 0.140 liters for placebo.
ATROVENT HFA (42 mcg) was shown to be clinically comparable to ATROVENT CFC (42 mcg). Figure 1 Day 1 and Day 85 (Primary Endpoint) Results In this study, both ATROVENT HFA and ATROVENT CFC formulations were equally effective in patients over 65 years of age and under 65 years of age. The median time to improvement in pulmonary function (FEV 1 increase of 15% or more) was within approximately 15 minutes, reached a peak in 1 to 2 hours, and persisted for 2 to 4 hours in the majority of the patients.
Improvements in Forced Vital Capacity (FVC) were also demonstrated. The other study was a 12-week, randomized, double-blind, active-controlled clinical study in 174 adults with COPD, in which ATROVENT HFA 42 mcg (n=118) was compared to ATROVENT CFC 42 mcg (n=56). Safety and efficacy of HFA and CFC formulations were shown to be comparable.
The bronchodilatory efficacy and comparability of ATROVENT HFA vs ATROVENT CFC were also studied in a one-year open-label safety and efficacy study in 456 COPD patients. The safety and efficacy of HFA and CFC formulations were shown to be comparable. Figure 1
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Two-year oral carcinogenicity studies in rats and mice have revealed no carcinogenic activity at doses up to 6 mg/kg (approximately 240 and 120 times the maximum recommended human daily inhalation dose (MRHDID) in adults on a mg/m 2 basis, respectively). Results of various mutagenicity/clastogenicity studies (Ames test, mouse dominant lethal test, mouse micronucleus test and chromosome aberrations of bone marrow in Chinese hamsters) were negative. Fertility of male or female rats at oral doses up to 50 mg/kg (approximately 2,000 times the MRHDID in adults on a mg/m 2 basis) was unaffected by ipratropium bromide administration.
At an oral dose of 500 mg/kg (approximately 20,000 times the MRHDID in adults on a mg/m 2 basis), ipratropium bromide produced a decrease in the conception rate.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Two-year oral carcinogenicity studies in rats and mice have revealed no carcinogenic activity at doses up to 6 mg/kg (approximately 240 and 120 times the maximum recommended human daily inhalation dose (MRHDID) in adults on a mg/m 2 basis, respectively). Results of various mutagenicity/clastogenicity studies (Ames test, mouse dominant lethal test, mouse micronucleus test and chromosome aberrations of bone marrow in Chinese hamsters) were negative. Fertility of male or female rats at oral doses up to 50 mg/kg (approximately 2,000 times the MRHDID in adults on a mg/m 2 basis) was unaffected by ipratropium bromide administration.
At an oral dose of 500 mg/kg (approximately 20,000 times the MRHDID in adults on a mg/m 2 basis), ipratropium bromide produced a decrease in the conception rate.
📖 Instructions for Use ▾
INSTRUCTIONS FOR USE ATROVENT ® HFA (ipratropium bromide HFA) Inhalation Aerosol, for oral inhalation use Read this Instructions for Use before using your ATROVENT HFA and each time you get a refill. There may be new information. This leaflet does not take the place of talking with your healthcare provider about your medical condition or your treatment.
Use ATROVENT HFA exactly as your healthcare provider tells you to. Do not change your dose or how often you use ATROVENT HFA without talking with your healthcare provider. Tell your doctor about all the medicines you take.
ATROVENT HFA may affect the way some other medicines work and some other medicines may affect the way ATROVENT HFA works. Important information about using ATROVENT HFA You do not have to shake ATROVENT HFA before using it. ATROVENT HFA should be "primed" 2 times before you use the first dose of a new ATROVENT HFA inhaler or when the inhaler has not been used for more than 3 days.
To prime, push the canister against the mouthpiece (see Figure 1 ), allowing the medicine to spray into the air. Do not spray the medicine into your eyes while priming ATROVENT HFA . Inhaler Description ATROVENT HFA Inhalation Aerosol (Figure 1) consists of a metal canister containing the medicine and a mouthpiece that releases the medicine from the canister.
The mouthpiece includes a clear colorless sleeve, a white plastic portion and a green protective dust cap. The inhaler comes with a dose indicator you can see through a small window on the plastic mouthpiece (see Figure 1 ). A new inhaler first shows "200" in the dose indicator window.
The dose indicator will show the approximate number of actuations (sprays) of medicine remaining in the inhaler. As you use the inhaler, the dose indicator will typically rotate during every 5 to 7 actuations (sprays) towards the next decreasing number (see Figure 2 ). Figure 1 Figure 2 Instructions for Use: 1.
Insert the metal canister into the clear end of the mouthpiece (see Figure 1 ). Make sure the canister is fully and firmly inserted into the mouthpiece. The ATROVENT HFA canister is to be used only with the ATROVENT HFA mouthpiece.
Do not use the ATROVENT HFA mouthpiece with other inhaled medicines. 2. Remove the green protective dust cap.
If the cap is not on the mouthpiece, make sure there is nothing in the mouthpiece before use. For best results, the canister should be at room temperature before use. 3.
Breathe out (exhale) deeply through your mouth. Hold the inhaler upright (see Figure 3 ). Put the mouthpiece in your mouth and close your lips.
Keep your eyes closed so that no medicine will be sprayed into your eyes. If sprayed into the eyes, ATROVENT HFA can cause blurry vision and other vision abnormalities, eye pain or discomfort, dilated pupils, or narrow-angle glaucoma or worsening of this condition. If any combination of these symptoms develops, you should consult your physician immediately.
Figure 3 4. Breathe in (inhale) slowly through your mouth and at the same time spray the ATROVENT HFA into your mouth. To spray ATROVENT HFA firmly press the canister against the mouthpiece 1 time (see Figure 4 ).
Keep breathing in deeply. Figure 4 5. Hold your breath for ten seconds and then take the mouthpiece out of your mouth and breathe out slowly (see Figure 5 ).
Figure 5 6. Wait at least 15 seconds and repeat steps 3 to 5 again. 7.
Replace the green protective dust cap after use. 8. Keep the mouthpiece clean.
At least once a week, wash the mouthpiece, shake it to remove excess water and let it air dry all the way (see Mouthpiece Cleaning Instructions ) . Mouthpiece Cleaning Instructions: Step A. Remove and set aside the canister and dust cap from the mouthpiece (see Figure 1 ).
Step B. Wash the mouthpiece through the top and bottom with warm running water for at least 30 seconds (see Figure 6 ). Do not use anything other than water to wash the mouthpiece.
Figure 6 Step C. Dry the mouthpiece by shaking off the excess water and allow it t… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 17 mcg Canister Carton NDC 0597-0087-17 Atrovent ® HFA (ipratropium bromide HFA inhalation aerosol) 17 mcg/actuation Each actuation delivers 17 mcg ipratropium bromide (monohydrate) from the mouthpiece. Rx only with Dose Indicator 12.9 grams/200 metered actuations Boehringer Ingelheim PRINCIPAL DISPLAY PANEL - 17 mcg Canister Carton