
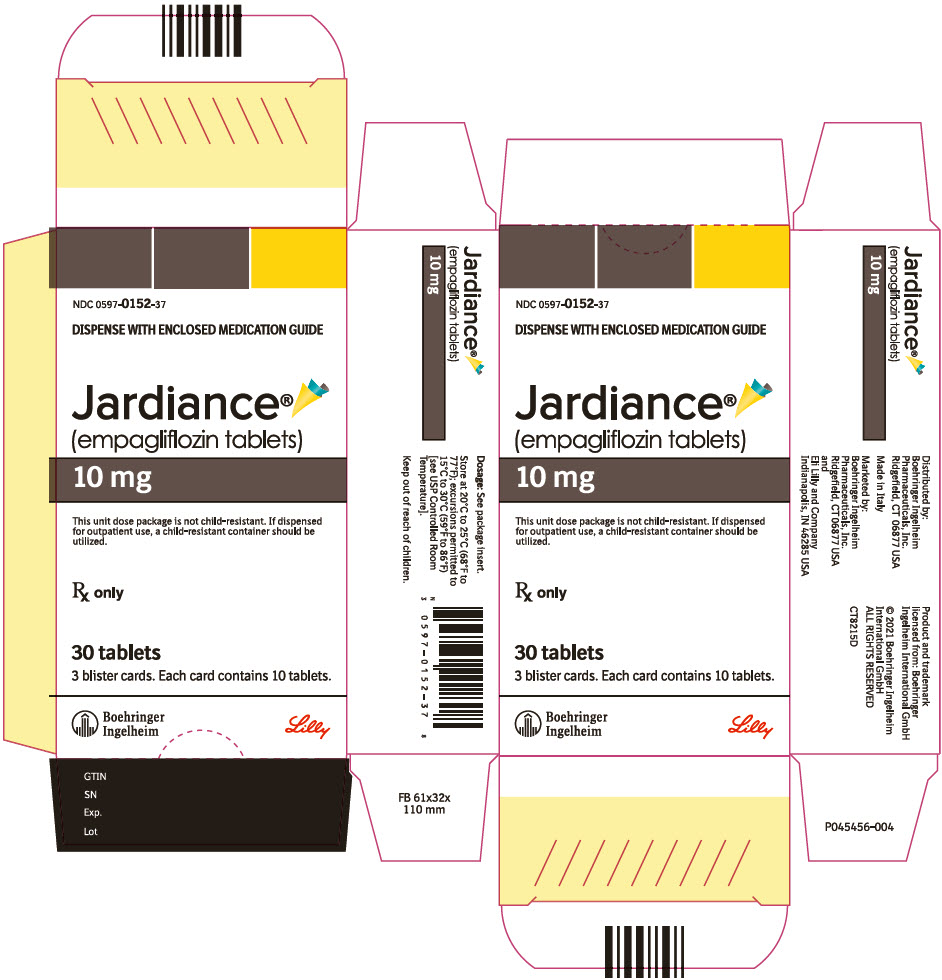
Jardiance Empagliflozin 10 mg Tablet, Film Coated
Past resolved recalls for this product (2)
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Sodium-Glucose Cotransporter 2 Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Jardiance does much more than just lower blood sugar. Yes, it's approved to help control blood sugar in type 2 diabetes — but it's also proven to reduce serious risks in heart fail...
- What exactly does Jardiance do — is it just for blood sugar?
- That's completely expected. Jardiance works by causing your kidneys to release excess glucose through your urine, and extra fluid follows along with it. This is actually part of ho...
- Why am I urinating more often since starting this medication?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Empagliflozin — tap one for details:
Empagliflozin may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Jardiance 10 mgthis 00597-0152-70 | Boehringer | 1 tablet | — | — | Discontinued | — |
| Jardiance 10 mg 50090-4492-00 | A-S | 90 tablets | — | — | FDA listed | — |
| Jardiance 10 mg 50090-6452-00 | A-S | 90 tablets | — | — | FDA listed | — |
| Jardiance 10 mg 55154-0411-08 | Cardinal | 720 tablets | — | — | FDA listed | — |
| Jardiance 10 mg 71610-0900-09 | Aphena | 9000 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9949998 ↗ | Method of use | U-2290 | Jun 11, 2034 |
| US 9949998 ↗ | Method of use | U-2290 | Jun 11, 2034 |
| US 9949997 ↗ | Method of use | U-2292 | May 17, 2034 |
| US 10258637 ↗ | Method of use | U-2290 | Apr 3, 2034 |
| US 8551957 ↗ | Method of use | U-1651 | Oct 14, 2029 |
| US 10258637 ↗ | Method of use | U-2290 | Apr 3, 2034 |
| US 9949997 ↗ | Method of use | U-2292 | May 17, 2034 |
| US 9949997 ↗ | Method of use | U-3325 | May 17, 2034 |
| US 9949997 ↗ | Method of use | U-3199 | May 17, 2034 |
| US 12115179 ↗ | Method of use | U-4023 | Feb 11, 2030 |
| US 12115179 ↗ | Method of use | U-4023 | Feb 11, 2030 |
| US 11090323 ↗ | Method of use | U-3191 | Apr 3, 2034 |
| US 11090323 ↗ | Method of use | U-3191 | Apr 3, 2034 |
| US 12433906 ↗ | Method of use | U-4304 | Apr 3, 2034 |
| US 12433906 ↗ | Method of use | U-4304 | Apr 3, 2034 |
| US 12263153 ↗ | Method of use | U-4171 | Apr 3, 2034 |
| US 12263153 ↗ | Method of use | U-4171 | Apr 3, 2034 |
| US 12433906 ↗ | Method of use | U-4293 | Apr 3, 2034 |
| US 12433906 ↗ | Method of use | U-4293 | Apr 3, 2034 |
| US 12433906 ↗ | Method of use | U-4294 | Apr 3, 2034 |
| US 12433906 ↗ | Method of use | U-4294 | Apr 3, 2034 |
| US 12433906 ↗ | Method of use | U-4295 | Apr 3, 2034 |
| US 12433906 ↗ | Method of use | U-4295 | Apr 3, 2034 |
| US 12433906 ↗ | Method of use | U-4296 | Apr 3, 2034 |
| US 12433906 ↗ | Method of use | U-4296 | Apr 3, 2034 |
| US 12427162 ↗ | Method of use | U-4287 | Apr 3, 2034 |
| US 12427162 ↗ | Method of use | U-4287 | Apr 3, 2034 |
| US 12527810 ↗ | Method of use | U-4403 | Apr 22, 2033 |
| US 12527810 ↗ | Method of use | U-4403 | Apr 22, 2033 |
| US 8551957 ↗ | Method of use | U-1651 | Oct 14, 2029 |
| US 11666590 ↗ | Method of use | U-3691 | Apr 3, 2034 |
| US 11833166 ↗ | Method of use | U-3776 | Apr 3, 2034 |
| US 11833166 ↗ | Method of use | U-3777 | Apr 3, 2034 |
| US 11833166 ↗ | Method of use | U-3777 | Apr 3, 2034 |
| US 11833166 ↗ | Method of use | U-3776 | Apr 3, 2034 |
| US 11813275 ↗ | Method of use | U-3759 | Apr 3, 2034 |
| US 11813275 ↗ | Method of use | U-3760 | Apr 3, 2034 |
| US 7579449 ↗ | Drug substance | — | Aug 1, 2028 |
| US 7713938 ↗ | Drug substance | — | Apr 15, 2027 |
| US 7713938 ↗ | Drug substance | — | Apr 15, 2027 |
| US 7579449 ↗ | Drug substance | — | Aug 1, 2028 |
| US 7579449*PED ↗ | Drug product | — | Feb 1, 2029 |
| US 7713938*PED ↗ | Drug product | — | Oct 15, 2027 |
| US 7713938*PED ↗ | Drug product | — | Oct 15, 2027 |
| US 7579449*PED ↗ | Drug product | — | Feb 1, 2029 |
| US 9949998*PED ↗ | Drug product | — | Dec 11, 2034 |
| US 9949997*PED ↗ | Drug product | — | Nov 17, 2034 |
| US 9949997*PED ↗ | Drug product | — | Nov 17, 2034 |
| US 9949998*PED ↗ | Drug product | — | Dec 11, 2034 |
| US 8551957*PED ↗ | Drug product | — | Apr 14, 2030 |
| US 8551957*PED ↗ | Drug product | — | Apr 14, 2030 |
| US 10258637*PED ↗ | Drug product | — | Oct 3, 2034 |
| US 10258637*PED ↗ | Drug product | — | Oct 3, 2034 |
| US 11813275*PED ↗ | Drug product | — | Oct 3, 2034 |
| US 11833166*PED ↗ | Drug product | — | Oct 3, 2034 |
| US 11833166*PED ↗ | Drug product | — | Oct 3, 2034 |
| US 12115179*PED ↗ | Drug product | — | Aug 11, 2030 |
| US 12115179*PED ↗ | Drug product | — | Aug 11, 2030 |
| US 11090323*PED ↗ | Drug product | — | Oct 3, 2034 |
| US 11090323*PED ↗ | Drug product | — | Oct 3, 2034 |
| US 12433906*PED ↗ | Drug product | — | Oct 3, 2034 |
| US 12433906*PED ↗ | Drug product | — | Oct 3, 2034 |
| US 12527810*PED ↗ | Drug product | — | Oct 22, 2033 |
| US 12527810*PED ↗ | Drug product | — | Oct 22, 2033 |
| Code | What it grants | Expires |
|---|---|---|
| I-922 | New indication (3-year) | Sep 21, 2026 |
| NPP | New Patient Population | Jun 20, 2026 |
| NPP | New Patient Population | Jun 20, 2026 |
| PED | Pediatric Exclusivity (+6 months) | Dec 20, 2026 |
| PED | Pediatric Exclusivity (+6 months) | Dec 20, 2026 |
Is there a generic version of this drug?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 00597-0152-07 | 1 BOTTLE in 1 CARTON (0597-0152-07) / 7 TABLET, FILM COATED in 1 BOTTLE | — | — | 2014-08-01 | Active |
| 00597-0152-30 | 30 TABLET, FILM COATED in 1 BOTTLE (0597-0152-30) | $11.19 / ea | $335.65 | 2014-08-01 | Active |
| 00597-0152-37 | 30 BLISTER PACK in 1 CARTON (0597-0152-37) / 1 TABLET, FILM COATED in 1 BLISTER PACK | $11.19 / ea | $335.65 | 2014-08-01 | Active |
| 00597-0152-70 You're viewing this | 7 BLISTER PACK in 1 CARTON (0597-0152-70) / 1 TABLET, FILM COATED in 1 BLISTER PACK | — | — | 2014-08-01 | Discontinued by firm |
| 00597-0152-90 | 90 TABLET, FILM COATED in 1 BOTTLE (0597-0152-90) | $11.19 / ea | $1,006.94 | 2014-08-01 | Active |
This pack shows little to no recent Medicaid volume — the 30 tablets pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 00597-0152-70?
What NDC number is used to bill for this package of Jardiance Empagliflozin 10 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
What does the discontinued status mean for this NDC?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE JARDIANCE is indicated: to reduce the risk of cardiovascular death and hospitalization for heart failure in adults with heart failure. to reduce the risk of sustained decline in eGFR, end-stage kidney disease, cardiovascular death, and hospitalization in adults with chronic kidney disease at risk of progression. to reduce the risk of cardiovascular death in adults with type 2 diabetes mellitus and established cardiovascular disease. as an adjunct to diet and exercise to improve glycemic control in adults and pediatric patients aged 10 years and older with type 2 diabetes mellitus.
JARDIANCE is a sodium-glucose co-transporter 2 (SGLT2) inhibitor indicated: To reduce the risk of cardiovascular death and hospitalization for heart failure in adults with heart failure. ( 1 ) To reduce the risk of sustained decline in eGFR, end-stage kidney disease, cardiovascular death, and hospitalization in adults with chronic kidney disease at risk of progression. ( 1 ) To reduce the risk of cardiovascular death in adults with type 2 diabetes mellitus and established cardiovascular disease.
( 1 ) As an adjunct to diet and exercise to improve glycemic control in adults and pediatric patients aged 10 years and older with type 2 diabetes mellitus. ( 1 ) Limitations of Use: Not recommended for use to improve glycemic control in patients with type 1 diabetes mellitus. It may increase the risk of diabetic ketoacidosis in these patients.
( 1 ) Not recommended for use to improve glycemic control in patients with type 2 diabetes mellitus with an eGFR less than 30 mL/min/1.73 m 2 . ( 1 ) Not recommended for the treatment of chronic kidney disease in patients with polycystic kidney disease or patients requiring or with a recent history of intravenous immunosuppressive therapy or greater than 45 mg of prednisone or equivalent for kidney disease. JARDIANCE is not expected to be effective in these populations.
( 1 ) Limitations of Use JARDIANCE is not recommended for use to improve glycemic control in patients with type 1 diabetes mellitus. It may increase the risk of diabetic ketoacidosis in these patients [see Warnings and Precautions (5.1) ] . JARDIANCE is not recommended for use to improve glycemic control in patients with type 2 diabetes mellitus with an eGFR less than 30 mL/min/1.73 m 2 .
JARDIANCE is likely to be ineffective in this setting based upon its mechanism of action. JARDIANCE is not recommended for the treatment of chronic kidney disease in patients with polycystic kidney disease or patients requiring or with a recent history of intravenous immunosuppressive therapy or greater than 45 mg of prednisone or equivalent for kidney disease [see Clinical Studies (14.5) ] . JARDIANCE is not expected to be effective in these populations.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Assess renal function before initiating and as clinically indicated. Assess volume status and correct volume depletion before initiating. ( 2.1 ) Recommended dosage is 10 mg orally once daily in the morning, taken with or without food.
( 2.2 ) For additional glycemic control, dosage may be increased to 25 mg orally once daily in patients tolerating JARDIANCE. ( 2.2 ) Withhold JARDIANCE for at least 3 days, if possible, prior to surgery or procedures associated with prolonged fasting. ( 2.3 )
2.1Testing Prior to Initiation of JARDIANCE Assess renal function before initiating JARDIANCE and as clinically indicated [see Warnings and Precautions (5.2) ] . Use for glycemic control is not recommended in patients with an eGFR less than 30 mL/min/1.73 m 2 [see Use in Specific Populations (8.6) ]. Assess volume status.
In patients with volume depletion, correct this condition before initiating JARDIANCE [see Warnings and Precautions (5.2) and Use in Specific Populations (8.5 , 8.6) ].
2.2Recommended Dosage Table 1 presents the recommended dosage of JARDIANCE in adult and pediatric patients aged 10 years and older. Table 1 Recommended Dosage of JARDIANCE Population Indication Recommended Dosage Adults Reduce the risk of cardiovascular death and hospitalization in patients with heart failure 10 mg orally once daily in the morning, taken with or without food. Reduce the risk of sustained decline in eGFR, end-stage kidney disease, cardiovascular death, and hospitalization in adults with chronic kidney disease at risk of progression.
Reduce the risk of cardiovascular death in patients with type 2 diabetes mellitus with established cardiovascular disease Glycemic control in type 2 diabetes mellitus 10 mg orally once daily in the morning, taken with or without food. For additional glycemic control, may increase to 25 mg orally once daily in patients tolerating 10 mg once daily. Pediatric patients aged 10 years and older Glycemic control in type 2 diabetes mellitus 10 mg orally once daily in the morning, taken with or without food.
For additional glycemic control, may increase to 25 mg orally once daily in patients tolerating 10 mg once daily.
2.3Temporary Interruption for Surgery Withhold JARDIANCE for at least 3 days, if possible, prior to surgery or procedures associated with prolonged fasting. Resume JARDIANCE when the patient is clinically stable and has resumed oral intake [see Warnings and Precautions (5.1) and Clinical Pharmacology (12.2) ].
2.4Recommendations Regarding Missed Dose If a dose is missed, instruct patients to take the dose as soon as possible. Advise patients not to double up the next dose.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS JARDIANCE tablets available as: 10 mg pale yellow, round, biconvex and bevel-edged, film-coated tablets debossed with "S 10" on one side and the Boehringer Ingelheim company symbol on the other side. 25 mg pale yellow, oval, biconvex, film-coated tablets debossed with "S 25" on one side and the Boehringer Ingelheim company symbol on the other side. Tablets: 10 mg, 25 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS JARDIANCE is contraindicated in patients: with a hypersensitivity to empagliflozin or any of the excipients in JARDIANCE, reactions such as angioedema have occurred [see Warnings and Precautions (5.6) ] . Hypersensitivity to empagliflozin or any of the excipients in JARDIANCE. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Diabetic Ketoacidosis in Patients with Type 1 Diabetes Mellitus and Other Ketoacidosis: Consider ketone monitoring in patients with type 1 diabetes mellitus and consider ketone monitoring in others at risk for ketoacidosis, as indicated. Assess for ketoacidosis regardless of presenting blood glucose levels and discontinue JARDIANCE if ketoacidosis is suspected. Monitor patients for resolution of ketoacidosis before restarting.
( 5.1 ) Volume Depletion: Before initiating JARDIANCE, assess volume status and renal function in patients with impaired renal function, elderly patients, or patients on loop diuretics. Monitor for signs and symptoms during therapy. ( 5.2 ) Genitourinary Infections, including Urosepsis, Pyelonephritis, Necrotizing Fasciitis of the Perineum (Fournier's Gangrene), and Genital Mycotic Infections: Monitor patients for signs and symptoms of genitourinary infections and treat promptly, if indicated.
Immediately evaluate patients presenting with pain or tenderness, erythema, or swelling in the genital or perineal area, along with fever or malaise, for necrotizing fasciitis and if suspected, discontinue JARDIANCE, and promptly institute appropriate medical and/or surgical intervention. ( 5.3 ) Hypoglycemia: Adult patients taking an insulin secretagogue or insulin may have an increased risk of hypoglycemia. In pediatric patients 10 years of age and older, the risk of hypoglycemia was higher regardless of insulin use.
Consider lowering the dosage of insulin secretagogue or insulin to reduce the risk of hypoglycemia when initiating JARDIANCE. ( 5.4 ) Lower Limb Amputation: Monitor patients for infections or ulcers of lower limbs, and institute appropriate treatment ( 5.5 ) Hypersensitivity Reactions: Serious hypersensitivity reactions (e.g., angioedema) have occurred with JARDIANCE. If hypersensitivity reactions occur, discontinue JARDIANCE, treat promptly, and monitor until signs and symptoms resolve.
( 5.6 )
5.1Diabetic Ketoacidosis in Patients with Type 1 Diabetes Mellitus and Other Ketoacidosis In patients with type 1 diabetes mellitus, JARDIANCE significantly increases the risk of diabetic ketoacidosis, a life-threatening event, beyond the background rate. In placebo-controlled trials of patients with type 1 diabetes mellitus, the risk of ketoacidosis was markedly increased in patients who received sodium glucose co-transporter 2 (SGLT2) inhibitors compared to patients who received placebo and fatal ketoacidosis has occurred with JARDIANCE.
JARDIANCE is not indicated for glycemic control in patients with type 1 diabetes mellitus. Type 2 diabetes mellitus and pancreatic disorders (e.g., history of pancreatitis or pancreatic surgery) are also risk factors for ketoacidosis. There have been postmarketing reports of fatal events of ketoacidosis in patients with type 2 diabetes mellitus using SGLT2 inhibitors, including JARDIANCE.
Precipitating conditions for diabetic ketoacidosis or other ketoacidosis include under-insulinization due to insulin dose reduction or missed insulin doses, acute febrile illness, reduced caloric intake, ketogenic diet, surgery, volume depletion, and alcohol abuse. Signs and symptoms are consistent with dehydration and severe metabolic acidosis and include nausea, vomiting, abdominal pain, generalized malaise, and shortness of breath. Blood glucose levels at presentation may be below those typically expected for diabetic ketoacidosis (e.g., less than 250 mg/dL).
Ketoacidosis and glucosuria may persist longer than typically expected. Urinary glucose excretion persists for 3 days after discontinuing JARDIANCE [see Clinical Pharmacology (12.2) ] ; however, there have been postmarketing reports of ketoacidosis and/or glucosuria lasting greater than 6 days and some up to 2 weeks after discontinuation of SGLT2 inhibitors. Consider ketone monitoring in patients with type 1 diabetes mellitus and consider ketone monitoring in others at risk for ketoacidosis if indicated…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following important adverse reactions are described below and elsewhere in the labeling: Diabetic Ketoacidosis in Patients with Type 1 Diabetes Mellitus and Other Ketoacidosis [see Warnings and Precautions (5.1) ] Volume Depletion [see Warnings and Precautions (5.2) ] Genitourinary Infections, including Urosepsis, Pyelonephritis, Necrotizing Fasciitis of the Perineum (Fournier's Gangrene), and Genital Mycotic Infections [see Warnings and Precautions (5.3) ] Hypoglycemia [see Warnings and Precautions (5.4) ] Hypersensitivity Reactions [see Warnings and Precautions (5.6) ] Most common adverse reactions (5% or greater incidence) were urinary tract infections and female genital mycotic infections ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Boehringer Ingelheim Pharmaceuticals, Inc. at 1-800-542-6257 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. JARDIANCE has been evaluated in clinical trials in adult and pediatric patients aged 10 to 17 years with type 2 diabetes mellitus, in adults with heart failure, and in adults with chronic kidney disease. The overall safety profile of JARDIANCE was generally consistent across the studied indications.
Clinical Trials in Adults with Type 2 Diabetes Mellitus The data in Table 2 are derived from a pool of four 24-week placebo-controlled trials and 18-week data from a placebo-controlled trial with insulin in adult patients with type 2 diabetes mellitus. JARDIANCE was used as monotherapy in one trial and as add-on therapy in four trials [see Clinical Studies (14.1) ] . These data reflect exposure of 1,976 adult patients to JARDIANCE with a mean exposure duration of approximately 23 weeks.
Patients received placebo (N=995), JARDIANCE 10 mg (N=999), or JARDIANCE 25 mg (N=977) once daily. The mean age of the population was 56 years and 3% were older than 75 years of age. More than half (55%) of the population was male; 46% were White, 50% were Asian, and 3% were Black or African American.
At baseline, 57% of the population had diabetes mellitus more than 5 years and had a mean hemoglobin A1c (HbA1c) of 8%. Established microvascular complications of diabetes mellitus at baseline included diabetic nephropathy (7%), retinopathy (8%), or neuropathy (16%). Baseline renal function was normal or mildly impaired in 91% of patients and moderately impaired in 9% of patients (mean eGFR 86.8 mL/min/1.73 m 2 ).
Table 2 shows adverse reactions (excluding hypoglycemia) that were not present at baseline, occurred more commonly in JARDIANCE-treated patients than on placebo and occurred in greater than or equal to 2% JARDIANCE-treated patients. Table 2 Adverse Reactions Reported in ≥2% of Adults with Type 2 Diabetes Mellitus Treated with JARDIANCE and Greater than Placebo in Pooled Placebo-Controlled Clinical Trials of JARDIANCE Monotherapy or Combination Therapy Adverse Reactions Placebo (%) N=995 JARDIANCE 10 mg (%) N=999 JARDIANCE 25 mg (%) N=977 a Predefined adverse event grouping, including, but not limited to, urinary tract infection, asymptomatic bacteriuria, cystitis b Female genital mycotic infections include the following adverse reactions: vulvovaginal mycotic infection, vaginal infection, vulvitis, vulvovaginal candidiasis, genital infection, genital candidiasis, genital infection fungal, genitourinary tract infection, vulvovaginitis, cervicitis, urogenital infection fungal, vaginitis bacterial.
Percentages calculated with the number of female subjects in each group as denominator: placebo (N=481), JARDIANCE 10 mg (N=443), JARDIANCE 25 mg (N=420). c Predefined adverse event grouping, including, but not limited to, polyuria, pollakiuria, and nocturia d Male genital mycotic infec…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS See Table 4 for clinically relevant interactions with JARDIANCE. Table 4 Clinically Relevant Interactions with JARDIANCE Diuretics Clinical Impact Coadministration of empagliflozin with diuretics resulted in increased urine volume and frequency of voids, which might enhance the potential for volume depletion. Intervention Before initiating JARDIANCE, assess volume status and renal function.
In patients with volume depletion, correct this condition before initiating JARDIANCE. Monitor for signs and symptoms of volume depletion, and renal function after initiating therapy. Insulin or Insulin Secretagogues Clinical Impact The risk of hypoglycemia is increased when JARDIANCE is used in combination with insulin secretagogues (e.g., sulfonylurea) or insulin.
Intervention Coadministration of JARDIANCE with an insulin secretagogue (e.g., sulfonylurea) or insulin may require lower dosages of the insulin secretagogue or insulin to reduce the risk of hypoglycemia. Lithium Clinical Impact Concomitant use of an SGLT2 inhibitor with lithium may decrease serum lithium concentrations. Intervention Monitor serum lithium concentration more frequently during JARDIANCE initiation and dosage changes.
Positive Urine Glucose Test Clinical Impact SGLT2 inhibitors increase urinary glucose excretion and will lead to positive urine glucose tests. Intervention Monitoring glycemic control with urine glucose tests is not recommended in patients taking SGLT2 inhibitors. Use alternative methods to monitor glycemic control.
Interference with 1,5-anhydroglucitol (1,5-AG) Assay Clinical Impact Measurements of 1,5-AG are unreliable in assessing glycemic control in patients taking SGLT2 inhibitors. Intervention Monitoring glycemic control with 1,5-AG assay is not recommended. Use alternative methods to monitor glycemic control.
See full prescribing information for information on drug interactions and interference of JARDIANCE with laboratory tests. ( 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Advise females of the potential risk to a fetus especially during the second and third trimesters. ( 8.1 ) Lactation: Not recommended when breastfeeding. ( 8.2 ) Geriatric Patients: Higher incidence of adverse reactions related to volume depletion and reduced renal function. ( 8.5 ) Renal Impairment: Higher incidence of adverse reactions related to reduced renal function. ( 8.6 )
8.1Pregnancy Risk Summary Based on animal data showing adverse renal effects, JARDIANCE is not recommended during the second and third trimesters of pregnancy. The limited available data with JARDIANCE in pregnant women are not sufficient to determine a drug-associated risk for major birth defects and miscarriage. There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy [see Clinical Considerations ] .
In animal studies, adverse renal changes were observed in rats when empagliflozin was administered during a period of renal development corresponding to the late second and third trimesters of human pregnancy. Doses approximately 13-times the maximum clinical dose caused renal pelvic and tubule dilatations that were reversible [see Data ] . The estimated background risk of major birth defects is 6% to 10% in women with pre-gestational diabetes with a HbA1c >7 and has been reported to be as high as 20% to 25% in women with HbA1c >10.
The estimated background risk of miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, pre-eclampsia, spontaneous abortions, preterm delivery, and delivery complications.
Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity. Data Animal Data Empagliflozin dosed directly to juvenile rats from postnatal day (PND) 21 until PND 90 at doses of 1, 10, 30, and 100 mg/kg/day caused increased kidney weights and renal tubular and pelvic dilatation at 100 mg/kg/day, which approximates 13-times the maximum clinical dose of 25 mg, based on AUC. These findings were not observed after a 13-week, drug-free recovery period.
These outcomes occurred with drug exposure during periods of renal development in rats that correspond to the late second and third trimester of human renal development. In embryo-fetal development studies in rats and rabbits, empagliflozin was administered for intervals coinciding with the first trimester period of organogenesis in humans. Doses up to 300 mg/kg/day, which approximates 48-times (rats) and 128-times (rabbits) the maximum clinical dose of 25 mg (based on AUC), did not result in adverse developmental effects.
In rats, at higher doses of empagliflozin causing maternal toxicity, malformations of limb bones increased in fetuses at 700 mg/kg/day or 154-times the 25 mg maximum clinical dose. Empagliflozin crosses the placenta and reaches fetal tissues in rats. In the rabbit, higher doses of empagliflozin resulted in maternal and fetal toxicity at 700 mg/kg/day, or 139-times the 25 mg maximum clinical dose.
In pre- and postnatal development studies in pregnant rats, empagliflozin was administered from gestation day 6 through to lactation day 20 (weaning) at up to 100 mg/kg/day (approximately 16-times the 25 mg maximum clinical dose) without maternal toxicity. Reduced body weight was observed in the offspring at greater than or equal to 30 mg/kg/day (approximately 4-times the 25 mg maximum clinical dose).
8.2Lactation Risk Summary There is limited information regarding the presence of JARDIANCE in human milk, the effects of JARDIANCE on the breastfed infant or the effects on milk production. Empagliflozin is present in the…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on animal data showing adverse renal effects, JARDIANCE is not recommended during the second and third trimesters of pregnancy. The limited available data with JARDIANCE in pregnant women are not sufficient to determine a drug-associated risk for major birth defects and miscarriage. There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy [see Clinical Considerations ] .
In animal studies, adverse renal changes were observed in rats when empagliflozin was administered during a period of renal development corresponding to the late second and third trimesters of human pregnancy. Doses approximately 13-times the maximum clinical dose caused renal pelvic and tubule dilatations that were reversible [see Data ] . The estimated background risk of major birth defects is 6% to 10% in women with pre-gestational diabetes with a HbA1c >7 and has been reported to be as high as 20% to 25% in women with HbA1c >10.
The estimated background risk of miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, pre-eclampsia, spontaneous abortions, preterm delivery, and delivery complications.
Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity. Data Animal Data Empagliflozin dosed directly to juvenile rats from postnatal day (PND) 21 until PND 90 at doses of 1, 10, 30, and 100 mg/kg/day caused increased kidney weights and renal tubular and pelvic dilatation at 100 mg/kg/day, which approximates 13-times the maximum clinical dose of 25 mg, based on AUC. These findings were not observed after a 13-week, drug-free recovery period.
These outcomes occurred with drug exposure during periods of renal development in rats that correspond to the late second and third trimester of human renal development. In embryo-fetal development studies in rats and rabbits, empagliflozin was administered for intervals coinciding with the first trimester period of organogenesis in humans. Doses up to 300 mg/kg/day, which approximates 48-times (rats) and 128-times (rabbits) the maximum clinical dose of 25 mg (based on AUC), did not result in adverse developmental effects.
In rats, at higher doses of empagliflozin causing maternal toxicity, malformations of limb bones increased in fetuses at 700 mg/kg/day or 154-times the 25 mg maximum clinical dose. Empagliflozin crosses the placenta and reaches fetal tissues in rats. In the rabbit, higher doses of empagliflozin resulted in maternal and fetal toxicity at 700 mg/kg/day, or 139-times the 25 mg maximum clinical dose.
In pre- and postnatal development studies in pregnant rats, empagliflozin was administered from gestation day 6 through to lactation day 20 (weaning) at up to 100 mg/kg/day (approximately 16-times the 25 mg maximum clinical dose) without maternal toxicity. Reduced body weight was observed in the offspring at greater than or equal to 30 mg/kg/day (approximately 4-times the 25 mg maximum clinical dose).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of JARDIANCE as an adjunct to diet and exercise to improve glycemic control in type 2 diabetes mellitus have been established in pediatric patients aged 10 years and older. Use of JARDIANCE for this indication is supported by evidence from a 26-week double-blind, placebo-controlled clinical trial, with a double-blind active treatment safety extension period of up to 52 weeks in 157 pediatric patients aged 10 to 17 years with type 2 diabetes mellitus and a pediatric pharmacokinetic study [see Clinical Pharmacology (12.3) and Clinical Studies (14.2) ] .
The safety profile of pediatric patients treated with JARDIANCE was similar to that observed in adults with type 2 diabetes mellitus, with the exception of hypoglycemia risk which was higher in pediatric patients treated with JARDIANCE regardless of concomitant insulin use [see Warnings and Precautions (5.4) and Adverse Reactions (6.1) ]. The safety and effectiveness of JARDIANCE have not been established in pediatric patients less than 10 years of age as an adjunct to diet and exercise to improve glycemic control in type 2 diabetes mellitus.
The safety and effectiveness of JARDIANCE have not been established in pediatric patients to reduce the risk of: cardiovascular death and hospitalization for heart failure in patients with heart failure. sustained decline in eGFR, end-stage kidney disease, cardiovascular death, and hospitalization in patients with chronic kidney disease at risk of progression. cardiovascular death in patients with type 2 diabetes mellitus and established cardiovascular disease.
🧓 Geriatric Use ▾
8.5Geriatric Use In glycemic control trials in patients with type 2 diabetes mellitus, a total of 2,721 (32%) patients treated with JARDIANCE were 65 years of age and older, and 491 (6%) were 75 years of age and older. JARDIANCE is expected to have diminished glycemic efficacy in elderly patients with renal impairment [see Use in Specific Populations (8.6) ] . The risk of volume depletion-related adverse reactions increased in patients who were 75 years of age and older to 2.1%, 2.3%, and 4.4% for placebo, JARDIANCE 10 mg, and JARDIANCE 25 mg.
The risk of urinary tract infections increased in patients who were 75 years of age and older to 10.5%, 15.7%, and 15.1% in patients randomized to placebo, JARDIANCE 10 mg, and JARDIANCE 25 mg, respectively [see Warnings and Precautions (5.2) and Adverse Reactions (6.1) ] . In the EMPEROR-Reduced, EMPEROR-Preserved, and EMPA-KIDNEY trials, no overall differences in safety and effectiveness have been observed between patients 65 years of age and older and younger adult patients. EMPEROR-Reduced included 1,188 (64%) patients treated with JARDIANCE 65 years of age and older, and 503 (27%) patients 75 years of age and older.
EMPEROR-Preserved included 2,403 (80%) patients treated with JARDIANCE 65 years of age and older, and 1,281 (43%) patients 75 years of age and older. EMPA-KIDNEY included 1,803 (55%) patients treated with JARDIANCE 65 years of age and older, and 758 (23%) patients 75 years of age and older.
🆘 Overdosage ▾
10 OVERDOSAGE In the event of an overdose with JARDIANCE, consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdosage management recommendations. Removal of empagliflozin by hemodialysis has not been studied.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Empagliflozin is an inhibitor of SGLT2, the predominant transporter responsible for reabsorption of glucose from the glomerular filtrate back into the circulation. By inhibiting SGLT2, empagliflozin reduces renal reabsorption of filtered glucose and lowers the renal threshold for glucose, and thereby increases urinary glucose excretion. Empagliflozin also reduces sodium reabsorption and increases the delivery of sodium to the distal tubule.
This may influence several physiological functions including, but not restricted to, increasing tubuloglomerular feedback and reducing intraglomerular pressure, lowering both pre- and afterload of the heart and downregulating sympathetic activity.
12.2Pharmacodynamics Urinary Glucose Excretion In patients with type 2 diabetes mellitus, urinary glucose excretion increased immediately following a dose of empagliflozin and was maintained at the end of a 4-week treatment period averaging at approximately 64 grams per day with 10 mg empagliflozin and 78 grams per day with 25 mg empagliflozin once daily [see Clinical Studies (14) ]. Data from single oral doses of empagliflozin in healthy subjects indicate that, on average, the elevation in urinary glucose excretion approaches baseline by about 3 days for the 10 mg and 25 mg doses.
Urinary Volume In a 5-day study, mean 24-hour urine volume increase from baseline was 341 mL on Day 1 and 135 mL on Day 5 of empagliflozin 25 mg once daily treatment. Cardiac Electrophysiology In a randomized, placebo-controlled, active-comparator, crossover study, 30 healthy subjects were administered a single oral dose of empagliflozin 25 mg, empagliflozin 200 mg (8 times the maximum dose), moxifloxacin, and placebo. No increase in QTc was observed with either 25 mg or 200 mg empagliflozin.
12.3Pharmacokinetics The pharmacokinetics of empagliflozin has been characterized in healthy volunteers and patients with type 2 diabetes mellitus and no clinically relevant differences were noted between the two populations. The steady-state mean plasma AUC and C max were 1,870 nmol∙h/L and 259 nmol/L, respectively, with 10 mg empagliflozin once daily treatment, and 4,740 nmol∙h/L and 687 nmol/L, respectively, with 25 mg empagliflozin once daily treatment. Systemic exposure of empagliflozin increased in a dose-proportional manner in the therapeutic dose range.
Empagliflozin does not appear to have time-dependent pharmacokinetic characteristics. Following once-daily dosing, up to 22% accumulation, with respect to plasma AUC, was observed at steady-state. Absorption After oral administration, peak plasma concentrations of empagliflozin were reached at 1.5 hours post-dose.
Administration of 25 mg empagliflozin after intake of a high-fat and high-calorie meal resulted in slightly lower exposure; AUC decreased by approximately 16% and C max decreased by approximately 37%, compared to fasted condition. The observed effect of food on empagliflozin pharmacokinetics was not considered clinically relevant and empagliflozin may be administered with or without food. Distribution The apparent steady-state volume of distribution was estimated to be
73.8L based on a population pharmacokinetic analysis. Following administration of an oral [ 14 C]-empagliflozin solution to healthy subjects, the red blood cell partitioning was approximately 36.8% and plasma protein binding was 86.2%. Elimination The apparent terminal elimination half-life of empagliflozin was estimated to be 12.4 h and apparent oral clearance was
10.6L/h based on the population pharmacokinetic analysis. Metabolism No major metabolites of empagliflozin were detected in human plasma and the most abundant metabolites were three glucuronide conjugates (2-O-, 3-O-, and 6-O-glucuronide). Systemic exposure of each metabolite was less than 10% of total drug-related material. In vitro studies suggested that the primary route of metabolism of empagliflozin in humans is glucuronidation by…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Empagliflozin is an inhibitor of SGLT2, the predominant transporter responsible for reabsorption of glucose from the glomerular filtrate back into the circulation. By inhibiting SGLT2, empagliflozin reduces renal reabsorption of filtered glucose and lowers the renal threshold for glucose, and thereby increases urinary glucose excretion. Empagliflozin also reduces sodium reabsorption and increases the delivery of sodium to the distal tubule.
This may influence several physiological functions including, but not restricted to, increasing tubuloglomerular feedback and reducing intraglomerular pressure, lowering both pre- and afterload of the heart and downregulating sympathetic activity.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING JARDIANCE tablets are available as follows: 10 mg tablets: pale yellow, round, biconvex, and bevel-edged film-coated tablets debossed with "S 10" on one side and the Boehringer Ingelheim company symbol on the other side. Bottles of 30 (NDC 0597-0152-30) Bottles of 90 (NDC 0597-0152-90) Cartons containing 3 blister cards of 10 tablets each (3 × 10) (NDC 0597-0152-37), institutional pack. 25 mg tablets: pale yellow, oval, biconvex film-coated tablets, debossed with "S 25" on one side and the Boehringer Ingelheim company symbol on the other side.
Bottles of 30 (NDC 0597-0153-30) Bottles of 90 (NDC 0597-0153-90) Cartons containing 3 blister cards of 10 tablets each (3 × 10) (NDC 0597-0153-37), institutional pack. Dispense in a well-closed container as defined in the USP. Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📦 Storage and Handling ▾
Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION JARDIANCE tablets for oral use contain empagliflozin, an inhibitor of the SGLT2. The chemical name of empagliflozin is D-Glucitol,1,5-anhydro-1-C-[4-chloro-3-[[4-[[(3S)-tetrahydro-3-furanyl]oxy]phenyl]methyl]phenyl]-, (1S). Its molecular formula is C 23 H 27 ClO 7 and the molecular weight is 450.91.
The structural formula is: Empagliflozin is a white to yellowish, non-hygroscopic powder. It is very slightly soluble in water, sparingly soluble in methanol, slightly soluble in ethanol and acetonitrile, soluble in 50% acetonitrile/water, and practically insoluble in toluene. Each film-coated tablet of JARDIANCE contains 10 mg or 25 mg of empagliflozin (free base) and the following inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, hydroxypropyl cellulose, lactose monohydrate, magnesium stearate, and microcrystalline cellulose.
In addition, the film coating contains the following inactive ingredients: ferric oxide yellow, hypromellose, polyethylene glycol, talc, and titanium dioxide. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Diabetic Ketoacidosis in Patients with Type 1 Diabetes Mellitus and Other Ketoacidosis In patients with type 1 diabetes mellitus, inform them that using JARDIANCE can increase their risk of life-threatening diabetic ketoacidosis and that fatal ketoacidosis has occurred. For all other patients, inform them that JARDIANCE can cause potentially fatal ketoacidosis and that type 2 diabetes mellitus and pancreatic disorders (e.g., history of pancreatitis or pancreatic surgery) are risk factors.
Educate all patients on precipitating factors (such as insulin dose reduction or missed insulin doses, infection, reduced caloric intake, ketogenic diet, surgery, dehydration, and alcohol abuse) and symptoms of ketoacidosis (including nausea, vomiting, abdominal pain, tiredness, and labored breathing). Inform patients that blood glucose may be normal even in the presence of ketoacidosis. Advise patients that they may be asked to monitor ketones.
If symptoms of ketoacidosis occur, instruct patients to discontinue JARDIANCE and seek medical attention immediately [see Warnings and Precautions (5.1) ] . Volume Depletion Inform patients that symptomatic hypotension may occur with JARDIANCE and advise them to contact their healthcare provider if they experience such symptoms [see Warnings and Precautions (5.2) ] . Inform patients that dehydration may increase the risk for hypotension, and to maintain adequate fluid intake.
Genitourinary Infections, including Urosepsis, Pyelonephritis, Necrotizing Fasciitis of the Perineum (Fournier's Gangrene), and Genital Mycotic Infections Counsel patients that genitourinary infections may occur when taking JARDIANCE and may become serious. Educate them on the symptoms and advise them to seek medical advice if symptoms occur. Specifically, advise patients to promptly seek medical attention if they develop pain or tenderness, redness, or swelling of the genitals or the area from the genitals back to the rectum, along with a fever above 100.4°F or malaise [see Warnings and Precautions (5.3) ] .
Hypoglycemia Inform patients that hypoglycemia has been reported when JARDIANCE is used with insulin secretagogues or insulin. Hypoglycemia may occur in pediatric patients regardless of concomitant antidiabetic treatment. Educate patients or caregivers on the signs and symptoms of hypoglycemia [see Warnings and Precautions (5.4) ] .
Lower Limb Amputation Counsel patients about the importance of routine preventative foot care. Instruct patients to monitor for new pain or tenderness, sores or ulcers, or infections involving the leg or foot and to seek medical advice immediately if such signs or symptoms develop [see Warnings and Precautions (5.5) ] . Hypersensitivity Reactions Inform patients that serious hypersensitivity reactions, such as urticaria and angioedema, have been reported with JARDIANCE.
Advise patients to report immediately any skin reaction or angioedema, and to discontinue drug until they have consulted prescribing healthcare provider [see Warnings and Precautions (5.6) ] . Laboratory Tests Inform patients that elevated glucose in urinalysis is expected when taking JARDIANCE [see Drug Interactions (7) ] . Pregnancy Advise pregnant patients, and patients of reproductive potential, of the potential risk to a fetus with treatment with JARDIANCE [see Use in Specific Populations (8.1) ] .
Instruct patients to report pregnancies to their healthcare provider as soon as possible. Lactation Advise patients that breastfeeding is not recommended during treatment with JARDIANCE [see Use in Specific Populations (8.2) ]. Missed Dose Instruct patients to take JARDIANCE only as prescribed.
If a dose is missed, it should be taken as soon as the patient remembers. Advise patients not to double their next dose [see Dosage and Administration (2.4) ] .
💬 Medication Guide ▾
This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: January 2026 MEDICATION GUIDE JARDIANCE ® (jar DEE ans) (empagliflozin tablets) for oral use What is the most important information I should know about JARDIANCE?
JARDIANCE can cause serious side effects, including: Diabetic ketoacidosis (increased ketones in your blood or urine) in people with type 1 and other ketoacidosis. JARDIANCE can cause ketoacidosis that can be life-threatening and may lead to death. Ketoacidosis is a serious condition which needs to be treated in a hospital.
People with type 1 diabetes have a high risk of getting ketoacidosis. People with type 2 diabetes or pancreas problems also have an increased risk of getting ketoacidosis. Ketoacidosis can also happen in people who: are sick, cannot eat or drink as usual, skip meals, are on a diet high in fat and low in carbohydrates (ketogenic diet), take less than the usual amount of insulin or miss insulin doses, drink too much alcohol, have a loss of too much fluid from the body (volume depletion), or who have surgery.
Ketoacidosis can happen even if your blood sugar is less than 250 mg/dL. Your healthcare provider may ask you to periodically check ketones in your urine or blood. Stop taking JARDIANCE and call your healthcare provider or get medical help right away if you get any of the following.
If possible, check for ketones in your urine or blood, even if your blood sugar is less than 250 mg/dL: nausea vomiting stomach-area (abdominal) pain tiredness trouble breathing ketones in your urine or blood Dehydration. JARDIANCE can cause some people to become dehydrated (the loss of body water and salt). Dehydration may cause you to feel dizzy, faint, light-headed, or weak, especially when you stand up (orthostatic hypotension).
There have been reports of sudden worsening of kidney function in people who are taking JARDIANCE. You may be at higher risk of dehydration if you: take medicines to lower your blood pressure, including diuretics (water pills) are on low sodium (salt) diet have kidney problems are 65 years of age or older Talk to your healthcare provider about what you can do to prevent dehydration including how much fluid you should drink on a daily basis. Call your healthcare provider right away if you reduce the amount of food or liquid you drink, for example if you are sick or you cannot eat, or start to lose liquids from your body, for example from vomiting, diarrhea or being in the sun too long.
What is JARDIANCE? JARDIANCE is a prescription medicine used to: reduce the risk of cardiovascular death and hospitalization for heart failure in adults with heart failure, when the heart cannot pump enough blood to the rest of your body. reduce the risk of further worsening of kidney disease, end-stage kidney disease (ESKD), death due to cardiovascular disease, and hospitalization in adults with chronic kidney disease. reduce the risk of cardiovascular death in adults with type 2 diabetes and who also have known cardiovascular disease. lower blood sugar (glucose) along with diet and exercise in adults and children who are 10 years of age and older with type 2 diabetes.
JARDIANCE is not for use to lower blood sugar (glucose) in people with type 1 diabetes. It may increase their risk of diabetic ketoacidosis (increased ketones in blood or urine). JARDIANCE is not for use to lower blood sugar (glucose) in people with type 2 diabetes who have severe kidney problems, because it may not work.
JARDIANCE is not for people with polycystic kidney disease, or who are taking or have recently received certain types of immunosuppressive therapy to treat kidney disease. JARDIANCE is not expected to work if you have these conditions. It is not known if JARDIANCE is safe and effective in children under 10 years of age.
Who should not take JARDIANCE? Do not take JARDIANCE if you: are allergic to empagliflozin or any of the ingredients in JARDIANCE. See the end of this Medication Guide…