
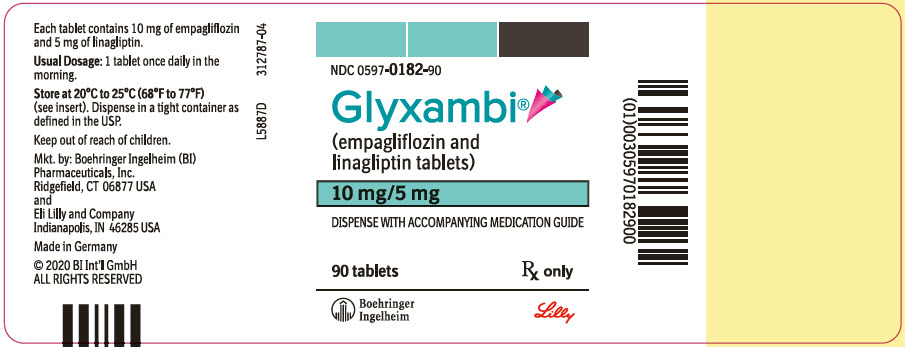
Glyxambi empagliflozin and linagliptin 10 mg; 5 mg Tablet, Film Coated
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Dipeptidyl Peptidase 4 Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Empagliflozin is used to: lower blood sugar in people with type 2 diabetes (condition in which blood sugar is too high because the body does not make or use insulin normally). reduce the risk of stroke, heart attack, or death in certain people who have type 2 diabetes. reduce the risk of being hospitalized for heart failure and death in adults with heart failure. reduce the risk of worsening of kidney disease, being hospitalized for heart failure, and death in certain adults with kidney disease. Empagliflozin is in a class of medications called sodium-glucose co-transporter 2 (SGLT2) inh...
Read the full MedlinePlus article ↗- Glyxambi works in two ways at the same time. The empagliflozin part tells your kidneys to flush extra sugar out of your body through urine instead of keeping it in your bloodstream...
- What is Glyxambi actually doing to help my diabetes?
- It's a real risk worth knowing about, but it's also something you can watch for. Ketoacidosis means your blood becomes dangerously acidic — and with SGLT2 inhibitors like empaglifl...
- I keep hearing about a dangerous condition called ketoacidosis. Should I be worried?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $11.244 | $337.31 / 30 tablet |
| Medicaid paysCMS SDUD · 12 mo | $20.31 | $609.31 / 30 tablet |
| Medicare drug plans payPart D · Q2 2026 | $11.23 | $337.01 / 30 tablet |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Glyxambi 10 mg/1; 5 mgthis 00597-0182-39 | Boehringer | 1 tablet | $11.244 | — | Availability likely | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9173859 ↗ delist req. | Method of use | U-1772 | May 4, 2027 |
| US 8551957 ↗ | Method of use | U-1651 | Oct 14, 2029 |
| US 9949998 ↗ | Method of use | U-2290 | Jun 11, 2034 |
| US 10258637 ↗ | Method of use | U-2290 | Apr 3, 2034 |
| US 9173859 ↗ delist req. | Method of use | U-1772 | May 4, 2027 |
| US 8673927 ↗ delist req. | Method of use | U-1652 | May 4, 2027 |
| US 9949998 ↗ | Method of use | U-2290 | Jun 11, 2034 |
| US 8551957 ↗ | Method of use | U-1651 | Oct 14, 2029 |
| US 8673927 ↗ delist req. | Method of use | U-1652 | May 4, 2027 |
| US 12433906 ↗ | Method of use | U-4304 | Apr 3, 2034 |
| US 12433906 ↗ | Method of use | U-4304 | Apr 3, 2034 |
| US 12433906 ↗ | Method of use | U-4293 | Apr 3, 2034 |
| US 12433906 ↗ | Method of use | U-4293 | Apr 3, 2034 |
| US 12433906 ↗ | Method of use | U-4294 | Apr 3, 2034 |
| US 12433906 ↗ | Method of use | U-4294 | Apr 3, 2034 |
| US 12433906 ↗ | Method of use | U-4295 | Apr 3, 2034 |
| US 12433906 ↗ | Method of use | U-4295 | Apr 3, 2034 |
| US 12433906 ↗ | Method of use | U-4296 | Apr 3, 2034 |
| US 12433906 ↗ | Method of use | U-4296 | Apr 3, 2034 |
| US 12364700 ↗ | Method of use | U-4224 | Jun 8, 2037 |
| US 12364700 ↗ | Method of use | U-4224 | Jun 8, 2037 |
| US 10258637 ↗ | Method of use | U-2290 | Apr 3, 2034 |
| US 11090323 ↗ | Method of use | U-3191 | Apr 3, 2034 |
| US 11090323 ↗ | Method of use | U-3191 | Apr 3, 2034 |
| US 11833166 ↗ | Method of use | U-3776 | Apr 3, 2034 |
| US 11833166 ↗ | Method of use | U-3777 | Apr 3, 2034 |
| US 11833166 ↗ | Method of use | U-3777 | Apr 3, 2034 |
| US 11833166 ↗ | Method of use | U-3776 | Apr 3, 2034 |
| US 12115179 ↗ | Method of use | U-4023 | Feb 11, 2030 |
| US 12115179 ↗ | Method of use | U-4023 | Feb 11, 2030 |
| US 12178819 ↗ | Drug product | — | May 4, 2027 |
| US 8883805 ↗ | Drug product | — | Nov 26, 2025 |
| US 8883805 ↗ | Drug product | — | Nov 26, 2025 |
| US 7713938 ↗ | Drug substance | — | Apr 15, 2027 |
| US 7713938 ↗ | Drug substance | — | Apr 15, 2027 |
| US 11033552 ↗ | Drug product | — | May 4, 2027 |
| US 11033552 ↗ | Drug product | — | May 4, 2027 |
| US 7579449 ↗ | Drug substance | — | Aug 1, 2028 |
| US 12178819 ↗ | Drug product | — | May 4, 2027 |
| US 7579449 ↗ | Drug substance | — | Aug 1, 2028 |
| US 8673927*PED ↗ | Drug product | — | Nov 4, 2027 |
| US 7579449*PED ↗ | Drug product | — | Feb 1, 2029 |
| US 8551957*PED ↗ | Drug product | — | Apr 14, 2030 |
| US 8883805*PED ↗ | Drug product | — | May 26, 2026 |
| US 7713938*PED ↗ | Drug product | — | Oct 15, 2027 |
| US 7713938*PED ↗ | Drug product | — | Oct 15, 2027 |
| US 8551957*PED ↗ | Drug product | — | Apr 14, 2030 |
| US 8883805*PED ↗ | Drug product | — | May 26, 2026 |
| US 8673927*PED ↗ | Drug product | — | Nov 4, 2027 |
| US 7579449*PED ↗ | Drug product | — | Feb 1, 2029 |
| US 10258637*PED ↗ | Drug product | — | Oct 3, 2034 |
| US 10258637*PED ↗ | Drug product | — | Oct 3, 2034 |
| US 12115179*PED ↗ | Drug product | — | Aug 11, 2030 |
| US 12115179*PED ↗ | Drug product | — | Aug 11, 2030 |
| US 12433906*PED ↗ | Drug product | — | Oct 3, 2034 |
| US 12433906*PED ↗ | Drug product | — | Oct 3, 2034 |
| US 11833166*PED ↗ | Drug product | — | Oct 3, 2034 |
| US 11833166*PED ↗ | Drug product | — | Oct 3, 2034 |
| US 12364700*PED ↗ | Drug product | — | Dec 8, 2037 |
| US 12364700*PED ↗ | Drug product | — | Dec 8, 2037 |
| US 11090323*PED ↗ | Drug product | — | Oct 3, 2034 |
| US 11090323*PED ↗ | Drug product | — | Oct 3, 2034 |
| US 11033552*PED ↗ | Drug product | — | Nov 4, 2027 |
| US 11033552*PED ↗ | Drug product | — | Nov 4, 2027 |
Is there a generic version of GLYXAMBI 10 MG-5 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 00597-0182-07 | 1 BOTTLE in 1 CARTON (0597-0182-07) / 7 TABLET, FILM COATED in 1 BOTTLE | — | — | 2015-01-30 | Discontinued by firm |
| 00597-0182-30 | 30 TABLET, FILM COATED in 1 BOTTLE (0597-0182-30) | $11.24 / ea | $337.31 | 2015-01-30 | Active |
| 00597-0182-39 You're viewing this | 30 BLISTER PACK in 1 CARTON (0597-0182-39) / 1 TABLET, FILM COATED in 1 BLISTER PACK | $11.24 / ea | $337.31 | 2015-01-30 | Active |
| 00597-0182-90 | 90 TABLET, FILM COATED in 1 BOTTLE (0597-0182-90) | $11.24 / ea | $1,011.93 | 2015-01-30 | Active |
This pack effectively ties for the lowest per-ea cost of the 3 priced pack sizes ($11.24 NADAC).
This pack accounts for about 0.9% of this product's recent Medicaid fills; most go to the 30 tablets pack. See all packs ↓
Pack size FAQ
What quantity is in NDC 00597-0182-39?
What NDC number is used to bill for this package of Glyxambi empagliflozin and linagliptin 10 mg; 5 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE GLYXAMBI is a combination of empagliflozin and linagliptin indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus . Empagliflozin is indicated to reduce the risk of cardiovascular (CV) death in adults with type 2 diabetes mellitus and established CV disease [see Clinical Studies (14.2) ] . GLYXAMBI is a combination of empagliflozin, a sodium-glucose co-transporter 2 (SGLT2) inhibitor and linagliptin, a dipeptidyl peptidase-4 (DPP-4) inhibitor, indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus.
Empagliflozin is indicated to reduce the risk of cardiovascular (CV) death in adults with type 2 diabetes mellitus and established CV disease. ( 1 ) Limitations of Use Not recommended for use to improve glycemic control in patients with type 1 diabetes mellitus. It may increase the risk of diabetic ketoacidosis in these patients.
( 1 ) Has not been studied in patients with a history of pancreatitis. ( 1 ) Not recommended for use to improve glycemic control in adults with type 2 diabetes mellitus with an eGFR less than 30 mL/min/1.73 m 2 . ( 1 ) Limitations of Use GLYXAMBI is not recommended for use to improve glycemic control in patients with type 1 diabetes mellitus.
It may increase the risk of diabetic ketoacidosis in these patients [see Warnings and Precautions (5.1) ] . GLYXAMBI has not been studied in patients with a history of pancreatitis. It is unknown whether patients with a history of pancreatitis are at an increased risk for the development of pancreatitis while using GLYXAMBI [see Warnings and Precautions (5.2) ].
GLYXAMBI is not recommended for use to improve glycemic control in adults with type 2 diabetes mellitus with an eGFR less than 30 mL/min/1.73 m 2 . GLYXAMBI is likely to be ineffective in this setting based upon its mechanism of action.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Assess renal function before initiating and as clinically indicated. Assess volume status and correct volume depletion before initiating. ( 2.1 ) The recommended dosage of GLYXAMBI is 10 mg empagliflozin and 5 mg linagliptin once daily, taken in the morning, with or without food.
( 2.2 ) Dosage may be increased to 25 mg empagliflozin and 5 mg linagliptin once daily. ( 2.2 ) Withhold GLYXAMBI for at least 3 days, if possible, prior to surgery or procedures associated with prolonged fasting. ( 2.4 )
2.1Testing Prior to Initiation of GLYXAMBI Assess renal function before initiating GLYXAMBI and as clinically indicated [see Warnings and Precautions (5.3) ] . Assess volume status. In patients with volume depletion, correct this condition before initiating GLYXAMBI [see Warnings and Precautions (5.3) and Use in Specific Populations (8.5 , 8.6) ] .
2.2Recommended Dosage and Administration The recommended dosage of GLYXAMBI is 10 mg empagliflozin/5 mg linagliptin once daily in the morning, taken with or without food. GLYXAMBI may be increased to 25 mg empagliflozin/5 mg linagliptin once daily for additional glycemic control.
2.3Dosage Recommendations in Patients with Renal Impairment GLYXAMBI is not recommended for use in patients with an eGFR less than 30 mL/min/1.73 m 2 [see Indications and Usage (1) , Warnings and Precautions (5.3) , and Use in Specific Populations (8.6) ] .
2.4Temporary Interruption for Surgery Withhold GLYXAMBI for at least 3 days, if possible, prior to surgery or procedures associated with prolonged fasting. Resume GLYXAMBI when the patient is clinically stable and has resumed oral intake [see Warnings and Precautions (5.1) and Clinical Pharmacology (12.2) ].
2.5Recommendations Regarding Missed Dose If a dose is missed, instruct patients to take the dose as soon as possible. Advise patients not to double up the next dose.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS GLYXAMBI tablets available as: 10 mg empagliflozin/5 mg linagliptin are pale yellow, arc triangular, flat-faced, bevel-edged, film-coated tablets. One side is debossed with the Boehringer Ingelheim company symbol; the other side is debossed with "10/5". 25 mg empagliflozin/5 mg linagliptin are pale pink, arc triangular, flat-faced, bevel-edged, film-coated tablets.
One side is debossed with the Boehringer Ingelheim company symbol; the other side is debossed with "25/5". Tablets: 10 mg empagliflozin/5 mg linagliptin ( 3 ) 25 mg empagliflozin/5 mg linagliptin ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS GLYXAMBI is contraindicated in patients: with a hypersensitivity to empagliflozin, linagliptin, or any of the excipients in GLYXAMBI, reactions such as anaphylaxis, angioedema, exfoliative skin conditions, urticaria, or bronchial hyperreactivity have occurred [see Warnings and Precautions (5.7) and Adverse Reactions (6) ] . Hypersensitivity to empagliflozin, linagliptin, or any of the excipients in GLYXAMBI. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Diabetic Ketoacidosis in Patients with Type 1 Diabetes Mellitus and Other Ketoacidosis: Consider ketone monitoring in patients at risk of ketoacidosis, as indicated. Assess for ketoacidosis regardless of presenting blood glucose levels and discontinue GLYXAMBI if ketoacidosis is suspected. Monitor patients for resolution of ketoacidosis before restarting.
( 5.1 ) Pancreatitis: There have been reports of acute pancreatitis, including fatal pancreatitis. If pancreatitis is suspected, promptly discontinue GLYXAMBI. ( 5.2 ) Volume Depletion: Before initiating GLYXAMBI, assess volume status and renal function in patients with impaired renal function, elderly patients, or patients on loop diuretics.
Monitor for signs and symptoms during therapy. ( 5.3 ) Genitourinary Infections, including Urosepsis, Pyelonephritis, Necrotizing Fasciitis of the Perineum (Fournier's Gangrene), and Genital Mycotic Infections: Monitor patients for signs and symptoms of genitourinary infections and treat promptly, if indicated. Immediately evaluate patients presenting with pain or tenderness, erythema, or swelling in the genital or perineal area, along with fever or malaise, for necrotizing fasciitis and if suspected, discontinue GLYXAMBI, and promptly institute appropriate medical and/or surgical intervention.
( 5.4 ) Hypoglycemia: Consider lowering the dosage of insulin secretagogue or insulin to reduce the risk of hypoglycemia when initiating GLYXAMBI. ( 5.5 ) Lower Limb Amputation: Monitor patients for infections or ulcers of lower limbs, and institute appropriate treatment. ( 5.6 ) Hypersensitivity Reactions: Serious hypersensitivity reactions (e.g., anaphylaxis, angioedema, and exfoliative skin conditions) have occurred with empagliflozin and linagliptin.
If hypersensitivity reactions occur, discontinue GLYXAMBI, treat promptly, and monitor until signs and symptoms resolve. ( 5.7 ) Arthralgia: Severe and disabling arthralgia has been reported in patients taking linagliptin. Consider as a possible cause for severe joint pain and discontinue drug if appropriate.
( 5.8 ) Bullous Pemphigoid: There have been reports of bullous pemphigoid requiring hospitalization. Tell patients to report development of blisters or erosions. If bullous pemphigoid is suspected, discontinue GLYXAMBI.
( 5.9 ) Heart Failure: Heart failure has been observed with two other members of the DPP-4 inhibitor class. Consider risks and benefits of GLYXAMBI in patients who have known risk factors for heart failure. Monitor for signs and symptoms.
( 5.10 )
5.1Diabetic Ketoacidosis in Patients with Type 1 Diabetes Mellitus and Other Ketoacidosis In patients with type 1 diabetes mellitus, empagliflozin, a component of GLYXAMBI, significantly increases the risk of diabetic ketoacidosis, a life-threatening event, beyond the background rate. In placebo-controlled trials of patients with type 1 diabetes mellitus, the risk of ketoacidosis was markedly increased in patients who received sodium glucose co-transporter 2 (SGLT2) inhibitors compared to patients who received placebo and fatal ketoacidosis has occurred with empagliflozin.
GLYXAMBI is not indicated for glycemic control in patients with type 1 diabetes mellitus. Type 2 diabetes mellitus and pancreatic disorders (e.g., history of pancreatitis or pancreatic surgery) are also risk factors for ketoacidosis. There have been postmarketing reports of fatal events of ketoacidosis in patients with type 2 diabetes mellitus using SGLT2 inhibitors, including GLYXAMBI.
Precipitating conditions for diabetic ketoacidosis or other ketoacidosis include under-insulinization due to insulin dose reduction or missed insulin doses, acute febrile illness, reduced caloric intake, ketogenic diet, surgery, volume depletion, and alcohol abuse. Signs and symptoms are consistent with dehydration and severe metabolic acidosis and include nausea, vomiting, abdominal pain, generalized malaise, and shortness of breath. Blood glucose levels…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following important adverse reactions are described below and elsewhere in the labeling: Diabetic Ketoacidosis in Patients with Type 1 Diabetes Mellitus and Other Ketoacidosis [see Warnings and Precautions (5.1) ] Pancreatitis [see Warnings and Precautions (5.2) ] Volume Depletion [see Warnings and Precautions (5.3) ] Genitourinary Infections, including Urosepsis, Pyelonephritis, Necrotizing Fasciitis of the Perineum (Fournier's Gangrene), and Genital Mycotic Infections [see Warnings and Precautions (5.4) ] Hypoglycemia with Concomitant Use with Insulin and Insulin Secretagogues [see Warnings and Precautions (5.5) ] Lower Limb Amputation [see Warnings and Precautions (5.6) ] Hypersensitivity Reactions [see Warnings and Precautions (5.7) ] Severe and Disabling Arthralgia [see Warnings and Precautions (5.8) ] Bullous Pemphigoid [see Warnings and Precautions (5.9) ] Heart Failure [see Warnings and Precautions (5.10) ] Most common adverse reactions (5% or greater incidence) were urinary tract infections, nasopharyngitis, and upper respiratory tract infections ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Boehringer Ingelheim Pharmaceuticals, Inc. at 1-800-542-6257, or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Empagliflozin and Linagliptin The safety of concomitantly administered empagliflozin (daily dosage 10 mg or 25 mg) and linagliptin (daily dosage 5 mg) has been evaluated in a total of 1,363 patients with type 2 diabetes mellitus treated for up to 52 weeks in active-controlled clinical trials.
The most common adverse reactions with concomitant administration of empagliflozin and linagliptin based on a pooled analyses of these trials are shown in Table 1. Table 1 Adverse Reactions Reported in ≥5% of Patients Treated with Empagliflozin and Linagliptin Adverse Reactions GLYXAMBI (%) 10 mg/5 mg n=272 GLYXAMBI (%) 25 mg/5 mg n=273 a Predefined adverse event grouping, including, but not limited to, urinary tract infection, asymptomatic bacteriuria, cystitis Urinary tract infection a 12.5
11.4Nasopharyngitis 5.9
6.6Upper respiratory tract infection 7.0
7.0Empagliflozin Adverse reactions that occurred in ≥2% of patients receiving empagliflozin and more commonly than in patients given placebo included (10 mg, 25 mg, and placebo): urinary tract infection (9.3%, 7.6%, and 7.6%), female genital mycotic infections (5.4%, 6.4%, and 1.5%), upper respiratory tract infection (3.1%, 4.0%, and 3.8%), increased urination (3.4%, 3.2%, and 1.0%), dyslipidemia (3.9%, 2.9%, and 3.4%), arthralgia (2.4%, 2.3%, and 2.2%), male genital mycotic infections (3.1%, 1.6%, and 0.4%), and nausea (2.3%, 1.1%, and 1.4%).
Thirst (including polydipsia) was reported in 0%, 1.7%, and 1.5% for placebo, empagliflozin 10 mg, and empagliflozin 25 mg, respectively. Empagliflozin causes an osmotic diuresis, which may lead to intravascular volume contraction and adverse reactions related to volume depletion. Events related to volume depletion (hypotension and syncope) were reported in 3 patients (1.1%) treated with GLYXAMBI plus metformin.
Linagliptin Adverse reactions reported in ≥2% of patients treated with linagliptin 5 mg and more commonly than in patients treated with placebo included: nasopharyngitis (7.0% and 6.1%), diarrhea (3.3% and 3.0%), and cough (2.1% and 1.4%). Other adverse reactions reported in clinical trials with treatment of linagliptin monotherapy were hypersensitivity (e.g., urticaria, angioedema, localized skin exfoliation, or bronchial hyperreactivity) and myalgia. In the clinical trial program, pancreatitis was reported in 15.2 cases per 10,000 patient year exposure while being treated with linagliptin compared with 3.7…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 3 describes clinically relevant interactions with GLYXAMBI. Table 3 Clinically Relevant Interactions with GLYXAMBI Diuretics Clinical Impact Coadministration of empagliflozin with diuretics resulted in increased urine volume and frequency of voids, which might enhance the potential for volume depletion. Intervention Before initiating GLYXAMBI, assess volume status and renal function.
In patients with volume depletion, correct this condition before initiating GLYXAMBI. Monitor for signs and symptoms of volume depletion, and renal function after initiating therapy. Insulin or Insulin Secretagogues Clinical Impact The risk of hypoglycemia is increased when GLYXAMBI is used in combination with an insulin secretagogue (e.g., sulfonylurea) or insulin.
Intervention Coadministration of GLYXAMBI with an insulin secretagogue (e.g., sulfonylurea) or insulin may require lower dosages of the insulin secretagogue or insulin to reduce the risk of hypoglycemia. Lithium Clinical Impact Concomitant use of an SGLT2 inhibitor with lithium may decrease serum lithium concentrations. Intervention Monitor serum lithium concentration more frequently during GLYXAMBI initiation and dosage changes.
Inducers of P-glycoprotein or CYP3A4 Enzymes Clinical Impact Rifampin decreased linagliptin exposure, suggesting that the efficacy of linagliptin may be reduced when administered in combination with a strong P-gp or CYP3A4 inducer. Intervention Use of alternative treatments is strongly recommended when linagliptin is to be administered with a strong P-gp or CYP3A4 inducer. Positive Urine Glucose Test Clinical Impact SGLT2 inhibitors increase urinary glucose excretion and will lead to positive urine glucose tests.
Intervention Monitoring glycemic control with urine glucose tests is not recommended in patients taking SGLT2 inhibitors. Use alternative methods to monitor glycemic control. Interference with 1,5-anhydroglucitol (1,5-AG) Assay Clinical Impact Measurements of 1,5-AG are unreliable in assessing glycemic control in patients taking SGLT2 inhibitors.
Intervention Monitoring glycemic control with 1,5-AG assay is not recommended. Use alternative methods to monitor glycemic control. See full prescribing information for information on drug interactions and interference of GLYXAMBI with laboratory tests.
( 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Advise females of the potential risk to a fetus especially during the second and third trimesters. ( 8.1 ) Lactation: Not recommended when breastfeeding. ( 8.2 ) Pediatric Patients : Safety and effectiveness of GLYXAMBI in pediatric patients have not been established.
( 8.4 ) Geriatric Patients: Higher incidence of adverse reactions related to volume depletion and reduced renal function. ( 8.5 ) Renal Impairment: Higher incidence of adverse reactions related to reduced renal function. ( 8.6 )
8.1Pregnancy Risk Summary Based on animal data showing adverse renal effects from empagliflozin, GLYXAMBI is not recommended during the second and third trimesters of pregnancy. The limited available data with GLYXAMBI, linagliptin, or empagliflozin in pregnant women are not sufficient to determine a drug-associated risk for major birth defects and miscarriage. There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy (see Clinical Considerations ).
In animal studies, empagliflozin, a component of GLYXAMBI, resulted in adverse renal changes in rats when administered during a period of renal development corresponding to the late second and third trimesters of human pregnancy. Doses approximately 13-times the maximum clinical dose caused renal pelvic and tubule dilatations that were reversible. No adverse developmental effects were observed when the combination of linagliptin and empagliflozin was administered to pregnant rats (see Data ).
The estimated background risk of major birth defects is 6% to 10% in women with pre-gestational diabetes with a HbA1c >7 and has been reported to be as high as 20% to 25% in women with HbA1c >10. The estimated background risk of miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, pre-eclampsia, spontaneous abortions, preterm delivery, and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity. Data Animal Data The combined components administered during the period of organogenesis were not teratogenic in rats up to and including a combined dose of 700 mg/kg/day empagliflozin and 140 mg/kg/day linagliptin, which is 253- and 353-times the clinical exposure.
A pre- and postnatal development study was not conducted with the combined components of GLYXAMBI. Empagliflozin: Empagliflozin dosed directly to juvenile rats from postnatal day (PND) 21 until PND 90 at doses of 1, 10, 30, and 100 mg/kg/day caused increased kidney weights and renal tubular and pelvic dilatation at 100 mg/kg/day, which approximates 13-times the maximum clinical dose of 25 mg, based on AUC. These findings were not observed after a 13-week, drug-free recovery period.
These outcomes occurred with drug exposure during periods of renal development in rats that correspond to the late second and third trimester of human renal development. In embryo-fetal development studies in rats and rabbits, empagliflozin was administered for intervals coinciding with the first trimester period of organogenesis in humans. Doses up to 300 mg/kg/day, which approximates 48-times (rats) and 128-times (rabbits) the maximum clinical dose of 25 mg (based on AUC), did not result in adverse developmental effects.
In rats, at higher doses of empagliflozin causing maternal toxicity, malformations of limb bones increased in fetuses at 700 mg/kg/day or 154-times the 25 mg maximum clinical dose. Empagliflozin crosses the placenta and reaches fetal tissues in rats. In the rabbit, higher doses of empagliflozin resulted in maternal and fetal toxicity at 700 mg/…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on animal data showing adverse renal effects from empagliflozin, GLYXAMBI is not recommended during the second and third trimesters of pregnancy. The limited available data with GLYXAMBI, linagliptin, or empagliflozin in pregnant women are not sufficient to determine a drug-associated risk for major birth defects and miscarriage. There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy (see Clinical Considerations ).
In animal studies, empagliflozin, a component of GLYXAMBI, resulted in adverse renal changes in rats when administered during a period of renal development corresponding to the late second and third trimesters of human pregnancy. Doses approximately 13-times the maximum clinical dose caused renal pelvic and tubule dilatations that were reversible. No adverse developmental effects were observed when the combination of linagliptin and empagliflozin was administered to pregnant rats (see Data ).
The estimated background risk of major birth defects is 6% to 10% in women with pre-gestational diabetes with a HbA1c >7 and has been reported to be as high as 20% to 25% in women with HbA1c >10. The estimated background risk of miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, pre-eclampsia, spontaneous abortions, preterm delivery, and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity. Data Animal Data The combined components administered during the period of organogenesis were not teratogenic in rats up to and including a combined dose of 700 mg/kg/day empagliflozin and 140 mg/kg/day linagliptin, which is 253- and 353-times the clinical exposure.
A pre- and postnatal development study was not conducted with the combined components of GLYXAMBI. Empagliflozin: Empagliflozin dosed directly to juvenile rats from postnatal day (PND) 21 until PND 90 at doses of 1, 10, 30, and 100 mg/kg/day caused increased kidney weights and renal tubular and pelvic dilatation at 100 mg/kg/day, which approximates 13-times the maximum clinical dose of 25 mg, based on AUC. These findings were not observed after a 13-week, drug-free recovery period.
These outcomes occurred with drug exposure during periods of renal development in rats that correspond to the late second and third trimester of human renal development. In embryo-fetal development studies in rats and rabbits, empagliflozin was administered for intervals coinciding with the first trimester period of organogenesis in humans. Doses up to 300 mg/kg/day, which approximates 48-times (rats) and 128-times (rabbits) the maximum clinical dose of 25 mg (based on AUC), did not result in adverse developmental effects.
In rats, at higher doses of empagliflozin causing maternal toxicity, malformations of limb bones increased in fetuses at 700 mg/kg/day or 154-times the 25 mg maximum clinical dose. Empagliflozin crosses the placenta and reaches fetal tissues in rats. In the rabbit, higher doses of empagliflozin resulted in maternal and fetal toxicity at 700 mg/kg/day, or 139-times the 25 mg maximum clinical dose.
In pre- and postnatal development studies in pregnant rats, empagliflozin was administered from gestation day 6 through to lactation day 20 (weaning) at up to 100 mg/kg/day (approximately 16-times the 25 mg maximum clinical dose) without maternal toxicity. Reduced body weight was observed in the offspring at greater than or equal to 30 mg/kg/day (approximately 4-times the 25 mg maximum clinical dose). Linagliptin: No adverse developmental outcome was observed when linagliptin was…
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of GLYXAMBI have not been established in pediatric patients.
🧓 Geriatric Use ▾
8.5Geriatric Use GLYXAMBI Empagliflozin is associated with osmotic diuresis, which could affect hydration status of patients age 75 years and older [see Warnings and Precautions (5.3) ] . Empagliflozin In empagliflozin type 2 diabetes mellitus trials, 2,721 empagliflozin-treated patients were 65 years of age and older and 491 patients were 75 years of age and older. In these trials, volume depletion-related adverse reactions occurred in 2.1%, 2.3%, and 4.4% of patients 75 years of age and older in the placebo, empagliflozin 10 mg, and empagliflozin 25 mg once daily groups, respectively; and urinary tract infections occurred in 10.5%, 15.7%, and 15.1% of patients 75 years of age and older in the placebo, empagliflozin 10 mg, and empagliflozin 25 mg once daily groups, respectively.
Linagliptin In linagliptin trials, 1,085 linagliptin-treated patients were 65 years of age and older and 131 patients were 75 years of age and older. In these linagliptin trials, no overall differences in safety or effectiveness of linagliptin were observed between geriatric patients and younger adult patients.
🆘 Overdosage ▾
10 OVERDOSAGE In the event of an overdose with GLYXAMBI, consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdosage management recommendations. Removal of empagliflozin by hemodialysis has not been studied, and removal of linagliptin by hemodialysis or peritoneal dialysis is unlikely.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action GLYXAMBI GLYXAMBI contains: empagliflozin, a SGLT2 inhibitor, and linagliptin, a DPP-4 inhibitor. Empagliflozin Empagliflozin is an inhibitor of SGLT2, the predominant transporter responsible for reabsorption of glucose from the glomerular filtrate back into the circulation. By inhibiting SGLT2, empagliflozin reduces renal reabsorption of filtered glucose and lowers the renal threshold for glucose, and thereby increases urinary glucose excretion.
Linagliptin Linagliptin is an inhibitor of DPP-4, an enzyme that degrades the incretin hormones glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP). Thus, linagliptin increases the concentrations of active incretin hormones, stimulating the release of insulin in a glucose-dependent manner and decreasing the levels of glucagon in the circulation. Both incretin hormones are involved in the physiological regulation of glucose homeostasis.
Incretin hormones are secreted at a low basal level throughout the day and levels rise immediately after meal intake. GLP-1 and GIP increase insulin biosynthesis and secretion from pancreatic beta cells in the presence of normal and elevated blood glucose levels. Furthermore, GLP-1 also reduces glucagon secretion from pancreatic alpha cells, resulting in a reduction in hepatic glucose output.
12.2Pharmacodynamics Empagliflozin Urinary Glucose Excretion In patients with type 2 diabetes mellitus, urinary glucose excretion increased immediately following a dose of empagliflozin and was maintained at the end of a 4-week treatment period averaging at approximately 64 grams per day with 10 mg empagliflozin and 78 grams per day with 25 mg empagliflozin once daily. Data from single oral doses of empagliflozin in healthy subjects indicate that, on average, the elevation in urinary glucose excretion approaches baseline by about 3 days for the 10 mg and 25 mg doses.
Urinary Volume In a 5-day study, mean 24-hour urine volume increase from baseline was 341 mL on Day 1 and 135 mL on Day 5 of empagliflozin 25 mg once daily treatment. Cardiac Electrophysiology In a randomized, placebo-controlled, active-comparator, crossover study, 30 healthy subjects were administered a single oral dose of empagliflozin 25 mg, empagliflozin 200 mg (8 times the maximum recommended dose), moxifloxacin, and placebo. No increase in QTc was observed with either 25 mg or 200 mg empagliflozin.
Linagliptin Linagliptin binds to DPP-4 in a reversible manner and increases the concentrations of incretin hormones. Linagliptin glucose-dependently increases insulin secretion and lowers glucagon secretion, thus resulting in a better regulation of the glucose homeostasis. Linagliptin binds selectively to DPP-4 and selectively inhibits DPP-4, but not DPP-8 or DPP-9 activity in vitro at concentrations approximating therapeutic exposures.
Cardiac Electrophysiology In a randomized, placebo-controlled, active-comparator, 4-way crossover study, 36 healthy subjects were administered a single oral dose of linagliptin 5 mg, linagliptin 100 mg (20 times the recommended dose), moxifloxacin, and placebo. No increase in QTc was observed with either the recommended dose of 5 mg or the 100 mg dose. At the 100 mg dose, peak linagliptin plasma concentrations were approximately 38-fold higher than the peak concentrations following a 5-mg dose.
12.3Pharmacokinetics GLYXAMBI Administration of the fixed-dose combination with food resulted in no change in overall exposure of empagliflozin or linagliptin; however, the peak exposure was decreased 39% and 32% for empagliflozin and linagliptin, respectively. These changes are not likely to be clinically significant. Empagliflozin The pharmacokinetics of empagliflozin has been characterized in healthy volunteers and patients with type 2 diabetes mellitus and no clinically relevant differences were noted between the two populations.
The steady-state mean plasma AUC and C max were 1,870 nmol∙h/…
🧬 Mechanism of Action ▾
12.1Mechanism of Action GLYXAMBI GLYXAMBI contains: empagliflozin, a SGLT2 inhibitor, and linagliptin, a DPP-4 inhibitor. Empagliflozin Empagliflozin is an inhibitor of SGLT2, the predominant transporter responsible for reabsorption of glucose from the glomerular filtrate back into the circulation. By inhibiting SGLT2, empagliflozin reduces renal reabsorption of filtered glucose and lowers the renal threshold for glucose, and thereby increases urinary glucose excretion.
Linagliptin Linagliptin is an inhibitor of DPP-4, an enzyme that degrades the incretin hormones glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP). Thus, linagliptin increases the concentrations of active incretin hormones, stimulating the release of insulin in a glucose-dependent manner and decreasing the levels of glucagon in the circulation. Both incretin hormones are involved in the physiological regulation of glucose homeostasis.
Incretin hormones are secreted at a low basal level throughout the day and levels rise immediately after meal intake. GLP-1 and GIP increase insulin biosynthesis and secretion from pancreatic beta cells in the presence of normal and elevated blood glucose levels. Furthermore, GLP-1 also reduces glucagon secretion from pancreatic alpha cells, resulting in a reduction in hepatic glucose output.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING GLYXAMBI tablets are available as follows: 10 mg/5 mg tablets: pale yellow, arc triangular, flat-faced, bevel-edged, film-coated tablets. One side is debossed with the Boehringer Ingelheim company symbol; the other side is debossed with "10/5". Bottles of 30 (NDC 0597-0182-30) Bottles of 90 (NDC 0597-0182-90) Cartons containing 3 blister cards of 10 tablets each (3 × 10) (NDC 0597-0182-39), institutional pack.
25 mg/5 mg tablets: pale pink, arc triangular, flat-faced, bevel-edged, film-coated tablets. One side is debossed with the Boehringer Ingelheim company symbol; the other side is debossed with "25/5". Bottles of 30 (NDC 0597-0164-30) Bottles of 90 (NDC 0597-0164-90) Cartons containing 3 blister cards of 10 tablets each (3 × 10) (NDC 0597-0164-39), institutional pack.
If repackaging is required, dispense in a tight container as defined in USP. Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📦 Storage and Handling ▾
Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION GLYXAMBI tablets for oral use contain: empagliflozin and linagliptin. Empagliflozin Empagliflozin is an inhibitor of the SGLT2. The chemical name of empagliflozin is D-Glucitol,1,5-anhydro-1-C-[4-chloro-3-[[4-[[(3S)-tetrahydro-3-furanyl]oxy]phenyl]methyl]phenyl]-, (1S).
The molecular formula is C 23 H 27 ClO 7 and the molecular weight is 450.91. The structural formula is: Empagliflozin is a white to yellowish, non-hygroscopic powder. It is very slightly soluble in water, sparingly soluble in methanol, slightly soluble in ethanol and acetonitrile, soluble in 50% acetonitrile/water, and practically insoluble in toluene.
Chemical Structure Linagliptin Linagliptin is an inhibitor of the DPP-4 enzyme. The chemical name of linagliptin is 1H-Purine-2,6-dione, 8-[(3R)-3-amino-1-piperidinyl]-7-(2-butyn-1-yl)-3,7-dihydro-3-methyl-1-[(4-methyl-2-quinazolinyl)methyl]- The molecular formula is C 25 H 28 N 8 O 2 and the molecular weight is 472.54. The structural formula is: Linagliptin is a white to yellowish, not or only slightly hygroscopic solid substance.
It is very slightly soluble in water. Linagliptin is soluble in methanol, sparingly soluble in ethanol, very slightly soluble in isopropanol, and very slightly soluble in acetone. Chemical Structure GLYXAMBI GLYXAMBI tablets are available in two dosage strengths containing 10 mg or 25 mg empagliflozin in combination with 5 mg linagliptin.
The inactive ingredients of GLYXAMBI are the following: Tablet Core: copovidone, corn starch, crospovidone, magnesium stearate, mannitol, pregelatinized starch, and talc. Coating: ferric oxide yellow (10 mg/5 mg) or ferric oxide red (25 mg/5 mg), hypromellose, mannitol, polyethylene glycol, talc, and titanium dioxide.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Diabetic Ketoacidosis in Patients with Type 1 Diabetes Mellitus and Other Ketoacidosis Inform patients that GLYXAMBI can cause potentially fatal ketoacidosis and that type 2 diabetes mellitus and pancreatic disorders (e.g., history of pancreatitis or pancreatic surgery) are risk factors. Educate all patients on precipitating factors (such as insulin dose reduction or missed insulin doses, infection, reduced caloric intake, ketogenic diet, surgery, dehydration, and alcohol abuse) and symptoms of ketoacidosis (including nausea, vomiting, abdominal pain, tiredness, and labored breathing).
Inform patients that blood glucose may be normal even in the presence of ketoacidosis. Advise patients that they may be asked to monitor ketones. If symptoms of ketoacidosis occur, instruct patients to discontinue GLYXAMBI and seek medical attention immediately [see Warnings and Precautions (5.1) ] .
Pancreatitis Inform patients that acute pancreatitis has been reported during use of linagliptin. Inform patients that persistent severe abdominal pain, sometimes radiating to the back, which may or may not be accompanied by vomiting, is the hallmark symptom of acute pancreatitis. Instruct patients to discontinue GLYXAMBI promptly and contact their healthcare provider if persistent severe abdominal pain occurs [see Warnings and Precautions (5.2) ] .
Volume Depletion Inform patients that symptomatic hypotension may occur with GLYXAMBI and advise them to contact their healthcare provider if they experience such symptoms [see Warnings and Precautions (5.3) ] . Inform patients that dehydration may increase the risk for hypotension, and to maintain adequate fluid intake. Genitourinary Infections, including Urosepsis, Pyelonephritis, Necrotizing Fasciitis of the Perineum (Fournier's Gangrene), and Genital Mycotic Infections Counsel patients that genitourinary infections may occur when taking empagliflozin, a component of GLYXAMBI, and may become serious.
Educate them on the symptoms and advise them to seek medical advice if symptoms occur. Specifically, advise patients to promptly seek medical attention if they develop pain or tenderness, redness, or swelling of the genitals or the area from the genitals back to the rectum, along with a fever above 100.4°F or malaise [see Warnings and Precautions (5.4) ] . Hypoglycemia with Concomitant Use with Insulin and Insulin Secretagogues Inform patients that the risk of hypoglycemia is increased when GLYXAMBI is used in combination with an insulin secretagogue (e.g., sulfonylurea) or insulin [see Warnings and Precautions (5.5) ] .
Lower Limb Amputation Counsel patients about the importance of routine preventative foot care. Instruct patients to monitor for new pain or tenderness, sores or ulcers, or infections involving the leg or foot and to seek medical advice immediately if such signs or symptoms develop [see Warnings and Precautions (5.6) ] . Hypersensitivity Reactions Inform patients that serious allergic reactions, such as anaphylaxis, angioedema, and exfoliative skin conditions, have been reported during postmarketing use of linagliptin or empagliflozin, components of GLYXAMBI.
If symptoms of allergic reactions (such as rash, skin flaking or peeling, urticaria, swelling of the skin, or swelling of the face, lips, tongue, and throat that may cause difficulty in breathing or swallowing) occur, patients must stop taking GLYXAMBI and seek medical advice promptly [see Warnings and Precautions (5.7) ] . Severe and Disabling Arthralgia Inform patients that severe and disabling joint pain may occur with this class of drugs. The time to onset of symptoms can range from one day to years.
Instruct patients to seek medical advice if severe joint pain occurs [see Warnings and Precautions (5.8) ] . Bullous Pemphigoid Inform patients that bullous pemphigoid has been reported during use of linagliptin. Instruct…
💬 Medication Guide ▾
MEDICATION GUIDE GLYXAMBI ® (glik-SAM-bee) (empagliflozin and linagliptin tablets) for oral use This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: January 2026 What is the most important information I should know about GLYXAMBI?
GLYXAMBI can cause serious side effects, including: Diabetic ketoacidosis (increased ketones in your blood or urine) in people with type 1 and other ketoacidosis. GLYXAMBI can cause ketoacidosis that can be life-threatening and may lead to death. Ketoacidosis is a serious condition which needs to be treated in a hospital.
People with type 1 diabetes have a high risk of getting ketoacidosis. People with type 2 diabetes or pancreas problems also have an increased risk of getting ketoacidosis. Ketoacidosis can also happen in people who: are sick, cannot eat or drink as usual, skip meals, are on a diet high in fat and low in carbohydrates (ketogenic diet), take less than the usual amount of insulin or miss insulin doses, drink too much alcohol, have a loss of too much fluid from the body (volume depletion), or who have surgery.
Ketoacidosis can happen even if your blood sugar is less than 250 mg/dL. Your healthcare provider may ask you to periodically check ketones in your urine or blood. Stop taking GLYXAMBI and call your healthcare provider or get medical help right away if you get any of the following.
If possible, check for ketones in your urine or blood, even if your blood sugar is less than 250 mg/dL: nausea vomiting stomach-area (abdominal) pain tiredness trouble breathing ketones in your urine or blood Inflammation of the pancreas (pancreatitis) which may be severe and lead to death. Certain medical problems make you more likely to get pancreatitis. Before you start taking GLYXAMBI, tell your healthcare provider if you have ever had: inflammation of your pancreas (pancreatitis) a history of alcoholism stones in your gallbladder (gallstones) high blood triglyceride levels Stop taking GLYXAMBI and call your healthcare provider right away if you have pain in your stomach area (abdomen) that is severe and will not go away.
The pain may be felt going from your abdomen to your back. The pain may happen with or without vomiting. These may be symptoms of pancreatitis.
Dehydration. GLYXAMBI can cause some people to become dehydrated (the loss of body water and salt). Dehydration may cause you to feel dizzy, faint, light-headed, or weak, especially when you stand up (orthostatic hypotension).
There have been reports of sudden worsening of kidney function in people who are taking GLYXAMBI. You may be at higher risk of dehydration if you: take medicines to lower your blood pressure, including diuretics (water pills) are on a low sodium (salt) diet have kidney problems are 65 years of age or older Talk to your healthcare provider about what you can do to prevent dehydration including how much fluid you should drink on a daily basis. Call your healthcare provider right away if you reduce the amount of food or liquid you drink, for example if you are sick or you cannot eat, or start to lose liquids from your body, for example from vomiting, diarrhea or being in the sun too long.
What is GLYXAMBI? GLYXAMBI is a prescription medicine that contains 2 diabetes medicines, empagliflozin (JARDIANCE) and linagliptin (TRADJENTA). GLYXAMBI can be used: along with diet and exercise to lower blood sugar (glucose) in adults with type 2 diabetes, in adults with type 2 diabetes who have known cardiovascular disease when empagliflozin (JARDIANCE), one of the medicines in GLYXAMBI, is needed to reduce the risk of cardiovascular death.
GLYXAMBI is not for use to lower blood sugar (glucose) in people with type 1 diabetes. It may increase their risk of diabetic ketoacidosis (increased ketones in blood or urine). If you have had pancreatitis in the past, it is not known if you have a higher chance of getting pancreatitis while you take GLYXAMBI.
GLYXAMBI is not for use to lower blood sugar (glu…