
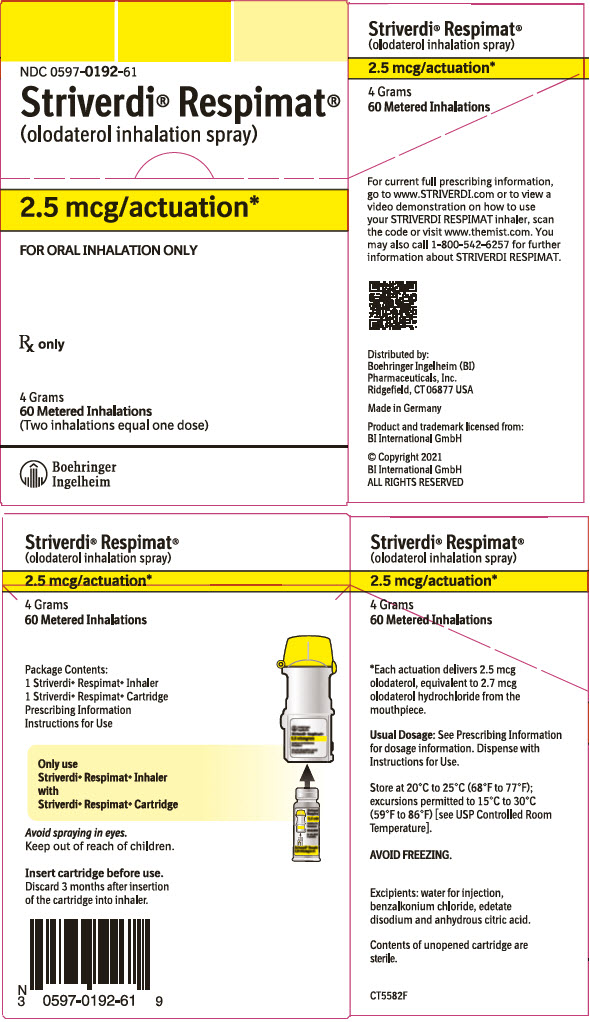
Striverdi Respimat olodaterol respimat inhalation spray 2.5 ug Spray, Metered
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the beta2-Adrenergic Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Striverdi Respimat is a maintenance inhaler — meaning it works in the background every day to keep your airways more open if you have COPD. It is not a rescue inhaler and won't act...
- What exactly is Striverdi Respimat used for, and will it help if I have a sudden attack?
- No, and this is really important — Striverdi Respimat is not approved for asthma, and using it alone for asthma can actually increase the risk of serious, life-threatening asthma e...
- I have asthma too — can I use this inhaler for both my COPD and my asthma?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per g | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $65.948 | — |
| Medicaid paysCMS SDUD · 12 mo | $65.54 | — |
| Medicare drug plans payPart D · Q2 2026 | $66.17 | — |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Striverdi Respimat 2.5 ugthis 00597-0192-61 | Boehringer | 1 cartridge | $65.948 | — | Availability likely | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 7727984 ↗ | Drug substance | — | Jan 19, 2027 |
Is there a generic version of STRIVERDI RESPIMAT INHAL SPRAY?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00597-0192-61 You're viewing this | 1 CARTRIDGE in 1 CARTON (0597-0192-61) / 60 SPRAY, METERED in 1 CARTRIDGE | 2014-08-01 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE STRIVERDI RESPIMAT Inhalation Spray is a long-acting beta 2 -adrenergic agonist (LABA) indicated for: The long-term, once-daily maintenance bronchodilator treatment of airflow obstruction in patients with chronic obstructive pulmonary disease (COPD), including chronic bronchitis and/or emphysema. ( 1.1 ) Important limitations: STRIVERDI RESPIMAT is NOT indicated to treat acute deterioration of COPD. ( 1.2 ) STRIVERDI RESPIMAT is NOT indicated to treat asthma.
( 1.2 )
1.1Maintenance Treatment of COPD STRIVERDI RESPIMAT is a long-acting beta 2 -agonist indicated for long-term, once-daily maintenance bronchodilator treatment of airflow obstruction in patients with chronic obstructive pulmonary disease (COPD), including chronic bronchitis and/or emphysema.
1.2Important Limitations of Use STRIVERDI RESPIMAT is not indicated to treat acute deteriorations of COPD [see Warnings and Precautions (5.2) ] . STRIVERDI RESPIMAT is not indicated to treat asthma. The safety and effectiveness of STRIVERDI RESPIMAT in asthma have not been established.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The recommended dosage of STRIVERDI RESPIMAT is two inhalations once-daily at the same time of the day. Do not use STRIVERDI RESPIMAT more than two inhalations every 24 hours. Prior to first use, the STRIVERDI RESPIMAT cartridge is inserted into the STRIVERDI RESPIMAT inhaler and the unit is primed.
When using the unit for the first time, patients are to actuate the inhaler toward the ground until an aerosol cloud is visible and then repeat the process three more times. The unit is then considered primed and ready for use. If not used for more than 3 days, patients are to actuate the inhaler once to prepare the inhaler for use.
If not used for more than 21 days, patients are to actuate the inhaler until an aerosol cloud is visible and then repeat the process three more times to prepare the inhaler for use [see Patient Counseling Information (17) ] . No dosage adjustment is required for geriatric patients, patients with mild and moderate hepatic impairment, or renally-impaired patients. There are no data available for use of STRIVERDI RESPIMAT in severe hepatically impaired patients [see Clinical Pharmacology (12.3) ].
For oral inhalation only. Two inhalations of STRIVERDI RESPIMAT once-daily at the same time of day. ( 2 )
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS STRIVERDI RESPIMAT consists of a STRIVERDI RESPIMAT inhaler and an aluminum cylinder (STRIVERDI RESPIMAT cartridge) containing olodaterol (as the hydrochloride). The STRIVERDI RESPIMAT cartridge is intended for use with the STRIVERDI RESPIMAT inhaler only. Each actuation from the STRIVERDI RESPIMAT inhaler delivers 2.5 mcg olodaterol (equivalent to 2.736 mcg olodaterol hydrochloride) from the mouthpiece.
Two actuations equal one dose. Inhalation spray: Each actuation from the mouthpiece delivers 2.5 mcg olodaterol (equivalent to 2.736 mcg olodaterol hydrochloride). Two actuations equal one dose.
( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Use of a LABA, including STRIVERDI RESPIMAT, without an inhaled corticosteroid is contraindicated in patients with asthma [see Warnings and Precautions (5.1) ] . STRIVERDI RESPIMAT is not indicated for the treatment of asthma. Use of a LABA, including STRIVERDI RESPIMAT, without an inhaled corticosteroid is contraindicated in patients with asthma. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS LABA as monotherapy (without an inhaled corticosteroid) for asthma increases the risk of serious asthma-related events. ( 5.1 ) Do not initiate STRIVERDI RESPIMAT in acutely deteriorating COPD patients. ( 5.2 ) Do not use for relief of acute symptoms.
Concomitant short-acting beta 2 -agonists can be used as needed for acute relief. ( 5.2 ) Do not exceed the recommended dosage. Excessive use of STRIVERDI RESPIMAT, or use in conjunction with other medications containing LABA can result in clinically significant cardiovascular effects and may be fatal.
( 5.3 ) Life-threatening paradoxical bronchospasm can occur. Discontinue STRIVERDI RESPIMAT immediately. ( 5.4 ) Use with caution in patients with cardiovascular or convulsive disorders, thyrotoxicosis or sensitivity to sympathomimetic drugs.
( 5.5 , 5.6 )
5.1Serious Asthma-Related Events – Hospitalizations, Intubations, Death The safety and efficacy of STRIVERDI RESPIMAT in patients with asthma have not been established. STRIVERDI RESPIMAT is not indicated for the treatment of asthma [see Contraindications (4) ] . Use of long-acting beta 2 -adrenergic agonists (LABA) as monotherapy [without inhaled corticosteroids (ICS)] for asthma is associated with an increased risk of asthma-related death.
Available data from controlled clinical trials also suggest that use of LABA as monotherapy increases the risk of asthma-related hospitalization in pediatric and adolescent patients. These findings are considered a class effect of LABA monotherapy. When LABA are used in fixed-dose combination with ICS, data from large clinical trials do not show a significant increase in the risk of serious asthma-related events (hospitalizations, intubations, death) compared with ICS alone.
A 28-week, placebo-controlled US study comparing the safety of another LABA (salmeterol) with placebo, each added to usual asthma therapy, showed an increase in asthma-related deaths in patients receiving salmeterol (13/13,176 in patients treated with salmeterol vs. 3/13,179 in patients treated with placebo; RR 4.37, 95% CI 1.25, 15.34). The increased risk of asthma-related death is considered a class effect of LABA, including STRIVERDI RESPIMAT.
No study adequate to determine whether the rate of asthma-related death is increased in patients treated with STRIVERDI RESPIMAT has been conducted. Available data do not suggest an increased risk of death with use of LABA in patients with COPD.
5.2Deterioration of Disease and Acute Episodes STRIVERDI RESPIMAT should not be initiated in patients with acutely deteriorating COPD, which may be a life-threatening condition. STRIVERDI RESPIMAT has not been studied in patients with acutely deteriorating COPD. The use of STRIVERDI RESPIMAT in this setting is inappropriate.
STRIVERDI RESPIMAT should not be used for the relief of acute symptoms, i.e., as rescue therapy for the treatment of acute episodes of bronchospasm. STRIVERDI RESPIMAT has not been studied in the relief of acute symptoms and extra doses should not be used for that purpose. Acute symptoms should be treated with an inhaled short-acting beta 2 -agonist.
When beginning STRIVERDI RESPIMAT, patients who have been taking inhaled, short-acting beta 2 -agonists on a regular basis (e.g., four times a day) should be instructed to discontinue the regular use of these drugs and use them only for symptomatic relief of acute respiratory symptoms. When prescribing STRIVERDI RESPIMAT, the healthcare provider should also prescribe an inhaled, short-acting beta 2 -agonist and instruct the patient on how it should be used. Increasing inhaled beta 2 -agonist use is a signal of deteriorating disease for which prompt medical attention is indicated.
COPD may deteriorate acutely over a period of hours or chronically over several days or longer. If STRIVERDI RESPIMAT no longer controls symptoms of bronchoconstriction, or the patient's inhaled, short-acting beta 2 -agonist becomes less effective or the patient needs…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Long-acting beta 2 -adrenergic agonists, such as STRIVERDI RESPIMAT, as monotherapy (without an inhaled corticosteroid) for asthma, increase the risk of asthma-related events. STRIVERDI RESPIMAT is not indicated for the treatment of asthma [see Warnings and Precautions (5.1) ] . Most common adverse reactions (incidence ≥2% and more than placebo) are nasopharyngitis, upper respiratory tract infection, bronchitis, urinary tract infection, cough, dizziness, rash, diarrhea, back pain and arthralgia.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Boehringer Ingelheim Pharmaceuticals, Inc. at 1-800-542-6257 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience in Chronic Obstructive Pulmonary Disease Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in practice. The STRIVERDI RESPIMAT clinical development program included seven dose-ranging trials and eight confirmatory trials. Four of the confirmatory trials were 6-week cross-over trials and four were 48-week parallel group trials.
Adverse reactions observed in the dose-ranging trials and four 6-week cross-over trials were consistent with those observed in the 48-week parallel group trials, which formed the primary safety database. The primary safety database consisted of pooled data from the four 48-week double-blind, active and placebo-controlled, parallel group confirmatory clinical trials. These trials included 3,104 adult COPD patients (77% males and 23% females) 40 years of age and older.
Of these patients, 876 and 883 patients were treated with STRIVERDI RESPIMAT 5 mcg and 10 mcg once-daily, respectively. The STRIVERDI RESPIMAT groups were composed of mostly Caucasians (66%) with a mean age of 64 years and a mean percent predicted FEV 1 at baseline of 44% for both the 5 mcg and 10 mcg treatment groups. Control arms for comparison included placebo in all four trials plus formoterol 12 mcg in two trials.
In these four clinical trials, seventy-two percent (72%) of patients exposed to any dose of STRIVERDI RESPIMAT reported an adverse reaction compared to 71% in the placebo group. The proportion of patients who discontinued due to an adverse reaction was 7.2% for STRIVERDI RESPIMAT treated patients compared to 8.8% for placebo treated patients. The adverse reaction most commonly leading to discontinuation was worsening COPD.
The most common serious adverse reactions were COPD exacerbation, pneumonia, and atrial fibrillation. Table 1 shows all adverse drug reactions reported by at least 2% of patients (and higher than placebo) who received STRIVERDI RESPIMAT 5 mcg during the 48-week trials. Table 1 Number and frequency of adverse drug reactions greater than 2% (and higher than placebo) in COPD patients exposed to STRIVERDI RESPIMAT 5 mcg: Pooled data from the four 48-week, double-blind, active- and placebo-controlled clinical trials in COPD patients 40 years of age and older Treatment STRIVERDI 5 mcg once-daily Placebo Body system (adverse drug reaction) n=876 n (%) n=885 n (%) *Rash includes a grouping of similar terms Infections and infestations Nasopharyngitis 99 (11.3) 68 (7.7) Upper Respiratory Tract Infection 72 (8.2) 66 (7.5) Bronchitis 41 (4.7) 32 (3.6) Urinary Tract Infection 22 (2.5) 9 (1.0) Respiratory, thoracic, and mediastinal disorders Cough 37 (4.2) 35 (4.0) Nervous system disorders Dizziness 20 (2.3) 19 (2.1) Skin and subcutaneous tissue disorders Rash* 19 (2.2) 10 (1.1) Gastrointestinal disorders Diarrhea 25 (2.9) 22 (2.5) Musculoskeletal and connective tissue disorders Back Pain 31 (3.5) 24 (2.7) Arthralgia 18 (2.1) 7 (0.8) Additional adverse reactions that occurred in greater than 2% (and higher than placebo) of patients exposed to STRIVERDI RESPIMAT 10 mcg were pneumonia, constipation, and pyrexia.
Lung ca…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Other adrenergic drugs may potentiate effect. Use with caution. ( 5.3 , 7.1 ) Xanthine derivatives, steroids, diuretics or non-potassium sparing diuretics may potentiate hypokalemia or ECG changes.
Use with caution. ( 7.2 , 7.3 ) MAO inhibitors, tricyclic antidepressants, and drugs that prolong QTc interval may potentiate effect on cardiovascular system. Use with extreme caution.
( 7.4 ) Beta-blockers may decrease effectiveness. Use with caution and only when medically necessary. ( 7.5 )
7.1Adrenergic Drugs If additional adrenergic drugs are to be administered by any route, they should be used with caution because the sympathetic effects of STRIVERDI RESPIMAT may be potentiated [see Warnings and Precautions (5.3 , 5.5 , 5.6 , 5.7) ] .
7.2Xanthine Derivatives, Steroids, or Diuretics Concomitant treatment with xanthine derivatives, steroids, or diuretics may potentiate any hypokalemic effect of STRIVERDI RESPIMAT [see Warnings and Precautions (5.7) ] .
7.3Non-Potassium Sparing Diuretics The ECG changes and/or hypokalemia that may result from the administration of non-potassium sparing diuretics (such as loop or thiazide diuretics) can be acutely worsened by beta-agonists, especially when the recommended dosage of the beta-agonist is exceeded. Although the clinical significance of these effects is not known, caution is advised in the co-administration of beta-agonists with non-potassium-sparing diuretics.
7.4Monoamine Oxidase Inhibitors, Tricyclic Antidepressants, QTc Prolonging Drugs STRIVERDI RESPIMAT, as with other beta 2 -agonists, should be administered with extreme caution to patients being treated with monoamine oxidase inhibitors or tricyclic antidepressants or other drugs known to prolong the QTc interval because the action of adrenergic agonists on the cardiovascular system may be potentiated by these agents. Drugs that are known to prolong the QTc interval may be associated with an increased risk of ventricular arrhythmias.
7.5Beta-Blockers Beta-adrenergic receptor antagonists (beta-blockers) and STRIVERDI RESPIMAT may interfere with the effect of each other when administered concurrently. Beta-blockers not only block the therapeutic effects of beta-agonists, but may produce severe bronchospasm in COPD patients. Therefore, patients with COPD should not normally be treated with beta-blockers.
However, under certain circumstances, e.g. as prophylaxis after myocardial infarction, there may be no acceptable alternatives to the use of beta-blockers in patients with COPD. In this setting, cardioselective beta-blockers could be considered, although they should be administered with caution.
7.6Inhibitors of Cytochrome P450 and P-gp Efflux Transporter In a drug interaction study using the strong dual CYP and P-gp inhibitor ketoconazole, a 1.7-fold increase of maximum plasma concentrations and AUC was observed [see Clinical Pharmacology (12.3) ] . STRIVERDI RESPIMAT was evaluated in clinical trials for up to one year at doses up to twice the recommended therapeutic dosage. No dosage adjustment is necessary.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no adequate and well-controlled clinical studies with STRIVERDI RESPIMAT in pregnant women to inform of drug-associated risk of adverse pregnancy-related outcomes. There are clinical considerations with the use of STRIVERDI RESPIMAT in pregnant women (see Clinical Considerations ) . Based on animal studies, olodaterol was not teratogenic when administered to pregnant rats or rabbits during organogenesis at inhalation doses of approximately 2,731 or 1,353 times the maximum recommended human daily inhalation dose (MRHDID) (on an AUC basis) in rats or rabbits, respectively (see Data ).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Labor and Delivery There are no adequate and well-controlled human studies that have investigated the effects of STRIVERDI RESPIMAT during labor and delivery. Because of the potential for beta-agonist interference with uterine contractility, use of STRIVERDI RESPIMAT during labor should be restricted to those patients in whom the benefits clearly outweigh the risks. Data Animal Data STRIVERDI RESPIMAT was not teratogenic in rats at inhalation doses approximately 2,731 times the MRHDID (on an AUC basis at a maternal inhalation dose of 1,054 mcg/kg/day).
No significant effects occurred in rabbits at inhalation doses approximately 1,353 times the MRHDID in adults (on an AUC basis at a maternal inhalation dose of 974 mcg/kg/day). Placental transfer of olodaterol was observed in pregnant rats. Olodaterol has been shown to be teratogenic in New Zealand rabbits at inhalation doses approximately 7,130 times the MRHDID in adults (on an AUC basis at a maternal inhalation dose of 2,489 mcg/kg/day).
STRIVERDI RESPIMAT exhibited the following fetal toxicities: enlarged or small heart atria or ventricles, eye abnormalities, and split or distorted sternum.
8.2Lactation Risk Summary There are no available data on the presence of olodaterol in human milk, the effects on the breastfed infant, or the effects on milk production. Olodaterol, the active component of STRIVERDI RESPIMAT, and/or its metabolites are present in the milk of lactating rats, however, due to species-specific differences in lactation physiology, the clinical relevance of these data are not clear (see Data ) . The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for STRIVERDI RESPIMAT and any potential adverse effects on the breastfed child from STRIVERDI RESPIMAT or from the underlying maternal condition.
Data The distribution of olodaterol into milk was investigated after a single intravenous administration of 0.4 μmol/kg to lactating rats. Olodaterol and/or its metabolites are present in the milk of lactating rats at concentrations above those in plasma.
8.4Pediatric Use STRIVERDI RESPIMAT is not indicated for use in children. The safety and effectiveness of STRIVERDI RESPIMAT in the pediatric population have not been established.
8.5Geriatric Use Based on available data, no adjustment of STRIVERDI RESPIMAT dosage in geriatric patients is necessary. Of the 876 patients who received STRIVERDI RESPIMAT at the recommended dose of 5 mcg once-daily in the clinical studies from the pooled 1-year database, 485 were less than or equal to 65 years of age and 391 (44.6%) were greater than 65 years of age. No overall differences in effectiveness were observed, and in the 1-year pooled data, the adverse drug reaction profiles were similar in the older population compared to the patient population overall.
8.6 Hepatic Impairment Subjects with mild and moderate hepatic impairment showe…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate and well-controlled clinical studies with STRIVERDI RESPIMAT in pregnant women to inform of drug-associated risk of adverse pregnancy-related outcomes. There are clinical considerations with the use of STRIVERDI RESPIMAT in pregnant women (see Clinical Considerations ) . Based on animal studies, olodaterol was not teratogenic when administered to pregnant rats or rabbits during organogenesis at inhalation doses of approximately 2,731 or 1,353 times the maximum recommended human daily inhalation dose (MRHDID) (on an AUC basis) in rats or rabbits, respectively (see Data ).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Labor and Delivery There are no adequate and well-controlled human studies that have investigated the effects of STRIVERDI RESPIMAT during labor and delivery. Because of the potential for beta-agonist interference with uterine contractility, use of STRIVERDI RESPIMAT during labor should be restricted to those patients in whom the benefits clearly outweigh the risks. Data Animal Data STRIVERDI RESPIMAT was not teratogenic in rats at inhalation doses approximately 2,731 times the MRHDID (on an AUC basis at a maternal inhalation dose of 1,054 mcg/kg/day).
No significant effects occurred in rabbits at inhalation doses approximately 1,353 times the MRHDID in adults (on an AUC basis at a maternal inhalation dose of 974 mcg/kg/day). Placental transfer of olodaterol was observed in pregnant rats. Olodaterol has been shown to be teratogenic in New Zealand rabbits at inhalation doses approximately 7,130 times the MRHDID in adults (on an AUC basis at a maternal inhalation dose of 2,489 mcg/kg/day).
STRIVERDI RESPIMAT exhibited the following fetal toxicities: enlarged or small heart atria or ventricles, eye abnormalities, and split or distorted sternum.
🧒 Pediatric Use ▾
8.4Pediatric Use STRIVERDI RESPIMAT is not indicated for use in children. The safety and effectiveness of STRIVERDI RESPIMAT in the pediatric population have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Based on available data, no adjustment of STRIVERDI RESPIMAT dosage in geriatric patients is necessary. Of the 876 patients who received STRIVERDI RESPIMAT at the recommended dose of 5 mcg once-daily in the clinical studies from the pooled 1-year database, 485 were less than or equal to 65 years of age and 391 (44.6%) were greater than 65 years of age. No overall differences in effectiveness were observed, and in the 1-year pooled data, the adverse drug reaction profiles were similar in the older population compared to the patient population overall.
🆘 Overdosage ▾
10 OVERDOSAGE The expected signs and symptoms with overdosage of STRIVERDI RESPIMAT are those of excessive beta-adrenergic stimulation and occurrence or exaggeration of any of the signs and symptoms, e.g., myocardial ischemia, angina pectoris, hypertension or hypotension, tachycardia, arrhythmias, palpitations, dizziness, nervousness, insomnia, anxiety, headache, tremor, dry mouth, muscle spasms, nausea, fatigue, malaise, hypokalemia, hyperglycemia, and metabolic acidosis. As with all inhaled sympathomimetic medications, cardiac arrest and even death may be associated with an overdose of STRIVERDI RESPIMAT.
Treatment of overdosage consists of discontinuation of STRIVERDI RESPIMAT together with institution of appropriate symptomatic and supportive therapy. The judicious use of a cardioselective beta-receptor blocker may be considered, bearing in mind that such medication can produce bronchospasm. There is insufficient evidence to determine if dialysis is beneficial for overdosage of STRIVERDI RESPIMAT.
Cardiac monitoring is recommended in cases of overdosage.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Olodaterol is a long-acting beta 2 -adrenergic agonist (LABA). The compound exerts its pharmacological effects by binding and activation of beta 2 -adrenoceptors after topical administration by inhalation. Activation of these receptors in the airways results in a stimulation of intracellular adenyl cyclase, an enzyme that mediates the synthesis of cyclic-3', 5' adenosine monophosphate (cAMP).
Elevated levels of cAMP induce bronchodilation by relaxation of airway smooth muscle cells. In vitro studies have shown that olodaterol has 241-fold greater agonist activity at beta 2 -adrenoceptors compared to beta 1 -adrenoceptors and 2,299-fold greater agonist activity compared to beta 3 -adrenoceptors. The clinical significance of these findings is unknown.
Beta-adrenoceptors are divided into three subtypes: beta 1 -adrenoceptors predominantly expressed on cardiac smooth muscle, beta 2 -adrenoceptors predominantly expressed on airway smooth muscle, and beta 3 -adrenoceptors predominantly expressed on adipose tissue. Beta 2 -agonists cause bronchodilation. Although the beta 2 -adrenoceptor is the predominant adrenergic receptor in the airway smooth muscle, it is also present on the surface of a variety of other cells, including lung epithelial and endothelial cells and in the heart.
The precise function of beta 2 -receptors in the heart is not known, but their presence raises the possibility that even highly selective beta 2 -agonists may have cardiac effects.
12.2Pharmacodynamics Systemic Safety The major adverse effects of inhaled beta 2 -adrenergic agonists occur as a result of excessive activation of systemic beta-adrenergic receptors. The most common adverse effects in adults include skeletal muscle tremor and cramps, insomnia, tachycardia, decreases in serum potassium, and increases in plasma glucose. Changes in serum potassium were evaluated in COPD patients in double-blind phase 3 studies.
In pooled data, at the recommended 5 mcg dose there was no clinically relevant change compared to placebo in serum potassium. Cardiac Electrophysiology The effect of STRIVERDI RESPIMAT on the QT/QTc interval of the ECG was investigated in 24 healthy male and female volunteers in a double-blind, randomized, placebo- and active (moxifloxacin)- controlled study at single doses of 10, 20, 30, and 50 mcg. Dose-dependent QTcI (individual subject corrected QT interval) prolongation was observed.
The maximum mean (one-sided 95% upper confidence bound) difference in QTcI from placebo after baseline correction was 2.5 (5.6) ms, 6.1 (9.2) ms, 7.5 (10.7) ms and 8.5 (11.6) ms following doses of 10, 20, 30 and 50 mcg, respectively. The effect of 5 mcg and 10 mcg STRIVERDI RESPIMAT on heart rate and rhythm was assessed using continuous 24-hour ECG recording (Holter monitoring) in a subset of 772 patients in the 48-week, placebo-controlled phase 3 trials. There were no dose- or time-related trends or patterns observed for the magnitudes of mean changes in heart rate or premature beats.
Shifts from baseline to the end of treatment in premature beats did not indicate meaningful differences between STRIVERDI RESPIMAT 5 mcg, 10 mcg, and placebo.
12.3Pharmacokinetics Olodaterol showed linear pharmacokinetics. On repeated once-daily inhalation steady-state of olodaterol plasma concentrations was achieved after 8 days, and the extent of exposure was increased up to 1.8-fold as compared to a single dose. Absorption Olodaterol reaches maximum plasma concentrations generally within 10 to 20 minutes following drug inhalation.
In healthy volunteers, the absolute bioavailability of olodaterol following inhalation was estimated to be approximately 30%, whereas the absolute bioavailability was below 1% when given as an oral solution. Thus, the systemic availability of olodaterol after inhalation is mainly determined by lung absorption, while any swallowed portion of the dose only negligibly contributes to systemic exposur…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Olodaterol is a long-acting beta 2 -adrenergic agonist (LABA). The compound exerts its pharmacological effects by binding and activation of beta 2 -adrenoceptors after topical administration by inhalation. Activation of these receptors in the airways results in a stimulation of intracellular adenyl cyclase, an enzyme that mediates the synthesis of cyclic-3', 5' adenosine monophosphate (cAMP).
Elevated levels of cAMP induce bronchodilation by relaxation of airway smooth muscle cells. In vitro studies have shown that olodaterol has 241-fold greater agonist activity at beta 2 -adrenoceptors compared to beta 1 -adrenoceptors and 2,299-fold greater agonist activity compared to beta 3 -adrenoceptors. The clinical significance of these findings is unknown.
Beta-adrenoceptors are divided into three subtypes: beta 1 -adrenoceptors predominantly expressed on cardiac smooth muscle, beta 2 -adrenoceptors predominantly expressed on airway smooth muscle, and beta 3 -adrenoceptors predominantly expressed on adipose tissue. Beta 2 -agonists cause bronchodilation. Although the beta 2 -adrenoceptor is the predominant adrenergic receptor in the airway smooth muscle, it is also present on the surface of a variety of other cells, including lung epithelial and endothelial cells and in the heart.
The precise function of beta 2 -receptors in the heart is not known, but their presence raises the possibility that even highly selective beta 2 -agonists may have cardiac effects.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING STRIVERDI RESPIMAT Inhalation Spray is supplied in a labeled carton containing one STRIVERDI RESPIMAT cartridge and one STRIVERDI RESPIMAT inhaler. The STRIVERDI RESPIMAT cartridge is an aluminum cylinder with a tamper protection seal on the cap. The STRIVERDI RESPIMAT cartridge is only intended for use with the STRIVERDI RESPIMAT inhaler.
The STRIVERDI RESPIMAT inhaler is a cylindrical-shaped plastic inhalation device with a gray-colored body and a clear base. The clear base is removed to insert the cartridge. The inhaler contains a dose indicator.
The yellow colored cap and the written information on the label of the gray inhaler body indicates that it is labeled for use with the STRIVERDI RESPIMAT cartridge. STRIVERDI RESPIMAT Inhalation Spray is available as: STRIVERDI RESPIMAT Inhalation Spray: 60 metered actuations (NDC 0597-0192-61) The STRIVERDI RESPIMAT cartridge has a net fill weight of at least 4 grams and when used with the STRIVERDI RESPIMAT inhaler, is designed to deliver the labeled number of metered actuations after preparation for use. When the labeled number of metered actuations has been dispensed from the inhaler, the STRIVERDI RESPIMAT locking mechanism will be engaged and no more actuations can be dispensed.
After assembly, the STRIVERDI RESPIMAT inhaler should be discarded at the latest 3 months after first use or when the locking mechanism is engaged, whichever comes first. Keep out of reach of children. Do not spray into eyes.
Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Avoid freezing.
📦 Storage and Handling ▾
Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Avoid freezing.
📋 Description ▾
11 DESCRIPTION The active moiety olodaterol is a selective beta 2 -adrenergic bronchodilator. The drug substance, olodaterol hydrochloride, is chemically described as 2H-1,4-Benzoxazin-3H(4H)-one, 6-hydroxy-8-[(1R)-1-hydroxy-2-[[2-(4-methoxyphenyl)-1,1-dimethylethyl]-amino]ethyl]-, monohydrochloride. Olodaterol hydrochloride is a white to off-white powder that is sparingly-slightly soluble in water and slightly soluble in ethanol.
The molecular weight is 422.9 g/mole (salt): 386.5 g/mole (base), and the molecular formula is C 21 H 26 N 2 O 5 × HCl as a hydrochloride. The conversion factor from salt to free base is 1.094. The structural formula is: The drug product, STRIVERDI RESPIMAT, is composed of a sterile, aqueous solution of olodaterol hydrochloride filled into a 4.5 mL plastic container crimped into an aluminum cylinder (STRIVERDI RESPIMAT cartridge) for use with the STRIVERDI RESPIMAT inhaler.
Excipients include anhydrous citric acid, benzalkonium chloride, edetate disodium, and water for injection. The STRIVERDI RESPIMAT cartridge is only intended for use with the STRIVERDI RESPIMAT inhaler. The STRIVERDI RESPIMAT inhaler is a hand held, pocket sized oral inhalation device that uses mechanical energy to generate a slow-moving aerosol cloud of medication from a metered volume of the drug solution.
The STRIVERDI RESPIMAT inhaler has a yellow-colored cap. When used with the STRIVERDI RESPIMAT inhaler, each cartridge containing a minimum of 4 grams of a sterile aqueous solution delivers the labeled number of metered actuations after preparation for use. Each dose (one dose equals two actuations) from the STRIVERDI RESPIMAT inhaler delivers 5 mcg olodaterol (equivalent to 5.473 mcg olodaterol hydrochloride) in 22.1 mcL of solution from the mouthpiece.
As with all inhaled drugs, the actual amount of drug delivered to the lung may depend on patient factors, such as the coordination between the actuation of the inhaler and inspiration through the delivery system. The duration of inspiration should be at least as long as the spray duration (1.5 seconds). Prior to first use, the STRIVERDI RESPIMAT cartridge is inserted into the STRIVERDI RESPIMAT inhaler and the unit is primed.
When using for the first time, patients are to actuate the inhaler toward the ground until an aerosol cloud is visible and then repeat the process three more times. The unit is then considered primed and ready for use. If not used for more than 3 days, patients are to actuate the inhaler once to prepare the inhaler for use.
If not used for more than 21 days, patients are to actuate the inhaler until an aerosol cloud is visible and then repeat the process three more times to prepare the inhaler for use [see Patient Counseling Information (17) ] . Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use). Serious Asthma-Related Events Inform patients that LABA, such as STRIVERDI RESPIMAT, when used as monotherapy [without an inhaled corticosteroid], increase the risk of serious asthma-related events, including asthma-related death. STRIVERDI RESPIMAT is not indicated for the treatment of asthma.
Not for Acute Symptoms STRIVERDI RESPIMAT is not meant to relieve acute asthma symptoms or exacerbations of COPD and extra doses should not be used for that purpose. Acute symptoms should be treated with an inhaled, short-acting beta 2 -agonist such as albuterol. (The healthcare provider should provide the patient with such medication and instruct the patient in how it should be used.) Instruct patients to notify their physician immediately if they experience any of the following: Worsening of symptoms Decreasing effectiveness of inhaled, short-acting beta 2 -agonists Need for more inhalations than usual of inhaled, short-acting beta 2 -agonists Significant decrease in lung function as outlined by the physician Instruct patients not to stop therapy with STRIVERDI RESPIMAT without physician/provider guidance since symptoms may recur after discontinuation.
Do Not Use Additional Long-Acting Beta 2 -Agonists Patients who have been taking inhaled, short-acting beta 2 -agonists on a regular basis should be instructed to discontinue the regular use of these products and use them only for the symptomatic relief of acute symptoms. When patients are prescribed STRIVERDI RESPIMAT, other inhaled medications containing long-acting beta 2 -agonists should not be used. Patients should not use more than the recommended once-daily dosage of STRIVERDI RESPIMAT.
Excessive use of sympathomimetics may cause significant cardiovascular effects, and may be fatal. Risks Associated with Beta 2 -Agonist Therapy Inform patients of adverse effects associated with beta 2 -agonists, such as palpitations, chest pain, rapid heart rate, tremor, or nervousness. Paradoxical Bronchospasm Inform patients that STRIVERDI RESPIMAT can produce paradoxical bronchospasm.
Advise patients that if paradoxical bronchospasm occurs, patients should discontinue STRIVERDI RESPIMAT. Hypersensitivity Reactions Inform patients that immediate hypersensitivity reactions, including angioedema, may occur after administration of STRIVERDI RESPIMAT. Advise patient to immediately discontinue STRIVERDI RESPIMAT and consult a physician.
Instructions for Administering STRIVERDI RESPIMAT It is important for patients to understand how to correctly administer STRIVERDI RESPIMAT inhalation spray using the STRIVERDI RESPIMAT inhaler. Instruct patients that STRIVERDI RESPIMAT inhalation spray should only be administered via the STRIVERDI RESPIMAT inhaler and the STRIVERDI RESPIMAT inhaler should not be used for administering other medications. Instruct patients that priming STRIVERDI RESPIMAT is essential to ensure appropriate content of the medication in each actuation.
When using the unit for the first time, the STRIVERDI RESPIMAT cartridge is inserted into the STRIVERDI RESPIMAT inhaler and the unit is primed. STRIVERDI RESPIMAT patients are to actuate the inhaler toward the ground until an aerosol cloud is visible and then repeat the process three more times. The unit is then considered primed and ready for use.
If not used for more than 3 days, patients are to actuate the inhaler once to prepare the inhaler for use. If not used for more than 21 days, patients are to actuate the inhaler until an aerosol cloud is visible and then repeat the process three more times to prepare the inhaler for use.