
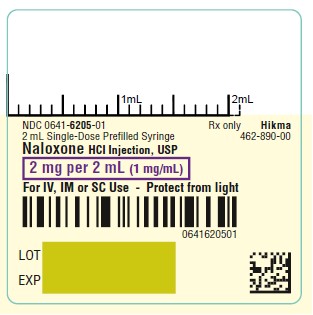
Naloxone Hydrochloride 1 mg/mL Injection — NDC 0641-6205-10 (Billing 00641-6205-10)
This is a package of Naloxone Hydrochloride 1 mg/mL Injection from Hikma Pharmaceuticals USA Inc., marketed since Jun 2022 and currently FDA-listed; retail pharmacies pay about $12.74 per mL (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0641-6205-10 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0641 labeler · 6205 product · 10 package
- Package marketed since
- Jun 10, 2022
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 0641620510 8
- Medicaid fills, this package
- 254 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 004514
- GCN: 17142
- GPI-14 (Medi-Span): 9340002010E540
- HICL (First Databank): 001874
- AHFS class code: 28:10.00.00
- RxCUI (RxNorm): 1191250
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Opioid Antagonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It is an emergency medicine that reverses an opioid overdose. Signs include very slow or stopped breathing and being unresponsive. Some injection forms have extra hospital or milit...
- Follow the instructions that came with your product. Nasal sprays go into one nostril. Zimhi goes into the outer thigh. Call 911 right away. If the person does not wake up or slips...
- Naloxone can wear off before the opioid does. Breathing problems can come back. Stay with the person until emergency help arrives.
- Why do I still need to call 911 if they wake up?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Naloxone Hydrochloride — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $12.741 | $254.82 / 20 ml |
| Medicaid paysCMS SDUD · 12 mo | $18.61 | $372.19 / 20 ml |
| Medicare drug plans payPart D · Q2 2026 | $11.23 | $224.69 / 20 ml |
| Medicare Part B allowsASP · J2312 | $0.069 / J2312 unit | — |
Where does this data come from?
- CMS NADAC weekly file · file of Oct 7, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Oct 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00641-6205-10 You're viewing this Main listing | 10 SYRINGE in 1 CARTON / 2 mL in 1 SYRINGE | 2022-06-10 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Naloxone Hydrochloride 1 mg/mL 42023-0224-01 | Par | 1 syringe | $6.271 | AP | Availability likely | save 51% |
| Naloxone Hydrochloride 1 mg/mL 43598-0750-11 | Dr. | 1 syringe | $6.271 | AP | Availability likely | save 51% |
| Naloxone Hydrochloride 1 mg/mL 55150-0345-01 | Eugia | 1 syringe | $6.271 | AP | Availability likely | save 51% |
| Naloxone Hydrochloride 1 mg/mL 67457-0992-02 | Mylan | 1 syringe | $6.271 | AP | Availability likely | save 51% |
| Naloxone Hydrochloride 1 mg/mLthis 00641-6205-10 | Hikma | 10 syringes | $12.741 | AP | Availability likely | — |
| naloxone hydrochloride 1 mg/mL 43066-0142-10 | Baxter | 1 syringe | $12.741 | AP | Availability likely | — |
| Naloxone Hydrochloride 1 mg/mL 76329-1469-01 | International | 10 syringes | $12.741 | AP | Availability likely | — |
| Naloxone Hydrochloride 1 mg/mL 76329-3369-01 | International | 10 syringes | $12.741 | AP | Availability likely | — |
| Naloxone Hydrochloride 1 mg/mL 76329-3469-01 | International | 10 syringes | $12.741 | AP | Availability likely | — |
| Naloxone Hydrochloride 1 mg/mL 00404-9922-02 | Henry | 1 syringe | — | AP | FDA listed | — |
| Naloxone Hydrochloride 1 mg/mL 51662-1239-01 | HF | 1 syringe | — | AP | FDA listed | — |
| Naloxone Hydrochloride 1 mg/mL 51662-1529-01 | HF | 1 syringe | — | AP | FDA listed | — |
| Naloxone Hydrochloride 1 mg/mL 51662-1586-01 | HF | 1 syringe | — | AP | FDA listed | — |
| Naloxone Hydrochloride 1 mg/mL 51662-1690-03 | HF | 10 pouches | — | AP | FDA listed | — |
| Naloxone Hydrochloride 1 mg/mL 54288-0124-01 | BPI | 2 ml | — | AP | FDA listed | — |
| Naloxone Hydrochloride 1 mg/mL 70518-2725-00 | REMEDYREPACK | 10 syringes | — | AP | FDA listed | — |
| Naloxone Hydrochloride 1 mg/mL 71872-7177-01 | Medical | 1 syringe | — | AP | FDA listed | — |
| Naloxone Hydrochloride 1 mg/mL 71872-7294-01 | Medical | 1 syringe | — | AP | FDA listed | — |
| Naloxone Hydrochloride 1 mg/mL 71872-7299-01 | Medical | 1 syringe | — | AP | FDA listed | — |
| Naloxone Hydrochloride 1 mg/mL 76045-0112-20 | Fresenius | 24 syringes | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Oct 7, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Naloxone inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
8.35 mg / 1 mL
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Hikma Pharmaceuticals USA Inc. labeler code 00641
- Naloxone Hydrochloride .4 mg/mL Injection NDC 0641-6193-10
- PROPOFOL 10 mg/mL Injection, Emulsion NDC 0641-6194-10
- PROPOFOL 10 mg/mL Injection, Emulsion NDC 0641-6195-20
- PROPOFOL 10 mg/mL Injection, Emulsion NDC 0641-6196-10
- Heparin Sodium 5000 [USP'U]/mL Injection NDC 0641-6199-10
- Heparin Sodium 5000 [USP'U]/.5mL Injection NDC 0641-6204-10
- Hydromorphone Hydrochloride .5 mg/.5mL Injection NDC 0641-6206-10
- Lorazepam 2 mg/mL Injection NDC 0641-6207-25
- Promethazine Hydrochloride 25 mg/mL Injection NDC 0641-6208-25
- Midazolam 1 mg/mL Injection NDC 0641-6209-25
- Midazolam 1 mg/mL Injection NDC 0641-6210-10
- Midazolam 5 mg/mL Injection NDC 0641-6211-10
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Naloxone hydrochloride injection is indicated for the complete or partial reversal of opioid depression, including respiratory depression, induced by natural and synthetic opioids including propoxyphene, methadone, and certain mixed agonist-antagonist analgesics: nalbuphine, pentazocine, butorphanol, and cyclazocine. Naloxone hydrochloride is also indicated for the diagnosis of suspected or known acute opioid overdosage. Naloxone may be useful as an adjunctive agent to increase blood pressure in the management of septic shock (see CLINICAL PHARMACOLOGY, Adjunctive Use in Septic Shock ).
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Naloxone Hydrochloride Injection, USP may be administered intravenously, intramuscularly, or subcutaneously. The most rapid onset of action is achieved by intravenous administration which is recommended in emergency situations. Since the duration of action of some opioids may exceed that of naloxone, the patient should be kept under continued surveillance.
Repeated doses of naloxone should be administered, as necessary. Intravenous Infusion: Naloxone Hydrochloride Injection, USP may be diluted for intravenous infusion in 0.9% sodium chloride injection or 5% dextrose injection. The addition of 2 mg of naloxone hydrochloride in 500 mL of either solution provides a concentration of 0.004 mg/mL.
Mixtures should be used within 24 hours. After 24 hours, the remaining unused solution must be discarded. The rate of administration should be titrated in accordance with the patient’s response.
Naloxone Hydrochloride Injection, USP should not be mixed with preparations containing bisulfite, metabisulfite, long-chain or high molecular weight anions, or any solution having an alkaline pH. No drug or chemical agent should be added to Naloxone Hydrochloride Injection, USP unless its effect on the chemical and physical stability of the solution has first been established. General: Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration whenever solution and container permit.
Usage in Adults Opioid Overdose - Known or Suspected: An initial dose of 0.4 mg to 2 mg of naloxone hydrochloride may be administered intravenously. If the desired degree of counteraction and improvement in respiratory functions is not obtained, it may be repeated at 2- to 3-minute intervals. If no response is observed after 10 mg of naloxone hydrochloride have been administered, the diagnosis of opioid-induced or partial opioid-induced toxicity should be questioned.
Intramuscular or subcutaneous administration may be necessary if the intravenous route is not available. Postoperative Opioid Depression: For the partial reversal of opioid depression following the use of opioids during surgery, smaller doses of naloxone hydrochloride are usually sufficient. The dose of naloxone should be titrated according to the patient’s response.
For the initial reversal of respiratory depression, naloxone hydrochloride should be injected in increments of 0.1 to 0.2 mg intravenously at two- to three-minute intervals to the desired degree of reversal, i.e., adequate ventilation and alertness without significant pain or discomfort. Larger than necessary dosage of naloxone may result in significant reversal of analgesia and increase in blood pressure. Similarly, too rapid reversal may induce nausea, vomiting, sweating or circulatory stress.
Repeat doses of naloxone may be required within one- to two-hour intervals depending upon the amount, type (i.e., short or long acting) and time interval since last administration of opioid. Supplemental intramuscular doses have been shown to produce a longer lasting effect. Septic Shock: The optimal dosage of naloxone or duration of therapy for the treatment of hypotension in septic shock patients has not been established (see CLINICAL PHARMACOLOGY ).
Usage in Children Opioid Overdose - Known or Suspected: The usual initial dose in pediatric patients is 0.01 mg/kg body weight given intravenously. If this dose does not result in the desired degree of clinical improvement, a subsequent dose of 0.1 mg/kg body weight may be administered. If an intravenous route of administration is not available, naloxone hydrochloride may be administered intramuscularly or subcutaneously in divided doses.
If necessary, Naloxone Hydrochloride Injection, USP can be diluted with sterile water for injection. Postoperative Opioid Depression: Follow the recommendations and cautions under Usage in Adults, Postoperative Opioid Depression . For the initial reversal of respiratory depression, nalo… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Naloxone hydrochloride injection is contraindicated in patients known to be hypersensitive to naloxone hydrochloride or to any of the other ingredients contained in the formulation.
⚠️ Warnings ▾
WARNINGS Drug Dependence Naloxone hydrochloride injection should be administered cautiously to persons, including newborns of mothers, who are known or suspected to be physically dependent on opioids. In such cases, an abrupt and complete reversal of opioid effects may precipitate an acute withdrawal syndrome. The signs and symptoms of opioid withdrawal in a patient physically dependent on opioids may include, but are not limited to, the following: body aches, diarrhea, tachycardia, fever, runny nose, sneezing, piloerection, sweating, yawning, nausea or vomiting, nervousness, restlessness or irritability, shivering or trembling, abdominal cramps, weakness, and increased blood pressure.
In the neonate, opioid withdrawal may also include convulsions, excessive crying, and hyperactive reflexes. Repeat Administration The patient who has satisfactorily responded to naloxone should be kept under continued surveillance and repeated doses of naloxone should be administered, as necessary, since the duration of action of some opioids may exceed that of naloxone. Respiratory Depression Due to Other Drugs Naloxone is not effective against respiratory depression due to non-opioid drugs and in the management of acute toxicity caused by levopropoxyphene.
Reversal of respiratory depression by partial agonists or mixed agonist/antagonists, such as buprenorphine and pentazocine, may be incomplete or require higher doses of naloxone. If an incomplete response occurs, respirations should be mechanically assisted as clinically indicated.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Postoperative The following adverse events have been associated with the use of naloxone hydrochloride injection in postoperative patients: hypotension, hypertension, ventricular tachycardia and fibrillation, dyspnea, pulmonary edema, and cardiac arrest. Death, coma, and encephalopathy have been reported as sequelae of these events. Excessive doses of naloxone in postoperative patients may result in significant reversal of analgesia and may cause agitation (see PRECAUTIONS and DOSAGE AND ADMINISTRATION: Usage in Adults - Postoperative Opioid Depression ).
Opioid Depression Abrupt reversal of opioid depression may result in nausea, vomiting, sweating, tachycardia, increased blood pressure, tremulousness, seizures, ventricular tachycardia and fibrillation, pulmonary edema, and cardiac arrest which may result in death (see PRECAUTIONS ). Opioid Dependence Abrupt reversal of opioid effects in persons who are physically dependent on opioids may precipitate an acute withdrawal syndrome which may include, but are not limited to, the following signs and symptoms: body aches, fever, sweating, runny nose, sneezing, piloerection, yawning, weakness, shivering or trembling, nervousness, restlessness or irritability, diarrhea, nausea or vomiting, abdominal cramps, increased blood pressure, and tachycardia.
In the neonate, opioid withdrawal may also include: convulsions, excessive crying, and hyperactive reflexes (See WARNINGS ). Adverse events associated with the postoperative use of naloxone hydrochloride injection are listed by organ system and in decreasing order of frequency as follows: Cardiac Disorders: pulmonary edema, cardiac arrest or failure, tachycardia, ventricular fibrillation, and ventricular tachycardia. Death, coma, and encephalopathy have been reported as sequelae of these events.
Gastrointestinal Disorders: vomiting, nausea Nervous System Disorders: convulsions, paraesthesia, grand mal convulsion Psychiatric Disorders: agitation, hallucination, tremulousness Respiratory, Thoracic, and Mediastinal Disorders: dyspnea, respiratory depression, hypoxia Skin and Subcutaneous Tissue Disorders: nonspecific injection site reactions, sweating Vascular Disorders: hypertension, hypotension, hot flashes, or flushing. See also PRECAUTIONS and DOSAGE AND ADMINISTRATION: Usage in Adults - Postoperative Opioid Depression .
🔄 Drug Interactions ▾
Drug Interactions Large doses of naloxone are required to antagonize buprenorphine since the latter has a long duration of action due to its slow rate of binding and subsequent slow dissociation from the opioid receptor. Buprenorphine antagonism is characterized by a gradual onset of the reversal effects and a decreased duration of action of the normally prolonged respiratory depression. The barbiturate methohexital appears to block the acute onset of withdrawal symptoms induced by naloxone in opiate addicts.
🤰 Pregnancy ▾
Use in Pregnancy Teratogenic Effects: Teratology studies conducted in mice and rats at doses 4-times and 8-times, respectively, the dose of a 50 kg human given 10 mg/day (when based on surface area or mg/m 2 ), demonstrated no embryotoxic or teratogenic effects due to naloxone. There are, however, no adequate and well-controlled studies in pregnant women. Because animal reproduction studies are not always predictive of human response, naloxone hydrochloride should be used during pregnancy only if clearly needed.
Non-teratogenic Effects: Risk-benefit must be considered before naloxone is administered to a pregnant woman who is known or suspected to be opioid-dependent since maternal dependence may often be accompanied by fetal dependence. Naloxone crosses the placenta and may precipitate withdrawal in the fetus as well as in the mother. Patients with mild to moderate hypertension who receive naloxone during labor should be carefully monitored as severe hypertension may occur.
🧒 Pediatric Use ▾
Pediatric Use Naloxone hydrochloride injection may be administered intravenously, intramuscularly, or subcutaneously in children and neonates to reverse the effects of opiates. The American Academy of Pediatrics, however, does not endorse subcutaneous or intramuscular administration in opiate intoxication since absorption may be erratic or delayed. Although the opiate-intoxicated child responds dramatically to naloxone hydrochloride injection, he/she must be carefully monitored for at least 24 hours as a relapse may occur as naloxone is metabolized.
When naloxone hydrochloride injection is given to the mother shortly before delivery, the duration of its effects lasts only for the first two hours of neonatal life. It is preferable to administer naloxone hydrochloride injection directly to the neonate if needed after delivery. Naloxone has no apparent benefit as an additional method of resuscitation in the newly born infant with intrauterine asphyxia, which is not related to opioid use.
Usage in Pediatric Patients and Neonates for Septic Shock: The safety and effectiveness of naloxone hydrochloride injection in the treatment of hypotension in pediatric patients and neonates with septic shock have not been established. One study of two neonates in septic shock reported a positive pressor response; however, one patient subsequently died after intractable seizures.
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of naloxone hydrochloride injection did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
OVERDOSAGE There is limited clinical experience with naloxone hydrochloride injection overdosage in humans. Adult Patients In one small study, volunteers who received 24 mg/70 kg did not demonstrate toxicity. In another study, 36 patients with acute stroke received a loading dose of 4 mg/kg (10 mg/m 2 /min) of naloxone hydrochloride injection followed immediately by 2 mg/kg/hr for 24 hours.
Twenty-three patients experienced adverse events associated with naloxone use, and naloxone was discontinued in seven patients because of adverse effects. The most serious adverse events were: seizures (2 patients), severe hypertension (1), and hypotension and/or bradycardia (3). At doses of 2 mg/kg in normal subjects, cognitive impairment and behavioral symptoms, including irritability, anxiety, tension, suspiciousness, sadness, difficulty concentrating, and lack of appetite have been reported.
In addition, somatic symptoms, including dizziness, heaviness, sweating, nausea, and stomachaches were also reported. Although complete information is not available, behavioral symptoms were reported to often persist for 2 to 3 days. Pediatric Patients Up to 11 doses of 0.2 mg naloxone (2.2 mg) have been administered to children following overdose of diphenoxylate hydrochloride with atropine sulfate.
Pediatric reports include a 2-1/2 year-old child who inadvertently received a dose of 20 mg naloxone for treatment of respiratory depression following overdose with diphenoxylate hydrochloride with atropine sulfate. The child responded well and recovered without adverse sequelae. There is also a report of a 4-1/2 year-old child who received 11 doses during a 12-hour period, with no adverse sequelae.
Patient Management Patients who experience a naloxone overdose should be treated symptomatically in a closely supervised environment. Physicians should contact a poison control center for the most up-to-date patient management information.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Complete or Partial Reversal of Opioid Depression Naloxone prevents or reverses the effects of opioids including respiratory depression, sedation and hypotension. Also, naloxone can reverse the psychotomimetic and dysphoric effects of agonist-antagonists, such as pentazocine. Naloxone is an essentially pure opioid antagonist, i.e., it does not possess the “agonistic” or morphine-like properties characteristic of other opioid antagonists.
When administered in usual doses and in the absence of opioids or agonistic effects of other opioid antagonists, it exhibits essentially no pharmacologic activity. Naloxone has not been shown to produce tolerance or cause physical or psychological dependence. In the presence of physical dependence on opioids, naloxone will produce withdrawal symptoms.
However, in the presence of opioid dependence, opiate withdrawal symptoms may appear within minutes of naloxone administration and will subside in about 2 hours. The severity and duration of the withdrawal syndrome are related to the dose of naloxone and to the degree and type of opioid dependence. While the mechanism of action of naloxone is not fully understood, in vitro evidence suggests that naloxone antagonizes opioid effects by competing for the mu, kappa, and sigma opiate receptor sites in the CNS, with the greatest affinity for the mu receptor.
When naloxone hydrochloride is administered intravenously, the onset of action is generally apparent within two minutes; the onset of action is slightly less rapid when it is administered subcutaneously or intramuscularly. The duration of action is dependent upon the dose and route of administration of naloxone hydrochloride. Intramuscular administration produces a more prolonged effect than intravenous administration.
Since the duration of action of naloxone may be shorter than that of some opiates, the effects of the opiate may return as the effects of naloxone dissipates. The requirement for repeat doses of naloxone, however, will also be dependent upon the amount, type and route of administration of the opioid being antagonized. Adjunctive Use in Septic Shock Naloxone has been shown in some cases of septic shock to produce a rise in blood pressure that may last up to several hours; however, this pressor response has not been demonstrated to improve patient survival.
In some studies, treatment with naloxone in the setting of septic shock has been associated with adverse effects, including agitation, nausea and vomiting, pulmonary edema, hypotension, cardiac arrhythmias, and seizures. The decision to use naloxone in septic shock should be exercised with caution, particularly in patients who may have underlying pain or have previously received opioid therapy and may have developed opioid tolerance. Because of the limited number of patients who have been treated, optimal dosage and treatment regimens have not been established.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Naloxone Hydrochloride Injection, USP is available in the following packages: 0.4 mg/mL 1 mL single-dose prefilled syringes packaged in 10s (NDC 0641-6193-10) 1 mg/mL 2 mL single-dose prefilled syringes packaged in 10s (NDC 0641-6205-10) Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Store in carton until ready for use. Needle not included. Protect from light.
To report SUSPECTED ADVERSE REACTIONS, contact Hikma Pharmaceuticals USA Inc. at 1-877-845-0689, or the FDA at 1-800-FDA-1088 or www.fda.gov/medwatch . For Product Inquiry call 1-877-845-0689.
📋 Description ▾
DESCRIPTION Naloxone Hydrochloride Injection, USP is a sterile, nonpyrogenic solution of naloxone hydrochloride in water for injection. Each milliliter (mL) in the 1 mL single dose syringe contains 0.4 mg (400 micrograms) of naloxone hydrochloride, 8.9 mg of sodium chloride to adjust tonicity, in Water for Injection. Each milliliter (mL) in the 2 mL single dose syringe contains 1 mg of naloxone hydrochloride, 8.35 mg of sodium chloride to adjust tonicity, in Water for Injection.
The pH is 3.0-4.0 with hydrochloric acid used, if needed, for pH adjustment. Sealed under nitrogen. Naloxone Hydrochloride Injection, USP may be administered intravenously, intramuscularly, or subcutaneously.
Naloxone, an opioid antagonist, is a synthetic congener of oxymorphone. It differs from oxymorphone in that the methyl group on the nitrogen atom is replaced by an allyl group. Naloxone Hydrochloride, USP is a chemically designated 17-Allyl-4,5α-epoxy-3,14-dihydroxymorphinan-6-one hydrochloride (C 19 H 21 NO 4 • HCl), a white to slightly off-white powder soluble in water, in dilute acids, and in strong alkali; slightly soluble in alcohol; practically insoluble in ether and chloroform.
It has a molecular weight of 363.84. It has the following structural formula: naloxone syringe structure
⚠️ Precautions ▾
PRECAUTIONS General In addition to naloxone, other resuscitative measures such as maintenance of a free airway, artificial ventilation, cardiac massage, and vasopressor agents should be available and employed when necessary to counteract acute opioid poisoning. Abrupt postoperative reversal of opioid depression may result in nausea, vomiting, sweating, tremulousness, tachycardia, increased blood pressure, seizures, ventricular tachycardia and fibrillation, pulmonary edema, and cardiac arrest which may result in death.
Excessive doses of naloxone in postoperative patients may result in significant reversal of analgesia and may cause agitation (see PRECAUTIONS and DOSAGE AND ADMINISTRATION: Usage in Adults - Postoperative Opioid Depression ). Several instances of hypotension, hypertension, ventricular tachycardia and fibrillation, pulmonary edema, and cardiac arrest have been reported in postoperative patients. Death, coma, and encephalopathy have been reported as sequelae of these events.
These have occurred in patients most of whom had pre-existing cardiovascular disorders or received other drugs which may have similar adverse cardiovascular effects. Although a direct cause and effect relationship has not been established, naloxone should be used with caution in patients with pre-existing cardiac disease or patients who have received medications with potential adverse cardiovascular effects such as hypotension, ventricular tachycardia or fibrillation, and pulmonary edema. It has been suggested that the pathogenesis of pulmonary edema associated with the use of naloxone is similar to neurogenic pulmonary edema, i.e., a centrally mediated massive catecholamine response leading to a dramatic shift of blood volume into the pulmonary vascular bed resulting in increased hydrostatic pressures.
Drug Interactions Large doses of naloxone are required to antagonize buprenorphine since the latter has a long duration of action due to its slow rate of binding and subsequent slow dissociation from the opioid receptor. Buprenorphine antagonism is characterized by a gradual onset of the reversal effects and a decreased duration of action of the normally prolonged respiratory depression. The barbiturate methohexital appears to block the acute onset of withdrawal symptoms induced by naloxone in opiate addicts.
Carcinogenesis, Mutagenesis, Impairment of Fertility Studies in animals to assess the carcinogenic potential of naloxone have not been conducted. Naloxone was weakly positive in the Ames mutagenicity and in the in vitro human lymphocyte chromosome aberration test but was negative in the in vitro Chinese hamster V79 cell HGPRT mutagenicity assay and in the in vivo rat bone marrow chromosome aberration study. Reproduction studies conducted in mice and rats at doses 4-times and 8-times, respectively, the dose of a 50 kg human given 10 mg/day (when based on surface area or mg/m 2 ), demonstrated no embryotoxic or teratogenic effects due to naloxone.
Use in Pregnancy Teratogenic Effects: Teratology studies conducted in mice and rats at doses 4-times and 8-times, respectively, the dose of a 50 kg human given 10 mg/day (when based on surface area or mg/m 2 ), demonstrated no embryotoxic or teratogenic effects due to naloxone. There are, however, no adequate and well-controlled studies in pregnant women. Because animal reproduction studies are not always predictive of human response, naloxone hydrochloride should be used during pregnancy only if clearly needed.
Non-teratogenic Effects: Risk-benefit must be considered before naloxone is administered to a pregnant woman who is known or suspected to be opioid-dependent since maternal dependence may often be accompanied by fetal dependence. Naloxone crosses the placenta and may precipitate withdrawal in the fetus as well as in the mother. Patients with mild to moderate hypertension who receive naloxone during labor should be carefully monitored as severe hypertension may occur.
Use in Labor and Delive… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers It is not known whether naloxone is excreted in human milk. Because many drugs are excreted in human milk, caution should be exercised when naloxone hydrochloride is administered to a nursing woman.
🔒 Drug Abuse and Dependence ▾
DRUG ABUSE AND DEPENDENCE Naloxone hydrochloride injection is an opioid antagonist. Physical dependence associated with the use of naloxone hydrochloride injection has not been reported. Tolerance to the opioid antagonist effect of naloxone is not known to occur.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility Studies in animals to assess the carcinogenic potential of naloxone have not been conducted. Naloxone was weakly positive in the Ames mutagenicity and in the in vitro human lymphocyte chromosome aberration test but was negative in the in vitro Chinese hamster V79 cell HGPRT mutagenicity assay and in the in vivo rat bone marrow chromosome aberration study. Reproduction studies conducted in mice and rats at doses 4-times and 8-times, respectively, the dose of a 50 kg human given 10 mg/day (when based on surface area or mg/m 2 ), demonstrated no embryotoxic or teratogenic effects due to naloxone.
📖 Instructions for Use ▾
INSTRUCTIONS FOR USE CAUTION: Certain glass syringes may malfunction, break or clog when connected to some Needleless Luer Access Devices (NLADs) and needles. This syringe has a larger internal syringe tip and an external collar (luer collar). The external collar must remain attached to the syringe.
Data show that the syringe achieves acceptable connections with the BD Eclipse™ Needle and the Terumo SurGuard3™ Safety Needle and with the following non-center post NLADs: BD SMARTSITE™ and BD-Q SYTE™. The data also show acceptable connections are achieved to the center post ICU Medical CLAVE™. However, spontaneous disconnection of this glass syringe from needles and NLADs with leakage of drug product may occur.
Assure that the needle or NLAD is securely attached before beginning the injection. Visually inspect the glass syringe-needle or glass syringe-NLAD connection before and during drug administration. Figure 1 1.
Inspect the outer packaging (plastic tube) by verifying: - plastic tube integrity - drug name - drug strength - dose volume - route of administration - expiration date to be sure that the drug has not expired - sterile field applicability Do not use if package has been damaged. 2. Remove the plastic tube cap of the outer packaging to access the syringe.
3. Remove the syringe from the plastic tube. 4.
Perform visual inspection on the syringe by verifying: - absence of syringe damage - absence of external particles - absence of internal particles - proper drug color - expiration date to be sure that the drug has not expired - drug name - drug strength - dose volume - route of administration - sterile field applicability 5. Push plunger rod slightly to break the stopper loose while tip cap is still on. 6.
Remove tip cap by twisting it off. (See Figure 2) Figure 2 7. Discard the tip cap.
8. Expel air bubble. 9.
Adjust dose by expelling extra volume (where applicable) from the syringe into sterile material prior to administration. 10. Connect the syringe to appropriate injection connection depending on route of administration.
Before injection, ensure that the syringe is securely attached to the needle or needleless luer access device (NLAD). 11. Depress plunger rod to deliver medication.
Ensure that pressure is maintained on the plunger rod during the entire administration. 12. Remove syringe from NLAD (if applicable) and discard into appropriate receptacle.
To prevent needle-stick injuries, needles should not be recapped. NOTES: - All steps must be done sequentially - Do not autoclave syringe - Do not use this product on a sterile field - Do not introduce any other fluid into the syringe at any time - This product is for single dose only; discard unused portion Manufactured by: Hikma Pharmaceuticals USA Inc. Berkeley Heights, NJ 07922 462-892-02 Revised May 2024 2 mL figure amended thumb Figure 2 thumb
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL NDC 0641- 6205 -01 Rx only 2 mL Single-Dose Prefilled Syringe Naloxone HCl Injection, USP 2 mg per 2 mL (1 mg/mL) For IV, IM or SC Use - Protect from light NDC 0641- 6205 -10 Rx only Naloxone HCl Injection, USP 2 mg per 2 mL (1 mg/mL) For Intravenous, Intramuscular or Subcutaneous use For syringe assembly, see package insert - Instructions for Use Needle not included 10 x 2 mL Single-Dose Prefilled Syringes NDC 0641- 6193 -01 Rx only 1 mL Single-Dose Prefilled Syringe Naloxone HCl Injection, USP 0.4 mg/mL For IV, IM or SC Use - Protect from light NDC 0641- 6193 -10 Rx only Naloxone HCl Injection, USP 0.4 mg/mL For Intravenous, Intramuscular or Subcutaneous use For syringe assembly, see package insert - Instructions for Use Needle not included 10 x 1 mL Single-Dose Prefilled Syringes 462-890-00 carton LBL CTN