
Estradiol Valerate and Estradiol Valerate/Dienogest Kit — NDC 0781-4110-15 (Billing 00781-4110-15)
This is a package of Estradiol Valerate and Estradiol Valerate/Dienogest Kit from Sandoz Inc, marketed since Aug 2015 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0781-4110-15 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0781 labeler · 4110 product · 15 package
- Package marketed since
- Jan 21, 2020
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 0781411015 5
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
- RxCUI (RxNorm): 748797
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
Clinical
Estrogen may be used for the following: to treat hot flushes ('hot flashes'; sudden strong feelings of heat and sweating) in women who are experiencing menopause ('change of life', the end of monthly menstrual periods) to treat vaginal dryness, itching, or burning to prevent osteoporosis (a condition in which the bones become thin and weak and break easily) in women who are experiencing or have experienced menopause to relieve symptoms of low estrogen in young women who do not produce enough estrogen naturally to relieve the symptoms of certain types of breast and prostate (a male repro...
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.2151 | $0.65 / 3 kit |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 5, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00781-4110-15 You're viewing this Main listing | 3 BLISTER PACK in 1 PACKAGE / 1 KIT in 1 BLISTER PACK | 2020-01-21 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Estradiol Valerate and Estradiol Valerate/Dienogestthis 00781-4110-15 | Sandoz | 1 kit | — | — | FDA listed | — |
| Natazia 50419-0409-00 | Bayer | 1 kit | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8153616 ↗ | Method of use | U-1240 | Jan 30, 2028 |
| US 8071577 ↗ | Method of use | U-1 | May 13, 2026 |
Is there a generic version of this drug?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Sandoz Inc labeler code 00781
- Omnitrope Somatropin Kit NDC 0781-4004-36
- Chlorpromazine Hydrochloride 30 mg/mL Concentrate NDC 0781-4027-53
- Chlorpromazine Hydrochloride 100 mg/mL Concentrate NDC 0781-4028-22
- Aprepitant Kit NDC 0781-4063-36
- Drospirenone/Ethinyl Estradiol/Levomefolate Calcium and Levomefolate Kit NDC 0781-4075-15
- Drospirenone/ethinyl estradiol/levomefolate calcium and levomefolate Kit NDC 0781-4103-15
- Amoxicillin 500 mg Tablet, Film Coated NDC 0781-5060-01
- Amoxicillin 875 mg Tablet, Film Coated NDC 0781-5061-01
- Mycophenolate Mofetil 500 mg Tablet, Film Coated NDC 0781-5175-01
- Fidaxomicin 200 mg Tablet, Film Coated NDC 0781-5194-20
- Carvedilol 3.125 mg Tablet, Film Coated NDC 0781-5221-01
- Carvedilol 12.5 mg Tablet, Film Coated NDC 0781-5223-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: CIGARETTE SMOKING AND SERIOUS CARDIOVASCULAR EVENTS Cigarette smoking increases the risk of serious cardiovascular events from combination oral contraceptives (COC) use. This risk increases with age, particularly in women over 35 years of age, and with the number of cigarettes smoked. For this reason, COCs should not be used by women who are over 35 years of age and smoke. [See Contraindications ( 4 ).] WARNING: CIGARETTE SMOKING AND SERIOUS CARDIOVASCULAR EVENTS See full prescribing information for complete boxed warning. • Women over 35 years old who smoke should not use Estradiol Valerate and Estradiol Valerate/Dienogest .
( 4 ) • Cigarette smoking increases the risk of serious cardiovascular events from combination oral contraceptive (COC) use. ( 4 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE • Estradiol Valerate and Estradiol Valerate/Dienogest is an estrogen/progestin COC indicated for use by women to prevent pregnancy. ( 1 ) • Treatment of heavy menstrual bleeding in women without organic pathology who choose to use an oral contraceptive as their method of contraception. ( 1.2 ) • The efficacy of Estradiol Valerate and Estradiol Valerate/Dienogest in women with a body mass index (BMI) of >30 kg/m 2 has not been evaluated.
( 1 , 8.8 )
1.1Oral Contraception Estradiol Valerate and Estradiol Valerate/Dienogest is indicated for use by women to prevent pregnancy. The efficacy of Estradiol Valerate and Estradiol Valerate/Dienogest in women with a body mass index (BMI) of > 30 kg/m 2 has not been evaluated.
1.2Heavy Menstrual Bleeding Estradiol Valerate and Estradiol Valerate/Dienogest is also indicated for the treatment of heavy menstrual bleeding in women without organic pathology who choose to use an oral contraceptive as their method of contraception [see Clinical Studies ( 14.2 )].
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Take one tablet daily by mouth at the same time every day. ( 2.1 ) • Tablets must be taken in the order directed on the blister pack. ( 2.1 ) • Do not skip or delay intake by more than 12 hours. ( 2.1 )
2.1How to Take Estradiol Valerate and Estradiol Valerate/Dienogest To achieve maximum contraceptive effectiveness, Estradiol Valerate and Estradiol Valerate/Dienogest must be taken exactly as directed. Take one tablet by mouth at the same time every day. Tablets must be taken in the order directed on the blister pack.
Tablets should not be skipped or intake delayed by more than 12 hours. For patient instructions for missed pills, see FDA-Approved Patient Labeling.
2.2How to Start Estradiol Valerate and Estradiol Valerate/Dienogest Instruct the patient to begin taking Estradiol Valerate and Estradiol Valerate/Dienogest on Day 1 of her menstrual cycle (that is, the first day of her menstrual bleeding). See FDA-Approved Patient Labeling . Instruct the patient to use a non-hormonal contraceptive as back-up during the first 9 days.
For postpartum women who do not breastfeed or after a second trimester abortion, start Estradiol Valerate and Estradiol Valerate/Dienogest no earlier than 4 weeks postpartum due to the increased risk of thromboembolism. If the patient starts on Estradiol Valerate and Estradiol Valerate/Dienogest postpartum and has not yet had a period, evaluate for possible pregnancy, and instruct her to use an additional method of contraception until she has taken Estradiol Valerate and Estradiol Valerate/Dienogest for 9 consecutive days.
The possibility of ovulation and conception prior to initiation of medication should also be considered. If the patient is switching from a combination hormonal method such as a: • Another pill • Vaginal ring • Patch • Instruct her to take the first dark yellow pill on the first day of her withdrawal bleed. She should not continue taking the pills from her previous birth control pack.
If she does not have a withdrawal bleed, rule out pregnancy before starting Estradiol Valerate and Estradiol Valerate/Dienogest. • If she previously used a vaginal ring or transdermal patch, she should start using Estradiol Valerate and Estradiol Valerate/Dienogest on the day the ring or patch is removed. • Instruct the patient to use a non-hormonal back-up method such as a condom or spermicide for the first 9 days. If the patient is switching from a progestin-only method such as a: • Progestin-only pill • Implant • Intrauterine system • Injection • Instruct her to take the first dark yellow pill on the day she would have taken her next progestin-only pill or on the day of removal of her implant or intrauterine system or on the day when she would have had her next injection. • Instruct the patient to use a non-hormonal back-up method such as a condom or spermicide for the first 9 days.
2.3Advice in Case of Gastrointestinal Disturbances In case of severe vomiting or diarrhea, absorption may not be complete and additional contraceptive measures should be taken. If vomiting or diarrhea occurs within 3-4 hours after taking a colored tablet, this can be regarded as a missed tablet.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Estradiol Valerate and Estradiol Valerate/Dienogest (estradiol valerate and estradiol valerate/dienogest) tablets are available in blister packs. Each blister pack contains 28 round, biconvex, film-coated tablets in the following order: • 2 dark yellow tablets, with an embossed “DD” in a regular hexagon on one side, each containing 3 mg estradiol valerate • 5 medium red tablets, with an embossed “DJ” in a regular hexagon on one side, each containing 2 mg estradiol valerate and 2 mg dienogest • 17 light yellow tablets, with an embossed “DH” in a regular hexagon on one side, each containing 2 mg estradiol valerate and 3 mg dienogest • 2 dark red tablets, with an embossed “DN” in a regular hexagon on one side, each containing 1 mg estradiol valerate • 2 white tablets (inert), with an embossed “DT” in a regular hexagon on one side Estradiol Valerate and Estradiol Valerate/Dienogest consists of 28 film-coated, unscored tablets in the following order ( 3 ): • 2 dark yellow tablets each containing 3 mg estradiol valerate • 5 medium red tablets each containing 2 mg estradiol valerate and 2 mg dienogest • 17 light yellow tablets each containing 2 mg estradiol valerate and 3 mg dienogest • 2 dark red tablets each containing 1 mg estradiol valerate • 2 white tablets (inert)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Do not prescribe Estradiol Valerate and Estradiol Valerate/Dienogest to women who are known to have the following: • A high risk of arterial or venous thrombotic diseases. Examples include women who are known to: • Smoke, if over age 35 [see Boxed Warning and Warnings and Precautions ( 5.1 )] • Have deep vein thrombosis or pulmonary embolism, now or in the past [see Warnings and Precautions ( 5.1 )] • Have cerebrovascular disease [see Warnings and Precautions ( 5.1 )] • Have coronary artery disease [see Warnings and Precautions ( 5.1 )] • Have thrombogenic valvular or thrombogenic rhythm diseases of the heart (for example, subacute bacterial endocarditis with valvular disease, or atrial fibrillation) [see Warnings and Precautions ( 5.1 )] • Have inherited or acquired hypercoagulopathies [see Warnings and Precautions ( 5.1 )] • Have uncontrolled hypertension [see Warnings and Precautions ( 5.4 )] • Have diabetes mellitus with vascular disease [see Warnings and Precautions ( 5.6 )] • Have headaches with focal neurological symptoms or have migraine headaches with or without aura if over age 35 [see Warnings and Precautions ( 5.7 )] • Undiagnosed abnormal uterine bleeding [see Warnings and Precautions ( 5.8 )] • Breast cancer or other estrogen- or progestin-sensitive cancer, now or in the past [see Warnings and Precautions ( 5.2 )] • Liver tumors, benign or malignant, or liver disease [see Warnings and Precautions ( 5.3 ), Use in Specific Populations ( 8.7 ) and Clinical Pharmacology ( 12.3 )] . • Pregnancy, because there is no reason to use COCs during pregnancy [see Warnings and Precautions ( 5.9 ) and Use in Specific Populations ( 8.1 )] . • A high risk of arterial or venous thrombotic diseases ( 4 ) • Undiagnosed abnormal uterine bleeding ( 4 ) • Breast cancer or other estrogen- or progestin-sensitive cancer ( 4 ) • Liver tumors or liver disease ( 4 ) • Pregnancy ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Vascular risks : Stop Estradiol Valerate and Estradiol Valerate/Dienogest if a thrombotic event occurs. Stop Estradiol Valerate and Estradiol Valerate/Dienogest at least 4 weeks before and through 2 weeks after major surgery. Start Estradiol Valerate and Estradiol Valerate/Dienogest no earlier than 4 weeks after delivery, in women who are not breastfeeding.
( 5.1 ) • Liver disease : Discontinue Estradiol Valerate and Estradiol Valerate/Dienogest if jaundice occurs. ( 5.3 ) • High blood pressure : Do not prescribe Estradiol Valerate and Estradiol Valerate/Dienogest for women with uncontrolled hypertension or hypertension with vascular disease. ( 5.4 ) • Carbohydrate and lipid metabolic effects : Monitor prediabetic and diabetic women taking Estradiol Valerate and Estradiol Valerate/Dienogest.
Consider an alternate contraceptive method for women with uncontrolled dyslipidemia. ( 5.6 ) • Headache : Evaluate significant change in headaches and discontinue Estradiol Valerate and Estradiol Valerate/Dienogest if indicated. ( 5.7 ) • Uterine bleeding : Evaluate irregular bleeding or amenorrhea.
( 5.8 ) • CYP3A4 induction : Women taking strong CYP3A4 inducers (for example, carbamazepine, phenytoin, rifampicin, and St. John’s wort) should not choose Estradiol Valerate and Estradiol Valerate/Dienogest as their oral contraceptive due to the possibility of decreased contraceptive efficacy. ( 5.13 , 7.1 )
5.1Thromboembolic Disorders and Other Vascular Problems Stop Estradiol Valerate and Estradiol Valerate/Dienogest if an arterial or venous thrombotic event (VTE) occurs. The use of COCs increases the risk of venous thromboembolism. However, pregnancy increases the risk of venous thromboembolism as much or more than the use of COCs.
The risk of VTE in women using COCs has been estimated to be 3 to 9 per 10,000 woman-years. The risk of VTE is highest during the first year of use. Data from a large, prospective cohort safety study of various COCs suggest that this increased risk, as compared to that in non-COC users, is greatest during the first 6 months of COC use.
Data from this safety study indicate that the greatest risk of VTE is present after initially starting a COC or restarting (following a 4 week or greater pill-free interval) the same or a different COC. Use of COCs also increases the risk of arterial thromboses such as strokes and myocardial infarctions, especially in women with other risk factors for these events. The risk of thromboembolic disease due to oral contraceptives gradually disappears after COC use is discontinued.
If feasible, stop Estradiol Valerate and Estradiol Valerate/Dienogest at least 4 weeks before and through 2 weeks after major surgery or other surgeries known to have an elevated risk of thromboembolism. Start Estradiol Valerate and Estradiol Valerate/Dienogest no earlier than 4 weeks after delivery, in women who are not breastfeeding. The risk of postpartum thromboembolism decreases after the third postpartum week, whereas the risk of ovulation increases after the third postpartum week.
COCs have been shown to increase both the relative and attributable risks of cerebrovascular events (thrombotic and hemorrhagic strokes), although, in general, the risk is greatest among older (>35 years of age), hypertensive women who also smoke. COCs also increase the risk for stroke in women with other underlying risk factors. Oral contraceptives must be used with caution in women with cardiovascular disease risk factors.
Stop Estradiol Valerate and Estradiol Valerate/Dienogest if there is unexplained loss of vision, proptosis, diplopia, papilledema, or retinal vascular lesions. Evaluate for retinal vein thrombosis immediately. [See Adverse Reactions ( 6 ).]
5.2Carcinoma of the Breasts and Reproductive Organs Women who currently have or have had breast cancer should not use Estradiol Valerate and Estradiol Valerate/Dienogest because breast cancer is a hormonally-sensitive tumor. There is subs… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions with the use of COCs are discussed elsewhere in the labeling: • Serious cardiovascular events and stroke [see Boxed Warning and Warnings and Precautions ( 5.1 )] • Vascular events [see Warnings and Precautions ( 5.1 )] • Liver disease [see Warnings and Precautions ( 5.3 )] Adverse reactions commonly reported by COC users are: • Irregular uterine bleeding • Nausea • Breast tenderness • Headache The most common adverse reactions (≥ 2%) in clinical trials for Estradiol Valerate and Estradiol Valerate/Dienogest are headaches, irregular uterine bleeding,headache (including migraines) 13%, breast tenderness,pain 7%, menstrual disorders 7%, nausea/ or vomiting, 6%, acne 4%, mood changes (3%) and increased weight.
3%. ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Bayer HealthCare Pharmaceuticals Inc. at 1-888-842-2937 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Contraception and Heavy Menstrual Bleeding Studies A total of 2,131 women, 18 to 54 years of age, who took at least one dose of Estradiol Valerate and Estradiol Valerate/Dienogest were enrolled in four clinical phase 3 trials.
A total of 1,867 subjects were included in two clinical phase 3 studies with a treatment duration up to 28 cycles with Estradiol Valerate and Estradiol Valerate/Dienogest as an oral contraceptive and 264 subjects in the two phase 3 clinical trials with a treatment duration of 7 cycles evaluating Estradiol Valerate and Estradiol Valerate/Dienogest in the treatment of heavy, prolonged, and/or frequent menstrual bleeding in women without organic pathology. [See Clinical Studies ( 14.1 , 14.2 .)] Adverse Reactions Leading to Study Discontinuation : 11.4% of the women discontinued from the clinical trials due to an adverse reaction; the most frequent adverse reactions leading to discontinuation were menstrual disorder (metrorrhagia, menorrhagia, menstruation irregular, genital hemorrhage, vaginal hemorrhage, dysfunctional uterine bleeding) (2.3%); mood changes (depression, mood swings, mood altered, depressed mood, dysthymic disorder, crying) (1.2%); acne (1.1%), headache (including migraines) (1.1%), and weight increased (0.7 %).
Common Adverse Reactions (≥ 2%): headache (including migraines) (12.7%), breast pain, discomfort or tenderness (7.0%), menstrual disorders (metrorrhagia, menstruation irregular, menorrhagia, vaginal hemorrhage, dysfunctional uterine bleeding, genital hemorrhage, abnormal withdrawal bleeding, uterine hemorrhage) (6.9%), nausea or vomiting (6.0%), acne (3.9%), mood changes (depression, mood swings, depressed mood, mood altered, affect lability, dysthymic disorder, crying) (3.0%) and increased weight (2.9%). Serious Adverse Reactions: myocardial infarction (2 cases), ruptured ovarian cyst (2 cases), deep vein thrombosis, focal nodular hyperplasia of the liver, uterine leiomyoma, acute cholecystitis, and chronic acalculous cholecystitis.
6.2Postmarketing Experience The following adverse reactions have been identified during post-approval use of Estradiol Valerate and Estradiol Valerate/Dienogest. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Vascular disorders: Venous and arterial thromboembolic events (including pulmonary emboli, deep vein thrombosis, cerebral thrombosis, myocardial infarction and stroke), hypertension Hepatobiliary disorders: Gallbladder disease, hepatitis Immune system disorders: Hypersensitivity Metabolism and nutrition disorders: Fluid retention, hypertriglyceridemia Nervous system disorders: Dizziness… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Consult the labeling of all concurrently-used drugs to obtain further information about interactions with hormonal contraceptives or the potential for enzyme alterations . Drugs or herbal products that induce certain enzymes (for example, CYP3A4) may decrease the effectiveness of COCs or increase breakthrough bleeding. Counsel patients to use a back-up or alternative method of contraception when enzyme inducers are used with COCs.
( 7.1 )
7.1Effects of Other Drugs on Combined Oral Contraceptives Interactions between oral contraceptives and other drugs may lead to breakthrough bleeding and/or contraceptive failure. The following interactions have been reported in the literature for COCs in general or were studied in clinical trials with Estradiol Valerate and Estradiol Valerate/Dienogest. CYP3A4 Inducers : Drugs or herbal products that induce certain enzymes, including CYP3A4, may decrease the effectiveness of COCs or increase breakthrough bleeding.
Some drugs or herbal products that may decrease the effectiveness of hormonal contraceptives include barbiturates, bosentan, felbamate, griseofulvin, oxcarbazepine, and topiramate. Counsel women to use an alternative method of contraception or a back-up method when moderate or weak enzyme inducers are used with COCs, and to continue back-up contraception for 28 days after discontinuing the enzyme inducer to ensure contraceptive reliability. Dienogest is a substrate of CYP3A4.
Women who take medications that are strong CYP3A4 inducers (for example, carbamazepine, phenytoin, rifampicin, and St. John’s wort) should not choose Estradiol Valerate and Estradiol Valerate/Dienogest as their oral contraceptive while using these inducers and for at least 28 days after discontinuation of these inducers due to the possibility of decreased contraceptive efficacy. The effect of the CYP3A4 inducer rifampicin was studied in healthy postmenopausal women.
Co-administration of rifampicin with estradiol valerate/dienogest tablets led to a 52 % and 83% decrease in the mean C max and AUC (0–24hr), respectively, for dienogest and a 25% and 44% decrease in C max and AUC (0–24hr), respectively, for estradiol at steady state. Strong CYP3A4 Inhibitors : Strong CYP3A4 inhibitors such as ketoconazole increased hormone serum concentrations. In a study investigating the effect of ketoconazole on dienogest and estradiol pharmacokinetics, co-administration with the strong CYP3A4 inhibitor ketoconazole resulted in a 186% increase of AUC (0–24hr) at steady state for dienogest and a 57% increase for estradiol.
There was also a 94% and 65% increase of C max at steady state for dienogest and estradiol when co-administered with ketoconazole. Moderate CYP3A4 Inhibitors : The AUC (0–24hr) of dienogest and estradiol at steady state were increased by 62% and 33%, respectively, when co-administered with a moderate CYP3A4 inhibitor, erythromycin. There was also a 33% and 51% increase of Cmax at steady state for dienogest and estradiol, respectively, when co-administered with erythromycin.
Other known CYP3A4 inhibitors like azole antifungals, cimetidine, verapamil, macrolides, diltiazem, antidepressants, and grapefruit juice may increase plasma concentrations of dienogest. Human Immunodeficiency Virus (HIV)/Hepatitis C Virus (HCV) Protease Inhibitors and Non-Nucleoside Reverse Transcriptase Inhibitors : Significant changes (increase and decrease) in plasma concentrations of estrogen and progestin have been noted in some cases of co-administration of HIV/HCV protease inhibitors or with non-nucleoside reverse transcriptase inhibitors.
Antibiotics : There have been reports of pregnancy while taking hormonal contraceptives and antibiotics, but clinical pharmacokinetic studies have not shown consistent effects of antibiotics on plasma concentrations of synthetic steroids.
7.2Effects of Combined Oral Contraceptives on Other Drugs COCs containing ethinyl estradiol may inhibit the metabolism of other compounds. CO… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Nursing mothers: Not recommended; can decrease milk production. ( 8.3 ) • Body Mass Index: The safety and efficacy of Estradiol Valerate and Estradiol Valerate/Dienogest in women with a body mass index (BMI) of >30 kg/m 2 has not been evaluated. ( 8.8 )
8.1Pregnancy There is little or no increased risk of birth defects in women who inadvertently use COCs during early pregnancy. Epidemiologic studies and meta-analyses have not found an increased risk of genital or non-genital birth defects (including cardiac anomalies and limb-reduction defects) following exposure to low dose COCs prior to conception or during early pregnancy. The administration of COCs to induce withdrawal bleeding should not be used as a test for pregnancy.
COCs should not be used during pregnancy to treat threatened or habitual abortion. Women who do not breastfeed may start COCs no earlier than four weeks postpartum.
8.3Nursing Mothers When possible, advise the nursing mother to use other forms of contraception until she has weaned her child. Estrogen-containing COCs can reduce milk production in breastfeeding mothers. This is less likely to occur once breastfeeding is well-established; however, it can occur at any time in some women. Small amounts of oral contraceptive steroids and/or metabolites are present in breast milk.
8.4Pediatric Use Safety and efficacy of Estradiol Valerate and Estradiol Valerate/Dienogest have been established in women of reproductive age. Efficacy is expected to be the same for postpubertal adolescents under the age of 18 and for users 18 years and older. Use of this product before menarche is not indicated.
8.5Geriatric Use Estradiol Valerate and Estradiol Valerate/Dienogest has not been studied in postmenopausal women and is not indicated in this population.
8.6Patients with Renal Impairment The pharmacokinetics of Estradiol Valerate and Estradiol Valerate/Dienogest has not been studied in subjects with renal impairment, but an effect requiring dose adjustment is unlikely to be present [see Clinical Pharmacology ( 12.3 )] .
8.7Patients with Hepatic Impairment The pharmacokinetics of Estradiol Valerate and Estradiol Valerate/Dienogest has not been studied in subjects with hepatic impairment. Steroid hormones may be poorly metabolized in patients with impaired liver function. Acute or chronic disturbances of liver function may necessitate the discontinuation of COC use until markers of liver function return to normal. [See Contraindications ( 4 ) and Warnings and Precautions ( 5.3 ).)]
8.8Body Mass Index The safety and efficacy of Estradiol Valerate and Estradiol Valerate/Dienogest in women with a BMI of > 30 kg/m 2 has not been evaluated.
🤰 Pregnancy ▾
8.1Pregnancy There is little or no increased risk of birth defects in women who inadvertently use COCs during early pregnancy. Epidemiologic studies and meta-analyses have not found an increased risk of genital or non-genital birth defects (including cardiac anomalies and limb-reduction defects) following exposure to low dose COCs prior to conception or during early pregnancy. The administration of COCs to induce withdrawal bleeding should not be used as a test for pregnancy.
COCs should not be used during pregnancy to treat threatened or habitual abortion. Women who do not breastfeed may start COCs no earlier than four weeks postpartum.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and efficacy of Estradiol Valerate and Estradiol Valerate/Dienogest have been established in women of reproductive age. Efficacy is expected to be the same for postpubertal adolescents under the age of 18 and for users 18 years and older. Use of this product before menarche is not indicated.
🧓 Geriatric Use ▾
8.5Geriatric Use Estradiol Valerate and Estradiol Valerate/Dienogest has not been studied in postmenopausal women and is not indicated in this population.
🆘 Overdosage ▾
10 OVERDOSAGE There have been no reports of serious ill effects from overdose, including ingestion by children. Overdosage may cause withdrawal bleeding in females and nausea.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action COCs lower the risk of becoming pregnant primarily by suppressing ovulation. Other possible mechanisms may include cervical mucus changes that inhibit sperm penetration and endometrial changes that reduce the likelihood of implantation.
12.2Pharmacodynamics The estrogen in Estradiol Valerate and Estradiol Valerate/Dienogest is estradiol valerate, a synthetic prodrug of 17ß-estradiol. The progestin in Estradiol Valerate and Estradiol Valerate/Dienogest is dienogest (DNG). DNG displays properties of 19-nortestosterone derivatives as well as properties associated with progesterone derivatives. [See Nonclinical Toxicology ( 13.2 ).] Cardiac Electrophysiology The effect of Estradiol Valerate and Estradiol Valerate/Dienogest on QT prolongation was evaluated in a randomized, double-blind, positive (moxifloxacin 400 mg) and negative (placebo) controlled crossover study in healthy subjects.
A total of 53 subjects were administered Estradiol Valerate and Estradiol Valerate/Dienogest (containing 3 mg dienogest and 2 mg estradiol valerate), dienogest 10 mg, and placebo as once daily doses for 4 days, and moxifloxacin 400 mg as a single oral dose. The upper bound of the 90% confidence interval for the largest placebo-adjusted, baseline-corrected QTc based on Fridericia’s correction method (QTcF) was below 10 msec, the threshold for regulatory concern.
12.3Pharmacokinetics Absorption After oral administration of estradiol valerate, cleavage to 17β-estradiol and valeric acid takes place during absorption by the intestinal mucosa or in the course of the first liver passage. This gives rise to estradiol and its metabolites, estrone and other metabolites. Maximum serum estradiol concentrations of 73.3 pg/mL are reached at a median of approximately 6 hours (range: 1.5–12 hours) and the area under the estradiol concentration curve [AUC(0–24hr)] was 1301 pg·hr/mL after single ingestion of a tablet containing 3 mg estradiol valerate under fasted condition on Day 1 of the 28-day sequential regimen.
Bioavailability of dienogest is about 91%. Maximum serum dienogest concentrations of 91.7 ng/mL are reached at a median of approximately 1 hour (range: 0.5–1.5 hour) and the area under the dienogest concentration curve [AUC(0–24hr)] was 964 ng/mL after single oral administration of Estradiol Valerate and Estradiol Valerate/Dienogest tablet containing 2 mg estradiol valerate/3 mg dienogest under fasted condition. The pharmacokinetics of dienogest are dose-proportional within the dose range of 1–8 mg.
Steady state is reached after 4 days of the same dosage of 2 mg dienogest. The mean accumulation ratio for AUC (0–24hr) is approximately 1.24. The mean plasma pharmacokinetic parameters at steady state following repeated oral doses of a 2 mg estradiol valerate/3 mg dienogest combination tablet in fertile women under fasted condition are reported in Table 1.
Table 1 Arithmetic Mean (SD) Serum Pharmacokinetic Parameters at Steady-state (on Day 24) following Repeated Oral Doses of 2 mg EV/3 mg DNG on Days 8-24 of the 28 day Regimen in Fertile Women under Fasted Condition (N=15) Parameter Dienogest Estradiol Estrone C max C max = Maximum serum concentration 85.2 (19.7) ng/ml 70.5 (25.9) pg/ml 483 (198) pg/ml T max Tmax = Time to reach maximum concentration (hr) Median (range) for T max 1.5 (1–2) 3 (1.5–12) 4 (3–12) AUC AUC(0-24hr) = Area under the concentration-time curve from 0 hr data point up to 48 hr post-administration (0–24hr) 828 (187) ng·hr/ml 1323 (480) pg·hr/ml 7562 (3403) pg·hr/ml t ½ (hr) 12.3 (1.4) NA NA: Data not available NA Food Effect Concomitant food intake in women resulted in a 28% decrease for dienogest C max and 23% increase of estradiol C max while the exposure (AUC) of both dienogest and estradiol did not change.
Distribution In serum, 38% of estradiol is bound to sex hormone-binding globulin (SHBG), 60% to albumin and 2–3% circulates in free form. An apparent volume of distribution of app… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action COCs lower the risk of becoming pregnant primarily by suppressing ovulation. Other possible mechanisms may include cervical mucus changes that inhibit sperm penetration and endometrial changes that reduce the likelihood of implantation.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Estradiol Valerate and Estradiol Valerate/Dienogest tablets are available in packages of three blister packs (NDC 50419-409-03). The active and inert film-coated tablets are rounded with biconvex faces, one side is embossed with a regular hexagon shape with the letters DD or DJ or DH or DN or DT. Each blister pack (28 film-coated tablets) contains in the following order: • 2 round biconvex dark yellow film-coated tablets with embossed “DD” in a regular hexagon on one side each containing 3 mg estradiol valerate • 5 round biconvex medium red film-coated tablets with embossed “DJ” in a regular hexagon on one side each containing 2 mg estradiol valerate and 2 mg dienogest • 17 round biconvex light yellow film-coated tablets with embossed “DH” in a regular hexagon on one side each containing 2 mg estradiol valerate and 3 mg dienogest • 2 round biconvex dark red film-coated tablets with embossed “DN” in a regular hexagon on one side each containing 1 mg estradiol valerate • 2 white round biconvex white film-coated tablets with embossed “DT” in a regular hexagon on one side (inert)
16.2Storage Store at 25º C (77º F); excursions permitted to 15–30 o C (59–86 o F) [see USP Controlled Room Temperature] .
📋 Description ▾
11 DESCRIPTION Estradiol Valerate and Estradiol Valerate/Dienogest tablets provide an oral contraceptive regimen consisting of 26 active film-coated tablets that contain the active ingredients specified for each tablet below, followed by two inert film-coated tablets: • 2 dark yellow tablets each containing 3 mg estradiol valerate • 5 medium red tablets each containing 2 mg estradiol valerate and 2 mg dienogest • 17 light yellow tablets each containing 2 mg estradiol valerate and 3 mg dienogest • 2 dark red tablets each containing 1 mg estradiol valerate • 2 white tablets (inert) Estradiol Valerate and Estradiol Valerate/Dienogest also contains the excipients lactose monohydrate, maize starch, maize starch pre-gelatinized, povidone 25, magnesium stearate, hypromellose, macrogol 6000, talc, titanium dioxide, and ferric oxide pigment, yellow, or ferric oxide pigment, red.
The empirical formula of estradiol valerate is C 23 H 32 O 3 and the chemical structure is: Estradiol Valerate Estradiol Valerate The chemical name of estradiol valerate is Estra-1,3,5(10)-triene-3,17-diol(17ß)-,17-pentanoate. The empirical formula of dienogest is C 20 H 25 NO 2 and the chemical structure is: Dienogest Dienogest The chemical name of dienogest is (17α)-17-Hydroxy-3-oxo-19-norpregna-4,9-diene-21-nitrile. EV Chem Struc Dien Chem Struc
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See “FDA-approved patient labeling (Patient Information).” • Counsel patients that cigarette smoking increases the risk of serious cardiovascular events from COC use, and that women who are over 35 years old and smoke should not use COCs. • Counsel patients that the increased risk of VTE compared to non-users of COCs is greatest after initially starting a COC or restarting (following a 4 week or greater pill-free interval) the same or a different COC. • Counsel patients that Estradiol Valerate and Estradiol Valerate/Dienogest does not protect against HIV infection (AIDS) and other sexually transmitted diseases. • Counsel patients on Warnings and Precautions associated with COCs. • Inform patients that Estradiol Valerate and Estradiol Valerate/Dienogest is not indicated during pregnancy.
If pregnancy occurs during treatment with Estradiol Valerate and Estradiol Valerate/Dienogest, instruct the patient to stop further intake. • Counsel patients to take one tablet daily by mouth at the same time every day in the exact order noted on the blister. Instruct patients what to do in the event pills are missed. See What Should I Do if I Miss any Pills section in FDA-Approved Patient Labeling. • Counsel women who are taking strong CYP3A4 inducers (for example, carbamazepine, phenytoin, rifampicin, and St.
John’s wort) not to choose Estradiol Valerate and Estradiol Valerate/Dienogest as their oral contraceptive due to the possibility of decreased contraceptive efficacy. • Counsel patients to use a back-up or alternative method of contraception when weak or moderate enzyme inducers are used with Estradiol Valerate and Estradiol Valerate/Dienogest. • Counsel patients who are breastfeeding or who desire to breastfeed that COCs may reduce breast milk production. This is less likely to occur if breastfeeding is well established. • Counsel any patient who starts COCs postpartum, and who has not yet had a period, to use an additional method of contraception until she has taken Estradiol Valerate and Estradiol Valerate/Dienogest for 9 consecutive days. • Counsel patients that amenorrhea may occur.
Rule out pregnancy in the event of amenorrhea in two or more consecutive cycles.
🍼 Nursing Mothers ▾
8.3Nursing Mothers When possible, advise the nursing mother to use other forms of contraception until she has weaned her child. Estrogen-containing COCs can reduce milk production in breastfeeding mothers. This is less likely to occur once breastfeeding is well-established; however, it can occur at any time in some women. Small amounts of oral contraceptive steroids and/or metabolites are present in breast milk.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption After oral administration of estradiol valerate, cleavage to 17β-estradiol and valeric acid takes place during absorption by the intestinal mucosa or in the course of the first liver passage. This gives rise to estradiol and its metabolites, estrone and other metabolites. Maximum serum estradiol concentrations of 73.3 pg/mL are reached at a median of approximately 6 hours (range: 1.5–12 hours) and the area under the estradiol concentration curve [AUC(0–24hr)] was 1301 pg·hr/mL after single ingestion of a tablet containing 3 mg estradiol valerate under fasted condition on Day 1 of the 28-day sequential regimen.
Bioavailability of dienogest is about 91%. Maximum serum dienogest concentrations of 91.7 ng/mL are reached at a median of approximately 1 hour (range: 0.5–1.5 hour) and the area under the dienogest concentration curve [AUC(0–24hr)] was 964 ng/mL after single oral administration of Estradiol Valerate and Estradiol Valerate/Dienogest tablet containing 2 mg estradiol valerate/3 mg dienogest under fasted condition. The pharmacokinetics of dienogest are dose-proportional within the dose range of 1–8 mg.
Steady state is reached after 4 days of the same dosage of 2 mg dienogest. The mean accumulation ratio for AUC (0–24hr) is approximately 1.24. The mean plasma pharmacokinetic parameters at steady state following repeated oral doses of a 2 mg estradiol valerate/3 mg dienogest combination tablet in fertile women under fasted condition are reported in Table 1.
Table 1 Arithmetic Mean (SD) Serum Pharmacokinetic Parameters at Steady-state (on Day 24) following Repeated Oral Doses of 2 mg EV/3 mg DNG on Days 8-24 of the 28 day Regimen in Fertile Women under Fasted Condition (N=15) Parameter Dienogest Estradiol Estrone C max C max = Maximum serum concentration 85.2 (19.7) ng/ml 70.5 (25.9) pg/ml 483 (198) pg/ml T max Tmax = Time to reach maximum concentration (hr) Median (range) for T max 1.5 (1–2) 3 (1.5–12) 4 (3–12) AUC AUC(0-24hr) = Area under the concentration-time curve from 0 hr data point up to 48 hr post-administration (0–24hr) 828 (187) ng·hr/ml 1323 (480) pg·hr/ml 7562 (3403) pg·hr/ml t ½ (hr) 12.3 (1.4) NA NA: Data not available NA Food Effect Concomitant food intake in women resulted in a 28% decrease for dienogest C max and 23% increase of estradiol C max while the exposure (AUC) of both dienogest and estradiol did not change.
Distribution In serum, 38% of estradiol is bound to sex hormone-binding globulin (SHBG), 60% to albumin and 2–3% circulates in free form. An apparent volume of distribution of approximately
1.2L/kg was determined after intravenous (IV) administration. A relatively high fraction (10%) of circulating dienogest is present in the free form, with approximately 90% being bound non-specifically to albumin. Dienogest does not bind to SHBG and corticosteroid-binding globulin (CBG).
The volume of distribution at steady state (V d,ss ) of dienogest is 46 L after the IV administration of 85 mcg 3 H-dienogest. Metabolism After oral administration of estradiol valerate, approximately 3% of the dose is directly bioavailable as estradiol. Estradiol undergoes an extensive first-pass effect and a considerable part of the dose administered is already metabolized in the gastrointestinal mucosa.
The CYP 3A family is known to play the most important role in human estradiol metabolism. Together with the pre-systemic metabolism in the liver, about 95% of the orally administered dose becomes metabolized before entering the systemic circulation. The main metabolites are estrone and its sulfate or glucuronide conjugates.
Dienogest is extensively metabolized by the known pathways of steroid metabolism (hydroxylation, conjugation), with the formation of endocrinologically mostly inactive metabolites. CYP3A4 was identified as a predominant enzyme catalyzing the metabolism of dienogest. Excretion Estradiol and its metabolites are mainly excreted in urine, with about 10% being excreted in the fe… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics The estrogen in Estradiol Valerate and Estradiol Valerate/Dienogest is estradiol valerate, a synthetic prodrug of 17ß-estradiol. The progestin in Estradiol Valerate and Estradiol Valerate/Dienogest is dienogest (DNG). DNG displays properties of 19-nortestosterone derivatives as well as properties associated with progesterone derivatives. [See Nonclinical Toxicology ( 13.2 ).] Cardiac Electrophysiology The effect of Estradiol Valerate and Estradiol Valerate/Dienogest on QT prolongation was evaluated in a randomized, double-blind, positive (moxifloxacin 400 mg) and negative (placebo) controlled crossover study in healthy subjects.
A total of 53 subjects were administered Estradiol Valerate and Estradiol Valerate/Dienogest (containing 3 mg dienogest and 2 mg estradiol valerate), dienogest 10 mg, and placebo as once daily doses for 4 days, and moxifloxacin 400 mg as a single oral dose. The upper bound of the 90% confidence interval for the largest placebo-adjusted, baseline-corrected QTc based on Fridericia’s correction method (QTcF) was below 10 msec, the threshold for regulatory concern.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Oral Contraceptive Clinical Trials The study conducted in North America (U.S. and Canada) was a multicenter, open-label, single-arm, unintended pregnancy study. There were 490 healthy subjects between 18 and 35 years of age (mean age: 25.1 years) who were treated for up to 28 cycles of 28 days each. The racial demographic of enrolled women was: Caucasian (76%), Hispanic (13%), African-American (7%), Asian (3%), and Other (1%).
The weight range for treated women was 40 to 100 kg (mean weight: 62.5 kg) and the BMI range was 14 to 30 kg/m 2 (mean BMI: 23.3 kg/m 2 ). Of treated women, 15% discontinued the study treatment due to an adverse event, 13% were lost to follow up, 10% withdrew their consent, 8% discontinued due to other reason, 1% discontinued due to protocol deviation, and 1% discontinued due to pregnancy. The study conducted in Europe (Germany, Austria and Spain) was a multicenter, open-label, single-arm contraceptive reliability study.
There were 1,377 healthy subjects between 18 and 50 years of age (mean age: 30.3 years) who were treated for 20 cycles of 28 days each. The racial demographic of enrolled women was predominantly Caucasian (99.2%). The weight range for treated women was 38 to 98 kg (mean weight: 63.8 kg) and the BMI range was 15 to 31.8 kg/m 2 (mean BMI: 22.8 kg/m 2 ).
Of treated women, 10% discontinued the study treatment due to an adverse event, 5% discontinued due to other reason, 2% were lost to follow up, 2% discontinued due to protocol deviation, 2% withdrew their consent, and 1% discontinued due to pregnancy. The Pearl Index (PI) was the primary efficacy endpoint used to assess contraceptive reliability and was assessed in each of the two studies, assuming all subjects were at risk of pregnancy in all medication cycles unless back-up contraception was documented. The PI is based on pregnancies that occurred after the onset of treatment and within 7 days after the last pill intake.
Cycles in which conception did not occur, but which included the use of back-up contraception, were not included in the calculation of the PI. The PI also includes patients who did not take the drug correctly. The estimated PI for the North American study is 1.64 and the estimated PI for the European study is 1.04.
The Kaplan-Meier method was also used to calculate the contraceptive failure rate. The summary of the Pearl Indexes and cumulative contraceptive failure rates are provided in Table 2: Table 2 Summary of the Pearl Indexes and the Cumulative Contraceptive Failure Rates Study Age Group Relative Treatment Exposure Cycles Total treatment exposure time without back-up contraception Number of Pregnancies within 13 Cycles and 7 Days after Last Treatment Pearl Index Upper Limit of 95% CI Contraceptive Failure Rate at the End of First Year North America 18–35 3,969 5 1.64 3.82 0.016 Europe 18–35 11,275 9 1.04 1.97 0.010
14.2Heavy Menstrual Bleeding Clinical Trials The efficacy and safety of Estradiol Valerate and Estradiol Valerate/Dienogest were evaluated in two multi-regional, multicenter, double-blind, randomized, placebo-controlled clinical trials. Study 308960 was performed in the United States and Canada and Study 308961 was performed in Australia and 9 European countries. The studies were identical in design.
The studies enrolled women, 18 years of age or older, with a diagnosis of dysfunctional uterine bleeding characterized as heavy, prolonged and/or frequent bleeding without organic pathology. Heavy menstrual bleeding (HMB) was defined as menstrual blood loss of 80 mL or more in at least 2 bleeding episodes. The diagnosis of HMB was documented through the collection of used sanitary protection (pads and tampons) to quantify blood loss assessed by the alkaline hematin method.
Overall, about 85% of the subjects qualified for the study because they had heavy menstrual bleeding symptoms. A total of 421 women with a mean age of 38.2 and a mean BMI of 25.5 were randomized to the two clinical… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In a 24 month carcinogenicity study in mice dosed orally with dienogest by gavage with doses of 5, 15 and 50 mg/kg/day (males) and 10, 30 and 100 mg/kg/day (females), the systemic exposures in the females were 1.1, 3.5, and 10.6 times the exposure (AUC of dienogest) of women taking a 3 mg dose. A statistically significantly higher incidence of stromal polyps of the uterus was observed in females given 100 mg/kg. In a similar study in rats given 1, 3, and 10 mg/kg for 104 weeks, 0.2, 1.4, and 6.1 times the exposure of women taking a 3 mg dose, there were no statistically significant drug-related neoplasms.
Dienogest was not mutagenic in in vitro reverse mutation tests in bacteria, in chromosome aberration tests in human peripheral lymphocytes, mouse lymphoma cells, and Chinese hamster lung cells, and tests of unscheduled DNA synthesis (UDS) in rat and human liver cells. Dienogest was also negative in an in vivo mouse micronucleus test, a rat liver initiation-promotion model, and an in vitro/in vivo UDS test in female rats.
13.2Animal Toxicology and/or Pharmacology Nonclinical studies in animals and in vitro , have shown that besides progestogenic activities, DNG is devoid of estrogenic, androgenic, glucocorticoid and mineralocorticoid activities.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In a 24 month carcinogenicity study in mice dosed orally with dienogest by gavage with doses of 5, 15 and 50 mg/kg/day (males) and 10, 30 and 100 mg/kg/day (females), the systemic exposures in the females were 1.1, 3.5, and 10.6 times the exposure (AUC of dienogest) of women taking a 3 mg dose. A statistically significantly higher incidence of stromal polyps of the uterus was observed in females given 100 mg/kg. In a similar study in rats given 1, 3, and 10 mg/kg for 104 weeks, 0.2, 1.4, and 6.1 times the exposure of women taking a 3 mg dose, there were no statistically significant drug-related neoplasms.
Dienogest was not mutagenic in in vitro reverse mutation tests in bacteria, in chromosome aberration tests in human peripheral lymphocytes, mouse lymphoma cells, and Chinese hamster lung cells, and tests of unscheduled DNA synthesis (UDS) in rat and human liver cells. Dienogest was also negative in an in vivo mouse micronucleus test, a rat liver initiation-promotion model, and an in vitro/in vivo UDS test in female rats.
📄 Patient Package Insert ▾
FDA-Approved Patient Labeling Guide for Using Estradiol Valerate and Estradiol Valerate/Dienogest WARNING TO WOMEN WHO SMOKE Do not use Estradiol Valerate and Estradiol Valerate/Dienogest if you smoke cigarettes and are over 35 years old. Smoking increases your risk of serious cardiovascular side effects (heart and blood vessel problems) from birth control pills, including death from heart attack, blood clots or stroke. This risk increases with age and the number of cigarettes you smoke.
Birth control pills help to lower the chances of becoming pregnant when taken as directed. They do not protect against HIV infection (AIDS) and other sexually transmitted diseases. What Is Estradiol Valerate and Estradiol Valerate/Dienogest?
Estradiol Valerate and Estradiol Valerate/Dienogest is a birth control pill. It contains two female hormones, an estrogen called estradiol valerate and a progestin called dienogest. Estradiol valerate is a synthetic estrogen that is converted to estradiol in your body.
Estradiol Valerate and Estradiol Valerate/Dienogest is used to treat heavy menstruation (your monthly period) that is not caused by any diagnosed conditions of the uterus (womb) in women who decide to use an oral contraceptive for birth control. Talk to your healthcare provider to determine if your bleeding is heavier than normal. How Does Estradiol Valerate and Estradiol Valerate/Dienogest Work?
Birth control pills prevent your ovaries from producing and releasing mature eggs. Estradiol Valerate and Estradiol Valerate/Dienogest decreases menstrual bleeding by thinning the lining of the uterus. How Well Does Estradiol Valerate and Estradiol Valerate/Dienogest Work For Contraception?
Your chance of getting pregnant depends on how well you follow the directions for taking your birth control pills. The better you follow the directions, the less chance you have of getting pregnant. Based on the results of two clinical studies, 1 to 2 women out of 100 women may get pregnant during the first year they use Estradiol Valerate and Estradiol Valerate/Dienogest.
The following chart shows the chance of getting pregnant for women who use different methods of birth control. Each box on the chart contains a list of birth control methods that are similar in effectiveness. The most effective methods are at the top of the chart.
The box on the bottom of the chart shows the chance of getting pregnant for women who do not use birth control and are trying to get pregnant. How Well Does Estradiol Valerate and Estradiol Valerate/Dienogest Work For Heavy Menstrual Bleeding? In two clinical trials in women with heavy menstrual bleeding who were treated with Estradiol Valerate and Estradiol Valerate/Dienogest, their menstrual bleeding was reduced by an average of 90% in one trial and 87% in the other.
For women treated with placebo, their menstrual bleeding was reduced by an average of 14% and 32% in the two trials, respectively. How Do I Take Estradiol Valerate and Estradiol Valerate/Dienogest? • Take one pill every day at the same time. Take the pills in the order directed on the blister pack. • Do not skip pills or delay taking your pill by more than 12 hours.
If you miss pills (including starting the pack late), you could get pregnant. The more pills you miss, the more likely you are to get pregnant. • If you have trouble remembering to take Estradiol Valerate and Estradiol Valerate/Dienogest, talk to your healthcare provider about how to make pill-taking easier, or about using another method of birth control. • You may have spotting or light bleeding when you first take Estradiol Valerate and Estradiol Valerate/Dienogest. Spotting or light bleeding is normal at first. • You may feel sick to your stomach (nauseous), especially during the first few months that you take Estradiol Valerate and Estradiol Valerate/Dienogest.
If you feel sick to your stomach, do not stop taking the pill. The problem will usually go away. If your nausea doesn't go away, call your health… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
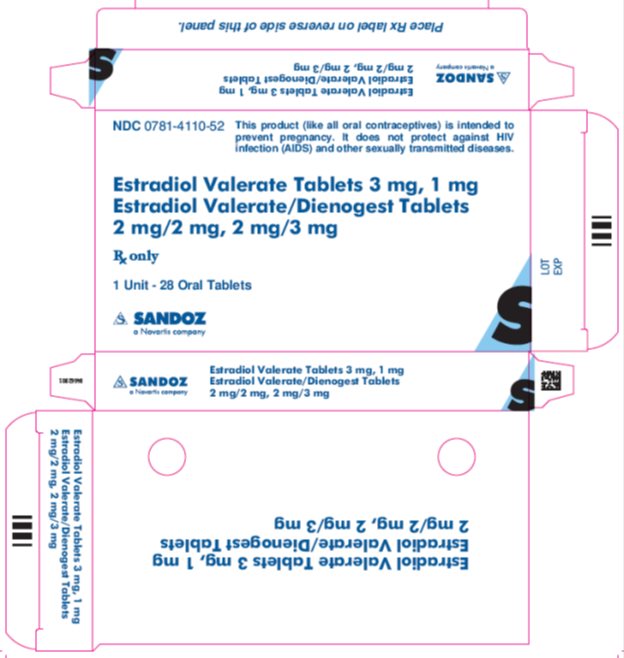
PACKAGE/LABEL PRINCIPAL DISPLAY PANEL Estradiol Valerate and Estradiol Valerate/Dienogest NDC 0781-4110-52 1 Unit Rx only This product (like all oral contraceptives) is intended to prevent pregnancy. It does not protect against HIV infection (AIDS) and other sexually transmitted diseases. Estradiol Valerate and Estradiol Valerate/Dienogest Tablets estradiol valerate 3 mg, 1 mg tablets estradiol valerate/dienogest 2 mg/2 mg, 2mg/3 mg tablets 28 tablets oral Single carton
Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Where does this data come from?
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |