
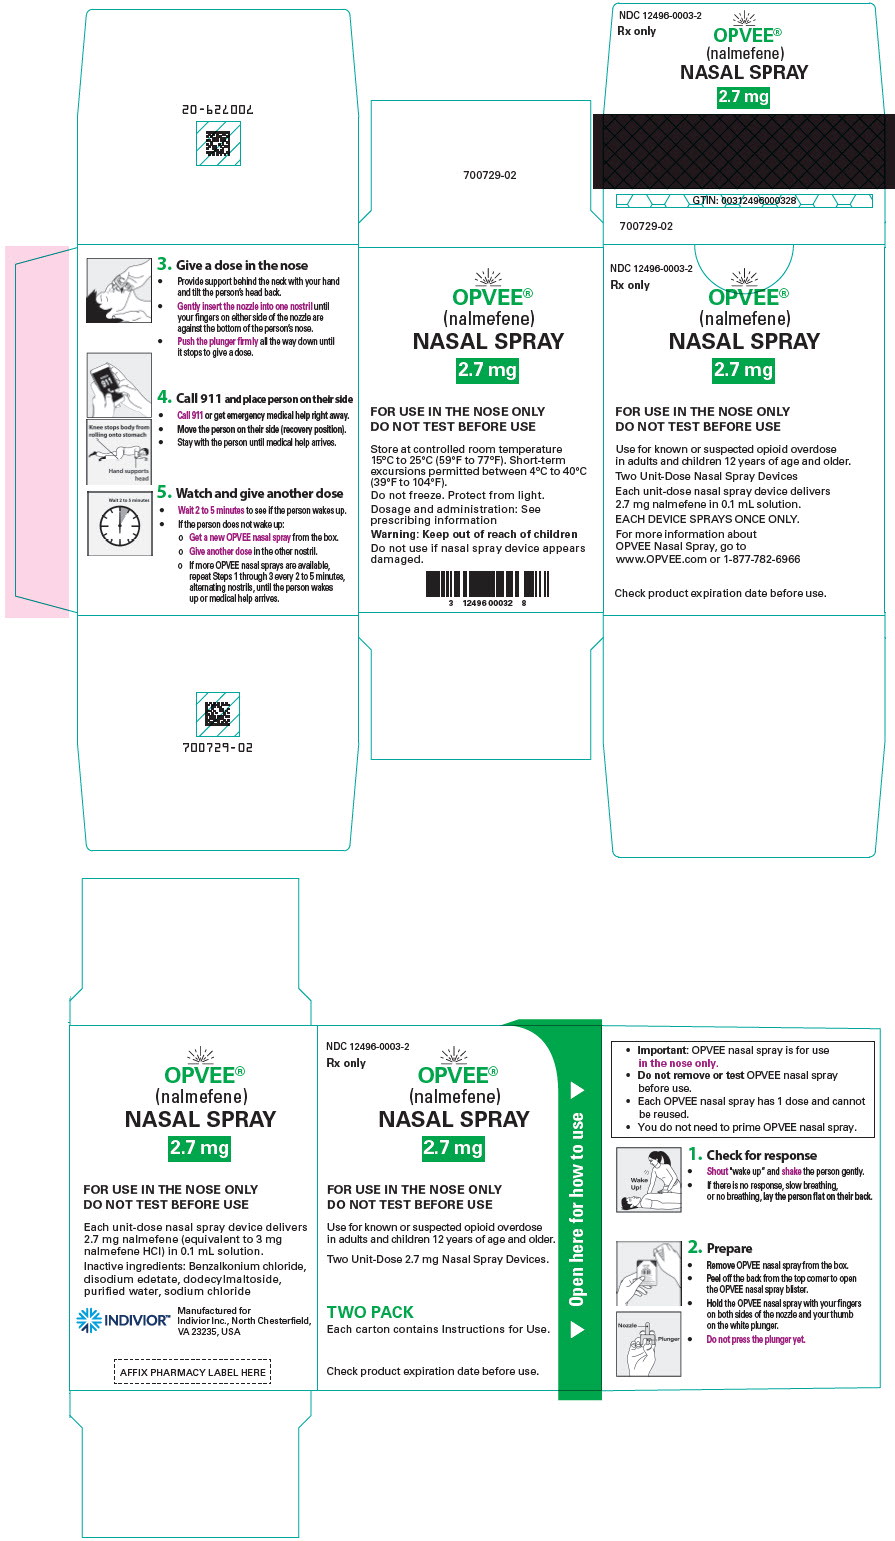
OPVEE nalmefene hydrochloride 2.7 mg/100uL Spray
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Opioid Antagonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Nalmefene nasal spray is used along with emergency medical treatment to reverse the life-threatening effects of a known or suspected opiate (narcotic) overdose in adults and children 12 years of age and older. Nalmefene nasal spray is in a class of medications called opiate antagonists. It works by blocking the effects of opiates to relieve dangerous symptoms caused by high levels of opiates in the blood.
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $46.736 | $9,347.26 / 200 uls |
| Medicaid paysCMS SDUD · 12 mo | $52.74 | $10,548.44 / 200 uls |
| Medicare drug plans payPart D · Q2 2026 | $49.73 | $9,946.20 / 200 uls |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Opvee 2.7 mg/100uLthis 12496-0003-02 | Indivior | 1 vial | $46.736 | — | Availability likely | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 12290596 ↗ | Method of use | U-4182 | Aug 4, 2042 |
| US 11458091 ↗ | Method of use | U-3630 | Jul 10, 2038 |
| Code | What it grants | Expires |
|---|---|---|
| NP | New Product | May 22, 2026 |
Is there a generic version of OPVEE 2.7 MG NASAL SPRAY?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 12496-0003-02 You're viewing this | 2 BLISTER PACK in 1 CARTON (12496-0003-2) / 1 VIAL, SINGLE-DOSE in 1 BLISTER PACK (12496-0003-1) / 100 uL in 1 VIAL, SINGLE-DOSE | 2023-10-02 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE OPVEE nasal spray is indicated for the emergency treatment of known or suspected overdose induced by natural or synthetic opioids in adults and pediatric patients aged 12 years and older, as manifested by respiratory and/or central nervous system depression. OPVEE nasal spray is intended for immediate administration as emergency therapy in settings where opioids may be present. OPVEE nasal spray is not a substitute for emergency medical care.
OPVEE nasal spray is an opioid antagonist indicated for the emergency treatment of known or suspected overdose induced by natural or synthetic opioids in adults and pediatric patients aged 12 years and older, as manifested by respiratory and/or central nervous system depression. OPVEE nasal spray is intended for immediate administration as emergency therapy in settings where opioids may be present. OPVEE nasal spray is not a substitute for emergency medical care.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION OPVEE nasal spray is for intranasal use only ( 2.1 ) Seek emergency care immediately after use ( 2.1 ) Administer a single spray of OPVEE nasal spray intranasally into nose. ( 2.2 ) Administer additional doses of OPVEE nasal spray, using a new nasal spray with each dose, if the patient does not respond or responds and then relapses into respiratory depression, additional doses of OPVEE nasal spray may be given every 2 to 5 minutes until emergency medical assistance arrives. ( 2.2 ) Additional supportive and/or resuscitative measures may be helpful while awaiting emergency medical assistance.
( 2.2 )
2.1Important Administration Instructions OPVEE is for intranasal use only. The device is ready to use. No device assembly is required.
Do not prime or test prior to administration. OPVEE nasal spray delivers its entire contents automatically, upon activation. Do not attempt to reuse OPVEE.
Each unit-dose device contains a single dose of nalmefene and cannot be reused. No device assembly is required. Because treatment of suspected opioid overdose must be performed by someone other than the patient, instruct the prescription recipient to inform those around them about the presence of OPVEE nasal spray and the Instructions for Use .
Instruct the patient or caregiver to read the Instructions for Use at the time they receive a prescription for OPVEE nasal spray. Emphasize the following instructions to the patient or caregiver: Administer OPVEE nasal spray as quickly as possible because prolonged respiratory depression may result in damage to the central nervous system or death. Always seek emergency medical assistance after administration of the first dose of OPVEE nasal spray in the event of a suspected, potentially life-threatening opioid emergency.
Keep the patient under continued surveillance until emergency personnel arrive. Additional doses of OPVEE nasal spray may be required until emergency medical assistance becomes available. Re-administer OPVEE nasal spray, using a new nasal spray, in the nose, every 2 to 5 minutes if the patient does not respond or responds and then relapses into respiratory depression.
Administer OPVEE nasal spray according to the printed instructions on the Quick Start Guide and the Instructions for Use . Place the patient in the supine position. Prior to administration, be sure the device nozzle is inserted in the nose of the patient and provide support to the back of the neck to allow the head to tilt back.
Do not prime or test the device prior to administration. To administer the dose, press firmly on the device plunger and remove the device nozzle from the nose after use. If the patient responds by waking up to the voice or touch or starts breathing normally, place the patient on their side (recovery position) as shown in the Instructions for Use and call for emergency medical assistance immediately after administration of the first dose of OPVEE nasal spray.
2.2Dosing in Adults and Pediatric Patients aged 12 years and older Initial Dosing: The recommended initial dose of OPVEE nasal spray in adults and pediatric patients aged 12 years and older is one spray delivered by intranasal administration, which delivers 2.7 mg of nalmefene. Repeat Dosing: Seek emergency medical assistance as soon as possible after intranasal administration of the first dose of OPVEE nasal spray. The requirement for repeat doses of OPVEE nasal spray (2.7 mg) depends upon the amount, type, and route of administration of the opioid being antagonized.
If the patient responds to OPVEE nasal spray and relapses back into respiratory depression before emergency assistance arrives, administer an additional dose of OPVEE in the opposite nostril using a new OPVEE nasal spray and continue surveillance of the patient. If the desired response is not obtained after 2 to 5 minutes, administer an additional dose of OPVEE using a new OPVEE nasal spray device. If there is still no response and additional doses are a…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Nasal spray: 2.7 mg nalmefene per device. Each unit-dose nasal spray device delivers a single spray containing 2.7 mg of nalmefene. Nasal spray: 2.7 mg of nalmefene in 0.1 mL ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS OPVEE nasal spray is contraindicated in patients known to be hypersensitive to nalmefene or to any of the other ingredients. Hypersensitivity to nalmefene or to any of the other ingredients. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Risk of Recurrent Respiratory and Central Nervous System Depression : While the duration of action of nalmefene is as long as most opioids, a recurrence of respiratory depression is possible, therefore, keep patient under continued surveillance and administer repeat doses of OPVEE using a new nasal spray with each dose, as necessary, while awaiting emergency medical assistance ( 5.1 ) Limited Efficacy with Partial Agonists or Mixed Agonist/Antagonists : Reversal of respiratory depression caused by partial agonists or mixed agonists/antagonists, such as buprenorphine and pentazocine, may be incomplete.
Larger or repeat doses may be required. ( 5.2 ) Precipitation of Severe Opioid Withdrawal : Use in patients who are opioid dependent may precipitate opioid withdrawal. In neonates, opioid withdrawal may be life-threatening if not recognized and properly treated.
Monitor for the development of opioid withdrawal. ( 5.3 ) Risk of Cardiovascular (CV) Effects : Abrupt postoperative reversal of opioid depression may result in adverse CV effects. These events have primarily occurred in patients who had preexisting CV disorders or received other drugs that may have similar adverse CV effects.
Monitor these patients closely in an appropriate healthcare setting after use of nalmefene hydrochloride. ( 5.3 ) Risk of Opioid Overdose from Attempts to Overcome the Blockade : Attempts to overcome opioid withdrawal symptoms caused by opioid antagonists with high or repeated doses of exogenous opioids may lead to opioid intoxication and death ( 5.4 )
5.1Risk of Recurrent Respiratory and Central Nervous System Depression Respiratory depression in the community overdose setting may be complex and involve the effects of multiple or unknown drugs, some of which may be long-acting opioids. While the duration of action of nalmefene is as long as most opioids, a recurrence of respiratory depression is possible, even after an apparently adequate initial response to OPVEE nasal spray treatment [See Clinical Pharmacology, Pharmacodynamics (12.3) ] . Therefore, it is necessary to seek emergency medical assistance immediately after administration of the first dose of OPVEE nasal spray and to keep the patient under continued surveillance.
A second dose may be necessary if there is recurrence of symptoms of opioid overdose. Additional supportive and/or resuscitative measures may be helpful while awaiting emergency medical assistance [see Dosage and Administration (2.2) ].
5.2Risk of Limited Efficacy with Partial Agonists or Mixed Agonist/Antagonists Reversal of respiratory depression by partial agonists or mixed agonist/antagonists such as buprenorphine and pentazocine, may be incomplete. Repeat doses of OPVEE nasal spray may be required to antagonize buprenorphine because the latter has a long duration of action due to its slow rate of binding and subsequent slow dissociation from the opioid receptor [see Dosage and Administration (2.3) ] . Buprenorphine antagonism is characterized by a gradual onset of the reversal effects and a decreased duration of action of the normally prolonged respiratory depression.
5.3Precipitation of Severe Opioid Withdrawal The use of OPVEE in patients who are opioid dependent may precipitate opioid withdrawal characterized by the following signs and symptoms: body aches, diarrhea, tachycardia, fever, runny nose, sneezing, piloerection, sweating, yawning, nausea or vomiting, nervousness, restlessness or irritability, shivering or trembling, abdominal cramps, weakness, and increased blood pressure. Abrupt postoperative reversal of opioid depression after using OPVEE may result in nausea, vomiting, sweating, tremulousness, tachycardia, hypotension, hypertension, seizures, ventricular tachycardia and fibrillation, pulmonary edema, and cardiac arrest.
Death, coma, and encephalopathy have been reported as sequelae of these events. These events have primarily occurred in patients who had pre-existing cardiova…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed elsewhere in the labeling: Recurrent Respiratory and Central Nervous System Depression [see Warnings and Precautions (5.1) ] Precipitation of Severe Opioid Withdrawal [see Warnings and Precautions (5.3) ] Most common adverse reactions (incidence at least 2%) are nasal discomfort, headache, nausea, dizziness, hot flush, vomiting, anxiety, fatigue, nasal congestion, throat irritation, rhinalgia, decreased appetite, dysgeusia, erythema, and hyperhidrosis.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Indivior Inc. at 1-877-782-6966 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to the rates in clinical trials of another drug and may not reflect the rates observed in practice. The safety of OPVEE nasal spray is supported by safety and pharmacokinetic studies of OPVEE nasal spray in healthy subjects in a normal state and under steady state opioid agonism. The following adverse reactions were observed.
In a pharmacokinetic study of 66 healthy adult volunteers exposed to one spray of OPVEE nasal spray in one nostril the most common adverse reactions were: nasal discomfort and dizziness. In a second pharmacokinetic study of 24 healthy adult volunteers exposed to one spray of OPVEE nasal spray in one nostril, two sprays of OPVEE nasal spray in one nostril or one spray of OPVEE nasal spray in each nostril, the most common adverse reactions were: rhinalgia, nasal congestion, nasal discomfort and nausea. In a pharmacodynamic study of 61 healthy adult volunteers exposed to one spray of OPVEE nasal spray in one nostril, the most common adverse reactions were: headache, nausea, hot flush and dizziness.
Table 1: Relative Frequencies of Treatment-Related Common Adverse Events That Occurred in Greater Than 1% of Healthy Adult Volunteers Nalmefene 2.7 mg Nalmefene 5.4 mg System Organ Class Preferred Term Total 2.7 mg N=150 n (%) PD Study N=61 n (%) PK Studies N=89 n (%) PK Study (1 spray in each nostril) N=23 n (%) PK Study (2 sprays in one nostril) N=24 n (%) PK Studies OPNT003-PK-001 + OPNT003-PK-002 and PD Study OPNT003-OOD-001 Respiratory, thoracic and mediastinal disorders Nasal discomfort 43 (28.7%) 5 (8.2%) 38 (42.7%) 3 (13.0%) 3 (12.5%) Nasal congestion 6 (4.0%) 2 (3.3%) 4 (4.5%) 1 (4.3%) 4 (16.7%) Throat irritation 6 (4.0%) 3 (4.9%) 3 (3.4%) 0 0 Rhinalgia 4 (2.7%) 1 (1.6%) 3 (3.4%) 2 (8.7%) 6 (25.0%) Dyspnea 2 (1.3%) 2 (3.3%) 0 0 0 Oropharyngeal pain 2 (1.3%) 2 (3.3%) 0 1 (4.3%) 1 (4.2%) Nervous system disorders Headache 40 (26.7%) 34 (55.7%) 6 (6.7%) 1 (4.3%) 0 Dizziness 14 (9.3%) 9 (14.8%) 5 (5.6%) 0 1 (4.2%) Dysgeusia 3 (2.0%) 2 (3.3%) 1 (1.1%) 0 0 Paresthesia 2 (1.3%) 2 (3.3%) 0 1 (4.3%) 1 (4.2%) Presyncope 0 0 0 1 (4.3%) 0 Gastrointestinal disorders Nausea 25 (16.7%) 22 (36.1%) 3 (3.4%) 5 (21.7%) 1 (4.2%) Vomiting 9 (6.0%) 7 (11.5%) 2 (2.2%) 1 (4.3%) 0 Abdominal pain 2 (1.3%) 1 (1.6%) 1 (1.1%) 0 0 Dry mouth 1 (0.7%) 1 (1.6%) 0 1 (4.3%) 0 Constipation 0 0 0 0 1 (4.2%) Vascular disorders Hot flush 12 (8.0%) 12 (19.7%) 0 0 0 Psychiatric disorders Anxiety 7 (4.7%) 7 (11.5%) 0 0 0 Agitation 2 (1.3%) 2 (3.3%) 0 0 0 Claustrophobia 2 (1.3%) 2 (3.3%) 0 0 0 Insomnia 1 (0.7%) 0 1 (1.1%) 1 (4.3%) 0 General disorders and administration site conditions Fatigue 6 (4.0%) 3 (4.9%) 3 (3.4%) 0 0 Chills 2 (1.3%) 2 (3.3%) 0 0 0 Chest discomfort 0 0 0 1 (4.3%) 0 Skin and subcutaneous tissue disorders Erythema 3 (2.0%) 0 3 (3.4%) 1 (4.3%) 1 (4.2%) Hyperhidrosis 3 (2.0%) 3 (6.6%) 0 0 1 (4.2%) Urticaria 0 0 0 0 1 (4.2%) Metabolism and nutrition disorders Decreased appetite 3 (2.0%) 2 (3.3%) 1 (1.1%) 0 0 Infections and infestations Rhinitis 1 (0.7%) 0 1 (1.1%) 1 (4.3%) 0 Eye disorders Dry eye 0 0 0 1 (4.3%) 0 Cardiac disorders Tachycardia 0 0 0 1 (4.3%) 0 Adverse reaction information…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Life-sustaining therapy for opioid overdose should not be withheld (see Clinical Considerations ). There are no available data on nalmefene use in pregnant women to evaluate for a drug-associated risk of major birth defects or miscarriage. In animal reproduction studies, no embryotoxic effects on embryo-fetal development were observed in rats and rabbits treated with nalmefene at exposures at least 6 times (rats) and up to 20 times (rabbits) the exposure at two human nasal doses of 5.4 mg (see Data ) .
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk An opioid overdose is a medical emergency and can be fatal for the pregnant woman and fetus if left untreated. Treatment with OPVEE for opioid overdose should not be withheld because of potential concerns regarding the effects of OPVEE on the fetus. Data Animal Data Reproduction studies have been performed in rats (up to 1200 mg/m 2 /day) and rabbits (up to 2400 mg/m 2 /day) by oral administration of nalmefene and in rabbits by intravenous administration up to 96 mg/m 2 /day.
No effects on embryo-fetal development were observed at exposures at least 6 times (rats) and up to 20 times (rabbits) the exposure corresponding to a human dose of 5.4 mg (two nalmefene nasal sprays) on an AUC basis. The treatment in rats did not affect offspring survival.
8.2Lactation Risk Summary There are no data on the presence of nalmefene and its metabolites in human milk, the effects of nalmefene on the breastfed child, or the effects on milk production. Nalmefene and its metabolites are present in rat milk (see Data ). When a drug is present in animal milk, it is likely that the drug will be present in human milk.
Data Nalmefene and its metabolites were secreted into rat milk, reaching concentrations approximately three times those in plasma at one hour and decreasing to about half the corresponding plasma concentrations by 24 hours following bolus administration. The concentration of nalmefene in animal milk does not necessarily predict the concentration of drug in human milk.
8.4Pediatric Use The safety and effectiveness of OPVEE nasal spray for the emergency treatment of known or suspected opioid overdose in adults and pediatric patients aged 12 years and older, as manifested by respiratory and/or central nervous system depression, have been established. Use for this indication in this age group is supported by adult studies and pharmacokinetic simulation [see Clinical Pharmacology (12.3) ] . There have been no studies conducted to evaluate the use of OPVEE nasal spray in pediatric patients.
The safety and effectiveness of OPVEE nasal spray for the emergency treatment of known or suspected opioid overdose, as manifested by respiratory and/or central nervous system depression have not been established in pediatric patients younger than 12 years of age.
8.5Geriatric Use Clinical studies of OPVEE nasal spray did not include subjects aged 65 and over. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. Geriatric patients have a greater frequency of decreased hepatic, renal, or cardiac function and of concomitant disease or other drug therapy. Therefore, the systemic exposure of nalmefene can be higher in these patients.
8.6Hepatic Impairment Hepatic impairment substantially reduces the clearance of nalmefene [see Clinical Pharmacology (12.3) ]. For single episodes of opioid antagonism, adjustment of OPVEE nasal spray dosage is not required.
8.7 Renal Impairment Renal impairment substa…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Life-sustaining therapy for opioid overdose should not be withheld (see Clinical Considerations ). There are no available data on nalmefene use in pregnant women to evaluate for a drug-associated risk of major birth defects or miscarriage. In animal reproduction studies, no embryotoxic effects on embryo-fetal development were observed in rats and rabbits treated with nalmefene at exposures at least 6 times (rats) and up to 20 times (rabbits) the exposure at two human nasal doses of 5.4 mg (see Data ) .
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk An opioid overdose is a medical emergency and can be fatal for the pregnant woman and fetus if left untreated. Treatment with OPVEE for opioid overdose should not be withheld because of potential concerns regarding the effects of OPVEE on the fetus. Data Animal Data Reproduction studies have been performed in rats (up to 1200 mg/m 2 /day) and rabbits (up to 2400 mg/m 2 /day) by oral administration of nalmefene and in rabbits by intravenous administration up to 96 mg/m 2 /day.
No effects on embryo-fetal development were observed at exposures at least 6 times (rats) and up to 20 times (rabbits) the exposure corresponding to a human dose of 5.4 mg (two nalmefene nasal sprays) on an AUC basis. The treatment in rats did not affect offspring survival.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of OPVEE nasal spray for the emergency treatment of known or suspected opioid overdose in adults and pediatric patients aged 12 years and older, as manifested by respiratory and/or central nervous system depression, have been established. Use for this indication in this age group is supported by adult studies and pharmacokinetic simulation [see Clinical Pharmacology (12.3) ] . There have been no studies conducted to evaluate the use of OPVEE nasal spray in pediatric patients.
The safety and effectiveness of OPVEE nasal spray for the emergency treatment of known or suspected opioid overdose, as manifested by respiratory and/or central nervous system depression have not been established in pediatric patients younger than 12 years of age.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of OPVEE nasal spray did not include subjects aged 65 and over. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. Geriatric patients have a greater frequency of decreased hepatic, renal, or cardiac function and of concomitant disease or other drug therapy. Therefore, the systemic exposure of nalmefene can be higher in these patients.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action OPVEE is an antagonist at opioid receptors.
12.2Pharmacodynamics Nalmefene reverses the effects of natural and synthetic opioids, including respiratory depression, sedation, and hypotension. Pharmacodynamic studies have shown that nalmefene injection has a longer duration of action than naloxone injection at fully reversing doses. Nalmefene has no opioid agonist activity.
The effect of 2.7 mg OPVEE on remifentanil-induced respiratory depression in an experimental ventilatory-response to hypercapnia model, assessed by changes in minute ventilation (MV), was evaluated in sixty-one opioid-experienced, non-dependent subjects. In this study subjects started receiving a hypercapnic gas mixture (50% O2, 43% N2, 7% CO2) at -25 minutes. Just prior to initiation of remifentanil infusion at -15 minutes is the baseline MV (marked as 100% in Figure 1 and marked as observed data as liters/minute in Figure 2).
Fifteen minutes after initiating remifentanil infusion, nadir in minute ventilation is observed at time zero, at which point OPVEE was administered. The subjects were then monitored for changes in MV over 120 minutes. Following OPVEE administration the time to onset of effect, that is onset of reversal of respiratory depression, was observed between 2.5 to 5 minutes (Figure 1 and Figure 2).
At 5 minutes the estimated mean increase in minute ventilation was 5.745 L/min (Figure 2). Full recovery of respiratory drive was noted between 5 and 15 minutes after OPVEE administration (Figure 1 and Figure 2). Figure 1 : Percentage recovery of respiratory drive after infusion of remifentanil in CO2 stimulated minute ventilation (mean +/- standard deviation) in adult healthy volunteers treated with OPVEE (nalmefene) nasal spray Figure 2: Reversal of Remifentanil-Induced Respiratory Depression (Mean Minute Ventilation +/- Standard Deviation) by OPVEE (nalmefene) nasal spray Remifentanil (an initial bolus of 0.5 µg/kg dose followed by an infusion rate of 0.175 µg/kg/min) was administered for 15 min prior to test agents and continued for the duration of the study.
The dashed line represents the mean minute ventilation (MV) prior to remifentanil administration. Based on population pharmacokinetic/pharmacodynamic model simulations, the EC50 (drug concentration at which pharmacological effect is half maximum change in response) was 1.50 ng/mL for OPVEE following a single 2.7 mg administration. The time to reach EC50 was 4 minutes for OPVEE.
The plasma concentrations remained above the EC50 for 5.94 hours for OPVEE. Nalmefene is not known to produce respiratory depression, psychotomimetic effects, or pupillary constriction. No pharmacological activity was observed when nalmefene was administered in the absence of opioid agonists.
Nalmefene has not been shown to produce tolerance, physical dependence, or abuse potential. Nalmefene can produce acute withdrawal symptoms in individuals who are opioid dependent. Figure 1 Figure 2
12.3Pharmacokinetics In a pharmacokinetic study (OPNT003-PK-001) in 68 healthy adult subjects, the relative bioavailability of one 2.7 mg OPVEE nasal spray in one nostril (0.1 mL of 27 mg/mL nalmefene), was compared to a single dose of nalmefene 1.0 mg administered as an intramuscular injection. Subjects remained fully supine and were instructed to hold their breath during the intranasal spray administration. The pharmacokinetic parameters obtained in this study are shown in Table 3 and the plasma concentration time profiles of nalmefene are presented in Figure 3.
Table 3: Geometric Mean (CV%) PK Parameters of Nalmefene after Intranasal (IN) Administration of 2.7 mg OPVEE nasal spray and Intramuscular (IM) Administration of 1.0 mg of Nalmefene Parameter OPVEE Nalmefene IM NA Not applicable T max (h) T max presented as median (range) 0.250 (0.0833-2.00) 0.33 (0.117-18.0) C max (ng/mL) Arithmetic mean 10.4 (62.6) 1.50 (59.4) AUC 0-2.5min (ng-hr/mL) 0.00763 (233) 0.00168 (186) AUC 0-5m…
🧬 Mechanism of Action ▾
12.1Mechanism of Action OPVEE is an antagonist at opioid receptors.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Each unit-dose nasal spray device delivers 2.7 mg of nalmefene (equivalent to 3 mg of nalmefene hydrochloride) in 0.1 mL. Each carton contains two unit-dose nasal spray devices. NDC # 12496-0003-2 OPVEE is not made with natural rubber latex.
16.2Storage and Handling Store OPVEE nasal spray in the blister and cartons provided. Store OPVEE nasal spray at controlled room temperature 15°C to 25°C (59°F to 77°F). Short-term excursions permitted between 4°C to 40°C (39°F to 104°F). Do not freeze. Protect from light. Do not open individual blister packs or test nasal spray devices before use. Each unit-dose nasal spray device sprays one (1) time and cannot be re-used.
📦 Storage and Handling ▾
16.2Storage and Handling Store OPVEE nasal spray in the blister and cartons provided. Store OPVEE nasal spray at controlled room temperature 15°C to 25°C (59°F to 77°F). Short-term excursions permitted between 4°C to 40°C (39°F to 104°F). Do not freeze. Protect from light. Do not open individual blister packs or test nasal spray devices before use. Each unit-dose nasal spray device sprays one (1) time and cannot be re-used.
📋 Description ▾
11 DESCRIPTION OPVEE (nalmefene) nasal spray is a pre-filled, unit-dose intranasal spray. Nalmefene, an opioid antagonist, is a 6-methylene analogue of naltrexone. The molecular structure of nalmefene is presented below: Molecular Formula: C 21 H 25 NO 3 ∙HCl Molecular Weight: 375.9, CAS # 58895-64-0 Chemical Name: 17-(Cyclopropylmethyl)-4,5α-epoxy-6-methylenemorphinan-3,14-diol, hydrochloride salt.
Nalmefene is a white to off-white crystalline powder which is freely soluble in methanol and water, with a pK of 7.63. Each OPVEE nasal spray unit delivers 2.7 mg nalmefene (equivalent to 3mg nalmefene hydrochloride) in 0.1 mL solution. Inactive ingredients include benzalkonium chloride, disodium ethylenediaminetetraacetate, dodecylmaltoside, sodium chloride, and purified water.
The pH range is 4.1 to 4.9. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient and family members or caregivers to read the FDA-approved patient labeling (Patient Information and Instructions for Use). Recognition of Opioid Overdose Inform patients and their family members or caregivers about how to recognize the signs and symptoms of an opioid overdose such as the following: Extreme somnolence -inability to awaken a patient verbally or upon a firm sternal rub. Respiratory depression -this can range from slow or shallow respiration to no respiration in a patient who is unarousable.
Other signs and symptoms that may accompany somnolence and respiratory depression include the following: Miosis Bradycardia and/or hypotension. Risk of Recurrent Respiratory Depression While the duration of action of nalmefene is as long as most opioids, instruct patients and their family members or caregivers that they must seek immediate emergency medical assistance after administration of the first dose of OPVEE and keep the patient under continued surveillance, even after an apparently adequate initial response to OPVEE nasal spray treatment.
A second dose may be necessary if there is recurrence of symptoms of opioid overdose [see Dosage and Administration (2.1) , Warnings and Precautions (5.1) ]. Limited Efficacy for/with Partial Agonists or Mixed Agonist/Antagonists Instruct patients and their family members or caregivers that the reversal of respiratory depression caused by partial agonists or mixed agonist/antagonists, such as buprenorphine and pentazocine, may be incomplete and may require repeated administration of OPVEE nasal spray, using a new nasal spray device each time [see Dosage and Administration (2.3) , Warnings and Precautions (5.2) ] .
Precipitation of Severe Opioid Withdrawal Instruct patients and their family members or caregivers that the use of OPVEE nasal spray in patients who are opioid dependent may precipitate opioid withdrawal [see Warnings and Precautions (5.3) , Adverse Reactions (6) ] . Administration Instructions Instruct patients and their family members or caregivers to: Ensure OPVEE is readily available in locations where persons may be intentionally or accidentally exposed to an opioid overdose (i.e., opioid emergencies). Use each OPVEE device only one time.
Do not test or prime prior to use [see Dosage and Administration (2.1) ] . Administer OPVEE as quickly as possible if a patient is unresponsive and an opioid overdose is suspected, even when in doubt, because prolonged respiratory depression may result in damage to the central nervous system or death. OPVEE is not a substitute for emergency medical care [see Dosage and Administration (2.1) ] .
Lay the patient on their back and administer OPVEE into one nostril while providing support to the back of the neck to allow the head to tilt back [see Dosage and Administration (2.1) ]. Hold the OPVEE nasal spray device with your fingers on either side of the nozzle and thumb on the white plunger. Insert the nozzle into the nose.
Press the plunger firmly to give a dose in the nose. The dose has been delivered when the white plunger has been pushed all the way down until it stops. Remove the OPVEE nasal spray from the nose after the dose has been given.
Call 911 after giving the first dose of OPVEE nasal spray. Put the person on their side in the recovery position. Watch the person carefully.
Wait 2 to 5 minutes to see if the person wakes up. If the patient responds by waking up to the voice or touch or starts breathing normally, place them in the recovery position by turning them to their side as shown in the Instructions for Use and call for emergency medical assistance immediately after administration of OPVEE. Additional supportive and/or resuscitative measures may be helpful while awaiting emergency medical assistance [see Dosage and Administration (2.1) ] .
Monitor the patient and re-administer additional doses of OPVEE every 2 to 5 minutes, using a new OPVEE device. If the patient is not…