
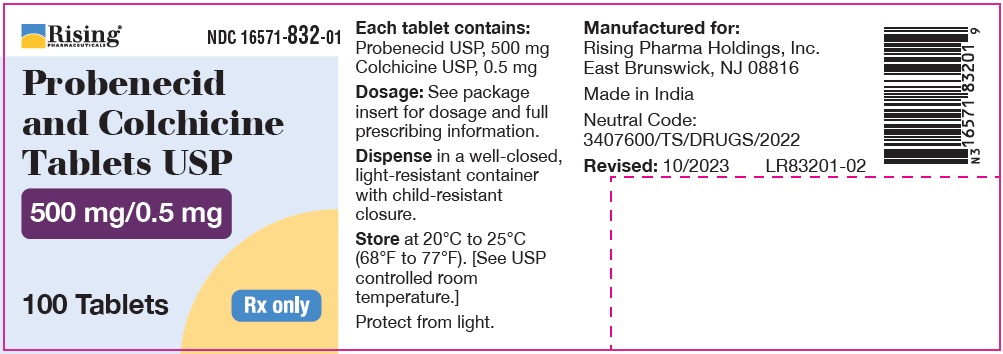
Probenecid and Colchicine 500 mg; .5 mg Tablet, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Alkaloid class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Colchicine is used to prevent gout attacks (sudden, severe pain in one or more joints caused by abnormally high levels of a substance called uric acid in the blood) in adults. Colchicine is also used to relieve the pain of gout attacks when they occur. Colchicine is also used to treat familial Mediterranean fever (FMF; an inborn condition that causes episodes of fever, pain, and swelling of the stomach area, lungs, and joints) in adults and children 4 years of age and older. Colchicine (Lodoco®) is used to reduce the risk of heart attack, stroke, cardiovascular death, and needing certain ty...
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 7T9FYH5QMK
A plant-derived powder that serves as a binder and filler in tablets and capsules. It helps hold ingredients together, adds bulk, and aids in smooth tablet disintegration when swallowed.
-
UNII RDH86HJV5Z
Povidone K90 is a synthetic polymer made from a chemical called vinyl pyrrolidone. It acts as a binder to hold pill ingredients together and as a dispersant to help the medicine break down and dissolve properly in your body.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.830 | $83.04 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $1.00 | $100.41 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $1.13 | $113.32 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Probenecid and Colchicine 500 mg/1; .5 mg 00591-5325-01 | Actavis | 100 tablets | $0.830 | — | Availability likely | — |
| Probenecid and Colchicine 500 mg/1; .5 mgthis 16571-0832-01 | Rising | 100 tablets | $0.830 | AB | Availability likely | — |
| Probenecid and Colchicine 500 mg/1; .5 mg 50742-0263-01 | Ingenus | 100 tablets | $0.830 | AB | Availability likely | — |
| Probenecid and Colchicine 500 mg/1; .5 mg 70518-4644-00 | REMEDYREPACK | 50 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 16571-0832-01 You're viewing this | 100 TABLET in 1 CONTAINER (16571-832-01) | 2023-10-24 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS & USAGE For the treatment of chronic gouty arthritis when complicated by frequent, recurrent acute attacks of gout.
⏱️ Dosage and Administration ▾
DOSAGE & ADMINISTRATION Therapy with probenecid and colchicine should not be started until an acute gouty attack has subsided. However, if an acute attack is precipitated during therapy, probenecid and colchicine may be continued without changing the dosage, and additional colchicine or other appropriate therapy should be given to control the acute attack. The recommended adult dosage is 1 tablet of probenecid and colchicine daily for one week, followed by 1 tablet twice a day thereafter.
Some degree of renal impairment may be present in patients with gout. A daily dosage of 2 tablets may be adequate. However, if necessary, the daily dosage may be increased by 1 tablet every four weeks within tolerance (and usually not above 4 tablets per day) if symptoms of gouty arthritis are not controlled or the 24 hour uric acid excretion is not above 700 mg.
As noted, probenecid may not be effective in chronic renal insufficiency particularly when the glomerular filtration rate is 30 mL/minute or less. Gastric intolerance may be indicative of overdosage, and may be corrected by decreasing the dosage. As uric acid tends to crystallize out of an acid urine, a liberal fluid intake is recommended, as well as sufficient sodium bicarbonate (3 to 7.5 g daily) or potassium citrate (7.5 g daily) to maintain an alkaline urine (see PRECAUTIONS ).
Alkalization of the urine is recommended until the serum urate level returns to normal limits and tophaceous deposits disappear, i.e., during the period when urinary excretion of uric acid is at a high level. Thereafter, alkalization of the urine and the usual restriction of purine-producing foods may be somewhat relaxed. Probenecid and colchicine (or probenecid) should be continued at the dosage that will maintain normal serum urate levels.
When acute attacks have been absent for six months or more and serum urate levels remain within normal limits, the daily dosage of probenecid and colchicine may be decreased by 1 tablet every six months. The maintenance dosage should not be reduced to the point where serum urate levels tend to rise.
⛔ Contraindications ▾
CONTRAINDICATIONS Hypersensitivity to this product or to probenecid or colchicine. Probenecid and colchicine tablets are contraindicated in children under 2 years of age. Not recommended in persons with known blood dyscrasias or uric acid kidney stones.
Therapy with probenecid and colchicine should not be started until an acute gouty attack has subsided. Pregnancy Probenecid crosses the placental barrier and appears in cord blood. Colchicine can arrest cell division in animals and plants.
In certain species of animals under certain conditions, colchicine has produced teratogenic effects. The possibility of such effects in humans also has been reported. Because of the colchicine component, probenecid and colchicine is contraindicated in pregnant patients.
The use of any drug in women of childbearing potential requires that the anticipated benefit be weighed against the possible hazards.
⚠️ Warnings ▾
WARNINGS Exacerbation of gout following therapy with probenecid and colchicine may occur; in such cases additional colchicine or other appropriate therapy is advisable. Probenecid increases plasma concentrations of methotrexate in both animals and humans. In animal studies, increased methotrexate toxicity has been reported.
If probenecid and colchicine is given with methotrexate, the dosage of methotrexate should be reduced and serum levels may need to be monitored. In patients on probenecid and colchicine the use of salicylates in either small or large doses is contraindicated because it antagonizes the uricosuric action of probenecid. The biphasic action of salicylates in the renal tubules accounts for the so-called “paradoxical effect” of uricosuric agents.
In patients on probenecid and colchicine who require a mild analgesic agent the use of acetaminophen rather than small doses of salicylates would be preferred. Rarely, severe allergic reactions and anaphylaxis have been reported with the use of probenecid and colchicine. Most of these have been reported to occur within several hours after readministration following prior usage of the drug.
The appearance of hypersensitivity reactions requires cessation of therapy with probenecid and colchicine. Colchicine has been reported to adversely affect spermatogenesis in animals. Reversible azoospermia has been reported in one patient.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The following adverse reactions have been observed and within each category are listed in order of decreasing severity. Probenecid Central Nervous System: headache, dizziness. Metabolic: precipitation of acute gouty arthritis.
Gastrointestinal: hepatic necrosis, vomiting, nausea, anorexia, sore gums. Genitourinary: nephrotic syndrome, uric acid stones with or without hematuria, renal colic, costovertebral pain, urinary frequency. Hypersensitivity: anaphylaxis, fever, urticaria, pruritus.
Hematologic: aplastic anemia, leukopenia, hemolytic anemia which in some patients could be related to genetic deficiency of glucose-6-phosphate dehydrogenase in red blood cells, anemia. Integumentary: dermatitis, alopecia, flushing. Colchicine Side effects due to colchicine appear to be a function of dosage.
The possibility of increased colchicine toxicity in the presence of hepatic dysfunction should be considered. The appearance of any of the following symptoms may require reduction of dosage or discontinuance of the drug. Central Nervous System: peripheral neuritis.
Musculoskeletal: muscular weakness. Gastrointestinal: nausea, vomiting, abdominal pain, or diarrhea may be particularly troublesome in the presence of peptic ulcer or spastic colon. Hypersensitivity: urticaria.
Hematologic: aplastic anemia, agranulocytosis. Integumentary: dermatitis, purpura, alopecia. At toxic doses, colchicine may cause severe diarrhea, generalized vascular damage, and renal damage with hematuria and oliguria.
To report SUSPECTED ADVERSE REACTIONS, contact Rising Pharma Holdings, Inc. at 1-844-874-7464 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
🔄 Drug Interactions ▾
DRUG INTERACTIONS When probenecid is used to elevate plasma concentrations of penicillin, or other beta-lactams, or when such drugs are given to patients taking probenecid therapeutically, high plasma concentrations of the other drug may increase the incidence of adverse reactions associated with that drug. In the case of penicillin, or other beta-lactams, psychic disturbances have been reported. The use of salicylates antagonizes the uricosuric action of probenecid (see WARNINGS ).
The uricosuric action of probenecid is also antagonized by pyrazinamide. Probenecid produces an insignificant increase in free sulfonamide plasma concentrations but a significant increase in total sulfonamide plasma levels. Since probenecid decreases the renal excretion of conjugated sulfonamides, plasma concentrations of the latter should be determined from time to time when a sulfonamide and probenecid and colchicine are coadministered for prolonged periods.
Probenecid may prolong or enhance the action of oral sulfonylureas and thereby increase the risk of hypoglycemia. It has been reported that patients receiving probenecid require significantly less thiopental for induction of anesthesia. In addition, ketamine and thiopental anesthesia were significantly prolonged in rats receiving probenecid.
The concomitant administration of probenecid increases the mean plasma elimination half-life of a number of drugs which can lead to increased plasma concentrations. These include agents such as indomethacin, acetaminophen, naproxen, ketoprofen, meclofenamate, lorazepam, and rifampin. Although the clinical significance of this observation has not been established, a lower dosage of the drug may be required to produce a therapeutic effect, and increases in dosage of the drug in question should be made cautiously and in small increments when probenecid is being co-administrated.
Although specific instances of toxicity due to this potential interaction have not been observed to date, physicians should be alert to this possibility. Probenecid given concomitantly with sulindac had only a slight effect on plasma sulfide levels, while plasma levels of sulindac and sulfone were increased. Sulindac was shown to produce a modest reduction in the uricosuric action of probenecid, which probably is not significant under most circumstances.
In animals and in humans, probenecid has been reported to increase plasma concentrations of methotrexate (see WARNINGS ). Falsely high readings for theophylline have been reported in an in vitro study, using the Schack and Waxler technique, when therapeutic concentrations of theophylline and probenecid were added to human plasma.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Probenecid is a uricosuric and renal tubular blocking agent. It inhibits the tubular reabsorption of urate, thus increasing the urinary excretion of uric acid and decreasing serum urate levels. Effective uricosuria reduces the miscible urate pool, retards urate deposition, and promotes resorption of urate deposits.
Probenecid inhibits the tubular secretion of penicillin and usually increases penicillin plasma levels by any route the antibiotic is given. A 2-fold to 4-fold elevation has been demonstrated for various penicillins. Probenecid also has been reported to inhibit the renal transport of many other compounds including amino hippuric acid (PAH), aminosalicylic acid (PAS), indomethacin, sodium iodomethamate and related iodinated organic acids, 17-ketosteroids, pantothenic acid, phenolsulfonphthalein (PSP), sulfonamides, and sulfonylureas.
See also Drug Interactions . Probenecid decreases both hepatic and renal excretion of sulfobromophthalein (BSP). The tubular reabsorption of phosphorus is inhibited in hypoparathyroid but not in euparathyroid individuals.
Probenecid does not influence plasma concentrations of salicylates, nor the excretion of streptomycin, chloramphenicol, chlortetracycline, oxytetracycline, or neomycin. The mode of action of colchicine in gout is unknown. It is not an analgesic, though it relieves pain in acute attacks of gout.
It is not a uricosuric agent and will not prevent progression of gout to chronic gouty arthritis. It does have a prophylactic, suppressive effect that helps to reduce the incidence of acute attacks and to relieve the residual pain and mild discomfort that patients with gout occasionally feel. In man and certain other animals, colchicine can produce a temporary leukopenia that is followed by leukocytosis.
Colchicine has other pharmacologic actions in animals: It alters neuromuscular function, intensifies gastrointestinal activity by neurogenic stimulation, increases sensitivity to central depressants, heightens response to sympathomimetic compounds, depresses the respiratory center, constricts blood vessels, causes hypertension by central vasomotor stimulation, and lowers body temperature.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Probenecid and Colchicine Tablets, USP 500 mg/0.5 mg are bisected, white to off-white capsule shaped, tablets debossed with “C81” on one side and break line on another side. They are supplied in bottles of 100 count: NDC 16571-832-01 Dispense in a well closed, light-resistant container with child-resistant closure. Store at 20º to 25ºC (68º to 77ºF); excursions permitted to 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature].
Protect from light. Manufactured for: Rising Pharma Holdings, Inc. East Brunswick, NJ 08816 Made in India.
Neutral Code: 4323066/TS/DRUGS/2025 Revised: 01/2026 PIR83201-05
📋 Description ▾
DESCRIPTION Probenecid and colchicine contains probenecid, which is a uricosuric agent, and colchicine, which has antigout activity, the mechanism of which is unknown. Probenecid is the generic name for p-(Dipropylsulfamoyl)benzoic acid. The structural formula is represented below: C 13 H 19 NO 4 S M.W.285.36 Probenecid is a white or practically white, fine, crystalline powder.
It is soluble in dilute alkali, in alcohol, in chloroform, and in acetone; it is practically insoluble in water and in dilute acids. Colchicine is an alkaloid obtained from various species of Colchicum. The chemical name for Colchicine is (S)-N-(5,6,7,9- tetrahydro-1,2,3,10-tetramethoxy-9-oxobenzo[α]heptalen-7-yl) acetamide.
The structural formula is represented below: C 22 H 25 NO 6 M.W.399.44 Colchicine consists of yellowish white to pale yellow to pale greenish-yellow powder which darken on exposure to light. Colchicine is freely soluble in chloroform. Each tablet for oral administration contains 500 mg of probenecid and 0.5 mg of colchicine.
Each tablet also contains the following inactive ingredients: colloidal silicon dioxide, corn starch, magnesium stearate, microcrystalline cellulose, povidone, sodium lauryl sulfate and sodium starch glycolate. FDA approved dissolution test specifications differ from the USP. probenecid-struc.jpg colchicine-struc.jpg