
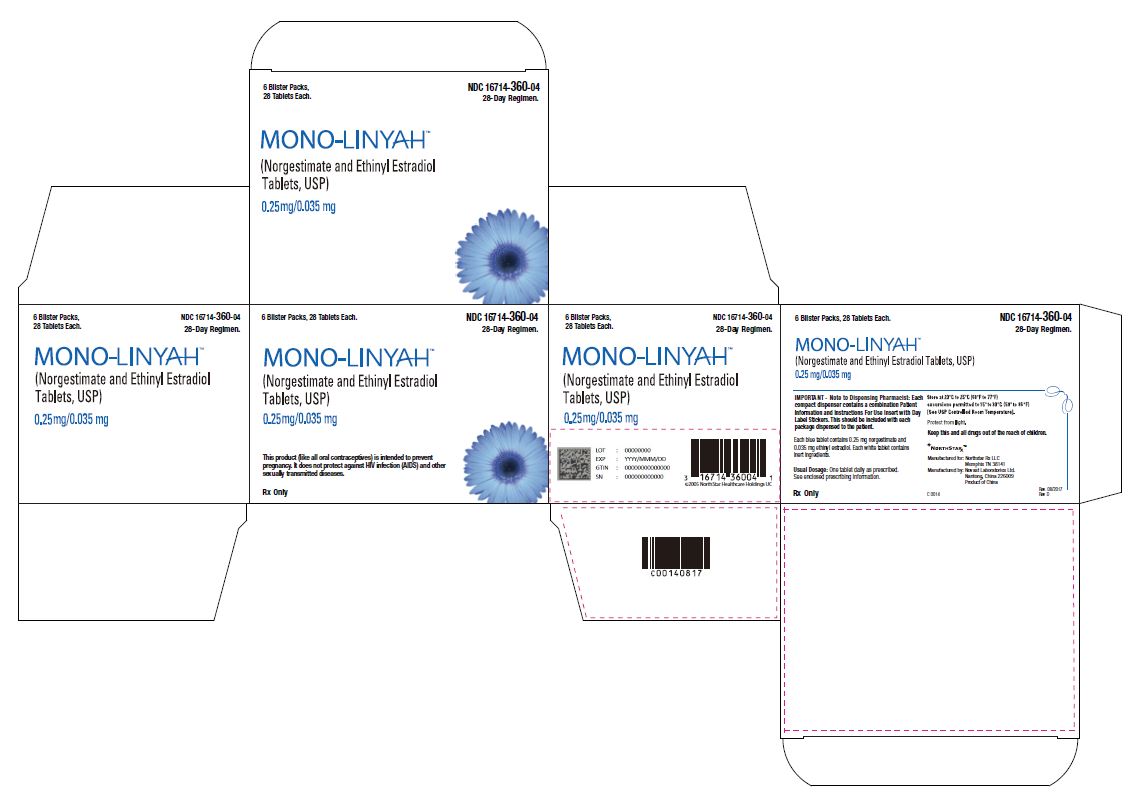
Mono-Linyah norgestimate and ethinyl estradiol Kit — NDC 16714-360-03 (Billing 16714-0360-03)
This is a package of Mono-Linyah norgestimate and ethinyl estradiol Kit from Northstar Rx LLC, marketed since May 2012 and currently FDA-listed.
Other active recalls for Norgestimate And Ethinyl Estradiol (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 013662
- GCN: 11300
- GPI-14 (Medi-Span): 25990002950310
- HICL (First Databank): 004845
- AHFS class code: 68:12.00.00
- RxCUI (RxNorm): 240128
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Progestin class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 2, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 16714-0360-01 16714-360-01 | 1 BLISTER PACK in 1 PACKET / 1 KIT in 1 BLISTER PACK | $0.1148 / ea | $0.11 | 2012-05-23 | — | Active |
| 16714-0360-02 16714-360-02 | 1 BLISTER PACK in 1 CARTON / 1 KIT in 1 BLISTER PACK | — | — | 2012-05-23 | — | Active |
| 16714-0360-03 You're viewing this | 3 BLISTER PACK in 1 CARTON / 1 KIT in 1 BLISTER PACK | — | — | 2012-05-23 | — | Active |
| 16714-0360-04 16714-360-04 Main listing | 6 BLISTER PACK in 1 CARTON / 1 KIT in 1 BLISTER PACK | $0.1148 / ea | $0.69 | 2012-05-23 | — | Active |
This pack shows little to no recent Medicaid volume — a different pack size carries most fills. See all packs ↓
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Mono-Linyah norgestimate and ethinyl estradiol Kit?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Tri-Lo-Sprintec 00093-2140-62 | Teva | 3 pouches | $0.108 | AB | Availability likely | — |
| Tri-Lo-Mili 65862-0778-28 | Aurobindo | 1 kit | $0.108 | AB | Availability likely | — |
| Tri-VyLibra Lo 50102-0231-13 | Afaxys | 1 kit | $0.108 | AB | Availability likely | — |
| Tri-Lo- Estarylla 70700-0120-85 | Xiromed, | 1 kit | $0.108 | AB | Availability likely | — |
| Tri-Lo-Marzia 68180-0837-73 | Lupin | 3 pouches | $0.108 | AB | Availability likely | — |
| Estarylla 70700-0119-85 | Xiromed, | 1 kit | $0.115 | AB | Availability likely | — |
| Sprintec 00555-9016-58 | Teva | 6 pouches | $0.115 | AB | Availability likely | — |
| VyLibra 50102-0235-11 | Afaxys | 1 kit | $0.115 | AB | Availability likely | — |
| Mili 65862-0776-28 | Aurobindo | 1 kit | $0.115 | AB | Availability likely | — |
| Norgestimate and Ethinyl Estradiol 68462-0309-29 | Glenmark | 1 kit | $0.115 | AB | Availability likely | — |
| Norgestimate and Ethinyl Estradiol 68180-0840-73 | Lupin | 3 pouches | $0.115 | AB | Availability likely | — |
| Tri-Mili 65862-0777-28 | Aurobindo | 1 kit | $0.126 | AB | Availability likely | — |
| Tri-Estarylla 70700-0121-85 | Xiromed, | 1 kit | $0.126 | AB | Availability likely | — |
| Norgestimate and Ethinyl Estradiol 68462-0565-29 | Glenmark | 1 kit | $0.126 | AB | Availability likely | — |
| Tri-Sprintec 00555-9018-58 | Teva | 6 pouches | $0.126 | AB | Availability likely | — |
| Norgestimate and ethinyl estradiol 68180-0838-73 | Lupin | 1 kit | $0.126 | AB | Availability likely | — |
| Tri-VyLibra 50102-0233-11 | Afaxys | 1 kit | $0.126 | AB | Availability likely | — |
| Tri-Linyah 16714-0363-01 | Northstar | 1 packet | $0.126 | AB | Availability likely | — |
| Nymyo 51862-0645-01 | Mayne | 1 packet | $0.135 | AB | FDA listed | — |
| Tri-Nymyo 51862-0646-01 | Mayne | 1 packet | $0.140 | AB | FDA listed | — |
| Tri Femynor 69238-1607-06 | Amneal | 1 kit | $0.140 | — | FDA listed | — |
| Femynor 69238-1551-06 | Amneal | 1 kit | $0.144 | — | FDA listed | — |
| Tri-Sprintec 63187-0458-28 | Proficient | 6 pouches | — | AB | FDA listed | — |
| Tri-Lo-Marzia 63187-0754-28 | Proficient | 1 pouch | — | AB | FDA listed | — |
| Sprintec 63187-0911-28 | Proficient | 1 pouch | — | AB | FDA listed | — |
| Norgestimate and Ethinyl Estradiol 71205-0191-28 | Proficient | 1 kit | — | AB | FDA listed | — |
| Norgestimate and Ethinyl Estradiol 42291-0553-84 | AvKARE | 1 kit | — | AB | FDA listed | — |
| Norgestimate and Ethinyl Estradiol 42291-0565-84 | AvKARE | 1 kit | — | AB | FDA listed | — |
| norgestimate and ethinyl estradiol 42291-0590-84 | AvKARE | 1 kit | — | AB | FDA listed | — |
| Norgestimate and Ethinyl Estradiol 50090-2603-00 | A-S | 1 kit | — | AB | FDA listed | — |
| Tri-Lo-Sprintec 71205-0287-28 | Proficient | 1 pouch | — | AB | FDA listed | — |
| Tri-Lo-Mili 71205-0746-28 | Proficient | 1 kit | — | AB | FDA listed | — |
| Norgestimate and ethinyl estradiol 79929-0008-07 | Naari | 1 kit | — | AB | FDA listed | — |
| Tri-Estarylla 63629-2350-01 | Bryant | 1 kit | — | AB | FDA listed | — |
| Norgestimate and ethinyl estradiol 79929-0009-07 | Naari | 1 kit | — | AB | FDA listed | — |
| Estarylla 82804-0158-28 | Proficient | 1 pouch | — | AB | FDA listed | — |
| Mono-Linyahthis 16714-0360-03 | Northstar | 1 kit | — | AB | FDA listed | — |
| Tri-Sprintec 68788-6325-02 | Preferred | 1 pouch | — | AB | FDA listed | — |
| norgestimate and ethinyl estradiol 72789-0435-79 | PD-Rx | 1 pouch | — | AB | FDA listed | — |
| Mono-Linyah 50090-4881-00 | A-S | 1 kit | — | AB | FDA listed | — |
| Norgestimate and Ethinyl Estradiol 72789-0434-79 | PD-Rx | 1 pouch | — | AB | FDA listed | — |
| Tri-Lo-Marzia 50090-2429-00 | A-S | 1 kit | — | AB | FDA listed | — |
| Estarylla 63629-2349-01 | Bryant | 1 kit | — | AB | Discontinued | — |
| Sprintec 68788-7429-02 | Preferred | 1 pouch | — | AB | FDA listed | — |
| Tri-Estarylla 50090-7861-00 | A-S | 1 kit | — | AB | FDA listed | — |
| Norgestimate and Ethinyl Estradiol 50090-2259-00 | A-S | 1 kit | — | AB | FDA listed | — |
| Tri-Lo- Estarylla 63629-2351-01 | Bryant | 1 kit | — | AB | FDA listed | — |
| Mono-Linyah 67296-2329-08 | Redpharm | 1 kit | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: CIGARETTE SMOKING and SERIOUS CARDIOVASCULAR EVENTS WARNING: CIGARETTE SMOKING and SERIOUS CARDIOVASCULAR EVENTS See full prescribing information for complete boxed warning. ● Mono-Linyah is contraindicated in women over 35 years old who smoke. (4) ● Cigarette smoking increases the risk of serious cardiovascular events from combination oral contraceptives (COC) use. (4) Cigarette smoking increases the risk of serious cardiovascular events from combination oral contraceptives (COC) use.
This risk increases with age, particularly in women over 35 years of age, and with the number of cigarettes smoked. For this reason, COCs are contraindicated in women who are over 35 years of age and smoke [see Contraindications (4) ] .
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Mono-Linyah is a combination of norgestimate, a progestin, and ethinyl estradiol, an estrogen, indicated for use by females of reproductive potential to prevent pregnancy. ( 1.1 )
1.1Oral Contraceptive Mono-Linyah tablets are indicated for use by females of reproductive potential to prevent pregnancy [see Clinical Studies ( 14 )] .
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Take one tablet daily by mouth at the same time every day (2.1) Take tablets in the order directed on the blister pack (2.1) Do not skip or delay tablet intake. (2.1)
2.1Recommended Dosage and Administration Take one tablet by mouth at the same time each day with or without food. Table 1 provides the recommended dosage and administration instructions for Mono-Linyah. Starting Mono-Linyah after Abortion or Miscarriage First-trimester After a first-trimester abortion or miscarriage, Mono-Linyah may be started immediately.
An additional method of contraception is not needed if Mono-Linyah is started immediately. If Mono-Linyah is not started within 5 days after termination of the pregnancy, the patient should use additional non-hormonal contraception (such as condoms and spermicide) for the first seven days of her first cycle pack of Mono-Linyah. Second-trimester Do not start until 4 weeks after a second-trimester abortion or miscarriage, due to the increased risk of thromboembolic disease.
Start Mono-Linyah, following the instructions in Table 1 for Day 1 or Sunday start, as desired. If using Sunday start, use additional non-hormonal contraception (such as condoms and spermicide) for the first seven days of the patient's first cycle pack of Mono-Linyah. [see Contraindications ( 4 ) and Warnings and Precautions ( 5.1 )]. Starting Mono-Linyah after Childbirth Do not start until 4 weeks after delivery, due to the increased risk of thromboembolic disease.
Start contraceptive therapy with Mono-Linyah following the instructions in Table 1 for women not currently using hormonal contraception. Mono-Linyah is not recommended for use in lactating women [see Use in Specific Populations ( 8.2 )] . If the woman has not yet had a period postpartum, consider the possibility of ovulation and conception occurring prior to use of Mono-Linyah. [see Contraindications ( 4 ), Warnings and Precautions ( 5.1 ), and Use in Specific Populations ( 8.1 and 8.2 )].
2.2Recommendations Regarding Missed Doses Contraceptive failure may occur when active tablets are missed. Table 2 describes instructions for Mono-Linyah dosing and use of additional non-hormonal contraception (such as condoms) when active tablets are missed.
2.3Dosage Recommendations if Vomiting or Diarrhea Occurs In case of severe vomiting or diarrhea, absorption may not be complete and additional contraceptive measures should be taken. If vomiting or diarrhea occurs within 3 to 4 hours after taking an active tablet, handle this as a missed tablet. table1 table2
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Mono-Linyah consists of 28 round, biconvex, coated tablets in the following order (3) : 21 blue tablets each containing 0.250 mg norgestimate and 0.035 mg ethinyl estradiol 7 white tablets (inert) Mono-Linyah Tablets are available in blister cards. Each blister card contains 28 tablets in the following order: 21 blue, round, biconvex, coated tablet imprinted "C3" on one side of the tablet and contains 0.250 mg norgestimate and 0.035 mg ethinyl estradiol 7 white, round, biconvex tablets (non-hormonal placebo) imprinted "P" on one side and " N " on the other side contains inert ingredients
⛔ Contraindications ▾
4 CONTRAINDICATIONS A high risk of arterial or venous thrombotic diseases (4) Liver tumors or liver disease (4) Undiagnosed abnormal uterine bleeding (4) Breast cancer (4) Co-administration with Hepatitis C drug combinations containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir ( 4 ) Mono-Linyah is contraindicated in females who are known to have or develop the following conditions: A high risk of arterial or venous thrombotic diseases. Examples include women who are known to: Smoke, if over age 35 [see Boxed Warning and Warnings and Precautions ( 5.1 )] Have deep vein thrombosis or pulmonary embolism, now or in the past [see Warnings and Precautions (5.1) ] Have inherited or acquired hypercoagulopathies [see Warnings and Precautions (5.1) ] Have cerebrovascular disease [see Warnings and Precautions (5.1) ] Have coronary artery disease [see Warnings and Precautions (5.1) ] Have thrombogenic valvular or thrombogenic rhythm diseases of the heart (for example, subacute bacterial endocarditis with valvular disease, or atrial fibrillation) [see Warnings and Precautions (5.1) ] Have uncontrolled hypertension [see Warnings and Precautions (5.4) ] Have diabetes mellitus with vascular disease [see Warnings and Precautions (5.6) ] Have headaches with focal neurological symptoms or migraine headaches with aura [see Warnings and Precautions (5.7) ] Women over age 35 with any migraine headaches [see Warnings and Precautions ( 5.7 )] Liver tumors, benign or malignant, or liver disease [see Warnings and Precautions (5.2) ] Undiagnosed abnormal uterine bleeding [see Warnings and Precautions (5.8) ] Current diagnosis of, or history of, breast cancer, which may be hormone-sensitive [ see Warnings and Precautions (5.10) ] Use of Hepatitis C drug combinations containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir, due to the potential for ALT elevations [see Warnings and Precautions (5.3) ]
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Thromboembolic Disorders and Other Vascular Problems: Stop Mono-Linyah if a thrombotic event occurs. Stop at least 4 weeks before and through 2 weeks after major surgery. Start no earlier than 4 weeks after delivery, in women who are not breastfeeding.
( 5.1 ) Liver disease: Discontinue Mono-Linyah if jaundice occurs. ( 5.2 ) High blood pressure: If used in women with well-controlled hypertension, monitor blood pressure and stop Mono-Linyah if blood pressure rises significantly. ( 5.4 ) Carbohydrate and lipid metabolic effects: Monitor prediabetic and diabetic women taking Mono-Linyah.
Consider an alternate contraceptive method for women with uncontrolled dyslipidemia. ( 5.6 ) Headache: Evaluate significant change in headaches and discontinue Mono-Linyah if indicated. ( 5.7 ) Bleeding Irregularities and Amenorrhea: Evaluate irregular bleeding or amenorrhea.
( 5.8 )
5.1Thromboembolic Disorders and Other Vascular Problems Stop Mono-Linyah if an arterial thrombotic event or venous thromboembolic (VTE) event occurs. Stop Mono-Linyah if there is unexplained loss of vision, proptosis, diplopia, papilledema, or retinal vascular lesions. Evaluate for retinal vein thrombosis immediately [see Adverse Reactions ( 6.2 )] .
If feasible, stop Mono-Linyah at least 4 weeks before and through 2 weeks after major surgery or other surgeries known to have an elevated risk of VTE as well as during and following prolonged immobilization. Start Mono-Linyah no earlier than 4 weeks after delivery, in women who are not breastfeeding. The risk of postpartum VTE decreases after the third postpartum week, whereas the risk of ovulation increases after the third postpartum week.
The use of COCs increases the risk of VTE. However, pregnancy increases the risk of VTE as much or more than the use of COCs. The risk of VTE in women using COCs is 3 to 9 cases per 10,000 woman-years.
The risk of VTE is highest during the first year of use of COCs and when restarting hormonal contraception after a break of 4 weeks or longer. The risk of thromboembolic disease due to COCs gradually disappears after use is discontinued. Use of COCs also increases the risk of arterial thromboses such as strokes and myocardial infarctions, especially in women with other risk factors for these events.
COCs have been shown to increase both the relative and attributable risks of cerebrovascular events (thrombotic and hemorrhagic strokes). This risk increases with age, particularly in women over 35 years of age who smoke. Use COCs with caution in women with cardiovascular disease risk factors.
5.2Liver Disease Impaired Liver Function Mono-Linyah is contraindicated in women with liver disease, such as acute viral hepatitis or severe (decompensated) cirrhosis of liver [ see Contraindications (4) ]. Acute or chronic disturbances of liver function may necessitate the discontinuation of COC use until markers of liver function return to normal and COC causation has been excluded. Discontinue Mono-Linyah if jaundice develops.
Liver Tumors Mono-Linyah is contraindicated in women with benign and malignant liver tumors [see Contraindications (4) ]. Hepatic adenomas are associated with COC use. An estimate of the attributable risk is 3.3 cases/100,000 COC users.
Rupture of hepatic adenomas may cause death through intra-abdominal hemorrhage. Studies have shown an increased risk of developing hepatocellular carcinoma in long-term (>8 years) COC users. However, the risk of liver cancers in COC users is less than one case per million users.
5.3Risk of Liver Enzyme Elevations with Concomitant Hepatitis C Treatment During clinical trials with the Hepatitis C combination drug regimen that contains ombitasvir/paritaprevir/ritonavir, with or without dasabuvir, ALT elevations greater than 5 times the upper limit of normal (ULN), including some cases greater than 20 times the ULN, were significantly more frequent in women using ethinyl estradiol-containing medications, such as COCs…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most common adverse reactions reported during clinical trials (≥2%) were: headache/migraine, abdominal/gastrointestinal pain, vaginal infection, genital discharge, breast issues (including breast pain, discharge, and enlargement), mood disorders (including depression and mood altered), flatulence, nervousness, rash. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Northstar Rx LLC at 1-800-206-7821 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch . The following serious adverse reactions with the use of COCs are discussed elsewhere in labeling: Serious cardiovascular events and stroke [ see Boxed Warning and Warnings and Precautions (5.1) ] Vascular events [ see Warnings and Precautions (5.1) ] Liver disease [ see Warnings and Precautions (5.2) ]
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. The safety of norgestimate and ethinyl estradiol 0.25mg/0.035mg tablets was evaluated in 1,647 healthy women of child-bearing potential who participated in 3 clinical trials and received at least 1 dose of norgestimate and ethinyl estradiol 0.25mg/0.035mg tablets for contraception.
Two trials were randomized active-controlled trials and 1 was an uncontrolled open-label trial. In all 3 trials, subjects were followed for up to 24 cycles. Common Adverse Reactions (≥2% of subjects) : The most common adverse reactions reported by at least 2% of the 1,647 women were the following in order of decreasing incidence: headache/migraine (32.9%), abdominal/gastrointestinal pain (7.8%), vaginal infection (8.4%), genital discharge (6.8%), breast issues (including breast pain, discharge,and enlargement) (6.3%), mood disorders (including depression and mood altered) (5.0%), flatulence (3.2%), nervousness (2.9%), and rash (2.6%).
Adverse Reactions Leading to Study Discontinuation : Over the three trials, between 11 to 21% of subjects discontinued the trial due to an adverse reaction. The most common adverse reactions (≥1%) leading to discontinuation were: metrorrhagia (6.9%), nausea/vomiting (5.0%), headache (4.1%), mood disorders (including depression and mood altered) (2.4%), premenstrual syndrome (1.7%), hypertension (1.4%), breast pain (1.4%), nervousness (1.3%), amenorrhea (1.1%), dysmenorrhea (1.1%), weight increased (1.1%), and flatulence (1.1%).
Serious Adverse Reactions : breast cancer (1 subject), mood disorders including depression, irritability, and mood swings (1 subject), myocardial infarction (1 subject), and venous thromboembolic events including pulmonary embolism (1 subject) and deep vein thrombosis (DVT) (1 subject).
6.2Postmarketing Experience Five studies that compared breast cancer risk between ever-users (current or past use) of COCs and never-users of COCs reported no association between ever use of COCs and breast cancer risk, with effect estimates ranging from 0.90 - 1.12 (Figure 1). Three studies compared breast cancer risk between current or recent COC users (<6 months since last use) and never users of COCs (Figure 1). One of these studies reported no association between breast cancer risk and COC use.
The other two studies found an increased relative risk of 1.19 - 1.33 with current or recent use. Both of these studies found an increased risk of breast cancer with current use of longer duration, with relative risks ranging from 1.03 with less than one year of COC use to approximately 1.4 with more than 8-10 years of COC use. Figure 1: Relevant Studies of Risk of Breast Cancer with Combined Oral Contraceptives RR = relative risk; OR = odds ratio; HR = hazard ratio. “ ever COC ” are females with current or past COC use; “ never COC use ” are females that never used COCs.
The following additional adverse drug reactions have been reported from world…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Drugs or herbal products that induce certain enzymes including CYP3A4, may decrease the effectiveness of COCs or increase breakthrough bleeding. Counsel patients to use a back-up or alternative method of contraception when enzyme inducers are used with COCs. ( 7.1 ) Consult the labeling of concurrently used drugs to obtain further information about interactions with hormonal contraceptives or the potential for enzyme alterations.
No drug-drug interaction studies were conducted with Mono-Linyah.
7.1Effects of Other Drugs on Combined Oral Contraceptives Substances decreasing the plasma concentrations of COCs Drugs or herbal products that induce certain enzymes, including cytochrome P450 3A4 (CYP3A4), may decrease the plasma concentrations of COCs and potentially diminish the effectiveness of COCs or increase breakthrough bleeding. Some drugs or herbal products that may decrease the effectiveness of hormonal contraceptives include phenytoin, barbiturates, carbamazepine, bosentan, felbamate, griseofulvin, oxcarbazepine, rifampicin, topiramate, rifabutin, rufinamide, aprepitant, and products containing St.
John's wort. Interactions between hormonal contraceptives and other drugs may lead to breakthrough bleeding and/or contraceptive failure. Counsel women to use an alternative method of contraception or a back-up method when enzyme inducers are used with COCs, and to continue back-up contraception for 28 days after discontinuing the enzyme inducer to ensure contraceptive reliability.
Colesevelam: Colesevelam, a bile acid sequestrant, given together with a COC, has been shown to significantly decrease the AUC of EE. The drug interaction between the contraceptive and colesevelam was decreased when the two drug products were given 4 hours apart. Substances increasing the plasma concentrations of COCs Co-administration of atorvastatin or rosuvastatin and certain COCs containing ethinyl estradiol (EE) increase AUC values for EE by approximately 20-25%.
Ascorbic acid and acetaminophen may increase plasma EE concentrations, possibly by inhibition of conjugation. CYP3A4 inhibitors such as itraconazole, voriconazole, fluconazole, grapefruit juice, or ketoconazole may increase plasma hormone concentrations. Human immunodeficiency virus (HIV)/Hepatitis C virus (HCV) protease inhibitors, non-nucleoside reverse transcriptase inhibitors , and HIV/AIDS medications containing strong inhibitors or inducers of CYP3A Significant changes (increase or decrease) in the plasma concentrations of estrogen and/or progestin have been noted in some cases of co-administration with HIV protease inhibitors (decrease [e.g., nelfinavir, ritonavir, darunavir/ritonavir, (fos)amprenavir/ritonavir, lopinavir/ritonavir, and tipranavir/ritonavir] or increase [e.g., indinavir and atazanavir/ritonavir])/HCV protease inhibitors (decrease [e.g., boceprevir and telaprevir]) or with non-nucleoside reverse transcriptase inhibitors (decrease [e.g., nevirapine] or increase [e.g., etravirine]) or with HIV/AIDS medications containing strong inhibitors (e.g., cobicistat and ritonavir) or inducers of CYP3A.
7.2Effects of Combined Oral Contraceptives on Other Drugs COCs containing EE may inhibit the metabolism of other compounds (e.g., cyclosporine, prednisolone, theophylline, tizanidine, and voriconazole) and increase their plasma concentrations. COCs have been shown to decrease plasma concentrations of acetaminophen, clofibric acid, morphine, salicylic acid, temazepam and lamotrigine. Significant decrease in plasma concentration of lamotrigine has been shown, likely due to induction of lamotrigine glucuronidation.
This may reduce seizure control; therefore, dosage adjustments of lamotrigine may be necessary. Women on thyroid hormone replacement therapy may need increased doses of thyroid hormone because the serum concentration of thyroid-binding globulin increases with use of COCs.
7.3 Interactions with Laboratory Tests The use of contraceptive steroids may in…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactating women: Not recommended; can decrease milk production. (8.2)
8.1Pregnancy Risk Summary There is no use for contraception in pregnancy, therefore, Mono-Linyah should be discontinued during pregnancy. Epidemiologic studies and meta-analyses have not found an increased risk of genital or non-genital birth defects (including cardiac anomalies and limb reduction defects) following exposure to CHCs before conception or during early pregnancy. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4 percent and 15 to 20 percent, respectively.
8.2Lactation Risk Summary Contraceptive hormones and/ or metabolites are present in human milk. CHCs can reduce milk production in breastfeeding females. This reduction can occur at any time but is less likely to occur once breastfeeding is well-established.
When possible, advise the nursing female to use other forms of contraception until she discontinues breast-feeding. The developmental and health benfits of breast-feeding should be considered along with the mother's clinical need for Mono-Linyah and any potential adverse effects on the breast-fed child from Mono-Linyah or from the underlying maternal condition.
8.4Pediatric Use Safety and efficacy of Mono-Linyah Tablets have been established in women of reproductive age. Efficacy is expected to be the same for post-pubertal adolescents under the age of 18 and for users 18 years and older. Use of this product before menarche is not indicated.
8.5Geriatric Use Mono-Linyah has not been studied in postmenopausal women and are not indicated in this population.
8.6Hepatic Impairment The pharmacokinetics of Mono-Linyah has not been studied in subjects with hepatic impairment. However, steroid hormones may be poorly metabolized in patients with hepatic impairment. Acute or chronic disturbances of liver function may necessitate the discontinuation of COC use until markers of liver function return to normal and COC causation has been excluded. [see Contraindications ( 4 ) and Warnings and Precautions ( 5.2 ).]
8.7Renal Impairment The pharmacokinetics of Mono-Linyah has not been studied in women with renal impairment.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and efficacy of Mono-Linyah Tablets have been established in women of reproductive age. Efficacy is expected to be the same for post-pubertal adolescents under the age of 18 and for users 18 years and older. Use of this product before menarche is not indicated.
🧓 Geriatric Use ▾
8.5Geriatric Use Mono-Linyah has not been studied in postmenopausal women and are not indicated in this population.
🆘 Overdosage ▾
10 OVERDOSAGE There have been no reports of serious ill effects from overdosage of oral contraceptives, including ingestion by children. Overdosage may cause withdrawal bleeding in females and nausea.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action COCs lower the risk of becoming pregnant primarily by suppressing ovulation.
12.2Pharmacodynamics No specific pharmacodynamic studies were conducted with Mono-Linyah.
12.3Pharmacokinetics Absorption Norgestimate (NGM) and EE are rapidly absorbed following oral administration. NGM is rapidly and completely metabolized by first pass (intestinal and/or hepatic) mechanisms to norelgestromin (NGMN) and norgestrel (NG), which are the major active metabolites of norgestimate. Peak serum concentrations of NGMN and EE are generally reached by 2 hours after administration of Mono-Linyah.
Accumulation following multiple dosing of the 250 mcg NGM / 35 mcg EE dose is approximately 2-fold for NGMN and EE compared with single dose administration. The pharmacokinetics of NGMN is dose-proportional following NGM doses of 180 mcg to 250 mcg. Steady-state concentration of EE is achieved by Day 7 of each dosing cycle.
Steady-state concentrations of NGMN and NG are achieved by Day 21. Non-linear accumulation (approximately 8 fold) of NG is observed as a result of high-affinity binding to SHBG, which limits its biological activity (Table 3). Food Effect The effect of food on the pharmacokinetics of Mono-Linyah has not been studied.
Distribution NGMN and NG are highly bound (>97%) to serum proteins. NGMN is bound to albumin and not to SHBG, while NG is bound primarily to SHBG. EE is extensively bound (>97%) to serum albumin and induces an increase in the serum concentrations of SHBG.
Metabolism NGM is extensively metabolized by first-pass mechanisms in the gastrointestinal tract and/or liver. NGM's primary active metabolite is NGMN. Subsequent hepatic metabolism of NGMN occurs and metabolites include NG, which is also active, and various hydroxylated and conjugated metabolites.
Although NGMN and its metabolites inhibit a variety of P450 enzymes in human liver microsomes, under the recommended dosing regimen, the in vivo concentrations of NGMN and its metabolites, even at the peak serum levels, are relatively low compared to the inhibitory constant (Ki). EE is also metabolized to various hydroxylated products and their glucuronide and sulfate conjugates. Excretion The metabolites of NGMN and EE are eliminated by renal and fecal pathways.
Following administration of 14 C-norgestimate, 47% (45-49%) and 37% (16-49%) of the administered radioactivity was eliminated in the urine and feces, respectively. Unchanged NGM was not detected in the urine. In addition to 17-deacetyl norgestimate, a number of metabolites of NGM have been identified in human urine following administration of radiolabeled NGM.
These include 18, 19-Dinor-17-pregn-4-en-20-yn-3-one,17-hydroxy-13-ethyl,(17α)-(-);18,19-Dinor-5β-17-pregnan-20-yn,3α,17β-dihydroxy-13-ethyl,(17α), various hydroxylated metabolites and conjugates of these metabolites. table3
🧬 Mechanism of Action ▾
12.1Mechanism of Action COCs lower the risk of becoming pregnant primarily by suppressing ovulation.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Mono-Linyah Tablets are available in a compact blister card (NDC 16714-360-01) containing 28 tablets in the following order: 21 blue, biconvex, round, coated tablets with "C3" debossed on one side containing 0.250 mg norgestimate and 0.035 mg ethinyl estradiol, and 7 white, biconvex, round, coated tablets with "P" debossed on one side and the " N " debossed on the other side containing inert ingredients. Mono-Linyah Tablets are available in the following configurations: Carton of 1 blister card NDC 16714-360-02 Carton of 3 blister cards NDC 16714-360-03 Carton of 6 blister cards NDC 16714-360-04
16.2Storage Conditions Store at 20° to 25℃ (68° to 77ºF); excursions permitted to 15° to 30°C (59° to 86°F) . Protect from light. Keep out of the reach of children.
16.1How Supplied Mono-Linyah Tablets are available in a compact blister card (NDC 16714-360-01) containing 28 tablets in the following order: 21 blue, biconvex, round, coated tablets with "C3" debossed on one side containing 0.250 mg norgestimate and 0.035 mg ethinyl estradiol, and 7 white, biconvex, round, coated tablets with "P" debossed on one side and the " N " debossed on the other side containing inert ingredients. Mono-Linyah Tablets are available in the following configurations: Carton of 1 blister card NDC 16714-360-02 Carton of 3 blister cards NDC 16714-360-03 Carton of 6 blister cards NDC 16714-360-04
📋 Description ▾
11 DESCRIPTION Mono-Linyah is a combination oral contraceptive containing the progestational compound norgestimate and the estrogenic compound ethinyl estradiol. Norgestimate is designated as (18,19-Dinor-17-pregn-4-en-20-yn-3-one,17-(acetyloxy)-13-ethyl-, oxime,(17α)(+)-) and ethinyl estradiol is designated as (19-nor-17α-pregna,1,3,5(10)-trien-20-yne-3,17-diol). Each active blue tablet contains 0.250 mg of norgestimate and 0.035 mg of ethinyl estradiol.
Inactive ingredients include: FD&C Blue No. 2 Aluminium Lake, FD&C Blue No. 1 Aluminum lake, FD&C Red No.
40 Aluminum Lake, FD&C Yellow No. 10 Aluminum Lake, titanium dioxide, polyvinyl alcohol, talc, macrogol/PEG 3350 NF, lecithin, lactose monohydrate, magnesium stearate and pregelatinized corn starch. Each white placebo tablet containing only inert ingredients, as follows: titanium dioxide, polydextrose, hypromellose, triacetin, macrogol/polyethylene glycol, lactose monohydrate, magnesium stearate and pregelatinized corn starch.
3
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See FDA-approved Patient Labeling (Patient Information and Instructions for Use) . Counsel patients about the following information: Cigarette smoking increases the risk of serious cardiovascular events from COC use, and that women who are over 35 years old and smoke should not use COCs [see Boxed Warning ] . Increased risk of VTE compared to non-users of COCs is greatest after initially starting a COC or restarting (following a 4-week or greater pill-free interval) the same or a different COC [see Warnings and Precautions ( 5.1 )] .
Mono-Linyah does not protect against HIV infection (AIDS) and other sexually transmitted infections. Mono-Linyah is not to be used during pregnancy; if pregnancy occurs during use of Mono-Linyah instruct the patient to stop further use [ see Use in Specific Populations (8.1)] . Take one tablet daily by mouth at the same time every day.
Instruct patients what to do in the event tablets are missed [see Dosage and Administration ( 2.1,2.2 )] . Use a back-up or alternative method of contraception when enzyme inducers are used with Mono-Linyah [see Drug Interactions ( 7.1 )] . COCs may reduce breast milk production; this is less likely to occur if breastfeeding is well established [see Use in Specific Populations ( 8.2 )] .
Women who start COCs postpartum, and who have not yet had a period, should use an additional method of contraception until they have taken an active tablet for 7 consecutive days [see Dosage and Administration ( 2.1 )] . Amenorrhea may occur. Consider pregnancy in the event of amenorrhea at the time of the first missed period.
Rule out pregnancy in the event of amenorrhea in two or more consecutive cycles [see Warnings and Precautions ( 5.8 )]. Revised: Jan 2025 I0020 Rev. F 5
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |