
Cisplatin 1 mg/mL Injection, 100 mL — NDC 16729-288-38 (Billing 16729-0288-38)
This is a package of 100 mL of Cisplatin 1 mg/mL Injection from Accord Healthcare Inc., marketed since Dec 2016 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
Past resolved recalls for this product (1)
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 008785
- GCN: 38920
- GPI-14 (Medi-Span): 21100020002020
- HICL (First Databank): 003902
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 309311
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Platinum-based Drug class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Cisplatin is used combination with other medications to treat cancer of the testicles that has not improved or that has worsened after treatment with other medications or radiation therapy. Cisplatin is used alone or in combination with other medications to treat cancer of the ovaries (cancer that begins in the female reproductive organs where eggs are formed) that has not improved or that has worsened after treatment with other medications or radiation therapy. Cisplatin is also used alone or in combination with other medications to treat bladder cancer that can not be treated with surgery or...
Read the full MedlinePlus article ↗- The fluids are there to protect your kidneys — one of cisplatin's most serious side effects is kidney damage, and staying well-hydrated helps flush the drug through your kidneys mo...
- Why do I need so much IV fluid before and after my cisplatin treatment?
- Cisplatin is one of the most strongly nausea-causing chemotherapy drugs there is — without prevention, almost everyone experiences severe nausea and vomiting. The good news is that...
- Will I definitely get sick to my stomach from cisplatin?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Cisplatin — tap one for details:
Cisplatin may be associated with lower levels of 6 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $0.4452 | $0.45 / 1 vial |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J9060 | $2.130 / J9060 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 16729-0288-11 16729-288-11 | 50 mL in 1 VIAL | 2016-12-13 | — | Active |
| 16729-0288-38 You're viewing this Main listing | 100 mL in 1 VIAL | 2016-12-13 | — | Active |
You're viewing the largest of 2 pack sizes for this product.
In Medicaid, this is the most-dispensed pack of this product — about 86% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 16729-0288-11?
What NDC number is used to bill for this package of Cisplatin 1 mg/mL Injection?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| CISplatin 1 mg/mL 00143-9504-01 | Hikma | 1 vial | — | AP | FDA listed | — |
| CISplatin 1 mg/mL 00143-9505-01 | Hikma | 1 vial | — | AP | FDA listed | — |
| Cisplatin 50 mg/50mL 00703-5747-11 | Teva | 1 vial | — | AP | FDA listed | — |
| Cisplatin 100 mg/100mL 00703-5748-11 | Teva | 1 vial | — | AP | FDA listed | — |
| Cisplatin 1 mg/mLthis 16729-0288-38 | Accord | 100 ml | — | AP | FDA listed | — |
| Cisplatin 1 mg/mL 25021-0253-50 | Sagent | 1 vial | — | AP | FDA listed | — |
| CISplatin 1 mg/mL 44567-0509-01 | WG | 1 vial | — | AP | FDA listed | — |
| CISplatin 1 mg/mL 44567-0510-01 | WG | 1 vial | — | AP | FDA listed | — |
| CISplatin 1 mg/mL 44567-0511-01 | WG | 1 vial | — | AP | FDA listed | — |
| CISplatin 1 mg/mL 60505-6279-00 | Apotex | 1 vial | — | AP | FDA listed | — |
| Cisplatin 1 mg/mL 63323-0103-51 | Fresenius | 1 vial | — | AP | FDA listed | — |
| Cisplatin 1 mg/mL 68001-0283-27 | BluePoint | 1 vial | — | AP | FDA listed | — |
| Cisplatin 1 mg/mL 68001-0608-24 | BluePoint | 1 vial | — | AP | FDA listed | — |
| Cisplatin 1 mg/mL 68001-0609-33 | BluePoint | 1 vial | — | AP | FDA listed | — |
| Cisplatin 1 mg/mL 68083-0162-01 | Gland | 1 vial | — | AP | FDA listed | — |
| Cisplatin 1 mg/mL 68083-0163-01 | Gland | 1 vial | — | AP | FDA listed | — |
| Cisplatin 1 mg/mL 72266-0252-01 | FOSUN | 1 vial | — | AP | FDA listed | — |
| Cisplatin 1 mg/mL 72266-0253-01 | FOSUN | 1 vial | — | AP | FDA listed | — |
| Cisplatin 1 mg/mL 44567-0530-01 | WG | 1 vial | — | AP | FDA listed | — |
| Cisplatin 1 mg/mL 65219-0359-50 | Fresenius | 1 vial | — | — | Discontinued | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: NEPHROTOXICITY, PERIPHERAL NEUROPATHY, NAUSEA AND VOMITING and MYELOSUPPRESSION. Nephrotoxicity: cisplatin injection can cause severe renal toxicity, including acute renal failure. Severe renal toxicities are dose-related and cumulative.
Ensure adequate hydration and monitor renal function and electrolytes. Consider dose reductions or alternative treatments in patients with renal impairment [see Dosage and Administration ( 2.1 ) and Warnings and Precautions ( 5.1 )]. Peripheral Neuropathy: cisplatin injection can cause dose-related peripheral neuropathy that becomes more severe with repeated courses of the drug [see Warnings and Precautions ( 5.2 )].
Nausea and Vomiting: cisplatin injection can cause severe nausea and vomiting. Use highly effective antiemetic premedication [see Dosage and Administration ( 2.1 ) and Warnings and Precautions ( 5.3 )]. Myelosuppression: cisplatin injection can cause severe myelosuppression with fatalities due to infections.
Monitor blood counts accordingly. Interruption of therapy may be required [see Warnings and Precautions ( 5.4 )]. WARNING: NEPHROTOXICITY, PERIPHERAL NEUROPATHY, NAUSEA AND VOMITING, and MYELOSUPPRESSION See full prescribing information for complete boxed warning.
Nephrotoxicity: cisplatin injection can cause severe renal toxicity, including acute renal failure. Ensure adequate hydration. Consider dose reductions or alternative treatments in patients with renal impairment.
( 2.1 , 5.1 ) Peripheral Neuropathy: cisplatin injection can cause dose-related peripheral neuropathy. ( 5.2 ) Nausea and Vomiting: cisplatin injection can cause severe nausea and vomiting. Premedicate with antiemetics.
( 2.1 , 5.3 ) Myelosuppression: cisplatin injection can cause severe myelosuppression with fatalities due to infections. Monitor blood counts and interrupt therapy accordingly. ( 5.4 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Cisplatin injection is a platinum-based drug indicated for the treatment of: • Advanced testicular cancer ( 1.1 ) • Advanced ovarian cancer ( 1.2 ) • Advanced bladder cancer ( 1.3 )
1.1Advanced Testicular Cancer Cisplatin injection is indicated for the treatment of advanced testicular cancer.
1.2Advanced Ovarian Cancer Cisplatin injection is indicated for the treatment of advanced ovarian cancer.
1.3Advanced Bladder Cancer Cisplatin injection is indicated for the treatment of advanced bladder cancer.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Administer pre-treatment hydration and pre- and post-treatment antiemetics. ( 2.1 ) • Cisplatin injection has been administered intravenously at: o Advanced testicular cancer: 20 mg/m2 daily for 5 days per cycle ( 2.2 ) o Advanced ovarian cancer: 75 mg/m2 to 100 mg/m2 per cycle once every 3 to 4 weeks ( 2.3 ) o Advanced bladder cancer: 50 mg/m2 to 70 mg/m2 intravenously per cycle once every 3 to 4 weeks ( 2.4 ) Refer to current treatment guidelines for specific dosing information. • Administer by slow intravenous infusion.
Avoid contact of cisplatin injection with aluminum parts. ( 2.6 )
2.1Hydration and Anti-Emetic Treatment Patients treated with cisplatin injection must receive appropriate pre-treatment hydration. Maintain adequate hydration and urinary output for 24 hours after cisplatin injection administration [see Warnings and Precautions ( 5.1 )] . Administer pre-treatment and post-treatment antiemetics as appropriate [see Warnings and Precautions ( 5.7 )] .
2.2Advanced Testicular Cancer Cisplatin injection has been administered at 20 mg/m 2 intravenously daily for 5 days per cycle. Other doses and combination regimens have been used.
2.3Advanced Ovarian Cancer Cisplatin injection has been administered at 75 mg/m 2 to 100 mg/m 2 intravenously per cycle once every 3 to 4 weeks on Day 1. Other doses and combination regimens have been used.
2.4Advanced Bladder Cancer Cisplatin injection has been administered at 50 mg/m 2 to 70 mg/m 2 intravenously per cycle once every 3 to 4 weeks. For heavily pretreated patients, an initial dose of 50 mg/m 2 per cycle repeated every 4 weeks is recommended. Other doses and combination in regimens have been used.
2.5Dose Modifications Consider alternative treatments or dose reductions for patients with impaired creatinine clearance, myelosuppression, or neuropathy. Consider permanent discontinuation for Grade 3-4 neuropathy. [See Warnings and Precautions ( 5.1 )]
2.6Preparation, Handling, and Administration Do not use needles or intravenous sets containing aluminum parts that can come in contact with cisplatin injection during preparation or administration. Aluminum reacts with cisplatin injection, causing precipitate formation and a loss of potency. Cisplatin injection is a cytotoxic drug.
Follow applicable special handling and disposable procedures. 1 Instructions for Preparation The aqueous solution should be used intravenously only and should be administered by IV infusion over a 6- to 8-hour period (see DOSAGE AND ADMINISTRATION ). Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit.
NOTE TO PHARMACIST: Exercise caution to prevent inadvertent cisplatin overdosage. Please call prescriber if dose is greater than 100 mg/m 2 per cycle. Aluminum flip-off seal of vial have been imprinted with the following statement: CALL DR.
IF DOSE > 100 MG/M 2 /CYCLE. Administration Administer cisplatin injection by slow intravenous infusion.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Cisplatin injection, USP, is a clear, colorless to pale yellow, sterile aqueous solution available in sterilie multiple-dose vials containing 50 mg/50 mL (1 mg/mL) 100 mg/100 mL (1 mg/mL) Cisplatin injection, USP, is multiple-dose vials containing 50 mg/50 mL (1 mg/mL) ( 3 ) 100 mg/100 mL (1 mg/mL) ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Cisplatin injection is contraindicated in patients with severe hypersensitivity to cisplatin [see Warnings and Precautions ( 5.4 )] . Severe hypersensitivity to cisplatin ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypersensitivity reactions: Anaphylaxis and death may occur; monitor for and treat accordingly ( 5.5 ) Ototoxicity: Cumulative toxicity may be severe particularly in pediatric patients; consider audiometric and vestibular function monitoring ( 5.6 , 8.4 ) Ocular toxicity: Optic neuritis, papilledema, and cortical blindness may occur ( 5.7 ) Secondary leukemia: Secondary acute leukemia may occur ( 5.8 ) Embryo-fetal toxicity: Can cause fetal harm. Advise of potential risk to a fetus and use of effective contraception.
( 5.9 , 8.1 , 8.3 )
5.1Nephrotoxicity Cisplatin injection can cause dose-related nephrotoxicity, including acute renal failure that becomes more prolonged and severe with repeated courses of the drug. Renal toxicity typically begins during the second week after a dose of cisplatin injection. Patients with baseline renal impairment, geriatric patients, patients who are taking other nephrotoxic drugs, or patients who are not well hydrated may be more susceptible to nephrotoxicity [see Use in Specific Populations ( 8.5 , 8.6 )] .
Ensure adequate hydration before, during, and after cisplatin injection administration [see Dosage and Administration ( 2.1 )] . Measure serum creatinine, blood urea nitrogen, creatinine clearance, and serum electrolytes including magnesium prior to initiating therapy, and as clinically indicated. Consider magnesium supplementation as clinically needed.
Consider alternative treatments or reduce the dose of cisplatin injection for patients with baseline renal impairment or who develop significant reductions in creatinine clearance during treatment with cisplatin injection according to clinical treatment guidelines [see Dosage and Administration ( 2.5 )].
5.2Peripheral Neuropathy Cisplatin injection can cause dose-related peripheral neuropathy that becomes more severe with repeated courses of the drug. Neurologic symptoms have been reported to occur after a single dose. Neuropathy can also have a delayed onset from 3 to 8 weeks after the last dose of cisplatin injection.
Manifestations include paresthesias in a stocking-glove distribution, areflexia, and loss of proprioception and vibratory sensation. The neuropathy may progress further even after stopping treatment. Peripheral neuropathy may be irreversible in some patients.
Perform a neurological examination before initiating cisplatin injection, at appropriate intervals during therapy, and after completion of therapy. Consider discontinuation of cisplatin injection for patients who develop symptomatic peripheral neuropathy. Geriatric patients may be more susceptible to peripheral neuropathy [see Use in Specific Populations ( 8.5 )] .
5.3Nausea and Vomiting Cisplatin injection is a highly emetogenic antineoplastic agent. Premedicate with anti-emetic agents [see Dosage and Administration ( 2.1 )] . Without antiemetic therapy, marked nausea and vomiting occur in almost all patients treated with cisplatin injection and may be so severe that the drug must be discontinued.
Nausea and vomiting may begin within 1 to 4 hours after treatment and last up to 72 hours. Maximal intensity occurs 48 to 72 hours after administration. Various degrees of vomiting, nausea, and/or anorexia may persist for up to 1 week after treatment.
Delayed nausea and vomiting (begins or persists 24 hours or more after chemotherapy) has occurred in patients attaining complete emetic control on the day of cisplatin injection therapy. Consider the use of additional anti-emetics following infusion.
5.4Myelosuppression Myelosuppression suppression occurs in 25% to 30% of patients treated with cisplatin injection. Fever and infection have been reported in patients with neutropenia. Potential fatalities due to infection (secondary to myelosuppression) have been reported.
Geriatric patients may be more susceptible to myelosuppression [see Use in Specific Populations ( 8.5 )] . Perform standard hematologic tests before initiating cisplatin injection, be… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are described in greater detail, in other sections: Nephrotoxicity [see Warnings and Precautions ( 5.1 )] Peripheral Neuropathy [see Warnings and Precautions ( 5.2 )] Nausea and vomiting [see Warnings and Precautions ( 5.3 )] Myelosuppression [see Warnings and Precautions ( 5.4 )] Hypersensitivity reactions [see Warnings and Precautions ( 5.5 )] Ototoxicity [see Warnings and Precautions ( 5.6 ] Ocular toxicity [see Warnings and Precautions ( 5.7 )] Secondary malignancies [see Warnings and Precautions ( 5.8 )] Injection site reactions [see Warnings and Precautions ( 5.10 )] Common adverse reactions are nephrotoxicity, peripheral neuropathy, nausea and vomiting myelosuppression, and ototoxicity.
The following adverse reactions have been identified from clinical trials or post-marketing surveillance. Blood and lymphatic system disorders: Coombs‑positive hemolytic anemia. hemolytic uremic syndrome, thrombotic thrombocytopenic purpura Cardiovascular disorders: Venous thromboembolism, arterial thromboembolism, myocardial infarction, cerebrovascular accident, thrombotic microangiopathy, cerebral arteritis, pericardial effusion, cardiac failure, ventricular dysfunction, Raynaud’s phenomenon Eye disorders: Optic neuritis, papilledema, cortical blindness, blurred vision, color blindness, retinal pigmentation Gastrointestinal disorders: Nausea, vomiting, anorexia, diarrhea, stomatitis, gastrointestinal perforation, pancreatitis, hiccups General disorders: Asthenia, malaise Hepatobiliary disorders: Elevations of aminotransferases, lactate dehydrogenase, and bilirubin; hepatic failure Hypersensitivity: Anaphylaxis, facial edema, wheezing, tachycardia, and hypotension Local Site Reactions: Tissue cellulitis, fibrosis, necrosis, pain, edema, and erythema Metabolism and nutrition disorders: Hypomagnesemia, often requiring magnesium supplementation; hyperuricemia, other electrolyte abnormalities (hypocalcemia, hyponatremia, hypokalemia, and hypophosphatemia), Syndrome of Inappropriate Antidiuretic Hormone Excretion (SIADH), dehydration, tumor lysis syndrome, increased serum amylase Musculoskeletal disorders: Muscle cramps (localized, painful, involuntary skeletal muscle contractions of sudden onset and short duration) Nervous system disorders: Peripheral neuropathy, Encephalopathy, loss of motor function, loss of taste, leukoencephalopathy, reversible posterior leukoencephalopathy syndrome, progressive multifocal leukoencephalopathy, seizures, Lhermitte’s sign, dorsal column myelopathy, autonomic neuropathy, seizures, involuntary skeletal muscle contractions, tetany (with hypocalcemia and hypomagnesemia) Ototoxicity: Tinnitus, hearing loss, deafness, vestibular toxicity Renal and urinary disorders: Nephrotoxicity including renal failure, renal electrolyte wasting, azotemia, decreased creatinine clearance Respiratory disorders: pneumonitis/interstitial lung disease, pulmonary embolism Skin and subcutaneous tissue disorders: Alopecia, rash Common adverse reactions are nephrotoxicity, peripheral neuropathy, nausea and vomiting, myelosuppression, and ototoxicity.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Accord Healthcare Inc. at 1-866-941-7875 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS The following drug interactions are described in other sections: Nephrotoxic drugs [see Warnings and Precautions ( 5.1 )] Ototoxic drugs [see Warnings and Precautions ( 5.6 )]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed. ( 8.2 ) Females and Males of Reproductive Potential: Verify pregnancy status prior to initiation of cisplatin injection. Can impair fertility. ( 8.3 )
8.1Pregnancy Risk Summary Based on human data from published literature, cisplatin injection can cause fetal harm when administered to pregnant women. Advise pregnant women and females of reproductive potential of the potential risk to a fetus. Data demonstrates transplacental transfer of cisplatin.
Exposure of pregnant women to cisplatin-containing chemotherapy has been associated with oligohydramnios, intrauterine growth restriction, and preterm birth. Cases of neonatal acute respiratory distress syndrome, cytopenias, and hearing loss have been reported. Cisplatin injection administration to animals during and after organogenesis resulted in teratogenicity.
A published study in mice showed placental transfer of cisplatin increased with placenta maturation. The background risk of major birth defects and miscarriage for the indicated populations are unknown. However, the background risk in the U.S. general population of major birth defects is 2-4% and of miscarriage is 15-20% of clinically recognized pregnancies.
8.2Lactation Risk Summary Limited data from published literature report the presence of cisplatin in human milk in low amounts. Because of the potential for serious adverse reactions from cisplatin injection in a breastfed child and because of the potential for tumorigenicity shown for cisplatin injection, advise lactating women not to breastfeed during treatment with cisplatin injection.
8.3Females and Males of Reproductive Potential Pregnancy Testing Verify the pregnancy status of females of reproductive potential prior to initiation of cisplatin injection. Contraception Females Cisplatin injection can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations ( 8.1 )] . Advise females of reproductive potential to use effective contraception during treatment and for 14 months following the last dose of cisplatin injection.
Males Advise male patients with female partners of reproductive potential to use effective contraception during treatment and for 11 months after the last dose of cisplatin injection. Infertility Females The use of cisplatin has been associated with cumulative dose-dependent ovarian failure, premature menopause, and reduced fertility. Males The use of cisplatin has been associated with a cumulative dose-dependent impairment of spermatogenesis (oligospermia, azoospermia; possibly irreversible) and reduced fertility.
8.4Pediatric Use Ototoxic effects may be more severe and detrimental in pediatric patients receiving cisplatin injection, particularly in patients less than 5 years of age. Consider audiometric and vestibular function monitoring in all patients receiving cisplatin injection. The prevalence of hearing loss in pediatric patients is particularly high and is estimated to be 40% to 60%.
Earlier detection of hearing loss can limit the potential impact of hearing impairment on a pediatric patient’s cognitive and social development [see Warnings and Precautions ( 5.6 )].
8.5Geriatric Use For the treatment of metastatic testicular tumors or advanced bladder cancer, clinical studies of cisplatin injection did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. In four clinical trials of combination chemotherapy for advanced ovarian carcinoma, 1,484 patients received cisplatin either in combination with cyclophosphamide or with paclitaxel. Of these, 426 (29%) were older than 65 years.
In these trials, age was not found to be a prognostic factor for survival. However, in a later secondary analysis for one of these trials, geriatric patients were found to have shorter survival compared with younger patients. In all four trials, geriatric patients experienced more severe neutro… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on human data from published literature, cisplatin injection can cause fetal harm when administered to pregnant women. Advise pregnant women and females of reproductive potential of the potential risk to a fetus. Data demonstrates transplacental transfer of cisplatin.
Exposure of pregnant women to cisplatin-containing chemotherapy has been associated with oligohydramnios, intrauterine growth restriction, and preterm birth. Cases of neonatal acute respiratory distress syndrome, cytopenias, and hearing loss have been reported. Cisplatin injection administration to animals during and after organogenesis resulted in teratogenicity.
A published study in mice showed placental transfer of cisplatin increased with placenta maturation. The background risk of major birth defects and miscarriage for the indicated populations are unknown. However, the background risk in the U.S. general population of major birth defects is 2-4% and of miscarriage is 15-20% of clinically recognized pregnancies.
🧒 Pediatric Use ▾
8.4Pediatric Use Ototoxic effects may be more severe and detrimental in pediatric patients receiving cisplatin injection, particularly in patients less than 5 years of age. Consider audiometric and vestibular function monitoring in all patients receiving cisplatin injection. The prevalence of hearing loss in pediatric patients is particularly high and is estimated to be 40% to 60%.
Earlier detection of hearing loss can limit the potential impact of hearing impairment on a pediatric patient’s cognitive and social development [see Warnings and Precautions ( 5.6 )].
🧓 Geriatric Use ▾
8.5Geriatric Use For the treatment of metastatic testicular tumors or advanced bladder cancer, clinical studies of cisplatin injection did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. In four clinical trials of combination chemotherapy for advanced ovarian carcinoma, 1,484 patients received cisplatin either in combination with cyclophosphamide or with paclitaxel. Of these, 426 (29%) were older than 65 years.
In these trials, age was not found to be a prognostic factor for survival. However, in a later secondary analysis for one of these trials, geriatric patients were found to have shorter survival compared with younger patients. In all four trials, geriatric patients experienced more severe neutropenia than did younger patients.
Higher incidences of severe thrombocytopenia and leukopenia were also seen in geriatric patients compared with younger patients, although not in all cisplatin-containing treatment arms. In the two trials where nonhematologic toxicity was evaluated according to age, geriatric patients had a numerically higher incidence of peripheral neuropathy than did younger patients. Other reported clinical experience suggests that geriatric patients may be more susceptible to nephrotoxicity, myelosuppression, and infectious complications than are younger patients [see Warnings and Precautions ( 5.1 , 5.2 , 5.4 )].
Cisplatin is known to be substantially excreted by the kidney. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and renal function should be monitored.
🆘 Overdosage ▾
10 OVERDOSAGE Acute overdosage with cisplatin injection may result in renal failure, hepatic failure, hearing loss, ocular toxicity, myelosuppression, nausea and vomiting, and neuritis. In addition, death can occur following overdosage. Management of overdosage should include general supportive measures to sustain the patient through any period of toxicity that may occur.
Important measures include renal protection by intravenous hydration with or without the use of an osmotic diuretic. Hemodialysis is not effective because of the high degree of protein binding of cisplatin injection. Plasmapheresis has been used to treat cases of cisplatin injection overdosage, but the optimal treatment regimen has not been established.
For current information on the management of poisoning or overdosage, contact the National Poison Control Center at 1-800-222-1222 or www.poison.org .
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The main mechanism of the cytotoxic action involves the binding of cisplatin to genomic DNA in the cell nucleus to form interstrand and intrastrand cross-links. This interferes with normal transcription and/or DNA replication mechanisms and triggers cytotoxic processes that lead to cell death.
12.3Pharmacokinetics Distribution Cisplatin dose not undergo the instantaneously and reversible binding to plasma protein that is characteristic of normal drug-protein binding. Platinum from cisplatin, but not cisplatin itself, becomes bound to several plasma proteins, including albumin, transferrin, and gamma globulin. Three hours after a bolus injection and 2 hours after the end of a 3 hour infusion, 90% of the plasma platinum is protein bound.
The complexes between albumin and the platinum from cisplatin do not dissociate to a significant extent and are slowly eliminated with a minimum half-life of 5 days or more. Following cisplatin doses of 20 mg/m 2 to 120 mg/m 2 , platinum is present in tissues for as long as 180 days after the last administration. With the exception of intracerebral tumors, platinum concentrations in tumors are generally somewhat lower than the concentrations in the organ where the tumor is located.
Hepatic metastases have the highest platinum concentrations, but these are similar to the platinum concentrations in normal liver. Maximum red blood cell concentrations of platinum are reached within 90 to 150 minutes after a 100 mg/m 2 dose of cisplatin and decline in a biphasic manner with a terminal half-life of 36 to 47 days. Metabolism The chlorine atoms of cisplatin are more subject to chemical displacement reactions by nucleophiles, such as water or sulfhydryl groups, than to enzyme-catalyzed metabolism.
At physiological pH, the predominant molecular species are cisplatin and monohydroxymonochloro cis -diamine platinum (II) in nearly equal concentrations. The latter, combined with the possible direct displacement of the chlorine atoms by sulfhydryl groups of amino acids or proteins, accounts for the instability of cisplatin in biological matrices. The ratios of cisplatin to total free (ultrafilterable) platinum in the plasma vary considerably between patients and range from 0.5 to 1.1 after a dose of 100 mg/m 2 .
Elimination Over a dose range of 40 mg to 140 mg cisplatin per m 2 given as a bolus injection or as infusions varying in length from 1 hour to 24 hours, from 10% to about 40% of the administered platinum is excreted in the urine in 24 hours. Over 5 days following administration of 40 mg/m 2 to 100 mg/m 2 doses given as rapid, 2 to 3 hour or 6 to 8 hour infusions, a mean of 35% to 51% of the dosed platinum is excreted in the urine. Similar mean urinary recoveries of platinum of about 14% to 30% of the dose are found following 5 daily administrations of 20 mg/m 2 per day, 30 mg/m 2 per day, or 40 mg/m 2 per day.
Only a small percentage of the administered platinum is excreted beyond 24 hours post-infusion and most of the platinum excreted in the urine in 24 hours is excreted within the first few hours. The parent compound, cisplatin, is excreted in the urine and accounts for 13% to 17% of the dose excreted within 1 hour after administration of 50 mg/m 2 . The mean renal clearance of cisplatin exceeds creatinine clearance and was 62 mL/min per m 2 and 50 mL/min per m 2 following administration of 100 mg/m 2 as 2 hour or 6 to 7 hour infusions, respectively.
Plasma concentrations of the parent compound, cisplatin, decrease monoexponentially with a half-life of about 20 to 30 minutes following bolus administrations of 50 mg/m 2 or 100 mg/m 2 doses. Monoexponential decreases and plasma half-lives of about 0.5 hour are also seen following 2 hour or 7 hour infusions of 100 mg/m 2 . After the latter, the total body clearances and volumes of distribution at steady-state for cisplatin are about 15 Liters per hour per m 2 to 16 Liters per hour per m 2 and 11 Liters… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action The main mechanism of the cytotoxic action involves the binding of cisplatin to genomic DNA in the cell nucleus to form interstrand and intrastrand cross-links. This interferes with normal transcription and/or DNA replication mechanisms and triggers cytotoxic processes that lead to cell death.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied Cisplatin injection, USP NDC 16729-288-11—Each multiple-dose amber vial contains 50 mg/50 mL (1 mg/mL) of cisplatin USP as a clear, colorless to pale yellow, sterile aqueous solution. NDC 16729-288-38—Each multiple-dose amber vial contains 100 mg/100 mL (1 mg/mL) of cisplatin USP as a clear, colorless to pale yellow, sterile aqueous solution. Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
Do not refrigerate or freeze cisplatin solution since a precipitate or crystal will form. If precipitate or crystal observed inside the vial, keep it at recommended storage condition till clear solution obtained. Protect unopened container from light.
The cisplatin remaining in the amber vial following initial entry is stable for 28 days protected from light or for 7 days under fluorescent room light. Handling and Disposal Cisplatin injection, USP, is a cytotoxic drug. Follow applicable special handling and disposal procedures.
1
📋 Description ▾
11 DESCRIPTION Cisplatin injection, USP, a platinum-based drug for intravenous use, is a clear, colorless to pale yellow, sterile aqueous solution. Each 50 mL or 100 mL amber vial of Cisplatin injection, USP, contains: 1 mg/mL cisplatin USP, 9 mg/mL sodium chloride, hydrochloric acid and/or sodium hydroxide to adjust pH, and water for injection to a final volume of 50 mL or 100 mL, respectively. The pH range of Cisplatin Injection, USP, is 3.5 to 5.0.
Cisplatin USP the active ingredient in Cisplatin injection, USP, is a yellow to orange crystalline powder with the molecular formula Cl 2 H 6 N 2 Pt and a molecular weight of 300.05. Cisplatin USP is a heavy metal complex containing a central atom of platinum surrounded by two chloride atoms and two ammonia molecules in the cis position. It is soluble in water or saline at 1 mg/mL and in dimethylformamide at 24 mg/mL.
It has a melting point of 207°C. The structural formula is: structural formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Nephrotoxicity Inform patients that cisplatin injection can cause nephrotoxicity and that renal function and electrolyte monitoring during treatment is necessary. If indicated, inform patients about the use of electrolyte supplements [see Warnings and Precautions ( 5.1 )]. Peripheral Neuropathy Advise patients to report any new paresthesias to their healthcare provider [see Warnings and Precautions ( 5.2 )].
Nausea and Vomiting Advise patients concerning the use of antiemetics to prevent nausea and vomiting and to report persistent or severe symptoms to their healthcare provider [see Warnings and Precautions ( 5.3 )]. Myelosuppression Advise patients that cisplatin injection can reduce the absolute neutrophil count and the platelet count resulting in an increased risk of infection and bleeding and to contact their healthcare provider for new onset fever, symptoms of infection, or bleeding [see Warnings and Precautions ( 5.4 )].
Ototoxicity Advise patients to report any symptoms of hearing loss or vestibular dysfunction to their healthcare provider and that periodic monitoring of hearing may be performed [see Warnings and Precautions ( 5.6 )]. Embryo-Fetal Toxicity Advise females of reproductive potential of the potential risk to a fetus and to inform their healthcare provider if they are pregnant or become pregnant [see Warnings and Precautions 5.9 and Use in Specific Populations 8.1 )]. Advise females of reproductive potential to use effective contraception during treatment and for 14 months following the last dose of cisplatin injection [see Use in Specific Populations ( 8.3 )].
Advise male patients with female partners of reproductive potential to use effective contraception during treatment and for 11 months following the last dose of cisplatin injection [see Use in Specific Populations ( 8.3 )]. Lactation Advise females not to breastfeed during treatment with cisplatin injection [ see Use in Specific Populations ( 8.2 )]. Infertility Inform patients that treatment with cisplatin injection may lead to permanent impairment of spermatogenesis, ovarian failure or premature menopause, and reduced fertility in both genders [see Use in Specific Populations ( 8.3 )] .
Alopecia Inform patients that cisplatin injection can cause alopecia. Manufactured For: Accord Healthcare, Inc., 8041 Arco Corporate Drive, Suite 200, Raleigh, NC 27617, USA. Manufactured By: Intas Pharmaceuticals Limited, Plot No.
5 to 14 Pharmez, Nr. Village Matoda, Bavla Road, Ta.- Sanand, Dist. Ahmedabad - 382213, India 51 2129 3 734154 Issued: December 2023
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Distribution Cisplatin dose not undergo the instantaneously and reversible binding to plasma protein that is characteristic of normal drug-protein binding. Platinum from cisplatin, but not cisplatin itself, becomes bound to several plasma proteins, including albumin, transferrin, and gamma globulin. Three hours after a bolus injection and 2 hours after the end of a 3 hour infusion, 90% of the plasma platinum is protein bound.
The complexes between albumin and the platinum from cisplatin do not dissociate to a significant extent and are slowly eliminated with a minimum half-life of 5 days or more. Following cisplatin doses of 20 mg/m 2 to 120 mg/m 2 , platinum is present in tissues for as long as 180 days after the last administration. With the exception of intracerebral tumors, platinum concentrations in tumors are generally somewhat lower than the concentrations in the organ where the tumor is located.
Hepatic metastases have the highest platinum concentrations, but these are similar to the platinum concentrations in normal liver. Maximum red blood cell concentrations of platinum are reached within 90 to 150 minutes after a 100 mg/m 2 dose of cisplatin and decline in a biphasic manner with a terminal half-life of 36 to 47 days. Metabolism The chlorine atoms of cisplatin are more subject to chemical displacement reactions by nucleophiles, such as water or sulfhydryl groups, than to enzyme-catalyzed metabolism.
At physiological pH, the predominant molecular species are cisplatin and monohydroxymonochloro cis -diamine platinum (II) in nearly equal concentrations. The latter, combined with the possible direct displacement of the chlorine atoms by sulfhydryl groups of amino acids or proteins, accounts for the instability of cisplatin in biological matrices. The ratios of cisplatin to total free (ultrafilterable) platinum in the plasma vary considerably between patients and range from 0.5 to 1.1 after a dose of 100 mg/m 2 .
Elimination Over a dose range of 40 mg to 140 mg cisplatin per m 2 given as a bolus injection or as infusions varying in length from 1 hour to 24 hours, from 10% to about 40% of the administered platinum is excreted in the urine in 24 hours. Over 5 days following administration of 40 mg/m 2 to 100 mg/m 2 doses given as rapid, 2 to 3 hour or 6 to 8 hour infusions, a mean of 35% to 51% of the dosed platinum is excreted in the urine. Similar mean urinary recoveries of platinum of about 14% to 30% of the dose are found following 5 daily administrations of 20 mg/m 2 per day, 30 mg/m 2 per day, or 40 mg/m 2 per day.
Only a small percentage of the administered platinum is excreted beyond 24 hours post-infusion and most of the platinum excreted in the urine in 24 hours is excreted within the first few hours. The parent compound, cisplatin, is excreted in the urine and accounts for 13% to 17% of the dose excreted within 1 hour after administration of 50 mg/m 2 . The mean renal clearance of cisplatin exceeds creatinine clearance and was 62 mL/min per m 2 and 50 mL/min per m 2 following administration of 100 mg/m 2 as 2 hour or 6 to 7 hour infusions, respectively.
Plasma concentrations of the parent compound, cisplatin, decrease monoexponentially with a half-life of about 20 to 30 minutes following bolus administrations of 50 mg/m 2 or 100 mg/m 2 doses. Monoexponential decreases and plasma half-lives of about 0.5 hour are also seen following 2 hour or 7 hour infusions of 100 mg/m 2 . After the latter, the total body clearances and volumes of distribution at steady-state for cisplatin are about 15 Liters per hour per m 2 to 16 Liters per hour per m 2 and 11 Liters per m 2 to 12 Liters per m 2 .
The renal clearance of free (ultrafilterable) platinum also exceeds the glomerular filtration rate, indicating that cisplatin or other platinum-containing molecules are actively secreted by the kidneys. The renal clearance of free platinum is nonlinear and variable and is dependent on dose, urine flow rate, and… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility The carcinogenic effect of cisplatin injection was studied in BDIX rats. Cisplatin injection was administered three times a week at 1 mg/kg body weight intraperitoneally to 50 BDIX rats for 3 weeks. Four hundred fifty-five days after the first application, 33 animals died, 13 of them related to malignancies (12 leukemias and 1 renal fibrosarcoma) [see Warnings and Precautions ( 5.8 )].
Cisplatin is mutagenic in the bacteria reverse mutation (Ames) test and produces chromosome aberrations in mammalian cells.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility The carcinogenic effect of cisplatin injection was studied in BDIX rats. Cisplatin injection was administered three times a week at 1 mg/kg body weight intraperitoneally to 50 BDIX rats for 3 weeks. Four hundred fifty-five days after the first application, 33 animals died, 13 of them related to malignancies (12 leukemias and 1 renal fibrosarcoma) [see Warnings and Precautions ( 5.8 )].
Cisplatin is mutagenic in the bacteria reverse mutation (Ames) test and produces chromosome aberrations in mammalian cells.
📚 References ▾
15 REFERENCES OSHA Hazardous Drugs. OSHA. http://www.osha.gov/SLTC/hazardousdrugs/index.html
📄 Package Label / Principal Display Panel ▾
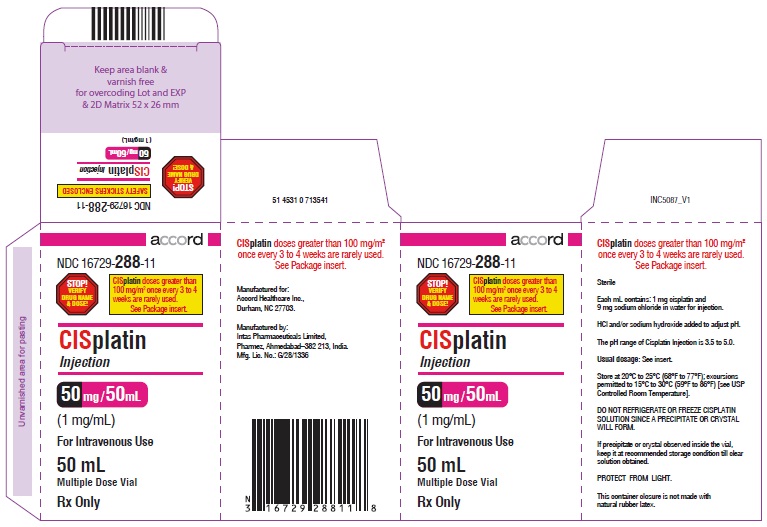
PACKAGE/LABEL PRINCIPAL DISPLAY PANEL Cisplatin Injection 50 mL Multiple Dose Vial (1 mg/mL)- Carton 50 mL Multiple Dose Vial (1 mg/mL)- Label 100 mL Multiple Dose Vial (1 mg/mL)- Carton 100 mL Multiple Dose Vial (1 mg/mL)- Label 50ml-vial-carton 50ml-vial-Label 100 ml-vial-carton 100 ml-vial-Label
Medicaid utilization & spend
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |