
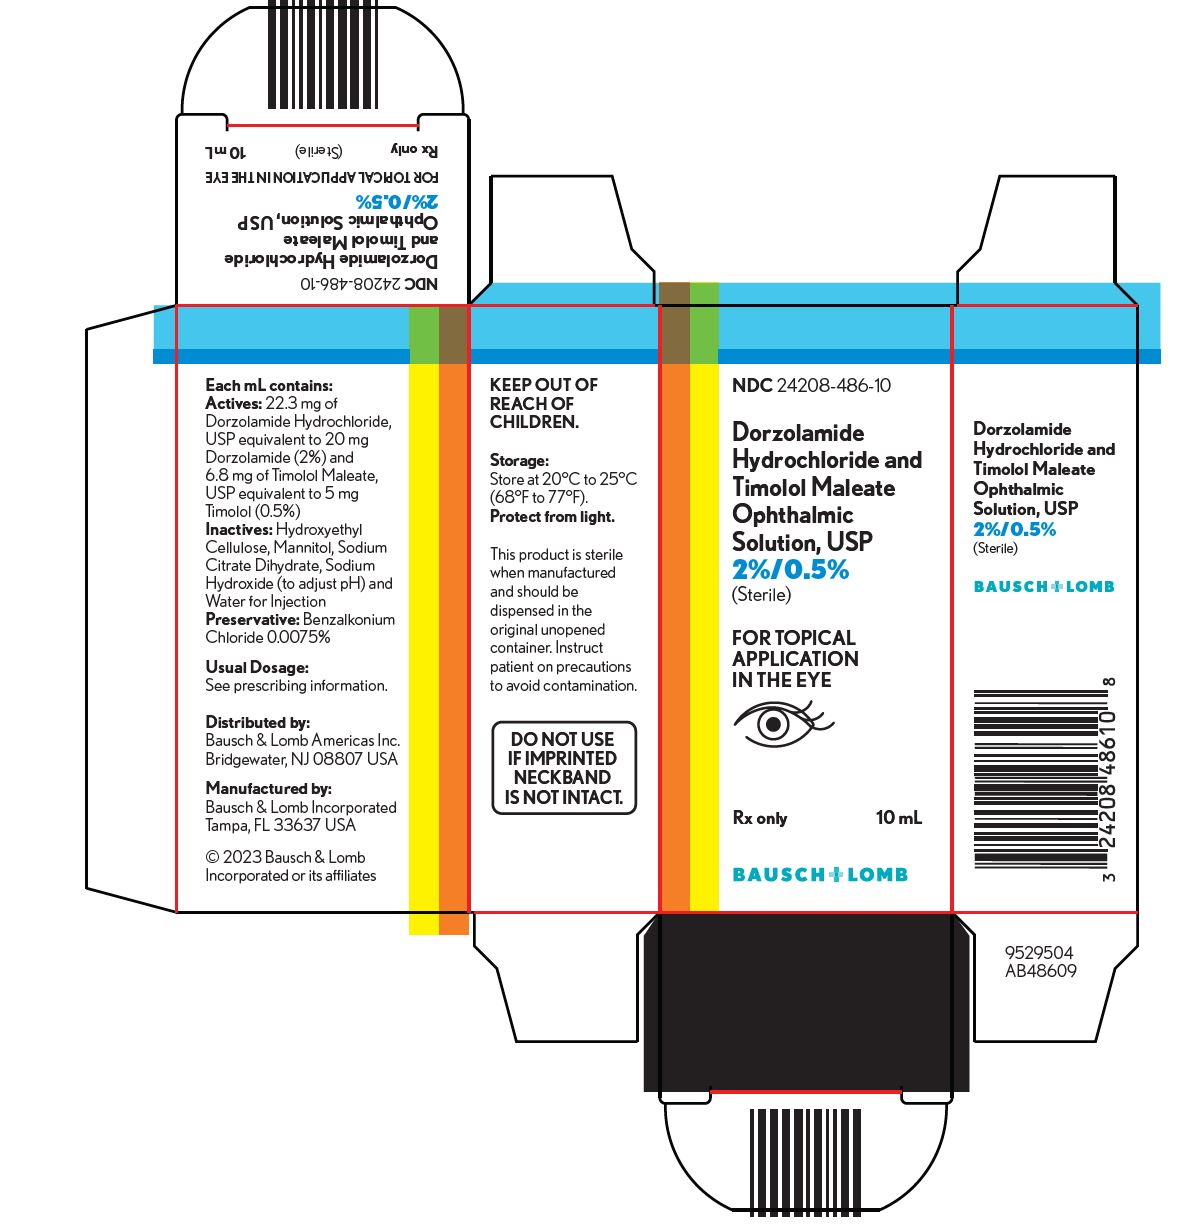
Dorzolamide Hydrochloride and Timolol Maleate 20 mg/mL; 5 mg/mL Solution/ Drops — NDC 24208-486-10 (Billing 24208-0486-10)
This is a package of Dorzolamide Hydrochloride and Timolol Maleate 20 mg/mL; 5 mg/mL Solution/ Drops from Bausch & Lomb Incorporated, marketed since Jul 2009 and currently FDA-listed; retail pharmacies pay about $0.8927 per mL (NADAC). It is the main listing for this product, which comes in 2 package sizes.
Other active recalls for Dorzolamide Hydrochloride And Timolol Maleate (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 039531
- GCN: 95919
- GPI-14 (Medi-Span): 86259902202020
- HICL (First Databank): 018269
- AHFS class code: 12:16.08.04
- RxCUI (RxNorm): 1923432
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the beta-Adrenergic Blocker class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Dorzolamide and timolol is used to treat glaucoma and ocular hypertension (eye conditions that lead to increased intraocular pressure and can progress to vision loss). Dorzolamide is in a class of medications called topical carbonic anhydrase inhibitors. Timolol is in a class of medications called topical beta blockers. Dorzolamide and timolol lowers pressure in the eye by decreasing the production of natural fluids in the eye.
Read the full MedlinePlus article ↗- It lowers high pressure inside the eye in open-angle glaucoma or ocular hypertension. It's used when beta-blockers alone haven't brought the pressure down enough. Lowering eye pres...
- You put one drop in the affected eye(s) twice a day. If you use other eye drops, wait at least five minutes between them. If yours is a preservative-free single-use unit, use it ri...
- The most common are a bitter or unusual taste, plus eye burning or stinging. Redness, blurry vision and itching can also happen. These are usually manageable, but tell me if they b...
- Call for wheezing, trouble breathing, swelling or signs of heart failure, a very slow heartbeat, fainting, or a severe rash or allergic reaction. Stop the drops and get help if the...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.893 | $8.93 / 10 ml |
| Medicaid paysCMS SDUD · 12 mo | $1.88 | $18.83 / 10 ml |
| Medicare drug plans payPart D · Q2 2026 | $1.23 | $12.33 / 10 ml |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 24208-0486-05 24208-486-05 | 1 BOTTLE, DROPPER in 1 CARTON / 5 mL in 1 BOTTLE, DROPPER | — | — | 2009-07-14 | — | Active |
| 24208-0486-10 You're viewing this Main listing | 1 BOTTLE, DROPPER in 1 CARTON / 10 mL in 1 BOTTLE, DROPPER | $0.8927 / mL | $8.93 | 2009-07-14 | — | Active |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Dorzolamide Hydrochloride and Timolol Maleate 20 mg/mL; 5 mg/mL Solution/ Drops?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII F5UM2KM3W7
Benzalkonium chloride is a chemical compound that works as a preservative and antimicrobial agent in medications. It prevents bacterial and fungal growth in liquid formulations to keep the product safe during storage and use.
-
UNII S38J6RZN16
Hydroxyethyl cellulose is a plant-derived thickening agent made from cellulose. In medicines, it acts as a binder to hold ingredients together, a thickener to adjust product texture, and a film-former to create smooth coatings on tablets.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII B22547B95K
A salt derived from citric acid that helps maintain the proper acid-base balance in the medicine. It's used as a buffer to keep the product stable and at the right pH level.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Dorzolamide hydrochloride and timolol maleate ophthalmic solution is indicated for the reduction of elevated intraocular pressure (IOP) in patients with open-angle glaucoma or ocular hypertension who are insufficiently responsive to beta-blockers (failed to achieve target IOP determined after multiple measurements over time). The IOP-lowering of dorzolamide hydrochloride and timolol maleate ophthalmic solution administered twice a day was slightly less than that seen with the concomitant administration of 0.5% timolol administered twice a day and 2% dorzolamide administered three times a day [see Clinical Studies (14) ]. • Dorzolamide hydrochloride and timolol maleate ophthalmic solution is a carbonic anhydrase inhibitor with a beta-adrenergic receptor blocking agent indicated for the reduction of elevated intraocular pressure (IOP) in patients with open-angle glaucoma or ocular hypertension who are insufficiently responsive to beta-blockers. • The IOP-lowering of dorzolamide hydrochloride and timolol maleate ophthalmic solution twice daily was slightly less than that seen with the concomitant administration of 0.5% timolol twice daily, and 2% dorzolamide three times daily.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The dose is one drop of dorzolamide hydrochloride and timolol maleate ophthalmic solution in the affected eye(s) two times daily. If more than one topical ophthalmic drug is being used, the drugs should be administered at least five minutes apart [see Drug Interactions (7.3) ]. The dose is one drop of dorzolamide hydrochloride and timolol maleate ophthalmic solution in the affected eye(s) two times daily. ( 2 )
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Dorzolamide hydrochloride and timolol maleate ophthalmic solution, USP containing dorzolamide 20 mg/mL (2%) equivalent to 22.26 mg/mL of dorzolamide hydrochloride and timolol 5 mg/mL (0.5%) equivalent to 6.83 mg/mL of timolol maleate. Ophthalmic solution containing dorzolamide 20 mg/mL (2%) and timolol 5 mg/mL (0.5%). ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Dorzolamide hydrochloride and timolol maleate ophthalmic solution is contraindicated in patients with: • Bronchial asthma or a history of bronchial asthma, severe chronic obstructive pulmonary disease. ( 4.1 ) • Sinus bradycardia, second or third degree atrioventricular block, overt cardiac failure, cardiogenic shock. ( 4.2 ) • Hypersensitivity to any component of this product. ( 4.3 , 5.3 )
4.1Asthma, COPD Dorzolamide hydrochloride and timolol maleate ophthalmic solution is contraindicated in patients with bronchial asthma, a history of bronchial asthma, or severe chronic obstructive pulmonary disease [see Warnings and Precautions (5.1) ].
4.2Sinus Bradycardia, AV Block, Cardiac Failure, Cardiogenic Shock Dorzolamide hydrochloride and timolol maleate ophthalmic solution is contraindicated in patients with sinus bradycardia, second or third degree atrioventricular block, overt cardiac failure, and cardiogenic shock [see Warnings and Precautions (5.2) ].
4.3Hypersensitivity Dorzolamide hydrochloride and timolol maleate ophthalmic solution is contraindicated in patients who are hypersensitive to any component of this product [see Warnings and Precautions (5.3) ].
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Potentiation of Respiratory Reactions Including Asthma ( 5.1 ) • Cardiac Failure ( 5.2 ) • Sulfonamide Hypersensitivity ( 5.3 ) • Obstructive Pulmonary Disease ( 5.4 ) • Increased Reactivity to Allergens ( 5.5 ) • Potentiation of Muscle Weakness ( 5.6 ) • Masking of Hypoglycemic Symptoms in Patients with Diabetes Mellitus ( 5.7 ) • Masking of Thyrotoxicosis ( 5.8 ) • Renal and Hepatic Impairment ( 5.9 ) • Impairment of Beta-Adrenergically Mediated Reflexes During Surgery ( 5.10 )
5.1Potentiation of Respiratory Reactions Including Asthma Dorzolamide hydrochloride and timolol maleate ophthalmic solution contains timolol maleate, a beta-adrenergic blocking agent; and although administered topically, is absorbed systemically. Therefore, the same types of adverse reactions that are attributable to systemic administration of beta-adrenergic blocking agents may occur with topical administration. For example, severe respiratory reactions, including death due to bronchospasm in patients with asthma, and rarely death in association with cardiac failure, have been reported following systemic or ophthalmic administration of timolol maleate [see Contraindications (4.1) ].
5.2Cardiac Failure Sympathetic stimulation may be essential for support of the circulation in individuals with diminished myocardial contractility, and its inhibition by beta-adrenergic receptor blockade may precipitate more severe failure. In patients without a history of cardiac failure continued depression of the myocardium with beta-blocking agents over a period of time can, in some cases, lead to cardiac failure. At the first sign or symptom of cardiac failure, dorzolamide hydrochloride and timolol maleate ophthalmic solution should be discontinued [see Contraindications (4.2) ].
5.3Sulfonamide Hypersensitivity Dorzolamide hydrochloride and timolol maleate ophthalmic solution contains dorzolamide, a sulfonamide; and although administered topically, it is absorbed systemically. Therefore, the same types of adverse reactions that are attributable to sulfonamides may occur with topical administration of dorzolamide hydrochloride and timolol maleate ophthalmic solution. Fatalities have occurred, although rarely, due to severe reactions to sulfonamides including Stevens-Johnson syndrome, toxic epidermal necrolysis, fulminant hepatic necrosis, agranulocytosis, aplastic anemia, and other blood dyscrasias.
Sensitization may recur when a sulfonamide is readministered irrespective of the route of administration. If signs of serious reactions or hypersensitivity occur, discontinue the use of this preparation [see Contraindications (4.3) ].
5.4Obstructive Pulmonary Disease Patients with chronic obstructive pulmonary disease (e.g., chronic bronchitis, emphysema) of mild or moderate severity, bronchospastic disease, or a history of bronchospastic disease (other than bronchial asthma or a history of bronchial asthma, in which dorzolamide hydrochloride and timolol maleate ophthalmic solution is contraindicated) should, in general, not receive beta-blocking agents, including dorzolamide hydrochloride and timolol maleate ophthalmic solution [see Contraindications (4.1) ].
5.5Increased Reactivity to Allergens While taking beta-blockers, patients with a history of atopy or a history of severe anaphylactic reactions to a variety of allergens may be more reactive to repeated accidental, diagnostic, or therapeutic challenge with such allergens. Such patients may be unresponsive to the usual doses of epinephrine used to treat anaphylactic reactions.
5.6Potentiation of Muscle Weakness Beta-adrenergic blockade has been reported to potentiate muscle weakness consistent with certain myasthenic symptoms (e.g., diplopia, ptosis, and generalized weakness). Timolol has been reported rarely to increase muscle weakness in some patients with myasthenia gravis or myasthenic symptoms.
5.7Masking of Hypoglycemic Symptoms in Patients with Diabetes Mellitus Beta-adrenerg… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most frequently reported adverse reactions were taste perversion (bitter, sour, or unusual taste) or ocular burning and/or stinging in up to 30% of patients. Conjunctival hyperemia, blurred vision, superficial punctate keratitis or eye itching were reported between 5 to 15% of patients. ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Bausch & Lomb Incorporated at 1-800-553-5340 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Dorzolamide hydrochloride and timolol maleate ophthalmic solution was evaluated in 1,035 patients with elevated intraocular pressure treated for open-angle glaucoma or ocular hypertension for up to 15 months. Approximately 5% of all patients discontinued therapy because of adverse reactions.
The most frequently reported adverse reactions occurring in up to 30% of patients were taste perversion (bitter, sour, or unusual taste) or ocular burning and/or stinging. The following adverse reactions were reported in 5 to 15% of patients: conjunctival hyperemia, blurred vision, superficial punctate keratitis or eye itching. The following adverse reactions were reported in 1 to 5% of patients: abdominal pain, back pain, blepharitis, bronchitis, cloudy vision, conjunctival discharge, conjunctival edema, conjunctival follicles, conjunctival injection, conjunctivitis, corneal erosion, corneal staining, cortical lens opacity, cough, dizziness, dryness of eyes, dyspepsia, eye debris, eye discharge, eye pain, eye tearing, eyelid edema, eyelid erythema, eyelid exudate/scales, eyelid pain or discomfort, foreign body sensation, glaucomatous cupping, headache, hypertension, influenza, lens nucleus coloration, lens opacity, nausea, nuclear lens opacity, pharyngitis, post-subcapsular cataract, sinusitis, upper respiratory infection, urinary tract infection, visual field defect, vitreous detachment.
Other adverse reactions that have been reported with the individual components are listed below: Dorzolamide 2% Angioedema, asthenia/fatigue, bronchospasm, contact dermatitis, epistaxis, eyelid crusting, ocular discomfort, photophobia, signs and symptoms of ocular allergic reaction, transient myopia. Timolol (ocular administration) Body as a Whole: Asthenia/fatigue; Cardiovascular: Arrhythmia, syncope, cerebral ischemia, worsening of angina pectoris, palpitation, cardiac arrest, pulmonary edema, edema, claudication, Raynaud’s phenomenon, and cold hands and feet; Digestive: Anorexia, abdominal pain; Immunologic: Systemic lupus erythematosus; Nervous System/Psychiatric: Increase in signs and symptoms of myasthenia gravis, somnolence, insomnia, nightmares, behavioral changes and psychic disturbances including confusion, hallucinations, anxiety, disorientation, nervousness, and memory loss; Skin: Alopecia, psoriasiform rash or exacerbation of psoriasis; Hypersensitivity: Signs and symptoms of systemic allergic reactions, including anaphylaxis, angioedema, urticaria, and localized and generalized rash; Respiratory: Bronchospasm (predominantly in patients with pre-existing bronchospastic disease); Endocrine: Masked symptoms of hypoglycemia in diabetic patients; Special Senses: Ptosis, decreased corneal sensitivity, cystoid macular edema, visual disturbances including refractive changes and diplopia, pseudopemphigoid, and tinnitus; Urogenital: Retroperitoneal fibrosis, decreased libido, impotence, and Peyronie’s disease; Musculoskeletal: Myalgia.
6.2Post-Marketing Experience The following adverse reactions have been identified during post-approval use of dorzolamide hydrochloride and timolol maleate ophthalmic solution. Because these reactions are reported voluntarily from a population of uncertain size, it is not alway… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Potential additive effect of oral carbonic anhydrase inhibitor with dorzolamide hydrochloride and timolol maleate ophthalmic solution. ( 7.1 ) • Potential acid-base and electrolyte disturbances. ( 7.2 ) • Concomitant use with systemic beta-blockers may potentiate systemic beta-blockade.
( 7.3 ) • Oral or intravenous calcium antagonists may cause atrioventricular conduction disturbances, left ventricular failure, and hypotension. ( 7.4 ) • Catecholamine-depleting drugs may have additive effects and produce hypotension and/or marked bradycardia. ( 7.5 ) • Digitalis and calcium antagonists, may have additive effects in prolonging atrioventricular conduction time.
( 7.6 ) • CYP2D6 inhibitors may potentiate systemic beta-blockade. ( 7.7 )
7.1Oral Carbonic Anhydrase Inhibitors There is a potential for an additive effect on the known systemic effects of carbonic anhydrase inhibition in patients receiving an oral carbonic anhydrase inhibitor and dorzolamide hydrochloride and timolol maleate ophthalmic solution. The concomitant administration of dorzolamide hydrochloride and timolol maleate ophthalmic solution and oral carbonic anhydrase inhibitors is not recommended.
7.2High-Dose Salicylate Therapy Although acid-base and electrolyte disturbances were not reported in the clinical trials with dorzolamide hydrochloride ophthalmic solution, these disturbances have been reported with oral carbonic anhydrase inhibitors and have, in some instances, resulted in drug interactions (e.g., toxicity associated with high-dose salicylate therapy). Therefore, the potential for such drug interactions should be considered in patients receiving dorzolamide hydrochloride and timolol maleate ophthalmic solution.
7.3Beta-Adrenergic Blocking Agents Patients who are receiving a beta-adrenergic blocking agent orally and dorzolamide hydrochloride and timolol maleate ophthalmic solution should be observed for potential additive effects of beta-blockade, both systemic and on intraocular pressure. The concomitant use of two topical beta-adrenergic blocking agents is not recommended.
7.4Calcium Antagonists Caution should be used in the coadministration of beta-adrenergic blocking agents, such as dorzolamide hydrochloride and timolol maleate ophthalmic solution, and oral or intravenous calcium antagonists because of possible atrioventricular conduction disturbances, left ventricular failure, and hypotension. In patients with impaired cardiac function, coadministration should be avoided.
7.5Catecholamine-Depleting Drugs Close observation of the patient is recommended when a beta-blocker is administered to patients receiving catecholamine-depleting drugs, such as reserpine, because of possible additive effects and the production of hypotension and/or marked bradycardia, which may result in vertigo, syncope, or postural hypotension.
7.6Digitalis and Calcium Antagonists The concomitant use of beta-adrenergic blocking agents with digitalis and calcium antagonists may have additive effects in prolonging atrioventricular conduction time.
7.7CYP2D6 Inhibitors Potentiated systemic beta-blockade (e.g., decreased heart rate, depression) has been reported during combined treatment with CYP2D6 inhibitors (e.g., quinidine, SSRIs) and timolol.
7.8Clonidine Oral beta-adrenergic blocking agents may exacerbate the rebound hypertension which can follow the withdrawal of clonidine. There have been no reports of exacerbation of rebound hypertension with ophthalmic timolol maleate.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Teratogenic Effects. Developmental toxicity studies with dorzolamide hydrochloride in rabbits at oral doses of ≥2.5 mg/kg/day (37 times the recommended human ophthalmic dose) revealed malformations of the vertebral bodies. These malformations occurred at doses that caused metabolic acidosis with decreased body weight gain in dams and decreased fetal weights.
No treatment-related malformations were seen at 1 mg/kg/day (15 times the recommended human ophthalmic dose). Teratogenicity studies with timolol in mice, rats, and rabbits at oral doses up to 50 mg/kg/day (7,000 times the systemic exposure following the maximum recommended human ophthalmic dose) demonstrated no evidence of fetal malformations. Although delayed fetal ossification was observed at this dose in rats, there were no adverse effects on postnatal development of offspring.
Doses of 1,000 mg/kg/day (142,000 times the systemic exposure following the maximum recommended human ophthalmic dose) were maternotoxic in mice and resulted in an increased number of fetal resorptions. Increased fetal resorptions were also seen in rabbits at doses of 14,000 times the systemic exposure following the maximum recommended human ophthalmic dose, in this case without apparent maternotoxicity. There are no adequate and well-controlled studies in pregnant women.
Dorzolamide hydrochloride and timolol maleate ophthalmic solution should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
8.3Nursing Mothers It is not known whether dorzolamide is excreted in human milk. Timolol maleate has been detected in human milk following oral and ophthalmic drug administration. Because of the potential for serious adverse reactions from dorzolamide hydrochloride and timolol maleate ophthalmic solution in nursing infants, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
8.4Pediatric Use The safety and effectiveness of dorzolamide hydrochloride ophthalmic solution and timolol maleate ophthalmic solution have been established when administered individually in pediatric patients aged 2 years and older. Use of these drug products in these children is supported by evidence from adequate and well-controlled studies in children and adults. Safety and efficacy in pediatric patients below the age of 2 years have not been established.
8.5Geriatric Use No overall differences in safety or effectiveness have been observed between elderly and younger patients.
🤰 Pregnancy ▾
8.1Pregnancy Teratogenic Effects. Developmental toxicity studies with dorzolamide hydrochloride in rabbits at oral doses of ≥2.5 mg/kg/day (37 times the recommended human ophthalmic dose) revealed malformations of the vertebral bodies. These malformations occurred at doses that caused metabolic acidosis with decreased body weight gain in dams and decreased fetal weights.
No treatment-related malformations were seen at 1 mg/kg/day (15 times the recommended human ophthalmic dose). Teratogenicity studies with timolol in mice, rats, and rabbits at oral doses up to 50 mg/kg/day (7,000 times the systemic exposure following the maximum recommended human ophthalmic dose) demonstrated no evidence of fetal malformations. Although delayed fetal ossification was observed at this dose in rats, there were no adverse effects on postnatal development of offspring.
Doses of 1,000 mg/kg/day (142,000 times the systemic exposure following the maximum recommended human ophthalmic dose) were maternotoxic in mice and resulted in an increased number of fetal resorptions. Increased fetal resorptions were also seen in rabbits at doses of 14,000 times the systemic exposure following the maximum recommended human ophthalmic dose, in this case without apparent maternotoxicity. There are no adequate and well-controlled studies in pregnant women.
Dorzolamide hydrochloride and timolol maleate ophthalmic solution should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of dorzolamide hydrochloride ophthalmic solution and timolol maleate ophthalmic solution have been established when administered individually in pediatric patients aged 2 years and older. Use of these drug products in these children is supported by evidence from adequate and well-controlled studies in children and adults. Safety and efficacy in pediatric patients below the age of 2 years have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use No overall differences in safety or effectiveness have been observed between elderly and younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE Symptoms consistent with systemic administration of beta-blockers or carbonic anhydrase inhibitors may occur, including electrolyte imbalance, development of an acidotic state, dizziness, headache, shortness of breath, bradycardia, bronchospasm, cardiac arrest and possible central nervous system effects. Serum electrolyte levels (particularly potassium) and blood pH levels should be monitored [see Adverse Reactions (6) ]. A study of patients with renal failure showed that timolol did not dialyze readily.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Dorzolamide hydrochloride and timolol maleate ophthalmic solution is comprised of two components: dorzolamide hydrochloride and timolol maleate. Each of these two components decreases elevated intraocular pressure, whether or not associated with glaucoma, by reducing aqueous humor secretion. Elevated intraocular pressure is a major risk factor in the pathogenesis of optic nerve damage and glaucomatous visual field loss.
The higher the level of intraocular pressure, the greater the likelihood of glaucomatous field loss and optic nerve damage. Dorzolamide hydrochloride is an inhibitor of human carbonic anhydrase II. Inhibition of carbonic anhydrase in the ciliary processes of the eye decreases aqueous humor secretion, presumably by slowing the formation of bicarbonate ions with subsequent reduction in sodium and fluid transport.
Timolol maleate is a beta 1 and beta 2 (non-selective) adrenergic receptor blocking agent that does not have significant intrinsic sympathomimetic, direct myocardial depressant, or local anesthetic (membrane-stabilizing) activity. The combined effect of these two agents administered as dorzolamide hydrochloride and timolol maleate ophthalmic solution twice daily results in additional intraocular pressure reduction compared to either component administered alone, but the reduction is not as much as when dorzolamide administered three times daily and timolol twice daily are administered concomitantly [see Clinical Studies (14) ] .
12.3Pharmacokinetics Dorzolamide Hydrochloride When topically applied, dorzolamide reaches the systemic circulation. To assess the potential for systemic carbonic anhydrase inhibition following topical administration, drug and metabolite concentrations in RBCs and plasma and carbonic anhydrase inhibition in RBCs were measured. Dorzolamide accumulates in RBCs during chronic dosing as a result of binding to CA-II.
The parent drug forms a single N-desethyl metabolite, which inhibits CA-II less potently than the parent drug but also inhibits CA-I. The metabolite also accumulates in RBCs where it binds primarily to CA-I. Plasma concentrations of dorzolamide and metabolite are generally below the assay limit of quantitation (15nM).
Dorzolamide binds moderately to plasma proteins (approximately 33%). Dorzolamide is primarily excreted unchanged in the urine; the metabolite also is excreted in urine. After dosing is stopped, dorzolamide washes out of RBCs nonlinearly, resulting in a rapid decline of drug concentration initially, followed by a slower elimination phase with a half-life of about four months.
To simulate the systemic exposure after long-term topical ocular administration, dorzolamide was given orally to eight healthy subjects for up to 20 weeks. The oral dose of 2 mg twice daily closely approximates the amount of drug delivered by topical ocular administration of dorzolamide 2% three times daily. Steady state was reached within 8 weeks.
The inhibition of CA-II and total carbonic anhydrase activities was below the degree of inhibition anticipated to be necessary for a pharmacological effect on renal function and respiration in healthy individuals. Timolol Maleate In a study of plasma drug concentrations in six subjects, the systemic exposure to timolol was determined following twice daily topical administration of timolol maleate ophthalmic solution 0.5%. The mean peak plasma concentration following morning dosing was 0.46 ng/mL.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Dorzolamide hydrochloride and timolol maleate ophthalmic solution is comprised of two components: dorzolamide hydrochloride and timolol maleate. Each of these two components decreases elevated intraocular pressure, whether or not associated with glaucoma, by reducing aqueous humor secretion. Elevated intraocular pressure is a major risk factor in the pathogenesis of optic nerve damage and glaucomatous visual field loss.
The higher the level of intraocular pressure, the greater the likelihood of glaucomatous field loss and optic nerve damage. Dorzolamide hydrochloride is an inhibitor of human carbonic anhydrase II. Inhibition of carbonic anhydrase in the ciliary processes of the eye decreases aqueous humor secretion, presumably by slowing the formation of bicarbonate ions with subsequent reduction in sodium and fluid transport.
Timolol maleate is a beta 1 and beta 2 (non-selective) adrenergic receptor blocking agent that does not have significant intrinsic sympathomimetic, direct myocardial depressant, or local anesthetic (membrane-stabilizing) activity. The combined effect of these two agents administered as dorzolamide hydrochloride and timolol maleate ophthalmic solution twice daily results in additional intraocular pressure reduction compared to either component administered alone, but the reduction is not as much as when dorzolamide administered three times daily and timolol twice daily are administered concomitantly [see Clinical Studies (14) ] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Dorzolamide hydrochloride and timolol maleate ophthalmic solution USP, 2% / 0.5% is supplied in a white low-density polyethylene (LDPE) bottle with a white LDPE dropper tip and a blue polypropylene cap as follows: NDC 24208-486-05, 5 mL in a 7.5 mL capacity bottle. NDC 24208-486-10, 10 mL in a 10 mL capacity bottle. Storage: Store at 20°C to 25°C (68°F to 77°F).
Protect from light. After opening, dorzolamide hydrochloride and timolol maleate ophthalmic solution, USP can be used until the expiration date on the bottle.
📋 Description ▾
11 DESCRIPTION Dorzolamide hydrochloride and timolol maleate ophthalmic solution, USP is the combination of a topical carbonic anhydrase inhibitor and a topical beta-adrenergic receptor blocking agent. Dorzolamide hydrochloride, USP is described chemically as: (4S-trans) -4-(ethylamino)-5,6-dihydro-6-methyl- 4H -thieno[2,3- b ]thiopyran-2-sulfonamide 7,7-dioxide monohydrochloride. Dorzolamide hydrochloride, USP is optically active.
The specific rotation is: Its empirical formula is C 10 H 16 N 2 O 4 S 3 •HCl and its structural formula is: Dorzolamide hydrochloride, USP has a molecular weight of 360.90. It is a white to off-white, crystalline powder, which is soluble in water and slightly soluble in methanol and ethanol. Timolol maleate, USP is described chemically as: (-)-1-( tert -butylamino)-3-[(4-morpholino-1,2,5-thiadiazol-3-yl)oxy]-2-propanol maleate (1:1) (salt).
Timolol maleate, USP possesses an asymmetric carbon atom in its structure and is provided as the levo-isomer. The optical rotation of timolol maleate, USP is: Its molecular formula is C 13 H 24 N 4 O 3 S•C 4 H 4 O 4 and its structural formula is: Timolol maleate, USP has a molecular weight of 432.49. It is a white, odorless, crystalline powder which is soluble in water, methanol, and alcohol.
Timolol maleate is stable at room temperature. Dorzolamide hydrochloride and timolol maleate ophthalmic solution is supplied as a sterile, clear, colorless to nearly colorless, isotonic, buffered, slightly viscous, aqueous solution. The pH of the solution is approximately 5.65, and the osmolarity is 242 to 323 mOsM.
Each mL of dorzolamide hydrochloride and timolol maleate ophthalmic solution contains 20 mg dorzolamide (equivalent to 22.26 mg of dorzolamide hydrochloride) and 5 mg timolol (equivalent to 6.83 mg timolol maleate). Inactive ingredients are hydroxyethyl cellulose, mannitol, sodium citrate dihydrate, sodium hydroxide, and water for injection. Benzalkonium chloride 0.0075% is added as a preservative.
SpecificRotation ChemStructure1 ChemStructure2 ChemStructure3
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-Approved patient labeling (Patient Information and Instructions for Use). Potential for Exacerbation of Asthma and COPD Dorzolamide hydrochloride and timolol maleate ophthalmic solution may cause severe worsening of asthma and COPD symptoms including death due to bronchospasm. Advise patients with bronchial asthma, a history of bronchial asthma, or severe chronic obstructive pulmonary disease not to take this product [see Contraindications (4.1) ].
Potential of Cardiovascular Effects Dorzolamide hydrochloride and timolol maleate ophthalmic solution may cause worsening of cardiac symptoms. Advise patients with sinus bradycardia, second or third degree atrioventricular block, or cardiac failure not to take this product [see Contraindications (4.2) ]. Sulfonamide Reactions Dorzolamide hydrochloride and timolol maleate ophthalmic solution contains dorzolamide (which is a sulfonamide) and, although administered topically, is absorbed systemically.
Therefore the same types of adverse reactions that are attributable to sulfonamides may occur with topical administration, including severe skin reactions. Advise patients that if serious or unusual reactions or signs of hypersensitivity occur, they should discontinue the use of the product and seek their physician’s advice [see Warnings and Precautions (5.3) ]. Handling Ophthalmic Solutions Instruct patients that ocular solutions, if handled improperly or if the tip of the dispensing container contacts the eye or surrounding structures, can become contaminated by common bacteria known to cause ocular infections.
Serious damage to the eye and subsequent loss of vision may result from using contaminated solutions [see Warnings and Precautions (5.12) ]. Intercurrent Ocular Conditions Advise patients that if they have ocular surgery or develop an intercurrent ocular condition (e.g., trauma or infection), they should immediately seek their physician’s advice concerning the continued use of the present multidose container. Concomitant Topical Ocular Therapy If more than one topical ophthalmic drug is being used, the drugs should be administered at least five minutes apart.
Contact Lens Use Advise patients that dorzolamide hydrochloride and timolol maleate ophthalmic solution contains benzalkonium chloride which may be absorbed by soft contact lenses. Contact lenses should be removed prior to administration of the solution. Lenses may be reinserted 15 minutes following administration of dorzolamide hydrochloride and timolol maleate ophthalmic solution.
Distributed by: Bausch & Lomb Americas Inc. Bridgewater, NJ 08807 USA Manufactured by: Bausch & Lomb Incorporated Tampa, FL 33637 USA © 2023 Bausch & Lomb Incorporated or its affiliates 9633205 (11" x 5" folded) 9633305 (0.9375" x 5" folded)
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Dorzolamide Hydrochloride When topically applied, dorzolamide reaches the systemic circulation. To assess the potential for systemic carbonic anhydrase inhibition following topical administration, drug and metabolite concentrations in RBCs and plasma and carbonic anhydrase inhibition in RBCs were measured. Dorzolamide accumulates in RBCs during chronic dosing as a result of binding to CA-II.
The parent drug forms a single N-desethyl metabolite, which inhibits CA-II less potently than the parent drug but also inhibits CA-I. The metabolite also accumulates in RBCs where it binds primarily to CA-I. Plasma concentrations of dorzolamide and metabolite are generally below the assay limit of quantitation (15nM).
Dorzolamide binds moderately to plasma proteins (approximately 33%). Dorzolamide is primarily excreted unchanged in the urine; the metabolite also is excreted in urine. After dosing is stopped, dorzolamide washes out of RBCs nonlinearly, resulting in a rapid decline of drug concentration initially, followed by a slower elimination phase with a half-life of about four months.
To simulate the systemic exposure after long-term topical ocular administration, dorzolamide was given orally to eight healthy subjects for up to 20 weeks. The oral dose of 2 mg twice daily closely approximates the amount of drug delivered by topical ocular administration of dorzolamide 2% three times daily. Steady state was reached within 8 weeks.
The inhibition of CA-II and total carbonic anhydrase activities was below the degree of inhibition anticipated to be necessary for a pharmacological effect on renal function and respiration in healthy individuals. Timolol Maleate In a study of plasma drug concentrations in six subjects, the systemic exposure to timolol was determined following twice daily topical administration of timolol maleate ophthalmic solution 0.5%. The mean peak plasma concentration following morning dosing was 0.46 ng/mL.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Clinical studies of 3 to 15 months duration were conducted to compare the IOP-lowering effect over the course of the day of dorzolamide hydrochloride and timolol maleate ophthalmic solution twice daily (dosed morning and bedtime) to individually and concomitantly administered 0.5% timolol twice daily and 2% dorzolamide twice and three times daily. The IOP-lowering effect of dorzolamide hydrochloride and timolol maleate ophthalmic solution twice daily was greater (1 to 3 mmHg) than that of monotherapy with either 2% dorzolamide three times daily or 0.5% timolol twice daily.
The IOP-lowering effect of dorzolamide hydrochloride and timolol maleate ophthalmic solution twice daily was approximately 1 mmHg less than that of concomitant therapy with 2% dorzolamide three times daily and 0.5% timolol twice daily. Open-label extensions of two studies were conducted for up to 12 months. During this period, the IOP-lowering effect of dorzolamide hydrochloride and timolol maleate ophthalmic solution twice daily was consistent during the 12 month follow-up period.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In a two-year study of dorzolamide hydrochloride administered orally to male and female Sprague-Dawley rats, urinary bladder papillomas were seen in male rats in the highest dosage group of 20 mg/kg/day (250 times the recommended human ophthalmic dose). Papillomas were not seen in rats given oral doses equivalent to approximately 12 times the recommended human ophthalmic dose. No treatment-related tumors were seen in a 21-month study in female and male mice given oral doses up to 75 mg/kg/day (~900 times the recommended human ophthalmic dose).
The increased incidence of urinary bladder papillomas seen in the high-dose male rats is a class-effect of carbonic anhydrase inhibitors in rats. Rats are particularly prone to developing papillomas in response to foreign bodies, compounds causing crystalluria, and diverse sodium salts. No changes in bladder urothelium were seen in dogs given oral dorzolamide hydrochloride for one year at 2 mg/kg/day (25 times the recommended human ophthalmic dose) or monkeys dosed topically to the eye at 0.4 mg/kg/day (~5 times the recommended human ophthalmic dose) for one year.
In a two-year study of timolol maleate administered orally to rats, there was a statistically significant increase in the incidence of adrenal pheochromocytomas in male rats administered 300 mg/kg/day (approximately 42,000 times the systemic exposure following the maximum recommended human ophthalmic dose). Similar differences were not observed in rats administered oral doses equivalent to approximately 14,000 times the maximum recommended human ophthalmic dose. In a lifetime oral study of timolol maleate in mice, there were statistically significant increases in the incidence of benign and malignant pulmonary tumors, benign uterine polyps and mammary adenocarcinomas in female mice at 500 mg/kg/day, (approximately 71,000 times the systemic exposure following the maximum recommended human ophthalmic dose), but not at 5 or 50 mg/kg/day (approximately 700 or 7,000, respectively, times the systemic exposure following the maximum recommended human ophthalmic dose).
In a subsequent study in female mice, in which post-mortem examinations were limited to the uterus and the lungs, a statistically significant increase in the incidence of pulmonary tumors was again observed at 500 mg/kg/day. The increased occurrence of mammary adenocarcinomas was associated with elevations in serum prolactin which occurred in female mice administered oral timolol at 500 mg/kg/day, but not at doses of 5 or 50 mg/kg/day. An increased incidence of mammary adenocarcinomas in rodents has been associated with administration of several other therapeutic agents that elevate serum prolactin, but no correlation between serum prolactin levels and mammary tumors has been established in humans.
Furthermore, in adult human female subjects who received oral dosages of up to 60 mg of timolol maleate (the maximum recommended human oral dosage), there were no clinically meaningful changes in serum prolactin. The following tests for mutagenic potential were negative for dorzolamide: (1) in vivo (mouse) cytogenetic assay; (2) in vitro chromosomal aberration assay; (3) alkaline elution assay; (4) V-79 assay; and (5) Ames test. Timolol maleate was devoid of mutagenic potential when tested in vivo (mouse) in the micronucleus test and cytogenetic assay (doses up to 800 mg/kg) and in vitro in a neoplastic cell transformation assay (up to 100 mcg/mL).
In Ames tests the highest concentrations of timolol employed, 5,000 or 10,000 mcg/plate, were associated with statistically significant elevations of revertants observed with tester strain TA100 (in seven replicate assays), but not in the remaining three strains. In the assays with tester strain TA100, no consistent dose response relationship was observed, and the ratio of test to control revertants did not reach 2. A ratio of 2 is usually considered… [Excerpted — this section continues on DailyMed.]
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In a two-year study of dorzolamide hydrochloride administered orally to male and female Sprague-Dawley rats, urinary bladder papillomas were seen in male rats in the highest dosage group of 20 mg/kg/day (250 times the recommended human ophthalmic dose). Papillomas were not seen in rats given oral doses equivalent to approximately 12 times the recommended human ophthalmic dose. No treatment-related tumors were seen in a 21-month study in female and male mice given oral doses up to 75 mg/kg/day (~900 times the recommended human ophthalmic dose).
The increased incidence of urinary bladder papillomas seen in the high-dose male rats is a class-effect of carbonic anhydrase inhibitors in rats. Rats are particularly prone to developing papillomas in response to foreign bodies, compounds causing crystalluria, and diverse sodium salts. No changes in bladder urothelium were seen in dogs given oral dorzolamide hydrochloride for one year at 2 mg/kg/day (25 times the recommended human ophthalmic dose) or monkeys dosed topically to the eye at 0.4 mg/kg/day (~5 times the recommended human ophthalmic dose) for one year.
In a two-year study of timolol maleate administered orally to rats, there was a statistically significant increase in the incidence of adrenal pheochromocytomas in male rats administered 300 mg/kg/day (approximately 42,000 times the systemic exposure following the maximum recommended human ophthalmic dose). Similar differences were not observed in rats administered oral doses equivalent to approximately 14,000 times the maximum recommended human ophthalmic dose. In a lifetime oral study of timolol maleate in mice, there were statistically significant increases in the incidence of benign and malignant pulmonary tumors, benign uterine polyps and mammary adenocarcinomas in female mice at 500 mg/kg/day, (approximately 71,000 times the systemic exposure following the maximum recommended human ophthalmic dose), but not at 5 or 50 mg/kg/day (approximately 700 or 7,000, respectively, times the systemic exposure following the maximum recommended human ophthalmic dose).
In a subsequent study in female mice, in which post-mortem examinations were limited to the uterus and the lungs, a statistically significant increase in the incidence of pulmonary tumors was again observed at 500 mg/kg/day. The increased occurrence of mammary adenocarcinomas was associated with elevations in serum prolactin which occurred in female mice administered oral timolol at 500 mg/kg/day, but not at doses of 5 or 50 mg/kg/day. An increased incidence of mammary adenocarcinomas in rodents has been associated with administration of several other therapeutic agents that elevate serum prolactin, but no correlation between serum prolactin levels and mammary tumors has been established in humans.
Furthermore, in adult human female subjects who received oral dosages of up to 60 mg of timolol maleate (the maximum recommended human oral dosage), there were no clinically meaningful changes in serum prolactin. The following tests for mutagenic potential were negative for dorzolamide: (1) in vivo (mouse) cytogenetic assay; (2) in vitro chromosomal aberration assay; (3) alkaline elution assay; (4) V-79 assay; and (5) Ames test. Timolol maleate was devoid of mutagenic potential when tested in vivo (mouse) in the micronucleus test and cytogenetic assay (doses up to 800 mg/kg) and in vitro in a neoplastic cell transformation assay (up to 100 mcg/mL).
In Ames tests the highest concentrations of timolol employed, 5,000 or 10,000 mcg/plate, were associated with statistically significant elevations of revertants observed with tester strain TA100 (in seven replicate assays), but not in the remaining three strains. In the assays with tester strain TA100, no consistent dose response relationship was observed, and the ratio of test to control revertants did not reach 2. A ratio of 2 is usually considered the criterion for a positi… [Excerpted — this section continues on DailyMed.]
📄 Patient Package Insert ▾
PATIENT INFORMATION Dorzolamide Hydrochloride and Timolol Maleate Ophthalmic Solution, USP (dor-ZOE-la-mide HYE-droe-KLOR-ide and TIM-oh-lol MAL-ee-ate) for topical ophthalmic use What is dorzolamide hydrochloride and timolol maleate ophthalmic solution? Dorzolamide hydrochloride and timolol maleate ophthalmic solution is a prescription eye drop solution that contains two medicines, dorzolamide hydrochloride called an ophthalmic carbonic anhydrase inhibitor and timolol maleate called a beta-blocker. Dorzolamide hydrochloride and timolol maleate ophthalmic solution is used to lower high pressure in the eye in people with open-angle glaucoma or ocular hypertension when a beta-blocking medicine alone does not work to control the eye pressure.
It is not known if dorzolamide hydrochloride and timolol maleate ophthalmic solution is safe and effective in children 2 years of age and younger. Do not use dorzolamide hydrochloride and timolol maleate ophthalmic solution if you: • have or have had asthma. • have chronic obstructive pulmonary disease (COPD) which includes emphysema, chronic bronchitis or both. • have heart problems including a slow heartbeat, heart block, heart failure, or your heart muscle suddenly becomes weak due to a severe heart attack or other problem that caused heart damage (cardiogenic shock). • are allergic to any of the ingredients in dorzolamide hydrochloride and timolol maleate ophthalmic solution.
See the end of this Patient Information leaflet for a complete list of ingredients in dorzolamide hydrochloride and timolol maleate ophthalmic solution. Before using dorzolamide hydrochloride and timolol maleate ophthalmic solution, tell your healthcare provider about all your medical conditions, including if you: • have or have had allergies to sulfa drugs • have a history of anaphylactic reactions to allergens • have atopy (genetic disposition to develop allergic reactions) • have or have had muscle weakness or myasthenia gravis • have diabetes • have thyroid disease • have or have had kidney or liver problems • plan to have any type of surgery • wear contact lenses • are using any other eye drops • have an eye infection or eye trauma • are pregnant or plan to become pregnant.
It is not known if dorzolamide hydrochloride and timolol maleate will harm your unborn baby. Tell your healthcare provider right away if you become pregnant while using dorzolamide hydrochloride and timolol maleate ophthalmic solution. You and your healthcare provider will decide if you should use dorzolamide hydrochloride and timolol maleate ophthalmic solution while you are pregnant. • are breastfeeding or plan to breastfeed.
It is not known if dorzolamide hydrochloride and timolol maleate passes into breastmilk. Talk to your healthcare provider about the best way to feed your baby while using dorzolamide hydrochloride and timolol maleate ophthalmic solution. Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements.
Dorzolamide hydrochloride and timolol maleate ophthalmic solution may affect the way medicines work, and other medicines may affect how dorzolamide hydrochloride and timolol maleate ophthalmic solution works. Do not start a new medicine without first talking to your healthcare provider. Ask your healthcare provider or pharmacist for a list of medicines you are using, if you are not sure.
Know the medicines you take. Keep a list of them and show it to your healthcare provider and pharmacist when you get a new medicine. How should I use dorzolamide hydrochloride and timolol maleate ophthalmic solution? • See the complete Instructions for Use at the end of this Patient Information leaflet for detailed instructions about the right way to use dorzolamide hydrochloride and timolol maleate ophthalmic solution. • Use dorzolamide hydrochloride and timolol maleate ophthalmic solution exactly as your healthcare provider tells you. • Use 1 drop o… [Excerpted — this section continues on DailyMed.]
📖 Instructions for Use ▾
INSTRUCTIONS FOR USE Dorzolamide Hydrochloride and Timolol Maleate Ophthalmic Solution, USP (dor-ZOE-la-mide HYE-droe-KLOR-ide and TIM-oh-lol MAL-ee-ate) for topical ophthalmic use Read this Instructions for Use before you start using dorzolamide hydrochloride and timolol maleate ophthalmic solution and each time you get a refill. There may be new information. This leaflet does not take the place of talking to your healthcare provider about your medical condition or treatment.
Important Information: • Dorzolamide Hydrochloride and Timolol Maleate Ophthalmic Solution is for use in the eye. • If you are using dorzolamide hydrochloride and timolol maleate ophthalmic solution with another eyedrop, wait at least 5 minutes before or after using dorzolamide hydrochloride and timolol maleate ophthalmic solution. • If you wear contact lenses, remove them before using dorzolamide hydrochloride and timolol maleate ophthalmic solution. The lenses can be placed back into your eyes 15 minutes after using dorzolamide hydrochloride and timolol maleate ophthalmic solution. • Do not touch your eye or eyelid with the dropper tip.
Eye medicines, not handled the right way, can become contaminated by bacteria that can cause eye infections. Serious damage to the eye and followed by loss of vision may happen from using contaminated eye medicines. If you think your dorzolamide hydrochloride and timolol maleate ophthalmic solution medicine may be contaminated, or if you develop an eye infection, contact your healthcare provider right away about continuing to use your bottle of dorzolamide hydrochloride and timolol maleate ophthalmic solution. • Wash your hands before each use to make sure you do not infect your eyes while using dorzolamide hydrochloride and timolol maleate ophthalmic solution. • Before using the eyedrops for the first time, be sure the Safety Seal around the cap is not broken.
If the Safety Seal is broken, call your pharmacist to get a new bottle of dorzolamide hydrochloride and timolol maleate ophthalmic solution. Step 1. Tear off the Safety Seal.
Step 2. To open the dorzolamide hydrochloride and timolol maleate ophthalmic solution bottle, unscrew the cap by turning counterclockwise. Step 3.
Tilt your head back. Gently pull your lower eyelid downwards to form a pocket between your eyelid and your eye, look up (See Figure A). Figure A Step 4.
Turn the dorzolamide hydrochloride and timolol maleate ophthalmic solution bottle upside down. Step 5. Place the dropper tip of the dorzolamide hydrochloride and timolol maleate ophthalmic solution bottle close to your eye but be careful not to touch your eye with it.
Gently press the dorzolamide hydrochloride and timolol maleate ophthalmic solution bottle lightly with your thumb or index finger until 1 drop of dorzolamide hydrochloride and timolol maleate ophthalmic solution falls into your eye (See Figure B). Figure B Step 6. Repeat Steps 4 and 5 with the other eye if instructed to do so by your healthcare provider.
Step 7. Replace the cap by turning until it is firmly touching the bottle. Do not overtighten the cap.
Step 8. If you use contact lenses, wait at least 15 minutes before placing them back into your eyes. • The dropper tip is made to give a single drop of dorzolamide hydrochloride and timolol maleate ophthalmic solution. Do not enlarge the hole of the dropper tip. • After you have used all of your doses for dorzolamide hydrochloride and timolol maleate ophthalmic solution, there will be some dorzolamide hydrochloride and timolol maleate ophthalmic solution left in the 5 mL bottle.
The 10 mL bottle contains the exact amount. • There is an extra amount of dorzolamide hydrochloride and timolol maleate ophthalmic solution that has been added to the 5 mL bottle. You will get the full amount of the dorzolamide hydrochloride and timolol maleate ophthalmic solution that your doctor prescribed. • Do not try to remove the extra dorzolamide hydrochloride and timolol maleate ophthalmic solution m… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PACKAGE/LABEL PRINCIPAL DISPLAY PANEL NDC 24208-486-10 Dorzolamide Hydrochloride and Timolol Maleate Ophthalmic Solution, USP 2%/0.5% (Sterile) FOR TOPICAL APPLICATION IN THE EYE Rx only 10 mL BAUSCH + LOMB 9529504 Carton