
Levobunolol Hydrochloride 5 mg/mL Solution/ Drops — NDC 24208-505-10 (Billing 24208-0505-10)
This is a package of Levobunolol Hydrochloride 5 mg/mL Solution/ Drops from Bausch & Lomb Incorporated, marketed since Mar 1994 and currently FDA-listed.
NDC database record
One package, one record: these facts belong to NDC 24208-505-10 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 24208 labeler · 505 product · 10 package
- Package marketed since
- Mar 4, 1994
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 2420850510 6
- FDA record last changed
- Oct 8, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 007858
- GCN: 33310
- GPI-14 (Medi-Span): 86250020102005
- HICL (First Databank): 003459
- AHFS class code: 52:40.08.00
- RxCUI (RxNorm): 1150836
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 8, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the beta-Adrenergic Blocker class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 8, 2026
Clinical
- It lowers pressure inside your eye. Doctors prescribe it for chronic open-angle glaucoma or ocular hypertension. Keeping eye pressure down helps protect your optic nerve and vision...
- It is usually started as one to two drops in the affected eye(s) once a day. Some people with tougher-to-control glaucoma use it twice a day. Follow your prescriber's directions, s...
- It can. Temporary burning or stinging happened in up to 1 in 3 people in studies. Call your doctor if it is bothersome or you notice eyelid redness, swelling or vision changes.
- You should not use it if you have asthma, a history of asthma or severe COPD. It is also not for people with a very slow heart rate, heart block, heart failure or cardiogenic shock...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $3.01 | $30.05 / 10 ml |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 9, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 24208-0505-05 24208-505-05 Main listing | 1 BOTTLE, DROPPER in 1 CARTON / 5 mL in 1 BOTTLE, DROPPER | $2.82 / mL | $14.09 | 1994-03-04 | — | Active |
| 24208-0505-10 You're viewing this | 1 BOTTLE, DROPPER in 1 CARTON / 10 mL in 1 BOTTLE, DROPPER | — | — | 1994-03-04 | — | Active |
| 24208-0505-15 24208-505-15 | 1 BOTTLE, DROPPER in 1 CARTON / 15 mL in 1 BOTTLE, DROPPER | — | — | 1994-03-04 | — | Active |
This pack shows little to no recent Medicaid volume — a different pack size carries most fills. See all packs ↓
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Levobunolol Hydrochloride 5 mg/mL Solution/ Drops?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Levobunolol Hydrochloride 5 mg/mLthis 24208-0505-10 | Bausch | 1 bottle | — | AT | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Levobunolol Ophthalmic inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
0.04 mg / 1 mL
UNII F5UM2KM3W7
Benzalkonium chloride is a chemical compound that works as a preservative and antimicrobial agent in medications. It prevents bacterial and fungal growth in liquid formulations to keep the product safe during storage and use.
-
UNII 7FLD91C86K
Edetate disodium is a chemical compound that binds and removes certain metal ions. In medicines, it acts as a preservative and stabilizer by preventing metals like calcium from interfering with the product's shelf life and consistency.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII 4J9FJ0HL51
Potassium phosphate, monobasic is a salt compound used in medicines as a pH buffer and electrolyte source. It helps stabilize the acidity level of liquid and powdered formulations.
-
14 mg / 1 mL
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 4VON5FNS3C
Sodium metabisulfite is a preservative derived from sulfur compounds. It prevents microbial growth and oxidation in medicines, helping extend shelf life and maintain product stability.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Bausch & Lomb Incorporated labeler code 24208
- Soothe XP light mineral oil and 10 mg/mL; 45 mg/mL Solution/ Drops NDC 24208-490-15
- Soothe glycerin and propylene glycol 6 mg/mL; 6 mg/mL Solution/ Drops NDC 24208-495-28
- Timoptic in Ocudose Timolol Maleate 3.4 mg/mL Solution NDC 24208-498-34
- Timoptic in Ocudose Timolol Maleate 6.8 mg/mL Solution NDC 24208-499-00
- LOTEMAX loteprednol etabonate 5 mg/g Gel NDC 24208-503-07
- Vyzulta latanoprostene bunod .24 mg/mL Solution/ Drops NDC 24208-504-01
- Lotemax SM loteprednol etabonate 3.8 mg/g Gel NDC 24208-507-01
- Loteprednol Etabonate 5 mg/g Gel NDC 24208-508-01
- ZIRGAN ganciclovir 1.5 mg/g Gel NDC 24208-535-15
- LUMIFY Redness Reliever Eye Drops BRIMONIDINE TARTRATE .25 mg/mL Solution/ Drops NDC 24208-537-01
- LUMIFY PRESERVATIVE FREE EYE DROPS brimonidine tartrate .25 mg/mL Solution/ Drops NDC 24208-538-05
- Miochol E acetylcholine chloride Kit NDC 24208-539-20
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Levobunolol hydrochloride ophthalmic solution has been shown to be effective in lowering intraocular pressure and may be used in patients with chronic open-angle glaucoma or ocular hypertension.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The recommended starting dose is one to two drops of levobunolol hydrochloride ophthalmic solution, 0.5% in the affected eye(s) once a day. In patients with more severe or uncontrolled glaucoma, levobunolol hydrochloride ophthalmic solution, 0.5% can be administered twice a day. As with any new medication, careful monitoring of patients is advised.
Dosages above one drop of levobunolol hydrochloride ophthalmic solution, 0.5% twice a day are not generally more effective. If the patient's IOP is not at a satisfactory level on this regimen, concomitant therapy with other ophthalmic IOP-lowering agents can be instituted. Patients should not typically use two or more topical ophthalmic beta-adrenergic blocking agents simultaneously.
⛔ Contraindications ▾
CONTRAINDICATIONS Levobunolol hydrochloride ophthalmic solution is contraindicated in those individuals with bronchial asthma, or with a history of bronchial asthma, or severe chronic obstructive pulmonary disease (see WARNINGS ); sinus bradycardia; second and third degree atrioventricular block; overt cardiac failure (see WARNINGS ); cardiogenic shock; or hypersensitivity to any component of these products.
⚠️ Warnings ▾
WARNINGS As with other topically applied ophthalmic drugs, levobunolol hydrochloride ophthalmic solution may be absorbed systemically. The same adverse reactions found with systemic administration of beta-adrenergic blocking agents may occur with topical administration. For example, severe respiratory reactions and cardiac reactions, including death due to bronchospasm in patients with asthma, and rarely death in association with cardiac failure, have been reported with topical application of beta-adrenergic blocking agents (see CONTRAINDICATIONS ).
Additionally, ophthalmic beta-blockers may impair compensatory tachycardia and increase risk of hypotension. Cardiac Failure Sympathetic stimulation may be essential for support of the circulation in individuals with diminished myocardial contractility, and its inhibition by beta-adrenergic receptor blockade may precipitate more severe failure. In Patients Without a History of Cardiac Failure Continued depression of the myocardium with beta-blocking agents over a period of time can, in some cases, lead to cardiac failure.
At the first sign or symptom of cardiac failure, levobunolol hydrochloride ophthalmic solution should be discontinued (see CONTRAINDICATIONS ). Potentiation of Vascular Insufficiency Levobunolol hydrochloride ophthalmic solution may potentiate syndromes associated with vascular insufficiency (i.e. Raynaud’s phenomenon), and therefore, should be used with caution in these patients.
Obstructive Pulmonary Disease PATIENTS WITH CHRONIC OBSTRUCTIVE PULMONARY DISEASE (e.g., CHRONIC BRONCHITIS, EMPHYSEMA) OF MILD OR MODERATE SEVERITY, BRONCHOSPASTIC DISEASE OR A HISTORY OF BRONCHOSPASTIC DISEASE (OTHER THAN BRONCHIAL ASTHMA OR A HISTORY OF BRONCHIAL ASTHMA, IN WHICH LEVOBUNOLOL HYDROCHLORIDE OPHTHALMIC SOLUTION IS CONTRAINDICATED, SEE CONTRAINDICATIONS ), SHOULD IN GENERAL NOT RECEIVE BETA BLOCKERS, INCLUDING LEVOBUNOLOL HYDROCHLORIDE OPHTHALMIC SOLUTION. However, if levobunolol hydrochloride ophthalmic solution is deemed necessary in such patients, then it should be administered cautiously since it may block bronchodilation produced by endogenous and exogenous catecholamine stimulation of beta 2 receptors.
Major Surgery The necessity or desirability of withdrawal of beta-adrenergic blocking agents prior to major surgery is controversial. Beta-adrenergic receptor blockade impairs the ability of the heart to respond to beta-adrenergically mediated reflex stimuli. This may augment the risk of general anesthesia in surgical procedures.
Some patients receiving beta-adrenergic receptor blocking agents have been subject to protracted severe hypotension during anesthesia. Difficulty in restarting and maintaining the heartbeat has also been reported. For these reasons, in patients undergoing elective surgery, gradual withdrawal of beta-adrenergic blocking agents may be appropriate.
If necessary during surgery, the effects of beta-adrenergic blocking agents may be reversed by sufficient doses of such agonists as isoproterenol, dopamine, dobutamine or levarterenol (see OVERDOSAGE ). Diabetes Mellitus Beta-adrenergic blocking agents should be administered with caution in patients subject to spontaneous hypoglycemia or to diabetic patients (especially those with labile diabetes) who are receiving insulin or oral hypoglycemic agents. Beta-adrenergic blocking agents may mask the signs and symptoms of acute hypoglycemia.
Thyrotoxicosis Beta-adrenergic blocking agents may mask certain clinical signs (e.g., tachycardia) of hyperthyroidism. Patients suspected of developing thyrotoxicosis should be managed carefully to avoid abrupt withdrawal of beta-adrenergic blocking agents which might precipitate a thyroid storm. Choroidal Detachment Choroidal detachment after filtration procedures has been reported with the administration of aqueous suppressant therapy.
These products contain sodium metabisulfite, a sulfite that may cause allergic-type reactions including anaphylactic symptoms and lif… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS In clinical trials the use of levobunolol hydrochloride ophthalmic solution has been associated with transient ocular burning and stinging in up to 1 in 3 patients, and with blepharoconjunctivitis in up to 1 in 20 patients. Decreases in heart rate and blood pressure have been reported (see CONTRAINDICATIONS and WARNINGS ). The following adverse reactions have been reported rarely with the use of levobunolol hydrochloride ophthalmic solution: iridocyclitis, headache, transient ataxia, dizziness, lethargy, urticaria, and pruritus.
Decreased corneal sensitivity has been noted in a small number of patients. Although levobunolol has minimal membrane-stabilizing activity, there remains a possibility of decreased corneal sensitivity after prolonged use. The following additional adverse reactions have been reported either with levobunolol hydrochloride ophthalmic solution or ophthalmic use of other beta-adrenergic receptor blocking agents: BODY AS A WHOLE: Headache, asthenia, chest pain.
CARDIOVASCULAR: Bradycardia, arrhythmia, hypotension, syncope, heart block, cerebral vascular accident, cerebral ischemia, congestive heart failure, palpitation, cardiac arrest. DIGESTIVE: Nausea, diarrhea. PSYCHIATRIC: Depression, confusion, increase in signs and symptoms of myasthenia gravis, paresthesia.
SKIN: Hypersensitivity, including localized and generalized rash, alopecia, Stevens-Johnson Syndrome. RESPIRATORY: Bronchospasm (predominantly in patients with pre-existing bronchospastic disease), respiratory failure, dyspnea, nasal congestion. UROGENITAL: Impotence.
ENDOCRINE: Masked symptoms of hypoglycemia in insulin-dependent diabetics (see WARNINGS ). SPECIAL SENSES: Signs and symptoms of keratitis or eye allergy, blepharoptosis, visual disturbances including refractive changes (due to withdrawal of miotic therapy in some cases), diplopia, ptosis, and foreign body sensation in eye. Other reactions associated with the oral use of non-selective adrenergic receptor blocking agents should be considered potential effects with ophthalmic use of these agents.
To report SUSPECTED ADVERSE REACTIONS, contact Bausch & Lomb Incorporated at 1-800-553-5340 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🤰 Pregnancy ▾
Pregnancy Fetotoxicity (as evidenced by a greater number of resorption sites) has been observed in rabbits when doses of levobunolol hydrochloride equivalent to 200 and 700 times the recommended dose for the treatment of glaucoma were given. No fetotoxic effects have been observed in similar studies with rats at up to 1,800 times the human dose for glaucoma. Teratogenic studies with levobunolol in rats at doses up to 25 mg/kg/day (1,800 times the recommended human dose for glaucoma) showed no evidence of fetal malformations.
There were no adverse effects on postnatal development of offspring. It appears when results from studies using rats and studies with other beta-adrenergic blockers are examined, that the rabbit may be a particularly sensitive species. There are no adequate and well-controlled studies in pregnant women.
Levobunolol hydrochloride ophthalmic solution should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
Geriatric Use No overall differences in safety or effectiveness have been observed between elderly and younger patients.
🆘 Overdosage ▾
OVERDOSAGE No data are available regarding overdosage in humans. Should accidental ocular overdosage occur, flush eye(s) with water or normal saline. If accidentally ingested, efforts to decrease further absorption may be appropriate (gastric lavage).
The most common signs and symptoms to be expected with overdosage with administration of a systemic beta-adrenergic blocking agent are symptomatic bradycardia, hypotension, bronchospasm, and acute cardiac failure. Should these symptoms occur, discontinue levobunolol hydrochloride ophthalmic solution therapy and initiate appropriate supportive therapy. The following supportive measures should be considered: 1.
Symptomatic bradycardia: Use atropine sulfate intravenously in a dosage of 0.25 mg to 2 mg to induce vagal blockade. If bradycardia persists, intravenous isoproterenol hydrochloride should be administered cautiously. In refractory cases the use of a transvenous cardiac pacemaker should be considered.
2. Hypotension: Use sympathomimetic pressor drug therapy, such as dopamine, dobutamine or levarterenol. In refractory cases the use of glucagon hydrochloride may be useful.
3. Bronchospasm: Use isoproterenol hydrochloride. Additional therapy with aminophylline may be considered.
4. Acute cardiac failure: Conventional therapy with digitalis, diuretics and oxygen should be instituted immediately. In refractory cases the use of intravenous aminophylline is suggested.
This may be followed, if necessary, by glucagon hydrochloride which may be useful. 5. Heart block (second or third degree): Use isoproterenol hydrochloride or a transvenous cardiac pacemaker.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Levobunolol hydrochloride is a noncardioselective beta-adrenoceptor blocking agent, equipotent at both beta 1 and beta 2 receptors. Levobunolol hydrochloride is greater than 60 times more potent than its dextro isomer in its beta-blocking activity, yet equipotent in its potential for direct myocardial depression. Accordingly, the levo isomer, levobunolol hydrochloride, is used.
Levobunolol hydrochloride does not have significant local anesthetic (membrane-stabilizing) or intrinsic sympathomimetic activity. Beta-adrenergic receptor blockade reduces cardiac output in both healthy subjects and patients with heart disease. In patients with severe impairment of myocardial function, beta-adrenergic receptor blockade may inhibit the stimulatory effect of the sympathetic nervous system necessary to maintain adequate cardiac function.
Beta-adrenergic receptor blockade in the bronchi and bronchioles results in increased airway resistance from unopposed parasympathetic activity. Such an effect in patients with asthma or other bronchospastic conditions is potentially dangerous. Levobunolol hydrochloride ophthalmic solution, USP has been shown to be an active agent in lowering elevated as well as normal intraocular pressure (IOP) whether or not accompanied by glaucoma.
Elevated IOP presents a major risk factor in glaucomatous field loss. The higher the level of IOP, the greater the likelihood of optic nerve damage and visual field loss. The onset of action with one drop of levobunolol hydrochloride ophthalmic solution can be detected within one hour after treatment, with maximum effect seen between 2 and 6 hours.
A significant decrease in IOP can be maintained for up to 24 hours following a single dose. In controlled clinical studies of approximately two years duration, intraocular pressure was well-controlled in approximately 80% of subjects treated with levobunolol hydrochloride ophthalmic solution 0.5% twice a day. The mean IOP decrease from baseline was between 7 mm Hg and 8 mm Hg.
No significant effects on pupil size, tear production or corneal sensitivity were observed. Levobunolol hydrochloride ophthalmic solution at the concentrations tested, when applied topically, decreased heart rate and blood pressure in some patients. The IOP-lowering effect of levobunolol hydrochloride ophthalmic solution was well maintained over the course of these studies.
In a three-month clinical study, a single daily application of 0.5% levobunolol hydrochloride ophthalmic solution controlled the IOP of 72% of subjects achieving an overall mean decrease in IOP of 7.0 mm Hg. The primary mechanism of the ocular hypotensive action of levobunolol hydrochloride in reducing IOP is most likely a decrease in aqueous humor production. Levobunolol hydrochloride ophthalmic solution reduces IOP with little or no effect on pupil size or accommodation.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Levobunolol hydrochloride ophthalmic solution USP, 0.5% is supplied sterile in a plastic bottle with a controlled drop tip in the following sizes: NDC 24208-505-05 - 5 mL NDC 24208-505-10 - 10 mL NDC 24208-505-15 - 15 mL Storage: Store between 15°C to 25°C (59°F to 77°F). Protect from light. Replace cap immediately after use.
KEEP OUT OF REACH OF CHILDREN. Distributed by: Bausch & Lomb Americas Inc. Bridgewater, NJ 08807 USA Manufactured by: Bausch & Lomb Incorporated Tampa, FL 33637 USA © 2022 Bausch & Lomb Incorporated or its affiliates Revised: October 2022 9117404 (Folded) 9117504 (Flat) Do not
📋 Description ▾
DESCRIPTION Levobunolol hydrochloride ophthalmic solution USP, 0.5% is a noncardioselective beta-adrenoceptor blocking agent for ophthalmic use. Levobunolol hydrochloride is represented by the following structural formula: Mol. Formula C 17 H 25 NO 3 •HCl Mol.
Wt. 327.85 Chemical Name: (–)-5-[3-( tert -Butylamino)-2-hydroxypropoxy]-3,4-dihydro-1(2 H )- naphthalenone hydrochloride. Each mL of 0.5% contains: Active: levobunolol hydrochloride 0.5%; Inactives: polyvinyl alcohol 1.4%, sodium chloride, dibasic sodium phosphate, edetate disodium, sodium metabisulfite, monobasic potassium phosphate, and purified water.
Hydrochloric acid and/or sodium hydroxide may be added to adjust pH (5.5 - 7.5); Preservative: benzalkonium chloride (0.004%). BETAGAN ® (levobunolol hydrochloride ophthalmic solution, USP) s terile
⚠️ Precautions ▾
PRECAUTIONS General Levobunolol hydrochloride ophthalmic solution, USP should be used with caution in patients with known hypersensitivity to other beta-adrenoceptor blocking agents. Use with caution in patients with known diminished pulmonary function. Levobunolol hydrochloride ophthalmic solution should be used with caution in patients who are receiving a beta-adrenergic blocking agent orally, because of the potential for additive effects on systemic beta-blockade or on intraocular pressure.
Patients should not typically use two or more topical ophthalmic beta-adrenergic blocking agents simultaneously. Because of the potential effects of beta-adrenergic blocking agents on blood pressure and pulse rates, these medications must be used cautiously in patients with cerebrovascular insufficiency. Should signs or symptoms develop that suggest reduced cerebral blood flow while using levobunolol hydrochloride ophthalmic solution, alternative therapy should be considered.
In patients with angle-closure glaucoma, the immediate objective of treatment is to reopen the angle. This requires, in most cases, constricting the pupil with a miotic. Levobunolol hydrochloride ophthalmic solution has little or no effect on the pupil.
When levobunolol hydrochloride ophthalmic solution is used to reduce elevated intraocular pressure in angle-closure glaucoma, it should be followed with a miotic and not alone. The preservative in levobunolol hydrochloride ophthalmic solution, benzalkonium chloride, may be absorbed by soft contact lenses. Patients wearing soft (hydrophilic) contact lenses should be instructed to remove contact lenses before administration of the solution and wait at least 15 minutes after instilling levobunolol hydrochloride ophthalmic solution before reinserting soft contact lenses.
Muscle Weakness Beta-adrenergic blockade has been reported to potentiate muscle weakness consistent with certain myasthenic symptoms (e.g., diplopia, ptosis and generalized weakness). Drug Interactions Although levobunolol hydrochloride ophthalmic solution used alone has little or no effect on pupil size, mydriasis resulting from concomitant therapy with levobunolol hydrochloride ophthalmic solution and epinephrine may occur. Close observation of the patient is recommended when a beta-blocker is administered to patients receiving catecholamine-depleting drugs such as reserpine, because of possible additive effects and the production of hypotension and/or marked bradycardia, which may produce vertigo, syncope, or postural hypotension.
Patients receiving beta-adrenergic blocking agents along with either oral or intravenous calcium antagonists should be monitored for possible atrioventricular conduction disturbances, left ventricular failure and hypotension. In patients with impaired cardiac function, simultaneous use should be avoided altogether. The concomitant use of beta-adrenergic blocking agents with digitalis and calcium antagonists may have additive effects on prolonging atrioventricular conduction time.
Phenothiazine-related compounds and beta-adrenergic blocking agents may have additive hypotensive effects due to the inhibition of each other’s metabolism. Risk of Anaphylactic Reaction While taking beta-blockers, patients with a history of severe anaphylactic reactions to a variety of allergens may be more reactive to repeated challenge, either accidental, diagnostic, or therapeutic. Such patients may be unresponsive to the usual doses of epinephrine used to treat allergic reactions.
Carcinogenesis, Mutagenesis, Impairment of Fertility In a lifetime oral study in mice, there were statistically significant (p≤0.05) increases in the incidence of benign leiomyomas in female mice at 200 mg/kg/day (14,000 times the recommended human dose for glaucoma), but not at 12 or 50 mg/kg/day (850 and 3,500 times the human dose). In a two year oral study of levobunolol hydrochloride in rats, there was a statistically significant (p≤0.05) increase in the incidence… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers It is not known whether this drug is excreted in human milk. Systemic beta-blockers and topical timolol maleate are known to be excreted in human milk. Caution should be exercised when levobunolol hydrochloride ophthalmic solution is administered to a nursing woman.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility In a lifetime oral study in mice, there were statistically significant (p≤0.05) increases in the incidence of benign leiomyomas in female mice at 200 mg/kg/day (14,000 times the recommended human dose for glaucoma), but not at 12 or 50 mg/kg/day (850 and 3,500 times the human dose). In a two year oral study of levobunolol hydrochloride in rats, there was a statistically significant (p≤0.05) increase in the incidence of benign hepatomas in male rats administered 12,800 times the recommended human dose for glaucoma.
Similar differences were not observed in rats administered oral doses equivalent to 350 times to 2,000 times the recommended human dose for glaucoma. Levobunolol did not show evidence of mutagenic activity in a battery of microbiological and mammalian in vitro and in vivo assays. Reproduction and fertility studies in rats showed no adverse effect on male or female fertility at doses up to 1,800 times the recommended human dose for glaucoma.
📄 Package Label / Principal Display Panel ▾
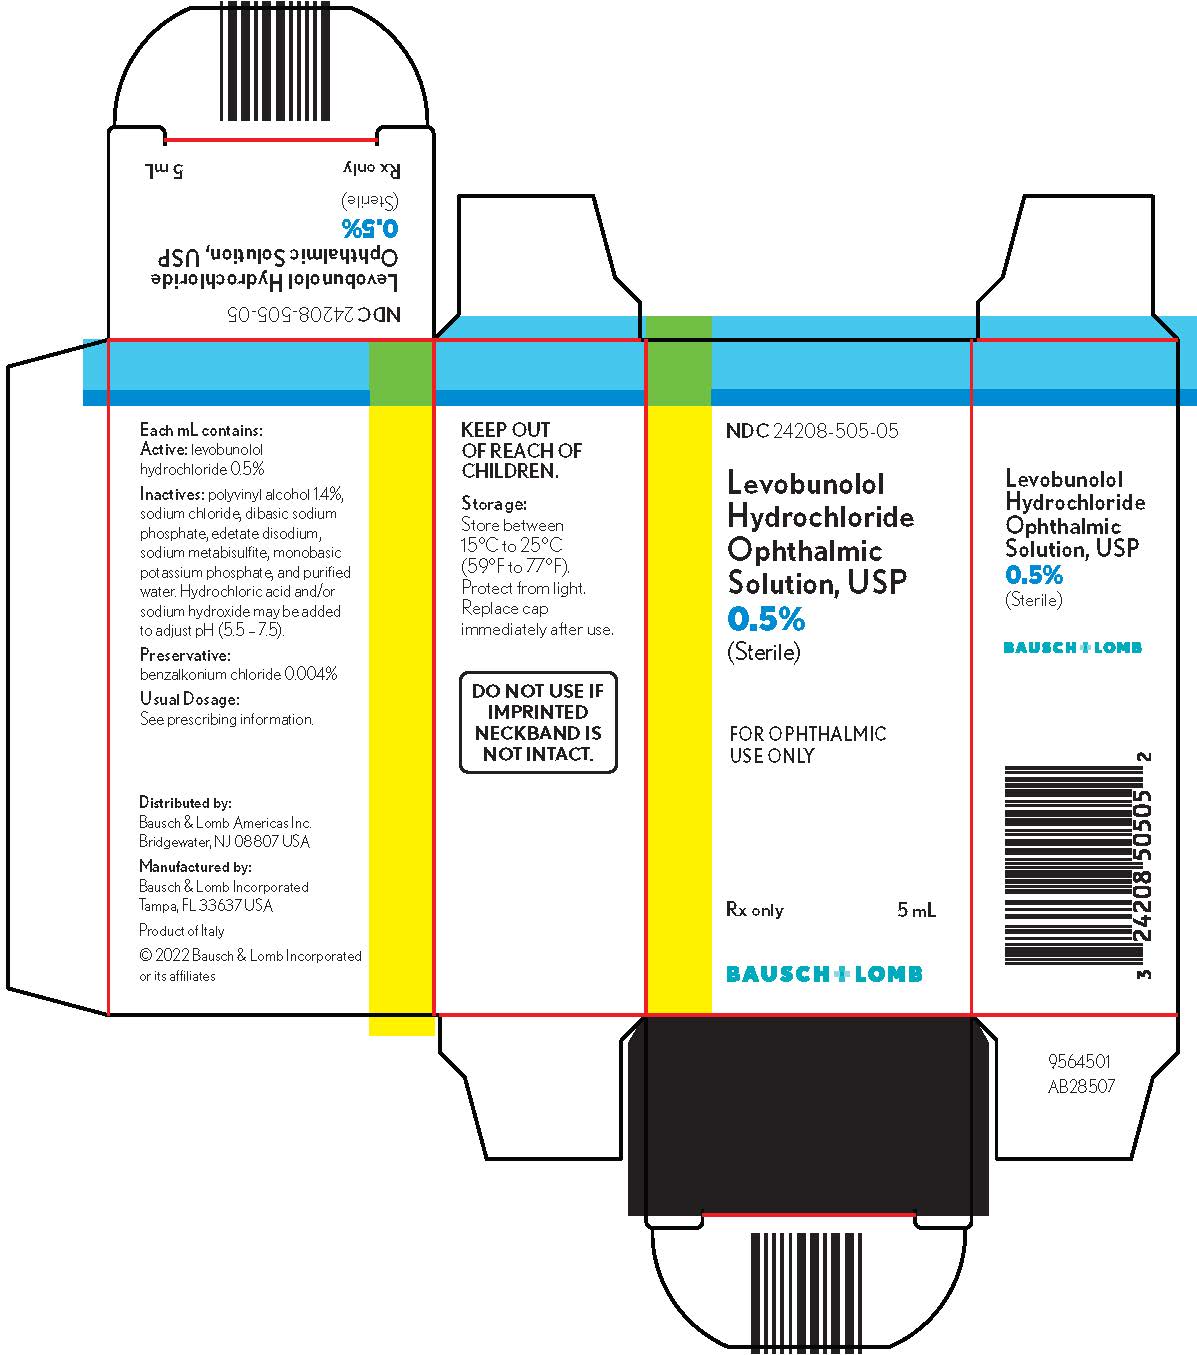
PACKAGE/LABEL PRINCIPAL DISPLAY PANEL NDC 24208-505-05 Levobunolol Hydrochloride Ophthalmic Solution, USP 0.5% (Sterile) FOR OPHTHALMIC USE ONLY. Rx only 5 mL BAUSCH + LOMB 9564502 AB28507 CARTON
Medicaid utilization by pack size
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |