
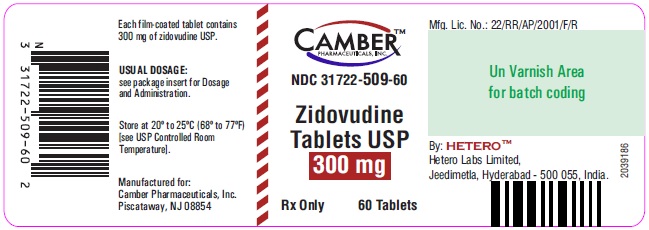
Zidovudine 300 mg Tablet, 720-count — NDC 31722-509-60 (Billing 31722-0509-60)
This is a package of 720 tablets of Zidovudine 300 mg Tablet from Camber Pharmaceuticals, Inc., marketed since Apr 2008 and currently FDA-listed; retail pharmacies pay about $0.4638 per tablet (NADAC). It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 026550
- GCN: 44533
- GPI-14 (Medi-Span): 12108085000330
- HICL (First Databank): 004185
- AHFS class code: 08:18.08.20
- RxCUI (RxNorm): 199663
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Human Immunodeficiency Virus Nucleoside Analog Reverse Transcriptase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Zidovudine is used to treat human immunodeficiency virus (HIV) infection. Zidovudine is given to HIV-positive pregnant women to reduce the chance of passing the infection to the baby. Zidovudine is in a class of medications called nucleoside reverse transcriptase inhibitors (NRTIs). It works by decreasing the amount of HIV in the blood. Although zidovudine does not cure HIV, it may decrease your chance of developing acquired immunodeficiency syndrome (AIDS) and HIV-related illnesses. Taking these medications along and making other life-style changes may decrease the risk of giving the HIV viru...
Read the full MedlinePlus article ↗- It treats HIV-1 infection and is always used with other HIV medicines. It is also used to help prevent HIV from passing from a pregnant woman to her baby.
- Most people take it by mouth twice a day, with or without food. Take it exactly as your prescriber directs. Children's doses are based on weight, and an oral solution is available...
- Headache, feeling unwell, nausea, poor appetite and vomiting are the most common ones. Tell your doctor if they bother you or don't ease up.
- Zidovudine can lower red and white blood cells, sometimes seriously. Regular blood counts catch this early, and your doctor may pause the medicine if needed.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Zidovudine — tap one for details:
Zidovudine may be associated with lower levels of 6 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.464 | $333.94 / 720 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.6481 | $466.63 / 720 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.7481 | $538.63 / 720 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 31722-0509-60 You're viewing this Main listing | 12 BOTTLE in 1 CASE / 60 TABLET in 1 BOTTLE | 2008-04-25 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Zidovudine 300 mgthis 31722-0509-60 | Camber | 720 tablets | $0.464 | AB | Availability likely | — |
| Zidovudine 300 mg 65862-0024-10 | Aurobindo | 10 tablets | — | AB | FDA listed | — |
| Zidovudine 300 mg 67046-1613-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
BOXED WARNING WARNING: RISK OF HEMATOLOGICAL TOXICITY, MYOPATHY, LACTIC ACIDOSIS AND SEVERE HEPATOMEGALY WITH STEATOSIS Zidovudine tablets have been associated with hematologic toxicity including neutropenia and severe anemia, particularly in patients with advanced HIV-1 disease [see Warnings and Precautions ( 5.1 )]. Prolonged use of zidovudine has been associated with symptomatic myopathy [see Warnings and Precautions ( 5.3 )]. Lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported with the use of nucleoside analogues alone or in combination, including zidovudine and other antiretrovirals.
Suspend treatment if clinical or laboratory findings suggestive of lactic acidosis or pronounced hepatotoxicity occur [see Warnings and Precautions ( 5.4 )]. WARNING: RISK OF HEMATOLOGICAL TOXICITY, MYOPATHY, LACTIC ACIDOSIS AND SEVERE HEPATOMEGALY WITH STEATOSIS See full prescribing information for complete boxed warning. • Hematologic toxicity including neutropenia and severe anemia have been associated with the use of zidovudine. ( 5.1 ) • Symptomatic myopathy associated with prolonged use of zidovudine.
( 5.3 ) • Lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported with the use of nucleoside analogues including zidovudine. Suspend treatment if clinical or laboratory findings suggestive of lactic acidosis or pronounced hepatotoxicity occur. ( 5.4 )
🎯 Indications and Usage ▾
1 INDICATIONS & USAGE Zidovudine tablets are a nucleoside analogue reverse transcriptase inhibitor indicated for: •Treatment of Human Immunodeficiency Virus (HIV-1) infection in combination with other antiretroviral agents. ( 1.1 ) • Prevention of maternal-fetal HIV-1 transmission. ( 1.2 )
1.1Treatment of HIV-1 Zidovudine tablets, a nucleoside reverse transcriptase inhibitor, are indicated in combination with other antiretroviral agents for the treatment of HIV-1 infection.
1.2Prevention of Maternal-Fetal HIV-1 Transmission Zidovudine tablets are indicated for the prevention of maternal-fetal HIV-1 transmission [see Dosage and Administration ( 2.3 )]. The indication is based on a dosing regimen that included 3 components: 1. antepartum therapy of HIV-1-infected mothers 2. intrapartum therapy of HIV-1-infected mothers 3. post-partum therapy of HIV-1-exposed neonate Points to consider prior to initiating zidovudine in pregnant women for the prevention of maternal-fetal HIV-1 transmission include: • In most cases, zidovudine for prevention of maternal-fetal HIV-1 transmission should be given in combination with other antiretroviral drugs. • Prevention of HIV-1 transmission in women who have received zidovudine for a prolonged period before pregnancy has not been evaluated. • Because the fetus is most susceptible to the potential teratogenic effects of drugs during the first 10 weeks of gestation and the risks of therapy with zidovudine during that period are not fully known, women in the first trimester of pregnancy who do not require immediate initiation of antiretroviral therapy for their own health may consider delaying use; this indication is based on use after 14 weeks' gestation.
⏱️ Dosage and Administration ▾
2 DOSAGE & ADMINISTRATION • Treatment of HIV-1 infection: Adults: Recommended oral dosage is 300 mg twice a day with other antiretroviral agents. ( 2.1 ) Pediatric patients (aged 4 weeks to less than 18 years): Dosage should be calculated based on body weight not to exceed adult dose. ( 2.2 ) • Prevention of maternal-fetal HIV-1 transmission: Specific dosage instructions for mother and infant.
( 2.3 ) • Patients with severe anemia and/or neutropenia: Dosage interruption may be necessary. ( 2.4 ) • Renal impairment: Recommended oral dosage in hemodialysis or peritoneal dialysis or in patients with creatinine clearance (CrCl) less than mL per minute is 100 mg every 6 to 8 hours. ( 2.5 )
2.1Adults - Treatment of HIV-1 Infection Oral Dosing The recommended oral dose of zidovudine is 300 mg twice daily in combination with other antiretroviral agents.
2.2Pediatric Patients (Aged 4 Weeks to Less than 18 Years) Healthcare professionals should pay special attention to accurate calculation of the dose of zidovudine, transcription of the medication order, dispensing information, and dosing instructions to minimize risk for medication dosing errors. Prescribers should calculate the appropriate dose of zidovudine for each child based on body weight (kg) and should not exceed the recommended adult dose. Before prescribing zidovudine tablets, children should be assessed for the ability to swallow tablets.
If a child is unable to reliably swallow a zidovudine tablet, the zidovudine syrup formulation should be prescribed. The recommended oral dosage in pediatric patients aged 4 weeks to less than 18 years and weighing greater than or equal to 4 kg is provided in Table 1. Zidovudine Syrup should be used to provide accurate dosage when tablets are not appropriate.
Table 1. Recommended Pediatric Oral Dosage of Zidovudine Body Weight (kg) Total Daily Dose Dosage Regimen and Dose Twice Daily Three Times Daily 4 to <9 24 mg/kg/day 12 mg/kg 8 mg/kg ≥9 to <30 18 mg/kg/day 9 mg/kg 6 mg/kg ≥30 600 mg/day 300 mg 200 mg Alternatively, dosing for zidovudine can be based on body surface area (BSA) for each child. The recommended oral dose of zidovudine is 480 mg per m 2 per day in divided doses (240 mg per m2 twice daily or 160 mg per m 2 three times daily).
In some cases the dose calculated by mg per kg will not be the same as that calculated by BSA.
2.3Prevention of Maternal-Fetal HIV-1 Transmission The recommended dosage regimen for administration to pregnant women (greater than 14 weeks of pregnancy) and their neonates is: Maternal Dosing 100 mg orally 5 times per day until the start of labor [see Clinical Studies ( 14.3 )]. During labor and delivery, intravenous zidovudine should be administered at 2 mg per kg (total body weight) over 1 hour followed by a continuous intravenous infusion of 1 mg per kg per hour (total body weight) until clamping of the umbilical cord.
Neonatal Dosing Start neonatal dosing within 12 hours after birth and continue through 6 weeks of age. Neonates unable to receive oral dosing may be administered zidovudine intravenously. See Table 2 for dosing recommendations.
Table 2. Recommended Neonatal Dosages of Zidovudine Route Total Daily Dose Dose and Dosage Regimen Oral 8 mg/kg/day 2 mg/kg every 6 hours Intravenous 6 mg/kg/day 1.5 mg/kg infused over 30 minutes, every 6 hours Use an appropriate-sized syringe with 0.1-mL graduation to ensure accurate dosing of the syrup formulation in neonates.
2.4Patients with Severe Anemia and/or Neutropenia Significant anemia (hemoglobin less than 7.5 g per dL or reduction greater than 25% of baseline) and/or significant neutropenia (granulocyte count less than 750 cells per mm 3 or reduction greater than 50% from baseline) may require a dose interruption until evidence of marrow recovery is observed [see Warnings and Precautions ( 5.1 )]. In patients who develop significant anemia, dose interruption does not necessarily eliminate the need for transfusion. If marrow recovery occurs following… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS & STRENGTHS Zidovudine Tablets USP, 300 mg are white to off white colored, biconvex, round film coated tablets debossed with 'H' on one side and '1' on other side. Tablets: 300 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Zidovudine tablets are contraindicated in patients who have had a potentially life-threatening hypersensitivity reaction (e.g., anaphylaxis, Stevens-Johnson syndrome) to any of the components of the formulations. Hypersensitivity to zidovudine or any of the components (e.g., anaphylaxis, Stevens-Johnson syndrome). ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • See boxed warning for information about the following: hematologic toxicity, myopathy, and lactic acidosis and severe hepatomegaly ( 5.1 , 5.3 , 5.4 ) • Exacerbation of anemia has been reported in HIV-1/HCV co-infected patients receiving ribavirin and zidovudine. Coadministration of ribavirin and zidovudine is not advised. ( 5.5 ) • Hepatic decompensation, (some fatal), has occurred in HIV-1/HCV co-infected patients receiving combination antiretroviral therapy and interferon alfa with/without ribavirin.
Discontinue zidovudine as medically appropriate and consider dose reduction or discontinuation of interferon alfa, ribavirin, or both. ( 5.5 ) • Immune reconstitution syndrome ( 5.6 ) and lipoatrophy ( 5.7 ) have been reported in patients treated with combination antiretroviral therapy.
5.1Hematologic Toxicity/Bone Marrow Suppression Zidovudine should be used with caution in patients who have bone marrow compromise evidenced by granulocyte count less than 1,000 cells per mm 3 or hemoglobin less than 9.5 g per dL. Hematologic toxicities appear to be related to pretreatment bone marrow reserve and to dose and duration of therapy. In patients with advanced symptomatic HIV-1 disease, anemia and neutropenia were the most significant adverse events observed.
In patients who experience hematologic toxicity, a reduction in hemoglobin may occur as early as 2 to 4 weeks, and neutropenia usually occurs after 6 to 8 weeks. There have been reports of pancytopenia associated with the use of zidovudine, which was reversible in most instances after discontinuance of the drug. However, significant anemia, in many cases requiring dose adjustment, discontinuation of zidovudine, and/or blood transfusions, has occurred during treatment with zidovudine alone or in combination with other antiretrovirals.
Frequent blood counts are strongly recommended to detect severe anemia or neutropenia in patients with poor bone marrow reserve, particularly in patients with advanced HIV-1 disease who are treated with zidovudine. For HIV-1-infected individuals and patients with asymptomatic or early HIV-1 disease, periodic blood counts are recommended. If anemia or neutropenia develops, dosage interruption may be needed [see Dosage and Administration ( 2.4 )].
5.3Myopathy Myopathy and myositis with pathological changes, similar to that produced by HIV-1 disease, have been associated with prolonged use of zidovudine.
5.4Lactic Acidosis and Severe Hepatomegaly with Steatosis Lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported with the use of nucleoside analogues, including zidovudine. A majority of these cases have been in women. Female sex and obesity may be risk factors for the development of lactic acidosis and severe hepatomegaly with steatosis in patients treated with antiretroviral nucleoside analogues.
Treatment with zidovudine should be suspended in any patient who develops clinical or laboratory findings suggestive of lactic acidosis or pronounced hepatotoxicity, which may include hepatomegaly and steatosis even in the absence of marked transaminase elevations.
5.5Use with Interferon- and Ribavirin-Based Regimens in HIV-1/HCV Co-infected Patients In vitro studies have shown ribavirin can reduce the phosphorylation of pyrimidine nucleoside analogues such as zidovudine. Although no evidence of a pharmacokinetic or pharmacodynamic interaction (e.g., loss of HIV-1/HCV virologic suppression) was seen when ribavirin was coadministered with zidovudine in HIV-1/HCV co-infected subjects [see Clinical Pharmacology ( 12.3 )], exacerbation of anemia due to ribavirin has been reported when zidovudine is part of the HIV regimen.
Coadministration of ribavirin and zidovudine is not advised. Consideration should be given to replacing zidovudine in established combination HIV-1/HCV therapy, especially in patients with a known history of zidovudine-induced anemia. Hepatic decompensation (some fatal)… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the labeling: • Hematologic toxicity, including neutropenia and anemia [see Boxed Warning, Warnings and Precautions ( 5.1 )]. • Symptomatic myopathy [see Boxed Warning, Warnings and Precautions ( 5.3 )]. • Lactic acidosis and severe hepatomegaly with steatosis [see Boxed Warning, Warnings and Precautions ( 5.4 )]. • Hepatic decompensation in patients co-infected with HIV-1 and hepatitis C [see Warnings and Precautions ( 5.5 )].
The following adverse reactions are discussed in greater detail in other sections of the labeling: • Hematologic toxicity, including neutropenia and anemia [see Boxed Warning, Warnings and Precautions ( 5.1 )]. • Symptomatic myopathy [see Boxed Warning, Warnings and Precautions ( 5.3 )]. • Lactic acidosis and severe hepatomegaly with steatosis [see Boxed Warning, Warnings and Precautions ( 5.4 )]. • Hepatic decompensation in patients co-infected with HIV-1 and hepatitis C [see Warnings and Precautions ( 5.5 )]. To report SUSPECTED ADVERSE REACTIONS, contact Hetero Labs Limited at 1-866-495-1995 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adults The frequency and severity of adverse reactions associated with the use of zidovudine are greater in patients with more advanced infection at the time of initiation of therapy. Table 3 summarizes adverse reactions reported at a statistically significant greater incidence for subjects receiving oral zidovudine in a monotherapy trial.
Table 3. Percentage (%) of Subjects with Adverse Reactions (Greater than or Equal to 5% Frequency) in Asymptomatic HIV-1 Infection (ACTG 019) Adverse Reaction Zidovudine 500 mg/day (n = 453) Placebo (n = 428) Body as a whole Asthenia Headache Malaise Gastrointestinal Anorexia Constipation Nausea Vomiting 9% a 63% 53% 20% 6% a 51% 17% 6% 53% 45% 11% 4% 30% 10% a Not statistically significant versus placebo. In addition to the adverse reactions listed in Table 3, adverse reactions observed at an incidence of greater than or equal to 5% in any treatment arm in clinical trials (NUCA3001, NUCA3002, NUCB3001, and NUCB3002) were abdominal cramps, abdominal pain, arthralgia, chills, dyspepsia, fatigue, insomnia, musculoskeletal pain, myalgia, and neuropathy.
Additionally, in these trials hyperbilirubinemia was reported at an incidence of less than or equal to 0.8%. Selected laboratory abnormalities observed during a clinical trial of monotherapy with oral zidovudine are shown in Table 4. Table 4.
Frequencies of Selected (Grade 3/4) Laboratory Abnormalities in Subjects with Asymptomatic HIV-1 Infection (ACTG 019) Test (Abnormal Level) Zidovudine 500 mg/day (n = 453) [ Placebo (n = 428) Anemia (Hgb <8 g/dL) 1% <1% Granulocytopenia (<750 cells/mm 3 ) 2% 2% Thrombocytopenia (platelets <50,000/mm 3 ) 0% <1% ALT (>5 x ULN) 3% 3% AST (>5 x ULN) 1% 2% ULN = Upper limit of normal. Pediatrics The clinical adverse reactions reported among adult recipients of zidovudine may also occur in pediatric patients. Trial ACTG 300: Selected clinical adverse reactions and physical findings with a greater than or equal to 5% frequency during therapy with EPIVIR (lamivudine) oral suspension 4 mg per kg twice daily plus zidovudine 160 mg per m 2 3 times daily compared with didanosine in therapy-naive (less than or equal to 56 days of antiretroviral therapy) pediatric subjects are listed in Table 5.
Table 5. Selected Clinical Adverse Reactions and Physical Findings (Greater than or Equal to 5% Frequency) in Pediatric Subjects in Trial ACTG 300 Adverse Reaction EPIVIR plus Zidovudine (n = 236) Didanosine (n = 235) Body as a whole Fever 25% 32% Digestive Hepatomegaly 1… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Avoid use with stavudine. ( 7.1 ) • Avoid use with doxorubicin. ( 7.2 ) • Bone marrow suppressive/cytotoxic agents: May increase the hematologic toxicity of zidovudine. ( 7.3 )
7.1Antiretroviral Agents Stavudine Concomitant use of zidovudine with stavudine should be avoided since an antagonistic relationship has been demonstrated in vitro. Nucleoside Analogues Affecting DNA Replication Some nucleoside analogues affecting DNA replication, such as ribavirin, antagonize the in vitro antiviral activity of zidovudine against HIV-1; concomitant use of such drugs should be avoided.
7.2Doxorubicin Concomitant use of zidovudine with doxorubicin should be avoided since an antagonistic relationship has been demonstrated in vitro.
7.3Hematologic/Bone Marrow Suppressive/Cytotoxic Coadministration of ganciclovir, interferon alfa, ribavirin, and other bone marrow suppressive or cytotoxic agents may increase the hematologic toxicity of zidovudine.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Lactation: Women infected with HIV should be instructed not to breastfeed due to potential for HIV transmission. ( 8.2 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to zidovudine during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Available data from the APR show no difference in the overall risk of birth defects for zidovudine compared with the background rate for birth defects of 2.7% in the Metropolitan Atlanta Congenital Defects Program (MACDP) reference population (see Data).
The APR uses the MACDP as the U.S. reference population for birth defects in the general population. The MACDP evaluates women and infants from a limited geographic area and does not include outcomes for births that occurred at less than 20 weeks' gestation. The rate of miscarriage is not reported in the APR.
The estimated background rate of miscarriage in clinically recognized pregnancies in the U.S. general population is 15% to 20%. The background risk for major birth defects and miscarriage for the indicated population is unknown. Hyperlactatemia, which may be due to mitochondrial dysfunction, has been reported in infants with in utero exposure to zidovudine-containing products.
These events were transient and asymptomatic in most cases. There have been few reports of developmental delay, seizures, and other neurological disease. However, a causal relationship between these events and exposure to zidovudine-containing products in utero or peri-partum has not been established (see Data).
In an animal reproduction study, administration of oral zidovudine to female rats prior to mating and throughout gestation resulted in embryotoxicity at doses that produced systemic exposure (AUC) approximately 33 times higher than exposure at the recommended clinical dose. However, no embryotoxicity was observed after oral administration of zidovudine to pregnant rats during organogenesis at doses that produced systemic exposure (AUC) approximately 117 times higher than exposures at the recommended clinical dose. Administration of oral zidovudine to pregnant rabbits during organogenesis resulted in embryotoxicity at doses that produced systemic exposure (AUC) approximately 108 times higher than exposure at the recommended clinical dose.
However, no embryotoxicity was observed at doses that produced systemic exposure (AUC) approximately 23 times higher than exposures at the recommended clinical dose (see Data). Data Human Data: Based on prospective reports to the APR of over 13,000 exposures to zidovudine during pregnancy resulting in live births (including over 4,000 exposed in the first trimester), there was no difference between the overall risk of birth defects for zidovudine compared with the background birth defect rate of 2.7% in a U.S. reference population of the MACDP.
The prevalence of birth defects in live births was 3.2% (95% CI: 2.7% to 3.8%) following first trimester exposure to zidovudine-containing regimens and 2.8% (95% CI: 2.5% to 3.2%) following second/third trimester exposure to zidovudine-containing regimens. A randomized, double-blind, placebo-controlled trial was conducted in HIV-1-infected pregnant women to determine the utility of zidovudine for the prevention of maternal-fetal HIV-1-transmission [see Clinical Studies ( 14.3 )]. Zidovudine treatment during pregnancy reduced the rate of maternal-fetal HIV-1 transmission from 24.9% for infants born to placebo-treated mothers to 7.8% for infants born to mothers treated with zidovudine.
There were no differences in pregnancy-related adverse events between the treatment groups. Of the 363 neonates that were evaluated, congenital abnormalities occurred with similar frequency between neonates born to mothers who received zidovudine and neonates born to mothers who received… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to zidovudine during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Available data from the APR show no difference in the overall risk of birth defects for zidovudine compared with the background rate for birth defects of 2.7% in the Metropolitan Atlanta Congenital Defects Program (MACDP) reference population (see Data).
The APR uses the MACDP as the U.S. reference population for birth defects in the general population. The MACDP evaluates women and infants from a limited geographic area and does not include outcomes for births that occurred at less than 20 weeks' gestation. The rate of miscarriage is not reported in the APR.
The estimated background rate of miscarriage in clinically recognized pregnancies in the U.S. general population is 15% to 20%. The background risk for major birth defects and miscarriage for the indicated population is unknown. Hyperlactatemia, which may be due to mitochondrial dysfunction, has been reported in infants with in utero exposure to zidovudine-containing products.
These events were transient and asymptomatic in most cases. There have been few reports of developmental delay, seizures, and other neurological disease. However, a causal relationship between these events and exposure to zidovudine-containing products in utero or peri-partum has not been established (see Data).
In an animal reproduction study, administration of oral zidovudine to female rats prior to mating and throughout gestation resulted in embryotoxicity at doses that produced systemic exposure (AUC) approximately 33 times higher than exposure at the recommended clinical dose. However, no embryotoxicity was observed after oral administration of zidovudine to pregnant rats during organogenesis at doses that produced systemic exposure (AUC) approximately 117 times higher than exposures at the recommended clinical dose. Administration of oral zidovudine to pregnant rabbits during organogenesis resulted in embryotoxicity at doses that produced systemic exposure (AUC) approximately 108 times higher than exposure at the recommended clinical dose.
However, no embryotoxicity was observed at doses that produced systemic exposure (AUC) approximately 23 times higher than exposures at the recommended clinical dose (see Data). Data Human Data: Based on prospective reports to the APR of over 13,000 exposures to zidovudine during pregnancy resulting in live births (including over 4,000 exposed in the first trimester), there was no difference between the overall risk of birth defects for zidovudine compared with the background birth defect rate of 2.7% in a U.S. reference population of the MACDP.
The prevalence of birth defects in live births was 3.2% (95% CI: 2.7% to 3.8%) following first trimester exposure to zidovudine-containing regimens and 2.8% (95% CI: 2.5% to 3.2%) following second/third trimester exposure to zidovudine-containing regimens. A randomized, double-blind, placebo-controlled trial was conducted in HIV-1-infected pregnant women to determine the utility of zidovudine for the prevention of maternal-fetal HIV-1-transmission [see Clinical Studies ( 14.3 )]. Zidovudine treatment during pregnancy reduced the rate of maternal-fetal HIV-1 transmission from 24.9% for infants born to placebo-treated mothers to 7.8% for infants born to mothers treated with zidovudine.
There were no differences in pregnancy-related adverse events between the treatment groups. Of the 363 neonates that were evaluated, congenital abnormalities occurred with similar frequency between neonates born to mothers who received zidovudine and neonates born to mothers who received placebo. The observed abnormalities included problems in embryogenesis (prior to 14 weeks) or were recognized on ultrasound before or immediately after… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use Zidovudine has been studied in HIV-1-infected pediatric subjects aged at least 6 weeks who had HIV-1-related symptoms or who were asymptomatic with abnormal laboratory values indicating significant HIV-1-related immunosuppression. Zidovudine has also been studied in neonates perinatally exposed to HIV-1 [see Dosage and Administration ( 2.2 ), Adverse Reactions ( 6.1 ), Clinical Pharmacology ( 12.3 ), Clinical Studies ( 14.2 , 14.3 )].
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of zidovudine did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Acute overdoses of zidovudine have been reported in pediatric patients and adults. These involved exposures up to 50 grams. No specific symptoms or signs have been identified following acute overdosage with zidovudine apart from those listed as adverse events such as fatigue, headache, vomiting, and occasional reports of hematological disturbances.
Patients recovered without permanent sequelae. Hemodialysis and peritoneal dialysis appear to have a negligible effect on the removal of zidovudine while elimination of its primary metabolite, 3'- azido-3'-deoxy-5'-O-β-D-glucopyranuronosylthymidine (GZDV), is enhanced. If overdose occurs, the patient should be monitored for evidence of toxicity and given standard supportive treatment as required.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Zidovudine is an antiretroviral agent [see Microbiology ( 12.4 )].
12.3Pharmacokinetics Absorption and Bioavailability In adults, following oral administration, zidovudine is rapidly absorbed and extensively distributed, with peak serum concentrations occurring within 0.5 to 1.5 hours. The AUC was equivalent when zidovudine was administered as zidovudine tablets or syrup compared with zidovudine capsules. The pharmacokinetic properties of zidovudine in fasting adult subjects are summarized in Table 7.
Table 7. Zidovudine Pharmacokinetic Parameters in Adult Subjects Parameter Mean ± SD (except where noted) Oral bioavailability (%) 64 ± 10 (n = 5) Apparent volume of distribution (L/kg) 1.6 ± 0.6 (n = 8) Cerebrospinal fluid (CSF):plasma ratio a 0.6 [0.04 to 2.62] (n = 39) Systemic clearance (L/h/kg) 1.6 ± 0.6 (n = 6) Renal clearance (L/h/kg) 0.34 ± 0.05 (n = 9) Elimination half-life (h) b 0.5 to 3 (n = 19) a Median [range] for 50 paired samples drawn 1 to 8 hours after the last dose in subjects on chronic therapy with zidovudine. b Approximate range.
Distribution The apparent volume of distribution of zidovudine is 1.6 ±
0.6L per kg (Table 7) and binding to plasma protein is low (less than 38%). Metabolism and Elimination Zidovudine is primarily eliminated by hepatic metabolism. The major metabolite of zidovudine is GZDV.
GZDV AUC is about 3-fold greater than the zidovudine AUC. Urinary recovery of zidovudine and GZDV accounts for 14% and 74%, respectively, of the dose following oral administration. A second metabolite, 3'-amino-3'-deoxythymidine (AMT), has been identified in the plasma following single-dose IV administration of zidovudine.
The AMT AUC was one-fifth of the zidovudine AUC. Pharmacokinetics of zidovudine were dose independent at oral dosing regimens ranging from 2 mg per kg every 8 hours to 10 mg per kg every 4 hours. Effect of Food on Absorption Zidovudine may be administered with or without food.
The zidovudine AUC was similar when a single dose of zidovudine was administered with food. Specific Populations Patients with Renal Impairment: Zidovudine clearance was decreased resulting in increased zidovudine and GZDV half-life and AUC in subjects with impaired renal function (n = 14) following a single 200-mg oral dose (Table 8). Plasma concentrations of AMT were not determined.
No dose adjustment is recommended for patients with CrCl greater than or equal to 15 mL per min. Table 8. Zidovudine Pharmacokinetic Parameters in Subjects with Severe Renal Impairment a Parameter Control Subjects (Normal Renal Function) (n = 6) Subjects with Renal Impairment (n = 14) CrCl (mL/min) 120 ± 8 18 ± 2 Zidovudine AUC (ng•h/mL) 1,400 ± 200 3,100 ± 300 Zidovudine half-life (h) 1.0 ± 0.2 1.4 ± 0.1 a Data are expressed as mean ± standard deviation.
Hemodialysis and Peritoneal Dialysis: The pharmacokinetics and tolerance of zidovudine were evaluated in a multiple-dose trial in subjects undergoing hemodialysis (n = 5) or peritoneal dialysis (n = 6) receiving escalating oral doses up to 200 mg 5 times daily for 8 weeks. Daily doses of 500 mg or less were well tolerated despite significantly elevated GZDV plasma concentrations. Apparent zidovudine oral clearance was approximately 50% of that reported in subjects with normal renal function.
Hemodialysis and peritoneal dialysis appeared to have a negligible effect on the removal of zidovudine, whereas GZDV elimination was enhanced. A dosage adjustment is recommended for patients undergoing hemodialysis or peritoneal dialysis [see Dosage and Administration ( 2.5 )]. Patients with Hepatic Impairment: Data describing the effect of hepatic impairment on the pharmacokinetics of zidovudine are limited.
However, zidovudine is eliminated primarily by hepatic metabolism and it appears that zidovudine clearance is decreased and plasma concentrations are increased in subjects with hepatic impairment. There are insufficient data to recommend dose adj… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Zidovudine is an antiretroviral agent [see Microbiology ( 12.4 )].
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Zidovudine Tablets USP, 300 mg are white to off white colored, biconvex, round film coated tablets debossed with 'H' on one side and '1' on other side. Bottle of 60 (NDC 31722-509-60). Store at 20° to 25° C (68° to 77°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Zidovudine (formerly called azidothymidine [AZT]), a pyrimidine nucleoside analogue active against HIV-1. The chemical name of zidovudine is 3'- azido-3'-deoxythymidine; it has the following structural formula: Zidovudine USP is a white to beige, odorless, crystalline solid with a molecular weight of 267.24 and a solubility of 20.1 mg per mL in water at 25°C. The molecular formula is C 10 H 13 N 5 O 4 .
Zidovudine tablets, USP are for oral administration. Each film-coated tablet contains 300 mg of zidovudine USP and the inactive ingredients microcrystalline cellulose, sodium starch glycolate, magnesium stearate and opadry white. (hypromellose, polyethylene glycol, and titanium dioxide).
ZidovudineStructure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Hypersensitivity Reactions Inform patients that potentially life-threatening hypersensitivity reactions (e.g., anaphylaxis, Stevens-Johnson syndrome) can occur while receiving zidovudine. Instruct patients to immediately contact their healthcare provider if they develop rash, as it may be a sign of a more serious reaction. Advise patients that it is very important that they remain under a healthcare provider's care during treatment with zidovudine [see Contraindications ( 4 )].
Neutropenia and Anemia Inform patients that the major toxicities of zidovudine are neutropenia and/or anemia. The frequency and severity of these toxicities are greater in patients with more advanced disease and in those who initiate therapy later in the course of their infection. Advise patients that if toxicity develops, they may require transfusions or drug discontinuation.
Advise patients of the extreme importance of having their blood counts followed closely while on therapy, especially for patients with advanced symptomatic HIV-1 disease [see Boxed Warning, Warnings and Precautions ( 5.1 )]. Myopathy Inform patients that myopathy and myositis with pathological changes, similar to that produced by HIV-1 disease, have been associated with prolonged use of zidovudine [see Boxed Warning, Warnings and Precautions ( 5.3 )]. Lactic Acidosis/Hepatomegaly with Steatosis Advise patients that lactic acidosis and severe hepatomegaly with steatosis have been reported with use of nucleoside analogues and other antiretrovirals.
Advise patients to stop taking zidovudine if they develop clinical symptoms suggestive of lactic acidosis or pronounced hepatotoxicity [see Boxed Warning, Warnings and Precautions ( 5.4 )]. HIV-1/HCV Co-infection Inform patients with HIV-1/HCV co-infection that hepatic decompensation (some fatal) has occurred in HIV-1/HCV co-infected patients receiving combination antiretroviral therapy for HIV-1 and interferon alfa with or without ribavirin [see Warnings and Precautions ( 5.5 )]. Immune Reconstitution Syndrome Advise patients to inform their healthcare provider immediately of any signs and symptoms of infection as inflammation from previous infection may occur soon after combination antiretroviral therapy, including when zidovudine is started [see Warnings and Precautions ( 5.6 )].
Lipoatrophy Advise patients that loss of subcutaneous fat may occur in patients receiving zidovudine and that they will be regularly assessed during therapy [see Warnings and Precautions ( 5.7 )]. Common Adverse Reactions Inform patients that the most commonly reported adverse reactions in adult patients being treated with zidovudine were headache, malaise, nausea, anorexia, and vomiting. The most commonly reported adverse reactions in pediatric patients receiving zidovudine were fever, cough, and digestive disorders.
Patients also should be encouraged to contact their physician if they experience muscle weakness, shortness of breath, symptoms of hepatitis or pancreatitis, or any other unexpected adverse events while being treated with zidovudine [see Adverse Reactions ( 6 )]. Drug Interactions Advise patients that other medications may interact with zidovudine and certain medications, including ganciclovir, interferon alfa, and ribavirin, may exacerbate the toxicity of zidovudine [see Drug Interactions ( 7 )]. Dosage and Administration in Neonates Due to the small volume of zidovudine administered to neonates, advise caregivers to use an appropriate-sized syringe with 0.1 mL graduation to ensure accurate dosing of the syrup formulation [see Dosage and Administration ( 2.3 )].
Pregnancy Inform pregnant women considering the use of zidovudine during pregnancy for prevention of HIV-1 transmission to their infants that transmission may still occur in some cases despite therapy. Pregnancy Registry Advise patients that there is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to zidovudine during preg… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption and Bioavailability In adults, following oral administration, zidovudine is rapidly absorbed and extensively distributed, with peak serum concentrations occurring within 0.5 to 1.5 hours. The AUC was equivalent when zidovudine was administered as zidovudine tablets or syrup compared with zidovudine capsules. The pharmacokinetic properties of zidovudine in fasting adult subjects are summarized in Table 7.
Table 7. Zidovudine Pharmacokinetic Parameters in Adult Subjects Parameter Mean ± SD (except where noted) Oral bioavailability (%) 64 ± 10 (n = 5) Apparent volume of distribution (L/kg) 1.6 ± 0.6 (n = 8) Cerebrospinal fluid (CSF):plasma ratio a 0.6 [0.04 to 2.62] (n = 39) Systemic clearance (L/h/kg) 1.6 ± 0.6 (n = 6) Renal clearance (L/h/kg) 0.34 ± 0.05 (n = 9) Elimination half-life (h) b 0.5 to 3 (n = 19) a Median [range] for 50 paired samples drawn 1 to 8 hours after the last dose in subjects on chronic therapy with zidovudine. b Approximate range.
Distribution The apparent volume of distribution of zidovudine is 1.6 ±
0.6L per kg (Table 7) and binding to plasma protein is low (less than 38%). Metabolism and Elimination Zidovudine is primarily eliminated by hepatic metabolism. The major metabolite of zidovudine is GZDV.
GZDV AUC is about 3-fold greater than the zidovudine AUC. Urinary recovery of zidovudine and GZDV accounts for 14% and 74%, respectively, of the dose following oral administration. A second metabolite, 3'-amino-3'-deoxythymidine (AMT), has been identified in the plasma following single-dose IV administration of zidovudine.
The AMT AUC was one-fifth of the zidovudine AUC. Pharmacokinetics of zidovudine were dose independent at oral dosing regimens ranging from 2 mg per kg every 8 hours to 10 mg per kg every 4 hours. Effect of Food on Absorption Zidovudine may be administered with or without food.
The zidovudine AUC was similar when a single dose of zidovudine was administered with food. Specific Populations Patients with Renal Impairment: Zidovudine clearance was decreased resulting in increased zidovudine and GZDV half-life and AUC in subjects with impaired renal function (n = 14) following a single 200-mg oral dose (Table 8). Plasma concentrations of AMT were not determined.
No dose adjustment is recommended for patients with CrCl greater than or equal to 15 mL per min. Table 8. Zidovudine Pharmacokinetic Parameters in Subjects with Severe Renal Impairment a Parameter Control Subjects (Normal Renal Function) (n = 6) Subjects with Renal Impairment (n = 14) CrCl (mL/min) 120 ± 8 18 ± 2 Zidovudine AUC (ng•h/mL) 1,400 ± 200 3,100 ± 300 Zidovudine half-life (h) 1.0 ± 0.2 1.4 ± 0.1 a Data are expressed as mean ± standard deviation.
Hemodialysis and Peritoneal Dialysis: The pharmacokinetics and tolerance of zidovudine were evaluated in a multiple-dose trial in subjects undergoing hemodialysis (n = 5) or peritoneal dialysis (n = 6) receiving escalating oral doses up to 200 mg 5 times daily for 8 weeks. Daily doses of 500 mg or less were well tolerated despite significantly elevated GZDV plasma concentrations. Apparent zidovudine oral clearance was approximately 50% of that reported in subjects with normal renal function.
Hemodialysis and peritoneal dialysis appeared to have a negligible effect on the removal of zidovudine, whereas GZDV elimination was enhanced. A dosage adjustment is recommended for patients undergoing hemodialysis or peritoneal dialysis [see Dosage and Administration ( 2.5 )]. Patients with Hepatic Impairment: Data describing the effect of hepatic impairment on the pharmacokinetics of zidovudine are limited.
However, zidovudine is eliminated primarily by hepatic metabolism and it appears that zidovudine clearance is decreased and plasma concentrations are increased in subjects with hepatic impairment. There are insufficient data to recommend dose adjustment of zidovudine in patients with impaired hepatic function or liver cirrhosis [see Dosage and Administration (… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Therapy with zidovudine has been shown to prolong survival and decrease the incidence of opportunistic infections in patients with advanced HIV-1 disease and to delay disease progression in asymptomatic HIV-1-infected patients.
14.1Adults Combination Therapy Zidovudine in combination with other antiretroviral agents has been shown to be superior to monotherapy for one or more of the following endpoints: delaying death, delaying development of AIDS, increasing CD4+ cell counts, and decreasing plasma HIV-1 RNA. The clinical efficacy of a combination regimen that includes zidovudine was demonstrated in trial ACTG 320. This trial was a multi-center, randomized, double-blind, placebo-controlled trial that compared zidovudine 600 mg per day plus EPIVIR 300 mg per day with zidovudine plus EPIVIR plus indinavir 800 mg three times daily.
The incidence of AIDS-defining events or death was lower in the triple-drug-containing arm compared with the 2-drug-containing arm (6.1% versus 10.9%, respectively). Monotherapy In controlled trials of treatment-naive subjects conducted between 1986 and 1989, monotherapy with zidovudine, as compared with placebo, reduced the risk of HIV-1 disease progression, as assessed using endpoints that included the occurrence of HIV-1-related illnesses, AIDS-defining events, or death. These trials enrolled subjects with advanced disease (BW 002), and asymptomatic or mildly symptomatic disease in subjects with CD4+ cell counts between 200 and 500 cells per mm 3 (ACTG 016 and ACTG 019).
A survival benefit for monotherapy with zidovudine was not demonstrated in the latter 2 trials. Subsequent trials showed that the clinical benefit of monotherapy with zidovudine was time limited.
14.2Pediatric Patients ACTG 300 was a multi-center, randomized, double-blind trial that provided for comparison of EPIVIR plus zidovudine to didanosine monotherapy. A total of 471 symptomatic, HIV-1-infected therapy-naive pediatric subjects were enrolled in these 2 treatment arms. The median age was 2.7 years (range: 6 weeks to 14 years), the mean baseline CD4+ cell count was 868 cells per mm 3 , and the mean baseline plasma HIV-1 RNA was 5.0 log 10 copies per mL.
The median duration that subjects remained on trial was approximately 10 months. Results are summarized in Table 11. Table 11.
Number of Subjects (%) Reaching a Primary Clinical Endpoint (Disease Progression or Death) Endpoint EPIVIR plus Zidovudine (n = 236) Didanosine (n = 235) HIV disease progression or death (total) 15 (6.4%) 37 (15.7%) Physical growth failure 7 (3.0%) 6 (2.6%) Central nervous system deterioration 4 (1.7%) 12 (5.1%) CDC Clinical Category C 2 (0.8%) 8 (3.4%) Death 2 (0.8%) 11 (4.7%)
14.3Prevention of Material-Fetal HIV-1 Transmission The utility of zidovudine for the prevention of maternal-fetal HIV-1 transmission was demonstrated in a randomized, double-blind, placebo-controlled trial (ACTG 076) conducted in HIV-1-infected pregnant women with CD4+ cell counts of 200 to 1,818 cells per mm 3 (median in the treated group: 560 cells per mm 3 ) who had little or no previous exposure to zidovudine. Oral zidovudine was initiated between 14 and 34 weeks of gestation (median 11 weeks of therapy) followed by IV administration of zidovudine during labor and delivery.
Following birth, neonates received oral zidovudine syrup for 6 weeks. The trial showed a statistically significant difference in the incidence of HIV-1 infection in the neonates (based on viral culture from peripheral blood) between the group receiving zidovudine and the group receiving placebo. Of 363 neonates evaluated in the trial, the estimated risk of HIV-1 infection was 7.8% in the group receiving zidovudine and 24.9% in the placebo group, a relative reduction in transmission risk of 68.7%.
Zidovudine was well tolerated by mothers and infants. There was no difference in pregnancy-related adverse events between the treatment groups.
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE
9.1 Controlled Substance
🔒 Controlled Substance ▾
9.1 Controlled Substance
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis & Mutagenesis & Impairment Of Fertility Carcinogenesis Zidovudine was administered orally at 3 dosage levels to separate groups of mice and rats (60 females and 60 males in each group). Initial single daily doses were 30, 60, and 120 mg per kg per day in mice and 80, 220, and 600 mg per kg per day in rats. The doses in mice were reduced to 20, 30, and 40 mg per kg per day after Day 90 because of treatment-related anemia, whereas in rats only the high dose was reduced to 450 mg per kg per day on Day 91 and then to 300 mg per kg per day on Day 279.
In mice, 7 late-appearing (after 19 months) vaginal neoplasms (5 non-metastasizing squamous cell carcinomas, 1 squamous cell papilloma, and 1 squamous polyp) occurred in animals given the highest dose. One late-appearing squamous cell papilloma occurred in the vagina of a middle-dose animal. No vaginal tumors were found at the lowest dose.
In rats, 2 late-appearing (after 20 months), non-metastasizing vaginal squamous cell carcinomas occurred in animals given the highest dose. No vaginal tumors occurred at the low or middle dose in rats. No other drug-related tumors were observed in either sex of either species.
At doses that produced tumors in mice and rats, the estimated drug exposure (as measured by AUC) was approximately 3 times (mouse) and 24 times (rat) the estimated human exposure at the recommended therapeutic dose of 100 mg every 4 hours. It is not known how predictive the results of rodent carcinogenicity studies may be for humans. Two transplacental carcinogenicity studies were conducted in mice.
One study administered zidovudine at doses of 20 mg per kg per day or 40 mg per kg per day from gestation Day 10 through parturition and lactation with dosing continuing in offspring for 24 months postnatally. The doses of zidovudine administered in this study produced zidovudine exposures approximately 3 times the estimated human exposure at recommended doses. After 24 months, an increase in incidence of vaginal tumors was noted with no increase in tumors in the liver or lung or any other organ in either gender.
These findings are consistent with results of the standard oral carcinogenicity study in mice, as described earlier. A second study administered zidovudine at maximum tolerated doses of 12.5 mg per day or 25 mg per day (approximately 1,000 mg per kg nonpregnant body weight or approximately 450 mg per kg of term body weight) to pregnant mice from Days 12 through 18 of gestation. There was an increase in the number of tumors in the lung, liver, and female reproductive tracts in the offspring of mice receiving the higher dose level of zidovudine.
Mutagenesis Zidovudine was mutagenic in a 5178Y/TK+/- mouse lymphoma assay, positive in an in vitro cell transformation assay, clastogenic in a cytogenetic assay using cultured human lymphocytes, and positive in mouse and rat micronucleus tests after repeated doses. It was negative in a cytogenetic study in rats given a single dose. Impairment of Fertility Zidovudine, administered to male and female rats at doses up to 450 mg per kg per day, which is 7 times the recommended adult dose (300 mg twice daily) based on body surface area, had no effect on fertility based on conception rates.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis & Mutagenesis & Impairment Of Fertility Carcinogenesis Zidovudine was administered orally at 3 dosage levels to separate groups of mice and rats (60 females and 60 males in each group). Initial single daily doses were 30, 60, and 120 mg per kg per day in mice and 80, 220, and 600 mg per kg per day in rats. The doses in mice were reduced to 20, 30, and 40 mg per kg per day after Day 90 because of treatment-related anemia, whereas in rats only the high dose was reduced to 450 mg per kg per day on Day 91 and then to 300 mg per kg per day on Day 279.
In mice, 7 late-appearing (after 19 months) vaginal neoplasms (5 non-metastasizing squamous cell carcinomas, 1 squamous cell papilloma, and 1 squamous polyp) occurred in animals given the highest dose. One late-appearing squamous cell papilloma occurred in the vagina of a middle-dose animal. No vaginal tumors were found at the lowest dose.
In rats, 2 late-appearing (after 20 months), non-metastasizing vaginal squamous cell carcinomas occurred in animals given the highest dose. No vaginal tumors occurred at the low or middle dose in rats. No other drug-related tumors were observed in either sex of either species.
At doses that produced tumors in mice and rats, the estimated drug exposure (as measured by AUC) was approximately 3 times (mouse) and 24 times (rat) the estimated human exposure at the recommended therapeutic dose of 100 mg every 4 hours. It is not known how predictive the results of rodent carcinogenicity studies may be for humans. Two transplacental carcinogenicity studies were conducted in mice.
One study administered zidovudine at doses of 20 mg per kg per day or 40 mg per kg per day from gestation Day 10 through parturition and lactation with dosing continuing in offspring for 24 months postnatally. The doses of zidovudine administered in this study produced zidovudine exposures approximately 3 times the estimated human exposure at recommended doses. After 24 months, an increase in incidence of vaginal tumors was noted with no increase in tumors in the liver or lung or any other organ in either gender.
These findings are consistent with results of the standard oral carcinogenicity study in mice, as described earlier. A second study administered zidovudine at maximum tolerated doses of 12.5 mg per day or 25 mg per day (approximately 1,000 mg per kg nonpregnant body weight or approximately 450 mg per kg of term body weight) to pregnant mice from Days 12 through 18 of gestation. There was an increase in the number of tumors in the lung, liver, and female reproductive tracts in the offspring of mice receiving the higher dose level of zidovudine.
Mutagenesis Zidovudine was mutagenic in a 5178Y/TK+/- mouse lymphoma assay, positive in an in vitro cell transformation assay, clastogenic in a cytogenetic assay using cultured human lymphocytes, and positive in mouse and rat micronucleus tests after repeated doses. It was negative in a cytogenetic study in rats given a single dose. Impairment of Fertility Zidovudine, administered to male and female rats at doses up to 450 mg per kg per day, which is 7 times the recommended adult dose (300 mg twice daily) based on body surface area, had no effect on fertility based on conception rates.
📄 Recent Major Changes ▾
Dosage and Administration, Prevention of Maternal-Fetal HIV-1 Transmission ( 2.3 ) 09/2018 Warnings and Precautions, Lactic Acidosis and Severe Hepatomegaly with Steatosis ( 5.4 ) 11/2017 Warnings and Precautions, Lipoatrophy ( 5.7 ) 11/2017
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL 300 mg - 60 tablets Zidovudine300mg60scount