
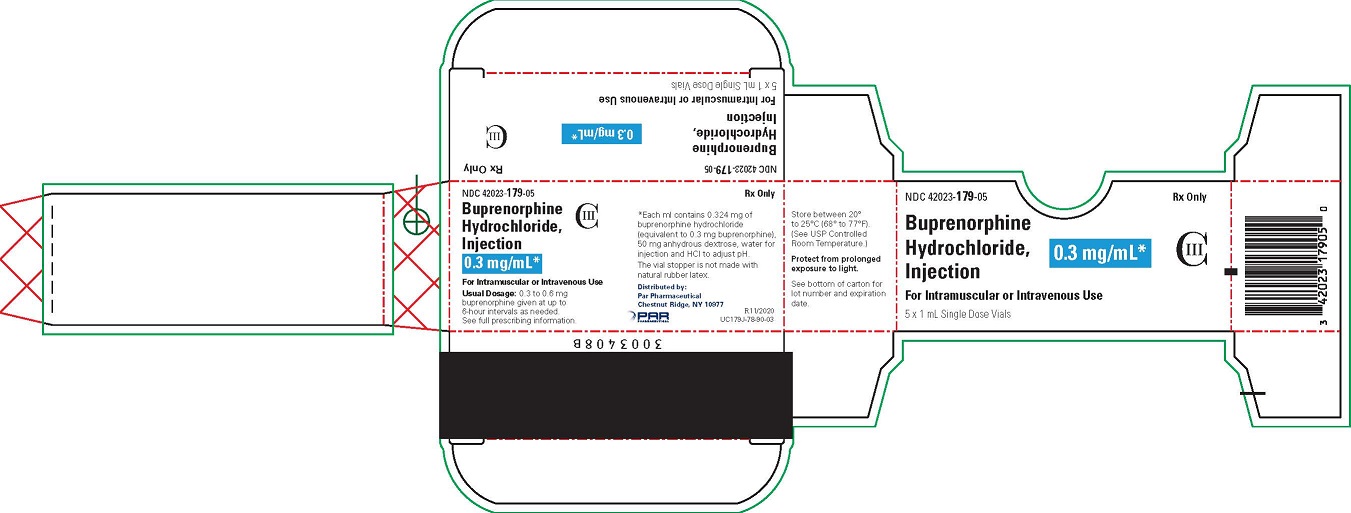
Buprenorphine Hydrochloride .324 mg/mL Injection, 5 vials — NDC 42023-179-05 (Billing 42023-0179-05)
This is a package of 5 vials of Buprenorphine Hydrochloride .324 mg/mL Injection from Par Health USA, LLC, marketed since Jul 2015 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 42023-179-05 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 42023 labeler · 179 product · 05 package
- Package marketed since
- Jul 30, 2015
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 4202317905 0
- Medicaid fills, this package
- 426 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Other active recalls for Buprenorphine Hydrochloride (different manufacturers) — 1 · tap to view
Past resolved recalls for this product (1)
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 059205
- GCN: 24749
- GPI-14 (Medi-Span): 65200010102005
- HICL (First Databank): 001762
- AHFS class code: 28:08.12.00
- RxCUI (RxNorm): 238129
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Partial Opioid Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Buprenorphine injection is used to treat certain people who are addicted to opioid (narcotic) drugs. Buprenorphine injection is in a class of medications called opiate partial agonists. It works to prevent withdrawal symptoms when someone stops taking opioid drugs.
Read the full MedlinePlus article ↗- It depends on the product. Sublingual tablets, Sublocade and Brixadi treat opioid dependence. Belbuca, Butrans, patches and the injection treat severe pain that needs an opioid.
- Follow your label exactly. Sublingual tablets dissolve under the tongue once daily and must not be chewed or swallowed. Patches stay on for 7 days, and injections are given by a pr...
- Nausea, headache, dizziness, constipation, sleepiness and dry mouth are common. With patches, you may get itching or redness at the site. Call for help if breathing slows or you ca...
- No, not without your prescriber's guidance. Alcohol, benzodiazepines and other sedatives can cause dangerous sedation, slowed breathing, coma and death.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Buprenorphine Hydrochloride — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $18.57 | $92.86 / 5 vials |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J0592 | $4.474 / J0592 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Oct 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 42023-0179-05 You're viewing this Main listing | 5 VIAL in 1 CARTON / 1 mL in 1 VIAL | 2015-07-30 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Buprenorphine Hydrochloride .324 mg/mL 00143-9246-05 | Hikma | 5 vials | — | AP | FDA listed | — |
| Buprenorphine Hydrochloride .324 mg/mLthis 42023-0179-05 | Par | 5 vials | — | AP | FDA listed | — |
| Buprenorphine Hydrochloride .324 mg/mL 70069-0027-05 | Somerset | 5 vials | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Buprenorphine inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
50 mg / 1 mL
UNII 5SL0G7R0OK
A simple sugar made from corn or other plants, used in medicines as a filler and sweetener. It helps create the right texture and taste in tablets, powders, and liquid formulations.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Par Health USA, LLC labeler code 42023
- ETHACRYNATE SODIUM 50 mg/50mL Injection, Powder, For Solution NDC 42023-157-01
- Adrenalin epinephrine 1 mg/mL Injection NDC 42023-159-25
- Vasostrict Vasopressin 20 [USP'U]/mL Injection NDC 42023-164-10
- Adrenalin epinephrine 1 mg/mL Injection NDC 42023-168-01
- Mycophenolate Mofetil 500 mg/20mL Injection, Powder, Lyophilized, For Solution NDC 42023-172-04
- Ganciclovir 500 mg/10mL Injection, Powder, Lyophilized, For Solution NDC 42023-173-25
- Argatroban 250 mg/2.5mL Injection NDC 42023-182-01
- Dexmedetomidine Hydrochloride 4 ug/mL Injection, Solution NDC 42023-186-20
- Dexmedetomidine Hydrochloride 4 ug/mL Injection, Solution NDC 42023-187-10
- NEOSTIGMINE METHYLSULFATE .5 mg/mL Injection NDC 42023-188-10
- NEOSTIGMINE METHYLSULFATE 1 mg/mL Injection NDC 42023-189-10
- Vasostrict Vasopressin 20 [USP'U]/mL Injection NDC 42023-190-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SERIOUS AND LIFE-THREATENING RISKS FROM USE OF BUPRENORPHINE Addiction, Abuse, and Misuse Because the use of buprenorphine exposes patients and other users to the risks of opioid addiction, abuse, and misuse, which can lead to overdose and death, assess each patient's risk prior to prescribing and reassess all patients regularly for the development of these behaviors and conditions ( see WARNINGS ) . Life-Threatening Respiratory Depression Serious, life-threatening, or fatal respiratory depression may occur with use of buprenorphine, especially during initiation or following a dosage increase.
To reduce the risk of respiratory depression, proper dosing and titration of buprenorphine are essential ( see WARNINGS ) . Risks From Concomitant Use With Benzodiazepines Or Other CNS Depressants C oncomitant use of opioids with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death. Reserve concomitant prescribing of buprenorphine and benzodiazepines or other CNS depressants for use in patients for whom alternative treatment options are inadequate ( see WARNINGS , PRECAUTIONS ) .
Neonatal Opioid Withdrawal Syndrome (NOWS) Advise pregnant women using opioids for an extended period of time of the risk of Neonatal Opioid Withdrawal Syndrome, which may be life-threatening if not recognized and treated. Ensure that management by neonatology experts will be available at delivery ( see WARNINGS ) .
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Buprenorphine hydrochloride injection is indicated for the management of pain severe enough to require an opioid analgesic and for which alternate treatments are inadequate. Limitations of Use: Because of the risks of addiction, abuse, misuse, overdose, and death which can occur at any dosage or duration and persist over the course of therapy [see WARNINGS ] , reserve opioid analgesics, including buprenorphine, for use in patients for whom alternative treatment options are ineffective, not tolerated, or would be otherwise inadequate to provide sufficient management of pain.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Buprenorphine should be prescribed only by healthcare professionals who are knowledgeable about the use of opioids and how to mitigate the associated risks. Use the lowest effective dosage for the shortest duration of time consistent with individual patient treatment goals [see WARNINGS ]. Because the risk of overdose increases as opioid doses increase, reserve titration to higher doses of buprenorphine for patients in whom lower doses are insufficiently effective and in whom the expected benefits of using a higher dose opioid clearly outweigh the substantial risks.
Many acute pain conditions (e.g., the pain that occurs with a number of surgical procedures or acute musculoskeletal injuries) require no more than a few days of an opioid analgesic. Clinical guidelines on opioid prescribing for some acute pain conditions are available. There is variability in the opioid analgesic dose and duration needed to adequately manage pain due both to the cause of pain and to individual patient factors.
Initiate the dosing regimen for each patient individually, taking into account the patient's underlying cause and severity of pain, prior analgesic treatment and response, and risk factors for addiction, abuse, and misuse [see WARNINGS ]. Respiratory depression can occur at any time during opioid therapy, especially when initiating and following dosage increases with buprenorphine. Consider this risk when selecting an initial dose and when making dose adjustments [see WARNINGS ] .
Inspect buprenorphine for particulate matter and discoloration prior to administration. Dosing Adults and Pediatric Patients over 12 years of age The initial starting dose is 1 mL buprenorphine hydrochloride (0.3 mg buprenorphine) given by deep intramuscular or slow (over at least 2 minutes) intravenous injection at up to 6-hour intervals, as needed. Repeat once (up to 0.3 mg) if required, 30 to 60 minutes after initial dosage, giving consideration to previous dose pharmacokinetics, and thereafter only as needed.
In high-risk patients (e.g., elderly, debilitated, presence of respiratory disease, etc.) and/or in patients where other CNS depressants are present, such as in the immediate postoperative period, the dose should be limited to the minimum required. Extra caution should be exercised with the intravenous route of administration, particularly with the initial dose. Occasionally, it may be necessary to administer single doses of up to 0.6 mg to adults depending on the severity of the pain and the response of the patient.
This dose should only be given I.M. and only to adult patients who are not in a high risk category [see WARNINGS and PRECAUTIONS ]. At this time, there are insufficient data to recommend single doses greater than 0.6 mg for long-term use. Pediatric Patients Buprenorphine hydrochloride injection has been used in pediatric patients 2 to 12 years of age at doses between 2 to 6 micrograms/kg of body weight given every 4 to 6 hours.
There is insufficient experience to recommend a dose in infants below the age of two years, single doses greater than 6 micrograms/kg of body weight, or the use of a repeat or second dose at 30 to 60 minutes (such as is used in adults). Since there is some evidence that not all pediatric patients clear buprenorphine faster than adults, fixed interval or "round-the-clock" dosing should not be undertaken until the proper inter-dose interval has been established by clinical observation of the child. Healthcare providers should recognize that, as with adults, some pediatric patients may not need to be remedicated for 6 to 8 hours.
Safety and Handling Buprenorphine hydrochloride injection is supplied in sealed vials and poses no known environmental risk to healthcare providers. Accidental dermal exposure should be treated by removal of any contaminated clothing and rinsing the affected area with water. Buprenorphine is a potent opioid and, like all drugs of this class, has been associated with abuse… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Buprenorphine hydrochloride is contraindicated in patients with: Significant respiratory depression [see WARNINGS ]. Acute or severe bronchial asthma in an unmonitored setting or in the absence of resuscitative equipment [see WARNINGS ]. Known or suspected gastrointestinal obstruction, including paralytic ileus [see WARNINGS ].
Hypersensitivity to buprenorphine (e.g., anaphylaxis) or any other ingredient in buprenorphine hydrochloride injection [see WARNINGS ].
⚠️ Warnings ▾
WARNINGS Addiction, Abuse, and Misuse Buprenorphine hydrochloride injection contains buprenorphine, a Schedule III controlled substance. As an opioid, buprenorphine exposes users to the risks of addiction, abuse, and misuse. Although the risk of addiction in any individual is unknown, it can occur in patients appropriately prescribed buprenorphine.
Addiction can occur at recommended doses and if the drug is misused or abused. The risk of opioid-related overdose or overdose-related death is increased with higher opioid doses, and this risk persists over the course of therapy. In postmarketing studies, addiction, abuse, misuse, and fatal and non-fatal opioid overdose were observed in patients with long-term opioid use [see ADVERSE REACTIONS ] .
Assess each patient's risk for opioid addiction, abuse, or misuse prior to prescribing buprenorphine, and reassess all patients receiving buprenorphine for the development of these behaviors and conditions. Risks are increased in patients with a personal or family history of substance abuse (including drug or alcohol addiction or abuse) or mental illness (e.g., major depression). The potential for these risks should not, however, prevent the prescribing of buprenorphine for the proper management of pain in any given patient.
Patients at increased risk may be prescribed opioids such as buprenorphine, but use in such patients necessitates intensive counseling about the risks and proper use of buprenorphine along with frequent reevaluation for signs of addiction, abuse, and misuse. Opioids are sought for nonmedical use and are subject to diversion from legitimate prescribed use. Consider these risks when prescribing or dispensing buprenorphine.
Strategies to reduce these risks include proper product storage and control practices for a C-III drug. Contact local state professional licensing board or state controlled substances authority for information on how to prevent and detect abuse or diversion of this product. Life-Threatening Respiratory Depression Serious, life-threatening, or fatal respiratory depression has been reported with the use of opioids, even when used as recommended.
Respiratory depression, if not immediately recognized and treated, may lead to respiratory depression and death. Management of respiratory depression may include close observation, supportive measures, and use of opioid overdose reversal agents (e.g., naloxone, nalmefene), depending on the patient's clinical status [see OVERDOSAGE ] . Carbon dioxide (CO 2 ) retention from opioid-induced respiratory depression can exacerbate the sedating effects of opioids.
While serious, life-threatening, or fatal respiratory depression can occur at any time during the use of buprenorphine, the risk is greatest during the initiation of therapy or following a dosage increase. To reduce the risk of respiratory depression, proper dosing and titration of buprenorphine are essential. Overestimating the buprenorphine dosage when converting patients from another opioid product can result in a fatal overdose with the first dose.
Opioids can cause sleep-related breathing disorders including central sleep apnea (CSA) and sleep-related hypoxemia. Opioid use increases the risk of CSA in a dose-dependent fashion. In patients who present with CSA, consider decreasing the opioid dosage using best practices for opioid taper [see DOSAGE AND ADMINISTRATION ].
Risks from Concomitant Use with Benzodiazepines or Other CNS Depressants Profound sedation, respiratory depression, coma, and death may result from the concomitant use of buprenorphine hydrochloride with benzodiazepines and/or other CNS depressants, including alcohol (e.g., non-benzodiazepine sedatives/hypnotics, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, gabapentinoids [gabapentin or pregabalin], and other opioids). Because of these risks, reserve concomitant prescribing of these drugs for use in patients for whom alternative treatment options are ina… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Postmarketing Experience The most frequent side effect in clinical studies involving 1,133 patients was sedation which occurred in approximately two-thirds of the patients. Although sedated, these patients could easily be aroused to an alert state. Other less frequent adverse reactions occurring in 5 to 10% of the patients were: Nausea Dizziness/Vertigo Occurring in 1 to 5% of the patients: Sweating Headache Hypotension Nausea/Vomiting Vomiting Hypoventilation Miosis The following adverse reactions were reported to have occurred in less than 1% of the patients: CNS Effect: confusion, blurred vision, euphoria, weakness/fatigue, dry mouth, nervousness, depression, slurred speech, paresthesia.
Cardiovascular: hypertension, tachycardia, bradycardia. Gastrointestinal: constipation. Respiratory: dyspnea, cyanosis.
Dermatological: pruritus. Ophthalmological: diplopia, visual abnormalities. Miscellaneous: injection site reaction, urinary retention, dreaming, flushing/warmth, chills/cold, tinnitus, conjunctivitis, Wenckebach block, and psychosis.
Other effects observed infrequently include malaise, hallucinations, depersonalization, coma, dyspepsia, flatulence, apnea, rash, amblyopia, tremor, and pallor. The following reactions have been reported to occur rarely: loss of appetite, dysphoria/agitation, diarrhea, urticaria, and convulsions/lack of muscle coordination. Allergic Reactions: Cases of acute and chronic hypersensitivity to buprenorphine have been reported both in clinical trials and in the postmarketing experience of buprenorphine hydrochloride injection and other buprenorphine-containing products.
The most common signs and symptoms include rashes, hives, and pruritus. Cases of bronchospasm, angioneurotic edema, and anaphylactic shock have been reported. A history of hypersensitivity to buprenorphine is a contraindication to buprenorphine hydrochloride.
In the United Kingdom, buprenorphine hydrochloride was made available under monitored release regulation during the first year of sale, and yielded data from 1,736 physicians on 9,123 patients (17,120 administrations). Data on 240 children under the age of 18 years were included in this monitored release program. No important new adverse effects attributable to buprenorphine hydrochloride were observed.
Serotonin syndrome : Cases of serotonin syndrome, a potentially life-threatening condition, have been reported during concomitant use of opioids with serotonergic drugs. Adrenal insufficiency : Cases of adrenal insufficiency have been reported with opioid use, more often following greater than one month of use. Androgen deficiency : Cases of androgen deficiency have occurred with use of opioids for an extended period of time (see CLINICAL PHARMACOLOGY: Pharmacodynamics ) .
Hyperalgesia and Allodynia: Cases of hyperalgesia and allodynia have been reported with opioid therapy of any duration ( see WARNINGS ) . Hypoglycemia: Cases of hypoglycemia have been reported in patients taking opioids. Most reports were in patients with at least one predisposing risk factor (e.g., diabetes).
Opioid-induced esophageal dysfunction (OIED): Cases of OIED have been reported in patients taking opioids and may occur more frequently in patients taking higher doses of opioids, and/or in patients taking opioids longer term (see WARNINGS ) . Adverse Reactions from Observational Studies A prospective, observational cohort study estimated the risks of addiction, abuse, and misuse in patients initiating long-term use of Schedule II opioid analgesics between 2017 and 2021. Study participants included in one or more analyses had been enrolled in selected insurance plans or health systems for at least one year, were free of at least one outcome at baseline, completed a minimum number of follow-up assessments, and either: 1) filled multiple extended-release/long-acting opioid analgesic prescriptions during a 90-day period (n=978); or 2) filled any Schedule II opioid analgesic prescriptions c… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
Drug Interactions Clinically significant drug interactions with Buprenorphine Hydrochloride Injection Benzodiazepines and Other Central Nervous System (CNS) Depressants Clinical Impact: Due to additive pharmacologic effect, the concomitant use of benzodiazepines or other CNS depressants, including alcohol, can increase the risk of hypotension, respiratory depression, profound sedation, coma, and death. Intervention: Reserve concomitant prescribing of these drugs for use in patients for whom alternative treatment options are inadequate.
Limit dosages and durations to the minimum required. Monitor patients closely for signs of respiratory depression and sedation [see WARNINGS] . Examples: Benzodiazepines and other sedatives/hypnotics, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, gabapentinoids [gabapentin or pregabalin], and other opioids, alcohol.
Inhibitors of CYP3A4 Clinical Impact: The concomitant use of buprenorphine and CYP3A4 inhibitors can increase the plasma concentration of buprenorphine, resulting in increased or prolonged opioid effects, particularly when an inhibitor is added after a stable dose of buprenorphine is achieved. After stopping a CYP3A4 inhibitor, as the effects of the inhibitor decline, the buprenorphine plasma concentration will decrease [see CLINICAL PHARMACOLOGY: Pharmacokinetics], potentially resulting in decreased opioid efficacy or a withdrawal syndrome in patients who had developed physical dependence to buprenorphine.
Intervention: If concomitant use is necessary, consider dosage reduction of buprenorphine until stable drug effects are achieved. Monitor patients for respiratory depression and sedation. If a CYP3A4 inhibitor is discontinued, consider increasing the buprenorphine dosage until stable drug effects are achieved.
Monitor for signs of opioid withdrawal. Examples: Macrolide antibiotics (e.g., erythromycin), azole-antifungal agents (e.g., ketoconazole), protease inhibitors (e.g., ritonavir) CYP3A4 Inducers Clinical Impact: The concomitant use of buprenorphine and CYP3A4 inducers can decrease the plasma concentration of buprenorphine [see CLINICAL PHARMACOLOGY: Pharmacokinetics ], potentially resulting in decreased efficacy or onset of a withdrawal syndrome in patients who have developed physical dependence to buprenorphine. After stopping a CYP3A4 inducer, as the effects of the inducer decline, the buprenorphine plasma concentration will increase [see CLINICAL PHARMACOLOGY: Pharmacokinetics ], which could increase or prolong both therapeutic effects and adverse reactions and may cause serious respiratory depression.
Intervention: If concomitant use is necessary, consider increasing the buprenorphine dosage until stable drug effects are achieved. Monitor for signs of opioid withdrawal. If a CYP3A4 inducer is discontinued, consider buprenorphine dosage reduction and monitor for signs of respiratory depression and sedation.
Examples: Rifampin, carbamazepine, phenytoin Serotonergic Drugs Clinical Impact: The concomitant use of opioids with other drugs that affect the serotonergic neurotransmitter system has resulted in serotonin syndrome. Intervention: If concomitant use is warranted, carefully observe the patient, particularly during treatment initiation and dose adjustment. Discontinue buprenorphine if serotonin syndrome is suspected.
Examples: Selective serotonin reuptake inhibitors (SSRIs), serotonin and norepinephrine reuptake inhibitors (SNRIs), tricyclic antidepressants (TCAs), triptans, 5-HT3 receptor antagonists, drugs that affect the serotonin neurotransmitter system (e.g., mirtazapine, trazodone, tramadol), certain muscle relaxants (i.e., cyclobenzaprine, metaxalone), monoamine oxidase (MAO) inhibitors (those intended to treat psychiatric disorders and also others, such as linezolid and intravenous methylene blue). Monoamine Oxidase Inhibitors (MAOIs) Clinical Impact: MAOI interactions with opioids may manifest as serotonin syndrome opioid tox… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
Pregnancy Risk Summary Use of opioid analgesics for an extended period of time during pregnancy may cause neonatal opioid withdrawal syndrome [see WARNINGS: Neonatal Opioid Withdrawal Syndrome ]. Available data with buprenorphine in pregnant women are insufficient to inform a drug-associated risk for major birth defects and miscarriage. Reproductive and developmental studies in rats and rabbits identified adverse events at approximately 2 times the maximum recommended human dose (MRHD) of 1.8 mg/day of buprenorphine.
Embryofetal death was observed in both rats and rabbits administered buprenorphine during the period of organogenesis at doses approximately 54 and 2.2 times, respectively, the MRHD of 1.8 mg/day of buprenorphine. Pre-and postnatal development studies in rats demonstrated increased neonatal deaths at 2.7 times and above and dystocia at approximately 27 times the MRHD of 1.8 mg/day of buprenorphine. No clear teratogenic effects were seen when buprenorphine was administered during organogenesis with a range of doses 5 times or greater than the MRHD of 1.8 mg/day of buprenorphine.
However, increases in skeletal abnormalities were noted in rats and rabbits administered buprenorphine daily during organogenesis at doses approximately 5.4 and 10.8 times the MRHD of 1.8 mg/day of buprenorphine, respectively. In a few studies, some events such as acephalus and omphalocele were also observed but these findings were not clearly treatment-related [see Data ]. Based on animal data, advise pregnant women of the potential risk to a fetus.
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Fetal/neonatal adverse reactions Use of opioid analgesics for an extended period of time during pregnancy for medical or nonmedical purposes can result in physical dependence in the neonate and neonatal opioid withdrawal syndrome shortly after birth. Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea, and/or failure to gain weight. Signs of neonatal withdrawal usually occur in the first days after birth.
The duration and severity of neonatal opioid withdrawal syndrome may vary. Observe newborns for signs of neonatal opioid withdrawal syndrome and manage accordingly [see WARNINGS: Neonatal Opioid Withdrawal Syndrome ]. Labor and Delivery The safety of buprenorphine hydrochloride given during labor and delivery has not been established.
As with all opioids, use of buprenorphine prior to delivery may result in respiratory depression in the newborn. Opioids cross the placenta and may produce respiratory depression and psycho-physiologic effects in neonates. An opioid overdose reversal agent, such as naloxone or nalmefene, should be available for reversal of opioid induced respiratory depression in the neonate.
Data Human Data Studies have been conducted to evaluate neonatal outcomes in women exposed to buprenorphine during pregnancy. Limited published data on malformations from trials, observational studies, case series, and case reports on buprenorphine use in pregnancy have not shown an increased risk of major malformations. Based on these studies the incidence of neonatal abstinence syndrome is not clear and there does not appear to be a dose-response relationship.
Animal Data The exposure margins listed below are based on body surface area comparisons (mg/m 2 ) to MRHD of 1.8 mg buprenorphine via buprenorphine hydrochloride injection. Following oral administration to rats no teratogenic effects were observed at buprenorphine doses up to 250 mg/kg/day (estimated exposure approximately 1351 times the MRHD o… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
Pediatric Use The safety and effectiveness of buprenorphine hydrochloride have been established for children between 2 and 12 years of age. Use of buprenorphine hydrochloride in children is supported by evidence from adequate and well controlled trials of buprenorphine hydrochloride in adults, with additional data from studies of 960 children ranging in age from 9 months to 18 years of age. Data is available from a pharmacokinetic study, several controlled clinical trials, and several large post-marketing studies and case series.
The available information provides reasonable evidence that buprenorphine hydrochloride may be used safely in children ranging from 2 to 12 years of age, and that it is of similar effectiveness in children as in adults.
🧓 Geriatric Use ▾
Geriatric Use Elderly patients (aged 65 years or older) may have increased sensitivity to buprenorphine. In general, use caution when selecting a dosage for an elderly patient, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function and of concomitant disease or other drug therapy. Respiratory depression is the chief risk for elderly patients treated with opioids, and has occurred after large initial doses were administered to patients who were not opioid-tolerant or when opioids were co-administered with other agents that depress respiration.
Titrate the dosage of buprenorphine slowly in geriatric patients and monitor for signs of central nervous system and respiratory depression [see WARNINGS , PRECAUTIONS ]. Buprenorphine is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
🆘 Overdosage ▾
OVERDOSAGE Clinical Presentation Acute overdose with buprenorphine can be manifested by respiratory depression, somnolence progressing to stupor or coma, skeletal muscle flaccidity, cold and clammy skin, constricted pupils, and, in some cases, pulmonary edema, bradycardia, hypotension, hypoglycemia, partial or complete airway obstruction, atypical snoring, and death. Marked mydriasis rather than miosis may be seen with hypoxia in overdose situations [see CLINICAL PHARMACOLOGY ]. Toxic leukoencephalopathy has been reported after opioid overdose and can present hours, days, or weeks after apparent recovery from the initial intoxication.
Treatment of Overdose In the case of overdose, priorities are the reestablishment of a patent and protected airway and institution of assisted or controlled ventilation, if needed. Employ other supportive measures (including oxygen and vasopressors) in the management of circulatory shock and pulmonary edema as indicated. Cardiac arrest or arrhythmias will require advanced life-support measures.
For clinically significant respiratory or circulatory depression secondary to buprenorphine overdose, administer an opioid overdose reversal agent such as naloxone or nalmefene. The healthcare provider must remember that buprenorphine is a long-acting depressant (36 to 48 hours), whereas the antagonists act for much shorter periods (one to three hours). Because the duration of opioid reversal is expected to be less than the duration of action of buprenorphine in buprenorphine hydrochloride, carefully monitor the patient until spontaneous respiration is reliably reestablished.
If the response to an opioid overdose reversal agent is suboptimal or only brief in nature, administer additional reversal agent as directed by the product's prescribing information. In an individual physically dependent on opioids, the administration of the usual dose of an opioid overdose reversal agent will precipitate an acute withdrawal syndrome. The severity of the withdrawal symptoms experienced will depend on the degree of physical dependence and the dose of the reversal agent administered.
If a decision is made to treat serious respiratory depression in the physically-dependent patient, administration of the reversal agent should be initiated with care and by titration with smaller than usual doses of the reversal agent.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action Buprenorphine is a partial agonist at the mu-opioid receptor and an antagonist at the kappa-opioid receptor. One unusual property of buprenorphine observed in vitro studies is its very slow rate of dissociation from its receptor. This could account for its longer duration of action than morphine, the unpredictability of its reversal by opioid antagonists, and its low level of manifest physical dependence.
Pharmacodynamics Buprenorphine hydrochloride is a parenteral opioid analgesic with 0.3 mg buprenorphine being approximately equivalent to 10 mg morphine sulfate in analgesic and respiratory depressant effects in adults. Pharmacological effects occur as soon as 15 minutes after intramuscular injection and persist for 6 hours or longer. Peak pharmacologic effects usually are observed at 1 hour.
When used intravenously, the times to onset and peak effect are shortened. Buprenorphine demonstrates narcotic antagonist activity and has been shown to be equipotent with naloxone as an antagonist of morphine in the mouse tail flick test. Effect s on the Central Nervous System The principal action of therapeutic value of buprenorphine is analgesia and is thought to be due to buprenorphine binding with high affinity to opioid receptors on neurons in the brain and spinal cord.
Buprenorphine produces respiratory depression by direct action on brain stem respiratory centers. The respiratory depression involves a reduction in the responsiveness of the brain stem respiratory centers to both increases in carbon dioxide tension and electrical stimulation. Under usual conditions of use in adults, both buprenorphine and morphine show similar dose-related respiratory depressant effects.
At adult therapeutic doses, buprenorphine (0.3 mg buprenorphine) can decrease respiratory rate in an equivalent manner to an equianalgesic dose of morphine (10 mg). [see WARNINGS ]. Buprenorphine causes miosis, even in total darkness. Pinpoint pupils are a sign of opioid overdose but are not pathognomonic (e.g., pontine lesions of hemorrhagic or ischemic origins may produce similar findings).
Marked mydriasis rather than miosis may be seen due to hypoxia in overdose situations. Effects on the Gastrointestinal Tract and Other Smooth Muscle Buprenorphine causes a reduction in motility associated with an increase in smooth muscle tone in the antrum of the stomach and duodenum. Digestion of food in the small intestine is delayed and propulsive contractions are decreased.
Propulsive peristaltic waves in the colon are decreased, while tone is increased to the point of spasm, resulting in constipation. Other opioid-induced effects may include a reduction in biliary and pancreatic secretions, spasm of sphincter of Oddi, transient elevations in serum amylase, and opioid-induced esophageal dysfunction (OIED). Effec ts on the Cardiovascular System Buprenorphine produces peripheral vasodilation, which may result in orthostatic hypotension or syncope.
Manifestations of histamine release and/or peripheral vasodilation may include pruritus, flushing, red eyes, sweating, and/or orthostatic hypotension. Buprenorphine may cause a decrease or, rarely, an increase in pulse rate and blood pressure in some patients. Thorough QT studies with buprenorphine products have demonstrated QT prolongation ≤ 15 msec.
Effects on the Endocrine System Opioids inhibit the secretion of adrenocorticotropic hormone (ACTH), cortisol, and luteinizing hormone (LH) in humans. They also stimulate prolactin, growth hormone (GH) secretion, and pancreatic secretion of insulin and glucagon. Use of opioids for an extended period of time may influence the hypothalamic-pituitary-gonadal axis, leading to androgen deficiency that may manifest as low libido, impotence, erectile dysfunction, amenorrhea, or infertility.
The causal role of opioids in the clinical syndrome of hypogonadism is unknown because the various medical, physical, lifestyle, and psychological stressors that… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
Mechanism of Action Buprenorphine is a partial agonist at the mu-opioid receptor and an antagonist at the kappa-opioid receptor. One unusual property of buprenorphine observed in vitro studies is its very slow rate of dissociation from its receptor. This could account for its longer duration of action than morphine, the unpredictability of its reversal by opioid antagonists, and its low level of manifest physical dependence.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Buprenorphine Hydrochloride Injection NDC 42023-179-05: 0.3 mg buprenorphine in a 1 mL single dose clear glass vial, supplied in packages of five vials. Store at 20° to 25°C (68° to 77°F). (See USP Controlled Room Temperature.) Protect from prolonged exposure to light. The vial stopper is not made with natural rubber latex.
📦 Storage and Handling ▾
Store at 20° to 25°C (68° to 77°F). (See USP Controlled Room Temperature.) Protect from prolonged exposure to light. The vial stopper is not made with natural rubber latex.
📋 Description ▾
DESCRIPTION Buprenorphine hydrochloride is a partial opioid agonist. The chemical name of buprenorphine hydrochloride is 17-(cyclopropylmethyl)-α-(1,1-dimethylethyl)-4, 5-epoxy-18,19-dihydro-3-hydroxy-6-methoxy-α-methyl-6, 14-ethenomorphinan-7-methanol, hydrochloride [5α, 7α(S)]. Buprenorphine hydrochloride is a white powder, weakly acidic and with limited solubility in water.
Buprenorphine hydrochloride injection is a clear, sterile, injectable agonist-antagonist analgesic intended for intravenous or intramuscular administration. Each ml of Buprenorphine hydrochloride injection contains 0.324 mg buprenorphine hydrochloride (equivalent to 0.3 mg buprenorphine), 50 mg anhydrous dextrose, water for injection and HCl to adjust pH. Buprenorphine hydrochloride has the molecular formula, C 29 H 41 NO 4 HCl, and the following structure: Molecular weight: 504.09 Chemical Structure
💬 Information for Patients ▾
Information for Patients Addiction, Abuse, and Misuse Inform patients that the use of buprenorphine, even when taken as recommended, can result in addiction, abuse, and misuse, which can lead to overdose or death [see WARNINGS ]. Life-Threatening Respiratory Depression Inform patients of the risk of life-threatening respiratory depression, including information that the risk is greatest when starting buprenorphine or when the dosage is increased, and that it can occur even at recommended dosages [see WARNINGS ]. Hyperalgesia and Allodynia Advise patients to inform their healthcare provider if they experience symptoms of hyperalgesia, including worsening pain, increased sensitivity to pain, or new pain [see WARNINGS , ADVERSE REACTIONS ] .
Serotonin Syndrome Inform patients that opioids could cause a rare but potentially life-threatening condition called serotonin syndrome resulting from concomitant administration of serotonergic drugs. Warn patients of the symptoms of serotonin syndrome and to seek medical attention right away if symptoms develop after discharge from the hospital. Instruct patients to inform their healthcare providers if they are taking, or plan to take serotonergic medications [see PRECAUTIONS; Drug Interactions ].
Constipation Advise patients of the potential for severe constipation, including management instructions and when to seek medical attention [see CLINICAL PHARMACOLOGY: Pharmacodynamics , ADVERSE REACTIONS ].
⚠️ Precautions ▾
PRECAUTIONS General: Buprenorphine hydrochloride should be administered with caution in the elderly, debilitated patients, in children and those with severe impairment of hepatic, pulmonary, or renal function; myxedema or hypothyroidism; adrenal cortical insufficiency (e.g., Addison's disease); CNS depression or coma; toxic psychoses; prostatic hypertrophy or urethral stricture; acute alcoholism; delirium tremens; or kyphoscoliosis. Because buprenorphine hydrochloride is metabolized by the liver, the activity of buprenorphine hydrochloride may be increased and/or extended in those individuals with impaired hepatic function or those receiving other agents known to decrease hepatic clearance.
Buprenorphine hydrochloride has been shown to increase intracholedochal pressure to a similar degree as other opioid analgesics, and thus should be administered with caution to patients with dysfunction of the biliary tract. Information for Patients Addiction, Abuse, and Misuse Inform patients that the use of buprenorphine, even when taken as recommended, can result in addiction, abuse, and misuse, which can lead to overdose or death [see WARNINGS ]. Life-Threatening Respiratory Depression Inform patients of the risk of life-threatening respiratory depression, including information that the risk is greatest when starting buprenorphine or when the dosage is increased, and that it can occur even at recommended dosages [see WARNINGS ].
Hyperalgesia and Allodynia Advise patients to inform their healthcare provider if they experience symptoms of hyperalgesia, including worsening pain, increased sensitivity to pain, or new pain [see WARNINGS , ADVERSE REACTIONS ] . Serotonin Syndrome Inform patients that opioids could cause a rare but potentially life-threatening condition called serotonin syndrome resulting from concomitant administration of serotonergic drugs. Warn patients of the symptoms of serotonin syndrome and to seek medical attention right away if symptoms develop after discharge from the hospital.
Instruct patients to inform their healthcare providers if they are taking, or plan to take serotonergic medications [see PRECAUTIONS; Drug Interactions ]. Constipation Advise patients of the potential for severe constipation, including management instructions and when to seek medical attention [see CLINICAL PHARMACOLOGY: Pharmacodynamics , ADVERSE REACTIONS ]. Drug Interactions Clinically significant drug interactions with Buprenorphine Hydrochloride Injection Benzodiazepines and Other Central Nervous System (CNS) Depressants Clinical Impact: Due to additive pharmacologic effect, the concomitant use of benzodiazepines or other CNS depressants, including alcohol, can increase the risk of hypotension, respiratory depression, profound sedation, coma, and death.
Intervention: Reserve concomitant prescribing of these drugs for use in patients for whom alternative treatment options are inadequate. Limit dosages and durations to the minimum required. Monitor patients closely for signs of respiratory depression and sedation [see WARNINGS] .
Examples: Benzodiazepines and other sedatives/hypnotics, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, gabapentinoids [gabapentin or pregabalin], and other opioids, alcohol. Inhibitors of CYP3A4 Clinical Impact: The concomitant use of buprenorphine and CYP3A4 inhibitors can increase the plasma concentration of buprenorphine, resulting in increased or prolonged opioid effects, particularly when an inhibitor is added after a stable dose of buprenorphine is achieved. After stopping a CYP3A4 inhibitor, as the effects of the inhibitor decline, the buprenorphine plasma concentration will decrease [see CLINICAL PHARMACOLOGY: Pharmacokinetics], potentially resulting in decreased opioid efficacy or a withdrawal syndrome in patients who had developed physical dependence to buprenorphine.
Intervention: If concomitant use is necessary, consider dosage reduction of buprenorphine until stable… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
Pharmacokinetics The limits of sensitivity of available analytical methodology precluded demonstration of bioequivalence between intramuscular and intravenous routes of administration. Elimination In postoperative adults, pharmacokinetic studies have shown elimination half-lives ranging from 1.2 to 7.2 hours (mean 2.2 hours) after intravenous administration of 0.3 mg of buprenorphine. A single, ten-patient, pharmacokinetic study of doses of 3 μg/kg in children (age 5 to 7 years) showed a high inter-patient variability, but suggests that the clearance of the drug may be higher in children than in adults.
This is supported by at least one repeat-dose study in postoperative pain that showed an optimal inter-dose interval of 4 to 5 hours in pediatric patients as opposed to the recommended 6 to 8 hours in adults. Metabolism Buprenorphine undergoes both N-dealkylation to norbuprenorphine and glucuronidation. The N-dealkylation pathway is mediated primarily by CYP3A4.
Norbuprenorphine, the major metabolite, can further undergo glucuronidation. Its clearance is related to hepatic blood flow. Studies in patients anesthetized with 0.5% halothane have shown that this anesthetic decreases hepatic blood flow by about 30%.
🧬 Pharmacodynamics ▾
Pharmacodynamics Buprenorphine hydrochloride is a parenteral opioid analgesic with 0.3 mg buprenorphine being approximately equivalent to 10 mg morphine sulfate in analgesic and respiratory depressant effects in adults. Pharmacological effects occur as soon as 15 minutes after intramuscular injection and persist for 6 hours or longer. Peak pharmacologic effects usually are observed at 1 hour.
When used intravenously, the times to onset and peak effect are shortened. Buprenorphine demonstrates narcotic antagonist activity and has been shown to be equipotent with naloxone as an antagonist of morphine in the mouse tail flick test. Effect s on the Central Nervous System The principal action of therapeutic value of buprenorphine is analgesia and is thought to be due to buprenorphine binding with high affinity to opioid receptors on neurons in the brain and spinal cord.
Buprenorphine produces respiratory depression by direct action on brain stem respiratory centers. The respiratory depression involves a reduction in the responsiveness of the brain stem respiratory centers to both increases in carbon dioxide tension and electrical stimulation. Under usual conditions of use in adults, both buprenorphine and morphine show similar dose-related respiratory depressant effects.
At adult therapeutic doses, buprenorphine (0.3 mg buprenorphine) can decrease respiratory rate in an equivalent manner to an equianalgesic dose of morphine (10 mg). [see WARNINGS ]. Buprenorphine causes miosis, even in total darkness. Pinpoint pupils are a sign of opioid overdose but are not pathognomonic (e.g., pontine lesions of hemorrhagic or ischemic origins may produce similar findings).
Marked mydriasis rather than miosis may be seen due to hypoxia in overdose situations. Effects on the Gastrointestinal Tract and Other Smooth Muscle Buprenorphine causes a reduction in motility associated with an increase in smooth muscle tone in the antrum of the stomach and duodenum. Digestion of food in the small intestine is delayed and propulsive contractions are decreased.
Propulsive peristaltic waves in the colon are decreased, while tone is increased to the point of spasm, resulting in constipation. Other opioid-induced effects may include a reduction in biliary and pancreatic secretions, spasm of sphincter of Oddi, transient elevations in serum amylase, and opioid-induced esophageal dysfunction (OIED). Effec ts on the Cardiovascular System Buprenorphine produces peripheral vasodilation, which may result in orthostatic hypotension or syncope.
Manifestations of histamine release and/or peripheral vasodilation may include pruritus, flushing, red eyes, sweating, and/or orthostatic hypotension. Buprenorphine may cause a decrease or, rarely, an increase in pulse rate and blood pressure in some patients. Thorough QT studies with buprenorphine products have demonstrated QT prolongation ≤ 15 msec.
Effects on the Endocrine System Opioids inhibit the secretion of adrenocorticotropic hormone (ACTH), cortisol, and luteinizing hormone (LH) in humans. They also stimulate prolactin, growth hormone (GH) secretion, and pancreatic secretion of insulin and glucagon. Use of opioids for an extended period of time may influence the hypothalamic-pituitary-gonadal axis, leading to androgen deficiency that may manifest as low libido, impotence, erectile dysfunction, amenorrhea, or infertility.
The causal role of opioids in the clinical syndrome of hypogonadism is unknown because the various medical, physical, lifestyle, and psychological stressors that may influence gonadal hormone levels have not been adequately controlled for in studies conducted to date. Effects on the Immune System Opioids have been shown to have a variety of effects on components of the immune system in in vitro and animal models. The clinical significance of these findings is unknown.
Overall, the effects of opioids appear to be modestly immunosuppressive. Concentration–Efficacy Relationships The minimum effective analges… [Excerpted — this section continues on DailyMed.]
🔒 Drug Abuse and Dependence ▾
DRUG ABUSE AND DEPENDENCE Controlled Substance Buprenorphine hydrochloride injection contains buprenorphine, a Schedule III controlled substance. Abuse Buprenorphine hydrochloride injection contains buprenorphine, a substance with high potential for misuse and abuse, which can lead to the development of substance use disorder, including addiction [see WARNINGS ]. Misuse is the intentional use, for therapeutic purposes, of a drug by an individual in a way other than prescribed by a healthcare provider or for whom it was not prescribed.
Abuse is the intentional, non-therapeutic use of a drug, even once, for its desirable psychological or physiological effects. Drug addiction is a cluster of behavioral, cognitive, and physiological phenomena that may include a strong desire to take the drug, difficulties in controlling drug use (e.g., continuing drug use despite harmful consequences, giving a higher priority to drug use than other activities and obligations), and possible tolerance or physical dependence. Misuse and abuse of Buprenorphine increases risk of overdose, which may lead to central nervous system and respiratory depression, hypotension, seizures, and death.
The risk is increased with concurrent abuse of Buprenorphine with alcohol and/or other CNS depressants. Abuse of and addiction to opioids in some individuals may not be accompanied by concurrent tolerance and symptoms of physical dependence. In addition, abuse of opioids can occur in the absence of addiction.
All patients treated with opioids require careful and frequent reevaluation for signs of misuse, abuse, and addiction, because use of opioid analgesic products carries the risk of addiction even under appropriate medical use. Patients at high risk of buprenorphine abuse include those with a history of prolonged use of any opioid, including products containing buprenorphine, those with drug or alcohol abuse, or those who use Buprenorphine in combination with other abused drugs. "Drug-seeking" behavior is very common in persons with substance use disorders.
Drug-seeking tactics include emergency calls or visits near the end of office hours, refusal to undergo appropriate examination, testing, or referral, repeated “loss” of prescriptions, tampering with prescriptions, and reluctance to provide prior medical records or contact information for other treating healthcare provider(s). “Doctor shopping” (visiting multiple prescribers to obtain additional prescriptions) is common among people who abuse drugs and people with substance use disorder. Preoccupation with achieving adequate pain relief can be appropriate behavior in a patient with inadequate pain control.
Buprenorphine, like other opioids, can be diverted for nonmedical use into illicit channels of distribution. Careful record-keeping of prescribing information, including quantity, frequency, and renewal requests, as required by state and federal law, is strongly advised. Proper assessment of the patient, proper prescribing practices, periodic reevaluation of therapy, and proper dispensing and storage are appropriate measures that help to limit abuse of opioid drugs.
Risks Specific to Abuse of Buprenorphine Abuse of buprenorphine poses a risk of overdose and death. The risk is increased with concurrent abuse of buprenorphine with alcohol and/or other CNS depressants. Parenteral drug abuse is commonly associated with transmission of infectious diseases such as hepatitis and HIV.
Dependence Both tolerance and physical dependence can develop during use of opioid therapy. Tolerance is a physiological state characterized by a reduced response to a drug after repeated administration (i.e., a higher dose of a drug is required to produce the same effect that was once obtained at a lower dose). Physical dependence is a state that develops as a result of a physiological adaptation in response to repeated drug use, manifested by withdrawal signs and symptoms after abrupt discontinuation or a significant dose reduction of… [Excerpted — this section continues on DailyMed.]
🔒 Controlled Substance ▾
Controlled Substance Buprenorphine hydrochloride injection contains buprenorphine, a Schedule III controlled substance.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis and Impairment of Fertility Carcinogenesis Carcinogenicity studies were conducted in Sprague-Dawley rats and CD-1 mice. Buprenorphine was administered in the diet at doses of 0.6, 5.5, and 56 mg/kg/day for 27 months in rats. These doses were approximately equivalent to 5.7, 52, and 534 times the recommended human dose (1.2 mg) on a mg/m 2 body surface area basis.
Statistically significant dose-related increases in testicular interstitial (Leydig's) cell tumors occurred, according to the trend test adjusted for survival. Pairwise comparison of the high dose against control failed to show statistical significance. In the mouse study, buprenorphine was administered in the diet at doses of 8, 50, and 100 mg/kg/day for 86 weeks.
The high dose was approximately equivalent to 477 times the recommended human dose (1.2 mg) on a mg/m 2 basis. Buprenorphine was not carcinogenic in mice. Mutagenesis Buprenorphine was studied in a series of tests.
Results were negative in Chinese hamster bone marrow and spermatogonia cells, and negative in mouse lymphoma L5178Y assay. Results were equivocal in the Ames test: negative in studies in two laboratories, but positive in frame shift mutation at high dose (5 mg/plate) in a third study. Impairment of Fertility Reproduction studies of buprenorphine in rats demonstrated no evidence of impaired fertility at daily oral doses up to 80 mg/kg (approximately 763 times the recommended human daily dose of 1.2 mg on a mg/m 2 basis) or up to 5 mg/kg I.M. or S.C.
(approximately 48 times the recommended human daily dose of 1.2 mg on a mg/m 2 basis).
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 0.3 mg/mL Vial Carton NDC 42023- 179 -05 Rx Only Buprenorphine Hydrochloride, Injection 0.3 mg/mL* CIII For Intramuscular or Intravenous Use 5 x 1 mL Single Dose Vials 5 x 1 mL Single Dose Vials
Medicaid utilization & spend
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |