
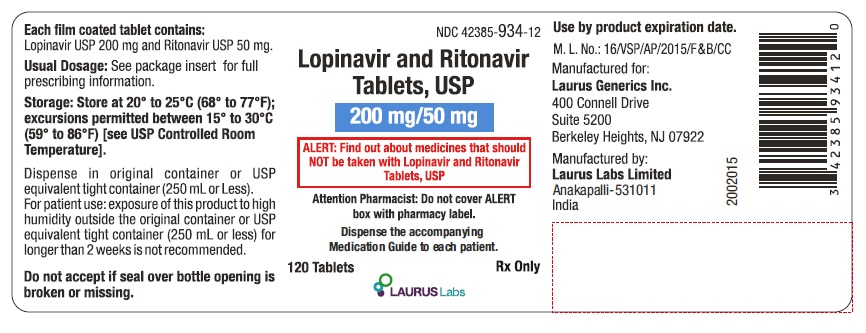
Lopinavir and Ritonavir 200 mg; 50 mg Tablet, Film Coated, 120-count — NDC 42385-934-12 (Billing 42385-0934-12)
This is a package of 120 tablets of Lopinavir and Ritonavir 200 mg; 50 mg Tablet, Film Coated from Laurus Labs Limited, marketed since Mar 2022 and currently FDA-listed; retail pharmacies pay about $4.46 per tablet (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 42385-934-12 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 42385 labeler · 934 product · 12 package
- Package marketed since
- Mar 22, 2022
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 120 EA per package
- Barcode (UPC)
- 0342385933604
- Medicaid fills, this package
- 41 prescriptions in the last four reported quarters
- FDA record last changed
- Oct 1, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 059972
- GCN: 25919
- GPI-14 (Medi-Span): 12109902550320
- HICL (First Databank): 021582
- AHFS class code: 08:18.08.08
- RxCUI (RxNorm): 597730
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Protease Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
The combination of lopinavir and ritonavir is used to treat human immunodeficiency virus (HIV) infection. Lopinavir and ritonavir are in a class of medications called protease inhibitors. They work by decreasing the amount of HIV in the blood. When lopinavir and ritonavir are taken together, ritonavir also helps to increase the amount of lopinavir in the body to have a greater effect. Although lopinavir and ritonavir will not cure HIV, these medications may decrease your chance of developing acquired immunodeficiency syndrome (AIDS) and HIV-related illnesses. Taking these medications and makin...
Read the full MedlinePlus article ↗- Lopinavir and ritonavir attacks HIV at a specific step in its life cycle. The virus needs an enzyme called protease to cut proteins into shapes it can use to build new, infectious...
- What exactly is this medication doing for my HIV?
- If you're taking the tablet form (Kaletra tablets or the generic lopinavir and ritonavir tablets), you can take it with or without food — that's flexible. Just be sure to swallow t...
- Does it matter when I take my tablets — do I have to take them with food?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $4.465 | $535.79 / 120 tablets |
| Medicaid paysCMS SDUD · 12 mo | $4.93 | $591.67 / 120 tablets |
| Medicare drug plans payPart D · Q2 2026 | $5.90 | $707.48 / 120 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 42385-0934-12 You're viewing this Main listing | 120 TABLET, FILM COATED in 1 BOTTLE | 2022-03-22 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lopinavir and ritonavir 200 mg/1; 50 mg 31722-0556-12 | Camber | 120 tablets | $4.465 | AB | Availability likely | — |
| Lopinavir and Ritonavir 200 mg/1; 50 mgthis 42385-0934-12 | Laurus | 120 tablets | $4.465 | AB | Availability likely | — |
| Kaletra 200 mg/1; 50 mg 00074-6799-22 | AbbVie | 120 tablets | $8.261 | AB | Discontinued | +85% |
| Kaletra 200 mg/1; 50 mg 00074-4014-12 | AbbVie | 120 tablets | — | AB | FDA listed | — |
| Lopinavir and Ritonavir 200 mg/1; 50 mg 33342-0164-09 | Macleods | 60 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII D9C330MD8B
Copovidone is a synthetic polymer made by combining two types of plastic-like molecules. It acts as a binder and film-former to help hold tablet ingredients together and improve how the medicine dissolves in your body.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 9XZ8H6N6OH
A plant-based cellulose derivative used as a binder to hold tablet ingredients together, a thickener in liquids, and a coating agent to control how fast the medicine dissolves.
-
UNII 36SFW2JZ0W
Hypromellose 2910 is a plant-based thickening agent derived from cellulose. In medicines, it forms a protective coating on tablets or capsules and controls how quickly the drug dissolves and releases into your body.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII G2M7P15E5P
Polyethylene glycol 3350 is a synthetic polymer used as a solvent, humectant, and thickening agent in medicines. It helps dissolve other ingredients, retain moisture in the product, and achieve the desired consistency.
-
UNII B697894SGQ
Polyethylene glycol 400 is a clear, thick liquid made from petroleum-derived polymers. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7CV7WJK4UI
Sodium stearyl fumarate is a synthetic compound made from stearyl alcohol and fumaric acid. It acts as a lubricant and glidant in tablets and capsules, helping ingredients flow smoothly during manufacturing and preventing sticking.
-
UNII 6W9PS8B71J
Sorbitan monolaurate is a natural oil-derived emulsifier made from sorbitol and lauric acid. It helps mix oils and water-based ingredients together in the medicine so the formula stays uniform and smooth.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
13 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Laurus Labs Limited labeler code 42385
- Efavirenz, Lamivudine and Tenofovir Disoproxil Fumarate 600 mg; 300 mg; 300 mg Tablet, Film Coated NDC 42385-928-30
- Efavirenz, Lamivudine and Tenofovir Disoproxil Fumarate 400 mg; 300 mg; 300 mg Tablet, Film Coated NDC 42385-929-18
- Sacubitril and Valsartan 24 mg; 26 mg Tablet, Film Coated NDC 42385-930-18
- Sacubitril and Valsartan 49 mg; 51 mg Tablet, Film Coated NDC 42385-931-18
- Sacubitril and Valsartan 97 mg; 103 mg Tablet, Film Coated NDC 42385-932-18
- Lopinavir and Ritonavir 100 mg; 25 mg Tablet, Film Coated NDC 42385-933-60
- Fenofibrate 54 mg Tablet, Film Coated NDC 42385-935-05
- Fenofibrate 160 mg Tablet, Film Coated NDC 42385-936-05
- Atorvastatin Calcium 10 mg Tablet, Film Coated NDC 42385-940-01
- Atorvastatin Calcium 20 mg Tablet, Film Coated NDC 42385-941-01
- Atorvastatin Calcium 40 mg Tablet, Film Coated NDC 42385-942-01
- Atorvastatin Calcium 80 mg Tablet, Film Coated NDC 42385-943-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Lopinavir and ritonavir is indicated in combination with other antiretroviral agents for the treatment of HIV- 1 infection in adults and pediatric patients 14 days and older. Limitations of Use: Genotypic or phenotypic testing and/or treatment history should guide the use of lopinavir and ritonavir. The number of baseline lopinavir resistance-associated substitutions affects the virologic response to lopinavir and ritonavir [ see Microbiology (12.4) ] .
Lopinavir and ritonavir is an HIV-1 protease inhibitor indicated in combination with other antiretroviral agents for the treatment of HIV-1 infection in adults and pediatric patients (14 days and older). ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Tablets: May be taken with or without food, swallowed whole and not chewed, broken, or crushed. ( 2.1 ) Oral solution: must be taken with food. ( 2.1 ) Adults ( 2.3 ): Total recommended daily dosage is 800/200 mg given once or twice daily.
Lopinavir and ritonavir can be given as once daily or twice daily regimen. See Full Prescribing Information for details. Lopinavir and ritonavir once daily dosing regimen is not recommended in: Adult patients with three or more of the following lopinavir resistance-associated substitutions: L10F/I/R/V, K20M/N/R, L24I, L33F, M36I, I47V, G48V, I54L/T/V, V82A/C/F/S/T, and I84V.
( 12.4 ) In combination with carbamazepine, phenobarbital, or phenytoin. ( 7.3 ) In combination with efavirenz, nevirapine, or nelfinavir. ( 12.3 ) In pregnant women.
( 2.5 , 8.1 , 12.3 ) Pediatric Patients (14 days and older) ( 2.4 ): Lopinavir and ritonavir once daily dosing regimen is not recommended in pediatric patients. Twice daily dose is based on body weight or body surface area. Concomitant Therapy in Adults and Pediatric Patients: Dose adjustments of lopinavir and ritonavir may be needed when co-administering with efavirenz, nevirapine, or nelfinavir.
( 2.3 , 2.4 , 7.3 ) Lopinavir and ritonavir oral solution should not be administered to neonates before a postmenstrual age (first day of the mother’s last menstrual period to birth plus the time elapsed after birth) of 42 weeks and a postnatal age of at least 14 days has been attained ( 2.4 , 5.2 ) Pregnancy ( 2.5 ): 400/100 mg twice daily in pregnant patients with no documented lopinavir-associated resistance substitutions. There are insufficient data to recommend a lopinavir and ritonavir dose for pregnant patients with any documented lopinavir and ritonavir-associated resistance substitutions.
No dose adjustment of lopinavir and ritonavir is required for patients during the postpartum period.
2.1General Administration Recommendations Lopinavir and ritonavir tablets may be taken with or without food. The tablets should be swallowed whole and not chewed, broken, or crushed. Lopinavir and ritonavir oral solution must be taken with food.
2.3Dosage Recommendations in Adults Lopinavir and ritonavir can be given in once daily or twice daily dosing regimen at dosages noted in Tables 1 and 2. Lopinavir and ritonavir once daily dosing regimen is not recommended in: Adult patients with three or more of the following lopinavir resistance-associated substitutions: L10F/I/R/V, K20M/N/R, L24I, L33F, M36I, I47V, G48V, I54L/T/V, V82A/C/F/S/T, and I84V [ see Microbiology (12.4) ] . In combination with carbamazepine, phenobarbital, or phenytoin [ see Drug Interactions (7.3) ] .
In combination with efavirenz, nevirapine, or nelfinavir [ see Drug Interactions (7.3) and Clinical Pharmacology (12.3) ] . In pediatric patients younger than 18 years of age [ see Dosage and Administration (2.4) ] . In pregnant women [ see Dosage and Administration (2.5) , Use in Specific Populations (8.1) and Clinical Pharmacology (12.3) ] .
Table 1. Recommended Dosage in Adults - Lopinavir and Ritonavir Once Daily Regimen Lopinavir and Ritonavir Dosage Form Recommended Dosage 200 mg/50 mg Tablets 800 mg/200 mg (4 tablets) once daily 80 mg/20 mg per mL Oral Solution 800 mg/200 mg (10 mL) once daily Table 2. Recommended Dosage in Adults - Lopinavir and Ritonavir Twice Daily Regimen Lopinavir and Ritonavir Dosage Form Recommended Dosage 200 mg/50 mg Tablets 400 mg/100 mg (2 tablets) twice daily 80 mg/20 mg per mL Oral Solution 400 mg/100 mg (5 mL) twice daily The dose of lopinavir and ritonavir must be increased when administered in combination with efavirenz, nevirapine or nelfinavir.
Table 3 outlines the dosage recommendations for twice daily dosing when lopinavir and ritonavir is taken in combination with these agents. Table 3. Recommended Dosage in Adults - Lopinavir and Ritonavir Twice Daily Regimen in Combination with Efavirenz, Nevirapine, or Nelfinavir Lopinavir and R… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: Lopinavir and Ritonavir Tablets USP, 200 mg/50 mg : Yellow colored, film coated oval shaped biconvex tablets debossed with “LA58” on one side and plain on other side. Lopinavir and Ritonavir Tablets USP, 100 mg/25 mg : Yellow colored, film coated oval shaped biconvex tablets debossed with “LA59” on one side and plain on other side. Tablets: 200 mg lopinavir and 50 mg ritonavir ( 3 ) Tablets: 100 mg lopinavir and 25 mg ritonavir ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Lopinavir and ritonavir is contraindicated in patients with previously demonstrated clinically significant hypersensitivity (e.g., toxic epidermal necrolysis, Stevens-Johnson syndrome, erythema multiforme, urticaria, angioedema) to any of its ingredients, including ritonavir. Lopinavir and ritonavir is contraindicated with drugs that are highly dependent on CYP3A for clearance and for which elevated plasma concentrations are associated with serious and/or life-threatening reactions [see Drug Interactions (7.1) and Clinical Pharmacology (12.3) ] . ○ Alpha 1- Adrenoreceptor Antagonist : alfuzosin ○ Antianginal: ranolazine ○ Antiarrhythmic: dronedarone ○ Anti-gout: colchicine ○ Antipsychotics: lurasidone, pimozide ○ Ergot Derivatives: dihydroergotamine, ergotamine, methylergonovine ○ GI Motility Agent: cisapride ○ Hepatitis C direct acting antiviral: elbasvir/grazoprevir ○ HMG-CoA Reductase Inhibitors: lovastatin, simvastatin ○ Microsomal triglyceride transfer protein (MTTP) Inhibitor: lomitapide ○ PDE5 Inhibitor: sildenafil (Revatio ® ) when used for the treatment of pulmonary arterial hypertension ○ Sedative/Hypnotics: triazolam, orally administered midazolam Lopinavir and ritonavir is contraindicated with drugs that are potent CYP3A inducers where significantly reduced lopinavir plasma concentrations may be associated with the potential for loss of virologic response and possible resistance and cross-resistance [see Drug Interactions (7.2) and Clinical Pharmacology (12.3) ]. ○ Anticancer Agents: apalutamide ○ Antimycobacterial: rifampin ○ Herbal Products: St.
John's Wort (hypericum perforatum) Hypersensitivity to lopinavir and ritonavir (e.g., toxic epidermal necrolysis, Stevens-Johnson syndrome, erythema multiforme, urticaria, angioedema) or any of its ingredients, including ritonavir. ( 4 ) Co-administration with drugs highly dependent on CYP3A for clearance and for which elevated plasma levels may result in serious and/or life-threatening events. ( 4 ) Co-administration with potent CYP3A inducers where significantly reduced lopinavir plasma concentrations may be associated with the potential for loss of virologic response and possible resistance and cross resistance.
( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS The following have been observed in patients receiving lopinavir and ritonavir: The concomitant use of lopinavir and ritonavir and certain other drugs may result in known or potentially significant drug interactions. Consult the full prescribing information prior to and during treatment for potential drug interactions. ( 5.1 , 7.3 ) Toxicity in preterm neonates: Lopinavir and ritonavir oral solution should not be used in preterm neonates in the immediate postnatal period because of possible toxicities.
A safe and effective dose of lopinavir and ritonavir oral solution in this patient population has not been established. ( 2.4 , 5.2 ) Pancreatitis: Fatalities have occurred; suspend therapy as clinically appropriate. ( 5.3 ) Hepatotoxicity: Fatalities have occurred.
Monitor liver function before and during therapy, especially in patients with underlying hepatic disease, including hepatitis B and hepatitis C, or marked transaminase elevations. ( 5.4 , 8.6 ) QT interval prolongation and isolated cases of torsade de pointes have been reported although causality could not be established. Avoid use in patients with congenital long QT syndrome, those with hypokalemia, and with other drugs that prolong the QT interval.
( 5.1 , 5.5 , 12.3 ) PR interval prolongation may occur in some patients. Cases of second and third degree heart block have been reported. Use with caution in patients with pre-existing conduction system disease, ischemic heart disease, cardiomyopathy, underlying structural heart disease or when administering with other drugs that may prolong the PR interval.
( 5.1 , 5.6 , 12.3 ) Patients may develop new onset or exacerbations of diabetes mellitus, hyperglycemia ( 5.7 ), immune reconstitution syndrome ( 5.8 ), redistribution/accumulation of body fat. ( 5.10 ) Total cholesterol and triglycerides elevations. Monitor prior to therapy and periodically thereafter.
( 5.9 ) Hemophilia: Spontaneous bleeding may occur, and additional factor VIII may be required. ( 5.11 )
5.1Risk of Serious Adverse Reactions Due to Drug Interactions Initiation of lopinavir and ritonavir, a CYP3A inhibitor, in patients receiving medications metabolized by CYP3A or initiation of medications metabolized by CYP3A in patients already receiving lopinavir and ritonavir, may increase plasma concentrations of medications metabolized by CYP3A. Initiation of medications that inhibit or induce CYP3A may increase or decrease concentrations of lopinavir and ritonavir, respectively. These interactions may lead to: Clinically significant adverse reactions, potentially leading to severe, life-threatening, or fatal events from greater exposures of concomitant medications.
Clinically significant adverse reactions from greater exposures of lopinavir and ritonavir. Loss of therapeutic effect of lopinavir and ritonavir and possible development of resistance. See Table 12 for steps to prevent or manage these possible and known significant drug interactions, including dosing recommendations [ see Drug Interactions (7) ] .
Consider the potential for drug interactions prior to and during lopinavir and ritonavir therapy; review concomitant medications during lopinavir and ritonavir therapy, and monitor for the adverse reactions associated with the concomitant medications [ see Contraindications (4) and Drug Interactions (7) ] .
5.2Toxicity in Preterm Neonates Lopinavir and ritonavir oral solution contains the excipients ethanol, approximately 42% (v/v) and propylene glycol, approximately 15% (w/v). When administered concomitantly with propylene glycol, ethanol competitively inhibits the metabolism of propylene glycol, which may lead to elevated concentrations. Preterm neonates may be at increased risk of propylene glycol-associated adverse events due to diminished ability to metabolize propylene glycol, thereby leading to accumulation and potential adverse events.
Postmarketing life-threatening cases of cardiac toxicity (including complete AV bl… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the labeling. QT Interval Prolongation, PR Interval Prolongation [ see Warnings and Precautions (5.5 , 5.6 )] Drug Interactions [ see Warnings and Precautions (5.1) ] Pancreatitis [ see Warnings and Precautions (5.3) ] Hepatotoxicity [ see Warnings and Precautions (5.4) ] Commonly reported adverse reactions to lopinavir and ritonavir included diarrhea, nausea, vomiting, hypertriglyceridemia and hypercholesterolemia.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Laurus Generics Inc. at 1-833-3-LAURUS (1-833-352-8787) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reactions rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Adverse Reactions in Adults The safety of lopinavir and ritonavir has been investigated in about 2,600 patients in Phase II to IV clinical trials, of which about 700 have received a dose of 800/200 mg (6 capsules or 4 tablets) once daily.
Along with nucleoside reverse transcriptase inhibitors (NRTIs), in some studies, lopinavir and ritonavir was used in combination with efavirenz or nevirapine. In clinical studies the incidence of diarrhea in patients treated with either lopinavir and ritonavir capsules or tablets was greater in those patients treated once daily than in those patients treated twice daily. Any grade of diarrhea was reported by at least half of patients taking once daily lopinavir and ritonavir capsules or tablets.
At the time of treatment discontinuation, 4.2 to 6.3% of patients taking once daily lopinavir and ritonavir and 1.8 to 3.7% of those taking twice daily lopinavir and ritonavir reported ongoing diarrhea. Commonly reported adverse reactions to lopinavir and ritonavir included diarrhea, nausea, vomiting, hypertriglyceridemia and hypercholesterolemia. Diarrhea, nausea and vomiting may occur at the beginning of the treatment while hypertriglyceridemia and hypercholesterolemia may occur later.
The following have been identified as adverse reactions of moderate or severe intensity (Table 8): Table 8. Adverse Reactions of Moderate or Severe Intensity Occurring in at Least 0.1% of Adult Patients Receiving Lopinavir and Ritonavir in Combined Phase II/IV Studies (N=2,612) System Organ Class (SOC) and Adverse Reaction n % BLOOD AND LYMPHATIC SYSTEM DISORDERS anemia* 54 2.1 leukopenia and neutropenia* 44 1.7 lymphadenopathy* 35
1.3CARDIAC DISORDERS atherosclerosis such as myocardial infarction* 10 0.4 atrioventricular block* 3 0.1 tricuspid valve incompetence* 3
0.1EAR AND LABYRINTH DISORDERS vertigo* 7 0.3 tinnitus 6
0.2ENDOCRINE DISORDERS hypogonadism* 16 0.8 1 EYE DISORDERS visual impairment* 8
0.3GASTROINTESTINAL DISORDERS diarrhea* 510 19.5 nausea 269 10.3 vomiting* 177 6.8 abdominal pain (upper and lower)* 160 6.1 gastroenteritis and colitis* 66 2.5 dyspepsia 53 2 pancreatitis* 45
1.7Gastroesophageal Reflux Disease (GERD)* 40 1.5 hemorrhoids 39 1.5 flatulence 36 1.4 abdominal distension 34 1.3 constipation* 26 1 stomatitis and oral ulcers* 24 0.9 duodenitis and gastritis* 20 0.8 gastrointestinal hemorrhage including rectal hemorrhage* 13 0.5 dry mouth 9 0.3 gastrointestinal ulcer* 6 0.2 fecal incontinence 5
0.2 GENERAL DISORDERS AND ADMINISTRATION SITE CONDITIONS fatigue including asthenia* 198
7.6HEPATOBILIARY DISORDERS hepatitis including AST, ALT, and GGT increases* 91 3.5 hepatomegaly 5 0.2 cholangitis 3 0.1 hepatic steatosis 3
0.1IMMUNE SYSTEM DISORDERS hypersensitivity including urticaria and angioedema* 70 2.7 immune reconstitution syndrome 3
0.1INFECTIONS AND INFESTATIONS upper respiratory tract infection* 363 13.9 lower respiratory tract infection* 202 7.7 skin infections including cellulitis, folliculitis, and furuncl… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Co-administration of lopinavir and ritonavir can alter the plasma concentrations of other drugs and other drugs may alter the plasma concentrations of lopinavir. The potential for drug-drug interactions must be considered prior to and during therapy. ( 4 , 5.1 , 7 , 12.3 )
7.1Potential for Lopinavir and Ritonavir to Affect Other Drugs Lopinavir/ritonavir is an inhibitor of CYP3A and may increase plasma concentrations of agents that are primarily metabolized by CYP3A. Agents that are extensively metabolized by CYP3A and have high first pass metabolism appear to be the most susceptible to large increases in AUC (>3-fold) when co-administered with lopinavir and ritonavir. Thus, co-administration of lopinavir and ritonavir with drugs highly dependent on CYP3A for clearance and for which elevated plasma concentrations are associated with serious and/or life-threatening events is contraindicated.
Co-administration with other CYP3A substrates may require a dose adjustment or additional monitoring as shown in Table 12. Additionally, lopinavir and ritonavir induces glucuronidation. Published data suggest that lopinavir is an inhibitor of OATP1B1.
These examples are a guide and not considered a comprehensive list of all possible drugs that may interact with lopinavir/ritonavir. The healthcare provider should consult appropriate references for comprehensive information.
7.2Potential for Other Drugs to Affect Lopinavir Lopinavir/ritonavir is a CYP3A substrate; therefore, drugs that induce CYP3A may decrease lopinavir plasma concentrations and reduce lopinavir and ritonavir’s therapeutic effect. Although not observed in the lopinavir and ritonavir/ketoconazole drug interaction study, co-administration of lopinavir and ritonavir and other drugs that inhibit CYP3A may increase lopinavir plasma concentrations.
7.3Established and Other Potentially Significant Drug Interactions Table 12 provides a listing of established or potentially clinically significant drug interactions. Alteration in dose or regimen may be recommended based on drug interaction studies or predicted interaction [see Contraindications (4) , Warnings and Precautions (5.1) , Clinical Pharmacology (12.3) ] for magnitude of interaction. Table 12.
Established and Other Potentially Significant Drug Interactions Concomitant Drug Class: Drug Name Effect on Concentration of Lopinavir or Concomitant Drug Clinical Comments HIV-1 Antiviral Agents HIV-1 Protease Inhibitor: fosamprenavir/ritonavir ↓ amprenavir ↓ lopinavir An increased rate of adverse reactions has been observed with co-administration of these medications. Appropriate doses of the combinations with respect to safety and efficacy have not been established. HIV-1 Protease Inhibitor: indinavir* ↑ indinavir Decrease indinavir dose to 600 mg twice daily, when co-administered with lopinavir and ritonavir 400/100 mg twice daily.
Lopinavir and ritonavir once daily has not been studied in combination with indinavir. HIV-1 Protease Inhibitor: nelfinavir* ↑ nelfinavir ↑ M8 metabolite of nelfinavir ↓ lopinavir Lopinavir and ritonavir once daily in combination with nelfinavir is not recommended [see Dosage and Administration (2) ] . HIV-1 Protease Inhibitor: ritonavir* ↑ lopinavir Appropriate doses of additional ritonavir in combination with lopinavir and ritonavir with respect to safety and efficacy have not been established.
HIV-1 Protease Inhibitor: saquinavir ↑ saquinavir The saquinavir dose is 1,000 mg twice daily, when co-administered with lopinavir and ritonavir 400/100 mg twice daily. Lopinavir and ritonavir once daily has not been studied in combination with saquinavir. HIV-1 Protease Inhibitor: tipranavir* ↓ lopinavir Co-administration with tipranavir (500 mg twice daily) and ritonavir (200 mg twice daily) is not recommended.
HIV CCR5 – Antagonist: maraviroc* ↑ maraviroc When co-administered, patients should receive 150 mg twice daily of maraviroc. For further details see complete prescribing informatio… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Breastfeeding not recommended. ( 8.2 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to lopinavir and ritonavir during pregnancy. Physicians are encouraged to register patients by calling the Antiretroviral Pregnancy Registry at 1-800-258-4263. Risk Summary Available data from the Antiretroviral Pregnancy Registry show no difference in the risk of overall major birth defects compared to the background rate for major birth defects of 2.7% in the U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP) (see Data) .
The estimated background rate of miscarriage in clinically recognized pregnancies in the U.S. general population is 15 to 20%. The background risk for major birth defects and miscarriage for the indicated population is unknown. Methodological limitations of the APR include the use of MACDP as the external comparator group.
The MACDP population is not disease-specific, evaluates women and infants from a limited geographic area, and does not include outcomes for births that occurred at <20 weeks gestation (see Data) . No treatment- related malformations were observed when lopinavir in combination with ritonavir was administered to pregnant rats or rabbits; however embryonic and fetal developmental toxicities occurred in rats administered maternally toxic doses. Clinical Considerations Dose Adjustments During Pregnancy and the Postpartum Period Administer 400/100 mg of lopinavir and ritonavir twice daily in pregnant patients with no documented lopinavir-associated resistance substitutions [see Dosage and Administration (2.5) and Clinical Pharmacology (12.3) ] .
There are insufficient data to recommend lopinavir and ritonavir dosing for pregnant patients with any documented lopinavir-associated resistance substitutions. No dose adjustment of lopinavir and ritonavir is required for patients during the postpartum period. Once daily lopinavir and ritonavir dosing is not recommended in pregnancy.
Avoid use of lopinavir and ritonavir oral solution during pregnancy due to the ethanol content. lopinavir and ritonavir oral solution contains the excipients ethanol, approximately 42% (v/v and propylene glycol, approximately 15%. Data Human Data Lopinavir and ritonavir was evaluated in 12 HIV-infected pregnant women in an open-label pharmacokinetic trial [see Clinical Pharmacology (12.3) ] . No new trends in the safety profile were identified in pregnant women dosed with lopinavir and ritonavir compared to the safety described in non-pregnant adults, based on the review of these limited data.
Antiretroviral Pregnancy Registry Data: Based on prospective reports from the Antiretroviral Pregnancy Registry (APR) of over 3,000 exposures to lopinavir containing regimens (including over 1,000 exposed in the first trimester), there was no difference between lopinavir and overall birth defects compared with the background birth defect rate of 2.7% in the U.S. reference population of the Metropolitan Atlanta Congenital Defects Program. The prevalence of birth defects in live births was 2.1% (95% CI: 1.4% to 3%) following first-trimester exposure to lopinavir-containing regimens and 3% (95% CI: 2.4% to 3.8%) following second and third trimester exposure to lopinavir-containing regimens.
Based on prospective reports from the APR of over 5,000 exposures to ritonavir containing regimens (including over 2,000 exposures in the first trimester) there was no difference between ritonavir and overall birth defects compared with the U.S. background rate (MACDP). The prevalence of birth defects in live births was 2.2% (95% CI: 1.7% to 2.8%) following first-trimester exposure to ritonavir-containing regimens and 2.9% (95% CI: 2.4% to 3.6%) following second and third trimester exposure to ritonavir- containing regimens.
For both lopinavir and ritonavir, sufficient numbers of first trimester exposures… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to lopinavir and ritonavir during pregnancy. Physicians are encouraged to register patients by calling the Antiretroviral Pregnancy Registry at 1-800-258-4263. Risk Summary Available data from the Antiretroviral Pregnancy Registry show no difference in the risk of overall major birth defects compared to the background rate for major birth defects of 2.7% in the U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP) (see Data) .
The estimated background rate of miscarriage in clinically recognized pregnancies in the U.S. general population is 15 to 20%. The background risk for major birth defects and miscarriage for the indicated population is unknown. Methodological limitations of the APR include the use of MACDP as the external comparator group.
The MACDP population is not disease-specific, evaluates women and infants from a limited geographic area, and does not include outcomes for births that occurred at <20 weeks gestation (see Data) . No treatment- related malformations were observed when lopinavir in combination with ritonavir was administered to pregnant rats or rabbits; however embryonic and fetal developmental toxicities occurred in rats administered maternally toxic doses. Clinical Considerations Dose Adjustments During Pregnancy and the Postpartum Period Administer 400/100 mg of lopinavir and ritonavir twice daily in pregnant patients with no documented lopinavir-associated resistance substitutions [see Dosage and Administration (2.5) and Clinical Pharmacology (12.3) ] .
There are insufficient data to recommend lopinavir and ritonavir dosing for pregnant patients with any documented lopinavir-associated resistance substitutions. No dose adjustment of lopinavir and ritonavir is required for patients during the postpartum period. Once daily lopinavir and ritonavir dosing is not recommended in pregnancy.
Avoid use of lopinavir and ritonavir oral solution during pregnancy due to the ethanol content. lopinavir and ritonavir oral solution contains the excipients ethanol, approximately 42% (v/v and propylene glycol, approximately 15%. Data Human Data Lopinavir and ritonavir was evaluated in 12 HIV-infected pregnant women in an open-label pharmacokinetic trial [see Clinical Pharmacology (12.3) ] . No new trends in the safety profile were identified in pregnant women dosed with lopinavir and ritonavir compared to the safety described in non-pregnant adults, based on the review of these limited data.
Antiretroviral Pregnancy Registry Data: Based on prospective reports from the Antiretroviral Pregnancy Registry (APR) of over 3,000 exposures to lopinavir containing regimens (including over 1,000 exposed in the first trimester), there was no difference between lopinavir and overall birth defects compared with the background birth defect rate of 2.7% in the U.S. reference population of the Metropolitan Atlanta Congenital Defects Program. The prevalence of birth defects in live births was 2.1% (95% CI: 1.4% to 3%) following first-trimester exposure to lopinavir-containing regimens and 3% (95% CI: 2.4% to 3.8%) following second and third trimester exposure to lopinavir-containing regimens.
Based on prospective reports from the APR of over 5,000 exposures to ritonavir containing regimens (including over 2,000 exposures in the first trimester) there was no difference between ritonavir and overall birth defects compared with the U.S. background rate (MACDP). The prevalence of birth defects in live births was 2.2% (95% CI: 1.7% to 2.8%) following first-trimester exposure to ritonavir-containing regimens and 2.9% (95% CI: 2.4% to 3.6%) following second and third trimester exposure to ritonavir- containing regimens.
For both lopinavir and ritonavir, sufficient numbers of first trimester exposures have been monitored to detect at least a 1.5 fold increase in risk of overall bi… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use The safety, efficacy, and pharmacokinetic profiles of lopinavir and ritonavir in pediatric patients below the age of 14 days have not been established. Lopinavir and ritonavir should not be administered once daily in pediatric patients. An open-label, multi-center, dose-finding trial was performed to evaluate the pharmacokinetic profile, tolerability, safety and efficacy of lopinavir and ritonavir oral solution containing lopinavir 80 mg/mL and ritonavir 20 mg/mL at a dose of 300/75 mg/m 2 twice daily plus two NRTIs in HIV-infected infants ≥14 days and < 6 months of age.
Results revealed that infants younger than 6 months of age generally had lower lopinavir AUC 12 than older children (6 months to 12 years of age), however, despite the lower lopinavir drug exposure observed, antiviral activity was demonstrated as reflected in the proportion of subjects who achieved HIV-1 RNA <400 copies/mL at Week 24 [see Adverse Reactions (6.2) , Clinical Pharmacology (12.3) , Clinical Studies (14.4) ] . Safety and efficacy in pediatric patients > 6 months of age was demonstrated in a clinical trial in 100 patients.
The clinical trial was an open-label, multicenter trial evaluating the pharmacokinetic profile, tolerability, safety, and efficacy of lopinavir and ritonavir oral solution containing lopinavir 80 mg/mL and ritonavir 20 mg/mL in 100 antiretroviral naïve and experienced pediatric patients ages 6 months to 12 years. Dose selection for patients 6 months to 12 years of age was based on the following results. The 230/57.5 mg/m 2 oral solution twice daily regimen without nevirapine and the 300/75 mg/m 2 oral solution twice daily regimen with nevirapine provided lopinavir plasma concentrations similar to those obtained in adult patients receiving the 400/100 mg twice daily regimen (without nevirapine) [ see Adverse Reactions (6.2) , Clinical Pharmacology (12.3) , Clinical Studies (14.4) ].
A prospective multicenter, open-label trial evaluated the pharmacokinetic profile, tolerability, safety and efficacy of high-dose lopinavir and ritonavir with or without concurrent NNRTI therapy (Group 1: 400/100 mg/m 2 twice daily + ≥ 2 NRTIs; Group 2: 480/120 mg/m 2 twice daily + ≥ 1 NRTI + 1 NNRTI) in 26 children and adolescents ≥ 2 years to < 18 years of age who had failed prior therapy. Patients also had saquinavir mesylate added to their regimen. This strategy was intended to assess whether higher than approved doses of lopinavir and ritonavir could overcome protease inhibitor cross-resistance.
High doses of lopinavir and ritonavir exhibited a safety profile similar to those observed in previous trials; changes in HIV-1 RNA were less than anticipated; three patients had HIV-1 RNA <400 copies/mL at Week 48. CD4+ cell count increases were noted in the eight patients who remained on treatment for 48 weeks [ see Adverse Reactions (6.2) , Clinical Pharmacology (12.3) ]. A prospective multicenter, randomized, open-label study evaluated the efficacy and safety of twice-daily versus once-daily dosing of lopinavir and ritonavir tablets dosed by weight as part of combination antiretroviral therapy (cART) in virologically suppressed HIV-1 infected children (n=173).
Children were eligible when they were aged < 18 years, ≥ 15 kg in weight, receiving cART that included lopinavir and ritonavir, HIV-1 ribonucleic acid (RNA) < 50 copies/mL for at least 24 weeks and able to swallow tablets. At week 24, efficacy (defined as the proportion of subjects with plasma HIV-1 RNA less than 50 copies per mL) was significantly higher in subjects receiving twice daily dosing compared to subjects receiving once daily dosing. The safety profile was similar between the two treatment arms although there was a greater incidence of diarrhea in the once daily treated subjects.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of lopinavir and ritonavir did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. In general, appropriate caution should be exercised in the administration and monitoring of lopinavir and ritonavir in elderly patients reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Overdoses with lopinavir and ritonavir oral solution have been reported. One of these reports described fatal cardiogenic shock in a 2.1 kg infant who received a single dose of 6.5 mL of lopinavir and ritonavir oral solution (520 mg lopinavir, approximately 10-fold above the recommended lopinavir dose) nine days prior. The following events have been reported in association with unintended overdoses in preterm neonates: complete AV block, cardiomyopathy, lactic acidosis, and acute renal failure [see Warnings and Precautions (5.2) ] .
Healthcare professionals should be aware that lopinavir and ritonavir oral solution is highly concentrated and therefore, should pay special attention to accurate calculation of the dose of lopinavir and ritonavir, transcription of the medication order, dispensing information and dosing instructions to minimize the risk for medication errors and overdose. This is especially important for infants and young children. Lopinavir and ritonavir oral solution contains approximately 42% (v/v) ethanol and approximately 15% (w/v) propylene glycol.
Ingestion of the product over the recommended dose by an infant or a young child could result in significant toxicity and could potentially be lethal. Human experience of acute overdosage with lopinavir and ritonavir is limited. Treatment of overdose with lopinavir and ritonavir should consist of general supportive measures including monitoring of vital signs and observation of the clinical status of the patient.
There is no specific antidote for overdose with lopinavir and ritonavir. If indicated, elimination of unabsorbed drug should be achieved by gastric lavage. Administration of activated charcoal may also be used to aid in removal of unabsorbed drug.
Since lopinavir is highly protein bound, dialysis is unlikely to be beneficial in significant removal of the drug. However, dialysis can remove both ethanol and propylene glycol in the case of overdose with lopinavir and ritonavir oral solution.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Lopinavir and ritonavir is a fixed-dose combination of HIV-1 antiviral drugs lopinavir [ see Microbiology (12.4) ] and ritonavir. As co-formulated in lopinavir and ritonavir, ritonavir inhibits the CYP3A-mediated metabolism of lopinavir, thereby providing increased plasma levels of lopinavir.
12.2Pharmacodynamics Cardiac Electrophysiology The effect of lopinavir and ritonavir on QTcF interval was evaluated in a placebo and active (moxifloxacin 400 mg once daily) controlled crossover study in 39 healthy adults. The maximum mean time-matched (95% upper confidence bound) differences in QTcF interval from placebo after baseline-correction were 5.3 (8.1) and 15.2 (18) mseconds (msec) for 400/100 mg twice daily and supratherapeutic 800/200 mg twice daily lopinavir and ritonavir, respectively. Lopinavir and ritonavir 800/200 mg twice daily resulted in a Day 3 mean C max approximately 2-fold higher than the mean C max observed with the approved once daily and twice daily lopinavir and ritonavir doses at steady state.
The maximum mean (95% upper confidence bound) difference from placebo in the PR interval after baseline-correction were 24.9 (21.5, 28.3) and 31.9 (28.5, 35.3) msec for 400/100 mg twice daily and supratherapeutic 800/200 mg twice daily lopinavir and ritonavir, respectively [ see Warnings and Precautions (5.5 , 5.6) ] .
12.3Pharmacokinetics The pharmacokinetic properties of lopinavir are summarized in Table 13. The steady-state pharmacokinetic parameters of lopinavir are summarized in Table 14. Under fed conditions, lopinavir concentrations were similar following administration of lopinavir and ritonavir tablets to capsules with less pharmacokinetic variability.
Under fed conditions (500 kcal, 25% from fat), lopinavir concentrations were similar following administration of lopinavir and ritonavir capsules and oral solution. Table 13. Pharmacokinetic Properties of Lopinavir Absorption T max (hr) a 4.4 ±
0.8Effect of meal (relative to fasting) Tablet Oral solution ↑ 19% b ↑ 130% b Distribution % Bound to human plasma proteins > 98 V d /F a (L)
16.9Metabolism Metabolism CYP3A Elimination Major route of elimination hepatic t 1/2 (h) a 6.9 ± 2.2 % of dose excreted in urine 10.4 ± 2.3 % of dose excreted in feces 82.6 ± 2.5 a. Lopinavir and ritonavir tablet b. Changes in AUC values Table 14. Steady-State Pharmacokinetic Parameters of Lopinavir, Mean ± SD Pharmacokinetic Parameter Twice Daily a Once Daily b C max (mcg/mL) 9.8 ± 3.7 11.8 ±
3.7C min (mcg/mL) 5.5 ± 2.7 1.7 ±
1.6AUC tau (mcg•h/mL) 92.6 ± 36.7 154.1 ± 61.4 a. 19 HIV-1 subjects, lopinavir and ritonavir 400/100 mg twice daily b. 24 HIV-1 subjects, lopinavir and ritonavir 800/200 mg + emtricitabine 200 mg + tenofovir DF 300 mg Specific Populations Gender, Race and Age No gender or race related pharmacokinetic differences have been observed in adult patients.
Lopinavir pharmacokinetics have not been studied in elderly patients. Pediatric Patients The 230/57.5 mg/m 2 twice daily regimen without nevirapine and the 300/75 mg/m 2 twice daily regimen with nevirapine provided lopinavir plasma concentrations similar to those obtained in adult patients receiving the 400/100 mg twice daily regimen without nevirapine. Table 15.
Lopinavir Pharmacokinetic Data from Pediatric Clinical Trials, Mean ± SD C max (mcg/mL) C min (mcg/mL) AUC 12 (mcg•hr/m) Age ≥ 14 Days to < 6 Weeks Cohort (N = 9): 5.17 ± 1.84 a 1.40 ± 0.48 a 43.39 ± 14.80 a Age ≥ 6 Weeks to < 6 Months Cohort (N = 18): 9.39 ± 4.91 a 1.95 ± 1.80 a 74.50 ± 37.87 a Age ≥ 6 Months to ≤ 12 years Cohort (N = 24): 8.2 ± 2.9 b 3.4 ± 2.1 b 72.6 ± 31.1 b 10.0 ± 3.3 c 3.6 ± 3.5 c 85.8 ± 36.9 c a. Lopinavir and ritonavir oral solution 300/75 mg/m 2 twice daily without concomitant NNRTI therapy b.
Lopinavir and ritonavir oral solution 230/57.5 mg/m 2 twice daily without nevirapine (n=12) c. Lopinavir and ritonavir oral solution 300/75 mg/m 2 twice daily with nevirapine (n=12) Pregnan… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Lopinavir and ritonavir is a fixed-dose combination of HIV-1 antiviral drugs lopinavir [ see Microbiology (12.4) ] and ritonavir. As co-formulated in lopinavir and ritonavir, ritonavir inhibits the CYP3A-mediated metabolism of lopinavir, thereby providing increased plasma levels of lopinavir.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Lopinavir and Ritonavir Tablets, USP are available in the following strengths and package sizes: Lopinavir and Ritonavir Tablets USP, 100 mg/25 mg : Yellow colored, film coated oval shaped biconvex tablets debossed with “LA59” on one side and plain on other side. Bottles of 60 NDC 42385-933-60 Lopinavir and Ritonavir Tablets USP, 200 mg/50 mg : Yellow colored, film coated oval shaped biconvex tablets debossed with “LA58” on one side and plain on other side. Bottles of 120 NDC 42385-934-12 Recommended Storage: Store lopinavir and ritonavir tablets, USP at 20° to 25°C (68° to 77°F); excursions permitted between 15° to 30°C (59° to 86°F) [see USP controlled room temperature].
Dispense in original container or USP equivalent tight container. For patient use: exposure of this product to high humidity outside the original container or USP equivalent tight container for longer than 2 weeks is not recommended.
📋 Description ▾
11 DESCRIPTION Lopinavir and ritonavir tablets, USP are a co-formulation of lopinavir USP and ritonavir USP. Lopinavir is an inhibitor of the HIV-1 protease. As co-formulated in lopinavir and ritonavir tablets, ritonavir inhibits the CYP3A-mediated metabolism of lopinavir, thereby providing increased plasma levels of lopinavir.
Lopinavir USP is chemically designated as [1 S -[1 R *,( R *),3 R *,4 R *]]- N -[4-[[(2,6- dimethylphenoxy)acetyl]amino]-3-hydroxy-5-phenyl-1-(phenylmethyl)pentyl]tetrahydro-α-(1-methylethyl)-2-oxo-1(2 H )-pyrimidineacetamide. Its molecular formula is C 37 H 48 N 4 O 5 , and its molecular weight is 628.8 g/mol. Lopinavir USP is a white to off-white color solid.
It is freely soluble in methanol, soluble in isopropyl alcohol and practically insoluble in water. Lopinavir USP has the following structural formula: Ritonavir USP is chemically designated as 2,4,7,12-Tetraazatridecan-13-oic acid, 10-hydroxy-2-methyl-5-(1-methylethyl)-1-[2-(1-methylethyl)-4-thiazolyl]-3,6-di-oxo-8,11-bis(phenylmethyl)-5-thiazolylmethylester[5 S -(5 R *,8 R *,10 R *,11 R *)]-. Its molecular formula is C 37 H 48 N 6 O 5 S 2 , and its molecular weight is 720.94 g/mol.
Ritonavir USP is a white or almost white solid. It is freely soluble in methanol and in dichloromethane; very slightly soluble in acetonitrile; practically insoluble in water. Ritonavir USP has the following structural formula: Lopinavir and ritonavir tablets, USP are available for oral administration in two strengths: Yellow tablets containing 200 mg of lopinavir USP and 50 mg of ritonavir USP.
Yellow tablets containing 100 mg of lopinavir USP and 25 mg of ritonavir USP. The yellow, Lopinavir and Ritonavir Tablets USP, 200 mg/50 mg contain the following inactive ingredients: colloidal silicon dioxide, copovidone, sodium stearyl fumarate and sorbitan monolaurate. The following are the ingredients in the film coating: colloidal silicon dioxide, hydroxypropyl cellulose, hypromellose, iron oxide yellow, polyethylene glycol 400, polyethylene glycol 3350, polysorbate 80, talc, and titanium dioxide.
The yellow, Lopinavir and Ritonavir Tablets USP, 100 mg/25 mg contain the following inactive ingredients: colloidal silicon dioxide, copovidone, sodium stearyl fumarate and sorbitan monolaurate. The following are the ingredients in the film coating: colloidal silicon dioxide, hydroxypropyl cellulose, hypromellose, iron oxide yellow, polyethylene glycol 400, polyethylene glycol 3350, polysorbate 80, talc, and titanium dioxide. lopinavir-structure ritonavir-structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide) General Administration Information [ see Dosage and Administration (2) ] : Advise patients to pay special attention to accurate administration of their dose to minimize the risk of accidental overdose or underdose of lopinavir and ritonavir. Advise patients and caregivers that the oral solution should be administered using the calibrated dosing cup (supplied) or oral dosing syringe. Advise caregivers to inform their healthcare provider if the child’s weight changes in order to make sure that the child’s lopinavir and ritonavir dose is adjusted as needed.
Inform patients and caregivers that lopinavir and ritonavir tablets may be taken with or without food but lopinavir and ritonavir oral solution should be taken with food to enhance absorption. Advise patients to remain under the care of a healthcare provider while using lopinavir and ritonavir and to take lopinavir and ritonavir in combination with other antiretroviral drugs as prescribed. Advise patients not to alter the dose or discontinue therapy without consulting with their healthcare provider.
If a dose of lopinavir and ritonavir is missed patients should take the dose as soon as possible and then return to their normal schedule. However, if a dose is skipped the patient should not double the next dose. Inform patients that it is important to take lopinavir and ritonavir on a regular dosing schedule as directed and to avoid missing doses as that can result in development of resistance.
Inform patients that there may be a greater chance of developing diarrhea with the once daily regimen as compared with the twice daily regimen. Inform patients that lopinavir and ritonavir is not a cure for HIV-1 infection and that they may continue to experience illnesses associated with HIV-1 infection, including opportunistic infections. Drug Interactions Inform patients that lopinavir and ritonavir may interact with some drugs; therefore, patients should be advised to report to their healthcare provider the use of any prescription, non-prescription medication or herbal products such as St.
John’s Wort [ see Contraindications (4) , Warnings and Precautions (5.1) and Drug Interactions (7) ] . Pancreatitis Advise patients that pancreatitis has been observed in patients receiving lopinavir and ritonavir and to alert their healthcare provider if they experience symptoms such as nausea, vomiting or abdominal pain [ see Warnings and Precautions (5.3) ] . Skin Rash Inform patients that skin rash ranging in severity from mild to toxic epidermal necrolysis (TEN), Stevens-Johnson syndrome, erythema multiforme, urticaria, and angioedema have been reported in patients receiving lopinavir and ritonavir or its components lopinavir and/or ritonavir.
Advise patients to contact their healthcare provider if they develop a rash while taking lopinavir and ritonavir [ see Adverse Reactions (6.1) ] . Hepatotoxicity Pre-existing liver disease including Hepatitis B or C can worsen with use of lopinavir and ritonavir. This can be seen as worsening of transaminase elevations or hepatic decompensation.
Advise patients that their liver function tests will need to be monitored closely especially during the first several months of lopinavir and ritonavir treatment and that they should notify their healthcare provider if they develop the signs and symptoms of worsening liver disease including loss of appetite, abdominal pain, jaundice, and itchy skin [ see Warnings and Precautions (5.4) ] . QT and PR Interval Prolongation Advise patients that lopinavir and ritonavir may produce changes in the electrocardiogram (e.g., PR and/or QT prolongation) and to consult their healthcare provider if they experience symptoms such as dizziness, lightheadedness, abnormal heart rhythm or loss of consciousness [ see Warnings and Precautions (5.5 , 5.6 )] .
Diabetes Mellitus/Hyperglycemia Advise patients that new onset of d… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
MEDICATION GUIDE Lopinavir and Ritonavir (loe-PIN-a-veer and ri-TOE-na-vir) Tablets, USP What is the most important information I should know about lopinavir and ritonavir? Lopinavir and ritonavir may cause serious side effects, including: • Interactions with other medicines. It is important to know the medicines that should not be taken with lopinavir and ritonavir .
For more information, see "Who should not take lopinavir and ritonavir?” • Side Effects in babies taking lopinavir and ritonavir oral solution . Lopinavir and ritonavir oral solution contains alcohol (ethanol) and propylene glycol. Call your healthcare provider right away if your baby appears too sleepy or their breathing changes. • Inflammation of your pancreas (pancreatitis).
Lopinavir and ritonavir can cause pancreatitis which may be serious and may lead to death. People who have high levels of a certain fat (triglycerides) have a risk for developing pancreatitis. If you have advanced HIV-1 disease, you may have an increased risk of high triglyceride levels in your blood, and pancreatitis.
If you have a history of pancreatitis, you may have an increased risk of it coming back again during treatment with lopinavir and ritonavir. Tell your healthcare provider if you have any signs or symptoms of pancreatitis including:◦ nausea ◦ vomiting ◦ stomach-area (abdominal) pain • Liver problems . Liver problems, including death, can happen in people who take lopinavir and ritonavir.
Your healthcare provider should do blood tests before and during your treatment with lopinavir and ritonavir to check your liver function. If you have Hepatitis B or Hepatitis C, or other liver problems, you may have an increased risk for developing new or worsening of liver problems during treatment with lopinavir and ritonavir. Tell your healthcare provider right away if you have any signs and symptoms of liver problems including: ◦ loss of appetite ◦ pale colored stools ◦ yellow skin and whites of eyes (jaundice) ◦ itchy skin ◦ dark-colored urine ◦ stomach area (abdominal) pain • Changes in your heart rhythm and the electrical activity of your heart .
These changes may be seen on an EKG (electrocardiogram) and can lead to serious heart problems. Your risk for these problems may be higher if you: ◦ have a history of abnormal heart rhythm or certain types of heart problems. ◦ take other medicines that can affect your heart rhythm during treatment with lopinavir and ritonavir. Tell your healthcare provider right away if you have any of these symptoms: ◦ dizziness ◦ fainting ◦ lightheadedness ◦ sensation of abnormal heartbeats See “What are the possible side effects of lopinavir and ritonavir?” for more information about serious side effects.
What is lopinavir and ritonavir? Lopinavir and ritonavir is a prescription medicine that is used with other antiretroviral medicines to treat Human Immunodeficiency Virus-1 (HIV-1) infection in adults and children 14 days of age and older. HIV is the virus that causes AIDS (Acquired Immune Deficiency Syndrome).
It is not known if lopinavir and ritonavir is safe and effective in children under 14 days old. Who should not take lopinavir and ritonavir? Do not take lopinavir and ritonavir if you: • are allergic to lopinavir, ritonavir, or any of the ingredients in lopinavir and ritonavir tablets.
See the end of this Medication Guide for a complete list of ingredients in lopinavir and ritonavir tablets. • if you take any of the following medicines: o alfuzosin o apalutamide o ranolazine o dronedarone o colchicine, if you have kidney or liver problems. o rifampin o lurasidone o pimozide o ergot containing medicines including: • dihydroergotamine mesylate • ergotamine tartrate • methylergonovine o cisapride o elbasvir/grazoprevir o lovastatin o simvastatin o lomitapide o sildenafil (Revatio®), when used for the treatment of pulmonary arterial hypertension o triazolam o midazolam when taken by mouth o St.
John’s Wort (Hypericum perforatum®) Serious problems can h… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
8.3Females and Males of Reproductive Potential Contraception Use of lopinavir and ritonavir may reduce the efficacy of combined hormonal contraceptives. Advise patients using combined hormonal contraceptives to use an effective alternative contraceptive method or an additional barrier method of contraception [ see Drug Interactions (7.3) ] .
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetic properties of lopinavir are summarized in Table 13. The steady-state pharmacokinetic parameters of lopinavir are summarized in Table 14. Under fed conditions, lopinavir concentrations were similar following administration of lopinavir and ritonavir tablets to capsules with less pharmacokinetic variability.
Under fed conditions (500 kcal, 25% from fat), lopinavir concentrations were similar following administration of lopinavir and ritonavir capsules and oral solution. Table 13. Pharmacokinetic Properties of Lopinavir Absorption T max (hr) a 4.4 ±
0.8Effect of meal (relative to fasting) Tablet Oral solution ↑ 19% b ↑ 130% b Distribution % Bound to human plasma proteins > 98 V d /F a (L)
16.9Metabolism Metabolism CYP3A Elimination Major route of elimination hepatic t 1/2 (h) a 6.9 ± 2.2 % of dose excreted in urine 10.4 ± 2.3 % of dose excreted in feces 82.6 ± 2.5 a. Lopinavir and ritonavir tablet b. Changes in AUC values Table 14. Steady-State Pharmacokinetic Parameters of Lopinavir, Mean ± SD Pharmacokinetic Parameter Twice Daily a Once Daily b C max (mcg/mL) 9.8 ± 3.7 11.8 ±
3.7C min (mcg/mL) 5.5 ± 2.7 1.7 ±
1.6AUC tau (mcg•h/mL) 92.6 ± 36.7 154.1 ± 61.4 a. 19 HIV-1 subjects, lopinavir and ritonavir 400/100 mg twice daily b. 24 HIV-1 subjects, lopinavir and ritonavir 800/200 mg + emtricitabine 200 mg + tenofovir DF 300 mg Specific Populations Gender, Race and Age No gender or race related pharmacokinetic differences have been observed in adult patients.
Lopinavir pharmacokinetics have not been studied in elderly patients. Pediatric Patients The 230/57.5 mg/m 2 twice daily regimen without nevirapine and the 300/75 mg/m 2 twice daily regimen with nevirapine provided lopinavir plasma concentrations similar to those obtained in adult patients receiving the 400/100 mg twice daily regimen without nevirapine. Table 15.
Lopinavir Pharmacokinetic Data from Pediatric Clinical Trials, Mean ± SD C max (mcg/mL) C min (mcg/mL) AUC 12 (mcg•hr/m) Age ≥ 14 Days to < 6 Weeks Cohort (N = 9): 5.17 ± 1.84 a 1.40 ± 0.48 a 43.39 ± 14.80 a Age ≥ 6 Weeks to < 6 Months Cohort (N = 18): 9.39 ± 4.91 a 1.95 ± 1.80 a 74.50 ± 37.87 a Age ≥ 6 Months to ≤ 12 years Cohort (N = 24): 8.2 ± 2.9 b 3.4 ± 2.1 b 72.6 ± 31.1 b 10.0 ± 3.3 c 3.6 ± 3.5 c 85.8 ± 36.9 c a. Lopinavir and ritonavir oral solution 300/75 mg/m 2 twice daily without concomitant NNRTI therapy b.
Lopinavir and ritonavir oral solution 230/57.5 mg/m 2 twice daily without nevirapine (n=12) c. Lopinavir and ritonavir oral solution 300/75 mg/m 2 twice daily with nevirapine (n=12) Pregnancy The C 12h values of lopinavir were lower during the second and third trimester by approximately 40% as compared to post-partum in 12 HIV-infected pregnant women received lopinavir and ritonavir 400 mg/100 mg twice daily. Yet this decrease is not considered clinically relevant in patients with no documented lopinavir and ritonavir-associated resistance substitutions receiving 400 mg/100 mg twice daily [see Use in Specific Populations (8.1) ] .
Renal Impairment Lopinavir pharmacokinetics have not been studied in patients with renal impairment; however, since the renal clearance of lopinavir is negligible, a decrease in total body clearance is not expected in patients with renal impairment. Hepatic Impairment Multiple dosing of lopinavir and ritonavir 400/100 mg twice daily to HIV-1 and HCV co-infected patients with mild to moderate hepatic impairment (n = 12) resulted in a 30% increase in lopinavir AUC and 20% increase in C max compared to HIV-1 infected subjects with normal hepatic function (n = 12).
Additionally, the plasma protein binding of lopinavir was statistically significantly lower in both mild and moderate hepatic impairment compared to controls (99.09 vs. 99.31%, respectively). Lopinavir and ritonavir has not been studied in patients with severe hepatic impairment [see Warnings and Precautions (5.4) and Use in Specific Populations (8.6) ] .
Drug Interactions Lop… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Cardiac Electrophysiology The effect of lopinavir and ritonavir on QTcF interval was evaluated in a placebo and active (moxifloxacin 400 mg once daily) controlled crossover study in 39 healthy adults. The maximum mean time-matched (95% upper confidence bound) differences in QTcF interval from placebo after baseline-correction were 5.3 (8.1) and 15.2 (18) mseconds (msec) for 400/100 mg twice daily and supratherapeutic 800/200 mg twice daily lopinavir and ritonavir, respectively. Lopinavir and ritonavir 800/200 mg twice daily resulted in a Day 3 mean C max approximately 2-fold higher than the mean C max observed with the approved once daily and twice daily lopinavir and ritonavir doses at steady state.
The maximum mean (95% upper confidence bound) difference from placebo in the PR interval after baseline-correction were 24.9 (21.5, 28.3) and 31.9 (28.5, 35.3) msec for 400/100 mg twice daily and supratherapeutic 800/200 mg twice daily lopinavir and ritonavir, respectively [ see Warnings and Precautions (5.5 , 5.6) ] .
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Adult Patients without Prior Antiretroviral Therapy Study 863: Lopinavir and Ritonavir Capsules twice daily + stavudine + lamivudine compared to nelfinavir three times daily + stavudine + lamivudine Study 863 was a randomized, double-blind, multicenter trial comparing treatment with lopinavir and ritonavir capsules (400/100 mg twice daily) plus stavudine and lamivudine versus nelfinavir (750 mg three times daily) plus stavudine and lamivudine in 653 antiretroviral treatment naïve patients. Patients had a mean age of 38 years (range: 19 to 84), 57% were Caucasian, and 80% were male.
Mean baseline CD4+ cell count was 259 cells/mm 3 (range: 2 to 949 cells/mm 3 ) and mean baseline plasma HIV-1 RNA was 4.9 log 10 copies/mL (range: 2.6 to 6.8 log 10 copies/mL). Treatment response and outcomes of randomized treatment are presented in Table 21. Table 21.
Outcomes of Randomized Treatment Through Week 48 (Study 863) Outcome Lopinavir and Ritonavir+d4T+3TC (N = 326) Nelfinavir+d4T+3TC (N = 327) Responder 1 75% 62% Virologic failure 2 Rebound Never suppressed through Week 48 9% 7% 2% 25% 15% 9% Death 2% 1% Discontinued due to adverse events 4% 4% Discontinued for other reasons 3 10% 8% 1 Patients achieved and maintained confirmed HIV-1 RNA < 400 copies/mL through Week 48. 2 Includes confirmed viral rebound and failure to achieve confirmed < 400 copies/mL through Week 48.
3 Includes lost to follow-up, patient's withdrawal, non-compliance, protocol violation and other reasons. Overall discontinuation through Week 48, including patients who discontinued subsequent to virologic failure, was 17% in the lopinavir and ritonavir arm and 24% in the nelfinavir arm. Through 48 weeks of therapy, there was a statistically significantly higher proportion of patients in the lopinavir and ritonavir arm compared to the nelfinavir arm with HIV-1 RNA < 400 copies/mL (75% vs.
62%, respectively) and HIV-1 RNA < 50 copies/mL (67% vs. 52%, respectively). Treatment response by baseline HIV-1 RNA level subgroups is presented in Table 22.
Table 22. Proportion of Responders Through Week 48 by Baseline Viral Load (Study 863) Baseline Viral Load (HIV- 1 RNA copies/mL) Lopinavir and Ritonavir+d4T+3TC Nelfinavir +d4T+3TC <400 copies/mL 1 <50 copies/mL 2 n <400 copies/mL 1 <50 copies/mL 2 n < 30,000 74% 71% 82 79% 72% 87 ≥ 30,000 to < 100,000 81% 73% 79 67% 54% 79 ≥ 100,000 to < 250,000 75% 64% 83 60% 47% 72 ≥ 250,000 72% 60% 82 44% 33% 89 1 Patients achieved and maintained confirmed HIV-1 RNA < 400 copies/mL through Week 48. 2 Patients achieved HIV-1 RNA < 50 copies/mL at Week 48.
Through 48 weeks of therapy, the mean increase from baseline in CD4+ cell count was 207 cells/mm 3 for the lopinavir and ritonavir arm and 195 cells/mm 3 for the nelfinavir arm. Study 730: Lopinavir and Ritonavir Tablets once daily + tenofovir DF + emtricitabine compared to Lopinavir and Ritonavir Tablets twice daily + tenofovir DF + emtricitabine Study 730 was a randomized, open-label, multicenter trial comparing treatment with lopinavir and ritonavir 800/200 mg once daily plus tenofovir DF and emtricitabine versus lopinavir and ritonavir 400/100 mg twice daily plus tenofovir DF and emtricitabine in 664 antiretroviral treatment-naïve patients.
Patients were randomized in a 1:1 ratio to receive either lopinavir and ritonavir 800/200 mg once daily (n = 333) or lopinavir and ritonavir 400/100 mg twice daily (n = 331). Further stratification within each group was 1:1 (tablet vs. capsule). Patients administered the capsule were switched to the tablet formulation at Week 8 and maintained on their randomized dosing schedule.
Patients were administered emtricitabine 200 mg once daily and tenofovir DF 300 mg once daily. Mean age of patients enrolled was 39 years (range: 19 to 71); 75% were Caucasian, and 78% were male. Mean baseline CD4+ cell count was 216 cells/mm 3 (range: 20 to 775 cells/mm 3 ) and mean baseline plasma HIV-1 RNA was 5.0 log 10 copies/mL (range: 1.7 to 7.0… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment Of Fertility Carcinogenesis Lopinavir/ritonavir combination was evaluated for carcinogenic potential by oral gavage administration to mice and rats for up to 104 weeks. Results showed an increase in the incidence of benign hepatocellular adenomas and an increase in the combined incidence of hepatocellular adenomas plus carcinoma in both males and females in mice and males in rats at doses that produced approximately 1.6 to 2.2 times (mice) and 0.5 times (rats) the human exposure (based on AUC 0 to 24hr measurement) at the recommended dose of 400/100 mg lopinavir and ritonavir twice daily.
Administration of lopinavir/ritonavir did not cause a statistically significant increase in the incidence of any other benign or malignant neoplasm in mice or rats. Carcinogenicity studies in mice and rats have been carried out on ritonavir. In male mice, there was a dose dependent increase in the incidence of both adenomas and combined adenomas and carcinomas in the liver.
Based on AUC measurements, the exposure at the high dose was approximately 4-fold for males that of the exposure in humans with the recommended therapeutic dose (400/100 mg lopinavir and ritonavir twice daily). There were no carcinogenic effects seen in females at the dosages tested. The exposure at the high dose was approximately 9-fold for the females that of the exposure in humans.
There were no carcinogenic effects in rats. In this study, the exposure at the high dose was approximately 0.7-fold that of the exposure in humans with the 400/100 mg lopinavir and ritonavir twice daily regimen. Based on the exposures achieved in the animal studies, the significance of the observed effects is not known.
Mutagenesis Neither lopinavir nor ritonavir was found to be mutagenic or clastogenic in a battery of in vitro and in vivo assays including the Ames bacterial reverse mutation assay using S. typhimurium and E. coli , the mouse lymphoma assay, the mouse micronucleus test and chromosomal aberration assays in human lymphocytes. Impairment of Fertility Lopinavir in combination with ritonavir at a 2:1 ratio produced no effects on fertility in male and female rats at levels of 10/5, 30/15 or 100/50 mg/kg/day. Based on AUC measurements, the exposures in rats at the high doses were approximately 0.7-fold for lopinavir and 1.8-fold for ritonavir of the exposures in humans at the recommended therapeutic dose (400/100 mg twice daily).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment Of Fertility Carcinogenesis Lopinavir/ritonavir combination was evaluated for carcinogenic potential by oral gavage administration to mice and rats for up to 104 weeks. Results showed an increase in the incidence of benign hepatocellular adenomas and an increase in the combined incidence of hepatocellular adenomas plus carcinoma in both males and females in mice and males in rats at doses that produced approximately 1.6 to 2.2 times (mice) and 0.5 times (rats) the human exposure (based on AUC 0 to 24hr measurement) at the recommended dose of 400/100 mg lopinavir and ritonavir twice daily.
Administration of lopinavir/ritonavir did not cause a statistically significant increase in the incidence of any other benign or malignant neoplasm in mice or rats. Carcinogenicity studies in mice and rats have been carried out on ritonavir. In male mice, there was a dose dependent increase in the incidence of both adenomas and combined adenomas and carcinomas in the liver.
Based on AUC measurements, the exposure at the high dose was approximately 4-fold for males that of the exposure in humans with the recommended therapeutic dose (400/100 mg lopinavir and ritonavir twice daily). There were no carcinogenic effects seen in females at the dosages tested. The exposure at the high dose was approximately 9-fold for the females that of the exposure in humans.
There were no carcinogenic effects in rats. In this study, the exposure at the high dose was approximately 0.7-fold that of the exposure in humans with the 400/100 mg lopinavir and ritonavir twice daily regimen. Based on the exposures achieved in the animal studies, the significance of the observed effects is not known.
Mutagenesis Neither lopinavir nor ritonavir was found to be mutagenic or clastogenic in a battery of in vitro and in vivo assays including the Ames bacterial reverse mutation assay using S. typhimurium and E. coli , the mouse lymphoma assay, the mouse micronucleus test and chromosomal aberration assays in human lymphocytes. Impairment of Fertility Lopinavir in combination with ritonavir at a 2:1 ratio produced no effects on fertility in male and female rats at levels of 10/5, 30/15 or 100/50 mg/kg/day. Based on AUC measurements, the exposures in rats at the high doses were approximately 0.7-fold for lopinavir and 1.8-fold for ritonavir of the exposures in humans at the recommended therapeutic dose (400/100 mg twice daily).
📄 Recent Major Changes ▾
Contraindications ( 4 ) 12/2019
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL-200 mg/50 mg - Container Label (120's count) NDC 42385-934-12 Lopinavir and Ritonavir Tablets, USP 200 mg/50 mg ALERT: Find out about medicines that should NOT be taken with Lopinavir and Ritonavir Tablets, USP Attention Pharmacist: Do not cover ALERT box with pharmacy label. Dispense the accompanying Medication Guide to each patient. 120 Tablets Rx Only Laurus Labs figure2
PRINCIPAL DISPLAY PANEL-100 mg/25 mg - Container Label (60's count) NDC 42385-933-60 Lopinavir and Ritonavir Tablets, USP 100 mg/25 mg ALERT : Find out about medicines that should NOT be taken with Lopinavir and Ritonavir Tablets, USP Attention Pharmacist: Do not cover ALERT box with pharmacy label. Dispense the accompanying Medication Guide to each patient. 60 Tablets Rx Only Laurus Labs figure3