
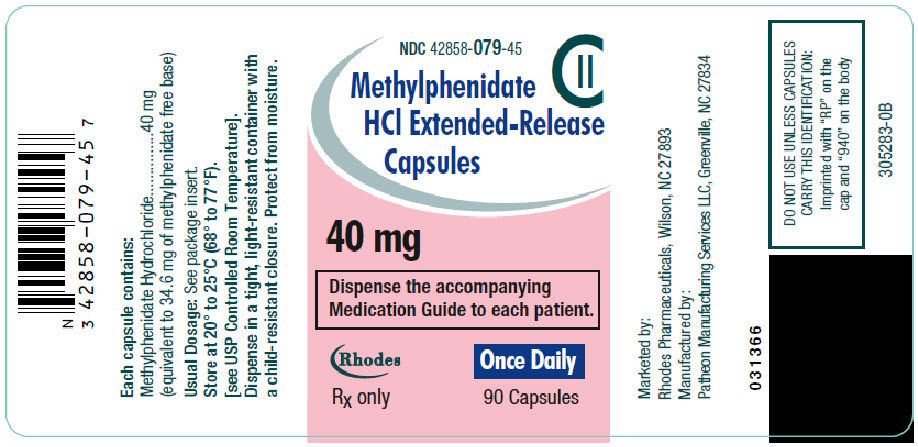
Methylphenidate Hydrochloride 40 mg Capsule, Extended Release, 90-count — NDC 42858-079-45 (Billing 42858-0079-45)
This is a package of 90 capsules of Methylphenidate Hydrochloride 40 mg Capsule, Extended Release from Rhodes Pharmaceuticals LLC, marketed since Apr 2020 and currently FDA-listed. It is this product's only package size.
Other active recalls for Methylphenidate Hydrochloride (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 061447
- GCN: 97238
- HICL (First Databank): 001682
- AHFS class code: 28:20.32.00
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
Clinical
Methylphenidate is used to control symptoms of attention deficit hyperactivity disorder (ADHD; condition that makes it hard to pay attention, control your behavior, and remain still or quiet) and to treat narcolepsy (condition that causes people to be very sleepy during the day and to fall asleep suddenly). Methylphenidate is in a class of medications called central nervous system (CNS) stimulants. It works by changing the amounts of certain natural substances in the brain.
Read the full MedlinePlus article ↗- It mainly treats ADHD, and some products are also used for narcolepsy. The exact approval depends on the product and the age group. Your prescriber chooses the right one for you.
- It depends on your product. Many extended-release forms are taken once daily in the morning, while Jornay PM is taken in the evening. Swallow extended-release tablets whole, and fo...
- The most common ones are decreased appetite, headache, dry mouth, nausea, trouble sleeping, anxiety and dizziness. Children and teens may get upper stomach pain. Call your doctor i...
- Call for chest pain, fainting, a racing heartbeat, hallucinations, seizures, painful erections that won’t go away, or color changes in your fingers or toes. Also call if you notice...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Methylphenidate Hydrochloride — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $5.30 | $477.39 / 90 capsules |
| Medicare drug plans payPart D · Q2 2026 | $5.17 | $465.35 / 90 capsules |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 42858-0079-45 You're viewing this Main listing | 90 CAPSULE, EXTENDED RELEASE in 1 BOTTLE | 2020-04-01 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Methylphenidate Hydrochloride Extended-Release 40 mg 00406-1840-01 | SpecGx | 100 capsules | $1.441 | AB2 | Availability likely | — |
| Methylphenidate Hydrochloride 40 mg 00115-1739-01 | Amneal | 100 capsules | $1.441 | AB2 | Availability likely | — |
| methylphenidate hydrochloride CD 40 mg 00527-4582-37 | Lannett | 100 capsules | $1.441 | AB2 | Availability likely | — |
| Methylphenidate Hydrochloride (LA) 40 mg 00093-5348-01 | Teva | 100 capsules | $1.854 | — | Discontinued | — |
| Methylphenidate Hydrochloride (LA) 40 mg 75907-0052-01 | Dr. | 100 capsules | $1.854 | AB1 | Availability likely | — |
| Methylphenidate Hydrochloride 40 mg 70010-0015-01 | Granules | 100 capsules | $1.854 | AB1 | Availability likely | — |
| Methylphenidate Hydrochloride (LA) 40 mg 51862-0612-01 | Mayne | 100 capsules | $2.078 | AB1 | Discontinued | — |
| Ritalin LA 40 mg 00078-0372-05 | Novartis | 100 capsules | $12.726 | AB1 | Availability likely | — |
| methylphenidate hydrochloride 40 mg 00591-3891-19 | Actavis | 90 capsules | — | AB3 | FDA listed | — |
| Methylphenidate Hydrochloride 40 mgthis 42858-0079-45 | Rhodes | 90 capsules | — | AB3 | FDA listed | — |
| Metadate Cd 40 mg 69654-0582-30 | Aytu | 30 capsules | — | AB2 | FDA listed | — |
| Metadate Cd 40 mg 00527-6582-30 | Lannett | 30 capsules | — | AB2 | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 161H3B14U2
A synthetic plastic polymer used as an enteric coating on tablets and capsules. It dissolves in the intestines rather than the stomach, controlling where and when the medicine is released in the digestive tract.
-
UNII 767IP0Y5NH
A synthetic red colorant used to give medicines their color. It helps patients identify their medication and makes the product visually appealing.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII WZB9127XOA
A synthetic red dye used to color medications and make them easier to identify. It serves as a colorant in tablets, capsules, and liquid formulations.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII NX76LV5T8J
A synthetic plastic polymer made from methacrylic acid and ethyl acrylate. It's used as a coating or binder to control how and where the medicine dissolves in your digestive system.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII WZH3C48M4T
Potassium hydroxide is a strong alkaline chemical used in medicines to adjust and maintain the pH level of liquid formulations, helping keep the product stable and the active ingredients effective.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 8Z96QXD6UM
Triethyl citrate is a clear liquid derived from citric acid. It acts as a plasticizer and solvent in tablet coatings and film formulations, helping the coating remain flexible and adhere properly to the medicine.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
18 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: ABUSE, MISUSE, AND ADDICTION Methylphenidate hydrochloride extended-release capsules have a high potential for abuse and misuse, which can lead to the development of a substance use disorder, including addiction. Misuse and abuse of CNS stimulants, including methylphenidate hydrochloride extended-release capsules, can result in overdose and death [see Overdosage (10) ] , and this risk is increased with higher doses or unapproved methods of administration, such as snorting or injection. Before prescribing methylphenidate hydrochloride extended-release capsules, assess each patient's risk for abuse, misuse, and addiction.
Educate patients and their families about these risks, proper storage of the drug, and proper disposal of any unused drug. Throughout methylphenidate hydrochloride extended-release capsules treatment, reassess each patient's risk of abuse, misuse, and addiction and frequently monitor for signs and symptoms of abuse, misuse, and addiction [see Warnings and Precautions (5.1) and Drug Abuse and Dependence (9.2) ] . WARNING: ABUSE, MISUSE, AND ADDICTION See full prescribing information for complete boxed warning.
Methylphenidate hydrochloride extended-release capsules have a high potential for abuse and misuse, which can lead to the development of a substance use disorder, including addiction. Misuse and abuse of CNS stimulants, including methylphenidate hydrochloride extended-release capsules, can result in overdose and death ( 5.1 , 9.2 , 10 ): Before prescribing methylphenidate hydrochloride extended-release capsules, assess each patient's risk for abuse, misuse, and addiction. Educate patients and their families about these risks, proper storage of the drug, and proper disposal of any unused drug.
Throughout treatment, reassess each patient's risk and frequently monitor for signs and symptoms of abuse, misuse, and addiction.
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Methylphenidate hydrochloride extended-release capsules are indicated for the treatment of Attention Deficit Hyperactivity Disorder (ADHD ) in patients 6 years and older [see Clinical Studies (14) ]. Methylphenidate hydrochloride extended-release capsules are a central nervous system (CNS) stimulant indicated for the treatment of Attention Deficit Hyperactivity Disorder (ADHD) in patients 6 years and older. ( 1 ) Limitations of Use : The use of methylphenidate hydrochloride extended-release capsules is not recommended in pediatric patients younger than 6 years of age because they had higher plasma exposure and a higher incidence of adverse reactions (e.g., weight loss) than patients 6 years and older at the same dosage.
( 5.7 , 8.4 ) Limitations of Use The use of methylphenidate hydrochloride extended-release capsules is not recommended in pediatric patients younger than 6 years of age because they had higher plasma exposure and a higher incidence of adverse reactions (e.g., weight loss) than patients 6 years and older at the same dosage [see Warnings and Precautions (5.7) , Use in Specific Populations (8.4) ].
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Recommended starting dose for patients 6 years and older: 10 mg once daily with or without food in the morning. Dosage may be increased weekly in increments of 10 mg per day. Daily dosage above 60 mg is not recommended. ( 2.1 ) Capsules may be swallowed whole or opened and the entire contents sprinkled onto applesauce. ( 2.1 )
2.1Pretreatment Screening Prior to treating patients with methylphenidate hydrochloride extended-release capsules, assess: for the presence of cardiac disease (i.e., perform a careful history, family history of sudden death or ventricular arrhythmia, and physical exam) [see Warnings and Precautions 5.2 ]. the family history and clinically evaluate patients for motor or verbal tics or Tourette's syndrome before initiating methylphenidate hydrochloride extended-release capsules [see Warnings and Precautions (5.10) ] .
2.2Recommended Dosage The recommended starting dose of methylphenidate hydrochloride extended-release capsules in patients 6 years and older is 10 mg once daily orally in the morning with or without food. Advise patients to establish a routine pattern with regard to meals. The dose should be individualized according to the needs and response of the patient.
The dose may be titrated weekly in increments of 10 mg. Daily doses above 60 mg have not been studied and are not recommended.
2.3Administration Instructions Methylphenidate hydrochloride extended-release capsules may be taken whole or the capsule may be opened and the entire contents sprinkled onto applesauce. If the patient is using the sprinkled administration method, the sprinkled applesauce should be consumed immediately; it should not be stored. Patients should take the applesauce with sprinkled beads in its entirety without chewing.
The dose of a single capsule should not be divided. The contents of the entire capsule should be taken, and patients should not take anything less than one capsule per day.
2.4Dosage Reduction and Discontinuation If paradoxical aggravation of symptoms or other adverse reactions occur; the dosage should be reduced, or, if necessary, discontinue methylphenidate hydrochloride extended-release capsules. If improvement is not observed after appropriate dosage adjustment over a one-month period, discontinue methylphenidate hydrochloride extended-release capsules.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 10 mg Extended-Release Capsules - Hard Gelatin Capsules, white opaque body & light turquoise blue opaque cap containing white spherical beads. Body Imprinting: 910. Cap imprinting: RP 15 mg Extended-Release Capsules - Hard Gelatin Capsules, white opaque body and orange cap containing white spherical beads.
Body imprinting: 915. Cap imprinting: RP 20 mg Extended-Release Capsules Hard Gelatin Capsules, white opaque body and yellow opaque cap containing white spherical beads. Body imprinting: 920.
Cap imprinting: RP 30 mg Extended-Release Capsules Hard Gelatin Capsules, white opaque body and blue violet cap containing white spherical beads. Body imprinting: 930. Cap imprinting: RP 40 mg Extended-Release Capsules - Hard Gelatin Capsules, white opaque body and pink opaque cap containing white spherical beads.
Body imprinting: 940. Cap imprinting: RP 50 mg Extended-Release Capsules - Hard Gelatin Capsules, white opaque body and green opaque cap containing white spherical beads. Body imprinting: 950.
Cap Imprinting: RP 60 mg Extended-Release Capsules Hard Gelatin Capsules, white opaque body and gray opaque cap containing white spherical beads. Body imprinting: 960. Cap imprinting: RP Extended-release capsules: 10 mg, 15 mg, 20 mg, 30 mg, 40 mg, 50 mg, and 60 mg of methylphenidate hydrochloride, which is equivalent to 8.6 mg, 13.0 mg, 17.3 mg, 25.9 mg, 34.6 mg, 43.2 mg, and 51.9 mg of methylphenidate free base, respectively, per capsule.
( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Hypersensitivity to methylphenidate or other components of the product. Hypersensitivity reactions such as angioedema and anaphylactic reactions have been reported in patients treated with methylphenidate products [see Adverse Reactions (6.1) ]. Concomitant treatment with monoamine oxidase inhibitors, and also within 14 days following discontinuation of treatment with a monoamine oxidase inhibitor, because of the risk of hypertensive crisis [see Drug Interactions (7.1) ] .
Known hypersensitivity to methylphenidate or product components. ( 4 ) Concurrent treatment with a monoamine oxidase inhibitor (MAOI), or use of an MAOI within the preceding 14 days. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Risks to Patients with Serious Cardiac Disease: Avoid use in patients with known structural cardiac abnormalities, cardiomyopathy, serious cardiac arrhythmias, coronary artery disease, or other serious cardiac disease. ( 5.2 ) Increased Blood Pressure and Heart Rate: Monitor blood pressure and pulse. ( 5.3 ) Psychiatric Adverse Reactions: Prior to initiating methylphenidate hydrochloride extended-release capsules, screen patients for risk factors for developing a manic episode.
If new psychotic or manic symptoms occur, consider discontinuing methylphenidate hydrochloride extended-release capsules. ( 5.4 ) Priapism: If abnormally sustained or frequent and painful erections occur, patients should seek immediate medical attention. ( 5.5 ) Peripheral Vasculopathy, including Raynaud's Phenomenon: Careful observation for digital changes is necessary during methylphenidate hydrochloride extended-release capsules treatment.
Further clinical evaluation (e.g., rheumatology referral) may be appropriate for patients who develop signs or symptoms of peripheral vasculopathy. ( 5.6 ) Long-Term Suppression of Growth in Pediatric Patients: Closely monitor growth (height and weight) in pediatric patients. Pediatric patients not growing or gaining height or weight as expected may need to have their treatment interrupted.
( 5.7 ) Acute Angle Closure Glaucoma: Methylphenidate hydrochloride extended-release capsules-treated patients considered at risk for acute angle closure glaucoma (e.g., patients with significant hyperopia) should be evaluated by an ophthalmologist. ( 5.8 ) Increased Intraocular Pressure (IOP) and Glaucoma: Prescribe methylphenidate hydrochloride extended-release capsules to patients with open-angle glaucoma or abnormally increased IOP only if the benefit of treatment is considered to outweigh the risk. Closely monitor patients with a history of increased IOP or open angle glaucoma.
( 5.9 ) Motor and Verbal Tics, and Worsening of Tourette's Syndrome: Before initiating methylphenidate hydrochloride extended-release capsules, assess the family history and clinically evaluate patients for tics or Tourette's syndrome. Regularly monitor patients for the emergence or worsening of tics or Tourette's syndrome. Discontinue treatment if clinically appropriate.
( 5.10 )
5.1Abuse, Misuse, and Addiction Methylphenidate hydrochloride extended-release capsules have a high potential for abuse and misuse. The use of methylphenidate hydrochloride extended-release capsules exposes individuals to the risks of abuse and misuse, which can lead to the development of a substance use disorder, including addiction. Methylphenidate hydrochloride extended-release capsules can be diverted for non-medical use into illicit channels or distribution [see Drug Abuse and Dependence (9.2) ].
Misuse and abuse of CNS stimulants, including methylphenidate hydrochloride extended-release capsules, can result in overdose and death [see Overdosage (10) ] , and this risk is increased with higher doses or unapproved methods of administration, such as snorting or injection. Before prescribing methylphenidate hydrochloride extended-release capsules, assess each patient's risk for abuse, misuse, and addiction. Educate patients and their families about these risks and proper disposal of any unused drug.
Advise patients to store methylphenidate hydrochloride extended-release capsules in a safe place, preferably locked, and instruct patients to not give methylphenidate hydrochloride extended-release capsules to anyone else. Throughout methylphenidate hydrochloride extended-release capsules treatment, reassess each patient's risk of abuse, misuse, and addiction and frequently monitor for signs and symptoms of abuse, misuse, and addiction.
5.2Risks to Patients with Serious Cardiac Disease Sudden death has been reported in patients with structural cardiac abnormalities or other serious cardiac disease who were treated with CNS stimulants at the recommen… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following are discussed in more detail in other sections of the labeling: Abuse, Misuse, and Addiction [see Boxed Warning , Warnings and Precautions (5.1) , and Drug Abuse and Dependence (9.2 , 9.3) ] Hypersensitivity to Methylphenidate [see Contraindications (4) ] Hypertensive Crisis with Concomitant Use of Monoamine Oxidase Inhibitors [see Contraindications (4) and Drug Interactions (7.1) ] Risks to Patients with Serious Cardiac Disease [see Warnings and Precautions (5.2) ] Increased Blood Pressure and Heart Rate [see Warnings and Precautions (5.3) ] Psychiatric Adverse Reactions [see Warnings and Precautions (5.4) ] Priapism [see Warnings and Precautions (5.5) ] Peripheral Vasculopathy, including Raynaud's Phenomenon [see Warnings and Precautions (5.6) ] Long-Term Suppression of Growth in Pediatric Patients [see Warnings and Precautions (5.7) ] Acute Angle Closure Glaucoma [see Warnings and Precautions (5.8) ] Increased Intraocular Pressure and Glaucoma [see Warnings and Precautions (5.9) ] Motor and Verbal Tics, and Worsening of Tourette's Syndrome [see Warnings and Precautions (5.10) ] The most common adverse reactions in double-blind clinical trials (> 5% and twice the rate of placebo) in pediatric patients 6 to 17 years were abdominal pain, decreased appetite, headache and insomnia.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Rhodes Pharmaceuticals LLC at 1-888-873-5329; or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Adverse Reactions in Studies with Other Methylphenidate Products in Children, Adolescents, and Adults with ADHD Commonly reported (≥2% of the methylphenidate group and at least twice the rate of the placebo group) adverse reactions from placebo-controlled trials of methylphenidate products include: decreased appetite, decreased weight, nausea, abdominal pain, dyspepsia, dry mouth, vomiting, insomnia, anxiety, nervousness, restlessness, affect lability, agitation, irritability, dizziness, vertigo, tremor, blurred vision, increased blood pressure, increased heart rate, tachycardia, palpitations, hyperhidrosis, and pyrexia.
Adverse Reactions in Studies with Methylphenidate Hydrochloride Extended-Release Capsules in Pediatric Patients with ADHD The safety data in this section is based on data from two one-week controlled clinical studies of methylphenidate hydrochloride extended-release capsules in pediatric patients with ADHD, one in children ages 6 to 12 years (RP-BP-EF001, hereafter "Study 1"), and one in children and adolescents ages 6 to 17 years (RP-BP-EF002, hereafter "Study 2"). Two methylphenidate hydrochloride extended-release capsules clinical studies evaluated a total of 256 patients with ADHD.
Two hundred and forty-three (243) patients participated in the double-blind phase of these two clinical studies. Study 1 was a randomized, double-blind, single center, placebo-controlled, flexible-dose, cross-over study to evaluate the time of onset, duration of efficacy, tolerability and safety of methylphenidate hydrochloride extended-release capsules 15 mg, 20 mg, 30 mg, or 40 mg administered for one week in 26 pediatric patients aged 6 to 12 years who met DSM-IV criteria for ADHD [see Clinical Studies (14) ] . Most Common Adverse Reactions (incidence of ≥ 5% and at a rate at least twice placebo): abdominal pain, pyrexia and headache.
Adverse Reactions Leading to Discontinuation: No subjects discontinued due to adverse reactions during the double-blind phase of this study. Study 2 was a randomized, double-blind, multicenter, placebo-controlled, parallel group, fixed-dose study of 10 mg, 15 mg, 20 mg, and 40 mg of methylphenidate hydrochloride extended-release capsules adm… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Antihypertensive Drugs: Monitor blood pressure. Adjust dosage of antihypertensive drug as needed. ( 7 )
7.1Clinically Important Interactions with Methylphenidate Hydrochloride Extended-Release Capsules Monoamine Oxidase Inhibitors (MAOIs) Do not administer methylphenidate hydrochloride extended-release capsules concomitantly or within 14 days after discontinuing MAOI treatment. Concomitant use of MAOIs and CNS stimulants can cause hypertensive crisis. Potential outcomes include death, stroke, myocardial infarction, aortic dissection, ophthalmological complications, eclampsia, pulmonary edema, and renal failure [see Contraindications (4) ].
Antihypertensive Drugs Methylphenidate hydrochloride extended-release capsules may decrease the effectiveness of drugs used to treat hypertension. Monitor blood pressure and adjust the dosage of the antihypertensive drug as needed [see Warnings and Precautions (5.3) ] . Halogenated Anesthetics Concomitant use of halogenated anesthetics and methylphenidate hydrochloride extended-release capsules may increase the risk of sudden blood pressure and heart rate increase during surgery.
Avoid use of methylphenidate hydrochloride extended-release capsules in patients being treated with anesthetics on the day of surgery. Risperidone Combined use of methylphenidate with risperidone when there is a change, whether an increase or decrease, in dosage of either or both medications, may increase the risk of extrapyramidal symptoms (EPS). Monitor for signs of EPS.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to methylphenidate hydrochloride extended-release capsules during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for Psychostimulants at 1-866-961-2388. Risk Summary Limited published studies report on the use of methylphenidate in pregnant women; however, the data are insufficient to inform any drug-associated risks.
No effects on morphological development were observed in embryo-fetal development studies with oral administration of methylphenidate to pregnant rats and rabbits during organogenesis at doses up to 10 and 15 times, respectively, the maximum recommended human dose (MRHD) of 60 mg/day given to adolescents on a mg/m 2 basis. However, spina bifida was observed in rabbits at a dose 52 times the MRHD given to adolescents. A decrease in pup body weight was observed in a pre- and post-natal development study with oral administration of methylphenidate to rats throughout pregnancy and lactation at the highest dose of 60 mg/kg/day (6 times the MRHD given to adolescents) [see Data ].
The background risk of major birth defects and miscarriage for the indicated population are unknown. However, the background risk in the U.S. general population of major birth defects is 2% to 4% and of miscarriage is 15% to 20% of clinically recognized pregnancies. Clinical Considerations Fetal/Neonatal adverse reactions CNS stimulants, such as methylphenidate hydrochloride extended-release capsules, can cause vasoconstriction and thereby decrease placental perfusion.
No fetal and/or neonatal adverse reactions have been reported with the use of therapeutic doses of methylphenidate during pregnancy; however, premature delivery and low birth weight infants have been reported in amphetamine-dependent mothers. Data Animal Data In embryo-fetal development studies conducted in rats and rabbits, methylphenidate was administered orally at doses of up to 75 and 200 mg/kg/day, respectively, during the period of organogenesis. Malformations (increased incidence of fetal spina bifida) were observed in rabbits at the highest dose, which is approximately 52 times the maximum recommended human dose (MRHD) of 60 mg/day given to adolescents on a mg/m 2 basis.
The no effect level for embryo-fetal development in rabbits was 60 mg/kg/day (15 times the MRHD given to adolescents on a mg/m 2 basis). There was no evidence of morphological development effects in rats, although increased incidences of fetal skeletal variations were seen at the highest dose level (10 times the MRHD of 60 mg/day given to adolescents on a mg/m 2 basis), which was also maternally toxic. The no effect level for embryo-fetal development in rats was 25 mg/kg/day (2 times the MRHD on a mg/m 2 basis).
When methylphenidate was administered to rats throughout pregnancy and lactation at doses of up to 45 mg/kg/day, offspring body weight gain was decreased at the highest dose (6 times the MRHD of 60 mg/day given to adolescents on a mg/m 2 basis), but no other effects on postnatal development were observed. The no effect level for pre- and postnatal development in rats was 15 mg/kg/day (1.5 times the MRHD given to adolescents on a mg/m 2 basis).
8.2Lactation Risk Summary Limited published literature, based on breast milk sampling from five mothers, reports that methylphenidate is present in human milk, which resulted in infant doses of 0.16% to 0.7% of the maternal weight-adjusted dosage and a milk/plasma ratio ranging between 1.1 and 2.7. There are no reports of adverse effects on the breastfed infant and no effects on milk production. However, long-term neurodevelopmental effects on infants from stimulant exposure are unknown.
The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for methylphenidate hydrochloride ex… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to methylphenidate hydrochloride extended-release capsules during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for Psychostimulants at 1-866-961-2388. Risk Summary Limited published studies report on the use of methylphenidate in pregnant women; however, the data are insufficient to inform any drug-associated risks.
No effects on morphological development were observed in embryo-fetal development studies with oral administration of methylphenidate to pregnant rats and rabbits during organogenesis at doses up to 10 and 15 times, respectively, the maximum recommended human dose (MRHD) of 60 mg/day given to adolescents on a mg/m 2 basis. However, spina bifida was observed in rabbits at a dose 52 times the MRHD given to adolescents. A decrease in pup body weight was observed in a pre- and post-natal development study with oral administration of methylphenidate to rats throughout pregnancy and lactation at the highest dose of 60 mg/kg/day (6 times the MRHD given to adolescents) [see Data ].
The background risk of major birth defects and miscarriage for the indicated population are unknown. However, the background risk in the U.S. general population of major birth defects is 2% to 4% and of miscarriage is 15% to 20% of clinically recognized pregnancies. Clinical Considerations Fetal/Neonatal adverse reactions CNS stimulants, such as methylphenidate hydrochloride extended-release capsules, can cause vasoconstriction and thereby decrease placental perfusion.
No fetal and/or neonatal adverse reactions have been reported with the use of therapeutic doses of methylphenidate during pregnancy; however, premature delivery and low birth weight infants have been reported in amphetamine-dependent mothers. Data Animal Data In embryo-fetal development studies conducted in rats and rabbits, methylphenidate was administered orally at doses of up to 75 and 200 mg/kg/day, respectively, during the period of organogenesis. Malformations (increased incidence of fetal spina bifida) were observed in rabbits at the highest dose, which is approximately 52 times the maximum recommended human dose (MRHD) of 60 mg/day given to adolescents on a mg/m 2 basis.
The no effect level for embryo-fetal development in rabbits was 60 mg/kg/day (15 times the MRHD given to adolescents on a mg/m 2 basis). There was no evidence of morphological development effects in rats, although increased incidences of fetal skeletal variations were seen at the highest dose level (10 times the MRHD of 60 mg/day given to adolescents on a mg/m 2 basis), which was also maternally toxic. The no effect level for embryo-fetal development in rats was 25 mg/kg/day (2 times the MRHD on a mg/m 2 basis).
When methylphenidate was administered to rats throughout pregnancy and lactation at doses of up to 45 mg/kg/day, offspring body weight gain was decreased at the highest dose (6 times the MRHD of 60 mg/day given to adolescents on a mg/m 2 basis), but no other effects on postnatal development were observed. The no effect level for pre- and postnatal development in rats was 15 mg/kg/day (1.5 times the MRHD given to adolescents on a mg/m 2 basis).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of methylphenidate hydrochloride extended-release capsules have not been established in pediatric patients below the age of 6 years. Safety and efficacy of methylphenidate hydrochloride extended-release capsules were evaluated in a multicenter, placebo-controlled, double-blind, parallel group study in 119 children 4 to <6 years of age with ADHD followed by a 12-month open-label extension in 44 of these children. In these studies, patients experienced high rates of adverse reactions, most notably weight loss.
Comparing weights prior to initiation of methylphenidate hydrochloride extended-release capsules (in the safety and efficacy study) to weights after 12 months of treatment (in the open-label extension), 20 of 39 patients with data (50%) had lost enough weight to decrease 10 or more percentiles on a Centers for Disease Control growth chart for weight. In addition, systemic drug exposures in patients 4 to <6 years of age were higher than those observed in older children and adolescents at the same dose (2 to 3 fold higher C max and AUC).
Therefore, the benefits of methylphenidate hydrochloride extended-release capsules do not outweigh the risks in pediatric patients 4 to <6 years of age. The safety and effectiveness of methylphenidate hydrochloride extended-release capsules have been established in pediatric patients ages 6 to 17 years in two adequate and well-controlled clinical trials [see Clinical Studies (14) ] . Long Term Suppression of Growth Growth should be monitored during treatment with stimulants, including methylphenidate hydrochloride extended-release capsules.
Pediatric patients who are not growing or gaining weight as expected may need to have their treatment interrupted [see Warnings and Precautions (5.7) ] . Juvenile Animal Toxicity Data Rats treated with methylphenidate early in the postnatal period through sexual maturation demonstrated a decrease in spontaneous locomotor activity in adulthood. A deficit in acquisition of a specific learning task was observed in females only.
The doses at which these findings were observed are at least 6 times the maximum recommended human dose (MRHD) of 60 mg/day given to children on a mg/m 2 basis. In the study conducted in young rats, methylphenidate was administered orally at doses of up to 100 mg/kg/day for 9 weeks, starting early in the postnatal period (postnatal day 7) and continuing through sexual maturity (postnatal week 10). When these animals were tested as adults (postnatal weeks 13-14), decreased spontaneous locomotor activity was observed in males and females previously treated with 50 mg/kg/day (approximately 6 times the MRHD of 60 mg/day given to children on a mg/m 2 basis) or greater, and a deficit in the acquisition of a specific learning task was observed in females exposed to the highest dose (8 times the MRHD given to children on a mg/m 2 basis).
The no effect level for juvenile neurobehavioral development in rats was 5 mg/kg/day (approximately 0.5 times the MRHD given to children on a mg/m 2 basis). The clinical significance of the long-term behavioral effects observed in rats is unknown.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of methylphenidate hydrochloride extended-release capsules did not include any patients aged 65 years and over. In general, dose selection for an elderly patient start at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Clinical Effects of Overdose Overdose of CNS stimulants is characterized by the following sympathomimetic effects: Cardiovascular effects including tachyarrhythmias, and hypertension or hypotension. Vasospasm, myocardial infarction, or aortic dissection may precipitate sudden cardiac death. Takotsubo cardiomyopathy may develop.
CNS effects including psychomotor agitation, confusion, and hallucinations. Serotonin syndrome, seizures, cerebral vascular accidents, and coma may occur. Life-threatening hyperthermia (temperatures greater than 104°F) and rhabdomyolysis may develop.
Overdose Management Consider the possibility of multiple drug ingestion. The pharmacokinetic profile of methylphenidate hydrochloride extended-release capsules should be considered when treating patients with overdose. Because methylphenidate has a large volume of distribution and is rapidly metabolized, dialysis is not useful.
Consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdose management recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Methylphenidate HCl is a central nervous system (CNS) stimulant. The mode of therapeutic action in ADHD is not known.
12.2Pharmacodynamics Methylphenidate is a racemic mixture comprised of the d- and l- isomers. The d- isomer is more pharmacologically active than the l- isomer. Methylphenidate blocks the reuptake of norepinephrine and dopamine into the presynaptic neuron and increase the release of these monoamines into the extraneuronal space.
12.3Pharmacokinetics Absorption Following oral administration of methylphenidate hydrochloride extended-release capsules in adults, plasma methylphenidate concentrations increase rapidly, reaching an initial maximum at about 2 hours, followed by gradual descending concentrations over the next 4 to 6 hours, after which a gradual increase begins, reaching a second peak at approximately 8 hours (Figure 1). The relative bioavailability of methylphenidate hydrochloride extended-release capsules given once daily as compared to a methylphenidate immediate-release oral product given three times daily in adults is comparable.
The relative bioavailability is 102%. The pharmacokinetic profiles and parameters of methylphenidate are similar when methylphenidate hydrochloride extended-release capsules are administered either as a whole capsule or sprinkled onto applesauce in subjects under fasting conditions (see Table 2 and Figure 1 ). Table 2: The Single Dose Pharmacokinetics of d,l-Methylphenidate d,l (racemic) methylphenidate HCl ER Capsule and Sprinkle following an Oral Dose of 80 mg Methylphenidate Hydrochloride Extended-Release Capsules under Fasted Conditions in Healthy Adults Pharmacokinetic Parameters Capsule Sprinkle C max C max , AUC (0-t) AUC (0-inf) presented as mean ± SD (ng/mL) 23.47 ± 11.4 21.78 ±
9.5AUC (0-t) (ng.hr/mL) 262.7 ± 135 262.9 ± 128 AUC (0-inf ) (ng.hr/mL) 258.1 ± 94.2 258.0 ±
84.4T max (hr) data presented as median (range) 2.0
2.0Half-life (hr) 5.09
5.43Relative bioavailability 102% 101% Figure 1: Mean d,l-Methylphenidate Plasma Concentration-Time Profiles following 80 mg Administered as Capsule and Sprinkle Dose in Healthy Adults Figure 1 Metabolism and Excretion In humans, methylphenidate is metabolized primarily via deesterification to alpha-phenyl-piperidine acetic acid (PPAA). The metabolite has little or no pharmacologic activity. After oral dosing of radiolabeled methylphenidate in humans, about 90% of the radioactivity was recovered in urine.
The main urinary metabolite was PPAA, accounting for approximately 80% of the dose. Food Effects Administration of methylphenidate hydrochloride extended-release capsules with high fat meal showed a decreased or diminished second peak. A high-fat meal also increased the average C max of methylphenidate by about 28% and the AUC by about 19%.
In the clinical trials of methylphenidate hydrochloride extended-release capsules, it was administered without regard to meals. Alcohol Effect At an alcohol concentration up to 40%, there was 96% release of methylphenidate from methylphenidate hydrochloride extended-release capsules 80 mg capsule within two hours. The results with the 80 mg capsule are considered to be representative of the other available capsules strengths.
Studies in Specific Populations Gender There is insufficient experience with the use of methylphenidate hydrochloride extended-release capsules to detect gender variations in pharmacokinetics. Race There is insufficient experience with the use of methylphenidate hydrochloride extended-release capsules to detect ethnic variations in pharmacokinetics. Age The pharmacokinetics of methylphenidate after methylphenidate hydrochloride extended-release capsules administration was studied in pediatric patients with ADHD between 6 and 12 years of age.
Following administration of methylphenidate hydrochloride extended-release capsules, the bi-phasic plasma methylphenidate concentration profile was qualitatively similar in… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Methylphenidate HCl is a central nervous system (CNS) stimulant. The mode of therapeutic action in ADHD is not known.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Methylphenidate Hydrochloride Extended-Release Capsules are available as follows: 10 mg Extended-Release Capsules - white opaque body & light turquoise blue opaque cap containing white spherical beads. Body Imprinting "910". Cap imprinting "RP" Bottles of 90 NDC 42858-075-45 15 mg Extended-Release Capsules - white opaque body and orange cap containing white spherical beads.
Body imprinting "915". Cap imprinting "RP" Bottles of 90 NDC 42858-076-45 20 mg Extended-Release Capsules - white opaque body and yellow opaque cap containing white spherical beads. Body imprinting "920".
Cap imprinting "RP" Bottles of 90 NDC 42858-077-45 30 mg Extended-Release Capsules - white opaque body and blue violet cap containing white spherical beads. Body imprinting "930". Cap imprinting "RP" Bottles of 90 NDC 42858-078-45 40 mg Extended-Release Capsules - white opaque body and pink opaque cap containing white spherical beads.
Body imprinting "940". Cap imprinting "RP" Bottles of 90 NDC 42858-079-45 50 mg Extended-Release Capsules - white opaque body and green opaque cap containing white spherical beads. Body imprinting "950".
Cap Imprinting "RP" Bottles of 90 NDC 42858-080-45 60 mg Extended-Release Capsules - white opaque body and gray opaque cap containing white spherical beads. Body imprinting "960". Cap imprinting "RP" Bottles of 90 NDC 42858-081-45 Storage and Handling Methylphenidate Hydrochloride Extended-Release Capsules should be stored at 20°C to 25°C (68°F to 77°F) [see USP Controlled Room Temperature].
Protect from moisture. Dispense in tight container (USP).
📦 Storage and Handling ▾
Storage and Handling Methylphenidate Hydrochloride Extended-Release Capsules should be stored at 20°C to 25°C (68°F to 77°F) [see USP Controlled Room Temperature]. Protect from moisture. Dispense in tight container (USP).
📋 Description ▾
11 DESCRIPTION Methylphenidate hydrochloride extended-release capsules contain methylphenidate hydrochloride, a central nervous system (CNS) stimulant. Methylphenidate hydrochloride extended-release capsules contain multi layered beads, which are composed of an immediate-release layer which contains approximately 40% of the methylphenidate dose, and a controlled release layer which contains approximately 60% of the methylphenidate dose. Methylphenidate hydrochloride extended-release capsules are available in seven capsule strengths.
Each extended-release capsule for once-a-day oral administration contains 10 mg, 15 mg, 20 mg, 30 mg, 40 mg, 50 mg, or 60 mg of methylphenidate HCl USP, which is equivalent to 8.6 mg, 13.0 mg, 17.3 mg, 25.9 mg, 34.6 mg, 43.2 mg, or 51.9 mg of methylphenidate free base, respectively. Chemically, methylphenidate HCl is d,l (racemic) methyl α-phenyl-2-piperidineacetate hydrochloride. Its molecular formula is C 14 H 19 NO 2 ∙HCl.
Its structural formula is: Methylphenidate hydrochloride USP is a white to off-white, odorless, fine crystalline powder. Its solutions are acid to litmus. It is freely soluble in water and in methanol, soluble in alcohol, and slightly soluble in chloroform and in acetone.
Its molecular weight is 269.77. Inactive Ingredients: ammonio methacrylate copolymer, type B; colloidal silicon dioxide (added if necessary); gelatin; hypromelloses; methacrylic acid copolymer, type C; polyethylene glycol; sugar spheres; talc; titanium oxide; and triethyl citrate. Each strength capsule also contains colorant ingredients in the capsule shell as follows: 10 mg: FD&C Blue No.
1 15 mg: D&C Red No. 28, D&C Yellow No. 10, FD&C Red No.
40 20 mg: D&C Red No. 33, D&C Yellow No. 10 30 mg: FD&C Blue No.
1, FD&C Red No. 3 40 mg: D&C Red No. 28, FD&C Blue No.
1, FD&C Red No. 40 50 mg: D&C Yellow No. 10, FD&C Green No.
3 60 mg: Black Iron Oxide Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients to read the FDA-approved patient labeling (Medication Guide). Abuse, Misuse, and Addiction Educate patients and their families about the risks of abuse, misuse, and addiction of methylphenidate hydrochloride extended-release capsules, which can lead to overdose and death, and proper disposal of any unused drug [see Warnings and Precautions (5.1) , Drug Abuse and Dependence (9.2) , Overdosage (10) ] . Advise patients to store methylphenidate hydrochloride extended-release capsules in a safe place, preferably locked, and instruct patients to not give methylphenidate hydrochloride extended-release capsules to anyone else.
Dosage and Administration Instructions Advise patients that methylphenidate hydrochloride extended-release capsules can be taken with or without food and that they should establish a routine pattern of taking methylphenidate hydrochloride extended-release capsules with regard to meals. For patients who take methylphenidate hydrochloride extended-release capsules sprinkled over applesauce, the contents of the entire capsule should be consumed immediately; it should not be stored. Patients should take the applesauce with sprinkled beads in its entirety without chewing.
When initiating treatment with methylphenidate hydrochloride extended-release capsules, provide dosage escalation and administration instructions [see Dosage and Administration (2.2) ]. Risks to Patients with Serious Cardiac Disease Advise patients that there are potential risks to patient with serious cardiac disease, including sudden death, with methylphenidate hydrochloride extended-release capsules use. Instruct patients to contact a healthcare provider immediately if they develop symptoms such as exertional chest pain, unexplained syncope, or other symptoms suggestive of cardiac disease [see Warnings and Precautions (5.2) ].
Increased Blood Pressure and Heart Rate Instruct patients that methylphenidate hydrochloride extended-release capsules can cause elevations of their blood pressure and pulse rate [see Warnings and Precautions (5.3) ] . Psychiatric Adverse Reactions Advise patients that methylphenidate hydrochloride extended-release capsules, at recommended doses, can cause psychotic or manic symptoms, even in patients without prior history of psychotic symptoms or mania [see Warnings and Precautions (5.4) ]. Priapism Advise patients of the possibility of painful or prolonged penile erections (priapism).
Instruct them to seek immediate medical attention in the event of priapism [see Warnings and Precautions (5.5) ]. Circulation problems in fingers and toes [Peripheral vasculopathy, including Raynaud's phenomenon] Instruct patients beginning treatment with methylphenidate hydrochloride extended-release capsules about the risk of peripheral vasculopathy, including Raynaud's Phenomenon, and associated signs and symptoms: fingers or toes may feel numb, cool, painful, and/or may change from pale, to blue, to red. Instruct patients to report to their physician any new numbness, pain, skin color change, or sensitivity to temperature in fingers or toes.
Instruct patients to call their physician immediately with any signs of unexplained wounds appearing on fingers or toes while taking methylphenidate hydrochloride extended-release capsules. Further clinical evaluation (e.g. rheumatology referral) may be appropriate for certain patients [see Warnings and Precautions (5.6) ]. Long-Term Suppression of Growth in Pediatric Patients Advise patients that methylphenidate hydrochloride extended-release capsules may cause slowing of growth and weight loss [see Warnings and Precautions (5.7) ].
Increased Intraocular Pressure (IOP) and Glaucoma Advise patients that IOP and glaucoma may occur during treatment with methylphenidate hydrochloride extended-release capsules [see Warnings and Precautions (5.9) ]. Motor and Verbal Tics, and Worsening of Tourette's Syndrome Advise patients that motor and verbal tics and w… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
MEDICATION GUIDE Methylphenidate (METH-il-FEN-i-date) Hydrochloride Extended-Release Capsules, CII This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: 05/2026 What is the most important information I should know about methylphenidate hydrochloride extended-release capsules?
Methylphenidate hydrochloride extended-release capsules may cause serious side effects, including: Abuse, misuse, and addiction. Methylphenidate hydrochloride extended-release capsules have a high chance for abuse and misuse and may lead to substance use problems, including addiction. Misuse and abuse of methylphenidate hydrochloride extended-release capsules, other methylphenidate containing medicines, and amphetamine containing medicines, can lead to overdose and death.
The risk of overdose and death is increased with higher doses of methylphenidate hydrochloride extended-release capsules or when it is used in ways that are not approved, such as snorting or injection. Your healthcare provider should check you or your child's risk for abuse, misuse, and addiction before starting treatment with methylphenidate hydrochloride extended-release capsules and will monitor you or your child during treatment. Methylphenidate hydrochloride extended-release capsules may lead to physical dependence after prolonged use, even if taken as directed by your healthcare provider.
Do not give methylphenidate hydrochloride extended-release capsules to anyone else. See " What are methylphenidate hydrochloride extended-release capsules? " for more information. Keep methylphenidate hydrochloride extended-release capsules in a safe place and properly dispose of any unused medicine.
See " How should I store methylphenidate hydrochloride extended-release capsules? " for more information. Tell your healthcare provider if you or your child have ever abused or been dependent on alcohol, prescription medicines, or street drugs. Risks for people with serious heart disease.
Sudden death has happened in people who have heart defects or other serious heart disease. Your healthcare provider should check you or your child carefully for heart problems before starting treatment with methylphenidate hydrochloride extended-release capsules. Tell your healthcare provider if you or your child have any heart problems, heart disease, or heart defects.
Your healthcare provider should check you or your child's blood pressure and heart rate regularly during treatment with methylphenidate hydrochloride extended-release capsules. Call your healthcare provider or go the nearest hospital emergency room right away if you or your child have any signs of heart problems such as chest pain, shortness of breath, or fainting during treatment with methylphenidate hydrochloride extended-release capsules Increased blood pressure and heart rate. Your healthcare provider should check your or your child's blood pressure and heart rate regularly during treatment with methylphenidate hydrochloride extended-release capsules.
Mental (psychiatric) problems, including: new or worse behavior and thought problems new or worse bipolar illness new psychotic symptoms (such as hearing voices, or seeing or believing things that are not real) or new manic symptoms Tell your healthcare provider about any mental problems you or your child have, or about a family history of suicide, bipolar illness, or depression. Call your healthcare provider right away if you or your child have any new or worsening mental symptoms or problems during treatment with methylphenidate hydrochloride extended-release capsules, especially hearing voices, seeing or believing things that are not real, or new manic symptoms.
What are methylphenidate hydrochloride extended-release capsules? Methylphenidate hydrochloride extended-release capsules are a central nervous system (CNS) stimulant prescription medicine used for the treatment of Attention Deficit Hyperactivity Disorder (ADHD) in people 6 years of age and older. Methy… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption Following oral administration of methylphenidate hydrochloride extended-release capsules in adults, plasma methylphenidate concentrations increase rapidly, reaching an initial maximum at about 2 hours, followed by gradual descending concentrations over the next 4 to 6 hours, after which a gradual increase begins, reaching a second peak at approximately 8 hours (Figure 1). The relative bioavailability of methylphenidate hydrochloride extended-release capsules given once daily as compared to a methylphenidate immediate-release oral product given three times daily in adults is comparable.
The relative bioavailability is 102%. The pharmacokinetic profiles and parameters of methylphenidate are similar when methylphenidate hydrochloride extended-release capsules are administered either as a whole capsule or sprinkled onto applesauce in subjects under fasting conditions (see Table 2 and Figure 1 ). Table 2: The Single Dose Pharmacokinetics of d,l-Methylphenidate d,l (racemic) methylphenidate HCl ER Capsule and Sprinkle following an Oral Dose of 80 mg Methylphenidate Hydrochloride Extended-Release Capsules under Fasted Conditions in Healthy Adults Pharmacokinetic Parameters Capsule Sprinkle C max C max , AUC (0-t) AUC (0-inf) presented as mean ± SD (ng/mL) 23.47 ± 11.4 21.78 ±
9.5AUC (0-t) (ng.hr/mL) 262.7 ± 135 262.9 ± 128 AUC (0-inf ) (ng.hr/mL) 258.1 ± 94.2 258.0 ±
84.4T max (hr) data presented as median (range) 2.0
2.0Half-life (hr) 5.09
5.43Relative bioavailability 102% 101% Figure 1: Mean d,l-Methylphenidate Plasma Concentration-Time Profiles following 80 mg Administered as Capsule and Sprinkle Dose in Healthy Adults Figure 1 Metabolism and Excretion In humans, methylphenidate is metabolized primarily via deesterification to alpha-phenyl-piperidine acetic acid (PPAA). The metabolite has little or no pharmacologic activity. After oral dosing of radiolabeled methylphenidate in humans, about 90% of the radioactivity was recovered in urine.
The main urinary metabolite was PPAA, accounting for approximately 80% of the dose. Food Effects Administration of methylphenidate hydrochloride extended-release capsules with high fat meal showed a decreased or diminished second peak. A high-fat meal also increased the average C max of methylphenidate by about 28% and the AUC by about 19%.
In the clinical trials of methylphenidate hydrochloride extended-release capsules, it was administered without regard to meals. Alcohol Effect At an alcohol concentration up to 40%, there was 96% release of methylphenidate from methylphenidate hydrochloride extended-release capsules 80 mg capsule within two hours. The results with the 80 mg capsule are considered to be representative of the other available capsules strengths.
Studies in Specific Populations Gender There is insufficient experience with the use of methylphenidate hydrochloride extended-release capsules to detect gender variations in pharmacokinetics. Race There is insufficient experience with the use of methylphenidate hydrochloride extended-release capsules to detect ethnic variations in pharmacokinetics. Age The pharmacokinetics of methylphenidate after methylphenidate hydrochloride extended-release capsules administration was studied in pediatric patients with ADHD between 6 and 12 years of age.
Following administration of methylphenidate hydrochloride extended-release capsules, the bi-phasic plasma methylphenidate concentration profile was qualitatively similar in healthy adult volunteers and pediatric patients with ADHD. The bi-phasic profile in both groups is characterized by an early peak due to rapid absorption of the immediate-release component followed by a delayed, secondary peak due to the controlled-release component of methylphenidate hydrochloride extended-release capsules. Renal Insufficiency There is no experience with the use of methylphenidate hydrochloride extended-release capsules in patients with renal insufficiency.
After oral administr… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Methylphenidate is a racemic mixture comprised of the d- and l- isomers. The d- isomer is more pharmacologically active than the l- isomer. Methylphenidate blocks the reuptake of norepinephrine and dopamine into the presynaptic neuron and increase the release of these monoamines into the extraneuronal space.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The efficacy of methylphenidate hydrochloride extended-release capsules for the treatment of ADHD was established in a randomized, double-blind, single center, placebo-controlled, flexible-dose, cross-over trial in pediatric patients aged 6 to 12 years and a second randomized, double-blind, multicenter, placebo-controlled, fixed–dose trial in pediatric patients 6 to 17 years. Pediatric Patients A randomized, double-blind, placebo-controlled, flexible-dose, cross-over, analog classroom study (Study 1) was conducted in pediatric patients ages 6 to 12 years (N=26) who met DSM-IV-TR criteria for ADHD inattentive, hyperactive-impulsive or combined inattentive/hyperactive-impulsive subtypes.
Following a 2 to 4 week open-label dose optimization phase in which patients received flexible-dose methylphenidate hydrochloride extended-release capsules 15 mg, 20 mg, 30 mg, or 40 mg administered once daily in the morning, patients were randomly assigned to methylphenidate hydrochloride extended-release capsules (dose from open-label phase) or placebo. After 1-week of treatment, patients were evaluated over a period of 12 hours. Subsequently, patients were given the opposite treatment for 1-week and returned for the second evaluation.
Patients could then enter an open-label extension phase for up to 21 months. Efficacy assessments were conducted at 1, 2, 3, 4.5, 6, 7.5, 9, 10.5 and 12 hours post-dose using the Swanson, Kotkin, Agler, M. Flynn, and Pelham Total score (SKAMP).
The primary efficacy endpoint was the average SKAMP Total Score, comparing methylphenidate hydrochloride extended-release capsules to placebo. SKAMP is a validated 13-item teacher-rated scale that assesses manifestations of ADHD in a classroom setting. The SKAMP Total Scores were statistically significantly better (lower) for methylphenidate hydrochloride extended-release capsules than for placebo at the test day average and at all time points (1, 2, 3, 4.5, 6, 7.5, 9, 10.5 and 12 hours) post-dosing (see Figure 2 ).
Figure 2: Absolute SKAMP- Total Score after treatment with Methylphenidate Hydrochloride Extended-Release Capsules or Placebo (Study 1). A randomized, double-blind, multicenter, placebo-controlled, parallel-group, fixed-dose study (Study 2) was conducted in pediatric patients age 6 to 17 years (N=230) who met DSM-IV-TR criteria for ADHD inattentive, hyperactive-impulsive or combined inattentive/hyperactive-impulsive subtypes. The ADHD-RS-IV is an 18-item questionnaire with a score range of 0 to 54 points that measures the core symptoms of ADHD and includes both hyperactive/impulsive and inattentive subscales.
Patients were randomized to a daily morning dose of methylphenidate hydrochloride extended-release capsules 10 mg, 15 mg, 20 mg, or 40 mg, or placebo for 1 week. An 11-week open label phase followed the double-blind phase. Patients could then enter another open-label phase for up to 21 months.
The primary efficacy endpoint was the mean decrease from baseline to the end of Week 1 in the ADHD-RS-IV Total Score. Each of the four methylphenidate hydrochloride extended-release capsules doses (10 mg, 15 mg, 20 mg, and 40 mg/day) was compared to placebo at the end of week 1. For both the 20 mg/day and the 40 mg/day doses, methylphenidate hydrochloride extended-release capsules was superior to placebo in reduction of the ADHD-RS-IV Total Score, but not for the 10 mg/day or the 15 mg/day doses.
A total of 221 patients completed the 1-week double-blind phase. Among those, 200 (90.5%) completed the 11-week open label phase and 173 (86.5%) patients continued into the 21-month open-label extension phase. Table 3: Summary of Parallel-Group Study Study Number Treatment Group Primary Efficacy Measure: ADHD-RS-IV Total Score Mean Baseline Score (SD) LS Mean Reduction from Baseline (SE) Placebo-subtracted Difference Difference (placebo minus drug) in least-squares mean change from baseline.
Positive numbers indicate reduction (improvement). (95% CI) Not… [Excerpted — this section continues on DailyMed.]
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE
9.1Controlled Substance Methylphenidate hydrochloride extended-release capsules contains methylphenidate a Schedule II controlled substance.
9.2Abuse Methylphenidate hydrochloride extended-release capsules have a high potential for abuse and misuse which can lead to the development of a substance use disorder, including addiction [see Warnings and Precautions (5.1) ] . Methylphenidate hydrochloride extended-release capsules can be diverted for non-medical use into illicit channels or distribution. Abuse is the intentional non-therapeutic use of a drug, even once, to achieve a desired psychological or physiological effect.
Misuse is the intentional use, for therapeutic purposes, of a drug by an individual in a way other than prescribed by a health care provider or for whom it was not prescribed. Drug addiction is a cluster of behavioral, cognitive, and physiological phenomena that may include a strong desire to take the drug, difficulties in controlling drug use (e.g., continuing drug use despite harmful consequences, giving a higher priority to drug use than other activities and obligations), and possible tolerance or physical dependence.
Misuse and abuse of methylphenidate may cause increased heart rate, respiratory rate, or blood pressure; sweating; dilated pupils; hyperactivity; restlessness; insomnia; decreased appetite; loss of coordination; tremors; flushed skin; vomiting; and/or abdominal pain. Anxiety, psychosis, hostility, aggression, and suicidal or homicidal ideation have also been observed with CNS stimulants abuse and/or misuse. Misuse and abuse of CNS stimulants, including methylphenidate hydrochloride extended-release capsules, can result in overdose and death [see Overdosage (10) ] , and this risk is increased with higher doses or unapproved methods of administration, such as snorting or injection.
9.3Dependence Physical Dependence Methylphenidate hydrochloride extended-release capsules may produce physical dependence. Physical dependence is a state that develops as a result of physiological adaptation in response to repeated drug use, manifested by withdrawal signs and symptoms after abrupt discontinuation or a significant dose reduction of a drug. Withdrawal signs and symptoms after abrupt discontinuation or dose reduction following prolonged use of CNS stimulants including methylphenidate hydrochloride extended-release capsules include dysphoric mood; depression; fatigue; vivid, unpleasant dreams; insomnia or hypersomnia; increased appetite; and psychomotor retardation or agitation.
Tolerance Methylphenidate hydrochloride extended-release capsules may produce tolerance. Tolerance is a physiological state characterized by a reduced response to a drug after repeated administration (i.e., a higher dose of a drug is required to produce the same effect that was once obtained at a lower dose).
🔒 Controlled Substance ▾
9.1Controlled Substance Methylphenidate hydrochloride extended-release capsules contains methylphenidate a Schedule II controlled substance.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis In a lifetime carcinogenicity study carried out in B6C3F1 mice, methylphenidate caused an increase in hepatocellular adenomas and, in males only, an increase in hepatoblastomas, at a daily dose of approximately 60 mg/kg/day. This dose is approximately 2 times the maximum recommended human dose (MRHD) of 60 mg/day given to children on a mg/m 2 basis. Hepatoblastoma is a relatively rare rodent malignant tumor type.
There was no increase in total malignant hepatic tumors. The mouse strain used is sensitive to the development of hepatic tumors, and the significance of these results to humans is unknown. Methylphenidate did not cause any increase in tumors in a lifetime carcinogenicity study carried out in F344 rats; the highest dose used was approximately 45 mg/kg/day, which is approximately 4 times the MRHD (children) on a mg/m 2 basis.
Mutagenesis Methylphenidate was not mutagenic in the in vitro Ames reverse mutation assay or in the in vitro mouse lymphoma cell forward mutation assay. Sister chromatid exchanges and chromosome aberrations were increased, indicative of a weak clastogenic response, in an in vitro assay in cultured Chinese Hamster Ovary (CHO) cells. Methylphenidate was negative in vivo in males and females in the mouse bone marrow micronucleus assay.
Impairment of Fertility Methylphenidate did not impair fertility in male or female mice that were fed diets containing the drug in an 18-week Continuous Breeding study. The study was conducted at doses of up to 160 mg/kg/day, approximately 10 times the maximum recommended human dose of 60 mg/day given to adolescents on a mg/m 2 basis.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis In a lifetime carcinogenicity study carried out in B6C3F1 mice, methylphenidate caused an increase in hepatocellular adenomas and, in males only, an increase in hepatoblastomas, at a daily dose of approximately 60 mg/kg/day. This dose is approximately 2 times the maximum recommended human dose (MRHD) of 60 mg/day given to children on a mg/m 2 basis. Hepatoblastoma is a relatively rare rodent malignant tumor type.
There was no increase in total malignant hepatic tumors. The mouse strain used is sensitive to the development of hepatic tumors, and the significance of these results to humans is unknown. Methylphenidate did not cause any increase in tumors in a lifetime carcinogenicity study carried out in F344 rats; the highest dose used was approximately 45 mg/kg/day, which is approximately 4 times the MRHD (children) on a mg/m 2 basis.
Mutagenesis Methylphenidate was not mutagenic in the in vitro Ames reverse mutation assay or in the in vitro mouse lymphoma cell forward mutation assay. Sister chromatid exchanges and chromosome aberrations were increased, indicative of a weak clastogenic response, in an in vitro assay in cultured Chinese Hamster Ovary (CHO) cells. Methylphenidate was negative in vivo in males and females in the mouse bone marrow micronucleus assay.
Impairment of Fertility Methylphenidate did not impair fertility in male or female mice that were fed diets containing the drug in an 18-week Continuous Breeding study. The study was conducted at doses of up to 160 mg/kg/day, approximately 10 times the maximum recommended human dose of 60 mg/day given to adolescents on a mg/m 2 basis.
📄 Recent Major Changes ▾
Indications and Usage ( 1 ) 09/2025 Warnings and Precautions ( 5.7 ) 09/2025
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 10 mg Capsule Bottle Label NDC 42858-075-45 CII Methylphenidate HCl Extended-Release Capsules 10 mg Dispense the accompanying Medication Guide to each patient. Rhodes R x only Once Daily 90 Capsules PRINCIPAL DISPLAY PANEL - 10 mg Capsule Bottle Label
PRINCIPAL DISPLAY PANEL - 15 mg Capsule Bottle Label NDC 42858-076-45 CII Methylphenidate HCl Extended-Release Capsules 15 mg Dispense the accompanying Medication Guide to each patient. Rhodes R x only Once Daily 90 Capsules PRINCIPAL DISPLAY PANEL - 15 mg Capsule Bottle Label
PRINCIPAL DISPLAY PANEL - 20 mg Capsule Bottle Label NDC 42858-077-45 CII Methylphenidate HCl Extended-Release Capsules 20 mg Dispense the accompanying Medication Guide to each patient. Rhodes R x only Once Daily 90 Capsules PRINCIPAL DISPLAY PANEL - 20 mg Capsule Bottle Label
PRINCIPAL DISPLAY PANEL - 30 mg Capsule Bottle Label NDC 42858-078-45 CII Methylphenidate HCl Extended-Release Capsules 30 mg Dispense the accompanying Medication Guide to each patient. Rhodes R x only Once Daily 90 Capsules PRINCIPAL DISPLAY PANEL - 30 mg Capsule Bottle Label
PRINCIPAL DISPLAY PANEL - 40 mg Capsule Bottle Label NDC 42858-079-45 CII Methylphenidate HCl Extended-Release Capsules 40 mg Dispense the accompanying Medication Guide to each patient. Rhodes R x only Once Daily 90 Capsules PRINCIPAL DISPLAY PANEL - 40 mg Capsule Bottle Label
PRINCIPAL DISPLAY PANEL - 50 mg Capsule Bottle Label NDC 42858-080-45 CII Methylphenidate HCl Extended-Release Capsules 50 mg Dispense the accompanying Medication Guide to each patient. Rhodes R x only Once Daily 90 Capsules PRINCIPAL DISPLAY PANEL - 50 mg Capsule Bottle Label
PRINCIPAL DISPLAY PANEL - 60 mg Capsule Bottle Label NDC 42858-081-45 CII Methylphenidate HCl Extended-Release Capsules 60 mg Dispense the accompanying Medication Guide to each patient. Rhodes R x only Once Daily 90 Capsules PRINCIPAL DISPLAY PANEL - 60 mg Capsule Bottle Label
Medicaid utilization & spend
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |