
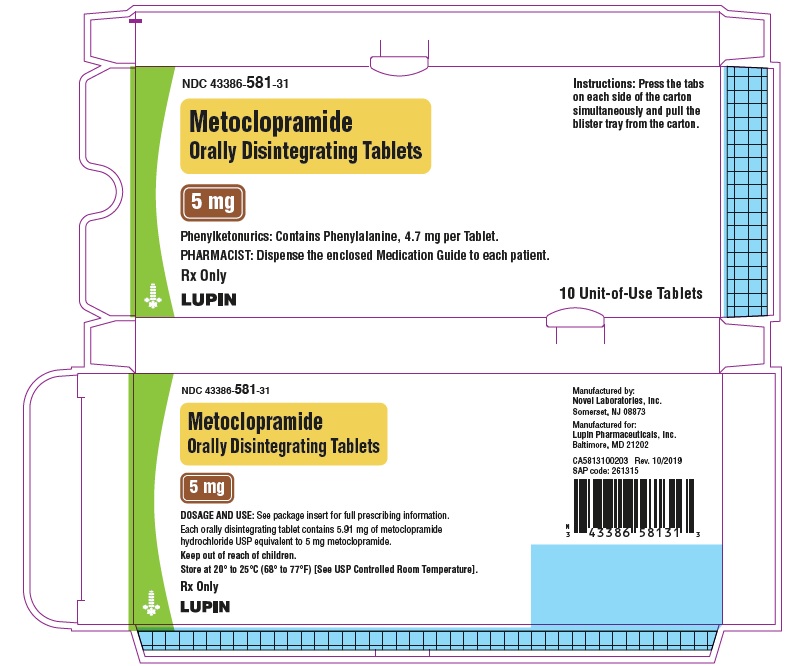
METOCLOPRAMIDE hydrochloride 5 mg Tablet, Orally Disintegrating, 10-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Dopamine-2 Receptor Antagonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Metoclopramide is used to treat gastroesophageal reflux disease (GERD; condition in which backward flow of acid from the stomach causes heartburn and injury of the esophagus) and gastroparesis (slow stomach emptying) . Metoclopramide is in a class of medications called prokinetic agents. It works by speeding the movement of food through the stomach and intestines.
Read the full MedlinePlus article ↗- It helps your digestive system move food along faster. If you have acid reflux, it tightens the valve between your esophagus and stomach so acid is less likely to back up. If you h...
- What exactly is metoclopramide supposed to do for me?
- This medication is meant to be short-term. For acid reflux, treatment is generally 4 to 12 weeks. For diabetic gastroparesis, it's usually 2 to 8 weeks. Using it longer than recomm...
- The most common ones — restlessness, drowsiness, and fatigue — affect roughly 1 in 10 people and are usually manageable. The ones that need urgent attention are any unusual or repe...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Metoclopramide Hydrochloride — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII Z0H242BBR1
Aspartame is an artificial sweetener made from amino acids. It's added to medicines to improve taste, making bitter or unpleasant-tasting drugs easier to take.
-
UNII REK4960K2U
Butylated hydroxyanisole is a synthetic preservative that prevents oils and fats in medicines from spoiling or becoming rancid. It keeps the medicine stable and extends its shelf life.
-
UNII 1P9D0Z171K
BHT is a synthetic antioxidant that prevents fats and oils in medicines from breaking down and becoming rancid. It helps keep the product stable and effective during storage.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII 905HNO1SIH
A synthetic polymer made from methacrylate compounds that forms a film coating on tablets or capsules. It helps control how quickly the medicine dissolves and releases its active ingredient in the digestive system.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII E4GA8884NN
Phosphoric acid is a weak mineral acid used in medicines as a buffer and pH adjuster. It helps stabilize the product and control its acidity level.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $7.43 | $74.28 / 10 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| METOCLOPRAMIDE hydrochloride 5 mgthis 43386-0581-31 | Lupin | 10 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 43386-0581-31 You're viewing this | 1 BLISTER PACK in 1 CARTON (43386-581-31) / 10 TABLET, ORALLY DISINTEGRATING in 1 BLISTER PACK | 2015-04-06 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING TARDIVE DYSKINESIA Metoclopramide Orally Disintegrating Tablets can cause tardive dyskinesia (TD), a serious movement disorder that is often irreversible. There is no known treatment for TD. The risk of developing TD increases with duration of treatment and total cumulative dosage [see Warnings and Precautions (5.1)].
Discontinue Metoclopramide Orally Disintegrating Tablets in patients who develop signs or symptoms of TD. In some patients, symptoms may lessen or resolve after Metoclopramide Orally Disintegrating Tablets is stopped [see Warnings and Precautions (5.1)]. Avoid treatment with Metoclopramide Orally Disintegrating Tablets for longer than 12 weeks because of the increased risk of developing TD with longer-term use [see Warnings and Precautions (5.1), Dosage and Administration (2.2, 2.3)].
WARNING: TARDIVE DYSKINESIA Metoclopramide Orally Disintegrating Tablets can cause tardive dyskinesia (TD), a serious movement disorder that is often irreversible. There is no known treatment for TD. The risk of developing TD increases with duration of treatment and total cumulative dosage.
( 5.1 ) Discontinue Metoclopramide Orally Disintegrating Tablets in patients who develop signs or symptoms of TD. ( 5.1 ) Avoid treatment with Metoclopramide Orally Disintegrating Tablets for longer than 12 weeks because of the risk of developing TD with longer-term use. ( 5.1 , 2.1 , 2.2 , 2.3 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Metoclopramide Orally Disintegrating Tablets is indicated in adults for the: Treatment for 4 to 12 weeks of symptomatic, documented gastroesophageal reflux disease (GERD) who fail to respond to conventional therapy. Relief of symptoms associated with acute and recurrent diabetic gastroparesis (gastric stasis). Limitations of Use : Metoclopramide Orally Disintegrating Tablets is not recommended for use in pediatric patients due to the risk of developing tardive dyskinesia (TD) and other extrapyramidal symptoms and the risk of methemoglobinemia in neonates [see Use in Specific Populations ( 8.4 )] Metoclopramide Orally Disintegrating Tablets is a dopamine-2 (D2) antagonist indicated in adults for: Treatment of symptomatic, documented gastroesophageal reflux disease (GERD) in adults with who fail to respond to conventional therapy.
Relief of symptoms associated with acute and recurrent diabetic gastroparesis (gastric stasis). Limitations of Use: Metoclopramide Orally Disintegrating Tablets is not recommended for use in pediatric patients due to the risk of developing tardive dyskinesia (TD) and other extrapyramidal symptoms and the risk of methemoglobinemia in neonates. (1, 8.4 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION GERD The recommended dosage is 10 mg to 15 mg up to four times daily at least 30 minutes before eating and at bedtime for 4 to 12 weeks. ( 2.2 ) Diabetic Gastroparesis (Gastric Stasis) The recommended dosage is 10 mg dose four times daily at least 30 minutes before eating and at bedtime for 2 to 8 weeks. ( 2.3 ) Dosage Adjustment in Specific Populations See Full Prescribing Information for recommended dosage reductions for elderly patients, patients with moderate or severe hepatic or renal impairment, and cytochrome P450 2D6 (CYP2D6) poor metabolizers.
( 2.2 , 2.3 )
2.1Important Administration Instructions Avoid treatment with Metoclopramide Orally Disintegrating Tablets for longer than 12 weeks because of the increased risk of developing TD with longer-term use [see Dosage and Administration ( 2.2 , 2.3), Warnings and Precautions ( 5.1 )]. Take on an empty stomach at least 30 minutes before eating [see Clinical Pharmacology ( 12.3 )]. Do not repeat dose if inadvertently taken with food.
Remove each dose from the packaging just prior to taking. Handle the tablet with dry hands and place on the tongue. If the tablet should break or crumble while handling, discard and remove a new tablet.
Place the tablet on the tongue and allow it to disintegrate (takes approximately one minute) and swallow the granules without water [see Clinical Pharmacology ( 12.3 )].
2.2Dosage for GERD Metoclopramide Orally Disintegrating Tablets may be administered continuously or intermittently in patients with symptomatic GERD who fail to respond to conventional therapy: Continuous Dosing The recommended adult dosage of Metoclopramide Orally Disintegrating Tablets is 10 to 15 mg four times daily for 4 to 12 weeks. The treatment duration is determined by endoscopic response. Administer the dosage thirty minutes before each meal and at bedtime.
The maximum recommended daily dosage is 60 mg. Table 1 displays the recommended daily dosage and maximum daily dosage for adults and dosage adjustments for patients with moderate or severe hepatic impairment (Child-Pugh B or C), in patients with creatinine clearance less than 60 mL/minute, in cytochrome P450 2D6 (CYP2D6) poor metabolizers, and with concomitant use with strong CYP2D6 inhibitors. Intermittent Dosing If symptoms only occur intermittently or at specific times of the day, administer Metoclopramide Orally Disintegrating Tablets in single dose up to 20 mg prior to the provoking situation.
Consider dosage reductions for the populations and situations in Table 1. Table 1 Recommended Metoclopramide Orally Disintegrating Tablets Dosage in Patients with Gastroesophageal Reflux Recommended Dosage Maximum Recommended Daily Dosage Adult patients 10 to 15 mg four times daily (thirty minutes before each meal and at bedtime) 60 mg Mild hepatic impairment (Child-Pugh A) Elderly patients1 [see Use in Specific Populations ( 8.5 )] 5 mg four times daily (thirty minutes before each meal and at bedtime) Moderate or severe hepatic impairment (Child-Pugh B or C) [see Use in Specific Populations ( 8.7 )] 5 mg four times daily (thirty minutes before each meal and at bedtime), or 10 mg taken three times daily 30 mg CYP2D6 poor metabolizers [see Use in Specific Populations ( 8.9 )] Concomitant use with strong CYP2D6 inhibitors (e.g., quinidine, bupropion, fluoxetine, and paroxetine) [see Drug Interactions ( 7.1 )] Moderate or severe renal impairment (creatinine clearance less than or equal to 60 mL/minute) [see Use in Specific Populations ( 8.6 )] Patients with End-Stage Renal Disease (ESRD) including those treated with hemodialysis and continuous ambulatory peritoneal dialysis [see Use in Specific Populations ( 8.6 )] 5 mg four times daily (thirty minutes before each meal and at bedtime) or 10 mg twice daily 20 mg 1 Elderly patients may be more sensitive to the therapeutic or adverse effects of Metoclopramide Orally Disintegrating Tablets; therefore, consider a lower starting dosage of 5 mg four ti…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 5 mg Tablets: Metoclopramide Orally Disintegrating Tablets are round, white to off- white, flat faced beveled edge tablet, debossed with 'N' on one side and "581" on the other side. 10 mg Tablets: Metoclopramide Orally Disintegrating Tablets are round, white to off- white, flat faced beveled edge tablet, debossed with 'N' on one side and "580" on the other side. Orally Disintegrating Tablets: 5 mg and 10 mg metoclopramide.
⛔ Contraindications ▾
4 CONTRAINDICATIONS Metoclopramide Orally Disintegrating Tablets is contraindicated: In patients with a history of tardive dyskinesia (TD) or a dystonic reaction to metoclopramide [see Warnings and Precautions (5.1, 5.2)]. When stimulation of gastrointestinal motility might be dangerous (e.g., in the presence of gastrointestinal hemorrhage, mechanical obstruction, or perforation). In patients with pheochromocytoma or other catecholamine-releasing paragangliomas.
Reglan may cause a hypertensive/pheochromocytoma crisis, probably due to release of catecholamines from the tumor [ see Warnings and Precautions (5.5 )]. In patients with epilepsy. Reglan may increase the frequency and severity of seizures [see Adverse Reactions (6) ].
In patients with hypersensitivity to metoclopramide. Reactions have included laryngeal and glossal angioedema and bronchospasm [see Adverse Reactions (6) ]. History of TD or dystonic reaction to metoclopramide ( 4 ) When stimulation of gastrointestinal motility might be dangerous ( 4 ) Pheochromocytoma, catecholamine-releasing paragangliomas ( 4 ) Epilepsy ( 4 ) Hypersensitivity to metoclopramide ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Tardive Dyskinesia (TD), Other Extrapyramidal Symptoms (EPS), and Neuroleptic Malignant Syndrome (NMS): Avoid concomitant use of other drugs known to cause TD/EPS/NMS and avoid use in patients with Parkinson's disease. If symptoms occur, discontinue Metoclopramide Orally Disintegrating Tablets and seek immediate medical attention. ( 5.1 , 5.2 , 5.3 , 7.1 , 7.2 ) Depression and suicidal ideation/suicide : Avoid use. ( 5.4 )
5.1Tardive Dyskinesia Metoclopramide can cause tardive dyskinesia (TD), a potentially irreversible and disfiguring disorder characterized by involuntary movements of the face or tongue, and sometimes of the trunk and/or extremities. Movements may be choreoathetoic in appearance. The risk of developing TD and the likelihood that TD will become irreversible increases with the duration of treatment and total cumulative dosage.
An analysis of utilization patterns showed that about 20% of patients who used metoclopramide took it for longer than 12 weeks. Treatment with metoclopramide for longer than the recommended 12 weeks should be avoided in all but rare cases where therapeutic benefit is thought to outweigh the risk of developing TD. Additionally, the risk of developing TD is increased among the elderly, especially elderly women [see Use in Specific Populations (8.5 )] , and in patients with diabetes mellitus.
Due to the risk of developing TD, avoid treatment with Metoclopramide Orally Disintegrating Tablets for longer than 12 weeks and reduce the dosage in elderly patients [see Dosage and Administration ( 2.2 , 2.3 )]. Discontinue Metoclopramide Orally Disintegrating Tablets immediately in patients who develop signs and symptoms of TD. There is no known effective treatment for established cases of TD, although in some patients TD may remit, partially or completely, within several weeks to months after Metoclopramide Orally Disintegrating Tablets is withdrawn.
Metoclopramide Orally Disintegrating Tablets itself may suppress, or partially suppress, the signs of TD, thereby masking the underlying disease process. The effect of this symptomatic suppression upon the long-term course of TD is unknown. Metoclopramide Orally Disintegrating Tablets is contraindicated in patients with a history of TD [see Contraindications (4) ].
Avoid Metoclopramide Orally Disintegrating Tablets in patients receiving other drugs that can cause TD (e.g., antipsychotics).
5.2Other Extrapyramidal Symptoms In addition to TD, metoclopramide may cause other extrapyramidal symptoms (EPS), parkinsonian symptoms, and motor restlessness. Advise patients to seek immediate medical attention if such symptoms occur and to discontinue Metoclopramide Orally Disintegrating Tablets. Extrapyramidal symptoms (EPS), such as acute dystonic reactions, occurred in patients treated with metoclopramide dosages of 30 to 40 mg daily.
Such reactions occurred more frequently in adults less than 30 years of age and at higher than recommended dosages. EPS occurred more frequently in pediatric patients compared to adults (Metoclopramide Orally Disintegrating Tablets is not approved for use in pediatric patients). Symptoms can occur in the first 24 to 48 hours after starting metoclopramide.
Symptoms included involuntary movements of limbs and facial grimacing, torticollis, oculogyric crisis, rhythmic protrusion of tongue, bulbar type of speech, trismus, or dystonic reactions resembling tetanus. Rarely, dystonic reactions were present as stridor and dyspnea, possibly due to laryngospasm. Diphenhydramine hydrochloride or benztropine mesylate may be used to treat these adverse reactions.
Avoid Metoclopramide Orally Disintegrating Tablets in patients receiving other drugs that can cause EPS (e.g., antipsychotics). Parkinsonism symptoms (bradykinesia, tremor, cogwheel rigidity, mask-like facies) have occurred after starting metoclopramide, more commonly within the first 6 months, but also after longer periods. Symptoms generally have subsided…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are described, or described in greater detail, in other sections of the labeling: Tardive dyskinesia [see Boxed Warning and Warnings and Precautions ( 5.1 )] Other extrapyramidal effects [see Warnings and Precautions ( 5.2 )] Neuroleptic malignant syndrome [see Warnings and Precautions ( 5.3 )] Depression [see Warnings and Precautions ( 5.4 )] Hypertension [see Warnings and Precautions ( 5.5 )] Fluid retention [see Warnings and Precautions ( 5.6 )] Hyperprolactinemia [see Warnings and Precautions ( 5.7 )] Effects on the ability to drive and operate machinery [see Warnings and Precautions (5.8) ] Metoclopramide The following adverse reactions have been identified from clinical studies or postmarketing reports of metoclopramide.
Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. The most common adverse reactions (in approximately 10% of patients receiving 10 mg of metoclopramide four times daily) were restlessness, drowsiness, fatigue, and lassitude. In general, the incidence of adverse reactions correlated with the dosage and duration of metoclopramide administration.
Adverse reactions, especially those involving the nervous system, occurred after stopping metoclopramide including dizziness, nervousness, and headaches. Central Nervous System Disorders Tardive dyskinesia, acute dystonic reactions, drug-induced parkinsonism, akathisia, and other extrapyramidal symptoms Convulsive seizures Hallucinations Restlessness, drowsiness, fatigue, and lassitude occurred in approximately 10% of patients who received 10 mg four times daily. Insomnia, headache, confusion, dizziness, or depression with suicidal ideation occurred less frequently Neuroleptic malignant syndrome, serotonin syndrome (in combination with serotonergic agents) Endocrine Disorders : Fluid retention secondary to transient elevation of aldosterone.
Galactorrhea, amenorrhea, gynecomastia, impotence secondary to hyperprolactinemia Cardiovascular Disorders : Acute congestive heart failure, possible atrioventricular block, hypotension, hypertension, supraventricular tachycardia, bradycardia, fluid retention Gastrointestinal Disorders : Nausea, bowel disturbances (primarily diarrhea) Hepatic Disorders : Hepatotoxicity, characterized by, e.g., jaundice and altered liver function tests, when metoclopramide was administered with other drugs with known hepatotoxic potential Renal and Urinary Disorders : Urinary frequency, urinary incontinence Hematologic Disorders : Agranulocytosis, neutropenia, leukopenia, methemoglobinemia, sulfhemoglobinemia Hypersensitivity Reactions : Bronchospasm (especially in patients with a history of asthma), urticaria; rash; angioedema, including glossal or laryngeal edema Eye Disorders : Visual disturbances Metabolism Disorders : Porphyria Most common adverse reactions (> 10%) are restlessness, drowsiness, fatigue, and lassitude.
To report SUSPECTED ADVERSE REACTIONS, contact Lupin Pharmaceuticals, Inc. at 1-866-403-7592 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Antipsychotics: Potential for additive effects, including TD, EPS, and NMS ; avoid concomitant use. ( 7.1 ) CNS depressants : Increased risk of CNS depression; avoid concomitant use and monitor for adverse reactions. ( 7.1 ) Strong CYP2D6 inhibitors (e.g., quinidine, bupropion, fluoxetine, and paroxetine) : See Full Prescribing Information for recommended dosage reductions.
( 2.2 , 2.3 , 7.1 ) MAO inhibitors : Increased risk of hypertension; avoid concomitant use. ( 5.5 , 7.1 ) Additional drug interactions : See Full Prescribing Information. ( 7.1 , 7.2 )
7.1Effects of Other Drugs on Metoclopramide Table 3 displays the effects of other drugs on metoclopramide. Antipsychotics Clinical Impact Potential for additive effects, including increased frequency and severity of tardive dyskinesia (TD), other extrapyramidal symptoms (EPS), and neuroleptic malignant syndrome (NMS). Intervention Avoid concomitant use [see Warnings and Precautions ( 5.1 , 5.2 , 5.3 )].
Strong CYP2D6 Inhibitors, not Included in Antipsychotic Category Above Clinical Impact Increased plasma concentrations of metoclopramide; risk of exacerbation of extrapyramidal symptoms [see Clinical Pharmacology ( 12.3 )]. Intervention Reduce the Metoclopramide Orally Disintegrating Tablets dosage [ see Dosage and Administration ( 2.2 , 2.3 )] . Examples quinidine, bupropion, fluoxetine, and paroxetine.
Monoamine Oxidase Inhibitors Clinical Impact Increased risk of hypertension [see Warnings and Precautions (5.5) ]. Intervention Avoid concomitant use. Central Nervous System (CNS) Depressants Clinical Impact Increased risk of CNS depression [see Warnings and Precautions (5.8) ].
Intervention Avoid Metoclopramide Orally Disintegrating Tablets or the interacting drug, depending on the importance of the drug to the patient. Examples alcohol, sedatives, hypnotics, opiates and anxiolytics. Drugs that Impair Gastrointestinal Motility Clinical Impact Decreased systemic absorption of metoclopramide.
Intervention Monitor for reduced therapeutic effect. Examples antiperistaltic antidiarrheal drugs, anticholinergic drugs, and opiates. Dopaminergic Agonists and Other Drugs that Increase Dopamine Concentrations Clinical Impact Decreased therapeutic effect of metoclopramide, a D2 antagonist, due to opposing effects on dopamine.
Intervention Monitor for reduced therapeutic effect. Examples Apomorphine, bromocriptine, cabergoline, levodopa, pramipexole, ropinirole, and rotigotine.
7.2Effects of Metoclopramide on Other Drugs Table 4 displays the effects of metoclopramide on other drugs. Dopaminergic Agonists and Other Drugs that Increase Dopamine Concentrations: Clinical Impact Opposing effects of metoclopramide and the interacting drug on dopamine. Potential exacerbation of symptoms (e.g., parkinsonian symptoms).
Intervention Avoid concomitant use [see Warnings and Precautions (5.2) ] . Examples Apomorphine, bromocriptine, cabergoline, levodopa, pramipexole, ropinirole, rotigotine. Succinylcholine, Mivacurium: Clinical Impact Metoclopramide inhibits plasma cholinesterase leading to enhanced neuromuscular blockade.
Intervention Monitor for signs and symptoms of prolonged neuromuscular blockade. Drugs with Absorption Altered due to Increased Gastrointestinal Motility: Clinical Impact The effect of metoclopramide on other drugs is variable. Increased gastrointestinal (GI) motility by metoclopramide may impact absorption of other drugs leading to decreased or increased drug exposure.
Intervention Drugs with Decreased Absorption (e.g., digoxin, atovaquone, posaconazole oral suspension*, fosfomycin) : Monitor for reduced therapeutic effect of the interacting drug. For digoxin monitor therapeutic drug concentrations and increase the digoxin dose as needed (see prescribing information for digoxin). Drugs with Increased Absorption (e.g., sirolimus, tacrolimus, cyclosporine) : Monitor therapeutic drug concentrations and adjust the dose as needed.
See prescribing information for th…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Published studies, including retrospective cohort studies, national registry studies, and meta-analyses, do not report an increased risk of adverse pregnancy-related outcomes with use of metoclopramide during pregnancy. There are potential risks to the neonate following exposure in utero to metoclopramide during delivery (see Clinical Considerations) . In animal reproduction studies, no adverse developmental effects were observed with oral administration of metoclopramide to pregnant rats and rabbits at exposures about 6 and 12 times the maximum recommended human dose (MRHD) (see Data) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defects, loss or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in the clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Fetal/Neonatal Adverse Reactions Metoclopramide crosses the placental barrier and may cause extrapyramidal signs and methemoglobinemia in neonates with maternal administration during delivery. Monitor neonates for extrapyramidal signs [see Warnings and Precautions ( 5.1 , 5.2 ), Use in Specific Populations ( 8.4 )] . Data Animal Data Reproduction studies have been performed following administration of oral metoclopramide during organogenesis in pregnant rats at about 6 times the MRHD calculated on body surface area and in pregnant rabbits at about 12 times the MRHD calculated on body surface area.
No evidence of adverse developmental effects due to metoclopramide were observed.
8.6Lactation Risk Summary Limited published data report the presence of metoclopramide in human milk in variable amounts. Breastfed infants exposed to metoclopramide have experienced gastrointestinal adverse reactions, including intestinal discomfort and increased intestinal gas formation (see Data) . Metoclopramide elevates prolactin levels [see Warnings and Precautions ( 5.7 )] ; however, the published data are not adequate to support drug effects on milk production.
The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for Metoclopramide Orally Disintegrating Tablets and any potential adverse effects on the breastfed child from Metoclopramide Orally Disintegrating Tablets or from the underlying maternal condition. Clinical Considerations Monitor breastfeeding neonates because metoclopramide may cause extrapyramidal signs (dystonias) and methemoglobinemia [see Warnings and Precautions ( 5.1 , 5.2 ), Use in Specific Populations ( 8.4 )] .
Data In published clinical studies, the estimated amount of metoclopramide received by the breastfed infant was less than 10% of the maternal weight-adjusted dose. In one study, the estimated daily amount of metoclopramide received by infants from breast milk ranged from 6 to 24 mcg/kg/day in early puerperium (3 to 9 days postpartum) and from 1 to 13 mcg/kg/day at 8 to 12 weeks postpartum.
8.4Pediatric Use Metoclopramide Orally Disintegrating Tablets is not recommended for use in pediatric patients due to the risk of tardive dyskinesia (TD) and other extrapyramidal symptoms as well as the risk of methemoglobinemia in neonates. The safety and effectiveness of Metoclopramide Orally Disintegrating Tablets in pediatric patients have not been established. Dystonias and other extrapyramidal reactions associated with metoclopramide are more common in the pediatric patients than in adults [see Warnings and Precautions ( 5.1 , 5.2 )] .
In addition, neonates have reduced levels of NADH-cytochrome b5 reductase, making them more susceptible to methemoglobinemia, a possible side effect of metoclopramide use in neonates [see Use in Specific Populations ( 8.8 )] .
8.5 Geriatric Use Metoclopramide is known to be substantially excreted b…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Published studies, including retrospective cohort studies, national registry studies, and meta-analyses, do not report an increased risk of adverse pregnancy-related outcomes with use of metoclopramide during pregnancy. There are potential risks to the neonate following exposure in utero to metoclopramide during delivery (see Clinical Considerations) . In animal reproduction studies, no adverse developmental effects were observed with oral administration of metoclopramide to pregnant rats and rabbits at exposures about 6 and 12 times the maximum recommended human dose (MRHD) (see Data) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defects, loss or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in the clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Fetal/Neonatal Adverse Reactions Metoclopramide crosses the placental barrier and may cause extrapyramidal signs and methemoglobinemia in neonates with maternal administration during delivery. Monitor neonates for extrapyramidal signs [see Warnings and Precautions ( 5.1 , 5.2 ), Use in Specific Populations ( 8.4 )] . Data Animal Data Reproduction studies have been performed following administration of oral metoclopramide during organogenesis in pregnant rats at about 6 times the MRHD calculated on body surface area and in pregnant rabbits at about 12 times the MRHD calculated on body surface area.
No evidence of adverse developmental effects due to metoclopramide were observed.
🧒 Pediatric Use ▾
8.4Pediatric Use Metoclopramide Orally Disintegrating Tablets is not recommended for use in pediatric patients due to the risk of tardive dyskinesia (TD) and other extrapyramidal symptoms as well as the risk of methemoglobinemia in neonates. The safety and effectiveness of Metoclopramide Orally Disintegrating Tablets in pediatric patients have not been established. Dystonias and other extrapyramidal reactions associated with metoclopramide are more common in the pediatric patients than in adults [see Warnings and Precautions ( 5.1 , 5.2 )] .
In addition, neonates have reduced levels of NADH-cytochrome b5 reductase, making them more susceptible to methemoglobinemia, a possible side effect of metoclopramide use in neonates [see Use in Specific Populations ( 8.8 )] .
🧓 Geriatric Use ▾
8.5Geriatric Use Metoclopramide is known to be substantially excreted by the kidney, and the risk of adverse reactions, including tardive dyskinesia (TD), may be greater in patients with impaired renal function [see Use in Specific Populations ( 8.6 ), Clinical Pharmacology (12.3)] . Elderly patients are more likely to have decreased renal function and may be more sensitive to the therapeutic or adverse effects of metoclopramide; therefore, consider a reduced dosage of METOZOLOV ODT in elderly patients [see Dosage and Administration ( 2.2 , 2.3 ), Warnings and Precautions (5.1) ].
🆘 Overdosage ▾
10 OVERDOSAGE Manifestations of metoclopramide overdosage included drowsiness, disorientation, extrapyramidal reactions, other adverse reactions associated with metoclopramide use (including, e.g., methemoglobinemia), and sometimes death. Neuroleptic malignant syndrome (NMS) has been reported in association with metoclopramide overdose and concomitant treatment with another drug associated with NMS [see Warnings and Precautions ( 5.1 , 5.2 , 5.3 )]. There are no specific antidotes for Metoclopramide Orally Disintegrating Tablets overdosage.
If over-exposure occurs, call your Poison Control Center at 1-800-222-1222 for current information on the management of poisoning or overdosage. Methemoglobinemia can be reversed by the intravenous administration of methylene blue. However, methylene blue may cause hemolytic anemia in patients with G6PD deficiency, which may be fatal.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Metoclopramide stimulates motility of the upper gastrointestinal tract without stimulating gastric, biliary, or pancreatic secretions. The exact mechanism of action of metoclopramide in the treatment of gastroesophageal reflux and acute and recurrent diabetic gastroparesis has not been fully established. It seems to sensitize tissues to the action of acetylcholine.
The effect of metoclopramide on motility is not dependent on intact vagal innervation, but it can be abolished by anticholinergic drugs. Metoclopramide increases the tone and amplitude of gastric (especially antral) contractions, relaxes the pyloric sphincter and the duodenal bulb, and increases peristalsis of the duodenum and jejunum resulting in accelerated gastric emptying and intestinal transit. It increases the resting tone of the lower esophageal sphincter.
It has little, if any, effect on the motility of the colon or gallbladder.
12.2Pharmacodynamics Gastroesophageal Reflux In patients with gastroesophageal reflux and low lower esophageal sphincter pressure (LESP), single oral doses of Reglan produced dose-related increases in LESP. Effects began at about 5 mg and increased through 20 mg. The increase in LESP from a 5 mg dose lasted about 45 minutes and that of 20 mg lasted between 2 and 3 hours. Increased rate of stomach emptying was observed with single oral doses of 10 mg.
12.3Pharmacokinetics Unless otherwise specified the PK of metoclopramide described below was obtained using other oral formulations of metoclopramide. Absorption Relative to an intravenous dose of 20 mg, the absolute oral bioavailability of metoclopramide was 80% ± 15.5% as demonstrated in a crossover study of 18 subjects. Following Metoclopramide Orally Disintegrating Tablets tablet administration, the time reported between placing the tablet on the tongue and it completely disintegrated into fine particles was approximately one minute (with a range of 10 seconds to 14 minutes) in two clinical trials (N = 96) with a mean ± SD being 77 ± 111 seconds and a median of 54 seconds [see Dosage and Administration ( 2.1 )] .
Peak plasma concentrations occurred at about 1 to 2 hours after a single oral dose. Similar time to peak is observed after individual doses at steady state. In a single dose study of 12 subjects showed that the area under the drug concentration-time curve increases linearly with doses from 20 to 100 mg of metoclopramide (5 times the maximum recommended single dose of Metoclopramide Orally Disintegrating Tablets).
Cmax increased linearly with dose; Tmax remained the same; whole body clearance was unchanged; and the elimination rate remained the same. Linear kinetic processes adequately describe the absorption and elimination of metoclopramide. The pharmacokinetic characteristics following single oral administration of 10 mg Metoclopramide Hydrochloride Orally Disintegrating Tablets under fasting conditions are shown in Table 5.
Table 5 Mean (± SD) Pharmacokinetic Parameters in Healthy Subjects Following a Single Oral Dose of 10 mg Metoclopramide Orally Disintegrating Tablets Under Fasting Conditions Treatment C max (ng/mL) T max (h)* AUC 0-inf (ng*h/mL) Single 10 mg Metoclopramide Orally Disintegrating Tablets (N=41) 28±7.4 2.0 (0.7 to 4.0) 268±72.6 *presented as median (range). Effect of Food When Metoclopramide Orally Disintegrating Tablets was taken immediately after a high-fat meal (approximately 900 total calories based on the composition being 150 protein calories, 250 carbohydrate calories and 500 fat calories), the Cmax was 17% lower than when taken after an overnight fast.
The Tmax increased from about 1.8 hours under fasted conditions to 3 hours when taken immediately after a high-fat meal. The extent of metoclopramide absorbed (area under the curve) was comparable whether Metoclopramide Orally Disintegrating Tablets was administered with or without food. The clinical relevance of a lower Cmax with a high-fat meal…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Metoclopramide stimulates motility of the upper gastrointestinal tract without stimulating gastric, biliary, or pancreatic secretions. The exact mechanism of action of metoclopramide in the treatment of gastroesophageal reflux and acute and recurrent diabetic gastroparesis has not been fully established. It seems to sensitize tissues to the action of acetylcholine.
The effect of metoclopramide on motility is not dependent on intact vagal innervation, but it can be abolished by anticholinergic drugs. Metoclopramide increases the tone and amplitude of gastric (especially antral) contractions, relaxes the pyloric sphincter and the duodenal bulb, and increases peristalsis of the duodenum and jejunum resulting in accelerated gastric emptying and intestinal transit. It increases the resting tone of the lower esophageal sphincter.
It has little, if any, effect on the motility of the colon or gallbladder.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Metoclopramide Orally Disintegrating Tablets 5 mg strength are round, white to off- white, flat faced beveled edge tablet debossed with 'N' on one side and "581" on the other side; it is comprised of 5 mg metoclopramide (as 5.91 mg of metoclopramide hydrochloride). These are packaged in blister cards as follows: Box of 10 (1x10) NDC 43386-581-31 Metoclopramide Orally Disintegrating Tablets 10 mg are round, white to off-white, flat faced beveled edge tablet debossed with 'N' on one side and "580" on the other side; it is comprised of 10 mg metoclopramide (as 11.82 mg of metoclopramide hydrochloride).
These are packaged in blister cards as follows: Box of 10 (1x10) NDC 43386-580-31 Tablets should be stored at controlled room temperature, between 20°C and 25°C (68°F and 77°F).
📋 Description ▾
11 DESCRIPTION Metoclopramide hydrochloride, the active ingredient of Metoclopramide Orally Disintegrating Tablets, is a dopamine-2 (D2) antagonist. Metoclopramide hydrochloride (metoclopramide monohydrochloride monohydrate), is a white or almost white crystalline powder, freely soluble in water. Chemically, it is 4-amino-5-chloro-N-[2-(diethylamino)ethyl]-2-methoxy benzamide monohydrochloride monohydrate.
The molecular formula is C14H22ClN3O2•HCl•H2O. Its molecular weight is 354.3. The structural formula is: Metoclopramide Orally Disintegrating Tablets is an orally disintegrating tablet for oral administration and is available in 5 mg and 10 mg strengths.
Each Metoclopramide Orally Disintegrating Tablets 5 mg tablet contains 5 mg metoclopramide (equivalent to 5.91 mg of metoclopramide hydrochloride USP). Each Metoclopramide Orally Disintegrating Tablets 10 mg tablet contains 10 mg metoclopramide (equivalent to 11.82 mg metoclopramide hydrochloride USP). Metoclopramide Orally Disintegrating Tablets includes the following inactive ingredients: phosphoric acid, mannitol and starch, microcrystalline cellulose, colloidal silicon dioxide, amino methacrylate copolymer, butylated hydroxyanisole, butylated hydroxytoluene, crospovidone, aspartame, N-C mint flavor, magnesium stearate.
Metoclopramide
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Adverse Reactions Inform patients or their caregivers that Metoclopramide Orally Disintegrating Tablets can cause serious adverse reactions. Instruct patients to discontinue Metoclopramide Orally Disintegrating Tablets and contact a healthcare provider immediately if the following serious reactions occur: Tardive dyskinesia and other extrapyramidal reactions [see Warnings and Precautions ( 5.1 , 5.2 )] Neuroleptic malignant syndrome [see Warnings and Precautions ( 5.3 )] Depression and/or possible suicidal ideation [see Warnings and Precautions ( 5.4 )] Inform patients or their caregivers that concomitant treatment with numerous other medications can precipitate or worsen serious adverse reactions such as tardive dyskinesia or other extrapyramidal reactions, neuroleptic malignant syndrome, and CNS depression [see Drug Interactions ( 7.1 , 7.2 )] .
Explain that the prescriber of any other medication must be made aware that the patient is taking Metoclopramide Orally Disintegrating Tablets. Inform patients or their caregivers that Metoclopramide Orally Disintegrating Tablets can cause drowsiness or dizziness, or otherwise impair the mental and/or physical abilities required for the performance of hazardous tasks such as operating machinery or driving a motor vehicle [see Warnings and Precautions (5.8) ] . Administration Instruct patients to: Take on an empty stomach at least 30 minutes before eating.
Do not repeat dose if inadvertently taken with food. Remove each dose from the packaging just prior to taking. Handle the tablet with dry hands and place on the tongue.
If the tablet should break or crumble while handling, discard and remove a new tablet. Place the tablet on the tongue and allow it to disintegrate (takes approximately one minute) and swallow the granules without water [see Dosage and Administration (2.1) ]. Manufactured by: Novel Laboratories, Inc.
Somerset, NJ 08873 USA Manufactured for: Lupin Pharmaceuticals, Inc. Baltimore, MD 21202 PI5800000203 SAP code: 260278 Rev. 10/2019
💬 Medication Guide ▾
SPL MEDGUIDE Metoclopramide Orally Disintegrating Tablets (MET-oh-KLOE-pra-mide) Read this Medication Guide before you start taking Metoclopramide Orally Disintegrating Tablets and each time you get a refill. There may be new information. If you take another product that contains metoclopramide (such as REGLAN tablets, REGLAN ODT, REGLAN injection or metoclopramide oral solution), you should read the Medication Guide that comes with that product.
Some of the information may be different. This Medication Guide does not take the place of talking with your doctor about your medical condition or your treatment. What is the most important information I should know about Metoclopramide Orally Disintegrating Tablets?
Metoclopramide Orally Disintegrating Tablets can cause serious side effects, including: Tardive dyskinesia (abnormal muscle movements) . These movements happen mostly in the face muscles. You cannot control these movements.
They may not go away even after stopping Metoclopramide Orally Disintegrating Tablets. There is no treatment for tardive dyskinesia, but symptoms may lessen or go away over time after you stop taking Metoclopramide Orally Disintegrating Tablets. Your chances for getting tardive dyskinesia go up: the longer you take Metoclopramide Orally Disintegrating Tablets and the more Metoclopramide Orally Disintegrating Tablets you take.
You should not take Metoclopramide Orally Disintegrating Tablets for more than 12 weeks. if you are older, especially if you are an older woman. if you have diabetes. It is not possible for your doctor to know if you will get tardive dyskinesia if you take Metoclopramide Orally Disintegrating Tablets. Call your doctor right away if you have movements you cannot stop or control, such as: lip smacking, chewing, or puckering of your lips frowning or scowling sticking out your tongue blinking and moving your eyes shaking of your arms and legs See the section "What are the possible side effects of Metoclopramide Orally Disintegrating Tablets?" for more information about side effects.
What is Metoclopramide Orally Disintegrating Tablets? Metoclopramide Orally Disintegrating Tablets is a prescription medicine used in adults: for 4 to 12 weeks to relieve heartburn symptoms of gastroesophageal reflux disease (GERD) when certain other treatments do not work. to relieve the symptoms of slow stomach emptying in people with diabetes. Metoclopramide Orally Disintegrating Tablets is not recommended for use in children.
Do not take Metoclopramide Orally Disintegrating Tablets if you: have a history of tardive dyskinesia or have a problem controlling your muscles and movements after taking Metoclopramide Orally Disintegrating Tablets or a medicine that works like Metoclopramide Orally Disintegrating Tablets. have stomach or intestine problems that could get worse with Metoclopramide Orally Disintegrating Tablets, such as bleeding, blockage or a tear in your stomach or bowel wall. have a type of tumor that can cause high blood pressure such as pheochromocytoma. have epilepsy (seizures).
Metoclopramide Orally Disintegrating Tablets can increase your chance for seizures and make them worse. are allergic to metoclopramide or any of the ingredients in Metoclopramide Orally Disintegrating Tablets. Metoclopramide Orally Disintegrating Tablets can cause serious allergic reactions. Stop taking Metoclopramide Orally Disintegrating Tablets right away and get emergency help if you have any of these symptoms: swelling of your tongue, throat, lips, eyes or face. trouble swallowing or breathing. skin rash, hives, sores in your mouth, or skin blisters.
See the end of this Medication Guide for a list of ingredients in Metoclopramide Orally Disintegrating Tablets. Before you take Metoclopramide Orally Disintegrating Tablets, tell your doctor about all of your medical conditions, including if you: have kidney or liver disease. had problems controlling your muscle movements after taking any medicine. have depression…