
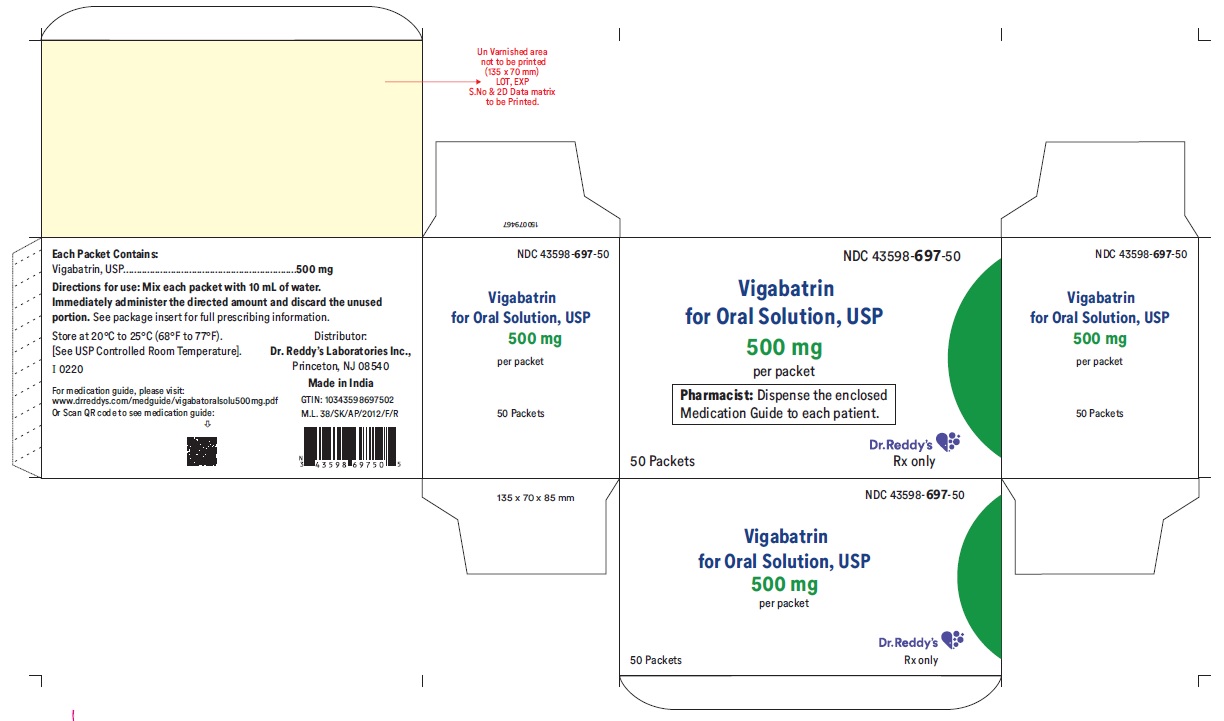
Vigabatrin 50 mg/mL Powder, For Solution
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Anti-epileptic Agent class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Vigabatrin is specifically for seizures that haven't responded well to other treatments. It's not a first choice — it's reserved for situations where other options haven't worked,...
- Why is my doctor prescribing this instead of a more common seizure medication?
- Yes, this is a real and serious risk that's important to understand. Vigabatrin can permanently narrow your field of vision — sometimes described as tunnel vision — and in some peo...
- What's this I heard about vision loss? Should I be worried?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Vigabatrin — tap one for details:
Vigabatrin may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
1 inactive ingredient listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $55.77 | $27,883.50 / 500 ml |
| Medicare drug plans payPart D · Q2 2026 | $55.24 | $27,619.30 / 500 ml |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Vigadrone 50 mg/mL 00245-0556-50 | Upsher-Smith | 50 packets | — | AA | FDA listed | — |
| vigabatrin for oral solution 50 mg/mL 31722-0009-50 | Camber | 50 packets | — | AA | FDA listed | — |
| Vigabatrin 50 mg/mLthis 43598-0697-50 | Dr. | 50 packets | — | AA | FDA listed | — |
| Vigabatrin 50 mg/mL 49884-0358-03 | Par | 50 packets | — | AA | FDA listed | — |
| Vigabatrin 500 mg 59651-0366-50 | Aurobindo | 50 packets | — | AA | FDA listed | — |
| Vigabatrin 500 mg 60219-1425-05 | Amneal | 50 fors | — | AA | FDA listed | — |
| Sabril 50 mg/mL 67386-0211-65 | Lundbeck | 50 packets | — | AA | FDA listed | — |
| Vigabatrin 50 mg/mL 67877-0674-63 | Ascend | 50 packets | — | AA | FDA listed | — |
| Vigabatrin 500 mg/mL 69097-0964-53 | Cipla | 50 packets | — | AA | FDA listed | — |
| Vigabatrin 500 mg 69238-1425-05 | Amneal | 50 fors | — | AA | FDA listed | — |
| vigabatrin 500 mg/10mL 70710-1494-08 | Zydus | 50 packets | — | — | FDA listed | — |
| vigabatrin 500 mg/10mL 70771-1742-08 | Zydus | 50 packets | — | — | FDA listed | — |
| Vigabatrin 50 mg/mL 72205-0093-50 | Novadoz | 50 packets | — | AA | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 43598-0697-50 You're viewing this | 50 PACKET in 1 CARTON (43598-697-50) / 10 mL in 1 PACKET (43598-697-11) | 2018-11-21 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: PERMANENT VISION LOSS Vigabatrin can cause permanent bilateral concentric visual field constriction, including tunnel vision that can result in disability. In some cases, vigabatrin also can damage the central retina and may decrease visual acuity [see Warnings and Precautions ( 5.1 ) ] . The onset of vision loss from vigabatrin is unpredictable, and can occur within weeks of starting treatment or sooner, or at any time after starting treatment, even after months or years.
Symptoms of vision loss from vigabatrin are unlikely to be recognized by patients or caregivers before vision loss is severe. Vision loss of milder severity, while often unrecognized by the patient or caregiver, can still adversely affect function. The risk of vision loss increases with increasing dose and cumulative exposure, but there is no dose or exposure known to be free of risk of vision loss.
Vision assessment is recommended at baseline (no later than 4 weeks after starting vigabatrin), at least every 3 months during therapy, and about 3 to 6 months after the discontinuation of therapy. Once detected, vision loss due to vigabatrin is not reversible. It is expected that, even with frequent monitoring, some patients will develop severe vision loss.
Consider drug discontinuation, balancing benefit and risk, if vision loss is documented. Risk of new or worsening vision loss continues as long as vigabatrin is used. It is possible that vision loss can worsen despite discontinuation of vigabatrin for oral solution.
Because of the risk of vision loss, vigabatrin should be withdrawn from patients with refractory complex partial seizures who fail to show substantial clinical benefit within 3 months of initiation and within 2 to 4 weeks of initiation for patients with infantile spasms, or sooner if treatment failure becomes obvious. Patient response to and continued need for vigabatrin should be periodically reassessed. Vigabatrin should not be used in patients with, or at high risk of, other types of irreversible vision loss unless the benefits of treatment clearly outweigh the risks.
Vigabatrin should not be used with other drugs associated with serious adverse ophthalmic effects such as retinopathy or glaucoma unless the benefits clearly outweigh the risks. Use the lowest dosage and shortest exposure to vigabatrin consistent with clinical objectives [see Dosage and Administration ( 2.1 ) ] . Because of the risk of permanent vision loss, vigabatrin for oral solution is available only through a restricted program under a Risk Evaluation and Mitigation Strategy (REMS) called the Vigabatrin REMS Program [see Warnings and Precautions ( 5.2 ) ] .
Further information is available at www.vigabatrinREMS.com or 1-866-244-8175. WARNING: PERMANENT VISION LOSS See full prescribing information for complete boxed warning. • Vigabatrin can cause permanent bilateral concentric visual field constriction, including tunnel vision that can result in disability. In some cases, vigabatrin may also decrease visual acuity ( 5.1 ). • Risk increases with increasing dose and cumulative exposure, but there is no dose or exposure to vigabatrin known to be free of risk of vision loss ( 5.1 ). • Risk of new and worsening vision loss continues as long as vigabatrin is used, and possibly after discontinuing vigabatrin for oral solution ( 5.1 ). • Baseline and periodic vision assessment is recommended for patients on vigabatrin.
However, this assessment cannot always prevent vision damage ( 5.1 ). • Vigabatrin for oral solution is available only through a restricted program called the Vigabatrin REMS Program ( 5.2 ).
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Vigabatrin for oral solution is indicated for the treatment of: Refractory Complex Partial Seizures as adjunctive therapy in patients 2 years of age and older who have responded inadequately to several alternative treatments; vigabatrin for oral solution is not indicated as a first line agent ( 1.1 ) Infantile Spasms - monotherapy in infants 1 month to 2 years of age for whom the potential benefits outweigh the potential risk of vision loss ( 1.2 )
1.1Refractory Complex Partial Seizures (CPS) Vigabatrin for oral solution is indicated as adjunctive therapy for adults and pediatric patients 2 years of age and older with refractory complex partial seizures who have inadequately responded to several alternative treatments and for whom the potential benefits outweigh the risk of vision loss [ see Warnings and Precautions ( 5.1 ) ]. Vigabatrin for oral solution is not indicated as a first line agent for complex partial seizures.
1.2Infantile Spasms (IS) Vigabatrin for oral solution is indicated as monotherapy for pediatric patients with infantile spasms 1 month to 2 years of age for whom the potential benefits outweigh the potential risk of vision loss [ see Warnings and Precautions ( 5.1 )].
1.1Refractory Complex Partial Seizures (CPS) Vigabatrin for oral solution is indicated as adjunctive therapy for adults and pediatric patients 2 years of age and older with refractory complex partial seizures who have inadequately responded to several alternative treatments and for whom the potential benefits outweigh the risk of vision loss [ see Warnings and Precautions ( 5.1 ) ]. Vigabatrin for oral solution is not indicated as a first line agent for complex partial seizures.
1.2Infantile Spasms (IS) Vigabatrin for oral solution is indicated as monotherapy for pediatric patients with infantile spasms 1 month to 2 years of age for whom the potential benefits outweigh the potential risk of vision loss [ see Warnings and Precautions ( 5.1 )].
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Refractory Complex Partial Seizures Adults (17 years of age and older): Initiate at 1,000 mg/day (500 mg twice daily); increase total daily dose weekly in 500 mg/day increments, to the recommended dose of 3,000 mg/day (1,500 mg twice daily) ( 2.2 ) · Pediatric (2 to 16 years of age): The recommended dosage is based on body weight and administered as two divided doses ( 2.2 ) The dosage may be increased in weekly intervals, depending on response ( 2.2 ) Dose patients weighing more than 60 kg according to adult recommendations ( 2.2 ) Infantile Spasms • Initiate at a daily dose of 50 mg/kg (25 mg/kg twice daily); increase total daily dose every 3 days, in increments of 25 mg/kg/day to 50 mg/kg/day, up to a maximum daily dose of 150 mg/kg (75 mg/kg twice daily) ( 2.3) Renal Impairment : Dose adjustment recommended ( 2.4 , 8.5 , 8.6 )
2.1Important Dosing and Administration Instructions Dosing Use the lowest dosage and shortest exposure to vigabatrin for oral solution consistent with clinical objectives [see Warnings and Precautions ( 5.1 )]. The vigabatrin for oral solution dosing regimen depends on the indication, age group, weight, and dosage form (tablets or for oral solution) [see Dosage and Administration ( 2.2 , 2.3 )] . Patients with impaired renal function require dose adjustment [see Dosage and Administration ( 2.4 ) ].
Monitoring of vigabatrin plasma concentrations to optimize therapy is not helpful. Administration Vigabatrin for oral solution is given orally with or without food. Vigabatrin for oral solution should be mixed with water prior to administration [ see Dosage and Administration ( 2.5 ) ].
A calibrated measuring device is recommended to measure and deliver the prescribed dose accurately. A household teaspoon or tablespoon is not an adequate measuring device. If a decision is made to discontinue vigabatrin for oral solution, the dose should be gradually reduced [see Dosage and Administration ( 2.2 , 2.3 ) and Warnings and Precautions ( 5.6 ) ].
2.2Refractory Complex Partial Seizures Adults (Patients 17 Years of Age and Older) Treatment should be initiated at 1,000 mg/day (500 mg twice daily). Total daily dose may be increased in 500 mg increments at weekly intervals, depending on response. The recommended dose of vigabatrin for oral solution in adults is 3,000 mg/day (1,500 mg twice daily).
A 6,000 mg/day dose has not been shown to confer additional benefit compared to the 3,000 mg/day dose and is associated with an increased incidence of adverse events. In controlled clinical studies in adults with complex partial seizures, vigabatrin was tapered by decreasing the daily dose 1,000 mg/day on a weekly basis until discontinued [ see Warnings and Precautions ( 5.6 ) ]. Pediatric (Patients 2 to 16 Years of Age) The recommended dosage is based on body weight and administered as two divided doses, as shown in Table 1.
The dosage may be increased in weekly intervals to the total daily maintenance dosage, depending on response. Pediatric patients weighing more than 60 kg should be dosed according to adult recommendations. Table 1.
CPS Dosing Recommendations for Pediatric Patients Weighing 10 kg up to 60 kg †† Body Weight [kg] Total Daily*Starting Dose [mg/day] Total Daily*Maintenance Dose † [mg/day] 10 kg to 15 kg 350 mg 1,050 mg Greater than 15 kg to 20 kg 450 mg 1,300 mg Greater than 20 kg to 25 kg 500 mg 1,500 mg Greater than 25 kg to 60 kg 500 mg 2,000 mg *Administered in two divided doses †Maintenance dose is based on 3,000 mg/day adult-equivalent dose †† Patients weighing more than 60 kg should be dosed according to adult recommendations In patients with refractory complex partial seizures, vigabatrin for oral solution should be withdrawn if a substantial clinical benefit is not observed within 3 months of initiating treatment.
If, in the clinical judgment of the prescriber, evidence of treatment failure becomes obvious earlier than 3 months, treatment should be discontinued at that…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS For oral solution: 500 mg packets of a white to off-white powder filled in packet. For oral solution: 500 mg per packet( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Abnormal MRI signal changes and intramyelinic edema have been reported in some infants with Infantile Spasms receiving vigabatrin ( 5.3, 5.4 ) Suicidal behavior and ideation: Antiepileptic drugs, including vigabatrin, increase the risk of suicidal thoughts and behavior ( 5.5 ) Withdrawal of AEDs: Taper dose to avoid withdrawal seizures ( 5.6 ) Anemia: Monitor for symptoms of anemia ( 5.7 ) Somnolence and fatigue: Advise patients not to drive or operate machinery until they have gained sufficient experience on vigabatrin ( 5.8 )
5.1Permanent Vision Loss Vigabatrin can cause permanent vision loss. Because of this risk and because, when it is effective, vigabatrin provides an observable symptomatic benefit; patient response and continued need for treatment should be periodically assessed. Based upon adult studies, 30 percent or more of patients can be affected with bilateral concentric visual field constriction ranging in severity from mild to severe.
Severe cases may be characterized by tunnel vision to within 10 degrees of visual fixation, which can result in disability. In some cases, vigabatrin also can damage the central retina and may decrease visual acuity. Symptoms of vision loss from vigabatrin are unlikely to be recognized by patients or caregivers before vision loss is severe.
Vision loss of milder severity, while often unrecognized by the patient or caregiver, can still adversely affect function. Because assessing vision may be difficult in infants and children, the frequency and extent of vision loss is poorly characterized in these patients. For this reason, the understanding of the risk is primarily based on the adult experience.
The possibility that vision loss from vigabatrin may be more common, more severe, or have more severe functional consequences in infants and children than in adults cannot be excluded. The onset of vision loss from vigabatrin is unpredictable and can occur within weeks of starting treatment or sooner, or at any time after starting treatment, even after months or years. The risk of vision loss increases with increasing dose and cumulative exposure, but there is no dose or exposure known to be free of risk of vision loss.
In patients with refractory complex partial seizures, vigabatrin should be withdrawn if a substantial clinical benefit is not observed within 3 months of initiating treatment. If, in the clinical judgment of the prescriber, evidence of treatment failure becomes obvious earlier than 3 months, treatment should be discontinued at that time [see Dosage and Administration ( 2.2 ) and Warnings and Precautions ( 5.6 )] . In patients with infantile spasms, vigabatrin should be withdrawn if a substantial clinical benefit is not observed within 2 to 4 weeks.
If, in the clinical judgment of the prescriber, evidence of treatment failure becomes obvious earlier than 2 to 4 weeks, treatment should be discontinued at that time [see Dosage and Administration ( 2.3 ) and Warnings and Precautions ( 5.6 )] . Vigabatrin should not be used in patients with, or at high risk of, other types of irreversible vision loss unless the benefits of treatment clearly outweigh the risks. The interaction of other types of irreversible vision damage with vision damage from vigabatrin has not been well-characterized, but is likely adverse.
Vigabatrin should not be used with other drugs associated with serious adverse ophthalmic effects such as retinopathy or glaucoma unless the benefits clearly outweigh the risks. Monitoring of Vision Monitoring of vision by an ophthalmic professional with expertise in visual field interpretation and the ability to perform dilated indirect ophthalmoscopy of the retina is recommended [see Warnings and Precautions ( 5.2 ) ]. Because vision testing in infants is difficult, vision loss may not be detected until it is severe.
For patients receiving vigabatrin, vision assessment is recommended at baseline (no later than 4 weeks after starting vigabatrin)…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious and otherwise important adverse reactions are described elsewhere in labeling: Permanent Vision Loss [see BOXED WARNING and Warnings and Precautions ( 5.1 )] Magnetic Resonance Imaging (MRI) Abnormalities in Infants [see Warnings and Precautions ( 5.3 )] Neurotoxicity [see Warnings and Precautions ( 5.4) ] Suicidal Behavior and Ideation [see Warnings and Precautions ( 5.5 )] Withdrawal of Antiepileptic Drugs (AEDs) [see Warnings and Precautions ( 5.6 )] Anemia [see Warnings and Precautions ( 5.7 )] Somnolence and Fatigue [see Warnings and Precautions ( 5.8) ] Peripheral Neuropathy [see Warnings and Precautions ( 5.9 )] Weight Gain [see Warnings and Precautions ( 5.10) ] Edema [see Warnings and Precautions ( 5.11 )] Refractory Complex Partial Seizures Most common adverse reactions in controlled studies include (incidence ≥5% over placebo): Adults: blurred vision, somnolence, dizziness, abnormal coordination, tremor, and fatigue ( 6.1 ) Pediatric patients (3 to 16 years of age): weight gain ( 6.1 ) Infantile Spasms (incidence >5% and greater than on placebo) Somnolence, bronchitis, ear infection, and acute otitis media ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Dr.
Reddy’s Laboratories, Inc. at 1-888-375-3784 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In U.S. and primary non-U.S. clinical studies of 4,079 vigabatrin-treated patients, the most common (≥5%) adverse reactions associated with the use of vigabatrin in combination with other AEDs were headache, somnolence, fatigue, dizziness, convulsion, nasopharyngitis, weight gain, upper respiratory tract infection, visual field defect, depression, tremor, nystagmus, nausea, diarrhea, memory impairment, insomnia, irritability, abnormal coordination, blurred vision, diplopia, vomiting, influenza, pyrexia, and rash.
The adverse reactions most commonly associated with vigabatrin treatment discontinuation in ≥1% of patients were convulsion and depression. In patients with infantile spasms, the adverse reactions most commonly associated with vigabatrin treatment discontinuation in ≥1% of patients were infections, status epilepticus, developmental coordination disorder, dystonia, hypotonia, hypertonia, weight gain, and insomnia. Refractory Complex Partial Seizures Adults Table 5 lists the adverse reactions that occurred in ≥2% and more than one patient per vigabatrin-treated group and that occurred more frequently than in placebo patients from 2 U.S. adjunctive clinical studies of refractory CPS in adults.
Table 5. Adverse Reactions in Pooled, Adjunctive Trials in Adults with Refractory Complex Partial Seizures Vigabatrin dosage (mg/day) 3,000 6,000 Placebo Body System [N=134] [N=43] [N=135] Adverse Reaction % % % Ear Disorders Tinnitus 2 0 1 Vertigo 2 5 1 Eye Disorders Blurred vision 13 16 5 Diplopia 7 16 3 Asthenopia 2 2 0 Eye pain 0 5 0 Gastrointestinal Disorders Diarrhea 10 16 7 Nausea 10 2 8 Vomiting 7 9 6 Constipation 8 5 3 Upper abdominal pain 5 5 1 Dyspepsia 4 5 3 Stomach discomfort 4 2 1 Abdominal pain 3 2 1 Toothache 2 5 2 Abdominal distension 2 0 1 General Disorders Fatigue 23 40 16 Gait disturbance 6 12 7 Asthenia 5 7 1 Edema peripheral 5 7 1 Fever 4 7 3 Chest pain 1 5 1 Thirst 2 0 0 Malaise 0 5 0 Infections Nasopharyngitis 14 9 10 Upper respiratory tract infection 7 9 6 Influenza 5 7 4 Urinary tract infection 4 5 0 Bronchitis 0 5 1 Injury Contusion 3 5 2 Joint sprain 1 2 1 Muscle strain 1 2 1 Wound secretion 0 2 0 Metabolism and Nutrition Disorders Increased appetite 1 5 1 Weight gain 6 14 3 Musculoskeletal Disorders Arthralgia 10 5 3 Back pain 4 7 2 Pain in extremity 6 2 4 Myalgia 3 5 1 Muscle twitching 1 9 1 Muscle spasms 3 0…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Decreased phenytoin plasma levels: dosage adjustment may be needed ( 7.1 )
7.1Antiepileptic Drugs Phenytoin Although phenytoin dose adjustments are not routinely required, dose adjustment of phenytoin should be considered if clinically indicated, since vigabatrin may cause a moderate reduction in total phenytoin plasma levels [see Clinical Pharmacology ( 12.3 )] . Clonazepam Vigabatrin may moderately increase the C max of clonazepam resulting in an increase of clonazepam-associated adverse reactions [see Clinical Pharmacology ( 12.3 )]. Other AEDs There are no clinically significant pharmacokinetic interactions between vigabatrin and either phenobarbital or sodium valproate.
Based on population pharmacokinetics, carbamazepine, clorazepate, primidone, and sodium valproate appear to have no effect on plasma concentrations of vigabatrin [see Clinical Pharmacology ( 12.3 )].
7.2Oral Contraceptives Vigabatrin is unlikely to affect the efficacy of steroid oral contraceptives [see Clinical Pharmacology ( 12.3 )].
7.3Drug-Laboratory Test Interactions Vigabatrin decreases alanine transaminase (ALT) and aspartate transaminase (AST) plasma activity in up to 90% of patients. In some patients, these enzymes become undetectable. The suppression of ALT and AST activity by vigabatrin may preclude the use of these markers, especially ALT, to detect early hepatic injury.
Vigabatrin may increase the amount of amino acids in the urine, possibly leading to a false positive test for certain rare genetic metabolic diseases (e.g., alpha aminoadipic aciduria).
7.1Antiepileptic Drugs Phenytoin Although phenytoin dose adjustments are not routinely required, dose adjustment of phenytoin should be considered if clinically indicated, since vigabatrin may cause a moderate reduction in total phenytoin plasma levels [see Clinical Pharmacology ( 12.3 )] . Clonazepam Vigabatrin may moderately increase the C max of clonazepam resulting in an increase of clonazepam-associated adverse reactions [see Clinical Pharmacology ( 12.3 )]. Other AEDs There are no clinically significant pharmacokinetic interactions between vigabatrin and either phenobarbital or sodium valproate.
Based on population pharmacokinetics, carbamazepine, clorazepate, primidone, and sodium valproate appear to have no effect on plasma concentrations of vigabatrin [see Clinical Pharmacology ( 12.3 )].
7.2Oral Contraceptives Vigabatrin is unlikely to affect the efficacy of steroid oral contraceptives [see Clinical Pharmacology ( 12.3 )].
7.3Drug-Laboratory Test Interactions Vigabatrin decreases alanine transaminase (ALT) and aspartate transaminase (AST) plasma activity in up to 90% of patients. In some patients, these enzymes become undetectable. The suppression of ALT and AST activity by vigabatrin may preclude the use of these markers, especially ALT, to detect early hepatic injury.
Vigabatrin may increase the amount of amino acids in the urine, possibly leading to a false positive test for certain rare genetic metabolic diseases (e.g., alpha aminoadipic aciduria).
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data, may cause fetal harm ( 8.1 ) Lactation: Vigabatrin is excreted in human milk ( 8.2 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to AEDs, including vigabatrin, during pregnancy. Encourage women who are taking vigabatrin during pregnancy to enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry. This can be done by calling the toll-free number 1-888-233-2334 or visiting the website, http://www.aedpregnancyregistry.org/.
This must be done by the patient herself. Risk Summary There are no adequate data on the developmental risk associated with the use of vigabatrin in pregnant women. Limited available data from case reports and cohort studies pertaining to vigabatrin use in pregnant women have not established a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes.
However, based on animal data, vigabatrin use in pregnant women may result in fetal harm. When administered to pregnant animals, vigabatrin produced developmental toxicity, including an increase in fetal malformations and offspring neurobehavioral and neurohistopathological effects, at clinically relevant doses. In addition, developmental neurotoxicity was observed in rats treated with vigabatrin during a period of postnatal development corresponding to the third trimester of human pregnancy (see Data) .
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown. Data Animal Data Administration of vigabatrin (oral doses of 50 to 200 mg/kg/day) to pregnant rabbits throughout the period of organogenesis was associated with an increased incidence of malformations (cleft palate) and embryofetal death; these findings were observed in two separate studies.
The no-effect dose for adverse effects on embryofetal development in rabbits (100 mg/kg/day) is approximately 1/2 the maximum recommended human dose (MRHD) of 3 grams/day on a body surface area (mg/m 2 ) basis. In rats, oral administration of vigabatrin (50, 100, or 150 mg/kg/day) throughout organogenesis resulted in decreased fetal body weights and increased incidences of fetal anatomic variations. The no-effect dose for adverse effects on embryo-fetal development in rats (50 mg/kg/day) is approximately 1/5 the MRHD on a mg/m 2 basis.
Oral administration of vigabatrin (50, 100, 150 mg/kg/day) to rats from the latter part of pregnancy through weaning produced long-term neurohistopathological (hippocampal vacuolation) and neurobehavioral (convulsions) abnormalities in the offspring. A no-effect dose for developmental neurotoxicity in rats was not established; the low-effect dose (50 mg/kg/day) is approximately 1/5 the MRHD on a mg/m 2 basis. In a published study, vigabatrin (300 or 450 mg/kg) was administered by intraperitoneal injection to a mutant mouse strain on a single day during organogenesis (day 7, 8, 9, 10, 11, or 12).
An increase in fetal malformations (including cleft palate) was observed at both doses. Oral administration of vigabatrin (5, 15, or 50 mg/kg/day) to young rats during the neonatal and juvenile periods of development (postnatal days 4 to 65) produced neurobehavioral (convulsions, neuromotor impairment, learning deficits) and neurohistopathological (brain vacuolation, decreased myelination, and retinal dysplasia) abnormalities in treated animals. The early postnatal period in rats is generally thought to correspond to late pregnancy in humans in terms of brain development.
The no-effect dose for developmental neurotoxicity in juvenile rats (5 mg/kg/day) was associated with plasma vigabatrin exposures (AUC) less than 1/30 of those measured in pediatric patients receiving an oral d…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to AEDs, including vigabatrin, during pregnancy. Encourage women who are taking vigabatrin during pregnancy to enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry. This can be done by calling the toll-free number 1-888-233-2334 or visiting the website, http://www.aedpregnancyregistry.org/.
This must be done by the patient herself. Risk Summary There are no adequate data on the developmental risk associated with the use of vigabatrin in pregnant women. Limited available data from case reports and cohort studies pertaining to vigabatrin use in pregnant women have not established a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes.
However, based on animal data, vigabatrin use in pregnant women may result in fetal harm. When administered to pregnant animals, vigabatrin produced developmental toxicity, including an increase in fetal malformations and offspring neurobehavioral and neurohistopathological effects, at clinically relevant doses. In addition, developmental neurotoxicity was observed in rats treated with vigabatrin during a period of postnatal development corresponding to the third trimester of human pregnancy (see Data) .
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown. Data Animal Data Administration of vigabatrin (oral doses of 50 to 200 mg/kg/day) to pregnant rabbits throughout the period of organogenesis was associated with an increased incidence of malformations (cleft palate) and embryofetal death; these findings were observed in two separate studies.
The no-effect dose for adverse effects on embryofetal development in rabbits (100 mg/kg/day) is approximately 1/2 the maximum recommended human dose (MRHD) of 3 grams/day on a body surface area (mg/m 2 ) basis. In rats, oral administration of vigabatrin (50, 100, or 150 mg/kg/day) throughout organogenesis resulted in decreased fetal body weights and increased incidences of fetal anatomic variations. The no-effect dose for adverse effects on embryo-fetal development in rats (50 mg/kg/day) is approximately 1/5 the MRHD on a mg/m 2 basis.
Oral administration of vigabatrin (50, 100, 150 mg/kg/day) to rats from the latter part of pregnancy through weaning produced long-term neurohistopathological (hippocampal vacuolation) and neurobehavioral (convulsions) abnormalities in the offspring. A no-effect dose for developmental neurotoxicity in rats was not established; the low-effect dose (50 mg/kg/day) is approximately 1/5 the MRHD on a mg/m 2 basis. In a published study, vigabatrin (300 or 450 mg/kg) was administered by intraperitoneal injection to a mutant mouse strain on a single day during organogenesis (day 7, 8, 9, 10, 11, or 12).
An increase in fetal malformations (including cleft palate) was observed at both doses. Oral administration of vigabatrin (5, 15, or 50 mg/kg/day) to young rats during the neonatal and juvenile periods of development (postnatal days 4 to 65) produced neurobehavioral (convulsions, neuromotor impairment, learning deficits) and neurohistopathological (brain vacuolation, decreased myelination, and retinal dysplasia) abnormalities in treated animals. The early postnatal period in rats is generally thought to correspond to late pregnancy in humans in terms of brain development.
The no-effect dose for developmental neurotoxicity in juvenile rats (5 mg/kg/day) was associated with plasma vigabatrin exposures (AUC) less than 1/30 of those measured in pediatric patients receiving an oral dose of 50 mg/kg.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of vigabatrin as adjunctive treatment of refractory complex partial seizures in pediatric patients 2 to 16 years of age have been established and is supported by three double-blind, placebo-controlled studies in patients 3 to 16 years of age, adequate and well-controlled studies in adult patients, pharmacokinetic data from patients 2 years of age and older, and additional safety information in patients 2 years of age [see Clinical Pharmacology ( 12.3 ) and Clinical Studies ( 14.1 )] .
The dosing recommendation in this population varies according to age group and is weight-based [see Dosage and Administration ( 2.2 )] . Adverse reactions in this pediatric population are similar to those observed in the adult population [see Adverse Reactions ( 6.1 )] . The safety and effectiveness of vigabatrin as monotherapy for pediatric patients with infantile spasms (1 month to 2 years of age) have been established [see Dosage and Administration ( 2.3 ) and Clinical Studies ( 14 .2 )].
Safety and effectiveness as adjunctive treatment of refractory complex partial seizures in pediatric patients below the age of 2 and as monotherapy for the treatment of infantile spasms in pediatric patients below the age of 1 month have not been established. Duration of therapy for infantile spasms was evaluated in a post hoc analysis of a Canadian Pediatric Epilepsy Network (CPEN) study of developmental outcomes in infantile spasms patients. This analysis suggests that a total duration of 6 months of vigabatrin therapy is adequate for the treatment of infantile spasms.
However, prescribers must use their clinical judgment as to the most appropriate duration of use [see Clinical Studies ( 14.2 ) ]. Abnormal MRI signal changes and Intramyelinic Edema (IME) in infants and young children being treated with vigabatrin have been observed [see Warnings and Precautions ( 5.3 , 5.4 )]. Juvenile Animal Toxicity Data Oral administration of vigabatrin (5, 15, or 50 mg/kg/day) to young rats during the neonatal and juvenile periods of development (postnatal days 4 to 65) produced neurobehavioral (convulsions, neuromotor impairment, learning deficits) and neurohistopathological (brain gray matter vacuolation, decreased myelination, and retinal dysplasia) abnormalities.
The no-effect dose for developmental neurotoxicity in juvenile rats (the lowest dose tested) was associated with plasma vigabatrin exposures (AUC) substantially less than those measured in pediatric patients at recommended doses. In dogs, oral administration of vigabatrin (30 or 100 mg/kg/day) during selected periods of juvenile development (postnatal days 22 to 112) produced neurohistopathological abnormalities (brain gray matter vacuolation). Neurobehavioral effects of vigabatrin were not assessed in the juvenile dog.
A no-effect dose for neurohistopathology was not established in juvenile dogs; the lowest effect dose (30 mg/kg/day) was associated with plasma vigabatrin exposures lower than those measured in pediatric patients at recommended doses [see Warnings and Precautions ( 5.4 )] .
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of vigabatrin did not include sufficient numbers of patients aged 65 and over to determine whether they responded differently from younger patients. Vigabatrin is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
Oral administration of a single dose of 1.5 grams of vigabatrin to elderly (≥65 years) patients with reduced creatinine clearance (<50 mL/min) was associated with moderate to severe sedation and confusion in 4 of 5 patients, lasting up to 5 days. The renal clearance of vigabatrin was 36% lower in healthy elderly subjects (≥65 years) than in young healthy males. Adjustment of dose or frequency of administration should be considered.
Such patients may respond to a lower maintenance dose [ see Dosage and Administration ( 2.4 ) and Clinical Pharmacology ( 12.3) ] . Other reported clinical experience has not identified differences in responses between the elderly and younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE
10.1Signs, Symptoms, and Laboratory Findings of Overdosage Confirmed and/or suspected vigabatrin overdoses have been reported during clinical trials and in post marketing surveillance. No vigabatrin overdoses resulted in death. When reported, the vigabatrin dose ingested ranged from 3 grams to 90 grams, but most were between 7.5 grams and 30 grams.
Nearly half the cases involved multiple drug ingestions including carbamazepine, barbiturates, benzodiazepines, lamotrigine, valproic acid, acetaminophen, and/or chlorpheniramine. Coma, unconsciousness, and/or drowsiness were described in the majority of cases of vigabatrin overdose. Other less commonly reported symptoms included vertigo, psychosis, apnea or respiratory depression, bradycardia, agitation, irritability, confusion, headache, hypotension, abnormal behavior, increased seizure activity, status epilepticus, and speech disorder.
These symptoms resolved with supportive care.
10.2Management of Overdosage There is no specific antidote for vigabatrin overdose. Standard measures to remove unabsorbed drug should be used, including elimination by emesis or gastric lavage. Supportive measures should be employed, including monitoring of vital signs and observation of the clinical status of the patient.
In an in vitro study, activated charcoal did not significantly adsorb vigabatrin. The effectiveness of hemodialysis in the treatment of vigabatrin overdose is unknown. In isolated case reports in renal failure patients receiving therapeutic doses of vigabatrin, hemodialysis reduced vigabatrin plasma concentrations by 40% to 60%.
10.1Signs, Symptoms, and Laboratory Findings of Overdosage Confirmed and/or suspected vigabatrin overdoses have been reported during clinical trials and in post marketing surveillance. No vigabatrin overdoses resulted in death. When reported, the vigabatrin dose ingested ranged from 3 grams to 90 grams, but most were between 7.5 grams and 30 grams.
Nearly half the cases involved multiple drug ingestions including carbamazepine, barbiturates, benzodiazepines, lamotrigine, valproic acid, acetaminophen, and/or chlorpheniramine. Coma, unconsciousness, and/or drowsiness were described in the majority of cases of vigabatrin overdose. Other less commonly reported symptoms included vertigo, psychosis, apnea or respiratory depression, bradycardia, agitation, irritability, confusion, headache, hypotension, abnormal behavior, increased seizure activity, status epilepticus, and speech disorder.
These symptoms resolved with supportive care.
10.2Management of Overdosage There is no specific antidote for vigabatrin overdose. Standard measures to remove unabsorbed drug should be used, including elimination by emesis or gastric lavage. Supportive measures should be employed, including monitoring of vital signs and observation of the clinical status of the patient.
In an in vitro study, activated charcoal did not significantly adsorb vigabatrin. The effectiveness of hemodialysis in the treatment of vigabatrin overdose is unknown. In isolated case reports in renal failure patients receiving therapeutic doses of vigabatrin, hemodialysis reduced vigabatrin plasma concentrations by 40% to 60%.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The precise mechanism of vigabatrin’s anti-seizure effect is unknown, but it is believed to be the result of its action as an irreversible inhibitor of γ-aminobutyric acid transaminase (GABA-T), the enzyme responsible for the metabolism of the inhibitory neurotransmitter GABA. This action results in increased levels of GABA in the central nervous system. No direct correlation between plasma concentration and efficacy has been established.
The duration of drug effect is presumed to be dependent on the rate of enzyme re-synthesis rather than on the rate of elimination of the drug from the systemic circulation.
12.2Pharmacodynamics Effects on Electrocardiogram There is no indication of a QT/QTc prolonging effect of vigabatrin in single doses up to 6 grams. In a randomized, placebo-controlled, crossover study, 58 healthy subjects were administered a single oral dose of vigabatrin (3 grams and 6 grams) and placebo. Peak concentrations for 6 grams vigabatrin were approximately 2-fold higher than the peak concentrations following the 3 grams single oral dose.
12.3Pharmacokinetics Vigabatrin displayed linear pharmacokinetics after administration of single doses ranging from 0.5 grams to 4 grams, and after administration of repeated doses of 0.5 grams and 2 grams twice daily. Bioequivalence has been established between the oral solution and tablet formulations. The following PK information (T max , half-life, and clearance) of vigabatrin was obtained from stand-alone PK studies and population PK analyses.
Absorption Following oral administration, vigabatrin is essentially completely absorbed. The time to maximum concentration (T max ) is approximately 1 hour for children and adolescents (3 years to 16 years of age) and adults, and approximately 2.5 hours for infants (5 months to 2 years of age). There was little accumulation with multiple dosing in adult and pediatric patients.
A food effect study involving administration of vigabatrin to healthy volunteers under fasting and fed conditions indicated that the C max was decreased by 33%, T max was increased to 2 hours, and AUC was unchanged under fed conditions. Distribution Vigabatrin does not bind to plasma proteins. Vigabatrin is widely distributed throughout the body; mean steady-state volume of distribution is
1.1L/kg (CV = 20%). Metabolism and Elimination Vigabatrin is not significantly metabolized; it is eliminated primarily through renal excretion. The terminal half-life of vigabatrin is about 5.7 hours for infants (5 months to 2 years of age), 6.8 hours for children (3 to 9 years of age), 9.5 hours for children and adolescents (10 to 16 years of age), and 10.5 hours for adults.
Following administration of [14] C-vigabatrin to healthy male volunteers, about 95% of total radioactivity was recovered in the urine over 72 hours with the parent drug representing about 80% of this. Vigabatrin induces CYP2C9, but does not induce other hepatic cytochrome P450 enzyme systems. Specific Populations Geriatric The renal clearance of vigabatrin in healthy elderly patients (≥65 years of age) was 36% less than those in healthy younger patients.
This finding is confirmed by an analysis of data from a controlled clinical trial [see Use in Specific Populations ( 8.5 )]. Pediatric The clearance of vigabatrin is
2.4 L/hr for infants (5 months to 2 years of age),
5.1 L/hr for children (3 to 9 years of age),
5.8L/hr for children and adolescents (10 to 16 years of age) and 7 L/hr for adults. Gender No gender differences were observed for the pharmacokinetic parameters of vigabatrin in patients. Race No specific study was conducted to investigate the effects of race on vigabatrin pharmacokinetics.
A cross study comparison between 23 Caucasian and 7 Japanese patients who received 1, 2, and 4 grams of vigabatrin indicated that the AUC, C max , and half-life were similar for the two populations. However, the mean renal clearance of Caucasians (5.2 L/hr)…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The precise mechanism of vigabatrin’s anti-seizure effect is unknown, but it is believed to be the result of its action as an irreversible inhibitor of γ-aminobutyric acid transaminase (GABA-T), the enzyme responsible for the metabolism of the inhibitory neurotransmitter GABA. This action results in increased levels of GABA in the central nervous system. No direct correlation between plasma concentration and efficacy has been established.
The duration of drug effect is presumed to be dependent on the rate of enzyme re-synthesis rather than on the rate of elimination of the drug from the systemic circulation.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Vigabatrin for oral solution USP, 500 mg packets contain a white to off-white powder. They are supplied in packages of 50 (NDC 43598-697-50). The oral syringes are provided separately by the pharmacy.
16.2Storage and Handling Store at 20°C to 25°C (68°F to 77°F). [See USP Controlled Room Temperature].
16.1How Supplied Vigabatrin for oral solution USP, 500 mg packets contain a white to off-white powder. They are supplied in packages of 50 (NDC 43598-697-50). The oral syringes are provided separately by the pharmacy.
16.2Storage and Handling Store at 20°C to 25°C (68°F to 77°F). [See USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Vigabatrin for oral solution, USP is an oral antiepileptic drug and is available as a white to off-white powder for oral solution in packets of 500 mg. The chemical name of vigabatrin, a racemate consisting of two enantiomers, is (±) 4-amino-5-hexenoic acid. The molecular formula is C 6 H 11 NO 2 and the molecular weight is 129.16.
It has the following structural formula: Vigabatrin, USP is a white or almost white powder which is freely soluble in water. The pH of a 1% aqueous solution is about 6.9. The n-octanol/water partition coefficient of vigabatrin is about 0.011 (log P=-1.96) at physiologic pH.
Vigabatrin melts with decomposition in a 3-degree range within the temperature interval of 171°C to 176°C. The dissociation constants (pKa) of vigabatrin are 4 and 9.7 at room temperature (25°C). Vigabatrin for oral solution, USP is available as a white to off white powder.
Each packet contains 500 mg of vigabatrin. The inactive ingredient is povidone.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients and caregivers to read the FDA-approved patient labeling (Medication Guide and Instructions for Use). Administration Instructions for Vigabatrin for Oral Solution Physicians should confirm that caregiver(s) understand how to mix vigabatrin for oral solution and to administer the correct dose to their infants and pediatric patients [see Dosage and Administration ( 2.5 )]. Permanent Vision Loss Inform patients and caregivers of the risk of permanent vision loss, particularly loss of peripheral vision, from vigabatrin for oral solution, and the need for monitoring vision [see Warnings and Precautions ( 5.1 )] .
Monitoring of vision, including assessment of visual fields and visual acuity, is recommended at baseline (no later than 4 weeks after starting vigabatrin for oral solution), at least every 3 months while on therapy, and about 3 to 6 months after discontinuation of therapy. In patients for whom vision testing is not possible, treatment may continue without recommended testing according to clinical judgment with appropriate patient or caregiver counseling. Patients or caregivers should be informed that if baseline or subsequent vision is not normal, vigabatrin for oral solution should only be used if the benefits of vigabatrin for oral solution treatment clearly outweigh the risks of additional vision loss.
Advise patients and caregivers that vision testing may be insensitive and may not detect vision loss before it is severe. Also advise patients and caregivers that if vision loss is documented, such loss is irreversible. Ensure that both of these points are understood by patients and caregivers.
Patients and caregivers should be informed that if changes in vision are suspected, they should notify their physician immediately. Vigabatrin REMS Program Vigabatrin for oral solution is available only through a restricted program called the Vigabatrin REMS Program [see Warnings and Precautions ( 5.2 )]. Inform patients/caregivers of the following: Patients/caregivers must be enrolled in the program.
Vigabatrin for oral solution is only available through pharmacies that are enrolled in the Vigabatrin REMS Program. MRI Abnormalities in Infants Inform caregiver(s) of the possibility that infants may develop an abnormal MRI signal of unknown clinical significance [see Warnings and Precautions ( 5.3 )]. Suicidal Thinking and Behavior Counsel patients, their caregiver(s), and families that AEDs, including vigabatrin, may increase the risk of suicidal thoughts and behavior.
Also advise patients and caregivers of the need to be alert for the emergence or worsening of symptoms of depression, any unusual changes in mood or behavior, or the emergence of suicidal thoughts, behavior, or thoughts of self-harm. Behaviors of concern should be reported immediately to healthcare providers [ see Warnings and Precautions ( 5.5 )]. Pregnancy Advise pregnant women and women of child-bearing potential that the use of vigabatrin during pregnancy can cause fetal harm which may occur early in pregnancy before many women know they are pregnant.
Instruct patients to notify their physician if they become pregnant or intend to become pregnant during therapy. Advise patients that there is a pregnancy exposure registry that collects information about the safety of antiepileptic drugs during pregnancy [see Use in Specific Populations ( 8.1 )]. Nursing Counsel patients that vigabatrin is excreted in breast milk.
Because of the potential for serious adverse reactions in nursing infants from vigabatrin, breastfeeding is not recommended. If a decision is made to breastfeed, nursing mothers should be counseled to observe their infants for signs of vision loss, sedation and poor sucking [see Use in Specific Populations ( 8.2 )] . Withdrawal of Vigabatrin Therapy Instruct patients and caregivers not to suddenly discontinue vigabatrin therapy without consulting with their healthcare provider.
As with all AEDs, withdrawa…
💬 Medication Guide ▾
MEDICATION GUIDE Vigabatrin for Oral Solution, USP (vye GA ba trin) What is the most important information I should know about vigabatrin for oral solution? Vigabatrin for oral solution can cause serious side effects, including: Permanent vision loss Magnetic resonance imaging (MRI) changes in babies with infantile spasms (IS) Risk of suicidal thoughts or actions 1. Permanent vision loss: Vigabatrin for oral solution can damage the vision of anyone who takes it.
Some people can have severe loss particularly to their ability to see to the side when they look straight ahead (peripheral vision). With severe vision loss, you may only be able to see things straight in front of you (sometimes called “tunnel vision”). You may also have blurry vision.
If this happens, it will not get better. Vision loss and use of vigabatrin for oral solution in adults and children 2 years and older: Because of the risk of vision loss, vigabatrin for oral solution is used to treat complex partial seizures (CPS) only in people who do not respond well enough to several other medicines. Tell your healthcare provider right away if you (or your child): might not be seeing as well as before starting vigabatrin for oral solution. start to trip, bump into things, or are more clumsy than usual. are surprised by people or things coming in front of you that seem to come out of nowhere.
These changes can mean that you (or your child) have damage to your vision. It is recommended that your healthcare provider test your (or your child’s) vision (including peripheral vision) and visual acuity (ability to read an eye chart) before you (or your child) start vigabatrin for oral solution or within 4 weeks after starting vigabatrin for oral solution, and at least every 3 months after that until vigabatrin for oral solution is stopped. It is also recommended that you (or your child) have a vision test about 3 to 6 months after vigabatrin for oral solution is stopped.
Your vision loss may get worse after you stop taking vigabatrin for oral solution. Some people are not able to complete testing of vision.Your healthcare provider will determine if you (or your child) can be tested. If you (or your child) cannot complete vision testing, your healthcare provider may continue prescribing vigabatrin for oral solution, but your healthcare provider will not be able to watch for any vision loss you (or your child) may get.
Even if your vision (or your child’s vision) seems fine, it is important that you (or your child) get these regular vision tests because vision damage can happen before you (or your child) notice any changes. These vision tests cannot prevent the vision damage that can happen with vigabatrin for oral solution, but they do allow the healthcare provider to decide if you (or your child) should stop vigabatrin for oral solution if your vision has gotten worse. Vision testing may not detect vision loss before it is severe.
If you do not have these vision tests regularly, your healthcare provider may stop prescribing vigabatrin for oral solution. If you drive and your vision is damaged by vigabatrin for oral solution, driving might be more dangerous, or you may not be able to drive safely at all. Talk about this with your healthcare provider.
Vision loss in babies: Because of the risk of vision loss, vigabatrin for oral solution is used in babies 1 month to 2 years of age with infantile spasms (IS) only when you and your healthcare provider decide that the possible benefits of vigabatrin for oral solution are more important than the risks. Parents or caregivers are not likely to recognize the symptoms of vision loss in babies until it is severe. Healthcare providers may not find vision loss in babies until it is severe.
It is difficult to test vision in babies, but, to the extent possible, all babies should have their vision tested before starting vigabatrin for oral solution or within 4 weeks after starting vigabatrin for oral solution, and every 3 months after that u…