
Darunavir 800 mg Tablet, Film Coated, 30-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Protease Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Darunavir is used to treat human immunodeficiency virus (HIV) infection. Darunavir is in a class of medications called protease inhibitors. It works by decreasing the amount of HIV in the blood. Although darunavir does not cure HIV, it may decrease your chance of developing acquired immunodeficiency syndrome (AIDS) and HIV-related illnesses. Taking these medications and making other lifestyle changes may decrease the risk of giving the HIV virus to other people.
Read the full MedlinePlus article ↗- No — darunavir really does need ritonavir to work properly. On its own, your body breaks darunavir down too quickly for it to control HIV. Ritonavir slows that breakdown, which kee...
- Why do I have to take ritonavir with my darunavir — can't I just take darunavir alone?
- Yes, it really does. Taking darunavir tablets with food increases how much the drug gets into your bloodstream by about 40% compared to taking it on an empty stomach. So the instru...
- Does it matter whether I take darunavir with food?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Darunavir — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII LMI26O6933
Alumina is a white powder form of aluminum oxide. It's used as a filler to add bulk to tablets and capsules, and sometimes as a thickening or anti-caking agent in powdered formulations.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII WZB9127XOA
A synthetic red dye used to color medications and make them easier to identify. It serves as a colorant in tablets, capsules, and liquid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII G2M7P15E5P
Polyethylene glycol 3350 is a synthetic polymer used as a solvent, humectant, and thickening agent in medicines. It helps dissolve other ingredients, retain moisture in the product, and achieve the desired consistency.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $2.488 | $74.65 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | $2.86 | $85.88 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $3.22 | $96.52 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Darunavir 800 mg 31722-0089-30 | Camber | 30 tablets | $2.488 | AB | Availability likely | — |
| Darunavir 800 mgthis 43598-0705-30 | Dr.Reddys | 30 tablets | $2.488 | AB | Availability likely | — |
| Darunavir 800 mg 59651-0086-30 | Aurobindo | 30 tablets | $2.488 | AB | Availability likely | — |
| Darunavir 800 mg 60219-1145-03 | Amneal | 30 tablets | $2.488 | AB | Availability likely | — |
| Darunavir 800 mg 60687-0819-21 | American | 30 tablets | $2.488 | AB | Availability likely | — |
| Darunavir 800 mg 68180-0346-06 | Lupin | 30 tablets | $2.488 | AB | Availability likely | — |
| Darunavir 600 and 800 mg 69097-0244-02 | Cipla | 30 tablets | $2.488 | AB | Availability likely | — |
| Darunavir 800 mg 72205-0185-30 | Novadoz | 30 tablets | $2.488 | AB | Availability likely | — |
| darunavir 800 mg 76282-0738-30 | EXELAN | 30 tablets | $2.488 | AB | Availability likely | — |
| Prezista 800 mg 59676-0566-30 | Janssen | 30 tablets | $70.137 | AB | Availability likely | +2719% |
| Darunavir 600 and 800 mg 63629-5686-01 | Bryant | 15 tablets | — | AB | FDA listed | — |
| Darunavir 800 mg 68071-3910-03 | NuCare | 3 tablets | — | AB | FDA listed | — |
| Darunavir 800 mg 70771-1746-03 | Zydus | 30 tablets | — | AB | FDA listed | — |
| Darunavir 800 mg 71335-2611-01 | Bryant | 15 tablets | — | AB | FDA listed | — |
| Darunavir 800 mg 72578-0148-05 | Viona | 500 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 43598-0705-05 | 500 TABLET, FILM COATED in 1 BOTTLE (43598-705-05) | — | — | 2023-11-29 | Active |
| 43598-0705-30 You're viewing this | 30 TABLET, FILM COATED in 1 BOTTLE (43598-705-30) | $2.49 / ea | $74.65 | 2023-11-29 | Active |
You're viewing the smallest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 43598-0705-30?
What is the difference between NDC 43598-0705-30 and NDC 43598-0705-05?
What NDC number is used to bill for this package of Darunavir 800 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Darunavir tablets, co-administered with ritonavir (darunavir/ritonavir), in combination with other antiretroviral agents, are indicated for the treatment of human immunodeficiency virus (HIV-1) infection in adult and pediatric patients 3 years of age and older [see Use in Specific Populations ( 8.4 ) and Clinical Studies ( 14 )]. Darunavir is a human immunodeficiency virus (HIV-1) protease inhibitor indicated for the treatment of HIV-1 infection in adult and pediatric patients 3 years of age and older.
Darunavir tablets must be co-administered with ritonavir (darunavir/ritonavir) and with other antiretroviral agents. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Testing: In treatment-experienced patients, treatment history genotypic and/or phenotypic testing is recommended prior to initiation of therapy with darunavir/ritonavir to assess drug susceptibility of the HIV-1 virus ( 2.1 , 12.4 ) Monitor serum liver chemistry tests before and during therapy with darunavir/ritonavir. ( 2.1 , 2.2 , 5.2 ) • Treatment-naïve adult patients and treatment-experienced adult patients with no darunavir resistance associated substitutions: 800 mg (one 800 mg tablet) taken with ritonavir 100 mg once daily and with food.
( 2.3 ) • Treatment-experienced adult patients with at least one darunavir resistance associated substitution: 600 mg (one 600 mg tablet) taken with ritonavir 100 mg twice daily and with food. ( 2.3 ) • Pregnant patients: 600 mg (one 600 mg tablet) taken with ritonavir 100 mg twice daily and with food. ( 2.4 ) • Pediatric patients (3 to less than 18 years of age and weighing at least 10 kg): dosage of darunavir and ritonavir is based on body weight and should not exceed the adult dose.
Darunavir tablets should be taken with ritonavir and with food. ( 2.5 ) • Darunavir/ritonavir is not recommended for use in patients with severe hepatic impairment. ( 2.6 )
2.1Testing Prior to Initiation of Darunavir/ritonavir In treatment-experienced patients, treatment history, genotypic and/or phenotypic testing is recommended to assess drug susceptibility of the HIV-1 virus [see Microbiology ( 12.4 )] . Refer to Dosage and Administration ( 2.3 ), ( 2.4 ) and ( 2.5 ) for dosing recommendations. Appropriate laboratory testing such as serum liver biochemistries should be conducted prior to initiating therapy with darunavir/ritonavir [see Warnings and Precautions ( 5.2 )].
2.2Monitoring During Treatment with Darunavir/ritonavir Patients with underlying chronic hepatitis, cirrhosis, or in patients who have pre-treatment elevations of transaminases should be monitored for elevation in serum liver biochemistries, especially during the first several months of darunavir/ritonavir treatment [see Warnings and Precautions ( 5.2 )].
2.3Recommended Dosage in Adult Patients Darunavir tablets must be co-administered with ritonavir to exert its therapeutic effect. Failure to correctly co-administer darunavir tablets with ritonavir will result in plasma levels of darunavir that will be insufficient to achieve the desired antiviral effect and will alter some drug interactions. Patients who have difficulty swallowing darunavir tablets can use the 100 mg per mL darunavir oral suspension.
Treatment-Naïve Adult Patients The recommended oral dose of darunavir is 800 mg (one 800 mg tablet or 8 mL of the oral suspension) taken with ritonavir 100 mg (one 100 mg tablet or capsule or 1.25 mL of a 80 mg per mL ritonavir oral solution) once daily and with food. An 8 mL darunavir dose should be taken as two 4 mL administrations with the included oral dosing syringe. Treatment-Experienced Adult Patients The recommended oral dosage for treatment-experienced adult patients is summarized in Table 1.
Baseline genotypic testing is recommended for dose selection. However, when genotypic testing is not feasible, darunavir tablets 600 mg taken with ritonavir 100 mg twice daily is recommended. Table 1: Recommended D arunavir/ritonavir Dosage in Treatment-Experienced Adult Patients Baseline Resistance Formulation and Recommended Dosing Darunavir tablets with ritonavir tablets or capsule Darunavir oral suspension (100 mg/mL ) with ritonavir oral solution (8 0 mg/mL) With no darunavir resistance associated substitutions a One 800 mg darunavir tablet with one 100 mg ritonavir tablet/capsule, taken once daily with food 8 mL b darunavir oral suspension with 1.25 mL ritonavir oral solution, taken once daily with food With at least one darunavir resistance associated substitutions a , or with no baseline resistance information One 600 mg darunavir tablet with one 100 mg ritonavir tablet/capsule, taken twice daily with…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS • 600 mg: White colored, oval shaped, film-coated tablets containing 600 mg of darunavir. Each tablet is debossed with ‘DA600’ on one side and plain on the other side. • 800 mg: Blue colored, oval shaped, film-coated tablets containing 800 mg of darunavir. Each tablet is debossed with ‘DA800’ on one side and plain on the other side. • Tablets: 600 mg, and 800 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Co-administration of darunavir/ritonavir is contraindicated with drugs that are highly dependent on CYP3A for clearance and for which elevated plasma concentrations are associated with serious and/or life-threatening events (narrow therapeutic index). Examples of these drugs and other contraindicated drugs (which may lead to reduced efficacy of darunavir) are listed below [see Drug Interactions ( 7.3 )] . Due to the need for co-administration of darunavir with ritonavir, please refer to ritonavir prescribing information for a description of ritonavir contraindications.
Alpha 1-adrenoreceptor antagonist: alfuzosin Anti-gout: colchicine, in patients with renal and/or hepatic impairment Antimycobacterial: rifampin Antipsychotics: lurasidone, pimozide Cardiac Disorders: dronedarone, ivabradine, ranolazine Ergot derivatives, e.g. dihydroergotamine, ergotamine, methylergonovine Herbal product: St. John’s wort (Hypericum perforatum) Hepatitis C direct acting antiviral: elbasvir/grazoprevir Lipid modifying agents: lomitapide, lovastatin, simvastatin Opioid Antagonist: naloxegol PDE-5 inhibitor: sildenafil when used for treatment of pulmonary arterial hypertension Sedatives/hypnotics: orally administered midazolam, triazolam • Co-administration of darunavir/ritonavir is contraindicated with drugs that are highly dependent on CYP3A for clearance and for which elevated plasma concentrations are associated with serious and/or life-threatening events (narrow therapeutic index).
( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Drug-induced hepatitis (e.g., acute hepatitis, cytolytic hepatitis) has been reported with darunavir/ritonavir. Monitor liver function before and during therapy, especially in patients with underlying chronic hepatitis, cirrhosis, or in patients who have pre-treatment elevations of transaminases. Post-marketing cases of liver injury, including some fatalities, have been reported.
( 5.2 ) • Skin reactions ranging from mild to severe, including Stevens-Johnson Syndrome, toxic epidermal necrolysis, drug rash with eosinophilia and systemic symptoms and acute generalized exanthematous pustulosis, have been reported. Discontinue treatment if severe reaction develops. ( 5.3 ) • Use with caution in patients with a known sulfonamide allergy.
( 5.4 ) • Patients may develop new onset diabetes mellitus or hyperglycemia. Initiation or dose adjustments of insulin or oral hypoglycemic agents may be required. ( 5.6 ) • Patients may develop redistribution/accumulation of body fat or immune reconstitution syndrome.
( 5.7 , 5.8 ) • Patients with hemophilia may develop increased bleeding events. ( 5.9 ) • Darunavir/ritonavir is not recommended in pediatric patients below 3 years of age in view of toxicity and mortality observed in juvenile rats dosed with darunavir up to days 23 to 26 of age. ( 5.10 )
5.1Importance of Co-administration with Ritonavir Darunavir must be co-administered with ritonavir and food to achieve the desired antiviral effect. Failure to administer darunavir with ritonavir and food may result in a loss of efficacy of darunavir. Please refer to ritonavir prescribing information for additional information on precautionary measures.
5.2Hepatotoxicity Drug-induced hepatitis (e.g., acute hepatitis, cytolytic hepatitis) has been reported with darunavir/ritonavir. During the clinical development program (N=3063), hepatitis was reported in 0.5% of patients receiving combination therapy with darunavir/ritonavir. Patients with pre-existing liver dysfunction, including chronic active hepatitis B or C, have an increased risk for liver function abnormalities including severe hepatic adverse events.
Post-marketing cases of liver injury, including some fatalities, have been reported. These have generally occurred in patients with advanced HIV-1 disease taking multiple concomitant medications, having co-morbidities including hepatitis B or C co-infection, and/or developing immune reconstitution syndrome. A causal relationship with darunavir/ritonavir therapy has not been established.
Appropriate laboratory testing should be conducted prior to initiating therapy with darunavir/ritonavir and patients should be monitored during treatment. Increased AST/ALT monitoring should be considered in patients with underlying chronic hepatitis, cirrhosis, or in patients who have pre-treatment elevations of transaminases, especially during the first several months of darunavir/ritonavir treatment. Evidence of new or worsening liver dysfunction (including clinically significant elevation of liver enzymes and/or symptoms such as fatigue, anorexia, nausea, jaundice, dark urine, liver tenderness, hepatomegaly) in patients on darunavir/ritonavir should prompt consideration of interruption or discontinuation of treatment.
5.3Severe Skin Reactions During the clinical development program (n=3063), severe skin reactions, accompanied by fever and/or elevations of transaminases in some cases, have been reported in 0.4% of subjects. Stevens-Johnson Syndrome was rarely (less than 0.1%) reported during the clinical development program. During post-marketing experience toxic epidermal necrolysis, drug rash with eosinophilia and systemic symptoms, and acute generalized exanthematous pustulosis have been reported.
Discontinue darunavir/ritonavir immediately if signs or symptoms of severe skin reactions develop. These can include but are not limited to severe rash or rash accompanied with fever, general malaise, fatigue, muscle or joint aches…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in other sections of labeling: • Hepatotoxicity [see Warnings and Precautions ( 5.2 )] • Severe Skin Reactions [see Warnings and Precautions ( 5.3 )] • Diabetes Mellitus/Hyperglycemia [see Warnings and Precautions ( 5.6 )] • Fat Redistribution [see Warnings and Precautions ( 5.7 )] • Immune Reconstitution Syndrome [see Warnings and Precautions ( 5.8 )] • Hemophilia [see Warnings and Precautions ( 5.9 )] Due to the need for co-administration of darunavir with ritonavir, please refer to ritonavir prescribing information for ritonavir-associated adverse reactions. • The most common clinical adverse drug reactions to darunavir/ritonavir (incidence greater than or equal to 5%) of at least moderate intensity (greater than or equal to Grade 2) were diarrhea, nausea, rash, headache, abdominal pain and vomiting.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Dr. Reddy’s Laboratories, Inc. at 1-888-375-3784 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Treatment Naïve-Adults: TMC114-C211 The safety assessment is based on all safety data from the Phase 3 trial TMC114-C211 comparing darunavir/ritonavir 800/100 mg once daily versus lopinavir/ritonavir 800/200 mg per day in 689 antiretroviral treatment-naïve HIV-1-infected adult subjects.
The total mean exposure for subjects in the darunavir/ritonavir 800/100 mg once daily arm and in the lopinavir/ritonavir 800/200 mg per day arm was 162.5 and 153.5 weeks, respectively. The majority of the adverse drug reactions (ADRs) reported during treatment with darunavir /ritonavir 800/100 mg once daily were mild in severity. The most common clinical ADRs to darunavir/ritonavir 800/100 mg once daily (greater than or equal to 5%) of at least moderate intensity (greater than or equal to Grade 2) were diarrhea, headache, abdominal pain and rash.
2.3% of subjects in the darunavir/ritonavir arm discontinued treatment due to ADRs. ADRs to darunavir/ritonavir 800/100 mg once daily of at least moderate intensity (greater than or equal to Grade 2) in antiretroviral treatment-naïve HIV-1-infected adult subjects are presented in Table 6 and subsequent text below the table. Table 6: Selected Clinical Adverse Drug Reactions to Darunavir/ritonavir 800/100 mg Once Daily a of at Least Moderate Intensity (≥Grade 2) Occurring in ≥2% of Antiretroviral Treatment-Naïve HIV-1-Infected Adult Subjects (Trial TMC114-C211) System organ class, preferred term, % Darunavir/ritonavir 800/100 mg once daily + TDF/FTC N=343 lopinavir/ritonavir 800/200 mg per day + TDF/FTC N=346 Gastrointestinal Disorders Abdominal pain 6% 6% Diarrhea 9% 16% Nausea 4% 4% Vomiting 2% 4% General Disorders and Administration Site Conditions Fatigue <1% 3% Metabolism and Nutrition Disorders Anorexia 2% <1% Nervous System Disorders Headache 7% 6% Skin and Subcutaneous Tissue Disorders Rash 6% 7% N=total number of subjects per treatment group; FTC=emtricitabine; TDF=tenofovir disoproxil fumarate a Excluding laboratory abnormalities reported as ADRs.
Less Common Adverse Reactions Treatment-emergent ADRs of at least moderate intensity (greater than or equal to Grade 2) occurring in less than 2% of antiretroviral treatment-naïve subjects receiving darunavir/ritonavir 800/100 mg once daily are listed below by body system: Gastrointestinal Disorders : acute pancreatitis, dyspepsia, flatulence General Disorders and Administration Site Conditions : asthenia Hepatobiliary Disorders : acute hepatitis (e.g., acute hepatitis, cytolytic hepatitis, hepatotoxicity) Immune System Disorders : (drug) hypersensitivity, immune reconstitution syndrome Metabolism and Nutrition Disorders : diabetes mellitus…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Co-administration of darunavir/ritonavir with other drugs can alter the concentrations of other drugs and other drugs may alter the concentrations of darunavir. The potential drug-drug interactions must be considered prior to and during therapy. ( 4 , 5.5 , 7 , 12.3 )
7.1Potential for Darunavir/ritonavir to Affect Other Drugs Darunavir co-administered with ritonavir is an inhibitor of CYP3A, CYP2D6, and P-gp. Co-administration of darunavir and ritonavir with drugs that are primarily metabolized by CYP3A and CYP2D6 or are transported by P-gp may result in increased plasma concentrations of such drugs, which could increase or prolong their therapeutic effect and adverse events. Darunavir co-administered with ritonavir with drugs that have active metabolite(s) formed by CYP3A may result in reduced plasma concentrations of these active metabolite(s), potentially leading to loss of their therapeutic effect (see Table 10).
7.2Potential for Other Drugs to Affect Darunavir Darunavir and ritonavir are metabolized by CYP3A. In vitro data indicate that darunavir may be a P-gp substrate. Drugs that induce CYP3A activity would be expected to increase the clearance of darunavir and ritonavir, resulting in lowered plasma concentrations of darunavir and ritonavir.
Co-administration of darunavir and ritonavir and other drugs that inhibit CYP3A, or P-gp may decrease the clearance of darunavir and ritonavir and may result in increased plasma concentrations of darunavir and ritonavir (see Table 10).
7.3Established and Other Potentially Significant Drug Interactions Table 10 provides dosing recommendations as a result of drug interactions with darunavir/ritonavir. These recommendations are based on either drug interaction studies or predicted interactions due to the expected magnitude of interaction and potential for serious adverse events or loss of efficacy. The table includes examples of potentially significant interactions but is not all inclusive [see Contraindications ( 4 ) and Clinical Pharmacology ( 12.3 )], and therefore the label of each drug that is co-administered with darunavir/ritonavir should be consulted for information related to the route of metabolism, interaction pathways, potential risks, and specific actions to be taken with regard to co-administration .
Table 10: Established and Other Potentially Significant Drug Interactions: Alterations in Dose or Regimen May be Recommended Based on Drug Interaction Studies or Predicted Interaction ( see Contraindications ( 4 ) for a list of examples of contraindicated drugs ) [ see Clinical Pharmacology ( 12.3 ) for Magnitude of Interaction, Tables 15 and 16] Concomitant Drug Class Drug Name Examples Effect on Concentration of Darunavir Or Concomitant Drug Clinical Comment HIV-1-Antiviral Agents: Nucleoside Reverse Transcriptase Inhibitors (NRTIs) didanosine ↔ darunavir ↔ didanosine Didanosine should be administered one hour before or two hours after darunavir/ritonavir (which are administered with food).
HIV-1-Antiviral Agents: HIV-Protease Inhibitors (PIs) indinavir (The reference regimen for indinavir was indinavir/ritonavir 800/100 mg twice daily.) lopinavir/ritonavir saquinavir Other HIV protease inhibitors, except atazanavir [see Drug Interactions (7.4)] ↑ darunavir ↑ indinavir ↓ darunavir ↔ lopinavir ↓ darunavir ↔ saquinavir The appropriate dose of indinavir in combination with darunavir/ritonavir has not been established. Appropriate doses of the combination have not been established. Hence, it is not recommended to co-administer lopinavir/ritonavir and darunavir, with or without ritonavir.
Appropriate doses of the combination have not been established. Hence, it is not recommended to co-administer saquinavir and darunavir, with or without ritonavir. As co-administration with darunavir/ritonavir has not been studied, co-administration is not recommended.
HIV-1-Antiviral Agents: CCR5 co-receptor antagonists maraviroc ↑ maraviroc When used in combination wit…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Pregnancy: Total darunavir exposures were generally lower during pregnancy compared to postpartum period. The reduction in darunavir exposures during pregnancy were greater for once daily dosing compared to the twice daily dosing regimen. ( 8.1 , 12.3 ) • Lactation: Women infected with HIV should be instructed not to breastfeed due to the potential for HIV transmission.
( 8.2 ) • Pediatrics: Not recommended for patients less than 3 years of age. ( 8.4 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to darunavir during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) 1-800-258-4263. Risk Summary Prospective pregnancy data from the APR are not sufficient to adequately assess the risk of birth defects or miscarriage.
Available limited data from the APR show no statistically significant difference in the overall risk of major birth defects for darunavir compared with the background rate for major birth defects of 2.7% in a U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP) [see Data] . The rate of miscarriage is not reported in the APR. The estimated background rate of miscarriage in clinically recognized pregnancies in the U.S. general population is 15 to 20%.
The background risk of major birth defects and miscarriage for the indicated population is unknown. Studies in animals did not show evidence of developmental toxicity. Exposures (based on AUC) in rats were 3-fold higher, whereas in mice and rabbits, exposures were lower (less than 1-fold) than human exposures at the recommended daily dose [see Data] .
Clinical Considerations The recommended dosage in pregnant patients is darunavir 600 mg taken with ritonavir 100 mg twice daily with food. Darunavir 800 mg taken with ritonavir 100 mg once daily should only be considered in certain pregnant patients who are already on a stable darunavir 800 mg with ritonavir 100 mg once daily regimen prior to pregnancy, are virologically suppressed (HIV-1 RNA less than 50 copies per mL), and in whom a change to twice daily darunavir 600 mg with ritonavir 100 mg may compromise tolerability or compliance [see Dosage and Administration ( 2.4 ) and Clinical Pharmacology ( 12.3 )].
Data Human Data Darunavir/ritonavir (600/100 mg twice daily or 800/100 mg once daily) in combination with a background regimen was evaluated in a clinical trial of 36 pregnant women during the second and third trimesters, and postpartum. Eighteen subjects were enrolled in each BID and QD treatment arms. Twenty-nine subjects completed the trial through the postpartum period (6 to 12 weeks after delivery) and 7 subjects discontinued before trial completion, 5 subjects in the BID arm and 2 subjects in the QD arm.
The pharmacokinetic data demonstrate that exposure to darunavir and ritonavir as part of an antiretroviral regimen was lower during pregnancy compared with postpartum (6 to 12 weeks). Exposure reductions during pregnancy were greater for the once daily regimen as compared to the twice daily regimen [see Clinical Pharmacology ( 12.3 )] . Virologic response was preserved.
In the BID arm, the proportion of subjects with HIV-1 RNA <50 copies/mL were 39% (7/18) at baseline, 61% (11/18) through the third trimester visit, and 61% (11/18) through the 6 to 12 week postpartum visit. Virologic outcomes during the third trimester visit showed HIV-1 RNA ≥50 copies/mL for 11% (2/18) of subjects and were missing for 5 subjects (1 subject discontinued prematurely due to virologic failure). In the QD arm, the proportion of subjects with HIV-1 RNA <50 copies/mL were 61% (11/18) at baseline, 83% (15/18) through the third trimester visit, and 78% (14/18) through the 6 to 12 week postpartum visit.
Virologic outcomes during the third trimester visit showed HIV-1 RNA ≥50 copies/mL for none of the subjects and wer…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to darunavir during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) 1-800-258-4263. Risk Summary Prospective pregnancy data from the APR are not sufficient to adequately assess the risk of birth defects or miscarriage.
Available limited data from the APR show no statistically significant difference in the overall risk of major birth defects for darunavir compared with the background rate for major birth defects of 2.7% in a U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP) [see Data] . The rate of miscarriage is not reported in the APR. The estimated background rate of miscarriage in clinically recognized pregnancies in the U.S. general population is 15 to 20%.
The background risk of major birth defects and miscarriage for the indicated population is unknown. Studies in animals did not show evidence of developmental toxicity. Exposures (based on AUC) in rats were 3-fold higher, whereas in mice and rabbits, exposures were lower (less than 1-fold) than human exposures at the recommended daily dose [see Data] .
Clinical Considerations The recommended dosage in pregnant patients is darunavir 600 mg taken with ritonavir 100 mg twice daily with food. Darunavir 800 mg taken with ritonavir 100 mg once daily should only be considered in certain pregnant patients who are already on a stable darunavir 800 mg with ritonavir 100 mg once daily regimen prior to pregnancy, are virologically suppressed (HIV-1 RNA less than 50 copies per mL), and in whom a change to twice daily darunavir 600 mg with ritonavir 100 mg may compromise tolerability or compliance [see Dosage and Administration ( 2.4 ) and Clinical Pharmacology ( 12.3 )].
Data Human Data Darunavir/ritonavir (600/100 mg twice daily or 800/100 mg once daily) in combination with a background regimen was evaluated in a clinical trial of 36 pregnant women during the second and third trimesters, and postpartum. Eighteen subjects were enrolled in each BID and QD treatment arms. Twenty-nine subjects completed the trial through the postpartum period (6 to 12 weeks after delivery) and 7 subjects discontinued before trial completion, 5 subjects in the BID arm and 2 subjects in the QD arm.
The pharmacokinetic data demonstrate that exposure to darunavir and ritonavir as part of an antiretroviral regimen was lower during pregnancy compared with postpartum (6 to 12 weeks). Exposure reductions during pregnancy were greater for the once daily regimen as compared to the twice daily regimen [see Clinical Pharmacology ( 12.3 )] . Virologic response was preserved.
In the BID arm, the proportion of subjects with HIV-1 RNA <50 copies/mL were 39% (7/18) at baseline, 61% (11/18) through the third trimester visit, and 61% (11/18) through the 6 to 12 week postpartum visit. Virologic outcomes during the third trimester visit showed HIV-1 RNA ≥50 copies/mL for 11% (2/18) of subjects and were missing for 5 subjects (1 subject discontinued prematurely due to virologic failure). In the QD arm, the proportion of subjects with HIV-1 RNA <50 copies/mL were 61% (11/18) at baseline, 83% (15/18) through the third trimester visit, and 78% (14/18) through the 6 to 12 week postpartum visit.
Virologic outcomes during the third trimester visit showed HIV-1 RNA ≥50 copies/mL for none of the subjects and were missing for 3 subjects (1 subject discontinued prematurely due to virologic failure). Darunavir/ritonavir was well tolerated during pregnancy and postpartum. There were no new clinically relevant safety findings compared with the known safety profile of darunavir/ritonavir in HIV-1-infected adults.
Among the 31 infants with HIV test results available data, born to the 31 HIV-infected pregnant women who completed trial through delivery or postpartum period, all 31 infants had test re…
🧒 Pediatric Use ▾
8.4Pediatric Use Darunavir/ritonavir is not recommended in pediatric patients below 3 years of age because of toxicity and mortality observed in juvenile rats dosed with darunavir (from 20 mg/kg to 1,000 mg/kg) up to days 23 to 26 of age [see Warnings and Precautions ( 5.10 ), Use in Specific Populations ( 8.1 ) and Clinical Pharmacology ( 12.3 )]. The safety, pharmacokinetic profile, and virologic and immunologic responses of darunavir/ritonavir administered twice daily were evaluated in treatment-experienced HIV-1-infected pediatric subjects 3 to less than 18 years of age and weighing at least 10 kg.
These subjects were evaluated in clinical trials TMC114-C212 (80 subjects, 6 to less than 18 years of age) and TMC114-228 (21 subjects, 3 to less than 6 years of age) [see Adverse Reactions ( 6.1 ), Clinical Pharmacology ( 12.3 ) and Clinical Studies ( 14.4 )] . Frequency, type, and severity of adverse drug reactions in pediatric subjects were comparable to those observed in adults [see Adverse Reactions ( 6.1 )] . Refer to Dosage and Administration ( 2.5 ) for twice-daily dosing recommendations for pediatric subjects 3 to less than 18 years of age and weighing at least 10 kg.
In clinical trial TMC114-C230, the safety, pharmacokinetic profile and virologic and immunologic responses of darunavir/ritonavir administered once daily were evaluated in treatment-naïve HIV-1 infected pediatric subjects 12 to less than 18 years of age (12 subjects) [see Adverse Reactions ( 6.1 ), Clinical Pharmacology ( 12.3 ) and Clinical Studies ( 14.4 )] . Frequency, type, and severity of adverse drug reactions in pediatric subjects were comparable to those observed in adults [see Adverse Reactions ( 6.1 )] . Once daily dosing recommendations for pediatric patients 3 to less than 12 years of age were derived using population pharmacokinetic modeling and simulation.
Although a darunavir/ritonavir once daily dosing pediatric trial was not conducted in children less than 12 years of age, there is sufficient clinical safety data to support the predicted darunavir exposures for the dosing recommendations in this age group [see Clinical Pharmacology ( 12.3 )] . Please see Dosage and Administration ( 2.5 ) for once-daily dosing recommendations for pediatric subjects 3 to less than 18 years of age and weighing at least 10 kg. Juvenile Animal Data In a juvenile toxicity study where rats were directly dosed with darunavir (up to 1,000 mg/kg), deaths occurred from post-natal day 5 at plasma exposure levels ranging from 0.1 to 1 of the human exposure levels.
In a 4-week rat toxicology study, when dosing was initiated on post-natal day 23 (the human equivalent of 2 to 3 years of age), no deaths were observed with a plasma exposure (in combination with ritonavir) 2 times the human plasma exposure levels.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of darunavir did not include sufficient numbers of patients aged 65 years and over to determine whether they respond differently from younger patients. In general, caution should be exercised in the administration and monitoring of darunavir in elderly patients, reflecting the greater frequency of decreased hepatic function, and of concomitant disease or other drug therapy [see Clinical Pharmacology ( 12.3 )].
🆘 Overdosage ▾
10 OVERDOSAGE Human experience of acute overdose with darunavir/ritonavir is limited. No specific antidote is available for overdose with darunavir. Treatment of overdose with darunavir consists of general supportive measures including monitoring of vital signs and observation of the clinical status of the patient. Since darunavir is highly protein bound, dialysis is unlikely to be beneficial in significant removal of the active substance.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Darunavir is an HIV-1 antiviral drug [see Microbiology ( 12.4 )].
12.2Pharmacodynamics Cardiac Electrophysiology In a thorough QT/QTc study in 40 healthy subjects, darunavir/ritonavir doses of 1.33 times the maximum recommended dose did not affect the QT/QTc interval.
12.3Pharmacokinetics Pharmacokinetics in Adults General Darunavir is primarily metabolized by CYP3A. Ritonavir inhibits CYP3A, thereby increasing the plasma concentrations of darunavir. When a single dose of darunavir 600 mg was given orally in combination with 100 mg ritonavir twice daily, there was an approximate 14-fold increase in the systemic exposure of darunavir.
Therefore, darunavir should only be used in combination with 100 mg of ritonavir to achieve sufficient exposures of darunavir. The pharmacokinetics of darunavir, co-administered with low dose ritonavir (100 mg), has been evaluated in healthy adult volunteers and in HIV-1-infected subjects. Table 11 displays the population pharmacokinetic estimates of darunavir after oral administration of darunavir/ritonavir 600/100 mg twice daily (based on sparse sampling in 285 patients in trial TMC114-C214, 278 patients in trial TMC114-C229 and 119 patients [integrated data] from trials TMC114-C202 and TMC114-C213) and darunavir/ritonavir 800/100 mg once daily (based on sparse sampling in 335 patients in trial TMC114-C211 and 280 patients in trial TMC114-C229) to HIV-1-infected patients.
Table 11: Population Pharmacokinetic Estimates of Darunavir at Darunavir/ritonavir 800/100 mg Once Daily (Trial TMC114-C211, 48-Week Analysis and Trial TMC114-C229, 48-Week Analysis) and Darunavir/ritonavir 600/100 mg Twice Daily (Trial TMC114-C214, 48-Week Analysis, Trial TMC114-C229, 48-Week Analysis and Integrated Data from Trials TMC114-C213 and TMC114-C202, Primary 24-Week Analysis) Parameter Darunavir/ritonavir 800/100 mg once daily Darunavir/ritonavir 600/100 mg twice daily TMC114-C211 N=335 TMC114-C229 N=280 TMC114-C214 N=285 TMC114-C229 N=278 TMC114-C213 + TMC114-C202 (integrated data) N=119 AUC 24h (ng.h/mL) a Mean ± Standard Deviation 93026 ± 27050 93334 ± 28626 116796 ± 33594 114302 ± 32681 124698 ± 32286 Median (Range) 87854 (45000 to 219240) 87788 (45456 to 236920) 111632 (64874 to 355360) 109401 (48934 to 323820) 123336 (67714 to 212980) C 0h (ng/mL) Mean ± Standard Deviation 2282 ± 1168 2160 ± 1201 3490 ± 1401 3386 ± 1372 3578 ± 1151 Median (Range) 2041 (368 to 7242) 1896 (184 to 7881) 3307 (1517 to 13198) 3197 (250 to 11865) 3539 (1255 to 7368) N=number of subjects with data a AUC 24h is calculated as AUC 12h * 2.
Absorption and Bioavailability Darunavir, co-administered with 100 mg ritonavir twice daily, was absorbed following oral administration with a T max of approximately 2.5 to 4 hours. The absolute oral bioavailability of a single 600 mg dose of darunavir alone and after co-administration with 100 mg ritonavir twice daily was 37% and 82%, respectively. In vivo data suggest that darunavir/ritonavir is an inhibitor of the P-glycoprotein (P-gp) transporters.
Effects of Food on Oral Absorption When darunavir tablets were administered with food, the C max and AUC of darunavir, co-administered with ritonavir, is approximately 40% higher relative to the fasting state. Within the range of meals studied, darunavir exposure is similar. The total caloric content of the various meals evaluated ranged from 240 Kcal (12 grams fat) to 928 Kcal (56 grams fat).
Distribution Darunavir is approximately 95% bound to plasma proteins. Darunavir binds primarily to plasma alpha 1-acid glycoprotein (AAG). Metabolism In vitro experiments with human liver microsomes (HLMs) indicate that darunavir primarily undergoes oxidative metabolism.
Darunavir is extensively metabolized by CYP enzymes, primarily by CYP3A. A mass balance study in healthy volunteers showed that after a single dose administration of 400 mg 14 C-darunavir, co-administered with 100 mg ritonavir, the majority of th…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Darunavir is an HIV-1 antiviral drug [see Microbiology ( 12.4 )].
📦 How Supplied / Storage and Handling ▾
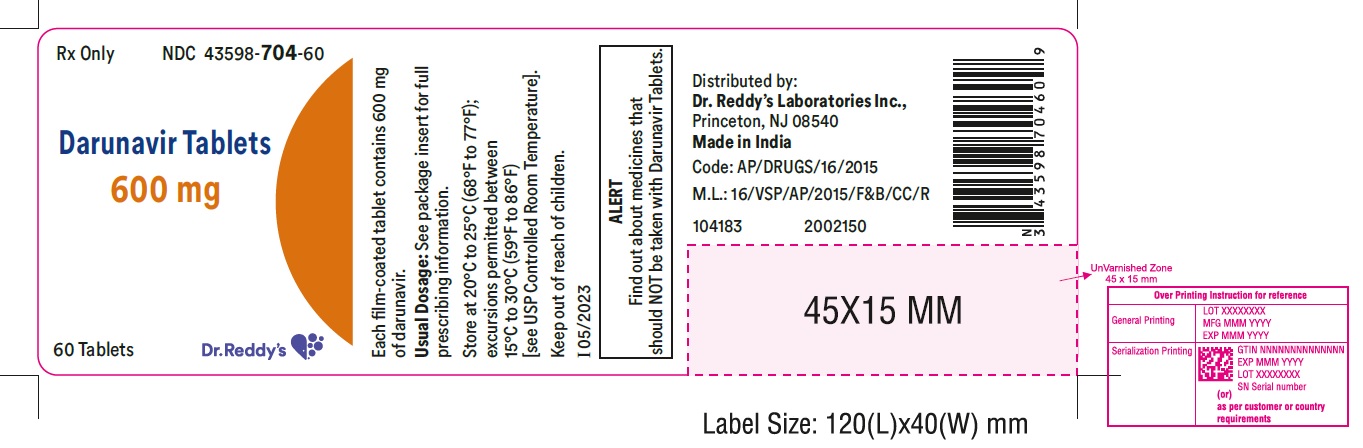
16 HOW SUPPLIED/STORAGE AND HANDLING Darunavir 600 mg tablets are supplied as white colored, oval shaped, film-coated tablets containing 600 mg of darunavir per tablet. Each tablet is debossed with ‘DA600’ on one side and plain on the other side. Bottle of 60 tablets NDC 43598-704-60 Bottle of 500 tablets NDC 43598-704-05 Darunavir 800 mg tablets are supplied as blue colored, oval shaped, film-coated tablets containing 800 mg of darunavir per tablet.
Each tablet is debossed with ‘DA800’ on one side and plain on the other side. Bottle of 30 tablets NDC 43598-705-30 Bottle of 500 tablets NDC 43598-705-05 Storage • Store a t 20°C to 25°C (68°F to 77°F); excursions permitted between 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Keep darunavir tablets out of reach of children.
📋 Description ▾
11 DESCRIPTION Darunavir is an inhibitor of the human immunodeficiency virus (HIV-1) protease. Darunavir tablets contain the active ingredient darunavir, which has the following chemical name: (3R, 3aS, 6aR)-hexahydrofuro [2,3-b]furan-3-yl(1S,2R)-3-[[(4-aminophenyl)sulfonyl](2-methylpropylamino]-1-benzyl-2-hydroxy propyl]carbamate). Its molecular formula is C 27 H 37 N 3 O 7 S and its molecular weight is 547.68.
Darunavir has the following structural formula: Darunavir is a white to pale yellow color solid with a solubility of approximately 0.08 mg per mL in water at ~37°C. It is freely soluble in dichloromethane and very slightly soluble in ethyl alcohol absolute. Darunavir 600 mg tablets are available as white colored, oval shaped, film-coated tablets for oral administration.
Each tablet contains 600 mg of darunavir. Darunavir 800 mg tablets are available as blue colored, oval shaped, film-coated tablets for oral administration. Each tablet contains 800 mg of darunavir.
Each tablet also contains the inactive ingredients colloidal silicon dioxide (colloidal anhydrous silica), croscarmellose sodium, magnesium stearate, and microcrystalline cellulose. The 600 mg tablet film coating, OPADRY® II White, contains polyethylene glycol 3350, polyvinyl alcohol-partially hydrolyzed, talc, and titanium dioxide. The 800 mg tablet film coating, OPADRY® II Blue, contains FD&C Blue No.
1/Brilliant Blue FCF Aluminium Lake, FD&C Blue No. 2/Indigo Caramine Aluminium Lake, FD&C Red No. 40/Alura Red AC Aluminium Lake, polyethylene glycol 3350, polyvinyl alcohol-partially hydrolyzed, talc, and titanium dioxide.
All strengths for darunavir are expressed in terms of the free form of darunavir.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Instructions for Use Advise patients to take darunavir and ritonavir with food every day on a regular dosing schedule, as missed doses can result in development of resistance. Darunavir must always be used with ritonavir in combination with other antiretroviral drugs.
Advise patients not to alter the dose of either darunavir or ritonavir, discontinue ritonavir, or discontinue therapy with darunavir without consulting their physician [see Dosage and Administration ( 2 )]. Hepatotoxicity Inform patients that drug-induced hepatitis (e.g., acute hepatitis, cytolytic hepatitis) has been reported with darunavir co-administered with 100 mg of ritonavir. Advise patients about the signs and symptoms of liver problems [see Warnings and Precautions ( 5.2 )] .
Severe Skin Reactions Inform patients that skin reactions ranging from mild to severe, including Stevens-Johnson Syndrome, drug rash with eosinophilia and systemic symptoms, and toxic epidermal necrolysis, have been reported with darunavir co-administered with 100 mg of ritonavir. Advise patients to discontinue darunavir/ritonavir immediately if signs or symptoms of severe skin reactions develop. These can include but are not limited to severe rash or rash accompanied with fever, general malaise, fatigue, muscle or joint aches, blisters, oral lesions, conjunctivitis, hepatitis and/or eosinophilia [see Warnings and Precautions ( 5.3 )] .
Drug Interactions Darunavir/ritonavir may interact with many drugs; therefore, advise patients to report to their healthcare provider the use of any other prescription or nonprescription medication or herbal products, including St. John’s wort [see Contraindications ( 4 ), Warnings and Precautions ( 5.4 , 5.5 ) and Drug Interactions ( 7 )]. Contraception Instruct patients receiving combined hormonal contraception or the progestin only pill to use an effective alternative (non-hormonal) contraceptive method or add a barrier method during therapy with darunavir/ritonavir because hormonal levels may decrease [see Drug Interactions ( 7.3 ) and Use in Specific Populations ( 8.3 )] .
Fat Redistribution Inform patients that redistribution or accumulation of body fat may occur in patients receiving antiretroviral therapy, including darunavir/ritonavir, and that the cause and long-term health effects of these conditions are not known at this time [see Warnings and Precautions ( 5.7 )]. Immune Reconstitution Syndrome Advise patients to inform their healthcare provider immediately of any symptoms of infection, as in some patients with advanced HIV infection (AIDS), signs and symptoms of inflammation from previous infections may occur soon after anti-HIV treatment is started [see Warnings and Precautions ( 5.8 )].
Pregnancy Registry Inform patients that there is an antiretroviral pregnancy registry to monitor fetal outcomes of pregnant women exposed to darunavir [see Use in Specific Populations ( 8.1 )] . Lactation Instruct women with HIV-1 infection not to breastfeed because HIV-1 can be passed to the baby in breast milk [see Use in Specific Populations ( 8.2 )] . Rx only Distributed by: Dr.
Reddy’s Laboratories Inc., Princeton, NJ 08540 Made in India Issued: 05/2023