
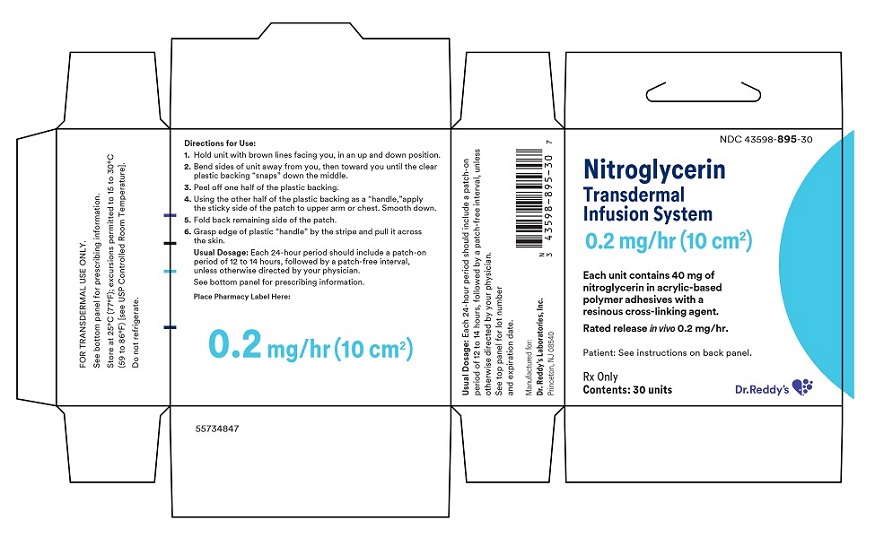
Nitroglycerin Transdermal Infusion System 40 mg Patch, 30 patches
Other active recalls for Nitroglycerin (different manufacturers) — 3 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Nitrate Vasodilator class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Nitroglycerin transdermal patches are used to prevent episodes of angina (chest pain) in people who have coronary artery disease (narrowing of the blood vessels that supply blood to the heart). Nitroglycerin transdermal patches can only be used to prevent attacks of angina; they cannot be used to treat an attack of angina once it has begun. Nitroglycerin is in a class of medications called vasodilators. It works by relaxing the blood vessels so that the heart does not need to work as hard and therefore does not need as much oxygen.
Read the full MedlinePlus article ↗- No — the nitroglycerin patch works too slowly for that. It's designed to prevent angina from happening in the first place, not to stop an attack once it starts. You should still ha...
- Can I use this patch to stop chest pain that's already started?
- Yes, the nightly break is essential. Wearing the patch around the clock causes your body to stop responding to it — this is called tolerance — and the patch can completely lose its...
- Do I really have to take the patch off every night? What happens if I just leave it on?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Nitroglycerin — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.601 | $18.03 / 30 patch |
| Medicaid paysCMS SDUD · 12 mo | $0.8983 | $26.95 / 30 patch |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Nitroglycerin .2 mg/h 00378-9104-93 | Mylan | 30 patches | $0.601 | AB2 | Availability likely | — |
| Nitroglycerin Transdermal Infusion System 40 mgthis 43598-0895-30 | Dr. | 30 patches | $0.601 | — | Availability likely | — |
| Nitro-Dur 40 mg 50742-0514-30 | Ingenus | 30 patches | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 43598-0895-30 You're viewing this | 30 POUCH in 1 BOX, UNIT-DOSE (43598-895-30) / 1 PATCH in 1 POUCH | 2020-03-01 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
You must consult your doctor for important information before using this drug.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Transdermal nitroglycerin is indicated for the prevention of angina pectoris due to coronary artery disease. The onset of action of transdermal nitroglycerin is not sufficiently rapid for this product to be useful in aborting an acute attack.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The suggested starting dose is between 0.2 mg/hr* and 0.4 mg/hr*. Doses between 0.4 mg/hr* and 0.8 mg/hr* have shown continued effectiveness for 10 to 12 hours daily for at least 1 month (the longest period studied) of intermittent administration. Although the minimum nitrate-free interval has not been defined, data show that a nitrate-free interval of 10 to 12 hours is sufficient (see CLINICAL PHARMACOLOGY ).
Thus, an appropriate dosing schedule for nitroglycerin patches would include a daily patch-on period of 12 to 14 hours and a daily patch-off period of 10 to 12 hours. *Release rates were formerly described in terms of drug delivered per 24 hours. In these terms, the supplied nitroglycerin transdermal system would be rated at 2.5 mg/24 hours (0.1 mg/hour), 5 mg/24 hours (0.2 mg/hour), 7.5 mg/24 hours (0.3 mg/hour), 10 mg/24 hours (0.4 mg/hour), and 15 mg/24 hours (0.6 mg/hour). Although some well-controlled clinical trials using exercise tolerance testing have shown maintenance of effectiveness when patches are worn continuously, the large majority of such controlled trials have shown the development of tolerance (ie, complete loss of effect) within the first 24 hours after therapy was initiated.
Dose adjustment, even to levels much higher than generally used, did not restore efficacy.
⛔ Contraindications ▾
CONTRAINDICATIONS Nitroglycerin is contraindicated in patients who are allergic to it. Allergy to the adhesives used in nitroglycerin patches has also been reported, and it similarly constitutes a contraindication to the use of this product. Do not use nitroglycerin transdermal infusion system in patients who are taking phosphodiesterase inhibitors (such as sildenafil, tadalafil, or vardenafil) for erectile dysfunction or pulmonary arterial hypertension.
Concomitant use can cause severe drops in blood pressure. Do not use nitroglycerin transdermal infusion system in patients who are taking the soluble guanylate cyclase stimulator riociguat. Concomitant use can cause hypotension.
⚠️ Warnings ▾
WARNINGS Amplification of the vasodilatory effects of the nitroglycerin transdermal infusion system patch by phosphodiesterase inhibitors, eg, sildenafil can result in severe hypotension. The time course and dose dependence of this inter action have not been studied. Appropriate supportive care has not been studied, but it seems reasonable to treat this as a nitrate overdose, with elevation of the extremities and with central volume expansion.
The benefits of transdermal nitroglycerin in patients with acute myocardial infarction or congestive heart failure have not been established. If one elects to use nitroglycerin in these conditions, careful clinical or hemodynamic monitoring must be used to avoid the hazards of hypotension and tachycardia. A cardioverter/defibrillator should not be discharged through a paddle electrode that overlies a nitroglycerin patch.
The arcing that may be seen in this situation is harmless in itself, but it may be associated with local current concentration that can cause damage to the paddles and burns to the patient.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Adverse reactions to nitroglycerin are generally dose related, and almost all of these reactions are the result of nitroglycerin's activity as a vasodilator. Headache, which may be severe, is the most commonly reported side effect. Headache may be recurrent with each daily dose, especially at higher doses.
Transient episodes of lightheadedness, occasionally related to blood pressure changes, may also occur. Hypotension occurs infrequently, but in some patients it may be severe enough to warrant discontinuation of therapy. Syncope, crescendo angina, and rebound hypertension have been reported but are uncommon.
Allergic reactions to nitroglycerin are also uncommon, and the great majority of those reported have been cases of contact dermatitis or fixed drug eruptions in patients receiving nitroglycerin in ointments or patches. There have been a few reports of genuine anaphylactoid reactions, and these reactions can probably occur in patients receiving nitroglycerin by any route. Extremely rarely, ordinary doses of organic nitrates have caused methemoglobinemia in normal-seeming patients.
Methemoglobinemia is so infrequent at these doses that further discussion of its diagnosis and treatment is deferred (see OVERDOSAGE ). Application-site irritation may occur but is rarely severe. In two placebo-controlled trials of intermittent therapy with nitroglycerin patches at 0.2 to 0.8 mg/hr, the most frequent adverse reactions among 307 subjects were as follows: Placebo Patch Headache 18% 63% Lightheadedness 4% 6% Hypotension, and/or Syncope 0% 4% Increased Angina 2% 2% To report SUSPECTED ADVERSE REACTIONS, contact USpharma Ltd at 1(844)-750-3729 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug Interactions ▾
Drug Interactions: The vasodilating effects of nitroglycerin may be additive with those of other vasodilators. Alcohol, in particular, has been found to exhibit additive effects of this variety. Concomitant use of nitroglycerin transdermal infusion system with phosphodiesterase inhibitors in any form is contraindicated (see CONTRAINDICATIONS ).
Concomitant use of nitroglycerin transdermal infusion system with riociguat, a soluble guanylate cyclase stimulator, is contraindicated (see CONTRAINDICATIONS ).
🤰 Pregnancy ▾
Pregnancy: Pregnancy Category C: Animal teratology studies have not been conducted with nitroglycerin transdermal systems. Teratology studies in rats and rabbits, however, were conducted with topically applied nitroglycerin ointment at doses up to 80 mg/kg/day and 240 mg/kg/day, respectively. No toxic effects on dams or fetuses were seen at any dose tested.
There are no adequate and well-controlled studies in pregnant women. Nitroglycerin should be given to a pregnant woman only if clearly needed.
🧒 Pediatric Use ▾
Pediatric Use: Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
Geriatric Use: Clinical studies of nitroglycerin transdermal infusion systemm did not include sufficient information to determine whether subjects 65 years and older respond differently from younger subjects. Additional clinical data from the published literature indicate that the elderly demonstrate increased sensitivity to nitrates, which may result in hypotension and increased risk of falling. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of the decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
OVERDOSAGE Hemodynamic Effects: Nitroglycerin toxicity is generally mild. The estimated adult oral lethal dose of nitroglycerin is 200 mg to 1,200 mg. Infants may be more susceptible to toxicity from nitroglycerin.
Consultation with a poison center should be considered. Laboratory determinations of serum levels of nitroglycerin and its metabolites are not widely available, and such determinations have, in any event, no established role in the management of nitroglycerin overdose. No data are available to suggest physiological maneuvers (eg, maneuvers to change the pH of the urine) that might accelerate elimination of nitroglycerin and its active metabolites.
Similarly, it is not known which – if any – of these substances can usefully be removed from the body by hemodialysis. No specific antagonist to the vasodilator effects of nitroglycerin is known, and no intervention has been subject to controlled study as a therapy of nitroglycerin overdose. Because the hypotension associated with nitroglycerin overdose is the result of venodilatation and arterial hypovolemia, prudent therapy in this situation should be directed toward increase in central fluid volume.
Passive elevation of the patient’s legs may be sufficient, but intravenous infusion of normal saline or similar fluid may also be necessary. The use of epinephrine or other arterial vasoconstrictors in this setting is likely to do more harm than good. In patients with renal disease or congestive heart failure, therapy resulting in central volume expansion is not without hazard.
Treatment of nitroglycerin overdose in these patients may be subtle and difficult, and invasive monitoring may be required. Methemoglobinemia: Nitrate ions liberated during metabolism of nitroglycerin can oxidize hemoglobin into methemoglobin. Even in patients totally without cytochrome b5 reductase activity, however, and even assuming that the nitrate moieties of nitroglycerin are quantitatively applied to oxidation of hemoglobin, about 1 mg/kg of nitroglycerin should be required before any of these patients manifests clinically significant ( 3 10%) methemoglobinemia.
In patients with normal reductase function, significant production of methemoglobin should require even larger doses of nitroglycerin. In one study in which 36 patients received 2 to 4 weeks of continuous nitroglycerin therapy at 3.1 to 4.4 mg/hr, the average methemoglobin level measured was 0.2%; this was comparable to that observed in parallel patients who received placebo. Notwithstanding these observations, there are case reports of significant methemoglobinemia in association with moderate overdoses of organic nitrates.
None of the affected patients had been thought to be unusually susceptible. Methemoglobin levels are available from most clinical laboratories. The diagnosis should be suspected in patients who exhibit signs of impaired oxygen delivery despite adequate cardiac output and adequate arterial PO 2 .
Classically, methemoglobinemic blood is described as chocolate brown, without color change on exposure to air. Methemoglobinemia should be treated with methylene blue if the patient develops cardiac or CNS effects of hypoxia. The initial dose is 1 to 2 mg/kg infused intravenously over 5 minutes.
Repeat methemoglobin levels should be obtained 30 minutes later and a repeat dose of 0.5 to 1.0 mg/kg may be used if the level remains elevated and the patient is still symptomatic. Relative contraindications for methylene blue include known NADH methemoglobin reductase deficiency or G-6-PD deficiency. Infants under the age of 4 months may not respond to methylene blue due to immature NADH methemoglobin reductase.
Exchange transfusion has been used successfully in critically ill patients when methemoglobinemia is refractory to treatment.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY The principal pharmacological action of nitroglycerin is relaxation of vascular smooth muscle and consequent dilatation of peripheral arteries and veins, especially the latter. Dilatation of the veins promotes peripheral pooling of blood and decreases venous return to the heart, thereby reducing left ventricular end-diastolic pressure and pulmonary capillary wedge pressure (preload). Arteriolar relaxation reduces systemic vascular resistance, systolic arterial pressure, and mean arterial pressure (afterload).
Dilatation of the coronary arteries also occurs. The relative importance of preload reduction, afterload reduction, and coronary dilatation remains undefined. Dosing regimens for most chronically used drugs are designed to provide plasma concentrations that are continuously greater than a minimally effective concentration.
This strategy is inappropriate for organic nitrates. Several well-controlled clinical trials have used exercise testing to assess the antianginal efficacy of continuously delivered nitrates. In the large majority of these trials, active agents were indistinguishable from placebo after 24 hours (or less) of continuous therapy.
Attempts to overcome nitrate tolerance by dose escalation, even to doses far in excess of those used acutely, have consistently failed. Only after nitrates have been absent from the body for several hours has their antianginal efficacy been restored. Pharmacokinetics: The volume of distribution of nitroglycerin is about 3 L/kg, and nitroglycerin is cleared from this volume at extremely rapid rates, with a resulting serum half-life of about 3 minutes.
The observed clearance rates (close to 1 L/kg/min) greatly exceed hepatic blood flow; known sites of extrahepatic metabolism include red blood cells and vascular walls. The first products in the metabolism of nitroglycerin are inorganic nitrate and the 1,2- and 1,3-dinitroglycerols. The dinitrates are less effective vasodilators than nitroglycerin, but they are longer-lived in the serum, and their net contribution to the overall effect of chronic nitroglycerin regimens is not known.
The dinitrates are further metabolized to (nonvasoactive) mononitrates and, ultimately, to glycerol and carbon dioxide. To avoid development of tolerance to nitroglycerin, drug-free intervals of 10 to 12 hours are known to be sufficient; shorter intervals have not been well studied. In one well-controlled clinical trial, subjects receiving nitroglycerin appeared to exhibit a rebound or withdrawal effect, so that their exercise tolerance at the end of the daily drug-free interval was less than that exhibited by the parallel group receiving placebo.
In healthy volunteers, steady-state plasma concentrations of nitroglycerin are reached by about 2 hours after application of a patch and are maintained for the duration of wearing the system (observations have been limited to 24 hours). Upon removal of the patch, the plasma concentration declines with a half-life of about an hour. Clinical Trials: Regimens in which nitroglycerin patches were worn for 12 hours daily have been studied in wellcontrolled trials up to 4 weeks in duration.
Starting about 2 hours after application and continuing until 10 to 12 hours after application, patches that deliver at least 0.4 mg of nitroglycerin per hour have consistently demonstrated greater antianginal activity than placebo. Lower-dose patches have not been as well studied, but in one large, well-controlled trial in which higher-dose patches were also studied, patches delivering 0.2 mg/hr had significantly less antianginal activity than placebo. It is reasonable to believe that the rate of nitroglycerin absorption from patches may vary with the site of application, but this relationship has not been adequately studied.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Nitroglycerin Transdermal Infusion System Rated Release In Vivo* Total nitroglycerin content System size Package Size 0.1 mg/hr 20 mg 5 cm 2 Unit Dose 30 (NDC 43598-896-11) Package 30 (NDC 43598-896-30) 0.2 mg/hr 40 mg 10 cm 2 Unit Dose 30 (NDC 43598-895-11) Package 30 (NDC 43598-895-30) 0.4 mg/hr 80 mg 20 cm 2 Unit Dose 30 (NDC 43598-894-11) Package 30 (NDC 43598-894-30) 0.6 mg/hr 120 mg 30 cm 2 Unit Dose 30 (NDC 43598-893-11) Package 30 (NDC 43598-893-30) *Release rates were formerly described in terms of drug delivered per 24 hours.
In these terms, the supplied nitroglycerin transdermal system would be rated at 2.5 mg/24 hours (0.1 mg/hour), 5 mg/24 hours (0.2 mg/hour), 10 mg/24 hours (0.4 mg/hour), and 15 mg/24 hours (0.6 mg/hour). Store at 25°C (77°F); excursions permitted to 15 to 30°C (59 to 86°F) [see USP Controlled Room Temperature]. Do not refrigerate.
📦 Storage and Handling ▾
Store at 25°C (77°F); excursions permitted to 15 to 30°C (59 to 86°F) [see USP Controlled Room Temperature]. Do not refrigerate.
📋 Description ▾
DESCRIPTION Nitroglycerin is 1,2,3-propanetriol trinitrate, an organic nitrate whose structural formula is: and whose molecular weight is 227.09. The organic nitrates are vasodilators, active on both arteries and veins. The nitroglycerin transdermal infusion system is a flat unit designed to provide continuous controlled release of nitroglycerin through intact skin.
The rate of release of nitroglycerin is linearly dependent upon the area of the applied system; each cm 2 of applied system delivers approximately 0.02 mg of nitroglycerin per hour. Thus, the 5-,10-, 15-, 20-, 30- and 40 cm 2 systems deliver approximately 0.1, 0.2, 0.3, 0.4, 0.6 and 0.8 mg of nitroglycerin per hour, respectively. The remainder of the nitroglycerin in each system serves as a reservoir and is not delivered in normal use.
After 12 hours, for example, each system has delivered approximately 6% of its original content of nitroglycerin. The nitroglycerin transdermal infusion system contains nitroglycerin in acrylic-based polymer adhesives with a resinous cross-linking agent to provide a continuous source of active ingredient. Each unit is sealed in a paper polyethylene-foil pouch.
Cross section of the system. Nitroglycerin Chemical Structure Cross section of system
💬 Information for Patients ▾
Information for Patients: Daily headaches sometimes accompany treatment with nitroglycerin. In patients who get these headaches, the headaches may be a marker of the activity of the drug. Patients should resist the temptation to avoid headaches by altering the schedule of their treatment with nitroglycerin, since loss of headache may be associated with simultaneous loss of antianginal efficacy.
Treatment with nitroglycerin may be associated with lightheadedness on standing, especially just after rising from a recumbent or seated position. This effect may be more frequent in patients who have also consumed alcohol. After normal use, there is enough residual nitroglycerin in discarded patches that they are a potential hazard to children and pets.
A patient leaflet is supplied with the systems.