
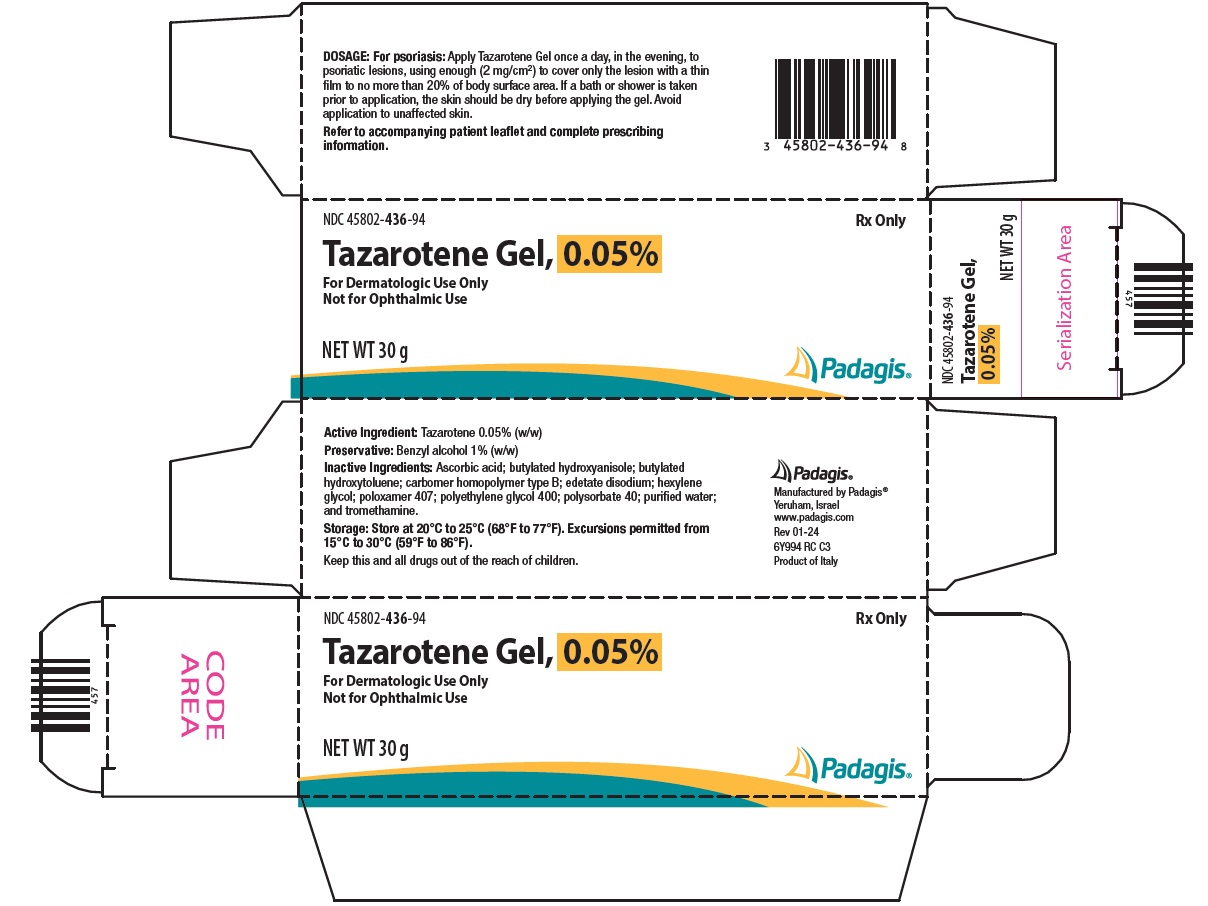
TAZAROTENE .5 mg/g Gel
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Retinoid class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Tazarotene (Tazorac, Fabior) is used to treat acne. Tazarotene (Tazorac) is also used to treat psoriasis (a skin disease in which red, scaly patches form on some areas of the body). Tazarotene (Avage) is used to reduce facial wrinkling and discoloration in patients who are also using other skin care and sunlight avoidance programs. Tazarotene is in a class of medications called retinoids. It works to treat acne and psoriasis by slowing skin cell overgrowth and decreasing skin cell inflammation, which can lead to acne or psoriasis. It works to reduce facial wrinkles and discoloration by causing...
Read the full MedlinePlus article ↗- It's designed to help reduce the look of fine facial wrinkles, uneven patches of lighter or darker skin, and flat age spots — but it works as part of a bigger picture that includes...
- What exactly is tazarotene cream supposed to do for my skin?
- Yes, some redness, peeling, burning, and dryness are very common when you first start using tazarotene, and they tend to be most noticeable in the beginning. Your skin often needs...
- My skin got really red and peely after I started using it — is that normal?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Tazarotene — tap one for details:
Tazarotene may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII PQ6CK8PD0R
Ascorbic acid, also known as vitamin C, is a white crystalline powder. It serves as an antioxidant to prevent degradation of other ingredients and may also function as a preservative in the formulation.
-
UNII LKG8494WBH
Benzyl alcohol is a clear liquid used as a preservative and solvent in medicines. It helps prevent bacterial and fungal growth and dissolves other ingredients to create uniform liquid formulations.
-
UNII REK4960K2U
Butylated hydroxyanisole is a synthetic preservative that prevents oils and fats in medicines from spoiling or becoming rancid. It keeps the medicine stable and extends its shelf life.
-
UNII 1P9D0Z171K
BHT is a synthetic antioxidant that prevents fats and oils in medicines from breaking down and becoming rancid. It helps keep the product stable and effective during storage.
-
UNII HHT01ZNK31
Carbomer Homopolymer Type B is a synthetic polymer made from acrylic acid. It absorbs water and forms a gel, so it's used in medicines as a thickener, suspending agent, and to help create a smooth texture in creams, gels, and lotions.
-
UNII 7FLD91C86K
Edetate disodium is a chemical compound that binds and removes certain metal ions. In medicines, it acts as a preservative and stabilizer by preventing metals like calcium from interfering with the product's shelf life and consistency.
-
UNII KEH0A3F75J
Hexylene glycol is a clear liquid alcohol used as a solvent and preservative in medicines. It helps dissolve other ingredients and keeps the product stable during storage.
-
UNII TUF2IVW3M2
Poloxamer 407 is a synthetic polymer made from ethylene oxide and propylene oxide. In medicines, it acts as a thickener, emulsifier, and solubilizer to help mix ingredients and create the right texture.
-
UNII B697894SGQ
Polyethylene glycol 400 is a clear, thick liquid made from petroleum-derived polymers. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII STI11B5A2X
Polysorbate 40 is a synthetic emulsifier derived from sorbitol and fatty acids. It helps keep oils and water mixed together in liquid medications and also improves how the product flows.
-
UNII 023C2WHX2V
Tromethamine is a chemical buffer that helps maintain the proper acidity level in liquid medicines. It neutralizes acids and stabilizes the solution so the medication remains effective and safe throughout its shelf life.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per g | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $8.04 | $804.34 / 100 g |
| Medicare drug plans payPart D · Q2 2026 | $8.26 | $826.04 / 100 g |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Tazarotene .5 mg/g 00713-0805-31 | Cosette | 1 tube | $4.634 | AB | Availability likely | — |
| Tazarotene .5 mg/g 45802-0706-94 | Padagis | 1 tube | $6.724 | AB | Availability likely | — |
| Tazarotene .5 mg/g 00713-0765-31 | Cosette | 1 tube | $6.724 | AB | Availability likely | — |
| Tazorac .5 mg/g 16110-0833-10 | Almirall, | 1 tube | — | AB | FDA listed | — |
| Tazarotene .5 mg/gthis 45802-0436-01 | Padagis | 1 tube | — | AB | FDA listed | — |
| Tazarotene .5 mg/g 73473-0309-10 | Solaris | 1 tube | — | AB | FDA listed | — |
| Tazarotene .5 mg/g 72162-2420-03 | Bryant | 1 tube | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 45802-0436-01 You're viewing this | 1 TUBE in 1 CARTON (45802-436-01) / 100 g in 1 TUBE | — | — | 2023-06-05 | Active |
| 45802-0436-94 | 1 TUBE in 1 CARTON (45802-436-94) / 30 g in 1 TUBE | $4.63 / g | $139.03 | 2023-06-05 | Active |
This pack accounts for about 26% of this product's recent Medicaid fills; most go to a different pack size. See all packs ↓
Pack size FAQ
What quantity is in NDC 45802-0436-01?
What NDC number is used to bill for this package of TAZAROTENE .5 mg/g Gel?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE • Tazarotene gel, 0.05% and 0.1% is a retinoid indicated for the topical treatment of plaque psoriasis of up to 20% body surface area involvement. ( 1.1 ) • Tazarotene gel, 0.1% is indicated for the topical treatment of mild to moderate facial acne vulgaris. ( 1.2 ) Limitations of Use • The safety of tazarotene gel use on more than 20% body surface area has not been established. ( 1.3 )
1.1Plaque Psoriasis Tazarotene gel, 0.05% and 0.1% are indicated for the topical treatment of patients with plaque psoriasis of up to 20% body surface area involvement.
1.2Acne Vulgaris Tazarotene gel, 0.1% is also indicated for the topical treatment of patients with facial acne vulgaris of mild to moderate severity. The efficacy of tazarotene gel in the treatment of acne previously treated with other retinoids or resistant to oral antibiotics has not been established.
1.3Limitations of Use The safety of tazarotene gel use on more than 20% body surface area has not been established in psoriasis or acne [see Warnings and Precautions (5.1) and Use in Specific Populations (8.1)] .
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Tazarotene gel is for topical use only. Tazarotene gel is not for ophthalmic, oral, or intravaginal use. Avoid accidental transfer of tazarotene gel into eyes, mouth, or other mucous membranes.
If contact with mucous membranes occurs, rinse thoroughly with water [see Warnings and Precautions (5.2)] . Wash hands thoroughly after application. • Apply a thin layer of tazarotene gel only to the affected area once daily in the evening. ( 2.1 , 2.2 ) • Not for ophthalmic, oral, or intravaginal use.
( 2.2 ) • If contact with eyes occurs, rinse thoroughly with water. ( 2.2 )
2.1Psoriasis It is recommended that treatment starts with tazarotene gel, 0.05%, with strength increased to 0.1% if tolerated and medically indicated. Apply a thin film (2 mg/cm 2 ) of tazarotene gel once per day, in the evening, to cover only the psoriatic lesions on no more than 20% of body surface area. If a bath or shower is taken prior to application, the skin should be dry before applying the gel.
If emollients are used, they should be applied at least an hour before application of tazarotene gel. Because unaffected skin may be more susceptible to irritation, application of tazarotene to these areas should be carefully avoided. Tazarotene gel was investigated for up to 12 months during clinical trials for psoriasis.
2.2Acne Cleanse the face gently. After the skin is dry, apply a thin layer (2 mg/cm 2 ) of tazarotene gel 0.1% once per day, in the evening, to the skin where acne lesions appear. Use enough to cover the entire affected area. Tazarotene gel was investigated for up to 12 weeks during clinical trials for acne. Use effective sunscreens and wear protective clothing while using tazarotene gel [see Warnings and Precautions (5.3)] .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Gel, 0.05% and 0.1%, in 30 g and 100 g tubes. Each gram of Tazarotene Gel, 0.05% and 0.1% contains 0.5 mg and 1 mg of tazarotene, respectively in a translucent, aqueous gel. Gel, 0.05% and 0.1% ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Tazarotene gel is contraindicated in: • Pregnancy. Retinoids may cause fetal harm when administered to a pregnant female [see Warnings and Precautions (5.1), Use in Specific Populations (8.1, 8.3)] . • Individuals who have known hypersensitivity to any of its components [see Warnings and Precautions (5.2)] . • Pregnancy ( 4 , 8.1 ) • Hypersensitivity ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Embryofetal Toxicity: Tazarotene gel contains tazarotene, which is a teratogen. Tazarotene gel is contraindicated in pregnancy. Females of child-bearing potential should have a negative pregnancy test within 2 weeks prior to initiating treatment and use an effective method of contraception during treatment.
( 5.1 ) • Local Irritation: Excessive pruritus, burning, skin redness or peeling can occur. If these reactions occur, discontinue until the integrity of the skin has been restored, or consider reducing dosing frequency or in the case of psoriasis, consider switching to the lower concentration. Tazarotene gel should not be used on eczematous skin, as it may cause severe irritation.
( 5.2 ) • Photosensitivity and Risk for Sunburn: Avoid exposure to sunlight, sunlamps, and weather extremes. Wear sunscreen daily. Tazarotene gel should be administered with caution if the patient is also taking drugs known to be photosensitizers.
( 5.3 )
5.1Embryofetal Toxicity Based on data from animal reproduction studies, retinoid pharmacology and the potential for systemic absorption, tazarotene gel may cause fetal harm when administered to a pregnant female and is contraindicated during pregnancy. Tazarotene elicits malformations and developmental effects associated with retinoids after topical and oral administration to pregnant rats and rabbits during organogenesis. Systemic exposure to tazarotenic acid is dependent upon the extent of the body surface area treated.
In patients treated topically over sufficient body surface area, exposure could be in the same order of magnitude as in orally treated animals. Although there may be less systemic exposure in the treatment of acne of the face alone due to less surface area for application, tazarotene is a teratogenic substance and causes fetal malformations in animals, and it is not known what level of exposure is required for teratogenicity in humans [see Clinical Pharmacology (12.3)] . There were thirteen reported pregnancies in subjects who participated in the clinical trials for topical tazarotene.
Nine of the subjects had been treated with topical tazarotene, and the other four had been treated with vehicle. One of the subjects who was treated with tazarotene cream elected to terminate the pregnancy for non-medical reasons unrelated to treatment. The other eight pregnant women who were inadvertently exposed to topical tazarotene during the clinical trials subsequently delivered apparently healthy babies.
As the exact timing and extent of exposure in relation to the gestation times are not certain, the significance of these findings is unknown. Females of Child-bearing Potential Females of child-bearing potential should be warned of the potential risk and use adequate birth-control measures when tazarotene gel is used. The possibility that a female of child-bearing potential is pregnant at the time of institution of therapy should be considered.
A negative result for pregnancy test should be obtained within 2 weeks prior to tazarotene gel therapy. Tazarotene gel therapy should begin during a normal menstrual period [see Use in Specific Populations (8.1)] .
5.2Local Irritation and Hypersensitivity Reactions Application of tazarotene gel may cause excessive irritation in the skin of certain sensitive individuals. Local reactions (including blistering and skin desquamation, pruritus, burning, erythema) and hypersensitivity adverse reactions (including urticaria) have been observed with topical tazarotene. If these adverse reactions occur, consider discontinuing the medication or reducing the dosing frequency, as appropriate, until the integrity of the skin is restored.
Alternatively, patients with psoriasis who are being treated with the 0.1% concentration can be switched to the lower concentration. Frequency of application should be closely monitored by careful observation of the clinical therapeutic response and skin tolerance. Therapy can be resumed, or the dru…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed in more detail in other sections of the labeling: • Embryofetal toxicity [see Warnings and Precautions (5.1)] • Photosensitivity and Risk of Sunburn [see Warnings and Precautions (5.3)] • Plaque Psoriasis: Most common adverse reactions occurring in 10 to 30% of patients are pruritus, burning/stinging, erythema, worsening of psoriasis, irritation, and skin pain. ( 6.1 ) • Acne Vulgaris: Most common adverse reactions occurring in 10 to 30% of patients are desquamation, burning/stinging, dry skin, erythema and pruritus.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Padagis ® at 1-866-634-9120 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Psoriasis A total of 439 subjects 14 to 87 years of age were treated with tazarotene gel, 0.05% and 0.1% in two controlled clinical trials. The most frequent adverse events reported with tazarotene gel, 0.05% and 0.1% occurring in 10 to 30% of subjects, in descending order, included pruritus, burning/stinging, erythema, worsening of psoriasis, irritation, and skin pain.
Reactions occurring in 1 to 10% of subjects included rash, desquamation, irritant contact dermatitis, skin inflammation, fissuring, bleeding, and dry skin. Increases in “psoriasis worsening” and “sun-induced erythema” were noted in some subjects over the 4th to 12th months of treatment as compared to the first three months of a 1 year study. In general, the incidence of adverse events with tazarotene gel 0.05% was 2 to 5% lower than that seen with tazarotene gel 0.1%.
Acne A total of 596 subjects 12 to 44 years of age were treated with tazarotene gel, 0.05% and 0.1% in two controlled clinical trials. The most frequent adverse events reported during clinical trials with tazarotene gel, 0.1% in the treatment of acne occurring in 10 to 30% of subjects, in descending order, included desquamation, burning/stinging, dry skin, erythema and pruritus. Reactions occurring in 1 to 10% of subjects included irritation, skin pain, fissuring, localized edema and skin discoloration.
6.2Postmarketing Experience Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. The following adverse reactions have been identified during postapproval use of tazarotene. Skin and subcutaneous tissue disorders: blister, dermatitis, urticaria, skin exfoliation, skin discoloration (including skin hyperpigmentation or skin hypopigmentation), swelling at or near application sites, and pain.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS No formal drug-drug interaction studies were conducted with tazarotene gel. In a trial of 27 healthy female subjects between the ages of 20–55 years receiving a combination oral contraceptive tablet containing 1 mg norethindrone and 35 mcg ethinyl estradiol, concomitant use of tazarotene administered as 1.1 mg orally (mean ± SD C max and AUC 0-24 of tazarotenic acid were 28.9 ± 9.4 ng/mL and 120.6 ± 28.5 ng•hr/mL, respectively) did not affect the pharmacokinetics of norethindrone and ethinyl estradiol over a complete cycle.
The impact of tazarotene on the pharmacokinetics of progestin only oral contraceptives (i.e., minipills) has not been evaluated.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Based on data from animal reproduction studies, retinoid pharmacology, and the potential for systemic absorption, tazarotene gel may cause fetal harm when administered to a pregnant female and is contraindicated during pregnancy. Safety in pregnant females has not been established. The potential risk to the fetus outweighs the potential benefit to the mother from tazarotene gel during pregnancy; therefore, tazarotene gel should be discontinued as soon as pregnancy is recognized [see Contraindications (4), Warnings and Precautions (5.1), Clinical Pharmacology (12.3)] .
Limited case reports of pregnancy in females enrolled in clinical trials for tazarotene gel have not established a clear association with tazarotene and major birth defects or miscarriage risk. Because the exact timing and extent of exposure in relation to the gestational age are not certain, the significance of these findings is unknown. In animal reproduction studies with pregnant rats, tazarotene dosed topically during organogenesis at 0.5 times the maximum systemic exposure in subjects treated with the maximum recommended human dose (MRHD) of tazarotene gel, 0.1% resulted in reduced fetal body weights and reduced skeletal ossification.
In animal reproduction studies with pregnant rabbits dosed topically with tazarotene gel at 7 times the maximum systemic exposure in subjects treated with the MRHD of tazarotene gel, 0.1%, there were single incidences of known retinoid malformations, including spina bifida, hydrocephaly, and heart anomalies. In animal reproduction studies with pregnant rats and rabbits, tazarotene dosed orally during organogenesis at 0.5 and 13 times, respectively, the maximum systemic exposure in subjects treated with the MRHD of tazarotene gel, 0.1% resulted in malformations, fetal toxicity, developmental delays, and/or behavioral delays.
In pregnant rats, tazarotene dosed orally prior to mating through early gestation resulted in decreased litter size, decreased numbers of live fetuses, decreased fetal body weights, and increased malformations at doses approximately 2 times higher than the maximum systemic exposure in subjects treated with the MRHD of tazarotene gel, 0.1% [see Data] . The background risk of major birth defects and miscarriage for the indicated population is unknown. Adverse outcomes in pregnancy occur regardless of the health of the mother or the use of medications.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Data Animal Data In rats, a tazarotene gel, 0.05% formulation dosed topically during gestation days 6 through 17 at 0.25 mg/kg/day, which represented 0.5 times the maximum systemic exposure in subjects treated with the MRHD of tazarotene gel, 0.1% (i.e., 2 mg/cm 2 over a 20% body surface area), resulted in reduced fetal body weights and reduced skeletal ossification.
Rabbits dosed topically with 0.25 mg/kg/day tazarotene gel, which represented 7 times the maximum systemic exposure in subjects treated with the MRHD of tazarotene gel, 0.1%, during gestation days 6 through 18 were noted with single incidences of known retinoid malformations, including spina bifida, hydrocephaly, and heart anomalies. When tazarotene was given orally to animals, developmental delays were seen in rats, and malformations and post-implantation loss were observed in rats and rabbits at doses producing 0.5 and 13 times, respectively, the maximum systemic exposure in subjects treated with the MRHD of tazarotene gel, 0.1%.
In female rats orally administered 2 mg/kg/day of tazarotene from 15 days before mating through gestation day 7, which represented 2 times the maximum systemic exposure in subjects treated with the MRHD of tazarotene gel, 0.1%, classic developmental effects of retinoids were observed including decreased number of implantation sites, decreased litte…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on data from animal reproduction studies, retinoid pharmacology, and the potential for systemic absorption, tazarotene gel may cause fetal harm when administered to a pregnant female and is contraindicated during pregnancy. Safety in pregnant females has not been established. The potential risk to the fetus outweighs the potential benefit to the mother from tazarotene gel during pregnancy; therefore, tazarotene gel should be discontinued as soon as pregnancy is recognized [see Contraindications (4), Warnings and Precautions (5.1), Clinical Pharmacology (12.3)] .
Limited case reports of pregnancy in females enrolled in clinical trials for tazarotene gel have not established a clear association with tazarotene and major birth defects or miscarriage risk. Because the exact timing and extent of exposure in relation to the gestational age are not certain, the significance of these findings is unknown. In animal reproduction studies with pregnant rats, tazarotene dosed topically during organogenesis at 0.5 times the maximum systemic exposure in subjects treated with the maximum recommended human dose (MRHD) of tazarotene gel, 0.1% resulted in reduced fetal body weights and reduced skeletal ossification.
In animal reproduction studies with pregnant rabbits dosed topically with tazarotene gel at 7 times the maximum systemic exposure in subjects treated with the MRHD of tazarotene gel, 0.1%, there were single incidences of known retinoid malformations, including spina bifida, hydrocephaly, and heart anomalies. In animal reproduction studies with pregnant rats and rabbits, tazarotene dosed orally during organogenesis at 0.5 and 13 times, respectively, the maximum systemic exposure in subjects treated with the MRHD of tazarotene gel, 0.1% resulted in malformations, fetal toxicity, developmental delays, and/or behavioral delays.
In pregnant rats, tazarotene dosed orally prior to mating through early gestation resulted in decreased litter size, decreased numbers of live fetuses, decreased fetal body weights, and increased malformations at doses approximately 2 times higher than the maximum systemic exposure in subjects treated with the MRHD of tazarotene gel, 0.1% [see Data] . The background risk of major birth defects and miscarriage for the indicated population is unknown. Adverse outcomes in pregnancy occur regardless of the health of the mother or the use of medications.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Data Animal Data In rats, a tazarotene gel, 0.05% formulation dosed topically during gestation days 6 through 17 at 0.25 mg/kg/day, which represented 0.5 times the maximum systemic exposure in subjects treated with the MRHD of tazarotene gel, 0.1% (i.e., 2 mg/cm 2 over a 20% body surface area), resulted in reduced fetal body weights and reduced skeletal ossification.
Rabbits dosed topically with 0.25 mg/kg/day tazarotene gel, which represented 7 times the maximum systemic exposure in subjects treated with the MRHD of tazarotene gel, 0.1%, during gestation days 6 through 18 were noted with single incidences of known retinoid malformations, including spina bifida, hydrocephaly, and heart anomalies. When tazarotene was given orally to animals, developmental delays were seen in rats, and malformations and post-implantation loss were observed in rats and rabbits at doses producing 0.5 and 13 times, respectively, the maximum systemic exposure in subjects treated with the MRHD of tazarotene gel, 0.1%.
In female rats orally administered 2 mg/kg/day of tazarotene from 15 days before mating through gestation day 7, which represented 2 times the maximum systemic exposure in subjects treated with the MRHD of tazarotene gel, 0.1%, classic developmental effects of retinoids were observed including decreased number of implantation sites, decreased litter size, decreased numbers of l…
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and efficacy of tazarotene gel have not been established in pediatric patients with psoriasis or acne under the age of 12 years.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of subjects in clinical trials of tazarotene gel for plaque psoriasis, 163 were over the age of 65. Subjects over 65 years of age experienced more adverse events and lower treatment success rates after 12 weeks of use of tazarotene gel compared with those 65 years of age and younger. Currently there is no other clinical experience on the differences in responses between the elderly and younger subjects, but greater sensitivity of some older individuals cannot be ruled out.
Tazarotene gel for the treatment of acne has not been clinically evaluated in persons over the age of 65.
🆘 Overdosage ▾
10 OVERDOSAGE Excessive topical use of tazarotene gel, 0.05% and 0.1% may lead to marked redness, peeling, or discomfort [see Warnings and Precautions (5.2)] . Tazarotene gel, 0.05% and 0.1% are not for oral use. Oral ingestion of the drug may lead to the same adverse effects as those associated with excessive oral intake of Vitamin A (hypervitaminosis A) or other retinoids.
If oral ingestion occurs, the patient should be monitored, and appropriate supportive measures should be administered as necessary.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Tazarotene is a retinoid prodrug which is converted to its active form, the carboxylic acid of tazarotene, by deesterification. Tazarotenic acid binds to all three members of the retinoic acid receptor (RAR) family: RARα, RARβ, and RARγ, but shows relative selectivity for RARβ, and RARγ and may modify gene expression. The clinical significance of these findings for the treatment of plaque psoriasis and facial acne vulgaris is unknown.
12.2Pharmacodynamics The pharmacodynamics of tazarotene gel in the treatment of plaque psoriasis and facial acne vulgaris are unknown.
12.3Pharmacokinetics Following topical application, tazarotene undergoes esterase hydrolysis to form its active metabolite, tazarotenic acid. Little parent compound could be detected in the plasma. Tazarotenic acid was highly bound to plasma proteins (greater than 99%).
Tazarotene and tazarotenic acid were metabolized to sulfoxides, sulfones and other polar metabolites which were eliminated through urinary and fecal pathways. The half-life of tazarotenic acid was approximately 18 hours, following topical application of tazarotene to normal, acne or psoriatic skin. The human in vivo studies described below were conducted with tazarotene gel applied topically at approximately 2 mg/cm 2 and left on the skin for 10 to 12 hours.
Both the peak plasma concentration (C max ) and area under the plasma concentration time curve (AUC) refer to the active metabolite only. Two single, topical dose studies were conducted using 14 C-tazarotene gel. Systemic absorption, as determined from radioactivity in the excreta, was less than 1% of the applied dose (without occlusion) in six subjects with psoriasis and approximately 5% of the applied dose (under occlusion) in six healthy subjects.
One non-radiolabeled single-dose study comparing the 0.05% gel to the 0.1% gel in healthy subjects indicated that the C max and AUC were 40% higher for the 0.1% gel. After 7 days of topical dosing with measured doses of tazarotene 0.1% gel on 20% of the total body surface without occlusion in 24 healthy subjects, the C max for tazarotenic acid was 0.72 ± 0.58 ng/mL (mean ± SD) occurring 9 hours after the last dose, and the AUC 0-24hr for tazarotenic acid was 10.1 ± 7.2 ng·hr/mL. Systemic absorption was 0.91 ± 0.67% of the applied dose.
In a 14-day study in five subjects with psoriasis, measured doses of tazarotene 0.1% gel were applied daily by nursing staff to involved skin without occlusion (8 to 18% of total body surface area; mean ± SD: 13 ± 5%). The C max for tazarotenic acid was 12.0 ± 7.6 ng/mL occurring 6 hours after the final dose, and the AUC 0-24hr for tazarotenic acid was 105 ± 55 ng·hr/mL. Systemic absorption was 14.8 ± 7.6% of the applied dose.
Extrapolation of these results to represent dosing on 20% of total body surface yielded estimates for tazarotenic acid with C max of 18.9 ± 10.6 ng/mL and AUC 0-24hr of 172 ± 88 ng·hr/mL. An in vitro percutaneous absorption study, using radiolabeled drug and freshly excised human skin or human cadaver skin, indicated that approximately 4 to 5% of the applied dose was in the stratum corneum (tazarotene: tazarotenic acid = 5:1) and 2 to 4% was in the viable epidermis-dermis layer (tazarotene: tazarotenic acid = 2:1) 24 hours after topical application of the gel.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Tazarotene is a retinoid prodrug which is converted to its active form, the carboxylic acid of tazarotene, by deesterification. Tazarotenic acid binds to all three members of the retinoic acid receptor (RAR) family: RARα, RARβ, and RARγ, but shows relative selectivity for RARβ, and RARγ and may modify gene expression. The clinical significance of these findings for the treatment of plaque psoriasis and facial acne vulgaris is unknown.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Tazarotene gel is a translucent, aqueous gel, available in concentrations of 0.05% and 0.1%. It is available in a collapsible aluminum tube with a tamper-evident aluminum membrane over the opening and a white polyethylene screw cap, in 30 g and 100 g sizes. Tazarotene Gel 0.05% 30 g NDC 45802-436-94 Tazarotene Gel 0.05% 100 g NDC 45802-436-01 Tazarotene Gel 0.1% 30 g NDC 45802-442-94 Tazarotene Gel 0.1% 100 g NDC 45802-442-01 Storage: Store at 20°C to 25°C (68°F to 77°F).
Excursions permitted from 15°C to 30°C (59°F to 86°F).
📋 Description ▾
11 DESCRIPTION Tazarotene Gel, 0.05% and 0.1% is for topical use and contains the active ingredient, tazarotene. Each gram of Tazarotene Gel, 0.05% and 0.1% contains 0.5 and 1 mg of tazarotene, respectively in a translucent, aqueous gel. Tazarotene is a member of the acetylenic class of retinoids.
Chemically, tazarotene is ethyl 6-[(4,4-dimethylthiochroman-6-yl)ethynyl]nicotinate. The compound has an empirical formula of C 21 H 21 NO 2 S and molecular weight of 351.46. The structural formula is shown below: Tazarotene gel contains the following inactive ingredients: benzyl alcohol 1%; ascorbic acid; butylated hydroxyanisole; butylated hydroxytoluene; carbomer homopolymer type B; edetate disodium; hexylene glycol; poloxamer 407; polyethylene glycol 400; polysorbate 40; purified water; and tromethamine. structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Embryofetal Toxicity Inform females of reproductive potential of the potential risk to a fetus. Advise these patients to use effective contraception during treatment with tazarotene gel.
Advise patients to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.1) and Use in Specific Populations (8.1, 8.3)] . Photosensitivity and Risk of Sunburn Advise patients to avoid excessive sun exposure and to use sunscreens and protective measures (hat, visor). Advise patients to avoid using tazarotene gel if also taking other medicines may increase sensitivity to sunlight.
Important Administration Instructions Advise the patient of the following: 1. For the patient with psoriasis, apply tazarotene gel only to psoriasis skin lesions, avoiding uninvolved skin. 2.
If undue irritation (redness, peeling, or discomfort) occurs, reduce frequency of application or temporarily interrupt treatment. Treatment may be resumed once irritation subsides [see Dosage and Administration (2.1)] . 3.
Moisturizers may be used as frequently as desired. 4. Patients with psoriasis may use a cream or lotion to soften or moisten skin at least 1 hour before applying tazarotene gel.
5. Avoid contact with the eyes. If tazarotene gel gets in or near eyes, rinse thoroughly with water.
Seek medical attention if eye irritation continues. 6. Tazarotene gel is for topical use only.
Do not apply to eyes, mouth, or other mucous membrane. Not for ophthalmic, oral, or intravaginal use. 7.
Wash hands thoroughly after applying tazarotene gel. Revised: 01/2024 Manufactured by Padagis ® Yeruham, Israel www.padagis.com 6Y900 RC PH3 Pharmacist: Please cut or tear at dotted line and provide this patient package insert to your customer.