
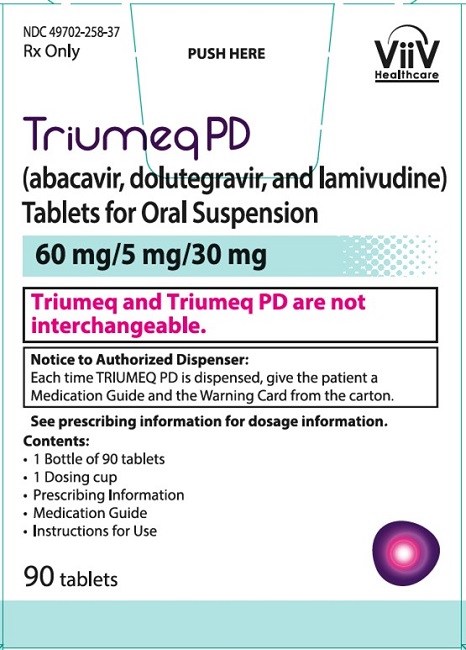
Triumeq PD abacavir sulfate, dolutegravir sodium, lamivudine Kit
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Human Immunodeficiency Virus Integrase Strand Transfer Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
The combination of abacavir, dolutegravir, and lamivudine is used to treat HIV infection. Abacavir and lamivudine are in a class of medications called nucleoside analogue reverse transcriptase inhibitors (NRTIs) and dolutegravir is in a class of medications called integrase strand transfer inhibitors (INSTIs). They work by decreasing the amount of HIV in your blood and increasing the number of immune cells that help fight infections in your body. Although abacavir, dolutegravir, and lamivudine will not cure HIV, these medications may decrease your chance of developing acquired immunodeficiency...
Read the full MedlinePlus article ↗- Triumeq treats HIV-1 infection by keeping the amount of virus in your body very low. It does not cure HIV, but when taken consistently every day, it helps protect your immune syste...
- What exactly is Triumeq treating — does it cure HIV?
- The reaction to abacavir can look like a flu or stomach bug at first — think fever, rash, nausea, vomiting, diarrhea, stomach pain, unusual tiredness, or trouble breathing. The key...
- I heard there's a serious allergic reaction risk. How will I know if it's happening to me?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $12.59 | — |
| Medicare drug plans payPart D · Q2 2026 | $13.54 | — |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Triumeq PDthis 49702-0258-37 | ViiV | 90 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9242986 ↗ | Drug substance | — | Dec 8, 2029 |
| US 8129385 ↗ | Drug substance | — | Oct 5, 2027 |
| US 9242986*PED ↗ | Drug product | — | Jun 8, 2030 |
| US 8129385*PED ↗ | Drug product | — | Apr 5, 2028 |
| Code | What it grants | Expires |
|---|---|---|
| NPP | New Patient Population | Jun 15, 2026 |
| PED | Pediatric Exclusivity (+6 months) | Dec 15, 2026 |
Is there a generic version of TRIUMEQ PD 60-5-30 MG TAB SUSP?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2025 (Q1-Q4)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 49702-0258-37 You're viewing this | 1 KIT in 1 CARTON (49702-258-37) * 90 TABLET, FILM COATED in 1 BOTTLE (49702-272-59) | 2022-03-30 | Active |
🧭 About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: HYPERSENSITIVITY REACTIONS, AND EXACERBATIONS OF HEPATITIS B Hypersensitivity Reactions Serious and sometimes fatal hypersensitivity reactions, with multiple organ involvement, have occurred with abacavir, a component of TRIUMEQ and TRIUMEQ PD (abacavir, dolutegravir, and lamivudine). Patients who carry the HLA ‑ B*5701 allele are at a higher risk of a hypersensitivity reaction to abacavir, although hypersensitivity reactions have occurred in patients who do not carry the HLA ‑ B*5701 allele [see Warnings and Precautions ( 5.1 )] .
TRIUMEQ and TRIUMEQ PD are contraindicated in patients with a prior hypersensitivity reaction to abacavir and in HLA ‑ B*5701-positive patients [see Contraindications ( 4 ), Warnings and Precautions ( 5.1 )] . All patients should be screened for the HLA ‑ B*5701 allele prior to initiating therapy with TRIUMEQ or TRIUMEQ PD or reinitiation of therapy with TRIUMEQ or TRIUMEQ PD, unless patients have a previously documented HLA ‑ B*5701 allele assessment. Discontinue TRIUMEQ or TRIUMEQ PD immediately if a hypersensitivity reaction is suspected, regardless of HLA ‑ B*5701 status and even when other diagnoses are possible [see Contraindications ( 4 ), Warnings and Precautions ( 5.1 )] .
Following a hypersensitivity reaction to TRIUMEQ or TRIUMEQ PD, NEVER restart TRIUMEQ or TRIUMEQ PD or any other abacavir ‑ containing product because more severe symptoms, including death can occur within hours. Similar severe reactions have also occurred rarely following the reintroduction of abacavir-containing products in patients who have no history of abacavir hypersensitivity [see Warnings and Precautions ( 5.1 )] . Exacerbations of Hepatitis B All patients with HIV-1 should be tested for the presence of hepatitis B virus (HBV) prior to or when initiating TRIUMEQ or TRIUMEQ PD.
Emergence of lamivudine-resistant HBV variants associated with lamivudine-containing antiretroviral regimens has been reported. If TRIUMEQ or TRIUMEQ PD is used in patients co-infected with HIV-1 and HBV, additional treatment should be considered for appropriate treatment of chronic HBV; otherwise, consider an alternative regimen. Severe acute exacerbations of hepatitis B have been reported in patients who are co ‑ infected with HBV and HIV-1 and have discontinued lamivudine, a component of TRIUMEQ and TRIUMEQ PD.
Closely monitor hepatic function in these patients and, if appropriate, initiate anti-HBV treatment [see Warnings and Precautions ( 5.2 )]. WARNING: HYPERSENSITIVITY REACTIONS, AND EXACERBATIONS OF HEPATITIS B See full prescribing information for complete boxed warning. Hypersensitivity Reactions • Serious and sometimes fatal hypersensitivity reactions have occurred with abacavir-containing products.
( 5.1 ) • Hypersensitivity to abacavir is a multi-organ clinical syndrome. ( 5.1 ) • Patients who carry the HLA ‑ B*5701 allele are at a higher risk of experiencing a hypersensitivity reaction to abacavir. ( 5.1 ) • TRIUMEQ and TRIUMEQ PD are contraindicated in patients with a prior hypersensitivity reaction to abacavir and in HLA-B*5701-positive patients.
( 4 ) • Discontinue TRIUMEQ or TRIUMEQ PD as soon as a hypersensitivity reaction is suspected. Regardless of HLA-B*5701 status, permanently discontinue TRIUMEQ or TRIUMEQ PD if hypersensitivity cannot be ruled out, even when other diagnoses are possible. ( 5.1 ) • Following a hypersensitivity reaction to TRIUMEQ or TRIUMEQ PD, NEVER restart TRIUMEQ, TRIUMEQ PD, or any other abacavir ‑ containing product.
( 5.1 ) Exacerbations of Hepatitis B • All patients with HIV-1 should be tested for the presence of hepatitis B virus (HBV) prior to or when initiating TRIUMEQ or TRIUMEQ PD. Emergence of lamivudine-resistant HBV variants associated with lamivudine-containing antiretroviral regimens has been reported. If TRIUMEQ or TRIUMEQ PD is used in patients co-infected with HIV-1 and HBV, additional treatment should be considered for appropriate treatment of chronic HBV; otherwise, cons…
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE TRIUMEQ and TRIUMEQ PD are indicated for the treatment of HIV-1 infection in adults and in pediatric patients aged at least 3 months and weighing at least 6 kg. Limitations of Use: TRIUMEQ and TRIUMEQ PD alone are not recommended in patients with resistance‑associated integrase substitutions or clinically suspected integrase strand transfer inhibitor (INSTI) resistance because the dose of dolutegravir in TRIUMEQ and TRIUMEQ PD is insufficient in these subpopulations. See full prescribing information for TIVICAY (dolutegravir).
TRIUMEQ and TRIUMEQ PD are a combination of dolutegravir (integrase strand transfer inhibitor [INSTI]), abacavir, and lamivudine (both nucleoside analogue reverse transcriptase inhibitors) indicated for the treatment of HIV-1 infection in adults and in pediatric patients aged at least 3 months and weighing at least 6 kg. ( 1 ) Limitations of Use: TRIUMEQ and TRIUMEQ PD alone are not recommended in patients with resistance-associated integrase substitutions or clinically suspected INSTI resistance because the dose of dolutegravir in TRIUMEQ and TRIUMEQ PD is insufficient in these subpopulations.
See the dolutegravir prescribing information. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Before initiating TRIUMEQ or TRIUMEQ PD, screen for the HLA‑B*5701 allele because TRIUMEQ and TRIUMEQ PD contain abacavir. ( 2.1 ). • Prior to or when initiating TRIUMEQ or TRIUMEQ PD, test patients for HBV infection. ( 2.2 ) • TRIUMEQ and TRIUMEQ PD may be taken with or without food.
( 2.4 , 2.5 ) • Adults: One tablet of TRIUMEQ daily. ( 2.4 ) ABC = abacavir, DTG = dolutegravir, 3TC = lamivudine. Pediatric Population Body Weight Number of Tablets (once daily) Recommended Daily Dose TRIUMEQ PD Tablets (6 kg to <25 kg) 6 kg to <10 kg 3 180 mg ABC, 15 mg DTG, and 90 mg 3TC 10 kg to <14 kg 4 240 mg ABC, 20 mg DTG, and 120 mg 3TC 14 kg to <20 kg 5 300 mg ABC, 25 mg DTG, and 150 mg 3TC 20 kg to <25 kg 6 360 mg ABC, 30 mg DTG, and 180 mg 3TC TRIUMEQ Tablets (≥25 kg) ≥25 kg 1 600 mg ABC, 50 mg DTG, and 300 mg 3TC • Do not substitute TRIUMEQ and TRIUMEQ PD on a milligram-per-milligram basis.
( 2.3 ) • If dosing with certain UGT1A or CYP3A inducers, then the recommended dolutegravir dosage regimen should be adjusted. See Table 2 for complete dosing recommendations. ( 2.6 ) • Because TRIUMEQ and TRIUMEQ PD are fixed-dose tablets and cannot be dose adjusted, TRIUMEQ and TRIUMEQ PD are not recommended in patients with creatinine clearance <30 mL/min and pediatric patients with a similar degree of renal impairment based on age-appropriate assessment of renal function, or patients with hepatic impairment.
( 2.7 , 4 )
2.1Screening for HLA−B*5701 Allele prior to Initiating TRIUMEQ Screen for the HLA‑B*5701 allele prior to initiating therapy with TRIUMEQ or TRIUMEQ PD [see Boxed Warning , Warnings and Precautions ( 5.1 )].
2.2Testing prior to or When Initiating Treatment with TRIUMEQ Prior to or when initiating TRIUMEQ or TRIUMEQ PD, test patients for HBV infection [see Warnings and Precautions ( 5.2 )] .
2.3Overview of TRIUMEQ Dosage Forms TRIUMEQ is available in two dosage forms. Do not substitute TRIUMEQ tablets and TRIUMEQ PD tablets for oral suspension on a milligram-per-milligram basis due to differing pharmacokinetic profiles for the dolutegravir component [see Warnings and Precautions ( 5.7 ) , Clinical Pharmacology ( 12.3 )] . • TRIUMEQ tablets: 600 mg of abacavir, 50 mg of dolutegravir, and 300 mg of lamivudine. TRIUMEQ is recommended in adults and pediatric patients weighing at least 25 kg [see Dosage and Administration ( 2.4 , 2.5 )] . • TRIUMEQ PD tablets for oral suspension: 60 mg of abacavir, 5 mg of dolutegravir, and 30 mg of lamivudine.
TRIUMEQ PD is recommended in pediatric patients weighing 6 kg to less than 25 kg [see Dosage and Administration ( 2.5 )] . • Because TRIUMEQ PD is a fixed-dose tablet and the dosage of individual components cannot be adjusted, it may lead to a suboptimal dosing for patients weighing ≥25 kg. TRIUMEQ PD is not recommended in patients weighing 25 kg or more [see Dosage and Administration ( 2.4 , 2.5 )] .
2.4Recommended Dosage in Adults TRIUMEQ is a fixed-dose combination product containing 600 mg of abacavir, 50 mg of dolutegravir, and 300 mg of lamivudine. The recommended dosage regimen of TRIUMEQ in adults is one tablet once daily orally with or without food. Do not use TRIUMEQ PD in adults.
2.5Recommended Dosage and Administration Instructions for Pediatric Patients Weighing at Least 6 kg The dosage and dosage form recommended for pediatric patients varies by weight as shown in Table 1 below. Table 1. Recommended Dosage of TRIUMEQ Tablets and TRIUMEQ PD Tablets for Oral Suspension in Pediatric Patients a TRIUMEQ is a fixed-dose combination product containing 600 mg of abacavir, 50 mg of dolutegravir, and 300 mg of lamivudine. b TRIUMEQ PD is a fixed-dose combination product containing 60 mg of abacavir, 5 mg of dolutegravir, and 30 mg of lamivudine.
Body Weight TRIUMEQ Tablets a TRIUMEQ PD b Number of Tablets Total Daily Dose 6 kg to <10 kg Not recommended 3 tablets once daily 180 mg abacavir, 15 mg dolutegravir, and 90 mg lamivudine once daily 10 kg to <14 kg…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS TRIUMEQ tablets are purple, biconvex, oval, and debossed with “572 Trı” on one side. Each film-coated tablet contains 600 mg of abacavir (as abacavir sulfate), 50 mg of dolutegravir (as dolutegravir sodium), and 300 mg of lamivudine [see Description ( 11 )] . TRIUMEQ PD tablets for oral suspension are yellow, capsule-shaped, strawberry cream flavored, biconvex, film-coated tablets debossed with “SV WTU” on one side.
Each film-coated tablet contains 60 mg of abacavir (as abacavir sulfate), 5 mg of dolutegravir (as dolutegravir sodium), and 30 mg of lamivudine [see Description ( 11 )] . • TRIUMEQ tablets: 600 mg of abacavir, 50 mg of dolutegravir, and 300 mg of lamivudine. ( 3 ) • TRIUMEQ PD tablets for oral suspension: 60 mg of abacavir, 5 mg of dolutegravir, and 30 mg of lamivudine. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS TRIUMEQ and TRIUMEQ PD are contraindicated in patients: • who have the HLA-B*5701 allele [see Warnings and Precautions ( 5.1 )] . • with prior hypersensitivity reaction to abacavir, dolutegravir [see Warnings and Precautions ( 5.1 )] , or lamivudine. • receiving dofetilide due to the potential for increased dofetilide plasma concentrations and the risk for serious and/or life-threatening events with concomitant use of dolutegravir [see Drug Interactions ( 7 )] . • with moderate or severe hepatic impairment [see Use in Specific Populations ( 8.7 )] . • Presence of HLA-B*5701 allele.
( 4 ) • Prior hypersensitivity reaction to abacavir, dolutegravir, or lamivudine. ( 4 ) • Coadministration with dofetilide. ( 4 ) • Moderate or severe hepatic impairment.
( 4 , 8.7 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Hepatotoxicity has been reported in patients receiving a dolutegravir-containing regimen. Monitoring for hepatotoxicity is recommended. ( 5.3 ) • Lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported with the use of nucleoside analogues.
( 5.4 ) • Immune reconstitution syndrome has been reported in patients treated with combination antiretroviral therapy. ( 5.6 ) • TRIUMEQ tablets and TRIUMEQ PD tablets for oral suspension are not substitutable. ( 2.3 , 5.7 )
5.1Hypersensitivity Reactions Hypersensitivity reactions have been reported with the use of abacavir or dolutegravir, components of TRIUMEQ and TRIUMEQ PD. Abacavir Serious and sometimes fatal hypersensitivity reactions have occurred with abacavir-containing regimens. See full prescribing information for ZIAGEN (abacavir).
Abacavir hypersensitivity reactions have included multi-organ failure and anaphylaxis and typically occurred within the first 6 weeks of treatment with abacavir (median time to onset was 9 days); although abacavir hypersensitivity reactions have occurred any time during treatment [see Adverse Reactions ( 6.1 )] . Patients who carry the HLA‑B*5701 allele are at a higher risk of abacavir hypersensitivity reactions; although, patients who do not carry the HLA‑B*5701 allele have developed hypersensitivity reactions. Hypersensitivity to abacavir was reported in approximately 206 (8%) of 2,670 patients in 9 clinical trials with abacavir-containing products where HLA‑B*5701 screening was not performed.
The incidence of suspected abacavir hypersensitivity reactions in clinical trials was 1% when subjects carrying the HLA-B*5701 allele were excluded. In any patient treated with abacavir, the clinical diagnosis of hypersensitivity reaction must remain the basis of clinical decision making. Due to the potential for severe, serious, and possibly fatal hypersensitivity reactions with abacavir: • All patients should be screened for the HLA‑B*5701 allele prior to initiating therapy with TRIUMEQ or TRIUMEQ PD or reinitiation of therapy with TRIUMEQ or TRIUMEQ PD, unless patients have a previously documented HLA‑B*5701 allele assessment. • TRIUMEQ and TRIUMEQ PD are contraindicated in patients with a prior hypersensitivity reaction to abacavir and in HLA‑B*5701‑positive patients. • Before starting TRIUMEQ or TRIUMEQ PD, review medical history for prior exposure to any abacavir-containing product.
NEVER restart TRIUMEQ or TRIUMEQ PD or any other abacavir-containing product following a hypersensitivity reaction to abacavir, regardless of HLA‑B*5701 status. • To reduce the risk of a life‑threatening hypersensitivity reaction, regardless of HLA‑B*5701 status, discontinue TRIUMEQ or TRIUMEQ PD immediately if a hypersensitivity reaction is suspected, even when other diagnoses are possible (e.g., acute onset respiratory diseases such as pneumonia, bronchitis, pharyngitis, or influenza; gastroenteritis; or reactions to other medications).
Clinical status, including liver chemistries, should be monitored and appropriate therapy initiated. • If a hypersensitivity reaction cannot be ruled out, do not restart TRIUMEQ or TRIUMEQ PD or any other abacavir-containing products because more severe symptoms, which may include life-threatening hypotension and death, can occur within hours. • Clinically, it is not possible to determine whether a hypersensitivity reaction with TRIUMEQ or TRIUMEQ PD would be caused by abacavir or dolutegravir. Therefore, never restart TRIUMEQ or TRIUMEQ PD or any other abacavir- or dolutegravir-containing product in patients who have stopped therapy with TRIUMEQ or TRIUMEQ PD due to a hypersensitivity reaction. • If a hypersensitivity reaction is ruled out, patients may restart TRIUMEQ or TRIUMEQ PD.
Rarely, patients who have stopped abacavir for reasons other than symptoms of hypersensitivity have also experienced life-threatening reactions within hours of reinitiating abacavir therapy…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in other sections of the labeling: • Serious and sometimes fatal hypersensitivity reaction [see Boxed Warning , Warnings and Precautions ( 5.1 )] . • Exacerbations of hepatitis B [see Boxed Warning , Warnings and Precautions ( 5.3 )] . • Hepatotoxicity [see Warnings and Precautions ( 5.3 )] . • Lactic acidosis and severe hepatomegaly with steatosis [see Warnings and Precautions ( 5.4 )] . • Immune reconstitution syndrome [see Warnings and Precautions ( 5.6 )] . • Myocardial infarction [see Warnings and Precautions ( 5.8 )] .
The most commonly reported adverse reactions of at least moderate intensity and incidence at least 2% (in those receiving TRIUMEQ) were insomnia, headache, and fatigue. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact ViiV Healthcare at 1-877-844-8872 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Clinical Trials in Adults Serious and Fatal Abacavir-Associated Hypersensitivity Reactions: In clinical trials, serious and sometimes fatal hypersensitivity reactions have occurred with abacavir, a component of TRIUMEQ and TRIUMEQ PD [see Boxed Warning , Warnings and Precautions ( 5.1 )].
These reactions have been characterized by 2 or more of the following signs or symptoms: (1) fever; (2) rash; (3) gastrointestinal symptoms (including nausea, vomiting, diarrhea, or abdominal pain); (4) constitutional symptoms (including generalized malaise, fatigue, or achiness); (5) respiratory symptoms (including dyspnea, cough, or pharyngitis). Almost all abacavir hypersensitivity reactions include fever and/or rash as part of the syndrome. Other signs and symptoms have included lethargy, headache, myalgia, edema, arthralgia, and paresthesia.
Anaphylaxis, liver failure, renal failure, hypotension, adult respiratory distress syndrome, respiratory failure, myolysis, and death have occurred in association with these hypersensitivity reactions. Physical findings have included lymphadenopathy, mucous membrane lesions (conjunctivitis and mouth ulcerations), and maculopapular or urticarial rash (although some patients had other types of rashes and others did not have a rash). There were reports of erythema multiforme.
Laboratory abnormalities included elevated liver chemistries, elevated creatine phosphokinase, elevated creatinine, and lymphopenia and abnormal chest x‑ray findings (predominantly infiltrates, which were localized). Serious Dolutegravir Hypersensitivity Reactions: In clinical trials, hypersensitivity reactions have occurred with dolutegravir, a component of TRIUMEQ and TRIUMEQ PD [see Warnings and Precautions ( 5.1 )]. These hypersensitivity reactions have been characterized by rash, constitutional findings, and sometimes organ dysfunction, including liver injury.
Additional Treatment-Emergent Adverse Drug Reactions (ADRs) with Use of TRIUMEQ: The safety assessment of TRIUMEQ is primarily based on the analyses of data from a randomized, international, multicenter, double-blind, active-controlled trial, SINGLE (ING114467) and supported by data in treatment-experienced, INSTI-naive subjects from SAILING (ING111762) and by data from other treatment-naive trials. See full prescribing information for TIVICAY. Treatment-Naive Subjects: In SINGLE, 833 adult subjects were randomized and received at least one dose of either dolutegravir (TIVICAY) 50 mg with fixed-dose abacavir and lamivudine (EPZICOM) once daily (n = 414) or fixed-dose efavirenz/emtricitabine/tenofovir (ATRIPLA) once daily (n = 419) (study treatment was blinded through Week 96 and open-label from Week 96 through Week 144).
Through 144 weeks, the rate of adverse events leading to disco…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Coadministration of TRIUMEQ or TRIUMEQ PD with other drugs can alter the concentration of other drugs and other drugs may alter the concentrations of TRIUMEQ or TRIUMEQ PD. The potential drug-drug interactions must be considered prior to and during therapy. ( 4 , 7 , 12.3 )
7.1Effect of Dolutegravir on the Pharmacokinetics of Other Agents In vitro, dolutegravir inhibited the renal organic cation transporters (OCT)2 (IC 50 = 1.93 microM) and multidrug and toxin extrusion transporter (MATE)1 (IC 50 = 6.34 microM). In vivo, dolutegravir inhibits tubular secretion of creatinine by inhibiting OCT2 and potentially MATE1. Dolutegravir may increase plasma concentrations of drugs eliminated via OCT2 or MATE1 (dofetilide, dalfampridine, and metformin) [see Contraindications ( 4 ), Drug Interactions ( 7.3 )] .
In vitro, dolutegravir inhibited the basolateral renal transporters, organic anion transporter (OAT) 1 (IC 50 = 2.12 microM) and OAT3 (IC 50 = 1.97 microM). However, in vivo, dolutegravir did not alter the plasma concentrations of tenofovir or para-amino hippurate, substrates of OAT1 and OAT3. In vitro, dolutegravir did not inhibit (IC 50 >50 microM) the following: cytochrome P450 (CYP)1A2, CYP2A6, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2D6, CYP3A, uridine diphosphate (UDP)-glucuronosyl transferase (UGT)1A1, UGT2B7, P-glycoprotein (P-gp), breast cancer resistance protein (BCRP), bile salt export pump (BSEP), organic anion transporter polypeptide (OATP)1B1, OATP1B3, OCT1, or multidrug resistance protein (MRP)2, or MRP4.
In vitro, dolutegravir did not induce CYP1A2, CYP2B6, CYP3A4. Based on these data and the results of drug interaction trials, dolutegravir is not expected to affect the pharmacokinetics of drugs that are substrates of these enzymes or transporters. In drug interaction trials, dolutegravir did not have a clinically relevant effect on the pharmacokinetics of the following drugs: tenofovir, methadone, midazolam, rilpivirine, and oral contraceptives containing norgestimate and ethinyl estradiol.
Using cross-study comparisons to historical pharmacokinetic data for each interacting drug, dolutegravir did not appear to affect the pharmacokinetics of the following drugs: atazanavir, darunavir, efavirenz, etravirine, fosamprenavir, lopinavir, ritonavir, and boceprevir.
7.2Effect of Other Agents on the Pharmacokinetics of Dolutegravir Dolutegravir is metabolized by UGT1A1 with some contribution from CYP3A. Dolutegravir is also a substrate of UGT1A3, UGT1A9, BCRP, and P-gp in vitro. Drugs that induce those enzymes and transporters may decrease dolutegravir plasma concentrations and reduce the therapeutic effect of dolutegravir.
Coadministration of dolutegravir and other drugs that inhibit these enzymes may increase dolutegravir plasma concentrations. Etravirine significantly reduced plasma concentrations of dolutegravir, but the effect of etravirine was mitigated by coadministration of lopinavir/ritonavir or darunavir/ritonavir and is expected to be mitigated by atazanavir/ritonavir ( Table 6 ) [see Drug Interactions ( 7.3 ), Clinical Pharmacology ( 12.3 )] . In vitro, dolutegravir was not a substrate of OATP1B1 or OATP1B3.
Darunavir/ritonavir, lopinavir/ritonavir, rilpivirine, tenofovir, boceprevir, prednisone, rifabutin, and omeprazole had no clinically significant effect on the pharmacokinetics of dolutegravir.
7.3Established and Other Potentially Significant Drug Interactions There were no drug-drug interaction trials conducted with the abacavir, dolutegravir, and lamivudine fixed-dose combination tablets. Information regarding potential drug interactions with the individual components of TRIUMEQ and TRIUMEQ PD are provided below. These recommendations are based on either drug interaction trials or predicted interactions due to the expected magnitude of interaction and potential for serious adverse events or loss of efficacy. [See Contraindications ( 4 ), Clinical Pharmacology ( 12.3 ).] Table 6.
Establi…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Pediatrics: Not recommended for patients aged <3 months or weighing <6 kg. ( 8.4 ) • TRIUMEQ and TRIUMEQ PD are not recommended in patients with creatinine clearance less than 30 mL/min and pediatric patients with a similar degree of renal impairment based on age-appropriate assessment of renal function. ( 8.6 ) • If a dose reduction of abacavir, a component of TRIUMEQ and TRIUMEQ PD, is required for patients with mild hepatic impairment, then the individual components should be used.
( 8.7 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in individuals exposed to TRIUMEQ during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1‑800‑258‑4263. Risk Summary Data from two, ongoing birth outcome surveillance studies in Botswana and Eswatini which together include over 14,000 individuals evaluated during pregnancy show similar prevalence of neural tube defects among infants born to individuals taking dolutegravir at the time of conception compared to those born to individuals taking non-dolutegravir-containing regimens at conception or infants born to HIV-negative individuals (see Data).
There are insufficient human data on the use of TRIUMEQ during pregnancy to definitively assess a drug-associated risk for birth defects and miscarriage. However, available human data from the APR with the individual components of TRIUMEQ do not indicate an increased risk of birth defects (see Data) . The background risk for major birth defects for the indicated population is unknown.
In the U.S. general population, the estimated background rate for major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. In animal reproduction studies, no evidence of adverse developmental outcomes (including neural tube defects) was observed with dolutegravir at systemic exposures (AUC) less than (rabbits) and approximately 50 times (rats) the exposure in humans at the recommended human dose (RHD) (see Data) . Oral administration of abacavir to pregnant rats during organogenesis resulted in fetal malformations and other embryonic and fetal toxicities at exposures 35 times the human exposure (AUC) at the RHD.
No adverse developmental effects were observed following oral administration of abacavir to pregnant rabbits during organogenesis at exposures approximately 9 times the human exposure (AUC) at the RHD. Oral administration of lamivudine to pregnant rabbits during organogenesis resulted in embryolethality at a human exposure (AUC) similar to the RHD; however, no adverse development effects were observed with oral administration of lamivudine to pregnant rats during organogenesis at plasma concentrations (C max ) 35 times the RHD (see Data).
Data Human Data: Dolutegravir: Observational studies: The first interim analysis from an ongoing birth outcome surveillance study in Botswana identified an association between dolutegravir and an increased risk of neural tube defects when dolutegravir was administered at the time of conception and in early pregnancy. A subsequent analysis was conducted based on a larger cohort from the birth outcome surveillance study in Botswana and included over 9,460 individuals exposed to dolutegravir at conception, 23,664 individuals exposed to non-dolutegravir-containing regimens, and 170,723 HIV-negative pregnant individuals.
The prevalence of neural tube defects in infants delivered to individuals taking dolutegravir at conception was 0.11% (95% CI: 0.05-0.19%). The observed prevalence rate did not differ significantly from that of infants delivered to individuals taking non-dolutegravir-containing regimens (0.11%, 95% CI: 0.07-0.16%), or to HIV-negative individuals (0.06%, 95% CI: 0.05-0.08%). The Eswatini birth outcome surveillance study includes 9,743 individuals exposed to dolutegravir at conception,…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in individuals exposed to TRIUMEQ during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1‑800‑258‑4263. Risk Summary Data from two, ongoing birth outcome surveillance studies in Botswana and Eswatini which together include over 14,000 individuals evaluated during pregnancy show similar prevalence of neural tube defects among infants born to individuals taking dolutegravir at the time of conception compared to those born to individuals taking non-dolutegravir-containing regimens at conception or infants born to HIV-negative individuals (see Data).
There are insufficient human data on the use of TRIUMEQ during pregnancy to definitively assess a drug-associated risk for birth defects and miscarriage. However, available human data from the APR with the individual components of TRIUMEQ do not indicate an increased risk of birth defects (see Data) . The background risk for major birth defects for the indicated population is unknown.
In the U.S. general population, the estimated background rate for major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. In animal reproduction studies, no evidence of adverse developmental outcomes (including neural tube defects) was observed with dolutegravir at systemic exposures (AUC) less than (rabbits) and approximately 50 times (rats) the exposure in humans at the recommended human dose (RHD) (see Data) . Oral administration of abacavir to pregnant rats during organogenesis resulted in fetal malformations and other embryonic and fetal toxicities at exposures 35 times the human exposure (AUC) at the RHD.
No adverse developmental effects were observed following oral administration of abacavir to pregnant rabbits during organogenesis at exposures approximately 9 times the human exposure (AUC) at the RHD. Oral administration of lamivudine to pregnant rabbits during organogenesis resulted in embryolethality at a human exposure (AUC) similar to the RHD; however, no adverse development effects were observed with oral administration of lamivudine to pregnant rats during organogenesis at plasma concentrations (C max ) 35 times the RHD (see Data).
Data Human Data: Dolutegravir: Observational studies: The first interim analysis from an ongoing birth outcome surveillance study in Botswana identified an association between dolutegravir and an increased risk of neural tube defects when dolutegravir was administered at the time of conception and in early pregnancy. A subsequent analysis was conducted based on a larger cohort from the birth outcome surveillance study in Botswana and included over 9,460 individuals exposed to dolutegravir at conception, 23,664 individuals exposed to non-dolutegravir-containing regimens, and 170,723 HIV-negative pregnant individuals.
The prevalence of neural tube defects in infants delivered to individuals taking dolutegravir at conception was 0.11% (95% CI: 0.05-0.19%). The observed prevalence rate did not differ significantly from that of infants delivered to individuals taking non-dolutegravir-containing regimens (0.11%, 95% CI: 0.07-0.16%), or to HIV-negative individuals (0.06%, 95% CI: 0.05-0.08%). The Eswatini birth outcome surveillance study includes 9,743 individuals exposed to dolutegravir at conception, 1,838 individuals exposed to non-dolutegravir-containing regimens, and 32,259 HIV-negative pregnant individuals.
The prevalence of neural tube defects in infants delivered to individuals taking dolutegravir at conception was 0.08% (95% CI: 0.04-0.16%). The observed prevalence rate did not differ significantly from that of infants delivered to individuals taking non-dolutegravir-containing regimens (0.22%, 95% CI: 0.06-0.56%) or to HIV-negative individuals (0.08%, 95% CI: 0.06-0.12%). The observed prevalence of neural tube de…
🆘 Overdosage ▾
10 OVERDOSAGE There is no known specific treatment for overdose with TRIUMEQ or TRIUMEQ PD. If overdose occurs, the patient should be monitored, and standard supportive treatment applied as required. Dolutegravir As dolutegravir is highly bound to plasma proteins, it is unlikely that it will be significantly removed by dialysis.
Abacavir It is not known whether abacavir can be removed by peritoneal dialysis or hemodialysis. Lamivudine Because a negligible amount of lamivudine was removed via (4-hour) hemodialysis, continuous ambulatory peritoneal dialysis, and automated peritoneal dialysis, it is not known if continuous hemodialysis would provide clinical benefit in a lamivudine overdose event.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action TRIUMEQ and TRIUMEQ PD are a fixed-dose combination of the HIV‑1 antiretroviral agents abacavir, dolutegravir, and lamivudine [see Microbiology ( 12.4 )].
12.2Pharmacodynamics Effects on Electrocardiogram A thorough QT trial has been conducted for dolutegravir. Neither the effects of abacavir nor lamivudine as single entities or the combination of abacavir, dolutegravir, and lamivudine on the QT interval have been evaluated. In a randomized, placebo-controlled, cross-over trial, 42 healthy subjects received single-dose oral administrations of placebo, dolutegravir 250‑mg suspension (exposures approximately 3–fold of the 50-mg once-daily dose at steady state), and moxifloxacin 400 mg (active control) in random sequence.
After baseline and placebo adjustment, the maximum mean QTc change based on Fridericia correction method (QTcF) for dolutegravir was 2.4 msec (1-sided 95% upper CI: 4.9 msec). Dolutegravir did not prolong the QTc interval over 24 hours postdose. Effects on Renal Function The effect of dolutegravir on renal function was evaluated in an open-label, randomized, 3-arm, parallel, placebo-controlled trial in healthy subjects (n = 37) who received dolutegravir 50 mg once daily (n = 12), dolutegravir 50 mg twice daily (n = 13), or placebo once daily (n = 12) for 14 days.
A decrease in creatinine clearance, as determined by 24-hour urine collection, was observed with both doses of dolutegravir after 14 days of treatment in subjects who received 50 mg once daily (9% decrease) and 50 mg twice daily (13% decrease). Neither dose of dolutegravir had a significant effect on the actual glomerular filtration rate (determined by the clearance of probe drug, iohexol) or effective renal plasma flow (determined by the clearance of probe drug, para-amino hippurate) compared with the placebo.
12.3Pharmacokinetics Pharmacokinetics in Adults One TRIUMEQ tablet was bioequivalent to one dolutegravir (TIVICAY) tablet (50 mg) plus one abacavir and lamivudine fixed-dose combination tablet (EPZICOM) under fasted conditions in healthy subjects (n = 62). TRIUMEQ tablets and TRIUMEQ PD tablets for oral suspension are bioequivalent for the abacavir and lamivudine components, but not for the dolutegravir component. The relative dolutegravir bioavailability of TRIUMEQ PD is approximately 1.7-fold higher than TRIUMEQ; therefore, the 2 dosage forms are not substitutable on a milligram-per-milligram basis [see Dosage and Administration ( 2.3 ), Warnings and Precautions ( 5.7 )] .
The relative dolutegravir bioavailability is expected to be similar between TRIUMEQ PD and TIVICAY PD. Abacavir: Following oral administration, abacavir is rapidly absorbed and extensively distributed. After oral administration of a single dose of 600 mg of abacavir in 20 subjects, C max was 4.26 ± 1.19 mcg/mL (mean ± SD) and AUC ∞ was 11.95 ± 2.51 mcg•hour/mL.
Binding of abacavir to human plasma proteins is approximately 50% and was independent of concentration. Total blood and plasma drug‑related radioactivity concentrations are identical, demonstrating that abacavir readily distributes into erythrocytes. The primary routes of elimination of abacavir are metabolism by alcohol dehydrogenase to form the 5′‑carboxylic acid and glucuronyl transferase to form the 5′‑glucuronide.
In single-dose trials, the observed elimination half-life (t ½ ) was 1.54 ± 0.63 hours. After intravenous administration, total clearance was 0.80 ±
0.24L/h/kg (mean ± SD). Dolutegravir: Following oral administration of dolutegravir, peak plasma concentrations were observed 2 to 3 hours postdose. With once-daily dosing, pharmacokinetic steady state is achieved within approximately 5 days with average accumulation ratios for AUC, C max , and C 24 h ranging from 1.2 to 1.5.
Dolutegravir is a P-gp substrate in vitro. The absolute bioavailability of dolutegravir has not been established. Dolutegravir is highly bound (≥98.9%) to human plasma proteins based…
🧬 Mechanism of Action ▾
12.1Mechanism of Action TRIUMEQ and TRIUMEQ PD are a fixed-dose combination of the HIV‑1 antiretroviral agents abacavir, dolutegravir, and lamivudine [see Microbiology ( 12.4 )].
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING TRIUMEQ tablets TRIUMEQ tablets are purple, oval, film-coated, biconvex tablets debossed with “572 Tri” on one side and contain 600 mg of abacavir (as abacavir sulfate), 50 mg of dolutegravir (as dolutegravir sodium), and 300 mg lamivudine. Bottle of 30 tablets with desiccant and child-resistant closure. NDC 49702-231-13.
Store and dispense in the original package, protect from moisture, and keep the bottle tightly closed. Do not remove desiccant. Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C and 30°C (59°F to 86°F). [See USP Controlled Room Temperature].
TRIUMEQ PD tablets for oral suspension TRIUMEQ PD tablets for oral suspension, are yellow, capsule-shaped, strawberry cream flavored, film-coated, biconvex tablets debossed with “SV WTU” on one side and contain 60 mg of abacavir (as abacavir sulfate), 5 mg of dolutegravir (as dolutegravir sodium), and 30 mg lamivudine. Bottle of 90 tablets (NDC 49702-272-59) with desiccant and child-resistant closure. Each bottle is packaged as a kit (NDC 49702-258-37) with one 40-mL dosing cup.
Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C and 30°C (59°F to 86°F). [See USP Controlled Room Temperature]. Store and dispense in the original bottle, protect from moisture, and keep the bottle tightly closed. Do not remove desiccant.
📋 Description ▾
11 DESCRIPTION TRIUMEQ and TRIUMEQ PD TRIUMEQ and TRIUMEQ PD contain an INSTI (dolutegravir) and 2 nucleoside analogues (abacavir and lamivudine) with inhibitory activity against HIV. Each film-coated tablet of TRIUMEQ, for oral use, contains 600 mg of abacavir (present as 702 mg of abacavir sulfate), 50 mg of dolutegravir (present as 52.6 mg of dolutegravir sodium), and 300 mg of lamivudine. The inactive ingredients of TRIUMEQ tablets include D-mannitol, magnesium stearate, microcrystalline cellulose, povidone, and sodium starch glycolate.
The tablet film‑coating contains the inactive ingredients iron oxide black, iron oxide red, macrogol/PEG, polyvinyl alcohol–part hydrolyzed, talc, and titanium oxide. Each film-coated tablet of TRIUMEQ PD for oral suspension contains 60 mg of abacavir (present as 70.2 mg of abacavir sulfate), 5 mg of dolutegravir (present as 5.26 mg of dolutegravir sodium), and 30 mg of lamivudine. The inactive ingredients of TRIUMEQ PD tablets include acesulfame potassium, crospovidone, mannitol, microcrystalline cellulose, povidone K29/32, silicified microcrystalline cellulose, sodium starch glycolate, sodium stearyl fumarate, strawberry cream flavor and sucralose.
The tablet film-coating contains the inactive ingredients: ferric oxide yellow, macrogol/PEG, polyvinyl alcohol-part hydrolyzed, talc and titanium dioxide. Abacavir Sulfate The chemical name of abacavir sulfate is ( 1 S,cis)- 4-[2-amino-6-(cyclopropylamino)-9 H -purin-9-yl]-2-cyclopentene-1-methanol sulfate (salt) (2:1). It has a molecular formula of (C 14 H 18 N 6 O) 2• H 2 SO 4 and a molecular weight of 670.76 g/mol.
It has the following structural formula: Abacavir sulfate is a white to off-white solid and is soluble in water. Dolutegravir Sodium The chemical name of dolutegravir sodium is sodium (4 R ,12a S )-9-{[(2,4-difluorophenyl)methyl]carbamoyl}-4-methyl-6,8-dioxo-3,4,6,8,12,12a-hexahydro-2 H -pyrido[1',2':4,5]pyrazino[2,1- b ][1,3]oxazin-7-olate. The empirical formula is C 20 H 18 F 2 N 3 NaO 5 and the molecular weight is 441.36 g/mol.
It has the following structural formula: Dolutegravir sodium is a white to light yellow powder and is slightly soluble in water. Lamivudine The chemical name of lamivudine is (2R,cis)-4-amino-1-(2-hydroxymethyl-1,3-oxathiolan-5-yl)-(1H)-pyrimidin-2-one. Lamivudine is the (‑)enantiomer of a dideoxy analogue of cytidine.
Lamivudine has also been referred to as (‑)2′,3′-dideoxy, 3′-thiacytidine. It has a molecular formula of C 8 H 11 N 3 O 3 S and a molecular weight of 229.3 g/mol. It has the following structural formula: Lamivudine is a white to off-white crystalline solid and is soluble in water.
Abacavir sulfate chemical structure Dolutegravir sodium chemical structure Lamivudine chemical structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide and Instructions for Use). Drug Interactions TRIUMEQ or TRIUMEQ PD may interact with many drugs; therefore, advise patients to report to their healthcare provider the use of any other prescription or nonprescription medication or herbal products, including St. John’s wort [see Contraindications ( 4 ), Warnings and Precautions ( 5.5 ), Drug Interactions ( 7 )].
Hypersensitivity Reaction Inform patients: • that a Medication Guide and Warning Card summarizing the symptoms of the abacavir hypersensitivity reaction and other product information will be dispensed by the pharmacist with each new prescription and refill of TRIUMEQ or TRIUMEQ PD, and instruct the patient to read the Medication Guide and Warning Card every time to obtain any new information that may be present about TRIUMEQ or TRIUMEQ PD. The complete text of the Medication Guide is reprinted at the end of this document. • to carry the Warning Card with them. • how to identify a hypersensitivity reaction [see Warnings and Precautions ( 5.1 ), Medication Guide] . • that if they develop symptoms consistent with a hypersensitivity reaction they should call their healthcare provider right away to determine if they should stop taking TRIUMEQ or TRIUMEQ PD. • that a hypersensitivity reaction can worsen and lead to hospitalization or death if TRIUMEQ or TRIUMEQ PD is not immediately discontinued. • to not restart TRIUMEQ or TRIUMEQ PD or any other abacavir‑containing product following a hypersensitivity reaction because more severe symptoms can occur within hours and may include life‑threatening hypotension and death. • that if they have a hypersensitivity reaction, they should dispose of any unused TRIUMEQ or TRIUMEQ PD to avoid restarting abacavir. • that a hypersensitivity reaction is usually reversible if it is detected promptly and TRIUMEQ or TRIUMEQ PD is stopped right away. • that if they have interrupted TRIUMEQ or TRIUMEQ PD for reasons other than symptoms of hypersensitivity (for example, those who have an interruption in drug supply), a serious or fatal hypersensitivity reaction may occur with reintroduction of abacavir. • to not restart TRIUMEQ or TRIUMEQ PD or any other abacavir‑containing product without medical consultation and only if medical care can be readily accessed by the patient or others. • to not restart TRIUMEQ or TRIUMEQ PD or any other dolutegravir-containing product following a hypersensitivity reaction to TRIUMEQ or TRIUMEQ PD.
Hepatotoxicity Inform patients that hepatotoxicity has been reported with dolutegravir, a component of TRIUMEQ and TRIUMEQ PD [see Warnings and Precautions ( 5.3 ), Adverse Reactions ( 6.1 )] . Inform patients that monitoring for hepatotoxicity during therapy with TRIUMEQ or TRIUMEQ PD is recommended. Severe Acute Exacerbations of Hepatitis in Patients with HBV Co-infection Advise all patients with HIV-1 to be tested for the presence of HBV prior to or when initiating TRIUMEQ or TRIUMEQ PD.
Advise patients co‑infected with HIV‑1 and HBV that worsening of liver disease has occurred in some cases when treatment with lamivudine was discontinued. Advise patients to discuss any changes in regimen with their physician [see Warnings and Precautions ( 5.2 )]. Lactic Acidosis/Hepatomegaly Inform patients that some HIV medicines, including TRIUMEQ and TRIUMEQ PD, can cause a rare, but serious condition called lactic acidosis with liver enlargement (hepatomegaly) [see Boxed Warning , Warnings and Precautions ( 5.4 )] .
Immune Reconstitution Syndrome Advise patients to inform their healthcare provider immediately of any signs and symptoms of infection as inflammation from previous infection may occur soon after combination antiretroviral therapy, including when TRIUMEQ or TRIUMEQ PD is started [see Warnings and Precautions ( 5.6 )]. TRIUMEQ Tablets and TRIUMEQ PD Tablets for Oral Suspension Are Not Bioequivalent Advise patie…
💬 Medication Guide ▾
MEDICATION GUIDE TRIUMEQ (TRI-u-meck) (abacavir, dolutegravir, and lamivudine) tablets TRIUMEQ PD (TRI-u-meck Pe De) (abacavir, dolutegravir, and lamivudine) tablets for oral suspension What is the most important information I should know about TRIUMEQ and TRIUMEQ PD? TRIUMEQ and TRIUMEQ PD can cause serious side effects, including: • Serious allergic reactions (hypersensitivity reaction) that can cause death have happened with TRIUMEQ or TRIUMEQ PD and other abacavir-containing products. Your risk of this allergic reaction to abacavir is much higher if you have a gene variation called HLA‑B*5701.
Your healthcare provider can determine with a blood test if you have this gene variation. If you get a symptom from 2 or more of the following groups while taking TRIUMEQ or TRIUMEQ PD, call your healthcare provider right away to find out if you should stop taking TRIUMEQ or TRIUMEQ PD. Symptom(s) Group 1 Fever Group 2 Rash Group 3 Nausea, vomiting, diarrhea, abdominal (stomach area) pain Group 4 Generally ill feeling, extreme tiredness, or achiness Group 5 Shortness of breath, cough, sore throat A list of these symptoms is on the Warning Card your pharmacist gives you.
Carry this Warning Card with you at all times. If you stop TRIUMEQ or TRIUMEQ PD because of an allergic reaction, never take TRIUMEQ, TRIUMEQ PD (abacavir, dolutegravir and lamivudine), or any other medicine that contains abacavir or dolutegravir (DOVATO, EPZICOM, JULUCA, TIVICAY, TIVICAY PD, TRIZIVIR, or ZIAGEN) again. • If you have an allergic reaction, dispose of any unused TRIUMEQ or TRIUMEQ PD. Ask your pharmacist how to properly dispose of medicines. • If you take TRIUMEQ, TRIUMEQ PD or any other abacavir‑containing medicine again after you have had an allergic reaction, within hours you may get life‑threatening symptoms that may include very low blood pressure or death. • If you stop TRIUMEQ or TRIUMEQ PD for any other reason, even for a few days, and you are not allergic to TRIUMEQ or TRIUMEQ PD, talk with your healthcare provider before taking it again.
Taking TRIUMEQ or TRIUMEQ PD again can cause a serious allergic or life‑threatening reaction, even if you never had an allergic reaction to it before. If your healthcare provider tells you that you can take TRIUMEQ or TRIUMEQ PD again, start taking it when you are around medical help or people who can call a healthcare provider if you need one. • Worsening of Hepatitis B virus (HBV) infection. Your healthcare provider will test you for HBV infection before you start treatment with TRIUMEQ or TRIUMEQ PD.
If you have HBV infection and take TRIUMEQ or TRIUMEQ PD, your HBV may get worse (flare-up) if you stop taking TRIUMEQ or TRIUMEQ PD. A “flare-up” is when your HBV infection suddenly returns in a worse way than before. o Do not run out of TRIUMEQ or TRIUMEQ PD. Refill your prescription or talk to your healthcare provider before your TRIUMEQ or TRIUMEQ PD is all gone. o Do not stop TRIUMEQ or TRIUMEQ PD without first talking to your healthcare provider. o If you stop taking TRIUMEQ or TRIUMEQ PD, your healthcare provider will need to check your health often and do blood tests regularly for several months to check your liver function and monitor your HBV infection.
It may be necessary to give you a medicine to treat hepatitis B. Tell your healthcare provider about any new or unusual symptoms you may have after you stop taking TRIUMEQ or TRIUMEQ PD. • Resistant HBV. If you have human immunodeficiency virus-1 (HIV-1) and HBV, the HBV can change (mutate) during your treatment with TRIUMEQ or TRIUMEQ PD and become harder to treat (resistant).
Your healthcare provider may give you other medicines to treat HBV infection if you have HIV-1 and HBV infections and take TRIUMEQ or TRIUMEQ PD. • For more information about side effects, see “What are the possible side effects of TRIUMEQ or TRIUMEQ PD?” What is TRIUMEQ and TRIUMEQ PD? TRIUMEQ and TRIUMEQ PD are prescription medicines used to treat HIV-1 infection in adults and…