
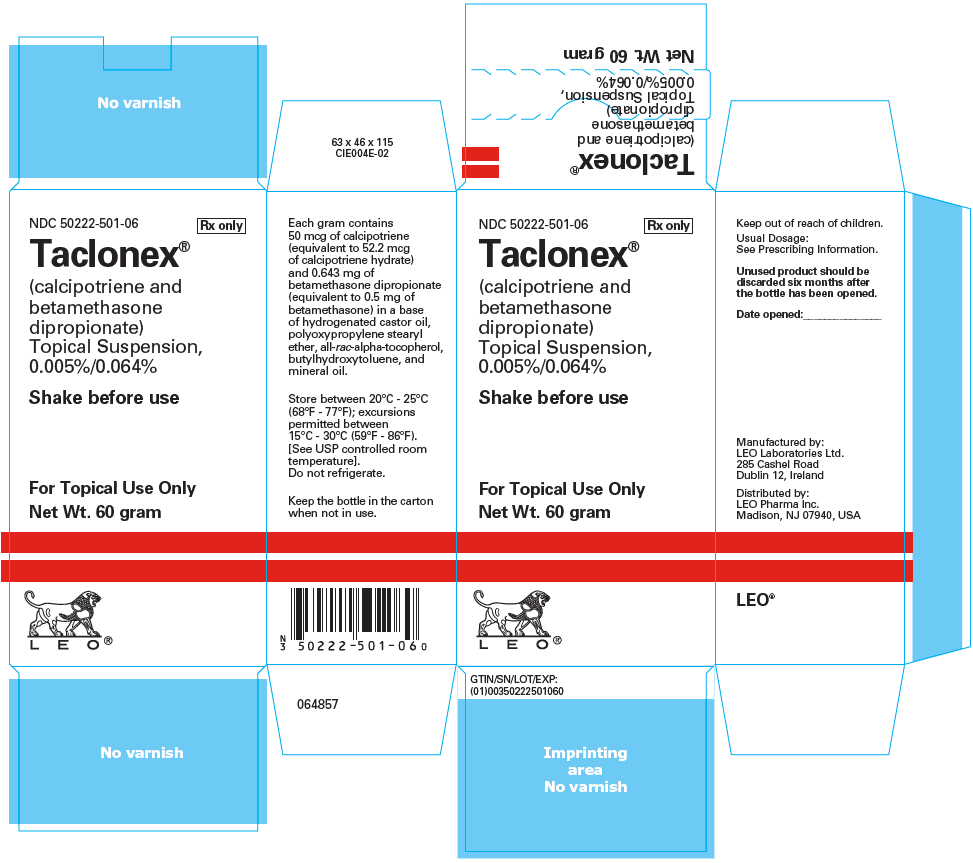
TACLONEX calcipotriene and betamethasone dipropionate 50 ug/g; .5 mg/g Suspension
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Corticosteroid class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- It works on two fronts at once. The betamethasone part is a strong steroid that calms down the inflammation causing your redness and itch. The calcipotriene part is a form of vitam...
- What exactly is this medication supposed to do for my psoriasis?
- Apply it to the affected areas once daily, rub it in gently, and always wash your hands after. If you're using a suspension or solution for your scalp, shake the bottle first and d...
- How do I apply this correctly — is there anything I should know before I start?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 7QWA1RIO01
A synthetic form of vitamin E used as an antioxidant in medicines. It prevents oils and fats in the formulation from breaking down, helping the drug remain stable and effective during storage.
-
UNII 1P9D0Z171K
BHT is a synthetic antioxidant that prevents fats and oils in medicines from breaking down and becoming rancid. It helps keep the product stable and effective during storage.
-
UNII ZF94AP8MEY
Hydrogenated castor oil is a processed plant oil made by adding hydrogen to castor oil. It's used as a binder to help hold tablet ingredients together and as a lubricant to prevent sticking during manufacturing.
-
UNII T5L8T28FGP
Mineral oil is a clear, odorless liquid derived from crude oil. It acts as a lubricant and emollient in medications, helping pills slide smoothly during manufacturing and aiding moisture retention in topical products.
-
UNII S4G2J0Y0LG
PPG-11 stearyl ether is a synthetic compound made from propylene glycol and stearyl alcohol. It acts as an emulsifier and solubilizer in medicines, helping blend oil and water-based ingredients and improve how the drug dissolves or spreads.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per g | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $20.697 | $49,672.32 / 2400 g |
| Medicaid paysCMS SDUD · 12 mo | $20.85 | $50,038.80 / 2400 g |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| calcipotriene and betamethasone dipropionate .5 mg/g; 50 ug/g 00713-0848-60 | Cosette | 1 bottle | $1.412 | AB | Availability likely | save 93% |
| Calcipotriene and Betamethasone Dipropionate 50 ug/g; 50 mg/g 51672-1402-04 | Sun | 1 bottle | $1.412 | AB | Availability likely | save 93% |
| Taclonex 50 ug/g; .5 mg/gthis 50222-0501-06 | LEO | 1 bottle | $20.697 | AB | Availability likely | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 50222-0501-06 You're viewing this | 40 CARTON in 1 CASE (50222-501-06) / 1 BOTTLE in 1 CARTON / 60 g in 1 BOTTLE | $20.70 / g | $49,672.32 | 2008-06-01 | Active |
| 50222-0501-66 | 10 PACKAGE in 1 BOX (50222-501-66) / 2 BOTTLE in 1 PACKAGE / 60 g in 1 BOTTLE | $20.72 / g | $24,860.16 | 2008-06-01 | Active |
This pack has the lowest per-g cost of the 2 priced pack sizes ($20.70 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 96% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 50222-0501-06?
What NDC number is used to bill for this package of TACLONEX calcipotriene and betamethasone dipropionate 50 ug/g; .5 mg/g Suspension?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Taclonex ® Topical Suspension is indicated for the topical treatment of plaque psoriasis of the scalp and body in patients 12 years and older. Taclonex Topical Suspension is a combination of calcipotriene, a vitamin D analog, and betamethasone dipropionate, a corticosteroid, indicated for the topical treatment of plaque psoriasis of the scalp and body in patients 12 years and older. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Instruct patients to shake bottle prior to using Taclonex Topical Suspension. Apply Taclonex Topical Suspension to affected areas on the scalp and body once daily for up to 8 weeks. Taclonex Topical Suspension should be discontinued when control is achieved.
Instruct patients to wash their hands after applying the product. Inform patients that they should not take a bath or shower or wash their hair right after application of Taclonex Topical Suspension. Patients 12 to 17 years should not use more than 60 grams per week and patients 18 years and older should not use more than 100 grams per week.
Taclonex Topical Suspension should not be: Used with occlusive dressings unless directed by a healthcare provider. Used on the face, groin, or axillae, or if skin atrophy is present at the treatment site. Applied to the scalp in the 12 hours before or after any chemical treatments to the hair.
Taclonex Topical Suspension is not for oral, ophthalmic, or intravaginal use. Shake bottle before use. ( 2 ) Apply Taclonex Topical Suspension to affected areas on the scalp and body once daily for up to 8 weeks.
Discontinue therapy when control is achieved. ( 2 ) Patients age 12 to 17 years should not use more than 60 grams per week.( 2 ) Adult patients should not use more than 100 grams per week. ( 2 ) Do not use with occlusive dressings unless directed by a healthcare provider.
( 2 ) Avoid use on the face, groin, or axillae, or if skin atrophy is present at the treatment site. ( 2 ) Not for oral, ophthalmic, or intravaginal use. ( 2 )
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Topical Suspension: 0.005%/0.064% - each gram contains 50 mcg of calcipotriene and 0.643 mg of betamethasone dipropionate in a viscous, nearly odorless, almost clear, colorless to slightly off-white suspension. Topical Suspension: 0.005%/0.064% - each gram of Taclonex Topical Suspension contains 50 mcg of calcipotriene and 0.643 mg of betamethasone dipropionate. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypercalcemia and Hypercalciuria: Hypercalcemia and hypercalciuria have been reported. If either occurs, discontinue until parameters of calcium metabolism normalize. ( 5.1 ) Effects on Endocrine System: Can cause reversible hypothalamic-pituitary-adrenal (HPA) axis suppression with the potential for glucocorticosteroid insufficiency during and after withdrawal of treatment.
Risk factors include the use of high-potency topical corticosteroid, use over a large surface area or to areas under occlusion, prolonged use, altered skin barrier, liver failure, and use in pediatric patients. Modify use should HPA axis suppression develop. ( 5.2 , 8.4 ) Ophthalmic Adverse Reactions: May increase the risk of cataracts and glaucoma.
If visual symptoms occur, consider referral to an ophthalmologist. ( 5.5 )
5.1Hypercalcemia and Hypercalciuria Hypercalcemia and hypercalciuria have been observed with use of Taclonex Topical Suspension. If hypercalcemia or hypercalciuria develop, discontinue treatment until parameters of calcium metabolism have normalized. The incidence of hypercalcemia and hypercalciuria following Taclonex Topical Suspension treatment of more than 8 weeks has not been evaluated [see Clinical Pharmacology (12.2) ].
5.2Effects on Endocrine System Hypothalamic-Pituitary-Adrenal Axis Suppression Taclonex Topical Suspension can cause reversible hypothalamic-pituitary-adrenal (HPA) axis suppression with the potential for clinical glucocorticosteroid insufficiency. This may occur during treatment or upon withdrawal of treatment. Factors that predispose a patient to HPA axis suppression include the use of high-potency steroids, large treatment surface areas, prolonged use, use of occlusive dressings, altered skin barrier, liver failure, and young age.
Evaluation for HPA axis suppression may be done by using the adrenocorticotropic hormone (ACTH) stimulation test. If HPA axis suppression is documented, gradually withdraw Taclonex Topical Suspension, reduce the frequency of application, or substitute with a less potent corticosteroid. The following trials evaluated the effects of Taclonex Topical Suspension on HPA axis suppression: In a trial evaluating the effects of Taclonex Topical Suspension and Taclonex Ointment on the HPA axis, 32 adult subjects applied both Taclonex Topical Suspension on the scalp and Taclonex Ointment on the body.
Adrenal suppression was identified in 5 of 32 subjects (16%) after 4 weeks of treatment and in 2 of 11 subjects (18%) who continued treatment for 8 weeks. In another trial, 36 adult subjects applied Taclonex Topical Suspension on the body and scalp and 7 subjects applied Taclonex Topical Suspension on the body. Adrenal suppression occurred in 3 out of 43 subjects (7%) after 4 weeks of treatment and in none of the 36 subjects who continued treatment for 8 weeks [ see Clinical Pharmacology (12.2) ].
In two trials, the effects of Taclonex Topical Suspension on the HPA axis were evaluated in 31 and 30 pediatric subjects aged 12 to 17 years old who applied Taclonex Topical suspension on the scalp and the scalp/body, respectively. Adrenal suppression occurred in 1 of 30 evaluable subjects (3%) after 4 weeks of treatment (scalp) and 5 of 31 evaluable subjects (16%) after up to 8 weeks of treatment (scalp and body) [see Use in Specific Populations (8.4) and Clinical Pharmacology (12.2) ]. Cushing's Syndrome and Hyperglycemia Cushing's syndrome and hyperglycemia may occur due to the systemic effects of the topical corticosteroid.
These complications are rare and generally occur after prolonged exposure to excessively large doses, especially of high-potency topical corticosteroids. Additional Considerations for Endocrine Adverse Reactions Pediatric patients may be more susceptible to systemic toxicity due to their larger skin surface to body mass ratios [see Use in Specific Populations (8.4) and Clinical Pharmacology (12.2) ]. Use of more than one corticosteroid-containing product a…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most common adverse reactions (≥ 1%) are folliculitis and burning sensation of skin. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact LEO Pharma Inc. at 1-877-494-4536 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Clinical Trials Conducted in Subjects 18 years and older with Psoriasis of the Scalp The rates of adverse reactions described below were from randomized, multicenter, vehicle- and/or active controlled clinical trials in adult subjects with psoriasis of the scalp [see Clinical Studies (14) ].
Subjects applied study product once daily for 8 weeks, and the median weekly dose was 12.6 grams. Adverse reactions that occurred in ≥ 1% of subjects treated with Taclonex Topical Suspension and at a rate higher than in subjects treated with vehicle are presented in Table 1. Table 1.
Number and Percentage of Subjects with Adverse Reactions in Scalp Psoriasis Trials (Events Reported by ≥1% of Subjects and for Which a Relationship is Possible) Taclonex Topical Suspension Betamethasone Dipropionate in vehicle Calcipotriene in vehicle Vehicle N=1,953 N=1,214 N=979 N=173 Event # of subjects (%) Folliculitis 16 (1%) 12 (1%) 5 (1%) 0 (0%) Burning sensation of skin 13 (1%) 10 (1%) 29 (3%) 0 (0%) Other less common adverse reactions (<1% but >0.1%) were, in decreasing order of incidence: acne, exacerbation of psoriasis, eye irritation, and pustular rash.
In a 52-week trial, adverse reactions that were reported by >1% of subjects treated with Taclonex Topical Suspension were pruritus (3.6%), psoriasis (2.4%), erythema (2.1%), skin irritation (1.4%), and folliculitis (1.2%). Clinical Trials Conducted in Subjects 18 years and older with Psoriasis of the Body In randomized, multicenter, vehicle- and/or active controlled clinical trials in adult subjects with plaque psoriasis on non-scalp areas, 824 subjects applied Taclonex Topical Suspension once daily for 8 weeks [see Clinical Studies (14) ].
The median weekly dose was 22.6 grams. There were no adverse reactions that occurred in ≥1% of subjects treated with Taclonex Topical Suspension and at a rate higher than in subjects treated with vehicle. Other less common adverse reactions (<1% but >0.1%) were, in decreasing order of incidence: rash and folliculitis.
Clinical Trials Conducted in Subjects 12 to 17 years with Psoriasis of the Scalp In two uncontrolled clinical trials, 109 subjects aged 12 to 17 years with plaque psoriasis of the scalp applied Taclonex ® Topical Suspension once daily for up to 8 weeks. The median weekly dose was 40 grams. Adverse reactions included acne, acneiform dermatitis and application site pruritus (0.9% each) [see Use in Specific Populations (8.4) and Clinical Pharmacology (12.2) ] .
Clinical Trial Conducted in Subjects 12 to 17 years with Psoriasis of the Scalp and Body In an uncontrolled clinical trial, 107 subjects aged 12 to 17 years with plaque psoriasis of the scalp and body applied Taclonex Topical Suspension once daily for up to 8 weeks. The median weekly dose was 26.6 grams. Adverse reactions were folliculitis, acne, and erythema (0.9% each) [see Use in Specific Populations (8.4) and Clinical Pharmacology (12.2) ] .
6.2Postmarketing Experience Because adverse reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Postmarketing reports for local adverse reactions to topical corticosteroids included atrophy, striae, telangiectasias, itching, dryness, hypopigmentation, perioral dermatitis, secondary infection, and miliaria. Ophthalmic adverse reactions of cataracts, glaucoma, increased intraocular pressur…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Available data with Taclonex Topical Suspension are not sufficient to evaluate a drug-associated risk for major birth defects, miscarriages, or adverse maternal or fetal outcomes. Although there are no available data on use of the calcipotriene component in pregnant women, systemic exposure to calcipotriene after topical administration of Taclonex Topical Suspension is likely to be low [see Clinical Pharmacology (12.3) ]. Observational studies suggest an increased risk of having low birth weight infants with the maternal use of potent or super potent topical corticosteroids ( see Data ).
Advise pregnant women that Taclonex Topical Suspension may increase the potential risk of having a low birth weight infant and to use Taclonex Topical Suspension on the smallest area of skin and for the shortest duration possible. In animal reproduction studies, oral administration of calcipotriene to pregnant rats during the period of organogenesis resulted in an increased incidence of minor skeletal abnormalities, including enlarged fontanelles and extra ribs ( see Data ). Oral administration of calcipotriene to pregnant rabbits during the period of organogenesis had no apparent effects on embryo-fetal development.
Subcutaneous administration of betamethasone dipropionate to pregnant rats and rabbits during the period of organogenesis resulted in fetal toxicity, including fetal deaths, reduced fetal weight, and fetal malformations (cleft palate and crooked or short tail) ( see Data ). The available data do not allow the calculation of relevant comparisons between the systemic exposures of calcipotriene and betamethasone dipropionate observed in animal studies to the systemic exposures that would be expected in humans after topical use of Taclonex Topical Suspension.
The estimated background risk of major birth defects and miscarriage of the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Human Data Available observational studies in pregnant women did not identify a drug-associated risk of major birth defects, preterm delivery, or fetal mortality with the use of topical corticosteroids of any potency. However, when the dispensed amount of potent or super potent topical corticosteroids exceeded 300 grams during the entire pregnancy, maternal use was associated with an increased risk of low birth weight in infants. Animal Data Embryo-fetal development studies with calcipotriene were performed by the oral route in rats and rabbits.
Pregnant rats received dosages of 0, 6, 18, or 54 mcg/kg/day (0, 36, 108, and 324 mcg/m 2 /day, respectively) on days 6-15 of gestation (the period of organogenesis). There were no apparent effects on maternal survival, behavior, or body weight gain, no effects on litter parameters, and no effects on the incidence of major malformations in fetuses. Fetuses from dams dosed at 54 mcg/kg/day exhibited a significantly increased incidence of minor skeletal abnormalities, including enlarged fontanelles and extra ribs.
Pregnant rabbits were dosed daily with calcipotriene at exposures of 0, 4, 12, or 36 mcg/kg/day (0, 48, 144, and 432 mcg/m 2 /day, respectively) on days 6-18 of gestation (the period of organogenesis). Mean maternal body weight gain was reduced in animals dosed at 12 or 36 mcg/kg/day. The incidence of fetal deaths was increased in the group dosed at 36 mcg/kg/day; reduced fetal weight was also observed in this group.
The incidence of major malformations among fetuses was not affected. An increase in the incidence of minor skeletal abnormalities, including incomplete ossification of sternebrae, pubic bones, and forelimb phalanges, was observed in the group dosed at 36 mcg/kg/day. Embryo-fetal develop…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data with Taclonex Topical Suspension are not sufficient to evaluate a drug-associated risk for major birth defects, miscarriages, or adverse maternal or fetal outcomes. Although there are no available data on use of the calcipotriene component in pregnant women, systemic exposure to calcipotriene after topical administration of Taclonex Topical Suspension is likely to be low [see Clinical Pharmacology (12.3) ]. Observational studies suggest an increased risk of having low birth weight infants with the maternal use of potent or super potent topical corticosteroids ( see Data ).
Advise pregnant women that Taclonex Topical Suspension may increase the potential risk of having a low birth weight infant and to use Taclonex Topical Suspension on the smallest area of skin and for the shortest duration possible. In animal reproduction studies, oral administration of calcipotriene to pregnant rats during the period of organogenesis resulted in an increased incidence of minor skeletal abnormalities, including enlarged fontanelles and extra ribs ( see Data ). Oral administration of calcipotriene to pregnant rabbits during the period of organogenesis had no apparent effects on embryo-fetal development.
Subcutaneous administration of betamethasone dipropionate to pregnant rats and rabbits during the period of organogenesis resulted in fetal toxicity, including fetal deaths, reduced fetal weight, and fetal malformations (cleft palate and crooked or short tail) ( see Data ). The available data do not allow the calculation of relevant comparisons between the systemic exposures of calcipotriene and betamethasone dipropionate observed in animal studies to the systemic exposures that would be expected in humans after topical use of Taclonex Topical Suspension.
The estimated background risk of major birth defects and miscarriage of the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Human Data Available observational studies in pregnant women did not identify a drug-associated risk of major birth defects, preterm delivery, or fetal mortality with the use of topical corticosteroids of any potency. However, when the dispensed amount of potent or super potent topical corticosteroids exceeded 300 grams during the entire pregnancy, maternal use was associated with an increased risk of low birth weight in infants. Animal Data Embryo-fetal development studies with calcipotriene were performed by the oral route in rats and rabbits.
Pregnant rats received dosages of 0, 6, 18, or 54 mcg/kg/day (0, 36, 108, and 324 mcg/m 2 /day, respectively) on days 6-15 of gestation (the period of organogenesis). There were no apparent effects on maternal survival, behavior, or body weight gain, no effects on litter parameters, and no effects on the incidence of major malformations in fetuses. Fetuses from dams dosed at 54 mcg/kg/day exhibited a significantly increased incidence of minor skeletal abnormalities, including enlarged fontanelles and extra ribs.
Pregnant rabbits were dosed daily with calcipotriene at exposures of 0, 4, 12, or 36 mcg/kg/day (0, 48, 144, and 432 mcg/m 2 /day, respectively) on days 6-18 of gestation (the period of organogenesis). Mean maternal body weight gain was reduced in animals dosed at 12 or 36 mcg/kg/day. The incidence of fetal deaths was increased in the group dosed at 36 mcg/kg/day; reduced fetal weight was also observed in this group.
The incidence of major malformations among fetuses was not affected. An increase in the incidence of minor skeletal abnormalities, including incomplete ossification of sternebrae, pubic bones, and forelimb phalanges, was observed in the group dosed at 36 mcg/kg/day. Embryo-fetal development studies with betamethason…
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of Taclonex Topical Suspension for the treatment of plaque psoriasis of the scalp and body have been established in pediatric patients age 12 to 17 years. The use of Taclonex Topical Suspension for this indication is supported by evidence from adequate and well-controlled trials in adults and from three uncontrolled trials in pediatric subjects that enrolled 109 adolescents with moderate psoriasis of the scalp and 107 adolescents with psoriasis of the scalp and body. After 4 weeks of once daily treatment with Taclonex Topical Suspension, HPA axis suppression was observed in 3% of adolescents with psoriasis of the scalp and 16% of adolescents with psoriasis of the scalp and body.
Calcium metabolism was evaluated in 107 adolescents with psoriasis of the scalp and body treated with Taclonex Topical Suspension and no cases of hypercalcemia or clinically relevant changes in urinary calcium were reported [see Warnings and Precautions (5.2) , Adverse Reactions (6.1) , and Clinical Pharmacology (12.2) ]. Because of a higher ratio of skin surface area to body mass, pediatric patients are at a greater risk than adults of systemic toxicity when treated with topical corticosteroids. Pediatric patients are, therefore, also at greater risk of HPA axis suppression and adrenal insufficiency with the use of topical corticosteroids including Taclonex ® Topical Suspension [see Clinical Pharmacology (12.2) ].
Rare systemic toxicities such as Cushing's syndrome, linear growth retardation, delayed weight gain, and intracranial hypertension have been reported in pediatric patients, especially those with prolonged exposure to large doses of high potency topical corticosteroids. Local adverse reactions including striae have also been reported with use of topical corticosteroids in pediatric patients. The safety and effectiveness of Taclonex Topical Suspension in pediatric patients less than 12 years of age have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of Taclonex Topical Suspension in plaque psoriasis on non-scalp areas included 124 subjects who were 65 years of age or older, and 36 were 75 years of age or older. Clinical studies of Taclonex Topical Suspension in subjects with psoriasis of the scalp included 334 subjects who were 65 years or older and 84 subjects who were 75 years or older. No overall differences in safety or effectiveness of Taclonex Topical Suspension were observed between these subjects and younger subjects, and other reported clinical experience has not identified any differences in responses between the elderly and younger subjects, but greater sensitivity of some older individuals cannot be ruled out.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Taclonex Topical Suspension combines the pharmacological effects of calcipotriene hydrate as a synthetic vitamin D 3 analog and betamethasone dipropionate as a synthetic corticosteroid. However, while their pharmacologic and clinical effects are known, the exact mechanisms of their actions in the treatment of plaque psoriasis of the scalp and body are unknown.
12.2Pharmacodynamics Hypothalamic-Pituitary-Adrenal (HPA) Axis Suppression: HPA axis suppression was evaluated in four trials (Trial A, B, C, and D) following the application of Taclonex Topical Suspension. In all these trials, adrenal suppression was defined by a 30-minute post-stimulation cortisol level ≤18 mcg/dL. In Trial A, HPA axis suppression was evaluated in adult subjects (N=32) with extensive psoriasis involving at least 30% of the scalp and, in total, 15-30% of the body surface area.
Treatment consisted of once daily application of Taclonex Topical Suspension on the scalp in combination with Taclonex Ointment on the body for 4 to 8 weeks. Adrenal suppression was observed in 5 of 32 subjects (16%) after 4 weeks of treatment and in 2 of 11 subjects (18%) who continued treatment for 8 weeks. In Trial B, HPA axis suppression was evaluated in adult subjects (N=43) with extensive psoriasis involving 15-30% of the body surface area (including the scalp).
Treatment consisted of once daily application of Taclonex Topical Suspension to the body (including the scalp in 36 out of 43 subjects) for 4 to 8 weeks. Adrenal suppression was observed in 3 out of 43 subjects (7%) after 4 weeks of treatment and in none of the 36 subjects (0%) who continued treatment for 8 weeks. In Trial C, HPA axis suppression was evaluated in pediatric subjects 12 to 17 years (N=30) with plaque psoriasis of the scalp involving at least 20% of the scalp area.
Treatment consisted of once daily application of Taclonex Topical Suspension to the affected area on the scalp for up to 8 weeks. Adrenal suppression was observed in 1 of 30 evaluable subjects (3%) after 4 weeks of treatment and in no subjects (0%) who continued treatment for 8 weeks [see Use in Specific Populations (8.4) ] . In Trial D, HPA axis suppression was evaluated in a subset of pediatric subjects aged 12 to 17 years (N=31) with plaque psoriasis of the scalp and body involving 10% to 29% of the body surface area.
Adrenal suppression was observed in 5 of 31 subjects (16%): 3 subjects after 4 weeks of treatment, 1 subject after 8 weeks of treatment, and 1 subject after both 4 and 8 weeks of treatment [see Use in Specific Populations (8.4) ] . Effects on Calcium Metabolism The effect on calcium metabolism was evaluated following the application of Taclonex Topical Suspension (these trials are described above). In Trial A, elevated urinary calcium levels outside the normal range were observed in two subjects (one at 4 weeks and one at 8 weeks).
In Trial B, there was no change in mean serum or urinary calcium levels. Elevated urinary calcium levels outside the normal range were observed in two subjects (one at 4 weeks and one at 8 weeks). In Trial C (N=109), including 31 subjects with at least 20% scalp involvement and 78 subjects with at least 10% scalp involvement, no cases of hypercalcemia and no clinically relevant changes in urinary calcium were reported.
In Trial D (N=107), no cases of hypercalcemia and no clinically relevant changes in urinary calcium were reported.
12.3Pharmacokinetics Absorption The systemic effect of Taclonex Topical Suspension in psoriasis was investigated in Trials A, B, and D [see Clinical Pharmacology (12.2) ]. In Trial A, the serum levels of calcipotriene and betamethasone dipropionate and their major metabolites were measured after 4 and 8 weeks of once daily application of Taclonex ® Topical Suspension on the scalp in combination with Taclonex Ointment on the body. Calcipotriene and betamethasone dipropionate were below the lower limit of quantification i…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Taclonex Topical Suspension combines the pharmacological effects of calcipotriene hydrate as a synthetic vitamin D 3 analog and betamethasone dipropionate as a synthetic corticosteroid. However, while their pharmacologic and clinical effects are known, the exact mechanisms of their actions in the treatment of plaque psoriasis of the scalp and body are unknown.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Taclonex (calcipotriene and betamethasone dipropionate) Topical Suspension, 0.005%/0.064% is a viscous, nearly odorless, almost clear, colorless to slightly off-white suspension. It is available as: 60 gram bottle (NDC 50222-501-06) 120 gram (2 bottles of 60 gram) (NDC 50222-501-66) Store between 20°C - 25°C (68°F - 77°F); excursions permitted between 15°C - 30°C (59°F - 86°F). [See USP controlled room temperature]. Do not refrigerate.
Keep the bottle in the carton when not in use. Unused product should be discarded six months after the bottle has been opened. Shake before use.
Keep out of reach of children.
📦 Storage and Handling ▾
Store between 20°C - 25°C (68°F - 77°F); excursions permitted between 15°C - 30°C (59°F - 86°F). [See USP controlled room temperature]. Do not refrigerate. Keep the bottle in the carton when not in use. Unused product should be discarded six months after the bottle has been opened. Shake before use. Keep out of reach of children.
📋 Description ▾
11 DESCRIPTION Taclonex Topical Suspension contains calcipotriene hydrate and betamethasone dipropionate. It is for topical use only. Calcipotriene hydrate is a synthetic vitamin D 3 analog.
Calcipotriene Hydrate Calcipotriene hydrate is a vitamin D analog and has the chemical name 9,10-secochola-5,7,10(19),22-tetraene-1,3,24-triol,24-cyclo-propyl-,monohydrate, (1α,3β,5Z,7E,22E,24S) with the empirical formula C 27 H 40 O 3 ∙H 2 O, a molecular weight of 430.6, and the following structural formula (calcipotriene hydrate is a white to almost white, crystalline compound): Betamethasone Dipropionate Betamethasone dipropionate is a synthetic corticosteroid and has the chemical name pregna-1,4-diene-3,20-dione-9-fluoro-11-hydroxy-16-methyl-17,21- bis (1-oxypropoxy)-(11β,16β), with the empirical formula C 28 H 37 FO 7 , a molecular weight of 504.6, and the following structural formula (betamethasone dipropionate is a white to almost white, crystalline powder): Taclonex ® Topical Suspension Each gram of Taclonex Topical Suspension contains 50 mcg of calcipotriene (equivalent to 52.2 mcg of calcipotriene hydrate) and 0.643 mg of betamethasone dipropionate (equivalent to 0.5 mg of betamethasone) in a base of hydrogenated castor oil, polyoxypropylene stearyl ether, all- rac -alpha-tocopherol, butylhydroxytoluene, and mineral oil.
Taclonex Topical Suspension is an odorless, clear to slightly off-white suspension. Chemical Structure Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See FDA-approved patient labeling ( Patient Information and Instructions for Use ). Administration Instructions Instruct pediatric patients (12 to 17 years) not to use more than 60 grams per week. Instruct adult patients (18 years and older) not to use more than 100 grams per week.
Instruct patients to discontinue therapy when control is achieved unless directed otherwise by the healthcare provider. Advise patients not to apply Taclonex ® Topical Suspension to the scalp in the 12 hours before or after any chemical treatments to the hair since hair treatments may involve strong chemicals. Talk with the healthcare provider first.
Inform patients that they should not take a bath or shower or wash their hair right after application of Taclonex Topical Suspension. Advise patients to avoid use of Taclonex Topical Suspension on the face, underarms, groin or eyes. If this medicine gets on face or in eyes, wash area right away.
Advise patients not to occlude the treatment area with a bandage or other covering unless directed by the healthcare provider. Instruct patients to shake bottle prior to using Taclonex Topical Suspension and to wash hands after application. Local Reactions and Skin Atrophy Advise patients that local reactions and skin atrophy are more likely to occur with occlusive use, prolonged use or use of higher potency corticosteroids.
Hypercalcemia and Hypercalciuria Advise patients that hypercalcemia and hypercalciuria have been observed with the use of Taclonex Topical Suspension [see Warnings and Precautions (5.1) ]. HPA Axis Suppression, Cushing's Syndrome, and Hyperglycemia Advise patients that Taclonex Topical Suspension can cause HPA axis suppression, Cushing's syndrome, and/or hyperglycemia [see Warnings and Precautions (5.2) ]. Ophthalmic Adverse Reactions Advise patients to avoid contact of Taclonex Topical Suspension with eyes and to report any visual symptoms [see Warnings and Precautions (5.5) ].
Possible Avoidance of Other Products Containing Calcipotriene or a Corticosteroid Instruct patients not to use other products containing calcipotriene or a corticosteroid with Taclonex Topical Suspension without first talking to the healthcare provider. Pregnancy and Lactation Advise pregnant women that Taclonex Topical Suspension may increase the potential risk of having a low birth weight infant and to use Taclonex Topical Suspension on the smallest area of skin and for the shortest duration possible [see Use in Specific Populations (8.1) ].
Advise breastfeeding women not to apply Taclonex Topical Suspension directly to the nipple and areola to avoid direct infant exposure [see Use in Specific Populations (8.2) ] .