
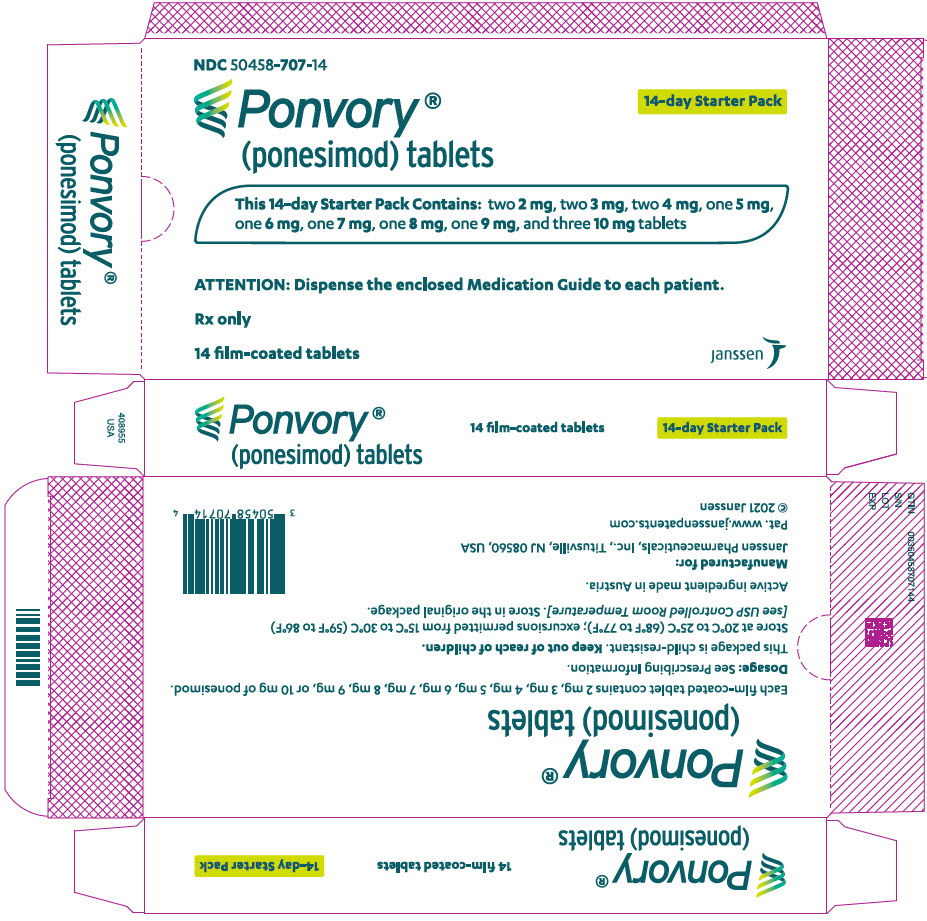
PONVORY Ponesimod Kit
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Sphingosine 1-phosphate Receptor Modulator class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Ponesimod is used to prevent episodes of symptoms and slow the worsening of disability in adults who have relapsing forms of multiple sclerosis (MS; a disease in which the nerves do not function properly and people may experience weakness, numbness, loss of muscle coordination, and problems with vision, speech, and bladder control) including, clinically isolated syndrome (CIS; nerve symptom episodes that last at least 24 hours), relapsing-remitting disease (course of disease where symptoms flare up from time to time), or active secondary progressive disesase (later stage of disease with contin...
Read the full MedlinePlus article ↗- Ponvory isn't a cure for MS, but it's a real treatment that can help control it. It's approved to treat relapsing forms of MS — meaning types where you have flare-ups (relapses) of...
- What exactly is Ponvory treating — is it curing my MS?
- That step-up schedule — called titration — is there to protect your heart. Ponvory can temporarily slow your heart rate, especially when you first start it. By gradually increasing...
- Why do I have to take so many different doses at the start instead of just jumping to my regular dose?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Ponesimod — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ponvory 43068-0610-09 | Vanda | 1 tablet | — | — | FDA listed | — |
| Ponvorythis 50458-0707-14 | Janssen | 1 tablet | — | — | Discontinued | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 12336980 ↗ | Method of use | U-3103 | Dec 10, 2035 |
| US 12336980 ↗ | Method of use | U-3103 | Dec 10, 2035 |
| US 12336980 ↗ | Method of use | U-3103 | Dec 10, 2035 |
| US 12336980 ↗ | Method of use | U-3103 | Dec 10, 2035 |
| US 12336980 ↗ | Method of use | U-3103 | Dec 10, 2035 |
| US 12336980 ↗ | Method of use | U-3103 | Dec 10, 2035 |
| US 12336980 ↗ | Method of use | U-3103 | Dec 10, 2035 |
| US 12336980 ↗ | Method of use | U-3103 | Dec 10, 2035 |
| US 12336980 ↗ | Method of use | U-3103 | Dec 10, 2035 |
| US 12336980 ↗ | Method of use | U-3103 | Dec 10, 2035 |
| US 11951097 ↗ | Method of use | U-3891 | Oct 10, 2042 |
| US 11951097 ↗ | Method of use | U-3891 | Oct 10, 2042 |
| US 11951097 ↗ | Method of use | U-3891 | Oct 10, 2042 |
| US 11951097 ↗ | Method of use | U-3891 | Oct 10, 2042 |
| US 9062014 ↗ | Drug substance | U-2774 | May 6, 2032 |
| US 9062014 ↗ | Drug substance | U-2774 | May 6, 2032 |
| US 9062014 ↗ | Drug substance | U-2774 | May 6, 2032 |
| US 9062014 ↗ | Drug substance | U-2774 | May 6, 2032 |
| US 9062014 ↗ | Drug substance | U-2774 | May 6, 2032 |
| US 9062014 ↗ | Drug substance | U-2774 | May 6, 2032 |
| US 9062014 ↗ | Drug substance | U-2774 | May 6, 2032 |
| US 9062014 ↗ | Drug substance | U-2774 | May 6, 2032 |
| US 9062014 ↗ | Drug substance | U-2774 | May 6, 2032 |
| US 9062014 ↗ | Drug substance | U-2774 | May 6, 2032 |
| US 10220023 ↗ | Method of use | U-3103 | Dec 10, 2035 |
| US 10220023 ↗ | Method of use | U-3103 | Dec 10, 2035 |
| US 10220023 ↗ | Method of use | U-3103 | Dec 10, 2035 |
| US 10220023 ↗ | Method of use | U-3103 | Dec 10, 2035 |
| US 10220023 ↗ | Method of use | U-3103 | Dec 10, 2035 |
| US 10220023 ↗ | Method of use | U-3103 | Dec 10, 2035 |
| US 10220023 ↗ | Method of use | U-3103 | Dec 10, 2035 |
| US 10220023 ↗ | Method of use | U-3103 | Dec 10, 2035 |
| US 10220023 ↗ | Method of use | U-3103 | Dec 10, 2035 |
| US 10220023 ↗ | Method of use | U-3103 | Dec 10, 2035 |
| US 11951097 ↗ | Method of use | U-3891 | Oct 10, 2042 |
| US 11951097 ↗ | Method of use | U-3891 | Oct 10, 2042 |
| US 11951097 ↗ | Method of use | U-3891 | Oct 10, 2042 |
| US 11951097 ↗ | Method of use | U-3891 | Oct 10, 2042 |
| US 11951097 ↗ | Method of use | U-3891 | Oct 10, 2042 |
| US 11951097 ↗ | Method of use | U-3891 | Oct 10, 2042 |
| US RE43728 ↗ | Drug substance | — | Nov 16, 2029 |
| US RE43728 ↗ | Drug substance | — | Nov 16, 2029 |
| US RE43728 ↗ | Drug substance | — | Nov 16, 2029 |
| US RE43728 ↗ | Drug substance | — | Nov 16, 2029 |
| US RE43728 ↗ | Drug substance | — | Nov 16, 2029 |
| US RE43728 ↗ | Drug substance | — | Nov 16, 2029 |
| US RE43728 ↗ | Drug substance | — | Nov 16, 2029 |
| US RE43728 ↗ | Drug substance | — | Nov 16, 2029 |
| US RE43728 ↗ | Drug substance | — | Nov 16, 2029 |
| US RE43728 ↗ | Drug substance | — | Nov 16, 2029 |
| Code | What it grants | Expires |
|---|---|---|
| NCE | New Chemical Entity (5-year) | Mar 18, 2026 |
| NCE | New Chemical Entity (5-year) | Mar 18, 2026 |
| NCE | New Chemical Entity (5-year) | Mar 18, 2026 |
| NCE | New Chemical Entity (5-year) | Mar 18, 2026 |
| NCE | New Chemical Entity (5-year) | Mar 18, 2026 |
| NCE | New Chemical Entity (5-year) | Mar 18, 2026 |
| NCE | New Chemical Entity (5-year) | Mar 18, 2026 |
| NCE | New Chemical Entity (5-year) | Mar 18, 2026 |
| NCE | New Chemical Entity (5-year) | Mar 18, 2026 |
| NCE | New Chemical Entity (5-year) | Mar 18, 2026 |
Is there a generic version of PONVORY 14-DAY STARTER PACK?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 50458-0707-14 You're viewing this | 1 KIT in 1 CARTON (50458-707-14) * 1 BLISTER PACK in 1 CARTON (50458-706-00) / 1 TABLET, FILM COATED in 1 BLISTER PACK * 1 BLISTER PACK in 1 CARTON (50458-709-00) / 1 TABLET, FILM COATED in 1 BLISTER PACK * 1 BLISTER PACK in 1 CARTON (50458-708-00) | 2021-03-18 | Discontinued by firm |
🧭 About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
What does the discontinued status mean for this NDC?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE PONVORY is indicated for the treatment of relapsing forms of multiple sclerosis (MS), to include clinically isolated syndrome, relapsing-remitting disease, and active secondary progressive disease, in adults. PONVORY is a sphingosine 1-phosphate receptor modulator indicated for the treatment of relapsing forms of multiple sclerosis (MS), to include clinically isolated syndrome, relapsing-remitting disease, and active secondary progressive disease, in adults. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Assessments are required prior to initiating PONVORY ( 2.1 ) Titration is required for treatment initiation ( 2.2 ) The recommended maintenance dosage is 20 mg taken orally once daily ( 2.2 ) First-dose monitoring is recommended for patients with sinus bradycardia, first- or second-degree [Mobitz type I] atrioventricular (AV) block, or a history of myocardial infarction or heart failure ( 2.3 )
2.1Assessments Prior to First Dose of PONVORY Before initiation of treatment with PONVORY, assess the following: Complete Blood Count Obtain a recent (i.e., within the last 6 months or after discontinuation of prior MS therapy) complete blood count (CBC), including lymphocyte count [see Warnings and Precautions (5.1) ] . Cardiac Evaluation Obtain an electrocardiogram (ECG) to determine whether preexisting conduction abnormalities are present. In patients with certain preexisting conditions, advice from a cardiologist should be sought and first-dose monitoring is recommended [see Dosage and Administration (2.3) and Warnings and Precautions (5.2) ] .
Determine whether patients are taking drugs that could slow heart rate or atrioventricular (AV) conduction [see Warnings and Precautions (5.2) and Drug Interactions (7.2 , 7.3) ] . Liver Function Tests Obtain recent (i.e., within the last 6 months) transaminase and bilirubin levels [see Warnings and Precautions (5.4) ] . Ophthalmic Evaluation Obtain an evaluation of the fundus, including the macula [see Warnings and Precautions (5.8) ] .
Current or Prior Medications with Immune System Effects If patients are taking anti-neoplastic, immunosuppressive, or immune-modulating therapies, or if there is a history of prior use of these drugs, consider possible unintended additive immunosuppressive effects before initiating treatment with PONVORY [see Warnings and Precautions (5.1 , 5.10) and Drug Interactions (7.1) ] . Vaccinations Test patients for antibodies to varicella zoster virus (VZV) before initiating PONVORY; VZV vaccination of antibody-negative patients is recommended prior to commencing treatment with PONVORY [see Warnings and Precautions (5.1) ] .
If live attenuated vaccine immunizations are required, administer at least 1 month prior to initiation of PONVORY.
2.2Recommended Dosage Maintenance Dosage After dose titration is complete (see Treatment Initiation ) , the recommended maintenance dosage of PONVORY is 20 mg taken orally once daily starting on Day 15. Administer PONVORY orally once daily. Swallow the tablet whole.
PONVORY can be taken with or without food. Treatment Initiation A starter pack must be used for patients initiating treatment with PONVORY [see How Supplied/Storage and Handling (16.1) ] . Initiate PONVORY treatment with a 14-day titration; start with one 2 mg tablet orally once daily and progress with the titration schedule as shown in Table 1 [see Warnings and Precautions (5.2) ] .
Table 1: Dose Titration Regimen Titration Day Daily Dose Days 1 and 2 2 mg Days 3 and 4 3 mg Days 5 and 6 4 mg Day 7 5 mg Day 8 6 mg Day 9 7 mg Day 10 8 mg Day 11 9 mg Days 12, 13, and 14 10 mg Maintenance Daily Dose Day 15 and thereafter 20 mg If dose titration is interrupted, missed dose instructions must be followed [see Dosage and Administration (2.4) ] .
2.3First Dose Monitoring in Patients with Certain Preexisting Cardiac Conditions Because initiation of PONVORY treatment results in a decrease in heart rate (HR), first-dose 4-hour monitoring is recommended for patients with sinus bradycardia [HR less than 55 beats per minute (bpm)], first- or second-degree [Mobitz type I] AV block, or a history of myocardial infarction or heart failure occurring more than 6 months prior to treatment initiation and in stable condition [see Warnings and Precautions (5.3) and Clinical Pharmacology (12.2) ] .
First Dose 4-Hour Monitoring Administer the first dose of PONVORY in a setting where resources to appropriately manage symptomatic bradycardia are available. Monitor pat…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS PONVORY is available as round, biconvex, film-coated tablets for oral use. PONVORY contains ponesimod in the following dosage strengths (see Table 2 ): Table 2: Dosage Form and Strengths for PONVORY Tablet Strength Tablet Color Tablet Size Tablet Debossing 2 mg White 5.0 mm "2" on one side and an arch on the other side. 3 mg Red 5.0 mm "3" on one side and an arch on the other side.
4 mg Purple 5.0 mm "4" on one side and an arch on the other side. 5 mg Green 8.6 mm "5" on one side and an arch and an "A" on the other side. 6 mg White 8.6 mm " 6 " on one side and an arch and an "A" on the other side.
7 mg Red 8.6 mm "7" on one side and an arch and an "A" on the other side. 8 mg Purple 8.6 mm "8" on one side and an arch and an "A" on the other side. 9 mg Brown 8.6 mm " 9 " on one side and an arch and an "A" on the other side.
10 mg Orange 8.6 mm "10" on one side and an arch and an "A" on the other side. 20 mg Yellow 8.6 mm "20" on one side and an arch and an "A" on the other side. Tablets: 2 mg, 3 mg, 4 mg, 5 mg, 6 mg, 7 mg, 8 mg, 9 mg, 10 mg, and 20 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS PONVORY is contraindicated in patients who: In the last 6 months, have experienced myocardial infarction, unstable angina, stroke, transient ischemic attack (TIA), decompensated heart failure requiring hospitalization, or Class III or IV heart failure [see Warnings and Precautions (5.2) ] Have presence of Mobitz type II second-degree, third-degree atrioventricular (AV) block, sick sinus syndrome, or sino-atrial block, unless patient has a functioning pacemaker [see Warnings and Precautions (5.2) ] In the last 6 months, experienced myocardial infarction, unstable angina, stroke, transient ischemic attack (TIA), decompensated heart failure requiring hospitalization, or Class III/IV heart failure ( 4 ) Presence of Mobitz type II second-degree, third-degree AV block, sick sinus syndrome, or sino-atrial block, unless the patient has a functioning pacemaker ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Infections : PONVORY may increase the risk of infections. Obtain a complete blood count (CBC) before initiating treatment. Monitor for infection during treatment and for 1–2 weeks after discontinuation.
Do not start PONVORY in patients with active infection. ( 5.1 ) Bradyarrhythmia and Atrioventricular Conduction Delays : PONVORY may result in a transient decrease in heart rate; titration is required for treatment initiation. Check an electrocardiogram (ECG) to assess for preexisting cardiac conduction abnormalities before starting PONVORY.
Consider cardiology consultation for conduction abnormalities or concomitant use with other drugs that decrease heart rate. ( 5.2 , 7.2 , 7.3 ) Respiratory Effects : May cause a decline in pulmonary function. Assess pulmonary function (e.g., spirometry) if clinically indicated.
( 5.3 ) Liver Injury : Discontinue if significant liver injury is confirmed. Obtain liver function tests before initiating PONVORY. ( 5.4 ) Increased Blood Pressure (BP) : Monitor BP during treatment.
( 5.5 ) Cutaneous Malignancies: Periodic skin examination is recommended. ( 5.6 ) Fetal Risk : Women of childbearing potential should use effective contraception during and for 1 week after stopping PONVORY. ( 5.7 ) Macular Edema : An ophthalmic evaluation is recommended before starting treatment and if there is any change in vision while taking PONVORY.
Diabetes mellitus and uveitis increase the risk. ( 5.8 )
5.1Infections Risk of Infections PONVORY causes a dose-dependent reduction in peripheral lymphocyte count to 30–40% of baseline values because of reversible sequestration of lymphocytes in lymphoid tissues [see Clinical Pharmacology (12.2) ] . PONVORY may therefore increase the susceptibility to infections. Life-threatening and rare fatal infections have been reported in association with other sphingosine 1-phosphate (S1P) receptor modulators.
In Study 1 [see Clinical Studies (14) ] , the overall rate of infections was comparable between the PONVORY-treated patients and those receiving teriflunomide 14 mg (54.2% vs 52.1%, respectively). PONVORY increased the risk of upper respiratory tract infections. Serious or severe infections occurred in 1.6% of PONVORY-treated patients compared to 0.9% of patients receiving teriflunomide 14 mg.
Before initiating treatment with PONVORY, results from a recent (i.e., within 6 months or after discontinuation of prior therapy) complete blood count including lymphocyte count should be reviewed. Initiation of treatment with PONVORY should be delayed in patients with active infection until resolution. Lymphocyte counts returned to the normal range in 90% of patients within 1 week of stopping therapy in modeling studies [see Clinical Pharmacology (12.2) ] .
In Study 1, peripheral lymphocyte counts returned to normal range within 2 weeks after discontinuation of PONVORY, which was the first timepoint evaluated. Because residual pharmacodynamic effects, such as lowering effects on peripheral lymphocyte count, may persist for 1 to 2 weeks after discontinuation of PONVORY, vigilance for infection should be continued for 1 to 2 weeks after PONVORY is discontinued [see Warnings and Precautions (5.12) ]. In Study 1, the proportion of patients who experienced lymphocyte counts less than 0.2×10 9 /L was 3.2%.
Effective diagnostic and therapeutic strategies should be employed in patients with symptoms of infection while on therapy. Consider interruption of treatment with PONVORY if a patient develops a serious infection. Herpes Viral Infections Cases of herpes viral infection have been reported in the development program of PONVORY; herpes simplex encephalitis and varicella zoster meningitis have been reported with other S1P receptor modulators.
In Study 1, the rate of herpetic infections was 4.8% for both PONVORY-treated patients and those receiving teriflunomide 14 mg. Patients without a healthcare professional confirmed history of varicella (chickenpox) or without…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described elsewhere in labeling: Infections [see Warnings and Precautions (5.1) ] Bradyarrhythmia and Atrioventricular Conduction Delays [see Warnings and Precautions (5.2) ] Respiratory Effects [see Warnings and Precautions (5.3) ] Liver Injury [see Warnings and Precautions (5.4) ] Increased Blood Pressure [see Warnings and Precautions (5.5) ] Cutaneous Malignancies [see Warnings and Precautions (5.6) ] Fetal Risk [see Warnings and Precautions (5.7) ] Macular Edema [see Warnings and Precautions (5.8) ] Posterior Reversible Encephalopathy Syndrome [see Warnings and Precautions (5.9) ] Unintended Additive Immunosuppressive Effects From Prior Treatment With Immunosuppressive or Immune-Modulating Therapies [see Warnings and Precautions (5.10) ] Severe Increase in Disability After Stopping PONVORY [see Warnings and Precautions (5.11) ] Immune System Effects After Stopping PONVORY [see Warnings and Precautions (5.12) ] Most common adverse reactions (incidence at least 10%) are upper respiratory tract infection, hepatic transaminase elevation, and hypertension.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Janssen Pharmaceuticals, Inc. at 1-800-JANSSEN (1-800-526-7736) FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. A total of 1438 MS patients have received PONVORY at doses of at least 2 mg daily. These patients were included in Study 1 (2-year active-controlled versus teriflunomide 14 mg) [see Clinical Studies (14) ] and in a Phase 2 (6-month placebo-controlled) study in patients with MS and the uncontrolled extension studies.
In Study 1, 82% of PONVORY-treated patients completed 2 years of study treatment, compared to 82.2% of patients receiving teriflunomide 14 mg. Adverse events led to discontinuation of treatment in 8.7% of PONVORY-treated patients, compared to 6% of patients receiving teriflunomide 14 mg. The most common adverse reactions (incidence at least 10%) in PONVORY-treated patients in Study 1 were upper respiratory tract infection, hepatic transaminase elevation, and hypertension.
Table 3 lists adverse reactions that occurred in at least 2% of PONVORY-treated patients and at a higher rate than in patients receiving teriflunomide 14 mg. Table 3: Adverse Reactions Reported in Study 1 Occurring in at Least 2% of PONVORY-Treated Patients and at a Higher Rate Than in Patients Receiving Teriflunomide 14 mg Adverse Reaction PONVORY Teriflunomide 14 mg N=565 (%) N=566 (%) Upper respiratory infection Includes the following terms: nasopharyngitis, upper respiratory tract infection, pharyngitis, respiratory tract infection, bronchitis, respiratory tract infection viral, viral upper respiratory tract infection, tracheitis, and laryngitis.
37 34 Hepatic transaminase elevation Includes the following terms: alanine aminotransferase increased, aspartate aminotransferase increased, hepatic enzyme increased, and transaminases increased. 23 12 Hypertension Includes the following terms: hypertension, hypertensive crisis, blood pressure increased, blood pressure systolic increased, and blood pressure diastolic increased. 10 9 Urinary tract infection 6 5 Dyspnea 5 1 Dizziness 5 3 Cough 4 2 Pain in extremity 4 3 Somnolence 3 2 Pyrexia 2 1 C-reactive protein increased 2 1 Hypercholesterolemia 2 1 Vertigo 2 1 In Study 1, the following adverse reactions occurred in less than 2% of PONVORY-treated patients, but at a rate at least 1% higher than in patients receiving teriflunomide 14 mg: viral infection, herpes zoster, hyperkalemia, lymphopenia [see Warnings and Precautions (5.1) , and macular edema [see Warnings and Precautions (5.8) ].
Adverse reactions in patients treated with PONVO…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Vaccines : Avoid live attenuated vaccines during and for up to 1–2 weeks after treatment with PONVORY. ( 7.4 ) Strong CYP3A4 and UGT1A1 Inducers : Coadministration with PONVORY is not recommended. ( 7.5 )
7.1Anti-Neoplastic, Immune-Modulating, or Immunosuppressive Therapies PONVORY has not been studied in combination with anti-neoplastic, immune-modulating, or immunosuppressive therapies. Caution should be used during concomitant administration because of the risk of additive immune effects during such therapy and in the weeks following administration [see Warnings and Precautions (5.1) ] . When switching from drugs with prolonged immune effects, the half-life and mode of action of these drugs must be considered in order to avoid unintended additive effects on the immune system [see Warnings and Precautions (5.10) ] .
Because of the characteristics and duration of alemtuzumab immune suppressive effects, initiating treatment with PONVORY after alemtuzumab is not recommended. PONVORY can generally be started immediately after discontinuation of beta interferon or glatiramer acetate.
7.2Anti-Arrhythmic Drugs, QT Prolonging Drugs, Drugs that may Decrease Heart Rate PONVORY has not been studied in patients taking QT prolonging drugs. Class Ia (e.g., quinidine, procainamide) and Class III (e.g., amiodarone, sotalol) anti-arrhythmic drugs have been associated with cases of Torsades de Pointes in patients with bradycardia. If treatment with PONVORY is considered, advice from a cardiologist should be sought.
Because of the potential additive effects on heart rate, treatment with PONVORY should generally not be initiated in patients who are concurrently treated with QT prolonging drugs with known arrhythmogenic properties, heart rate lowering calcium channel blockers (e.g., verapamil, diltiazem), or other drugs that may decrease heart rate (e.g., digoxin) [see Warnings and Precautions (5.2) and Drug Interactions (7.3) ] . If treatment with PONVORY is considered, advice from a cardiologist should be sought.
7.3Beta-Blockers Caution should be applied when PONVORY is initiated in patients receiving treatment with a beta-blocker because of the additive effects on lowering heart rate; temporary interruption of the beta-blocker treatment may be needed prior to initiation of PONVORY [see Warnings and Precautions (5.2) ] . Beta-blocker treatment can be initiated in patients receiving stable doses of PONVORY.
7.4Vaccination During, and for up to 1 to 2 weeks after discontinuation of, treatment with PONVORY, vaccinations may be less effective. The use of live attenuated vaccines may carry the risk of infection and should therefore be avoided during PONVORY treatment and for 1 to 2 weeks after discontinuation of treatment with PONVORY [see Warnings and Precautions (5.1) ] .
7.5Strong CYP3A4 and UGT1A1 Inducers In vitro assessments and limited clinical data indicated that concomitant use of strong CYP3A4 and UGT1A1 inducers (e.g., rifampin, phenytoin, carbamazepine) may decrease the systemic exposure of ponesimod. It is unclear whether this decrease in ponesimod systemic exposure would be considered of clinical relevance. Coadministration of PONVORY with strong CYP3A4 and UGT1A1 inducers is not recommended.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Hepatic Impairment : PONVORY is not recommended in patients with moderate or severe hepatic impairment (Child-Pugh class B and C). ( 8.6 )
8.1Pregnancy Risk Summary There are no adequate and well-controlled studies of PONVORY in pregnant women. In animal studies, administration of ponesimod during pregnancy produced adverse effects on development, including embryo lethality and fetal malformations, in the absence of maternal toxicity. In rats and rabbits, visceral and skeletal malformations occurred at clinically relevant maternal ponesimod exposures (see Data ) .
The receptor affected by ponesimod (sphingosine-1-phosphate receptor 1) has been demonstrated to have an important role in embryogenesis, including vascular and neural development. In the US general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2%–4% and 15%–20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown.
Data Animal Data When ponesimod (0, 1, 10, or 40 mg/kg/day) was orally administered to pregnant rats during the period of organogenesis, increased incidences of fetal malformations primarily involving the limbs (syndactyly and ectrodactyly) and cardiovascular system (including ventricular septal defects) were observed at all but the lowest dose tested. A high incidence of embryofetal death was observed at the highest dose tested. Maternal toxicity was not observed, indicating a selective effect on the fetus.
Plasma exposure (AUC) at the no-effect dose (1 mg/kg/day) for adverse effects on embryofetal development in rats was lower than that in humans at the recommended human dose (RHD) of 20 mg/day. When ponesimod (0, 0.25, 1, or 4 mg/kg/day) was orally administered to pregnant rabbits during the period of organogenesis, an increase in post-implantation loss and fetal variations (visceral and skeletal) were noted at the highest dose tested. No maternal toxicity was observed.
Plasma exposure at the no-effect dose (1 mg/kg/day) for adverse effects on embryofetal development in rabbits was lower than that in humans at the RHD. In a dose-range finding study in pregnant rabbits, oral administration of ponesimod (0, 6, 20, or 60 mg/kg/day) during organogenesis, an increase in embryofetal death and fetal limb malformation (brachydactyly) were observed at the lowest dose tested; at the higher doses, there were no live fetuses. When ponesimod (5, 10, or 20 mg/kg) was orally administered to female rats throughout pregnancy and lactation, the offspring exhibited decreased survival, reduced body weight gain, and reduced fertility and reproductive performance (increases in pre- and post-implantation loss) at the highest dose tested, neurobehavioral impairment (increased locomotor activity) at the mid and high doses, and delayed sexual maturation at all doses tested.
A no-effect dose for adverse effects on pre- and postnatal development in rats was not identified. Plasma exposure (AUC) in dams at the lowest dose tested was less than that in humans at the RHD.
8.2Lactation Risk Summary There are no data on the presence of PONVORY in human milk, the effects on the breastfed infant, or the effects of the drug on milk production. When ponesimod was orally administered to female rats during pregnancy and lactation, ponesimod was detected in the plasma of the offspring, suggesting excretion of ponesimod in milk. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for PONVORY and any potential adverse effects on the breastfed infant from PONVORY or from the underlying maternal condition.
8.3Females and Males of Reproductive Potential Contraception Females Before initiation of PONVORY treatment, women of childbearing potential should be counseled on the potential for a serious risk to the fetus and the need for effective contraception during treatment w…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate and well-controlled studies of PONVORY in pregnant women. In animal studies, administration of ponesimod during pregnancy produced adverse effects on development, including embryo lethality and fetal malformations, in the absence of maternal toxicity. In rats and rabbits, visceral and skeletal malformations occurred at clinically relevant maternal ponesimod exposures (see Data ) .
The receptor affected by ponesimod (sphingosine-1-phosphate receptor 1) has been demonstrated to have an important role in embryogenesis, including vascular and neural development. In the US general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2%–4% and 15%–20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown.
Data Animal Data When ponesimod (0, 1, 10, or 40 mg/kg/day) was orally administered to pregnant rats during the period of organogenesis, increased incidences of fetal malformations primarily involving the limbs (syndactyly and ectrodactyly) and cardiovascular system (including ventricular septal defects) were observed at all but the lowest dose tested. A high incidence of embryofetal death was observed at the highest dose tested. Maternal toxicity was not observed, indicating a selective effect on the fetus.
Plasma exposure (AUC) at the no-effect dose (1 mg/kg/day) for adverse effects on embryofetal development in rats was lower than that in humans at the recommended human dose (RHD) of 20 mg/day. When ponesimod (0, 0.25, 1, or 4 mg/kg/day) was orally administered to pregnant rabbits during the period of organogenesis, an increase in post-implantation loss and fetal variations (visceral and skeletal) were noted at the highest dose tested. No maternal toxicity was observed.
Plasma exposure at the no-effect dose (1 mg/kg/day) for adverse effects on embryofetal development in rabbits was lower than that in humans at the RHD. In a dose-range finding study in pregnant rabbits, oral administration of ponesimod (0, 6, 20, or 60 mg/kg/day) during organogenesis, an increase in embryofetal death and fetal limb malformation (brachydactyly) were observed at the lowest dose tested; at the higher doses, there were no live fetuses. When ponesimod (5, 10, or 20 mg/kg) was orally administered to female rats throughout pregnancy and lactation, the offspring exhibited decreased survival, reduced body weight gain, and reduced fertility and reproductive performance (increases in pre- and post-implantation loss) at the highest dose tested, neurobehavioral impairment (increased locomotor activity) at the mid and high doses, and delayed sexual maturation at all doses tested.
A no-effect dose for adverse effects on pre- and postnatal development in rats was not identified. Plasma exposure (AUC) in dams at the lowest dose tested was less than that in humans at the RHD.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established. Juvenile Animal Toxicity Data Oral administration of ponesimod (0, 1, 10, 30, or 100 mg/kg/day) to young rats from postnatal day 28 to 91 resulted in lung histopathology (alveolar histiocytosis/edema) and decreased immune function (T-cell dependent antibody response) at the two highest doses tested. Decreased growth (body weight gain and/or long bone length) was observed at all but the low dose, and neurobehavioral impairment (increased locomotor activity) was observed at the highest dose tested.
Decreased lymphocyte count and neurobehavioral impairment persisted at the end of a 4-week recovery period.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of PONVORY did not include patients 65 years of age and over to determine whether they respond differently from younger subjects. Use of PONVORY in elderly patients should be cautious, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy [see Clinical Pharmacology (12.3) ] .
🆘 Overdosage ▾
10 OVERDOSAGE Symptoms and Signs In patients with overdosage of PONVORY, especially upon initiation/reinitiation of treatment, it is important to observe for signs and symptoms of bradycardia as well as AV conduction blocks, which may include overnight monitoring. Regular measurements of pulse rate and blood pressure are required, and ECGs should be performed [see Warnings and Precautions (5.2 , 5.5) and Clinical Pharmacology (12.2) ] . Treatment There is no specific antidote to ponesimod.
Neither dialysis nor plasma exchange would result in meaningful removal of ponesimod from the body. The decrease in heart rate induced by PONVORY can be reversed by atropine. In the event of overdose, PONVORY should be discontinued, and general supportive treatment given until clinical toxicity has been diminished or resolved.
It is advisable to contact a poison control center to obtain the latest recommendations for the management of an overdose.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Ponesimod is a sphingosine 1-phosphate (S1P) receptor 1 modulator that binds with high affinity to S1P receptor 1. Ponesimod blocks the capacity of lymphocytes to egress from lymph nodes, reducing the number of lymphocytes in peripheral blood. The mechanism by which ponesimod exerts therapeutic effects in multiple sclerosis is unknown, but may involve reduction of lymphocyte migration into the central nervous system.
12.2Pharmacodynamics Immune System In healthy volunteers, PONVORY induces a dose-dependent reduction of the peripheral blood lymphocyte count from a single dose of 5 mg onwards, with the greatest reduction observed 6 hours post-dose, caused by reversible sequestration of lymphocytes in lymphoid tissues. After 7 daily doses of 20 mg, the greatest decrease in absolute mean lymphocyte count was to 26% of baseline (650 cells/µL), observed 6 hours after administration. Peripheral blood B cells [CD19+] and T cells [CD3+], T-helper [CD3+CD4+], and T-cytotoxic [CD3+CD8+] cell subsets are all affected, while NK cells are not.
T-helper cells were more sensitive to the effects of ponesimod than T-cytotoxic cells. PK/PD modeling indicates lymphocyte counts returned to the normal range in greater than 90% of healthy subjects within 1 to 2 weeks of stopping therapy. In Study 1, peripheral lymphocyte counts returned to the normal range within 2 weeks after discontinuation of PONVORY.
Heart Rate and Rhythm PONVORY causes a transient dose-dependent reduction in heart rate (HR) and AV conduction delays upon treatment initiation [see Warnings and Precautions (5.2) ] . The heart rate decreases plateaued at doses greater than or equal to 40 mg [2 times the recommended maintenance dosage], and bradyarrhythmic events (AV blocks) were detected at a higher incidence under PONVORY treatment, compared to placebo. This effect starts within the first hour of dosing and is maximal at 2–4 hours post-dose.
HR generally returns to pre-dose values by 4–5 hours post-dose on Day 1, and the effect diminishes with repeated administration, indicating tolerance. The decrease in heart rate induced by ponesimod can be reversed by atropine. Beta-Blockers The negative chronotropic effect of coadministration of PONVORY and propranolol was evaluated in a dedicated pharmacodynamics safety study.
The addition of PONVORY to propranolol at steady state has an additive effect on HR effect [see Drug Interactions (7.3) ] . Cardiac Electrophysiology In a thorough QT study, daily administration of ponesimod doses of 40 mg and 100 mg (respectively 2- and 5-fold the recommended maintenance dose) until steady-state conditions were achieved resulted in prolongation of Fridericia-corrected QT (QTcF) intervals, with the maximum mean (upper bound of 90% two-sided confidence interval) at 11.8 ms (40 mg) and 16.2 ms (100 mg).
No subject had absolute QTcF greater than 480 ms or ΔQTcF greater than 90 ms for ponesimod treatment. Pulmonary Function Dose-dependent reductions in FEV 1 and FVC were observed in PONVORY-treated subjects, and were greater than in subjects taking placebo [see Warnings and Precautions (5.3) ] . These effects can be reversed with administration of a short acting beta2 agonist.
12.3Pharmacokinetics Following ponesimod oral dosing, C max and AUC increased approximately dose-proportionally in the dose-range studied (1–75 mg). Steady-state levels are approximately 2.0- to 2.6-fold greater than with a single dose, and are achieved following 3 days of administration of the maintenance dose of ponesimod. The pharmacokinetics of ponesimod are similar in healthy subjects and patients with multiple sclerosis, with 25% inter-subject variability across studies.
Absorption The time to reach maximum plasma concentration of ponesimod is 2–4 hours post-dose. The absolute oral bioavailability of a 10 mg dose is 84%. Food Effect Food does not have a clinically relevant effect on ponesimod pharmacokinetics; therefore, PONVO…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Ponesimod is a sphingosine 1-phosphate (S1P) receptor 1 modulator that binds with high affinity to S1P receptor 1. Ponesimod blocks the capacity of lymphocytes to egress from lymph nodes, reducing the number of lymphocytes in peripheral blood. The mechanism by which ponesimod exerts therapeutic effects in multiple sclerosis is unknown, but may involve reduction of lymphocyte migration into the central nervous system.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied PONVORY ® (ponesimod) tablet is available as round, biconvex, film-coated tablets supplied in the following dosage strengths and package configurations. Starter Pack Tablet Strength Tablet Color Tablet Size Tablet Debossing Pack Size NDC Code 2 mg White 5.0 mm "2" on one side and an arch on the other side. Child Resistant Starter Pack (14 tablets) NDC 50458-707-14 3 mg Red 5.0 mm "3" on one side and an arch on the other side.
4 mg Purple 5.0 mm "4" on one side and an arch on the other side. 5 mg Green 8.6 mm "5" on one side and an arch and an "A" on the other side. 6 mg White 8.6 mm " 6 " on one side and an arch and an "A" on the other side.
7 mg Red 8.6 mm "7" on one side and an arch and an "A" on the other side. 8 mg Purple 8.6 mm "8" on one side and an arch and an "A" on the other side. 9 mg Brown 8.6 mm " 9 " on one side and an arch and an "A" on the other side.
10 mg Orange 8.6 mm "10" on one side and an arch and an "A" on the other side. Maintenance Dose Bottle Tablet Strength Tablet Color Tablet Size Tablet Debossing Pack Size NDC Code 20 mg Yellow 8.6 mm "20" on one side and an arch and an "A" on the other side. Bottle of 30 tablets with child-resistant closure.
Each bottle contains a desiccant sachet. NDC 50458-720-30
16.2Storage and Handling Starter Pack Store at 20ºC to 25ºC (68ºF to 77ºF); excursions permitted from 15ºC to 30ºC (59ºF to 86ºF) [see USP Controlled Room Temperature] . Store in the original package. Maintenance Dose Bottle Store at 20ºC to 25ºC (68ºF to 77ºF); excursions permitted from 15ºC to 30ºC (59ºF to 86ºF) [see USP Controlled Room Temperature] .
Store in the original package. Do not discard desiccant. Protect from moisture.
Keep out of reach of children.
📦 Storage and Handling ▾
16.2Storage and Handling Starter Pack Store at 20ºC to 25ºC (68ºF to 77ºF); excursions permitted from 15ºC to 30ºC (59ºF to 86ºF) [see USP Controlled Room Temperature] . Store in the original package. Maintenance Dose Bottle Store at 20ºC to 25ºC (68ºF to 77ºF); excursions permitted from 15ºC to 30ºC (59ºF to 86ºF) [see USP Controlled Room Temperature] .
Store in the original package. Do not discard desiccant. Protect from moisture.
Keep out of reach of children.
📋 Description ▾
11 DESCRIPTION PONVORY (ponesimod) is a sphingosine 1-phosphate receptor modulator. The chemical name for ponesimod is (2 Z ,5 Z )-5-[3-chloro-4-[(2 R )-2,3-dihydroxypropoxy]benzylidene]-3-(2-methylphenyl)-2-(propylimino)-1,3-thiazolidin-4-one. It has one chiral center with absolute configuration of (R) .
Its molecular formula is C 23 H 25 ClN 2 O 4 S and its molecular weight is 460.97 g/mol. Ponesimod has the following structural formula: Ponesimod is a white to light yellowish powder that is practically insoluble or insoluble in water. PONVORY ® (ponesimod) is provided as 2 mg, 3 mg, 4 mg, 5 mg, 6 mg, 7 mg, 8 mg, 9 mg, 10 mg, and 20 mg film-coated tablets for oral administration.
Each tablet contains the following inactive ingredients: croscarmellose sodium, lactose monohydrate, magnesium stearate, microcrystalline cellulose, povidone K30, silica colloidal anhydrous, and sodium lauryl sulfate. Each tablet coating contains ferrosoferric oxide (included in 4 mg, 5 mg, 8 mg, and 9 mg film-coated tablets), hydroxypropyl methylcellulose 2910, iron oxide red (included in 3 mg, 4 mg, 7 mg, 8 mg, 9 mg, and 10 mg film-coated tablets), iron oxide yellow (included in 3 mg, 5 mg, 7 mg, 9 mg, 10 mg, and 20 mg film-coated tablets), lactose monohydrate, polyethylene glycol 3350, titanium dioxide, and triacetin.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Administration Tell patients not to discontinue PONVORY without first discussing this with the prescribing healthcare provider. Advise patients to contact their healthcare provider if they accidently take more PONVORY than prescribed.
Instruct patients to administer tablets whole. Risk of Infections Inform patients that they may have an increased risk of infections, some of which could be life-threatening, when taking PONVORY and for 1 to 2 weeks after stopping it, and that they should contact their healthcare provider if they develop symptoms of infection [see Warnings and Precautions (5.1) ] . Advise patients that the use of some vaccines containing live virus (live attenuated vaccines) should be avoided during treatment with PONVORY, and PONVORY should be paused 1 to 2 weeks prior and until 4 weeks after a planned vaccination.
Recommend that patients postpone treatment with PONVORY for at least 1 month after VZV vaccination. Inform patients that prior or concomitant use of drugs that suppress the immune system may increase the risk of infection. Cardiac Effects Advise patients that initiation of PONVORY treatment results in transient decrease in heart rate [see Warnings and Precautions (5.2) ] .
Inform patients that to reduce this effect, dose titration is required. Advise patients that dose titration is also required if 4 or more consecutive daily doses are missed during treatment initiation or maintenance treatment [see Dosage and Administration (2.2 , 2.4) and Warnings and Precautions (5.2) ] . Inform certain patients with certain preexisting cardiac conditions that they will need to be observed in the doctor's office or other facility for at least 4 hours after the first dose and after reinitiation if treatment is interrupted or discontinued for certain periods [see Dosage and Administration (2.3) ] .
Respiratory Effects Advise patients that they should contact their healthcare provider if they experience new onset or worsening of dyspnea [see Warnings and Precautions (5.3) ] . Liver Injury Inform patients that PONVORY may increase liver enzymes. Advise patient that they should contact their healthcare provider if they experience any unexplained nausea, vomiting, abdominal pain, fatigue, anorexia, or jaundice and/or dark urine during treatment [see Warnings and Precautions (5.4) ] .
Cutaneous Malignancies Inform patients that the risk of basal cell carcinoma is increased with the use of PONVORY and that cases of melanoma and squamous cell carcinoma have been reported. Advise patients that any suspicious skin lesions should be promptly evaluated. Advise patients to limit exposure to sunlight and ultraviolet light by wearing protective clothing and using a sunscreen with high protection factor [see Warnings and Precautions (5.6) ] .
Pregnancy and Fetal Risk Inform patients that, based on animal studies, PONVORY may cause fetal harm. Discuss with women of childbearing age whether they are pregnant, might be pregnant, or are trying to become pregnant. Advise women of childbearing potential of the need for effective contraception during treatment with PONVORY and for one week after stopping PONVORY.
Advise a female patient to immediately inform her healthcare provider if she is pregnant or planning to become pregnant [see Warnings and Precautions (5.7) ]. Macular Edema Advise patients that PONVORY may cause macular edema, and that they should contact their healthcare provider if they experience any changes in their vision while taking PONVORY [see Warnings and Precautions (5.8) ] . Inform patients with diabetes mellitus or a history of uveitis that their risk of macular edema is increased.
Posterior Reversible Encephalopathy Syndrome Advise patients to immediately report to their healthcare provider any symptoms involving sudden onset of severe headache, altered mental status, visual disturbances, or seizure. In…
💬 Medication Guide ▾
MEDICATION GUIDE PONVORY ® (pon-VOR-ee) (ponesimod) tablets, for oral use This Medication Guide has been approved by the U.S. Food and Drug Administration. Approved: 09/2022 What is the most important information I should know about PONVORY?
PONVORY may cause serious side effects, including: Infections. PONVORY can increase your risk of serious infections that can be life-threatening and cause death. PONVORY lowers the number of white blood cells (lymphocytes) in your blood.
This will usually go back to normal within 1 to 2 weeks of stopping treatment. Your healthcare provider should review a recent blood test of your white blood cells before you start taking PONVORY. Call your healthcare provider right away if you have any of these symptoms of an infection during treatment with PONVORY and for 1 to 2 weeks after your last dose of PONVORY: fever tiredness body aches chills nausea vomiting headache with fever, neck stiffness, sensitivity to light, nausea, or confusion (these may be symptoms of meningitis, an infection of the lining around your brain and spine) Your healthcare provider may delay starting or may stop your PONVORY treatment if you have an infection.
Slow heart rate (bradycardia or bradyarrhythmia) when you start taking PONVORY. PONVORY can cause your heart rate to slow down, especially after you take your first dose. You should have a test to check the electrical activity of your heart called an electrocardiogram (ECG) before you take your first dose of PONVORY.
Only start your treatment with PONVORY using the Starter Pack. You must use the PONVORY Starter Pack to slowly increase the dose over a 14-day period to help reduce the effect of slowing of your heart rate. It is important to follow the recommended dosing instructions.
See " How should I take PONVORY ?" Call your healthcare provider if you experience the following symptoms of slow heart rate: dizziness lightheadedness feeling like your heart is beating slowly or skipping beats shortness of breath confusion chest pain tiredness Follow directions from your healthcare provider when starting PONVORY and when you miss a dose. See " How should I take PONVORY? " See " What are possible side effects of PONVORY? " for more information about side effects. What is PONVORY?
PONVORY is a prescription medicine that is used to treat relapsing forms of multiple sclerosis, to include clinically isolated syndrome, relapsing-remitting disease, and active secondary progressive disease, in adults. It is not known if PONVORY is safe and effective in children. Do not take PONVORY if you: have had a heart attack, chest pain called unstable angina, stroke or mini-stroke (transient ischemic attack or TIA), or certain types of heart failure in the last 6 months. have certain types of heart block or irregular or abnormal heartbeat (arrhythmia), unless you have a pacemaker.
Talk to your healthcare provider before taking PONVORY if you have any of these conditions, or do not know if you have any of these conditions. Before you take PONVORY, tell your healthcare provider about all of your medical conditions, including if you: have a fever or infection, or you are unable to fight infections due to a disease or taking medicines that weaken your immune system. have had chicken pox or have received the vaccine for chicken pox. Your healthcare provider may do a blood test for chicken pox virus.
You may need to get the full course of vaccine for chicken pox and then wait 1 month before you start taking PONVORY. have slow heart rate. have an irregular or abnormal heartbeat (arrhythmia). have a history of stroke. have heart problems, including a heart attack or chest pain. have breathing problems, including during your sleep (sleep apnea). have liver problems. have high blood pressure. had or now have a type of skin cancer called basal cell carcinoma (BCC), melanoma, or squamous cell carcinoma. have eye problems, especially an inflammation of the eye called uveitis. have diabetes. are pregnant…