
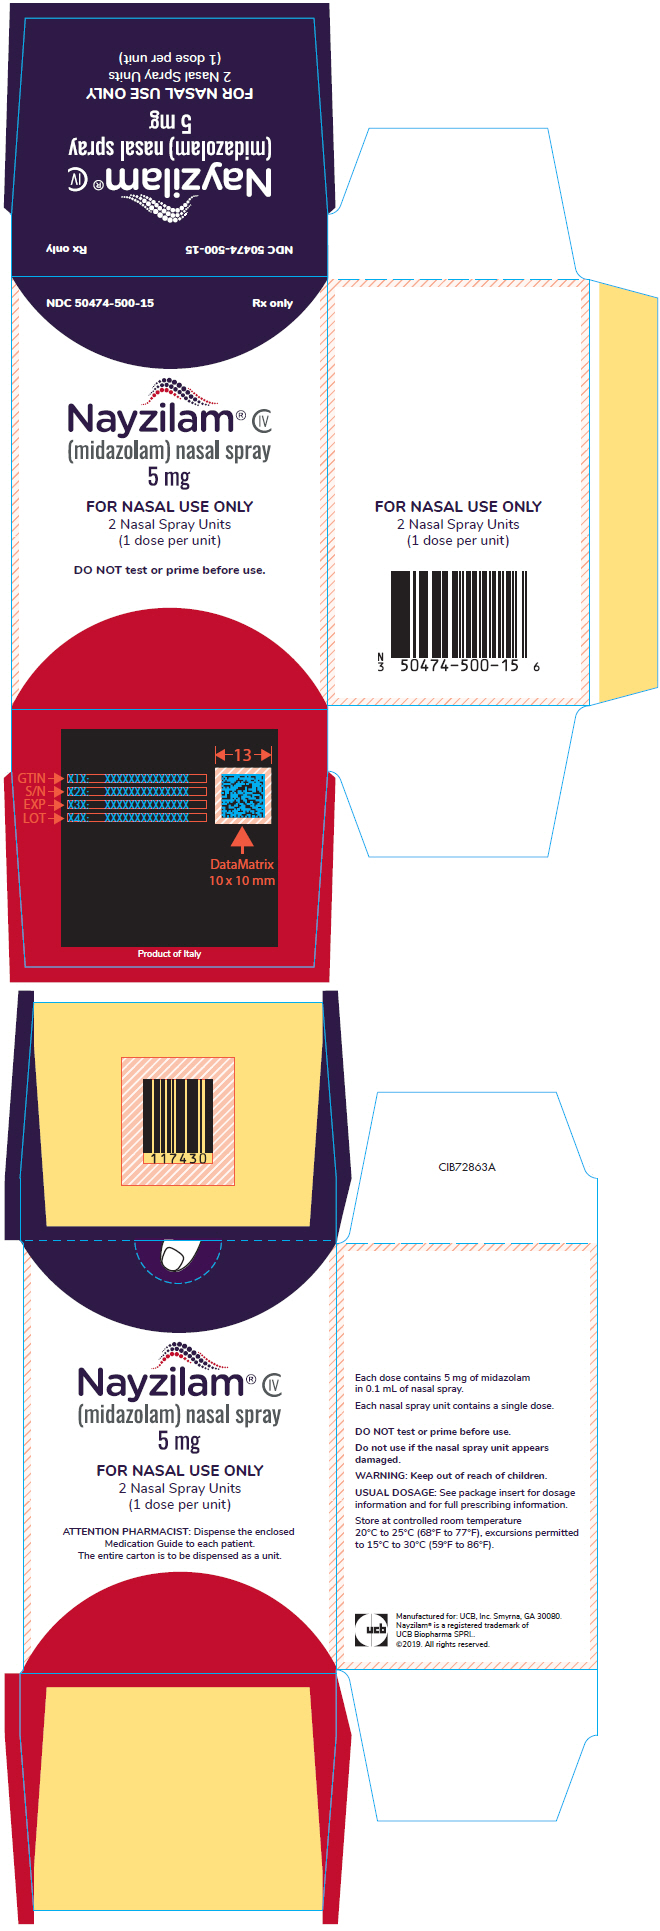
Nayzilam midazolam 5 mg/.1mL Spray — NDC 50474-500-15 (Billing 50474-0500-15)
This is a package of Nayzilam midazolam 5 mg/.1mL Spray from UCB, Inc., marketed since May 2019 and currently FDA-listed; retail pharmacies pay about $327.05 per unit (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 50474-500-15 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 50474 labeler · 500 product · 15 package
- Package marketed since
- May 17, 2019
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 5047450015 6
- Medicaid fills, this package
- 112,304 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 079754
- GCN: 46309
- GPI-14 (Medi-Span): 72100060002010
- HICL (First Databank): 010329
- AHFS class code: 28:12.08.00
- RxCUI (RxNorm): 2173494
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Benzodiazepine class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Midazolam nasal spray is used for emergency situations control certain types of seizures. Midazolam is in a class of medications called benzodiazepines. It works by calming abnormal overactivity in the brain.
Read the full MedlinePlus article ↗- It depends on the form. Injections and the children's syrup are used to calm you, ease anxiety and block memory around procedures or surgery. Injections are also used for anesthesi...
- Injections and the syrup are given by trained staff in monitored settings. The syrup is a single dose before a procedure, not for home use. Nayzilam is sprayed into one nostril, wi...
- Drowsiness, nausea, vomiting and trouble remembering things for several hours are common. Blood pressure may dip slightly. Slow or shallow breathing, severe sleepiness or agitation...
- No, avoid them unless your prescriber says otherwise. Alcohol and opioids can cause dangerously slow breathing, coma and death. Tell your team about every medicine you take, includ...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Midazolam — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $327.048 | $654.10 / 2 vials |
| Medicaid paysCMS SDUD · 12 mo | $3,172.41 | $6,344.83 / 2 vials |
| Medicare drug plans payPart D · Q2 2026 | $328.43 | $656.86 / 2 vials |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 50474-0500-15 You're viewing this Main listing | 2 BLISTER PACK in 1 CARTON / 1 VIAL, SINGLE-DOSE in 1 BLISTER PACK / .1 mL in 1 VIAL, SINGLE-DOSE | 2019-05-17 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Nayzilam 5 mg/.1mLthis 50474-0500-15 | UCB, | 1 vial | $327.048 | — | Availability likely | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9687495 ↗ | Method of use | U-2526 | Jan 18, 2028 |
| US 9289432 ↗ | Method of use | U-2526 | Jan 18, 2028 |
| US 8217033 ↗ | Method of use | U-2526 | Jan 18, 2028 |
| US 8809322 ↗ | Drug product | — | Jan 18, 2028 |
| Code | What it grants | Expires |
|---|---|---|
| ODE-243 | Orphan Drug Exclusivity (7-year) | May 17, 2026 |
Is there a generic version of NAYZILAM 5 MG NASAL SPRAY?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Midazolam inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII WXH089JZ5E
A synthetic compound made from polyethylene glycol, used as a solvent and humectant to help dissolve active ingredients and maintain moisture in the formulation.
-
UNII B697894SGQ
Polyethylene glycol 400 is a clear, thick liquid made from petroleum-derived polymers. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from UCB, Inc. labeler code 50474
- Keppra levetiracetam 100 mg/mL Solution NDC 50474-001-48
- Keppra levetiracetam 100 mg/mL Injection, Solution, Concentrate NDC 50474-002-63
- Kygevvi doxecitine and doxribtimine 2 g; 2 g Powder, For Solution NDC 50474-350-30
- Briviact brivaracetam 10 mg Tablet, Film Coated NDC 50474-370-66
- Briviact brivaracetam 25 mg Tablet, Film Coated NDC 50474-470-09
- Briviact brivaracetam 50 mg Tablet, Film Coated NDC 50474-570-09
- Keppra levetiracetam 250 mg Tablet, Film Coated NDC 50474-594-40
- Keppra levetiracetam 500 mg Tablet, Film Coated NDC 50474-595-40
- Keppra levetiracetam 750 mg Tablet, Film Coated NDC 50474-596-40
- Keppra levetiracetam 1000 mg Tablet, Film Coated NDC 50474-597-66
- Keppra XR levetiracetam 500 mg Tablet, Film Coated, Extended Release NDC 50474-598-66
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: RISKS FROM CONCOMITANT USE WITH OPIOIDS; ABUSE, MISUSE, AND ADDICTION; and DEPENDENCE AND WITHDRAWAL REACTIONS Concomitant use of benzodiazepines and opioids may result in profound sedation, respiratory depression, coma, and death . Reserve concomitant prescribing of these drugs for patients for whom alternative treatment options are inadequate. Limit dosages and durations to the minimum required.
Follow patients for signs and symptoms of respiratory depression and sedation [see Warnings and Precautions (5.1) and Drug Interactions (7.2) ] . The use of benzodiazepines, including NAYZILAM, exposes users to risks of abuse, misuse, and addiction, which can lead to overdose or death. Abuse and misuse of benzodiazepines commonly involve concomitant use of other medications, alcohol, and/or illicit substances, which is associated with an increased frequency of serious adverse outcomes.
Before prescribing NAYZILAM and throughout treatment, assess each patient's risk for abuse, misuse, and addiction [see Warnings and Precautions (5.2) ]. The continued use of benzodiazepines may lead to clinically significant physical dependence. The risks of dependence and withdrawal increase with longer treatment duration and higher daily dose.
Although NAYZILAM is indicated only for intermittent use [see Indications and Usage (1) and Dosage and Administration (2) ] , if used more frequently than recommended abrupt discontinuation or rapid dosage reduction of NAYZILAM may precipitate acute withdrawal reactions, which can be life-threatening. For patients using NAYZILAM more frequently than recommended, to reduce the risk of withdrawal reactions, use a gradual taper to discontinue NAYZILAM [see Warnings and Precautions (5.3) ]. WARNING: RISKS FROM CONCOMITANT USE WITH OPIOIDS; ABUSE, MISUSE, AND ADDICTION; and DEPENDENCE AND WITHDRAWAL REACTIONS See full prescribing information for complete boxed warning.
Concomitant use of benzodiazepines and opioids may result in profound sedation, respiratory depression, coma, and death ( 5.1 , 7.2 ) The use of benzodiazepines, including NAYZILAM, exposes users to risks of abuse, misuse, and addiction, which can lead to overdose or death. Before prescribing NAYZILAM and throughout treatment, assess each patient's risk for abuse, misuse, and addiction ( 5.2 ). Although NAYZILAM is indicated only for intermittent use ( 1 , 2 ), if used more frequently than recommended, abrupt discontinuation or rapid dosage reduction of NAYZILAM may precipitate acute withdrawal reactions, which can be life-threatening.
For patients using NAYZILAM more frequently than recommended, to reduce the risk of withdrawal reactions, use a gradual taper to discontinue NAYZILAM ( 5.3 ).
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE NAYZILAM is indicated for the acute treatment of intermittent, stereotypic episodes of frequent seizure activity (i.e., seizure clusters, acute repetitive seizures) that are distinct from a patient's usual seizure pattern in patients with epilepsy 12 years of age and older. NAYZILAM is a benzodiazepine indicated for the acute treatment of intermittent, stereotypic episodes of frequent seizure activity (i.e., seizure clusters, acute repetitive seizures) that are distinct from a patient's usual seizure pattern in patients with epilepsy 12 years of age and older.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Administer NAYZILAM by the nasal route only. ( 2.2 ) Initial Dose : Administer one spray (5 mg dose) into one nostril. ( 2.2 ) Second Dose : One additional spray (5 mg dose) into the opposite nostril may be administered after 10 minutes if the patient has not responded to the initial dose.
( 2.2 ) Maximum Dosage and Treatment Frequency: Do not use more than 2 doses of NAYZILAM to treat a seizure cluster. It is recommended that NAYZILAM be used to treat no more than one episode every three days and treat no more than five episodes per month. ( 2.2 )
2.1Instructions Prior to Dosing NAYZILAM prescribers should consider the following prior to initiation of treatment: For patients at increased risk of respiratory depression from benzodiazepines, administration of NAYZILAM under healthcare professional supervision should be considered prior to treatment with NAYZILAM; this administration may be performed in the absence of a seizure episode [see Warnings and Precautions (5.4) ] . Prior to treatment, the healthcare professional should instruct the individual administering NAYZILAM on how to identify seizure clusters and use the product appropriately [see Patient Counseling Information: Administration Information (17) ] .
Patients and caregivers should be counseled to read carefully the "Instructions for Use" for complete directions on how to properly administer NAYZILAM.
2.2Dosage Information Administer NAYZILAM by the nasal route only. Initial Dose: Administer one spray (5 mg dose) into one nostril. Second Dose (if needed): One additional spray (5 mg dose) into the opposite nostril may be administered after 10 minutes if the patient has not responded to the initial dose.
A second dose of NAYZILAM should not be administered if the patient has trouble breathing or if there is excessive sedation that is uncharacteristic of the patient during a seizure cluster episode [see Warnings and Precautions (5.4) ]. Maximum Dosage and Treatment Frequency: Do not use more than 2 doses of NAYZILAM to treat a single episode. It is recommended that NAYZILAM be used to treat no more than one episode every three days and no more than 5 episodes per month [see Drug Abuse and Dependence (9.4) ] .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS NAYZILAM is supplied as a single-dose nasal spray unit containing 5 mg of midazolam in 0.1 mL solution. Single-dose nasal spray unit containing 5 mg midazolam per 0.1 mL solution. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS NAYZILAM is contraindicated in patients with: Known hypersensitivity to midazolam. Acute narrow-angle glaucoma [see Warnings and Precautions (5.8) ]. Patients with hypersensitivity to midazolam ( 4 ) Patients with acute narrow-angle glaucoma ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS CNS Depression From Concomitant Use With Other CNS Depressants or Moderate or Strong CYP3A4 Inhibitors : May cause an increased CNS-depressant effect when used with alcohol or other CNS depressants. Concomitant use with moderate or strong CYP3A4 inhibitors may result in prolonged sedation because of a decrease in plasma clearance of midazolam. ( 5.5 , 7.3 ) Suicidal Behavior and Ideation: Antiepileptic drugs increase the risk of suicidal ideation and behavior.
( 5.6 ) Impaired Cognitive Function: Midazolam is associated with a high incidence of partial or complete impairment of recall for the next several hours. ( 5.7 ) Glaucoma: NAYZILAM can increase intraocular pressure in patients with glaucoma. Patients with open-angle glaucoma may need to have their ophthalmologic status evaluated following treatment with NAYZILAM.
( 5.8 ) Neonatal Sedation and Withdrawal Syndrome: NAYZILAM use during pregnancy can result in neonatal sedation and/or neonatal withdrawal. ( 5.9 , 8.1 )
5.1Risks from Concomitant Use with Opioids Concomitant use of benzodiazepines, including NAYZILAM, and opioids may result in profound sedation, respiratory depression, coma, and death. Because of these risks, reserve concomitant prescribing of benzodiazepines and opioids for patients for whom alternative treatment options are inadequate. Observational studies have demonstrated that concomitant use of opioid analgesics and benzodiazepines increases the risk of drug-related mortality compared to use of opioids alone.
If a decision is made to prescribe NAYZILAM concomitantly with opioids, prescribe the lowest effective dosages and minimum durations of concomitant use, and follow patients closely for signs and symptoms of respiratory depression and sedation. Advise both patients and caregivers about the risks of respiratory depression and sedation when NAYZILAM is used with opioids [see Drug Interactions (7.2) ] .
5.2Abuse, Misuse, and Addiction The use of benzodiazepines, including NAYZILAM, exposes users to the risks of abuse, misuse, and addiction, which can lead to overdose or death. Abuse and misuse of benzodiazepines often (but not always) involve the use of doses greater than the maximum recommended dosage and commonly involve concomitant use of other medications, alcohol, and/or illicit substances, which is associated with an increased frequency of serious adverse outcomes, including respiratory depression, overdose, or death [see Drug Abuse and Dependence (9.2) ] .
Before prescribing NAYZILAM and throughout treatment, assess each patient's risk for abuse, misuse, and addiction. Use of NAYZILAM, particularly in patients at elevated risk, necessitates counseling about the risks and proper use of NAYZILAM along with monitoring for signs and symptoms of abuse, misuse, and addiction. Do not exceed the recommended dosing frequency; avoid or minimize concomitant use of CNS depressants and other substances associated with abuse, misuse, and addiction (e.g., opioid analgesics, stimulants); and advise patients on the proper disposal of unused drug.
If a substance use disorder is suspected, evaluate the patient and institute (or refer them for) early treatment, as appropriate.
5.3Dependence and Withdrawal Reactions After Use of NAYZILAM More Frequently Than Recommended For patients using NAYZILAM more frequently than recommended, to reduce the risk of withdrawal reactions, use a gradual taper to discontinue NAYZILAM (a patient-specific plan should be used to taper the dose). Patients at an increased risk of withdrawal adverse reactions after benzodiazepine discontinuation or rapid dosage reduction include those who take higher dosages, and those who have had longer durations of use. Acute Withdrawal Reactions The continued use of benzodiazepines may lead to clinically significant physical dependence.
Although NAYZILAM is indicated only for intermittent use [see Indications and Usage (1) and Dosage and Administration (2) ] , if used mor… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed in more detail in other sections of the labeling: Risks from Concomitant Use with Opioids [see Warnings and Precautions (5.1) ] Abuse, Misuse, and Addiction [see Warnings and Precautions (5.2) ] Dependence and Withdrawal Reactions After Use of NAYZILAM More Frequently Than Recommended [see Warnings and Precautions (5.3) ] Risks of Cardiorespiratory Adverse Reactions [see Warnings and Precautions (5.4) ] CNS Depression from Concomitant Use with Other CNS Depressants or Moderate or Strong CYP3A4 Inhibitors [see Warnings and Precautions (5.5) ] Suicidal Behavior and Ideation [see Warnings and Precautions (5.6) ] Impaired Cognitive Function [see Warnings and Precautions (5.7) ] Glaucoma [see Warnings and Precautions (5.8) ] Neonatal Sedation and Withdrawal Syndrome [see Warnings and Precautions (5.9) ] Other Adverse Reactions [see Warnings and Precautions (5.10) ] The most common adverse reactions (≥5% in any NAYZILAM treatment group) were somnolence, headache, nasal discomfort, throat irritation, and rhinorrhea ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact UCB, Inc. at 1-844-599-2273 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. NAYZILAM was studied for the outpatient treatment of a single seizure cluster in 292 adult and adolescent patients with epilepsy (Study 1) [see Clinical Studies (14) ] . The study was conducted in two phases; an open-label Test Dose Phase followed by a double-blind, placebo-controlled, Comparative Phase.
The mean age of patients enrolled in the Comparative Phase (N=201) was 33 years, 51% were female, and 95% were White. Table 2 lists the adverse reactions occurring in 2% or more of the NAYZILAM-treated patients and at a rate greater than the placebo-treated patients in the Comparative Phase of Study 1. Table 2: Adverse Reactions Adverse reactions that occurred within 2 days after NAYZILAM administration are included that Occurred in ≥2% of Patients (Any NAYZILAM) and Greater than Placebo in the Comparative Phase of Study 1 Body System/Adverse Reaction Placebo NAYZILAM Patients in Study 1 were permitted to take a second, open-label dose of NAYZILAM 5 mg between 10 minutes and 6 hours following the initial blinded dose of NAYZILAM 5 mg or placebo if they experience seizure recurrence or an incomplete resolution of the episode.
The Placebo + NAYZILAM 5 mg and NAYZILAM 5 mg + 5 mg columns represent patients who received a second dose of NAYZILAM 5 mg and received a blinded initial dose of placebo or NAYZILAM 5 mg, respectively. NAYZILAM 5 mg Placebo + NAYZILAM 5 mg NAYZILAM 5 mg + 5 mg Any NAYZILAM Treatment Group N = 26 % N = 91 % N = 41 % N = 43 % N = 175 % Nervous System Somnolence 4 10 10 9 10 Headache 0 7 0 2 4 Dysarthria 0 2 2 2 2 Application Site Nasal Discomfort 8 5 7 16 9 Throat Irritation 0 2 2 7 3 Rhinorrhea 0 3 0 5 3 Product Taste Abnormal 0 4 0 0 2 Eye Disorders Lacrimation Increased 0 1 2 2 2 For patients who experienced a decrease in peripheral oxygen saturation in the Test Dose Phase of Study 1, the decreases were generally transitory.
Two patients (one with a history of sleep apnea and one with intercurrent seizure) with decreases in peripheral oxygen saturation in the Test Dose Phase required therapeutic supplemental oxygen.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 3: Clinically Significant Drug Interactions With NAYZILAM
7.1CYP3A4 Inhibitors Clinical Impact: Concomitant use of CYP3A4 inhibitors may result in prolonged sedation because of a decrease in plasma clearance of midazolam. Intervention: Avoid co-administration of NAYZILAM with moderate or strong CYP3A4 inhibitors. NAYZILAM should be used with caution when co-administered with mild CYP3A4 inhibitors.
Examples: Moderate CYP3A4 inhibitors: erythromycin, diltiazem, verapamil Strong CYP3A4 inhibitors: ketoconazole, itraconazole, clarithromycin
7.2Opioids Clinical Impact: The concomitant use of benzodiazepines and opioids increases the risk of respiratory depression because of actions at different receptor sites in the CNS that control respiration. Benzodiazepines interact at GABA A sites and opioids interact primarily at mu receptors. When benzodiazepines and opioids are combined, the potential for benzodiazepines to significantly worsen opioid-related respiratory depression exists.
Intervention: Reserve concomitant prescribing of these drugs for use in patients for whom alternative treatment options are inadequate. Limit dosages and durations to the minimum required [see Warnings and Precautions (5.1) ]. Examples: Morphine, hydrocodone, oxymorphone, codeine, fentanyl
7.3Other Central Nervous System (CNS) Depressants Clinical Impact: Concomitant use of barbiturates, alcohol, or other CNS depressants may increase the risk of hypoventilation, airway obstruction, desaturation, or apnea and may contribute to profound and/or prolonged drug effect. Intervention: Reserve concomitant prescribing of these drugs for use in patients for whom alternative treatment options are inadequate. Limit dosages and durations to the minimum required [see Warnings and Precautions (5.5) ] .
Examples: Other benzodiazepines and sedatives/hypnotics, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, opioids, alcohol. CYP3A4 Inhibitors : Avoid co-administration of NAYZILAM with moderate or strong CYP3A4 inhibitors. NAYZILAM should be used with caution when co-administered with mild CYP3A4 inhibitors.
( 7.1 ) Opioids : Risk of respiratory depression is increased. ( 7.2 ) Other CNS Depressants : May increase the risks of hypoventilation, airway obstruction, desaturation, or apnea and may contribute to profound and/or prolonged drug effect. ( 7.3 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data, may cause fetal harm. ( 8.1 ) Lactation: Midazolam is excreted in human milk. Caution should be exercised when NAYZILAM is administered to a nursing woman. ( 8.2 ) Renal Impairment: Patients with renal impairment may have longer elimination half-lives for midazolam and its metabolites which may result in prolonged exposure. ( 8.6 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antiepileptic drugs (AEDs), such as NAYZILAM, during pregnancy. Healthcare providers are encouraged to recommend that pregnant women who are taking NAYZILAM during pregnancy enroll in the North American Antiepileptic Drug (NAAED) pregnancy registry by calling 1-888-233-2334 or visiting http://www.aedpregnancyregistry.org/. Risk Summary Neonates born to mothers using benzodiazepines late in pregnancy have been reported to experience symptoms of sedation and/or neonatal withdrawal [see Warnings and Precautions (5.9) and Clinical Considerations ].
Available data from published observational studies of pregnant women exposed to benzodiazepines do not report a clear association with benzodiazepines and major birth defects (see Data ). Administration of midazolam to rats and rabbits during the period of organogenesis or to rats during late pregnancy and throughout lactation at doses greater than those used clinically did not result in any apparent adverse effects on development (see Animal Data ). However, published data for midazolam and other benzodiazepines suggest the possibility of neuronal cell death and long-term effects on neurobehavioral and immunological function in animals following prenatal or early postnatal exposure at clinically relevant doses.
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Fetal/Neonatal Adverse Reactions Benzodiazepines cross the placenta and may produce respiratory depression, hypotonia, and sedation in neonates. Monitor neonates exposed to NAYZILAM during pregnancy or labor for signs of sedation, respiratory depression, hypotonia, and feeding problems. Monitor neonates exposed to NAYZILAM during pregnancy for signs of withdrawal.
Manage these neonates accordingly [see Warnings and Precautions (5.9) ] . Data Human Data Published data from observational studies on the use of benzodiazepines during pregnancy do not report a clear association with benzodiazepines and major birth defects. Although early studies reported an increased risk of congenital malformations with diazepam and chlordiazepoxide, there was no consistent pattern noted.
In addition, the majority of more recent case-control and cohort studies of benzodiazepine use during pregnancy, which were adjusted for confounding exposures to alcohol, tobacco and other medications, have not confirmed these findings. Animal Data When midazolam (0, 0.2, 1, or 4 mg/kg/day) was administered intravenously to pregnant rats during the period of organogenesis, no adverse effects on embryofetal development were observed. The highest dose tested, which was associated with minimal evidence of maternal toxicity, is approximately 4 times the maximum recommended human dose (MRHD) of 10 mg based on body surface area (mg/m 2 ).
When midazolam (0, 0.2, 0.6, and 2 mg/kg/day) was administered intravenously to rabbits during the period of organogenesis, no adverse effects on embryofetal development were reported. The high dose, which was not associated with evidence of maternal toxicity, is approximately 4 times the MRHD on a mg/m 2 basis. When midazolam (0, 0.2, 1, or 4 mg/kg/day) was administered intravenou… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antiepileptic drugs (AEDs), such as NAYZILAM, during pregnancy. Healthcare providers are encouraged to recommend that pregnant women who are taking NAYZILAM during pregnancy enroll in the North American Antiepileptic Drug (NAAED) pregnancy registry by calling 1-888-233-2334 or visiting http://www.aedpregnancyregistry.org/. Risk Summary Neonates born to mothers using benzodiazepines late in pregnancy have been reported to experience symptoms of sedation and/or neonatal withdrawal [see Warnings and Precautions (5.9) and Clinical Considerations ].
Available data from published observational studies of pregnant women exposed to benzodiazepines do not report a clear association with benzodiazepines and major birth defects (see Data ). Administration of midazolam to rats and rabbits during the period of organogenesis or to rats during late pregnancy and throughout lactation at doses greater than those used clinically did not result in any apparent adverse effects on development (see Animal Data ). However, published data for midazolam and other benzodiazepines suggest the possibility of neuronal cell death and long-term effects on neurobehavioral and immunological function in animals following prenatal or early postnatal exposure at clinically relevant doses.
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Fetal/Neonatal Adverse Reactions Benzodiazepines cross the placenta and may produce respiratory depression, hypotonia, and sedation in neonates. Monitor neonates exposed to NAYZILAM during pregnancy or labor for signs of sedation, respiratory depression, hypotonia, and feeding problems. Monitor neonates exposed to NAYZILAM during pregnancy for signs of withdrawal.
Manage these neonates accordingly [see Warnings and Precautions (5.9) ] . Data Human Data Published data from observational studies on the use of benzodiazepines during pregnancy do not report a clear association with benzodiazepines and major birth defects. Although early studies reported an increased risk of congenital malformations with diazepam and chlordiazepoxide, there was no consistent pattern noted.
In addition, the majority of more recent case-control and cohort studies of benzodiazepine use during pregnancy, which were adjusted for confounding exposures to alcohol, tobacco and other medications, have not confirmed these findings. Animal Data When midazolam (0, 0.2, 1, or 4 mg/kg/day) was administered intravenously to pregnant rats during the period of organogenesis, no adverse effects on embryofetal development were observed. The highest dose tested, which was associated with minimal evidence of maternal toxicity, is approximately 4 times the maximum recommended human dose (MRHD) of 10 mg based on body surface area (mg/m 2 ).
When midazolam (0, 0.2, 0.6, and 2 mg/kg/day) was administered intravenously to rabbits during the period of organogenesis, no adverse effects on embryofetal development were reported. The high dose, which was not associated with evidence of maternal toxicity, is approximately 4 times the MRHD on a mg/m 2 basis. When midazolam (0, 0.2, 1, or 4 mg/kg/day) was administered intravenously to female rats during late gestation and throughout lactation, no clear adverse effects were noted in the offspring.
The high dose, which was not associated with evidence of maternal toxicity, is approximately 4 times the MRHD on a mg/m 2 basis. In published animal studies, administration of benzodiazepines, including midazolam, or other drugs that enhance GABAergic neurotransmission to neo… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of NAYZILAM have been evaluated in the age group 12 to 17 years. Use of NAYZILAM in this age group is supported by evidence from an adequate and well-controlled study of NAYZILAM in adults and adolescents with seizure clusters [see Clinical Studies (14) ] and pharmacokinetic and safety data from adult and pediatric patients [see Clinical Pharmacology (12.3) ] . Safety and effectiveness in pediatric patients below the age of 12 years have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Safety and efficacy studies of NAYZILAM did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Geriatric patients have longer elimination half-lives for midazolam and its metabolites, which may result in prolonged drug exposure. Geriatric patients may have altered drug distribution; diminished hepatic and/or renal function; and subjects over 70 years of age may be particularly sensitive [see Clinical Pharmacology (12.3) ].
Administration of intramuscular (IM) midazolam to elderly patients has been associated with rare reports of death under circumstances compatible with cardiorespiratory depression [see Warnings and Precautions (5.4) ]. In most of these cases, the patients also received other CNS depressants capable of depressing respiration, especially narcotics [see Warnings and Precautions (5.1 , 5.5) ]. Close monitoring of geriatric patients is recommended.
🆘 Overdosage ▾
10 OVERDOSAGE Overdosage of benzodiazepines is characterized by central nervous system depression ranging from drowsiness to coma. In mild to moderate cases, symptoms can include drowsiness, confusion, dysarthria, lethargy, hypnotic state, diminished reflexes, ataxia, and hypotonia. Rarely, paradoxical or disinhibitory reactions (including agitation, irritability, impulsivity, violent behavior, confusion, restlessness, excitement, and talkativeness) may occur.
In severe overdosage cases, patients may develop respiratory depression and coma. Overdosage of benzodiazepines in combination with other CNS depressants (including alcohol and opioids) may be fatal [see Warnings and Precautions (5.2) ] . Markedly abnormal (lowered or elevated) blood pressure, heart rate, or respiratory rate raise the concern that additional drugs and/or alcohol are involved in the overdosage.
In managing benzodiazepine overdosage, employ general supportive measures, including intravenous fluids and airway maintenance. Flumazenil, a specific benzodiazepine receptor antagonist indicated for the complete or partial reversal of the sedative effects of benzodiazepines in the management of benzodiazepine overdosage, can lead to withdrawal and adverse reactions, including seizures, particularly in the context of mixed overdosage with drugs that increase seizure risk (e.g., tricyclic and tetracyclic antidepressants) and in patients with long-term benzodiazepine use and physical dependency.
The risk of withdrawal seizures with flumazenil may be increased in patients with epilepsy. Flumazenil is contraindicated in patients who have received a benzodiazepine for control of a potentially life-threatening condition (e.g., status epilepticus). If the decision is made to use flumazenil, it should be used as an adjunct to, not as a substitute for, supportive management of benzodiazepine overdosage.
See the flumazenil injection Prescribing Information. Consider contacting the Poison Help line (1-800-222-1222) or medical toxicologist for additional overdosage management recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The exact mechanism of action for midazolam is not fully understood, but it is thought to involve potentiation of GABAergic neurotransmission resulting from binding at the benzodiazepine site of the GABA A receptor.
12.2Pharmacodynamics The pharmacodynamic properties of midazolam and its metabolites, are similar to those of other benzodiazepines, including sedative, anxiolytic, amnestic, and hypnotic activities. The effects of midazolam on the CNS are dependent on the dose administered, the route of administration, and the presence or absence of other medications. Treatment with NAYZILAM was associated with effects on measures of sedation and measures of psychomotor performance [see Warnings and Precautions (5.5) ].
Sedation and psychomotor impairment effects generally began to occur within 10 minutes post dose with peak effects observed within 30 minutes to 2 hours post dose. The pharmacodynamic effects generally returned to near baseline levels by 4 hours post-dose.
12.3Pharmacokinetics Pharmacokinetics Based on a population pharmacokinetic analysis, plasma exposures (C max and AUC) of midazolam in epilepsy patients increase approximately proportional to dose from 5.0 mg to 15 mg, 0.5 and 1.5 times the recommended maximum total dose (5 mg Initial Dose + 5 mg Second Dose), respectively. Absorption Following nasal administration of a single 5 mg midazolam dose to healthy adults, midazolam was absorbed with median T max (range) of 17.3 (7.8 to 28.2) minutes; midazolam mean (±SD) C max and AUC 0-∞ were 54.7 (±30.4) ng/mL and 126.2 (±59) ng∙hr/mL, respectively.
The mean absolute bioavailability is approximately 44%. Distribution In adults and pediatric patients, midazolam is approximately 97% bound to plasma protein, principally albumin. In healthy volunteers, 1-hydroxy midazolam is bound to the extent of 89%.
The estimated total volume of distribution of midazolam is 226.5 L. In humans, midazolam has been shown to cross the placenta and enter into fetal circulation and has been detected in human milk and CSF [see Use in Specific Populations (8.1 , 8.2) ] . Elimination Following administration of NAYZILAM in clinical trials, median midazolam and 1-hydroxy-midazolam elimination half-lives ranged from 2.1 to 6.2 hours and 2.7 to 7.2 hours, respectively, independent of dose.
Metabolism Midazolam is primarily metabolized by liver and intestinal cytochrome P450 3A4 (CYP3A4) to its pharmacologic active metabolite, 1-hydroxy midazolam (also termed α-hydroxy-midazolam). Midazolam is also metabolized to two other minor metabolites: 4-hydroxy metabolite and 1,4-dihydroxy metabolite. The principal urinary excretion products are glucuronide conjugates of the hydroxylated derivatives.
Studies of the intravenous administration of 1-hydroxy-midazolam in humans suggest that 1-hydroxy-midazolam is at least as potent as the parent compound and may contribute to the net pharmacologic activity of midazolam. Excretion The principal urinary excretion product is 1-OH midazolam in the form of a glucuronide conjugate. Smaller amounts of the glucuronide conjugates of 4-hydroxy- and dihydroxy-midazolam are detected as well.
Specific Populations Geriatric Patients In a parallel group study of 2.5 mg and 5 mg doses of NAYZILAM, mean systemic exposure (AUC) and peak plasma concentrations (C max ) of midazolam were 21 to 45% higher in geriatric subjects (> 65 years old) as compared to non-geriatric subjects. The terminal half-life was increased by approximately 2 hours in the geriatric subjects because of a decrease in clearance [see Use in Specific Populations (8.5) ]. Obesity In a study comparing normal (n=20) and obese patients (n=20), the mean half-life of midazolam administered by parental route was greater in the obese group (5.9 versus 2.3 hours).
This was because of an increase of approximately 50% in the volume of distribution (Vd) corrected for total body weight. The clearance was not significantly… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action The exact mechanism of action for midazolam is not fully understood, but it is thought to involve potentiation of GABAergic neurotransmission resulting from binding at the benzodiazepine site of the GABA A receptor.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED / STORAGE AND HANDLING
16.1How Supplied NAYZILAM is supplied as a solution of midazolam. Each single-dose nasal spray unit delivers 5 mg of midazolam in 0.1 mL of solution. NAYZILAM is supplied in boxes of 2 nasal spray units (NDC 50474-500-15), each contained within an individual blister pack.
16.2Storage and Handling Do not open the blister packaging until ready to use. Do not test or prime before use. Do not use if the nasal spray unit appears damaged. Store at controlled room temperature 20°C to 25°C (68°F to 77°F). Excursions permitted to 15°C to 30°C (59°F to 86°F).
📦 Storage and Handling ▾
16.2Storage and Handling Do not open the blister packaging until ready to use. Do not test or prime before use. Do not use if the nasal spray unit appears damaged. Store at controlled room temperature 20°C to 25°C (68°F to 77°F). Excursions permitted to 15°C to 30°C (59°F to 86°F).
📋 Description ▾
11 DESCRIPTION NAYZILAM contains midazolam, a compound of the benzodiazepine class. Midazolam is chemically designated as 8-Chloro-6-(ο-fluorophenyl)-1-methyl-4H-imidazo[1,5-a][1,4]benzodiazepine, and it has the following structure: The empirical formula is C 18 H 13 ClFN 3 representing a molecular weight of 325.8. Midazolam, USP is a white or yellowish, crystalline powder that is practically insoluble in water, soluble in methanol, and freely soluble in acetone and in alcohol.
NAYZILAM nasal spray is a clear, colorless to yellowish colored liquid. Each single-dose NAYZILAM unit is for nasal administration and delivers 5 mg of midazolam in 0.1 mL of solution containing ethanol; PEG-6 methyl ether; polyethylene glycol 400; propylene glycol; and purified water. The pH range of solution is approximately 5.0 to 9.0.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients and caregivers to read the FDA-approved patient labeling (Medication Guide and Instructions for Use). Risks from Concomitant Use with Opioids Inform patients and caregivers that potentially fatal additive effects may occur if NAYZILAM is used with opioids and not to use NAYZILAM concomitantly with opioids unless supervised by a healthcare provider. If a decision is made to prescribe NAYZILAM concomitantly with opioids, instruct caregivers to follow patients closely for signs and symptoms of respiratory depression and sedation [see Warnings and Precautions (5.1) ] .
Abuse, Misuse, and Addiction Inform patients that use of NAYZILAM more frequently than recommended, even at recommended dosages, exposes users to risks of abuse, misuse, and addiction, which can lead to overdose and death, especially when used in combination with other medications (e.g., opioid analgesics), alcohol, and/or illicit substances. Inform patients about the signs and symptoms of benzodiazepine abuse, misuse, and addiction; to seek medical help if they develop these signs and/or symptoms; and on the proper disposal of unused drug [see Warnings and Precautions (5.2) and Drug Abuse and Dependence (9.2) ].
Withdrawal Reactions Inform patients that use of NAYZILAM more frequently than recommended may lead to clinically significant physical dependence and that abrupt discontinuation or rapid dosage reduction of NAYZILAM may precipitate acute withdrawal reactions, which can be life-threatening. Inform patients that in some cases, patients taking benzodiazepines have developed a protracted withdrawal syndrome with withdrawal symptoms lasting weeks to more than 12 months [see Warnings and Precautions (5.3) and Drug Abuse and Dependence (9.3) ].
Risks of Cardiorespiratory Adverse Reactions Warn patients and caregivers about the risks of respiratory depression, cardiac and respiratory arrest [see Warnings and Precautions (5.4) ] . Advise caregivers on the signs and symptoms of respiratory depression to look for, how long to observe patients after administering NAYZILAM, the circumstances under which a second dose should not be given, and the circumstances under which emergency medical care should be summoned [see Dosage and Administration (2.1) ]. CNS Depression from Concomitant Use with Other CNS Depressants Warn patients and caregivers that the use of NAYZILAM in combination with alcohol or other CNS depressant drugs may increase the risk of hypoventilation, airway obstruction, desaturation, or apnea and may contribute to profound and/or prolonged drug effect [see Warnings and Precautions (5.5) ] .
Caution patients against engaging in hazardous occupations requiring mental alertness, such as operating machinery, driving a motor vehicle or riding a bicycle until they have completely returned to their level of baseline functioning. Suicidal Behavior and Ideation Counsel patients, their caregivers, and families that AEDs, including NAYZILAM, may increase the risk of suicidal thoughts and behavior and that they should be alert for the emergence or worsening of the signs and symptoms of depression, any unusual changes in mood or behavior or the emergence of suicidal thoughts, behavior or thoughts about self-harm.
Behaviors of concern should be reported immediately to healthcare providers [see Warnings and Precautions (5.6) ] . Impaired Cognitive Function Warn patients that midazolam, including NAYZILAM, is associated with a high incidence of partial or complete impairment of recall for the next several hours. Counsel patients on when they can engage in activities requiring complete mental alertness, operate hazardous machinery, or drive a motor vehicle after taking NAYZILAM [see Warnings and Precautions (5.7) ].
Pregnancy Advise pregnant females that the use of NAYZILAM late in pregnancy can result in sedation (respiratory depression, lethargy, hypotonia) and/or withdrawal symptoms (hyperreflexia, irritability, restless… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
MEDICATION GUIDE NAYZILAM ® (NAY-zil-am) (midazolam) nasal spray, CIV This Medication Guide has been approved by the U.S. Food and Drug Administration Issued: 1/2023 What is the most important information I should know about NAYZILAM? NAYZILAM is a benzodiazepine medicine.
Taking benzodiazepines with opioid medicines, alcohol, or other central nervous system (CNS) depressants (including street drugs) can cause severe drowsiness, breathing problems (respiratory depression), coma, and death. Get emergency medical help right away if any of the following happens: shallow or slowed breathing breathing stops (which may lead to the heart stopping) excessive sleepiness (sedation) Do not drive or operate heavy machinery until you know how taking NAYZILAM with opioids may affect you. Risk of abuse, misuse, and addiction.
There is a risk of abuse, misuse, and addiction with benzodiazepines, including NAYZILAM, which can lead to overdose and serious side effects including coma and death. Serious side effects including coma and death have happened in people who have abused or misused benzodiazepines, including midazolam (the active ingredient in NAYZILAM). These serious side effects may also include delirium, paranoia, suicidal thoughts or actions, seizures, and difficulty breathing.
Call your healthcare provider or go to the nearest hospital emergency room right away if you have any of these serious side effects. You can develop an addiction even if you use NAYZILAM as prescribed by your healthcare provider. Use NAYZILAM exactly as your healthcare provider prescribed.
Do not share your NAYZILAM with other people . Keep NAYZILAM in a safe place and away from children. Physical dependence and withdrawal reactions .
Benzodiazepines, including NAYZILAM, can cause physical dependence and withdrawal reactions, especially if you use NAYZILAM daily. NAYZILAM is not intended for daily use. Do not suddenly stop using NAYZILAM without talking to your healthcare provider .
Stopping NAYZILAM suddenly can cause serious and life-threatening side effects, including, unusual movements, responses, or expressions, seizures, sudden and severe mental or nervous system changes, depression, seeing or hearing things that others do not see or hear, an extreme increase in activity or talking, losing touch with reality, and suicidal thoughts or actions. Call your healthcare provider or go to the nearest hospital emergency room right away if you have any of these symptoms. Some people who suddenly stop benzodiazepines have symptoms that can last for several weeks to more than 12 months , including, anxiety, trouble remembering, learning, or concentrating, depression, problems sleeping, feeling like insects are crawling under your skin, weakness, shaking, muscle twitching, burning or prickling feeling in your hands, arms, legs or feet, and ringing in your ears.
Physical dependence is not the same as drug addiction. Your healthcare provider can tell you more about the differences between physical dependence and drug addiction. Do not use more NAYZILAM than prescribed or use NAYZILAM more often than prescribed.
NAYZILAM can make you sleepy or dizzy and can slow your thinking and motor skills. Do not drive, operate heavy machinery, or do other dangerous activities until you know how NAYZILAM affects you. Do not drink alcohol or take other drugs that may make you sleepy or dizzy while using NAYZILAM without first talking to your healthcare provider.
When taken with alcohol or drugs that cause sleepiness or dizziness, NAYZILAM may make your sleepiness or dizziness worse. Like other antiepileptic medicines, NAYZILAM may cause suicidal thoughts or actions in a very small number of people, about 1 in 500. Call your healthcare provider right away if you have any of these symptoms, especially if they are new, worse, or worry you: thoughts about suicide or dying feeling agitated or restless acting aggressive, being angry, or violent attempts to commit suicide panic attacks acti… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Pharmacokinetics Based on a population pharmacokinetic analysis, plasma exposures (C max and AUC) of midazolam in epilepsy patients increase approximately proportional to dose from 5.0 mg to 15 mg, 0.5 and 1.5 times the recommended maximum total dose (5 mg Initial Dose + 5 mg Second Dose), respectively. Absorption Following nasal administration of a single 5 mg midazolam dose to healthy adults, midazolam was absorbed with median T max (range) of 17.3 (7.8 to 28.2) minutes; midazolam mean (±SD) C max and AUC 0-∞ were 54.7 (±30.4) ng/mL and 126.2 (±59) ng∙hr/mL, respectively.
The mean absolute bioavailability is approximately 44%. Distribution In adults and pediatric patients, midazolam is approximately 97% bound to plasma protein, principally albumin. In healthy volunteers, 1-hydroxy midazolam is bound to the extent of 89%.
The estimated total volume of distribution of midazolam is 226.5 L. In humans, midazolam has been shown to cross the placenta and enter into fetal circulation and has been detected in human milk and CSF [see Use in Specific Populations (8.1 , 8.2) ] . Elimination Following administration of NAYZILAM in clinical trials, median midazolam and 1-hydroxy-midazolam elimination half-lives ranged from 2.1 to 6.2 hours and 2.7 to 7.2 hours, respectively, independent of dose.
Metabolism Midazolam is primarily metabolized by liver and intestinal cytochrome P450 3A4 (CYP3A4) to its pharmacologic active metabolite, 1-hydroxy midazolam (also termed α-hydroxy-midazolam). Midazolam is also metabolized to two other minor metabolites: 4-hydroxy metabolite and 1,4-dihydroxy metabolite. The principal urinary excretion products are glucuronide conjugates of the hydroxylated derivatives.
Studies of the intravenous administration of 1-hydroxy-midazolam in humans suggest that 1-hydroxy-midazolam is at least as potent as the parent compound and may contribute to the net pharmacologic activity of midazolam. Excretion The principal urinary excretion product is 1-OH midazolam in the form of a glucuronide conjugate. Smaller amounts of the glucuronide conjugates of 4-hydroxy- and dihydroxy-midazolam are detected as well.
Specific Populations Geriatric Patients In a parallel group study of 2.5 mg and 5 mg doses of NAYZILAM, mean systemic exposure (AUC) and peak plasma concentrations (C max ) of midazolam were 21 to 45% higher in geriatric subjects (> 65 years old) as compared to non-geriatric subjects. The terminal half-life was increased by approximately 2 hours in the geriatric subjects because of a decrease in clearance [see Use in Specific Populations (8.5) ]. Obesity In a study comparing normal (n=20) and obese patients (n=20), the mean half-life of midazolam administered by parental route was greater in the obese group (5.9 versus 2.3 hours).
This was because of an increase of approximately 50% in the volume of distribution (Vd) corrected for total body weight. The clearance was not significantly different between groups. Patients with Renal Impairment Patients with renal impairment may have longer elimination half-lives for midazolam and its metabolites [see Use in Specific Populations (8.6) ] .
Midazolam and 1-hydroxy-midazolam pharmacokinetics in 6 ICU patients who developed acute renal failure (ARF) were compared with a normal renal function control group. Midazolam was administered as an infusion (5 to 15 mg/hr). Midazolam clearance was reduced (1.9 vs 2.8 mL/min/kg) and the half-life was prolonged (7.6 vs 13 hours) in the ARF patients.
The renal clearance of the 1-hydroxy-midazolam glucuronide was prolonged in the ARF group (4 vs 136 mL/min) and the half-life was prolonged (12 vs >25 hours). Plasma levels accumulated in all ARF patients to about ten times that of the parent drug. The relationship between accumulating metabolite levels and prolonged sedation is unclear.
In a study of chronic renal failure patients (n=15) receiving a single intravenous dose of midazolam, there was a 2-fold increase in the c… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics The pharmacodynamic properties of midazolam and its metabolites, are similar to those of other benzodiazepines, including sedative, anxiolytic, amnestic, and hypnotic activities. The effects of midazolam on the CNS are dependent on the dose administered, the route of administration, and the presence or absence of other medications. Treatment with NAYZILAM was associated with effects on measures of sedation and measures of psychomotor performance [see Warnings and Precautions (5.5) ].
Sedation and psychomotor impairment effects generally began to occur within 10 minutes post dose with peak effects observed within 30 minutes to 2 hours post dose. The pharmacodynamic effects generally returned to near baseline levels by 4 hours post-dose.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The effectiveness of NAYZILAM for the acute treatment of intermittent, stereotypic episodes of frequent seizure activity (i.e., seizure clusters, acute repetitive seizures) that are distinct from a patient's usual seizure pattern in patients with epilepsy 12 years of age and older was established in a randomized, double-blind, placebo-controlled trial (Study 1; NCT 01390220). Study 1 enrolled patients with epilepsy on a stable regimen of antiepileptic drugs who were identified by their physicians as having intermittent, stereotypic episodes of frequent seizure activity that were distinct from the patient's usual seizure pattern.
Study 1 was conducted in two phases: an open-label Test Dose Phase followed by a randomized, double-blind, placebo-controlled, Comparative Phase. In the Test Dose Phase, tolerability was assessed in 292 patients who, in the absence of a seizure, received two 5 mg doses of NAYZILAM (10 mg total dosage) separated by 10 minutes. Patients were excluded from participation in the Comparative Phase if they failed to meet pre-defined blood pressure, heart rate, sedation, electrocardiogram, and peripheral oxygen saturation criteria.
In the Comparative Phase, 201 patients treated a single seizure cluster episode in an outpatient setting with either a blinded dose of NAYZILAM 5 mg (134 patients) or placebo (67 patients). If the seizure activity persisted or recurred, patients in both groups had the option to receive a subsequent unblinded dose of NAYZILAM 5 mg to be used between 10 minutes and 6 hours after administration of the initial blinded dose of study drug. The primary efficacy endpoint for Study 1 was treatment success, defined as the termination of seizures within 10 minutes after the initial blinded dose of study drug and the absence of a recurrence of seizures within 6 hours of the initial blinded dose of study drug.
A statistically significantly higher percentage of NAYZILAM-treated patients met the primary efficacy endpoint, as shown in Table 4. Table 4: Primary Endpoint Results: Treatment Success (Study 1) NAYZILAM (N=134) Placebo (N=67) Treatment success (%) 53.7 34.3 95% CI (45.3, 62.2) (23.0, 45.7) p-value 0.011 Numerical differences in favor of NAYZILAM were observed on each of the components of the treatment success responder definition; termination of seizure(s) within 10 minutes after initial dose of study drug (80.6 versus 70.1%) and the absence of seizure recurrence between 10 minutes and 6 hours after the initial dose of study drug (58.2 versus 37.3%).
Study 1 also evaluated the occurrence and time to next seizure after the initial blinded dose of study drug. A smaller proportion of NAYZILAM-treated patients experienced the next seizure within 24 hours after the initial blinded dose of study drug (37.3% versus 46.3%). NAYZILAM-treated patients experienced a statistically longer time-to-next-seizure than the placebo group (Figure 1).
FIGURE 1: Kaplan-Meier Analysis of Time-to-Next-Seizure (Study 1) Analysis by gender revealed no substantial differences in treatment response. Informative subgroup analyses by age and race were not possible because of the small percentage of patients less than 18 years of age or 65 years of age or greater, and of non-White patients in the study. Figure 1
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE
9.1Controlled Substance NAYZILAM contains midazolam, a Schedule IV controlled substance.
9.2Abuse NAYZILAM is a benzodiazepine and a CNS depressant with a potential for abuse and addiction. Abuse is the intentional, non-therapeutic use of a drug, even once, for its desirable psychological or physiological effects. Misuse is the intentional use, for therapeutic purposes, of a drug by an individual in a way other than prescribed by a health care provider or for whom it was not prescribed.
Drug addiction is a cluster of behavioral, cognitive, and physiological phenomena that may include a strong desire to take the drug, difficulties in controlling drug use (e.g., continuing drug use despite harmful consequences, giving a higher priority to drug use than other activities and obligations), and possible tolerance or physical dependence. Even taking benzodiazepines as prescribed may put patients at risk for abuse and misuse of their medication. Abuse and misuse of benzodiazepines may lead to addiction.
Abuse and misuse of benzodiazepines often (but not always) involve the use of doses greater than the maximum recommended dosage and commonly involve concomitant use of other medications, alcohol, and/or illicit substances, which is associated with an increased frequency of serious adverse outcomes, including respiratory depression, overdose, or death. Benzodiazepines are often sought by individuals who abuse drugs and other substances, and by individuals with addictive disorders [see Warnings and Precautions (5.2) ].
The following adverse reactions have occurred with benzodiazepine abuse and/or misuse: abdominal pain, amnesia, anorexia, anxiety, aggression, ataxia, blurred vision, confusion, depression, disinhibition, disorientation, dizziness, euphoria, impaired concentration and memory, indigestion, irritability, muscle pain, slurred speech, tremors, and vertigo. The following severe adverse reactions have occurred with benzodiazepine abuse and/or misuse: delirium, paranoia, suicidal ideation and behavior, seizures, coma, breathing difficulty, and death.
Death is more often associated with polysubstance use (especially benzodiazepines with other CNS depressants such as opioids and alcohol). Midazolam was actively self-administered in primate models used to assess the positive reinforcing effects of psychoactive drugs. Midazolam produced physical dependence of a mild to moderate intensity in cynomolgus monkeys after 5 to 10 weeks of administration.
Assessment of the abuse-related subjective effects comparing NAYZILAM to oral midazolam syrup was conducted in adult subjects with a history of benzodiazepine recreational drug use. No statistically significant or clinically-relevant differences in subjective positive effects (i.e., Drug Liking, Overall Drug Liking, Take Drug Again, and High) were observed between NAYZILAM and oral midazolam syrup. However, subjective positive effects on all these measures were significantly greater for NAYZILAM than for placebo confirming that NAYZILAM has abuse potential.
Somnolence occurred at a similar rate in both midazolam groups, but euphoric mood occurred at a greater rate in NAYZILAM (4 to 16%) compared to the oral midazolam syrup (4 to 8.5%).
9.3Dependence Physical Dependence After Use of NAYZILAM More Frequently Than Recommended NAYZILAM may produce physical dependence if used more frequently than recommended. Physical dependence is a state that develops as a result of physiological adaptation in response to repeated drug use, manifested by withdrawal signs and symptoms after abrupt discontinuation or a significant dose reduction of a drug. Although NAYZILAM is indicated only for intermittent use [see Indications and Usage (1) and Dosage and Administration (2) ], if used more frequently than recommended, abrupt discontinuation or rapid dosage reduction or administration of flumazenil, a benzodiazepine antagonist, may precipitate acute withdrawal reactions, including… [Excerpted — this section continues on DailyMed.]
🔒 Controlled Substance ▾
9.1Controlled Substance NAYZILAM contains midazolam, a Schedule IV controlled substance.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Midazolam maleate was administered in the diet to mice and rats for 2 years at doses of 0, 1, 9, or 80 mg/kg/day. In female mice in the highest dose group there was a marked increase in the incidence of hepatic tumors. In high-dose male rats there was a small but statistically significant increase in benign thyroid follicular cell tumors.
The highest dose not associated with increased tumor incidences in mice and rats (9 mg/kg/day) is approximately 4 and 9 times, respectively, the recommended human dose (RHD) of 10 mg based on body surface area (mg/m 2 ). The pathogenesis of induction of these tumors is not known. These tumors were found after chronic administration, whereas human use will ordinarily be of single or several doses.
Mutagenesis Midazolam was negative for genotoxicity in in vitro (Ames, mammalian cell clastogenicity) and in vivo (mouse bone marrow micronucleus) assays. Impairment of Fertility When midazolam (0, 1, 4, or 16 mg/kg) was orally administered to male and female rats prior to and during mating and continuing in females throughout gestation and lactation, no adverse effects on male or female fertility were noted.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Midazolam maleate was administered in the diet to mice and rats for 2 years at doses of 0, 1, 9, or 80 mg/kg/day. In female mice in the highest dose group there was a marked increase in the incidence of hepatic tumors. In high-dose male rats there was a small but statistically significant increase in benign thyroid follicular cell tumors.
The highest dose not associated with increased tumor incidences in mice and rats (9 mg/kg/day) is approximately 4 and 9 times, respectively, the recommended human dose (RHD) of 10 mg based on body surface area (mg/m 2 ). The pathogenesis of induction of these tumors is not known. These tumors were found after chronic administration, whereas human use will ordinarily be of single or several doses.
Mutagenesis Midazolam was negative for genotoxicity in in vitro (Ames, mammalian cell clastogenicity) and in vivo (mouse bone marrow micronucleus) assays. Impairment of Fertility When midazolam (0, 1, 4, or 16 mg/kg) was orally administered to male and female rats prior to and during mating and continuing in females throughout gestation and lactation, no adverse effects on male or female fertility were noted.
📖 Instructions for Use ▾
Instructions for Use NAYZILAM ® (NAY-zil-am) (midazolam) nasal spray, CIV You and your family members or caregivers should read this Instructions for Use before you start using NAYZILAM nasal spray and each time you get a refill. There may be new information. This information does not take the place of talking to your healthcare provider about your medical condition or treatment.
If you and your family members or caregivers have any questions about NAYZILAM, ask your healthcare provider or pharmacist. Important : NAYZILAM is for use in the nose only . There is only 1 dose of NAYZILAM in the nasal spray unit .
Do not try to test or prime the nasal spray unit before use. You will lose the dose. Do not open the blister packaging until ready to use.
Do not use if the nasal spray unit appears damaged. Do not use past the expiration date printed on the blister packaging. Throw away (dispose of) the nasal spray unit after use.
How to use NAYZILAM nasal spray: Step 1: Peel open the blister packaging When ready to use, open the blister packaging. Hold blister packaging in the palm of your hand. On the foil backing, find the " Peel Here " tab and pull down (see Figure 1 ) .
Remove the nasal spray unit carefully. Step 2: Hold the nasal spray unit Hold the nasal spray unit with your thumb on the plunger and your middle and index fingers on each side of the nozzle ( see Figure 2 ). Do not press the plunger yet.
If you press the plunger now, you will lose the dose. Step 3: Place the tip into 1 nostril Place the tip of the nozzle into 1 nostril until your fingers on either side of the nozzle touches the bottom of the nose (see Figure 3 ) . Step 4: Press the plunger Press the plunger firmly to deliver the dose of NAYZILAM nasal spray (see Figure 4 ) .
Make sure to firmly press the plunger using 1 motion. The patient does not need to breathe deeply when you give them the medicine. What to do after the NAYZILAM nasal spray has been used: Remove the nozzle from the nostril after giving the dose.
Note: The plunger will remain inside the nasal spray unit after the dose is given. Throw away (dispose of) the nasal spray unit and blister packaging in the trash. What to do if a Second Dose is needed: Important: If the seizure cluster is continuing 10 minutes after the first dose of NAYZILAM, a second dose of NAYZILAM may be used if you have been told to do so by your healthcare provider .
If you need to give a second dose of NAYZILAM, follow the instructions in this Instructions for Use using a new nasal spray unit in the other nostril . (Repeat Step 1 through Step 4) Call for help if any of the following happens: Seizure or seizures continue after giving NAYZILAM to the person as instructed by the healthcare provider. Local Emergency Number:________________________ Seizure behavior in the person is different from other episodes.
Healthcare Provider's Number:_______________________ You are alarmed by the number or severity of the seizure or seizures in the person. Information for Emergency Responder You are alarmed by the color or breathing of the person. Time of first NAYZILAM dose:________________ Time of second NAYZILAM dose (if given):_________________________ Manufactured for UCB, Inc., Smyrna, GA 30080.
NAYZILAM ® is a registered trademark of the UCB Group of Companies. ©2022. All rights reserved. For more information, go to www.nayzilam.com or call 1-844-599-2273.
This Instructions for Use has been approved by the U.S. Food and Drug Administration Issued: 1/2023 Figure Figure 1 Figure 2 Figure 3 Figure 4 Figure
📄 Recent Major Changes ▾
Warnings and Precautions ( 5.9 ) 1/2023
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 5 mg Vial Blister Pack Carton NDC 50474-500-15 Rx only Nayzilam ® CIV (midazolam) nasal spray 5 mg FOR NASAL USE ONLY 2 Nasal Spray Units (1 dose per unit) DO NOT test or prime before use. PRINCIPAL DISPLAY PANEL - 5 mg Vial Blister Pack Carton