
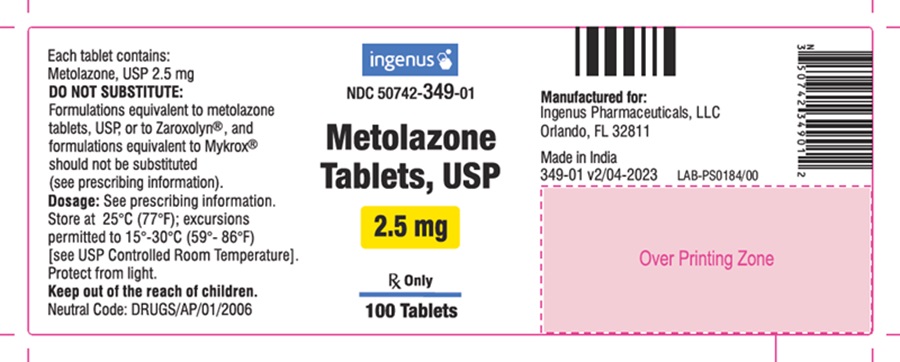
Metolazone 2.5 mg Tablet, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Thiazide-like Diuretic class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Metolazone, is used to reduce the swelling and fluid retention caused by heart failure or kidney disease. It also is used alone or with other medications to treat high blood pressure. Metolazone is in a class of medications called diuretics ('water pills'). It causes the kidneys to reduce the amount of water and salt in the body by increasing the amount of urine.
Read the full MedlinePlus article ↗- Think of your kidneys as a filter. Normally, they reabsorb a lot of the sodium (salt) that passes through them. Metolazone blocks that process, so more sodium — and the water that...
- What is metolazone actually doing in my body?
- Because metolazone makes your kidneys flush out more than just water — it also causes you to lose potassium, sodium, and magnesium. If those levels drop too low, you can develop mu...
- Why does my doctor keep checking my blood levels while I'm on this?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Metolazone — tap one for details:
Metolazone may be associated with lower levels of 8 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.228 | $22.79 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.5336 | $53.36 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.6266 | $62.66 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Metolazone 2.5 mg 00185-5050-01 | Sandoz | 100 tablets | $0.228 | AB | Availability likely | — |
| Metolazone 2.5 mg 00378-6172-01 | Mylan | 100 tablets | $0.228 | AB | Availability likely | — |
| Metolazone 2.5 mg 00904-7520-61 | Major | 100 tablets | $0.228 | AB | Availability likely | — |
| Metolazone 2.5 mgthis 50742-0349-01 | Ingenus | 100 tablets | $0.228 | AB | Availability likely | — |
| Metolazone 2.5 mg 51079-0023-20 | Mylan | 100 tablets | $0.228 | AB | Availability likely | — |
| Metolazone 2.5 mg 58657-0740-01 | Method | 100 tablets | $0.228 | AB | Availability likely | — |
| Metolazone 2.5 mg 58657-0940-01 | Method | 100 tablets | $0.228 | AB | Availability likely | — |
| Metolazone 2.5 mg 60687-0624-01 | American | 100 tablets | $0.228 | AB | Availability likely | — |
| Metolazone 2.5 mg 62332-0532-31 | Alembic | 100 tablets | $0.228 | AB | Availability likely | — |
| Metolazone 2.5 mg 69292-0562-01 | Amici | 100 tablets | $0.228 | AB | Availability likely | — |
| Metolazone 2.5 mg 72888-0052-01 | Advagen | 100 tablets | $0.228 | AB | Availability likely | — |
| Metolazone 2.5 mg 76385-0136-01 | Unichem | 100 tablets | $0.228 | AB | Availability likely | — |
| Metolazone 2.5 mg 10135-0765-01 | Marlex | 100 tablets | — | AB | FDA listed | — |
| Metolazone 2.5 mg 42571-0416-01 | Micro | 100 tablets | — | AB | Discontinued | — |
| Metolazone 2.5 mg 43353-0890-09 | Aphena | 9000 tablets | — | AB | FDA listed | — |
| Metolazone 2.5 mg 46708-0532-31 | Alembic | 100 tablets | — | AB | FDA listed | — |
| Metolazone 2.5 mg 48433-0068-20 | Safecor | 100 tablets | — | AB | FDA listed | — |
| Metolazone 2.5 mg 50090-6802-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Metolazone 2.5 mg 50090-6972-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Metolazone 2.5 mg 51407-0431-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Metolazone 2.5 mg 63629-8722-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Metolazone 2.5 mg 71610-0285-09 | Aphena | 9000 tablets | — | AB | FDA listed | — |
| Metolazone 2.5 mg 72162-1056-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Metolazone 2.5 mg 72162-2389-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Metolazone 2.5 mg 81005-0124-01 | Aarkish | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 50742-0349-01 You're viewing this | 100 TABLET in 1 BOTTLE (50742-349-01) | 2023-01-24 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Metolazone tablets are indicated for the treatment of salt and water retention including: • edema accompanying congestive heart failure; • edema accompanying renal diseases, including the nephrotic syndrome and states of diminished renal function. Metolazone tablets are also indicated for the treatment of hypertension, alone or in combination with other antihypertensive drugs of a different class. MYKROX Tablets, a more rapidly available form of metolazone, are intended for the treatment of new patients with mild to moderate hypertension.
A dose titration is necessary if MYKROX Tablets are to be substituted for metolazone tablets in the treatment of hypertension. See package circular for MYKROX Tablets. Usage In Pregnancy The routine use of diuretics in an otherwise healthy woman is inappropriate and exposes mother and fetus to unnecessary hazard.
Diuretics do not prevent development of toxemia of pregnancy, and there is no evidence that they are useful in the treatment of developed toxemia. Edema during pregnancy may arise from pathologic causes or from the physiologic and mechanical consequences of pregnancy. Metolazone tablets are indicated in pregnancy when edema is due to pathologic causes, just as it is in the absence of pregnancy (see PRECAUTIONS).
Dependent edema in pregnancy resulting from restriction of venous return by the expanded uterus is properly treated through elevation of the lower extremities and use of support hose; use of diuretics to lower intravascular volume in this case is illogical and unnecessary. There is hypervolemia during normal pregnancy which is harmful to neither the fetus nor the mother (in the absence of cardiovascular disease), but which is associated with edema, including generalized edema, in the majority of pregnant women. If this edema produces discomfort, increased recumbency will often provide relief.
In rare instances, this edema may cause extreme discomfort which is not relieved by rest. In these cases, a short course of diuretics may be appropriate.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Effective dosage of metolazone tablets should be individualized according to indication and patient response. A single daily dose is recommended. Therapy with metolazone tablets should be titrated to gain an initial therapeutic response and to determine the minimal dose possible to maintain the desired therapeutic response.
Usual Single Daily Dosage Schedules Suitable initial dosages will usually fall in the ranges given. Edema of cardiac failure: Metolazone tablets 5 to 20 mg once daily Edema of renal disease: Metolazone tablets 5 to 20 mg once daily. Mild to moderate essential hypertension: Metolazone tablets 2½ to 5 mg once daily.
New patients – MYKROX Tablets (metolazone tablets) (see MYKROX package circular). If considered desirable to switch patients currently on metolazone tablets to MYKROX, the dose should be determined by titration starting at one tablet (½ mg) once daily and increasing to two tablets (1 mg) once daily if needed. Treatment Of Edematous States The time interval required for the initial dosage to produce an effect may vary.
Diuresis and saluresis usually begin within one hour and persist for 24 hours or longer. When a desired therapeutic effect has been obtained, it may be advisable to reduce the dose if possible. The daily dose depends on the severity of the patient's condition, sodium intake, and responsiveness.
A decision to change the daily dose should be based on the results of thorough clinical and laboratory evaluations. If antihypertensive drugs or diuretics are given concurrently with metolazone tablets more careful dosage adjustment may be necessary. For patients who tend to experience paroxysmal nocturnal dyspnea, it may be advisable to employ a larger dose to ensure prolongation of diuresis and saluresis for a full 24-hour period.
Treatment Of Hypertension The time interval required for the initial dosage regimen to show effect may vary from three or four days to three to six weeks in the treatment of elevated blood pressure. Doses should be adjusted at appropriate intervals to achieve maximum therapeutic effect.
⛔ Contraindications ▾
CONTRAINDICATIONS Anuria, hepatic coma or precoma, known allergy or hypersensitivity to metolazone.
⚠️ Warnings ▾
WARNINGS Rapid Onset Hyponatremia And/Or Hypokalemia Rarely, the rapid onset of severe hyponatremia and/or hypokalemia has been reported following initial doses of thiazide and non-thiazide diuretics. When symptoms consistent with severe electrolyte imbalance appear rapidly, drug should be discontinued and supportive measures should be initiated immediately. Parenteral electrolytes may be required.
Appropriateness of therapy with this class of drugs should be carefully reevaluated. Hypokalemia Hypokalemia may occur with consequent weakness, cramps, and cardiac dysrhythmias. Serum potassium should be determined at regular and appropriate intervals, and dose reduction, potassium supplementation or addition of a potassium-sparing diuretic instituted whenever indicated.
Hypokalemia is a particular hazard in patients who are digitalized or who have or have had a ventricular arrhythmia; dangerous or fatal arrhythmias may be precipitated. Hypokalemia is dose related. Concomitant Therapy Lithium In general, diuretics should not be given concomitantly with lithium because they reduce its renal clearance and add a high risk of lithium toxicity.
Read prescribing information for lithium preparations before use of such concomitant therapy. Furosemide Unusually large or prolonged losses of fluids and electrolytes may result when metolazone tablets, are administered concomitantly to patients receiving furosemide (see PRECAUTIONS , Drug Interactions ). Other Antihypertensive Drugs When metolazone tablets are used with other antihypertensive drugs, particular care must be taken to avoid excessive reduction of blood pressure, especially during initial therapy.
Cross-Allergy Cross-allergy may occur when metolazone tablets are given to patients known to be allergic to sulfonamide-derived drugs, thiazides, or quinethazone. Sensitivity Reactions Sensitivity reactions (e.g., angioedema, bronchospasm) may occur with or without a history of allergy or bronchial asthma and may occur with the first dose of metolazone tablets.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Metolazone tablets are usually well tolerated, and most reported adverse reactions have been mild and transient. Many of metolazone tablets related adverse reactions represent extensions of its expected pharmacologic activity and can be attributed to either its antihypertensive action or its renal/metabolic actions. The following adverse reactions have been reported.
Several are single or comparably rare occurrences. Adverse reactions are listed in decreasing order of severity within body systems. Cardiovascular Chest pain/discomfort, orthostatic hypotension, excessive volume depletion, hemoconcentration, venous thrombosis, palpitations.
Central And Peripheral Nervous System Syncope, neuropathy, vertigo, paresthesias, psychotic depression, impotence, dizziness/lightheadedness, drowsiness, fatigue, weakness, restlessness (sometimes resulting in insomnia), headache. Dermatologic/Hypersensitivity Toxic epidermal necrolysis (TEN), Stevens-Johnson Syndrome, necrotizing angiitis (cutaneous vasculitis), skin necrosis, purpura, petechiae, dermatitis (photosensitivity), urticaria, pruritus, skin rashes. Gastrointestinal Hepatitis, intrahepatic cholestatic jaundice, pancreatitis, vomiting, nausea, epigastric distress, diarrhea, constipation, anorexia, abdominal bloating, abdominal pain.
Hematologic Aplastic/hypoplastic anemia, agranulocytosis, leukopenia, thrombocytopenia. Metabolic Hypokalemia, hyponatremia, hyperuricemia, hypochloremia, hypochloremic alkalosis, hyperglycemia, glycosuria, increase in serum urea nitrogen (BUN) or creatinine, hypophosphatemia, hypomagnesemia, hypercalcemia. Musculoskeletal Joint pain, acute gouty attacks, muscle cramps or spasm.
Other Transient blurred vision, chills, dry mouth. In addition, adverse reactions reported with similar antihypertensive-diuretics, but which have not been reported to date for metolazone tablets include: bitter taste, sialadenitis, xanthopsia, respiratory distress (including pneumonitis), and anaphylactic reactions. These reactions should be considered as possible occurrences with clinical usage of metolazone tablets.
Whenever adverse reactions are moderate or severe, metolazone tablets dosage should be reduced or therapy withdrawn. "To report SUSPECTED ADVERSE REACTIONS, contact Ingenus Pharmaceuticals, LLC at 1-877-748-1970 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch."
🔄 Drug Interactions ▾
Drug Interactions Diuretics Furosemide and probably other loop diuretics given concomitantly with metolazone can cause unusually large or prolonged losses of fluid and electrolytes (see WARNINGS ). Other Antihypertensives When metolazone tablets are used with other antihypertensive drugs, care must be taken, especially during initial therapy. Dosage adjustments of other antihypertensives may be necessary.
Alcohol, Barbiturates, And Narcotics The hypotensive effects of these drugs may be potentiated by the volume contraction that may be associated with metolazone therapy. Digitalis Glycosides Diuretic-induced hypokalemia can increase the sensitivity of the myocardium to digitalis. Serious arrhythmias can result.
Corticosteroids Or ACTH May increase the risk of hypokalemia and increase salt and water retention. Lithium Serum lithium levels may increase (see WARNINGS ). Curariform Drugs Diuretic-induced hypokalemia may enhance neuromuscular blocking effects of curariform drugs (such as tubocurarine) – the most serious effect would be respiratory depression which could proceed to apnea.
Accordingly, it may be advisable to discontinue metolazone tablets three days before elective surgery. Salicylates And Other Non-Steroidal Anti-Inflammatory Drugs May decrease the antihypertensive effects of metolazone tablets. Sympathomimetics Metolazone may decrease arterial responsiveness to norepinephrine, but this diminution is not sufficient to preclude effectiveness of the pressor agent for therapeutic use.
Insulin And Oral Antidiabetic Agents See Glucose Tolerance under PRECAUTIONS , General . Methenamine Efficacy may be decreased due to urinary alkalizing effect of metolazone. Anticoagulants Metolazone, as well as other thiazide-like diuretics, may affect the hypoprothrombinemic response to anticoagulants; dosage adjustments may be necessary.
🔄 Drug / Laboratory Test Interactions ▾
Drug/Laboratory Test Interactions None reported.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects Reproduction studies performed in mice, rabbits, and rats treated during the appropriate period of gestation at doses up to 50 mg/kg/day have revealed no evidence of harm to the fetus due to metolazone. There are, however, no adequate and well-controlled studies in pregnant women. Because animal reproduction studies are not always predictive of human response, metolazone tablets should be used during pregnancy only if clearly needed.
Metolazone crosses the placental barrier and appears in cord blood. Non-Teratogenic Effects The use of metolazone tablets in pregnant women requires that the anticipated benefit be weighed against possible hazards to the fetus. These hazards include fetal or neonatal jaundice, thrombocytopenia, and possibly other adverse reactions which have occurred in the adult.
It is not known what effect the use of the drug during pregnancy has on the later growth, development, and functional maturation of the child. No such effects have been reported with metolazone.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in pediatric patients have not been established in controlled clinical trials. There is limited experience with the use of metolazone tablets in pediatric patients with congestive heart failure, hypertension, bronchopulmonary dysplasia, nephrotic syndrome and nephrogenic diabetes insipidus. Doses used generally ranged from 0.05 to 0.1 mg/kg administered once daily and usually resulted in a 1 to 2.8 kg weight loss and 150 to 300 cc increase in urine output.
Not all patients responded and some gained weight. Those patients who did respond did so in the first few days of treatment. Prolonged use (beyond a few days) was generally associated with no further beneficial effect or a return to baseline status and is not recommended.
There is limited experience with the combination of metolazone tablets and furosemide in pediatric patients with furosemide-resistant edema. Some benefited while others did not or had an exaggerated response with hypovolemia, tachycardia, and orthostatic hypotension requiring fluid replacement. Severe hypokalemia was reported and there was a tendency for diuresis to persist for up to 24 hours after metolazone tablets were discontinued.
Hyperbilirubinemia has been reported in 1 neonate. Close clinical and laboratory monitoring of all children treated with diuretics is indicated. See CONTRAINDICATIONS , WARNINGS , PRECAUTIONS .
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of metolazone tablets did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
This drug is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
🆘 Overdosage ▾
OVERDOSAGE Intentional overdosage has been reported rarely with metolazone and similar diuretic drugs. Signs And Symptoms Orthostatic hypotension, dizziness, drowsiness, syncope, electrolyte abnormalities, hemoconcentration and hemodynamic changes due to plasma volume depletion may occur. In some instances depressed respiration may be observed.
At high doses, lethargy of varying degree may progress to coma within a few hours. The mechanism of CNS depression with thiazide overdosage is unknown. Also, GI irritation and hypermotility may occur.
Temporary elevation of BUN has been reported, especially in patients with impairment of renal function. Serum electrolyte changes and cardiovascular and renal function should be closely monitored. Treatment There is no specific antidote available but immediate evacuation of stomach contents is advised.
Dialysis is not likely to be effective. Care should be taken when evacuating the gastric contents to prevent aspiration, especially in the stuporous or comatose patient. Supportive measures should be initiated as required to maintain hydration, electrolyte balance, respiration, and cardiovascular and renal function.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Metolazone is a quinazoline diuretic, with properties generally similar to the thiazide diuretics. The actions of metolazone result from interference with the renal tubular mechanism of electrolyte reabsorption. Metolazone acts primarily to inhibit sodium reabsorption at the cortical diluting site and to a lesser extent in the proximal convoluted tubule.
Sodium and chloride ions are excreted in approximately equivalent amounts. The increased delivery of sodium to the distal tubular exchange site results in increased potassium excretion. Metolazone does not inhibit carbonic anhydrase.
A proximal action of metolazone has been shown in humans by increased excretion of phosphate and magnesium ions and by a markedly increased fractional excretion of sodium in patients with severely compromised glomerular filtration. This action has been demonstrated in animals by micropuncture studies. When metolazone tablets, are given, diuresis and saluresis usually begin within one hour and may persist for 24 hours or more.
For most patients, the duration of effect can be varied by adjusting the daily dose. High doses may prolong the effect. A single daily dose is recommended.
When a desired therapeutic effect has been obtained, it may be possible to reduce dosage to a lower maintenance level. The diuretic potency of metolazone tablets, at maximum therapeutic dosage is approximately equal to thiazide diuretics. However, unlike thiazides, metolazone tablets, may produce diuresis in patients with glomerular filtration rates below 20 mL/min.
Metolazone tablets, and furosemide administered concurrently have produced marked diuresis in some patients where edema or ascites was refractory to treatment with maximum recommended doses of these or other diuretics administered alone. The mechanism of this interaction is unknown (see WARNINGS and PRECAUTIONS , Drug Interactions ). Maximum blood levels of metolazone are found approximately eight hours after dosing.
A small fraction of metolazone is metabolized. Most of the drug is excreted in the unconverted form in the urine.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Metolazone tablets, USP, are bevel edged, round tablets, and are available in three strengths: 2½ mg, pink, debossed “ZNM” on one side, and “2½” on reverse side. NDC 50742-349-01 Bottle of 100’s 5 mg, white to off white, debossed “ZNM” on one side, and “5” on reverse side. NDC 50742-350-01 Bottle of 100’s 10 mg, pale yellow to yellow, debossed “ZNM” on one side, and “10” on reverse side.
NDC 50742-351-01 Bottle of 100’s Storage Store at 25°C (77°F); excursions permitted to 15°-30°C (59°-86°F) [See USP Controlled Room Temperature]. Protect from light. Keep out of the reach of children.
For more information about Metolazone Tablets call 1-877-748-1970. Manufactured for: Ingenus Pharmaceuticals, LLC Orlando, FL 32811 Made in India Revised: 04/2023 All brand names are the trademarks of their respective owners. Ingenus Logo
📋 Description ▾
DESCRIPTION Metolazone tablets, USP, for oral administration contain 2½, 5, or 10 mg of metolazone, USP, a diuretic/saluretic/antihypertensive drug of the quinazoline class. Metolazone has the molecular formula C 16 H 16 ClN 3 O 3 S, the chemical name 7-chloro-1, 2, 3, 4-tetrahydro-2-methyl-3-(2-methylphenyl)-4-oxo-6-quinazolinesulfonamide, and a molecular weight of 365.83. The structural formula is: Metolazone is only sparingly soluble in methanol and insoluble in water.
Inactive Ingredients: colloidal silicon dioxide, magnesium stearate, microcrystalline cellulose, iron oxide red and iron oxide yellow. Structure
💬 Information for Patients ▾
Information For Patients Patients should be informed of possible adverse effects, advised to take the medication as directed, and promptly report any possible adverse reactions to the treating physician.