
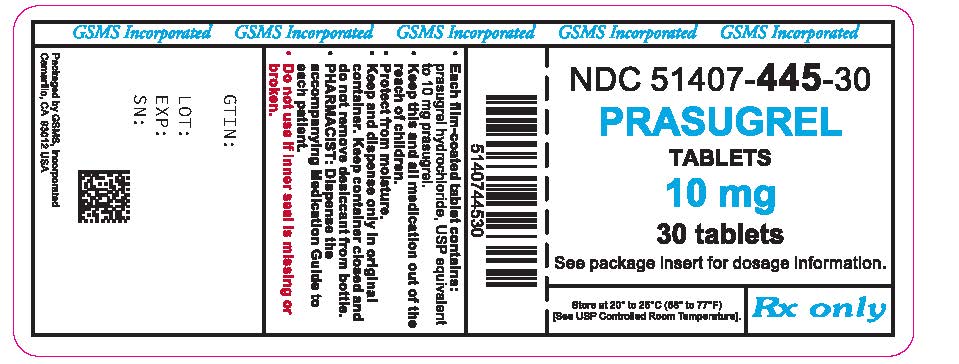
Prasugrel 10 mg Tablet, Film Coated, 30-count
Other active recalls for Prasugrel (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the P2Y12 Platelet Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Prasugrel is used to prevent serious problems with heart and blood vessels in certain people who have had a heart attack or severe chest pain. Prasugrel is in a class of medications called anti-platelet medications. It works by preventing platelets (a type of blood cell) from collecting and forming clots that may cause a heart attack or stroke.
Read the full MedlinePlus article ↗- After a heart procedure like a stent placement, your arteries need time to heal. During that time, platelets — tiny blood cells — can clump together and form a clot inside the sten...
- What exactly is prasugrel doing for me — why do I need it?
- Please don't — this is really important. Stopping prasugrel too early, especially in the first weeks after your procedure, can cause your stent to clot suddenly, which can trigger...
- Can I ever stop taking this on my own if I feel fine?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII R8WTH25YS2
Glyceryl dibehenate is a wax-like substance made from behenate fatty acids and glycerol. It functions as a binder and release-control agent in tablets and capsules, helping hold ingredients together and regulate how quickly the medicine dissolves and releases in your body.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 114S1GA41U
A man-made compound combining sugar (sucrose) with stearic acid, a fatty substance. It works as an emulsifier and surfactant, helping mix oil and water components and improving the texture and stability of the medicine.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII XHX3C3X673
Triacetin is a clear, oily liquid made from glycerin and acetic acid. It works as a plasticizer and solvent in medicines, helping soften coatings and improve how liquids mix together in formulations.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.5596 | $16.79 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Prasugrel 10 mg 00378-5186-93 | Mylan | 30 tablets | $0.262 | AB | Availability likely | — |
| Prasugrel 10 mg 29300-0302-13 | Unichem | 30 tablets | $0.262 | AB | Availability likely | — |
| Prasugrel 10 mg 60505-4643-03 | Apotex | 30 tablets | $0.262 | AB | Availability likely | — |
| Prasugrel 10 mg 60505-4856-03 | Apotex | 30 tablets | $0.262 | AB | Availability likely | — |
| Prasugrel 10 mg 60687-0883-21 | American | 1 tablet | $0.262 | AB | Availability likely | — |
| Prasugrel 10 mg 65162-0002-03 | Amneal | 30 tablets | $0.262 | — | Availability likely | — |
| Prasugrel 10 mg 16729-0273-10 | Accord | 30 tablets | $0.306 | AB | Availability likely | — |
| Effient 10 mg 00713-0882-30 | Cosette | 30 tablets | — | AB | FDA listed | — |
| Prasugrel 10 mg 43817-0240-01 | Panacea | 30 tablets | — | AB | FDA listed | — |
| Prasugrel 10 mgthis 51407-0445-30 | Golden | 30 tablets | — | AB | FDA listed | — |
| Prasugrel 10 mg 63629-4829-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Prasugrel 10 mg 65862-0830-03 | Aurobindo | 10 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 51407-0445-30 You're viewing this | 30 TABLET, FILM COATED in 1 BOTTLE, PLASTIC (51407-445-30) | 2021-01-20 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: BLEEDING RISK Prasugrel tablets can cause significant, sometimes fatal, bleeding [see Warnings and Precautions (5.1 , 5.2) and Adverse Reactions (6.1) ] . Do not use prasugrel tablets in patients with active pathological bleeding or a history of transient ischemic attack (TIA) or stroke [see Contraindications (4.1 , 4.2) ] . In patients ≥ 75 years of age, prasugrel tablets are generally not recommended, because of the increased risk of fatal and intracranial bleeding and uncertain benefit, except in high-risk situations (patients with diabetes or a history of prior myocardial infarction [MI]) where their effect appears to be greater and their use may be considered [see Use in Specific Populations (8.5) ] .
Do not start prasugrel tablets in patients likely to undergo urgent coronary artery bypass graft surgery (CABG). When possible, discontinue prasugrel tablets at least 7 days prior to any surgery [see Warnings and Precautions (5.2) ] . Additional risk factors for bleeding include: body weight < 60 kg, propensity to bleed, concomitant use of medications that increase the risk of bleeding (e.g., warfarin, heparin, fibrinolytic therapy, chronic use of nonsteroidal anti-inflammatory drugs [NSAIDs]) [see Warnings and Precautions (5.1) ].
Suspect bleeding in any patient who is hypotensive and has recently undergone coronary angiography, percutaneous coronary intervention (PCI), CABG, or other surgical procedures in the setting of prasugrel tablets [see Warnings and Precautions (5.1) ] . If possible, manage bleeding without discontinuing prasugrel tablets. Discontinuing prasugrel tablets, particularly in the first few weeks after acute coronary syndrome, increases the risk of subsequent cardiovascular (CV) events [see Warnings and Precautions (5.3) ] .
WARNING: BLEEDING RISK See full prescribing information for complete boxed warning. Prasugrel tablets can cause significant, sometimes fatal, bleeding ( 5.1 , 5.2 , 6.1 ). Do not use prasugrel tablets in patients with active pathological bleeding or a history of transient ischemic attack or stroke ( 4.1 , 4.2 ).
In patients ≥ 75 years of age, prasugrel tablets are generally not recommended, except in high-risk patients (diabetes or prior myocardial infarction [MI]), where their use may be considered ( 8.5 ). Do not start prasugrel tablets in patients likely to undergo urgent coronary artery bypass graft surgery (CABG). When possible, discontinue prasugrel tablets at least 7 days prior to any surgery ( 5.2 ).
Additional risk factors for bleeding include: body weight < 60 kg, propensity to bleed, concomitant use of medications that increase the risk of bleeding ( 5.1 ). Suspect bleeding in any patient who is hypotensive and has recently undergone invasive or surgical procedures ( 5.1 ). If possible, manage bleeding without discontinuing prasugrel tablets.
Stopping prasugrel tablets increases the risk of subsequent cardiovascular events ( 5.3 ).
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Prasugrel tablets are a P2Y 12 platelet inhibitor indicated for the reduction of thrombotic cardiovascular events (including stent thrombosis) in patients with acute coronary syndrome who are to be managed with percutaneous coronary intervention (PCI) as follows: Patients with unstable angina or non-ST-elevation myocardial infarction (NSTEMI) ( 1.1 ). Patients with ST-elevation myocardial infarction (STEMI) when managed with either primary or delayed PCI ( 1.1 ).
1.1Acute Coronary Syndrome Prasugrel tablets are indicated to reduce the rate of thrombotic CV events (including stent thrombosis) in patients with acute coronary syndrome (ACS) who are to be managed with percutaneous coronary intervention (PCI) as follows: Patients with unstable angina (UA) or non-ST-elevation myocardial infarction (NSTEMI). Patients with ST-elevation myocardial infarction (STEMI) when managed with primary or delayed PCI. Prasugrel tablets have been shown to reduce the rate of a combined endpoint of cardiovascular death, nonfatal myocardial infarction (MI), or nonfatal stroke compared to clopidogrel.
The difference between treatments was driven predominantly by MI, with no difference on strokes and little difference on CV death [see Clinical Studies (14) ] .
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Initiate prasugrel tablets treatment as a single 60 mg oral loading dose and then continue at 10 mg orally once daily. Patients taking prasugrel tablets should also take aspirin (75 mg to 325 mg) daily [see Drug Interactions (7.4) and Clinical Pharmacology (12.3) ] . Prasugrel tablets may be administered with or without food [see Clinical Pharmacology (12.3) and Clinical Studies (14) ] .
Timing of Loading Dose: In the clinical trial that established the efficacy and safety of prasugrel tablets, the loading dose of prasugrel tablets was not administered until coronary anatomy was established in UA/NSTEMI patients and in STEMI patients presenting more than 12 hours after symptom onset. In STEMI patients presenting within 12 hours of symptom onset, the loading dose of prasugrel tablets was administered at the time of diagnosis, although most received prasugrel tablets at the time of PCI [see Clinical Studies (14) ] .
For the small fraction of patients that required urgent CABG after treatment with prasugrel tablets, the risk of significant bleeding was substantial. Although it is generally recommended that antiplatelet therapy be administered promptly in the management of ACS because many cardiovascular events occur within hours of initial presentation, in a trial of 4033 NSTEMI patients, no clear benefit was observed when prasugrel tablets loading dose was administered prior to diagnostic coronary angiography compared to at the time of PCI; however, risk of bleeding was increased with early administration in patients undergoing PCI or early CABG.
Dosing in Low Weight Patients: Compared to patients weighing ≥ 60 kg, patients weighing < 60 kg have an increased exposure to the active metabolite of prasugrel and an increased risk of bleeding on a 10 mg once daily maintenance dose. Consider lowering the maintenance dose to 5 mg in patients < 60 kg. The effectiveness and safety of the 5 mg dose have not been prospectively studied [see Warnings and Precautions (5.1) , Adverse Reactions (6.1) , and Clinical Pharmacology (12.3) ] .
Initiate treatment with a single 60 mg oral loading dose ( 2 ). Continue at 10 mg once daily with or without food. Consider 5 mg once daily for patients < 60 kg ( 2 ).
Patients should also take aspirin (75 mg to 325 mg) daily ( 2 ).
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Prasugrel Tablets, USP are available containing prasugrel hydrochloride, USP equivalent to 5 mg or 10 mg prasugrel, respectively. The 5 mg tablets are yellow, film-coated, capsule shaped, unscored tablets debossed with M on one side of the tablet and PH1 on the other side. The 10 mg tablets are brown, film-coated, capsule shaped, unscored tablets debossed with M on one side of the tablet and PH2 on the other side.
5 mg and 10 mg tablets ( 3 ).
⛔ Contraindications ▾
4 CONTRAINDICATIONS Active pathological bleeding ( 4.1 ). Prior transient ischemic attack or stroke ( 4.2 ). Hypersensitivity to prasugrel or any component of the product ( 4.3 ).
4.1Active Bleeding Prasugrel tablets are contraindicated in patients with active pathological bleeding such as peptic ulcer or intracranial hemorrhage (ICH) [see Warnings and Precautions (5.1) and Adverse Reactions (6.1) ] .
4.2Prior Transient Ischemic Attack or Stroke Prasugrel tablets are contraindicated in patients with a history of prior transient ischemic attack (TIA) or stroke. In TRITON-TIMI 38 ( TR ial to Assess I mprovement in T herapeutic Outcomes by O ptimizing Platelet Inhibitio N with Prasugrel), patients with a history of TIA or ischemic stroke (> 3 months prior to enrollment) had a higher rate of stroke on prasugrel tablets (6.5%; of which 4.2% were thrombotic stroke and 2.3% were intracranial hemorrhage [ICH]) than on clopidogrel (1.2%; all thrombotic).
In patients without such a history, the incidence of stroke was 0.9% (0.2% ICH) and 1.0% (0.3% ICH) with prasugrel tablets and clopidogrel, respectively. Patients with a history of ischemic stroke within 3 months of screening and patients with a history of hemorrhagic stroke at any time were excluded from TRITON-TIMI 38. Patients who experience a stroke or TIA while on prasugrel tablets generally should have therapy discontinued [see Adverse Reactions (6.1) and Clinical Studies (14) ] .
4.3Hypersensitivity Prasugrel tablets are contraindicated in patients with hypersensitivity (e.g., anaphylaxis) to prasugrel or any component of the product [see Adverse Reactions (6.2) ] .
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS CABG-related bleeding: Risk increases in patients receiving prasugrel tablets who undergo CABG ( 5.2 ). Discontinuation of prasugrel tablets: Premature discontinuation increases risk of stent thrombosis, MI, and death ( 5.3 ). Thrombotic thrombocytopenic purpura (TTP): TTP has been reported with prasugrel tablets ( 5.4 ).
Hypersensitivity: Hypersensitivity including angioedema has been reported with prasugrel tablets including in patients with a history of hypersensitivity reaction to other thienopyridines ( 5.5 ).
5.1General Risk of Bleeding Thienopyridines, including prasugrel tablets, increase the risk of bleeding. With the dosing regimens used in TRITON-TIMI 38, TIMI (Thrombolysis in Myocardial Infarction) Major (clinically overt bleeding associated with a fall in hemoglobin ≥ 5 g/dL, or intracranial hemorrhage) and TIMI Minor (overt bleeding associated with a fall in hemoglobin of ≥ 3 g/dL but < 5 g/dL), bleeding events were more common on prasugrel tablets than on clopidogrel [see Adverse Reactions (6.1) ] . The bleeding risk is highest initially, as shown in Figure 1 (events through 450 days; inset shows events through 7 days).
Suspect bleeding in any patient who is hypotensive and has recently undergone coronary angiography, PCI, CABG, or other surgical procedures even if the patient does not have overt signs of bleeding. Do not use prasugrel tablets in patients with active bleeding, prior TIA or stroke [see Contraindications (4.1 , 4.2) ] . Other risk factors for bleeding are: Age ≥ 75 years.
Because of the risk of bleeding (including fatal bleeding) and uncertain effectiveness in patients ≥ 75 years of age, use of prasugrel tablets is generally not recommended in these patients, except in high-risk situations (patients with diabetes or history of myocardial infarction) where their effect appears to be greater and their use may be considered [see Adverse Reactions (6.1) , Use in Specific Populations (8.5) , Clinical Pharmacology (12.3) , and Clinical Studies (14) ] . CABG or other surgical procedure [see Warnings and Precautions (5.2) ] .
Body weight < 60 kg. Consider a lower (5 mg) maintenance dose [see Dosage and Administration (2) , Adverse Reactions (6.1) , and Use in Specific Populations (8.6) ] . Propensity to bleed (e.g., recent trauma, recent surgery, recent or recurrent gastrointestinal (GI) bleeding, active peptic ulcer disease, severe hepatic impairment, or moderate to severe renal impairment) [see Adverse Reactions (6.1) and Use in Specific Populations (8.7 , 8.8) ] .
Medications that increase the risk of bleeding (e.g., oral anticoagulants, chronic use of nonsteroidal anti-inflammatory drugs [NSAIDs], and fibrinolytic agents). Aspirin and heparin were commonly used in TRITON-TIMI 38 [see Drug Interactions (7.1 , 7.2 , 7.4) and Clinical Studies (14) ] . Thienopyridines inhibit platelet aggregation for the lifetime of the platelet (7-10 days), so withholding a dose will not be useful in managing a bleeding event or the risk of bleeding associated with an invasive procedure.
Because the half-life of prasugrel’s active metabolite is short relative to the lifetime of the platelet, it may be possible to restore hemostasis by administering exogenous platelets; however, platelet transfusions within 6 hours of the loading dose or 4 hours of the maintenance dose may be less effective. Figure 1: Non-CABG-Related TIMI Major or Minor Bleeding Events.
5.2Coronary Artery Bypass Graft Surgery-Related Bleeding The risk of bleeding is increased in patients receiving prasugrel tablets who undergo CABG. If possible, prasugrel tablets should be discontinued at least 7 days prior to CABG. Of the 437 patients who underwent CABG during TRITON-TIMI 38, the rates of CABG-related TIMI Major or Minor bleeding were 14.1% in the prasugrel tablets group and 4.5% in the clopidogrel group [see Adverse Reactions (6.1) ] .
The higher risk for bleeding events in patients treated with prasugrel tablets persisted…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are also discussed elsewhere in the labeling: Bleeding [see Boxed Warning and Warnings and Precautions (5.1 , 5.2) ] Thrombotic Thrombocytopenic Purpura [see Warnings and Precautions (5.4) ] Hypersensitivity Including Angioedema [see Warnings and Precautions (5.5) ] Bleeding, including life-threatening and fatal bleeding, is the most commonly reported adverse reaction ( 6.1 ). To report SUSPECTED ADVERSE REACTIONS, contact Mylan at 1-877-446-3679 (1-877-4-INFO-RX) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Safety in patients with ACS undergoing PCI was evaluated in a clopidogrel-controlled study, TRITON-TIMI 38, in which 6741 patients were treated with prasugrel tablets (60 mg loading dose and 10 mg once daily) for a median of 14.5 months (5802 patients were treated for over 6 months; 4136 patients were treated for more than 1 year). The population treated with prasugrel tablets was 27 to 96 years of age, 25% female, and 92% Caucasian. All patients in the TRITON-TIMI 38 study were to receive aspirin.
The dose of clopidogrel in this study was a 300 mg loading dose and 75 mg once daily. Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with the rates observed in other clinical trials of another drug and may not reflect the rates observed in practice. Drug Discontinuation The rate of study drug discontinuation because of adverse reactions was 7.2% for prasugrel tablets and 6.3% for clopidogrel.
Bleeding was the most common adverse reaction leading to study drug discontinuation for both drugs (2.5% for prasugrel tablets and 1.4% for clopidogrel). Bleeding Bleeding Unrelated to CABG Surgery In TRITON-TIMI 38, overall rates of TIMI Major or Minor bleeding adverse reactions unrelated to coronary artery bypass graft surgery (CABG) were significantly higher on prasugrel tablets than on clopidogrel, as shown in Table 1. Table 1: Non-CABG-Related Bleeding Patients may be counted in more than one row.
(TRITON-TIMI 38) Prasugrel Tablets (%) (N = 6741) Clopidogrel (%) (N = 6716) TIMI Major or Minor bleeding 4.5
3.4TIMI Major bleeding See 5.1 for definition. 2.2
1.7Life-threatening 1.3
0.8Fatal 0.3
0.1Symptomatic intracranial hemorrhage (ICH) 0.3
0.3Requiring inotropes 0.3
0.1Requiring surgical intervention 0.3
0.3Requiring transfusion (≥ 4 units) 0.7
0.5TIMI Minor bleeding 2.4
1.9Figure 1 demonstrates non-CABG-related TIMI Major or Minor bleeding. The bleeding rate is highest initially, as shown in Figure 1 (inset: Days 0 to 7) [see Warnings and Precautions (5.1) ] . Bleeding by Weight and Age In TRITON-TIMI 38, non-CABG-related TIMI Major or Minor bleeding rates in patients with the risk factors of age ≥ 75 years and weight < 60 kg are shown in Table 2.
Table 2: Bleeding Rates for Non-CABG-Related Bleeding by Weight and Age (TRITON-TIMI 38) Major/Minor Fatal Prasugrel Tablets 10 mg prasugrel tablets maintenance dose (%) Clopidogrel 75 mg clopidogrel maintenance dose (%) Prasugrel Tablets (%) Clopidogrel (%) Weight < 60 kg (N = 308 prasugrel tablets, N = 356 clopidogrel) 10.1 6.5 0.0
0.3Weight ≥ 60 kg (N = 6373 prasugrel tablets, N = 6299 clopidogrel) 4.2 3.3 0.3
0.1Age < 75 years (N = 5850 prasugrel tablets, N = 5822 clopidogrel) 3.8 2.9 0.2
0.1Age ≥ 75 years (N = 891 prasugrel tablets, N = 894 clopidogrel) 9.0 6.9 1.0
0.1Bleeding Related to CABG In TRITON-TIMI 38, 437 patients who received a thienopyridine underwent CABG during the course of the study. The rate of CABG-related TIMI Major or Minor bleeding was 14.1% for the prasugrel tablets group and 4.5% in the clopidogrel group (see Table 3). The higher risk for bleeding adverse reactions in patients treated with prasugrel tablets persisted up to 7 days from the most recent dose of study drug.
Table 3: CABG-Related Bleeding Patients may be counted in more than one r…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Opioids: Decreased exposure to prasugrel. Consider use of parenteral antiplatelet agent ( 7.3 ).
7.1Warfarin Coadministration of prasugrel tablets and warfarin increases the risk of bleeding [see Warnings and Precautions (5.1) and Clinical Pharmacology (12.3) ] .
7.2Nonsteroidal Anti-Inflammatory Drugs Coadministration of prasugrel tablets and NSAIDs (used chronically) may increase the risk of bleeding [see Warnings and Precautions (5.1) ] .
7.3Opioids As with other oral P2Y 12 inhibitors, coadministration of opioid agonists delay and reduce the absorption of prasugrel’s active metabolite presumably because of slowed gastric emptying [see Clinical Pharmacology (12.3) ] . Consider the use of a parenteral anti-platelet agent in acute coronary syndrome patients requiring coadministration of morphine or other opioid agonists.
7.4Other Concomitant Medications Prasugrel tablets can be administered with drugs that are inducers or inhibitors of cytochrome P450 enzymes [see Clinical Pharmacology (12.3) ] . Prasugrel tablets can be administered with aspirin (75 mg to 325 mg per day), heparin, GPIIb/IIIa inhibitors, statins, digoxin, and drugs that elevate gastric pH, including proton pump inhibitors and H 2 blockers [see Clinical Pharmacology (12.3) ] .
Drug Interaction Studies Potential for Other Drugs to Affect Prasugrel Inhibitors of CYP3A Ketoconazole (400 mg daily), a selective and potent inhibitor of CYP3A4 and CYP3A5, did not affect prasugrel-mediated inhibition of platelet aggregation or the active metabolite’s AUC and T max , but decreased the C max by 34% to 46%. Therefore, CYP3A inhibitors such as verapamil, diltiazem, indinavir, ciprofloxacin, clarithromycin, and grapefruit juice are not expected to have a significant effect on the pharmacokinetics of the active metabolite of prasugrel [see Drug Interactions (7.4) ] .
Inducers of Cytochromes P450 Rifampicin (600 mg daily), a potent inducer of CYP3A and CYP2B6 and an inducer of CYP2C9, CYP2C19, and CYP2C8, did not significantly change the pharmacokinetics of prasugrel’s active metabolite or its inhibition of platelet aggregation. Therefore, known CYP3A inducers such as rifampicin, carbamazepine, and other inducers of cytochromes P450 are not expected to have significant effect on the pharmacokinetics of the active metabolite of prasugrel [see Drug Interactions (7.4) ] . Drugs that Elevate Gastric pH Daily coadministration of ranitidine (an H 2 blocker) or lansoprazole (a proton pump inhibitor) decreased the C max of the prasugrel active metabolite by 14% and 29%, respectively, but did not change the active metabolite’s AUC and T max .
In TRITON-TIMI 38, prasugrel tablets were administered without regard to coadministration of a proton pump inhibitor or H 2 blocker [see Drug Interactions (7.4) ] . Statins Atorvastatin (80 mg daily), a drug metabolized by CYP450 3A4, did not alter the pharmacokinetics of prasugrel’s active metabolite or its inhibition of platelet aggregation [see Drug Interactions (7.4) ] . Heparin A single intravenous dose of unfractionated heparin (100 units/kg) did not significantly alter coagulation or the prasugrel-mediated inhibition of platelet aggregation; however, bleeding time was increased compared with either drug alone [see Drug Interactions (7.4) ] .
Aspirin Aspirin 150 mg daily did not alter prasugrel-mediated inhibition of platelet aggregation; however, bleeding time was increased compared with either drug alone [see Drug Interactions (7.4) ] . Warfarin A significant prolongation of the bleeding time was observed when prasugrel was coadministered with 15 mg of warfarin [see Drug Interactions (7.1) ] . Potential for Prasugrel to Affect Other Drugs In vitro metabolism studies demonstrate that prasugrel’s main circulating metabolites are not likely to cause clinically significant inhibition of CYP1A2, CYP2C9, CYP2C19, CYP2D6, or CYP3A, or induction of CYP1A2 or CYP3A.
Drugs Metabolized by CYP2B6 Prasugrel is a weak inhibito…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no data with prasugrel tablets use in pregnant women to inform a drug-associated risk. No structural malformations were observed in animal reproductive and developmental toxicology studies when rats and rabbits were administered prasugrel during organogenesis at doses of up to 30 times the recommended therapeutic exposures in humans [see Data ] . Due to the mechanism of action of prasugrel tablets, and the associated identified risk of bleeding, consider the benefits and risks of prasugrel tablets and possible risks to the fetus when prescribing prasugrel tablets to a pregnant woman [see Boxed Warning and Warnings and Precautions (5.1 , 5.3) ] .
The background risk of major birth defects and miscarriage for the indicated population is unknown. The background risk in the U.S. general population of major birth defects is 2-4% and of miscarriage is 15-20% of clinically recognized pregnancies. Data Animal Data In embryo-fetal developmental toxicology studies, pregnant rats and rabbits received prasugrel at maternally toxic oral doses equivalent to more than 40 times the human exposure.
A slight decrease in fetal body weight was observed, but there were no structural malformations in either species. In prenatal and postnatal rat studies, maternal treatment with prasugrel had no effect on the behavioral or reproductive development of the offspring at doses greater than 150 times the human exposure.
8.2Lactation Risk Summary There is no information regarding the presence of prasugrel in human milk, the effects on the breastfed infant, or the effects on milk production. Metabolites of prasugrel were found in rat milk [see Data ] . The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for prasugrel tablets and any potential adverse effects on the breastfed child from prasugrel tablets or from the underlying maternal condition.
Data Animal Data Following a 5 mg/kg oral dose of [ 14 C]-prasugrel to lactating rats, metabolites of prasugrel were detected in the maternal milk and blood.
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established. In a randomized, placebo-controlled trial, the primary objective of reducing the rate of vaso-occlusive crisis (painful crisis or acute chest syndrome) in pediatric patients, aged 2 to less than 18 years, with sickle cell anemia was not met.
8.5Geriatric Use In TRITON-TIMI 38, 38.5% of patients were ≥ 65 years of age and 13.2% were ≥ 75 years of age. The risk of bleeding increased with advancing age in both treatment groups, although the relative risk of bleeding (prasugrel tablets compared with clopidogrel) was similar across age groups. Patients ≥ 75 years of age who received prasugrel tablets 10 mg had an increased risk of fatal bleeding events (1.0%) compared to patients who received clopidogrel (0.1%).
In patients ≥ 75 years of age, symptomatic intracranial hemorrhage occurred in 7 patients (0.8%) who received prasugrel tablets and in 3 patients (0.3%) who received clopidogrel. Because of the risk of bleeding, and because effectiveness is uncertain in patients ≥ 75 years of age [see Clinical Studies (14) ] , use of prasugrel tablets is generally not recommended in these patients, except in high-risk situations (diabetes and past history of myocardial infarction) where their effect appears to be greater and their use may be considered [see Warnings and Precautions (5.1) , Clinical Pharmacology (12.3) , and Clinical Studies (14) ] .
8.6Low Body Weight In TRITON-TIMI 38, 4.6% of patients treated with prasugrel tablets had body weight < 60 kg. Individuals with body weight < 60 kg had an increased risk of bleeding and an increased exposure to the active metabolite of prasugrel [see Dosage and Administration (2) , Warnings and Precautions (5.1) , and Clinical Pharmacology (12.3) ] . Consider lowering the maintenance dose to 5 mg in patients…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no data with prasugrel tablets use in pregnant women to inform a drug-associated risk. No structural malformations were observed in animal reproductive and developmental toxicology studies when rats and rabbits were administered prasugrel during organogenesis at doses of up to 30 times the recommended therapeutic exposures in humans [see Data ] . Due to the mechanism of action of prasugrel tablets, and the associated identified risk of bleeding, consider the benefits and risks of prasugrel tablets and possible risks to the fetus when prescribing prasugrel tablets to a pregnant woman [see Boxed Warning and Warnings and Precautions (5.1 , 5.3) ] .
The background risk of major birth defects and miscarriage for the indicated population is unknown. The background risk in the U.S. general population of major birth defects is 2-4% and of miscarriage is 15-20% of clinically recognized pregnancies. Data Animal Data In embryo-fetal developmental toxicology studies, pregnant rats and rabbits received prasugrel at maternally toxic oral doses equivalent to more than 40 times the human exposure.
A slight decrease in fetal body weight was observed, but there were no structural malformations in either species. In prenatal and postnatal rat studies, maternal treatment with prasugrel had no effect on the behavioral or reproductive development of the offspring at doses greater than 150 times the human exposure.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established. In a randomized, placebo-controlled trial, the primary objective of reducing the rate of vaso-occlusive crisis (painful crisis or acute chest syndrome) in pediatric patients, aged 2 to less than 18 years, with sickle cell anemia was not met.
🧓 Geriatric Use ▾
8.5Geriatric Use In TRITON-TIMI 38, 38.5% of patients were ≥ 65 years of age and 13.2% were ≥ 75 years of age. The risk of bleeding increased with advancing age in both treatment groups, although the relative risk of bleeding (prasugrel tablets compared with clopidogrel) was similar across age groups. Patients ≥ 75 years of age who received prasugrel tablets 10 mg had an increased risk of fatal bleeding events (1.0%) compared to patients who received clopidogrel (0.1%).
In patients ≥ 75 years of age, symptomatic intracranial hemorrhage occurred in 7 patients (0.8%) who received prasugrel tablets and in 3 patients (0.3%) who received clopidogrel. Because of the risk of bleeding, and because effectiveness is uncertain in patients ≥ 75 years of age [see Clinical Studies (14) ] , use of prasugrel tablets is generally not recommended in these patients, except in high-risk situations (diabetes and past history of myocardial infarction) where their effect appears to be greater and their use may be considered [see Warnings and Precautions (5.1) , Clinical Pharmacology (12.3) , and Clinical Studies (14) ] .
🆘 Overdosage ▾
10 OVERDOSAGE
10.1Signs and Symptoms Platelet inhibition by prasugrel is rapid and irreversible, lasting for the life of the platelet, and is unlikely to be increased in the event of an overdose. In rats, lethality was observed after administration of 2000 mg/kg. Symptoms of acute toxicity in dogs included emesis, increased serum alkaline phosphatase, and hepatocellular atrophy.
Symptoms of acute toxicity in rats included mydriasis, irregular respiration, decreased locomotor activity, ptosis, staggering gait, and lacrimation.
10.2Recommendations about Specific Treatment Platelet transfusion may restore clotting ability. The prasugrel active metabolite is not likely to be removed by dialysis.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Prasugrel is an inhibitor of platelet activation and aggregation through the irreversible binding of its active metabolite to the P2Y 12 class of ADP receptors on platelets.
12.2Pharmacodynamics Prasugrel produces inhibition of platelet aggregation to 20 μM or 5 μM ADP, as measured by light transmission aggregometry. Following a 60 mg loading dose of prasugrel tablets, approximately 90% of patients had at least 50% inhibition of platelet aggregation by 1 hour. Maximum platelet inhibition was about 80% (see Figure 2).
Mean steady-state inhibition of platelet aggregation was about 70% following 3 to 5 days of dosing at 10 mg daily after a 60 mg loading dose of prasugrel tablets. Platelet aggregation gradually returns to baseline values over 5-9 days after discontinuation of prasugrel, this time course being a reflection of new platelet production rather than pharmacokinetics of prasugrel. Discontinuing clopidogrel 75 mg and initiating a prasugrel 10 mg maintenance dose with or without a prasugrel 60 mg loading dose results in a decrease of 14 percentage points in maximum platelet aggregation (MPA) by Day 7.
This decrease in MPA is not greater than that typically produced by a 10 mg maintenance dose of prasugrel alone. The relationship between inhibition of platelet aggregation and clinical activity has not been established. Figure 2: Inhibition (Mean ± SD) of 20 μM ADP-induced Platelet Aggregation (IPA) Measured by Light Transmission Aggregometry after Prasugrel 60 mg.
5 mg in Low Body Weight Patients In patients with stable coronary artery disease, mean platelet inhibition in subjects < 60 kg taking 5 mg prasugrel was similar to that of subjects ≥ 60 kg taking 10 mg prasugrel. The relationship between inhibition of platelet aggregation and clinical activity has not been established.
12.3Pharmacokinetics Prasugrel is a prodrug and is rapidly metabolized to a pharmacologically active metabolite and inactive metabolites. The active metabolite has an elimination half-life of about 7 hours (range 2-15 hours). Healthy subjects, patients with stable atherosclerosis, and patients undergoing PCI show similar pharmacokinetics.
Absorption and Binding Following oral administration, ≥ 79% of the dose is absorbed. The absorption and metabolism are rapid, with peak plasma concentrations (C max ) of the active metabolite occurring approximately 30 minutes after dosing. The active metabolite’s exposure (AUC) increases slightly more than proportionally over the dose range of 5 to 60 mg.
Repeated daily doses of 10 mg do not lead to accumulation of the active metabolite. In a study of healthy subjects given a single 15 mg dose, the AUC of the active metabolite was unaffected by a high-fat, high-calorie meal, but C max was decreased by 49% and T max was increased from 0.5 to 1.5 hours. Prasugrel tablets can be administered without regard to food.
The active metabolite is bound about 98% to human serum albumin. Metabolism and Elimination Prasugrel is not detected in plasma following oral administration. It is rapidly hydrolyzed in the intestine to a thiolactone, which is then converted to the active metabolite by a single step, primarily by CYP3A4 and CYP2B6 and to a lesser extent by CYP2C9 and CYP2C19.
The estimates of apparent volume of distribution of prasugrel’s active metabolite ranged from 44 to 68 L and the estimates of apparent clearance ranged from 112 to 166 L/hr in healthy subjects and patients with stable atherosclerosis. The active metabolite is metabolized to two inactive compounds by S-methylation or conjugation with cysteine. The major inactive metabolites are highly bound to human plasma proteins.
Approximately 68% of the prasugrel dose is excreted in the urine and 27% in the feces as inactive metabolites. Specific Populations Geriatric Patients In a study of 32 healthy subjects between the ages of 20 and 80 years, age had no significant effect on pharmacokinetics of prasugrel’s ac…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Prasugrel is an inhibitor of platelet activation and aggregation through the irreversible binding of its active metabolite to the P2Y 12 class of ADP receptors on platelets.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Prasugrel Tablets, USP are available containing prasugrel hydrochloride, USP equivalent to 5 mg or 10 mg prasugrel, respectively. The 5 mg tablets are yellow, film-coated, capsule shaped, unscored tablets debossed with M on one side of the tablet and PH1 on the other side. They are available as follows: NDC 51407-444-30 bottles of 30 tablets The 10 mg tablets are brown, film-coated, capsule shaped, unscored tablets debossed with M on one side of the tablet and PH2 on the other side.
They are available as follows: NDC 51407-445-30 bottles of 30 tablets
16.2Storage and Handling Store at 20º to 25ºC (68º to 77ºF). [See USP Controlled Room Temperature.] Protect from moisture. Keep and dispense only in original container. Keep container closed and do not remove desiccant from bottle. Do not break the tablet. PHARMACIST: Dispense a Medication Guide with each prescription.
📋 Description ▾
11 DESCRIPTION Prasugrel tablets, USP contain prasugrel, a thienopyridine class inhibitor of platelet activation and aggregation mediated by the P2Y 12 ADP receptor. Prasugrel tablets are formulated as the hydrochloride salt, a racemate, which is chemically designated as 5-[(1RS)-2-cyclopropyl-1-(2-fluorophenyl)-2-oxoethyl]-4,5,6,7-tetrahydrothieno[3,2-c]pyridin-2-yl acetate hydrochloride. Prasugrel hydrochloride has the molecular formula C 20 H 20 FNO 3 S•HCl representing a molecular weight of 409.90.
The chemical structure of prasugrel hydrochloride is: Prasugrel hydrochloride, USP is a white to light brown crystalline solid. It is soluble at pH 2, slightly soluble at pH 3 to 4, and practically insoluble at pH 6 to 7.5. It also dissolves freely in methanol and is slightly soluble in 1- and 2-propanol and acetone.
It is practically insoluble in diethyl ether and ethyl acetate. Prasugrel tablets are available for oral administration as 5 mg or 10 mg capsule shaped, film-coated, unscored tablets, debossed on each side. Each yellow 5 mg tablet is manufactured with 5.49 mg prasugrel hydrochloride, equivalent to 5 mg prasugrel and each brown 10 mg tablet with 10.98 mg prasugrel hydrochloride, equivalent to 10 mg of prasugrel.
Other ingredients include crospovidone, glyceryl dibehenate, hypromellose, lactose monohydrate, mannitol, pregelatinized starch (corn), sucrose stearic acid esters, titanium dioxide, triacetin and yellow iron oxide. The 5 mg tablets also contain FD&C Yellow No. 6 Aluminum Lake.
The 10 mg tablets also contain black iron oxide and red iron oxide. Meets USP Dissolution Test 2. Prasugrel Hydrochloride Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Medication Guide ). Administration: Advise patients not to break prasugrel tablets. Remind patients not to discontinue prasugrel tablets without first discussing it with the physician who prescribed prasugrel tablets [see Warnings and Precautions (5.3) ] .
Inform patients to keep prasugrel tablets in the container in which they come, and keep the container closed tightly with the desiccant inside. Bleeding: Inform patients that they: will bruise and bleed more easily. will take longer than usual to stop bleeding. should report any unanticipated, prolonged, or excessive bleeding, or blood in their stool or urine [see Warnings and Precautions (5.1) ] . Thrombotic Thrombocytopenic Purpura: Inform patients that TTP is a rare but serious condition that has been reported with prasugrel tablets.
Instruct patients to get prompt medical attention if they experience symptoms of TTP that cannot otherwise be explained [see Warnings and Precautions (5.4) ] . Hypersensitivity: Inform patients that they may have hypersensitivity reactions and to seek immediate medical attention if any signs and symptoms of a hypersensitivity reaction occur. Patients who have had hypersensitivity reactions to other thienopyridines may have hypersensitivity reactions to prasugrel tablets.
Invasive Procedures: Instruct patients to: inform physicians and dentists that they are taking prasugrel tablets before any invasive procedure is scheduled [see Warnings and Precautions (5.1) ] . tell the doctor performing the invasive procedure to talk to the prescribing healthcare professional before stopping prasugrel tablets. Concomitant Medications: Ask patients to list all prescription medications, over-the-counter medications, or dietary supplements they are taking or plan to take so the physician knows about other treatments that may affect bleeding risk (e.g., warfarin and NSAIDs) [see Drug Interactions (7.1 , 7.2) ] .
💬 Medication Guide ▾
Medication Guide Prasugrel Tablets, USP (pra′ soo grel) What is the most important information I should know about prasugrel tablets? Prasugrel tablets are used to lower your chance of having a heart attack or other serious problems with your heart or blood vessels. But, prasugrel tablets can cause bleeding, which can be serious, and sometimes lead to death.
You should not start to take prasugrel tablets if it is likely that you will have heart bypass surgery (coronary artery bypass graft surgery or CABG) right away. You have a higher risk of bleeding if you take prasugrel tablets and then have heart bypass surgery. What are prasugrel tablets?
Prasugrel tablets are a prescription medicine used to treat people who: have had a heart attack or severe chest pain that happens when your heart does not get enough oxygen, and have been treated with a procedure called “angioplasty” (also called balloon angioplasty). Prasugrel tablets are used to lower your chance of having another serious problem with your heart or blood vessels, such as another heart attack, a stroke, blood clots in your stent, or death. Platelets are blood cells that help with normal blood clotting.
Prasugrel tablets help prevent platelets from sticking together and forming a clot that can block an artery or a stent. It is not known if prasugrel tablets are safe and work in children. Who should not take prasugrel tablets?
Do not take prasugrel tablets if you: currently have abnormal bleeding, such as stomach or intestinal bleeding, or bleeding in your head have had a stroke or “mini-stroke” (also known as transient ischemic attack or TIA) are allergic to prasugrel or any of the ingredients in prasugrel tablets. See the end of this Medication Guide for a list of ingredients in prasugrel tablets. Get medical help right away if you think you may be having a stroke or TIA.
Symptoms that you may be having a stroke or TIA include: sudden slurring of speech, sudden weakness or numbness in one part of your body, sudden blurry vision, or sudden severe headache. If you have a stroke or TIA while taking prasugrel tablets, your doctor will probably stop your prasugrel tablets. Follow your doctor's instructions about stopping prasugrel tablets.
Do not stop taking prasugrel tablets unless your doctor tells you to. Before having any surgery, you should talk to your doctor about stopping prasugrel tablets. If possible, prasugrel tablets should be stopped at least 1 week (7 days) before any surgery, as instructed by the doctor who prescribed prasugrel tablets for you.
Your risk of bleeding while taking prasugrel tablets may be higher if you also: have had trauma, such as an accident or surgery have stomach or intestine bleeding that is recent or keeps coming back, or you have a stomach ulcer have severe liver problems have moderate to severe kidney problems weigh less than 132 pounds take other medicines that increase your risk of bleeding, including: warfarin sodium (Coumadin ® , Jantoven ® ) a medicine that contains heparin other medicines to prevent or treat blood clots o regular daily use of nonsteroidal anti-inflammatory drugs (NSAIDs) Tell your doctor if you take any of these medicines.
Ask your doctor if you are not sure if your medicine is one listed above. Prasugrel tablets increase your risk of bleeding because they lessen the ability of your blood to clot. While you take prasugrel tablets: you will bruise and bleed more easily you are more likely to have nose bleeds it will take longer for any bleeding to stop Call your doctor right away if you have any of these signs or symptoms of bleeding: unexpected bleeding or bleeding that lasts a long time bleeding that is severe or you cannot control pink or brown urine red or black stool (looks like tar) bruises that happen without a known cause or get larger cough up blood or blood clots vomit blood or your vomit looks like “coffee grounds” Do not stop taking prasugrel tablets without talking to the doctor who prescribes them for…