
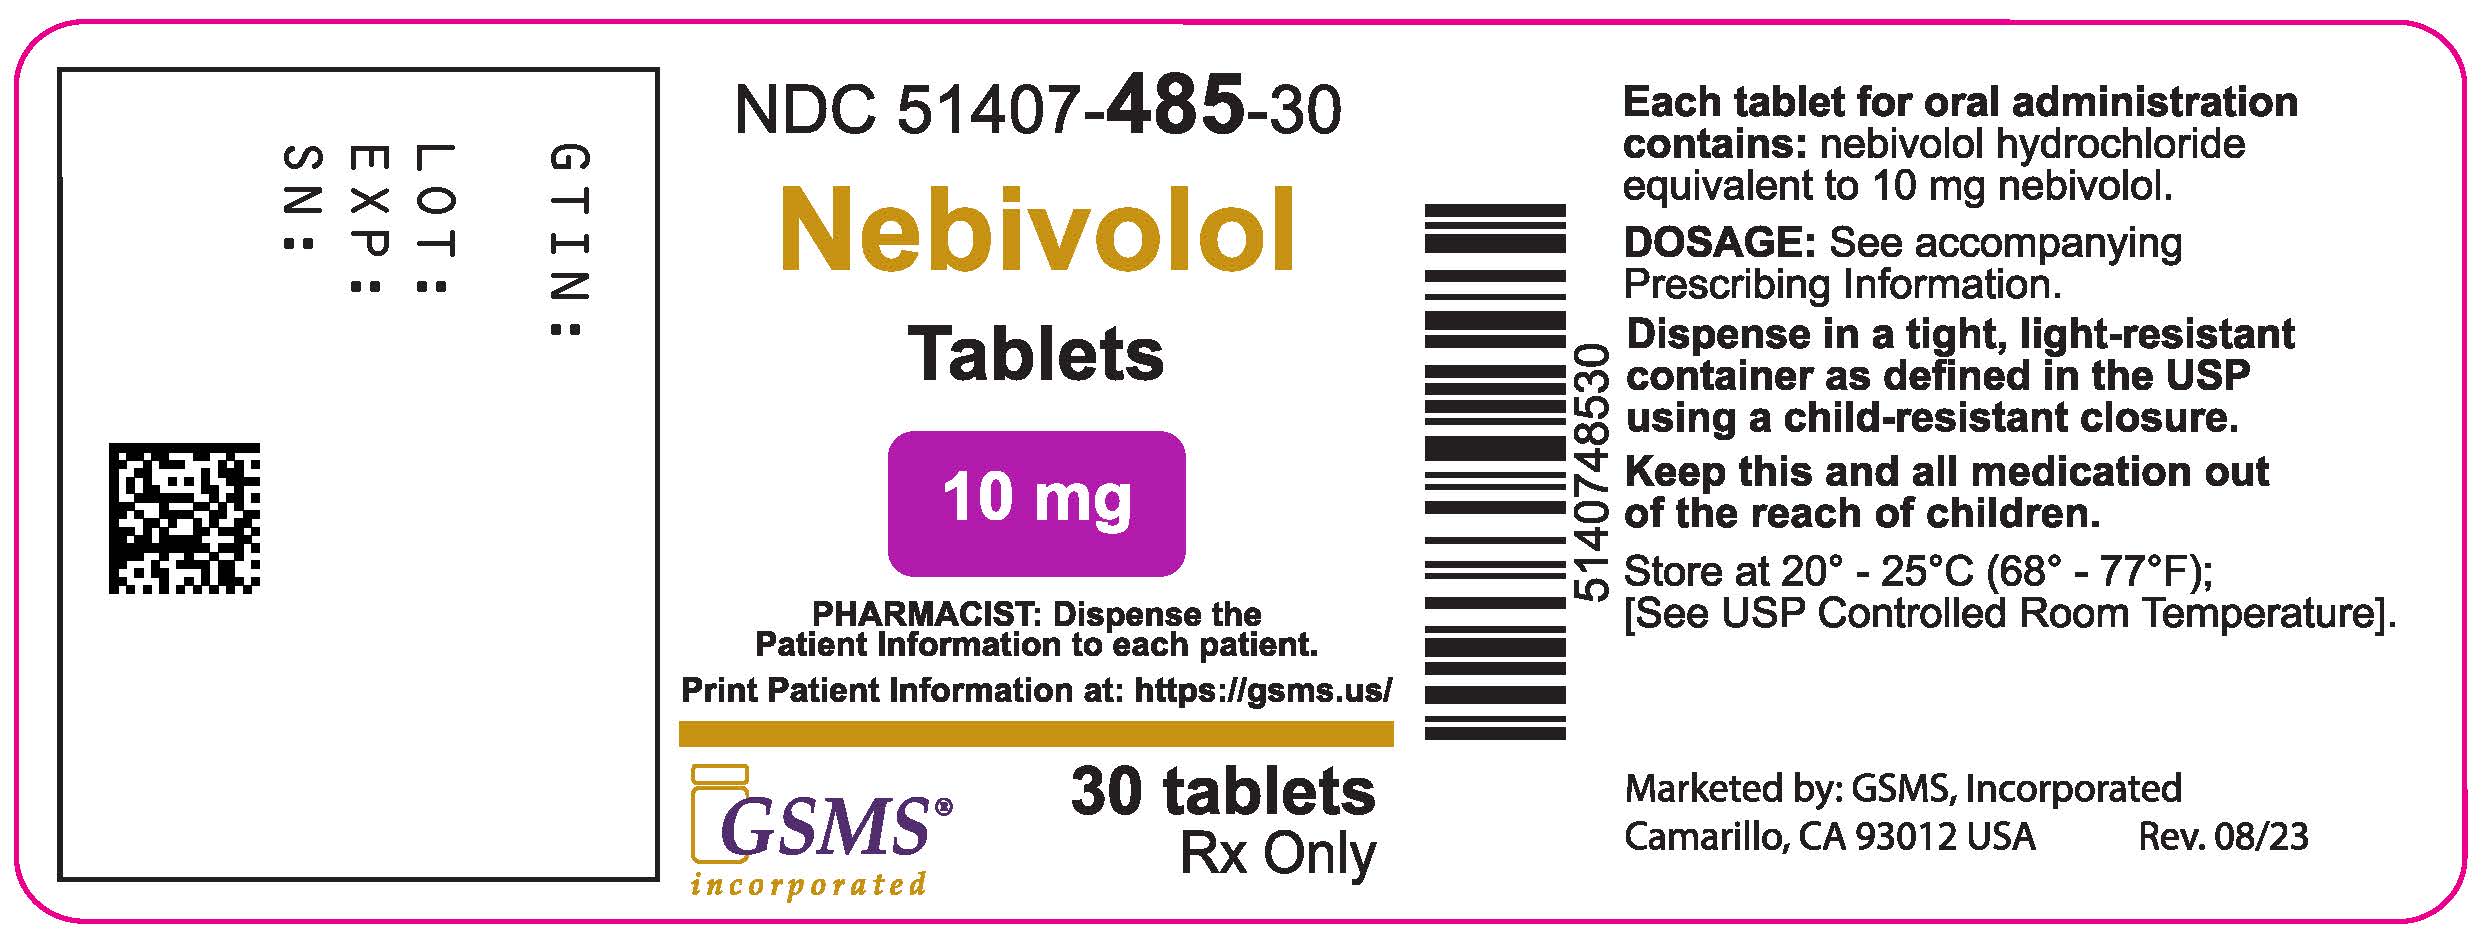
Nebivolol 10 mg Tablet, 30-count
Other active recalls for Nebivolol (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the beta-Adrenergic Blocker class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Nebivolol is used to treat high blood pressure. Nebivolol is in a class of medications called beta blockers. It works by relaxing blood vessels and slowing heart rate to improve blood flow and decrease blood pressure.
Read the full MedlinePlus article ↗- Nebivolol is used to treat high blood pressure — that's its approved use. By bringing your blood pressure down, it helps lower your risk of serious problems like stroke and heart a...
- Please don't stop it suddenly without talking to your doctor first. If you have any underlying heart disease, stopping abruptly can trigger chest pain, a heart attack, or dangerous...
- Can I stop taking nebivolol if I feel fine or don't like the side effects?
- No — nebivolol can be taken with or without food. It doesn't change how the drug is absorbed or how well it works. The most important thing is to take it at roughly the same time e...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Nebivolol — tap one for details:
Nebivolol may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII R75537T0T4
Hypromellose 2910 is a plant-derived thickening agent made from cellulose. It serves as a binder that holds tablet ingredients together, a film-coating for pills, and a viscosity controller in liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII R4OXA9G5BV
A fatty acid salt derived from palm and stearic oils. It works as a lubricant and glidant to help the medicine flow smoothly during manufacturing and prevent ingredients from sticking together.
-
UNII 7T9FYH5QMK
A plant-derived powder that serves as a binder and filler in tablets and capsules. It helps hold ingredients together, adds bulk, and aids in smooth tablet disintegration when swallowed.
-
UNII PNR0YF693Y
A plant-based powder made from purified wood cellulose. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in the stomach.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.3058 | $9.17 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Nebivolol 10 mg 00904-7499-04 | Major | 30 tablets | $0.144 | AB | Availability likely | — |
| nebivolol 10 mg 24689-0161-01 | Apnar | 30 tablets | $0.144 | AB | Availability likely | — |
| Nebivolol 10 mg 33342-0459-07 | Macleods | 30 tablets | $0.144 | AB | Availability likely | — |
| Nebivolol 10 mg 43547-0526-03 | Solco | 30 tablets | $0.144 | AB | Availability likely | — |
| Nebivolol 10 mg 59651-0139-30 | Aurobindo | 30 tablets | $0.144 | AB | Availability likely | — |
| Nebivolol 10 mg 60687-0652-21 | American | 30 tablets | $0.144 | AB | Availability likely | — |
| Nebivolol 10 mg 62559-0277-05 | ANI | 500 tablets | $0.144 | AB | Availability likely | — |
| Nebivolol 10 mg 72205-0152-30 | Novadoz | 30 tablets | $0.144 | AB | Availability likely | — |
| Nebivolol 10 mg 72241-0034-04 | Modavar | 90 tablets | $0.144 | AB | Availability likely | — |
| Nebivolol 10 mg 72603-0872-01 | NorthStar | 30 tablets | $0.144 | AB | Availability likely | — |
| Nebivolol 10 mg 70756-0292-30 | Lifestar | 30 tablets | $0.175 | AB | FDA listed | — |
| Bystolic 10 mg 00456-1410-01 | Allergan, | 100 tablets | — | AB | FDA listed | — |
| Nebivolol Hydrochloride 10 mg 29300-0377-05 | Unichem | 500 tablets | — | AB | FDA listed | — |
| Nebivolol 10 mg 31722-0587-01 | Camber | 100 tablets | — | AB | FDA listed | — |
| nebivolol 10 mg 42291-0873-90 | AvKARE | 90 tablets | — | AB | FDA listed | — |
| Nebivolol 10 mg 50090-5761-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Nebivolol 10 mg 50090-7185-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Nebivolol 10 mgthis 51407-0485-30 | Golden | 30 tablets | — | AB | FDA listed | — |
| Nebivolol 10 mg 63629-9424-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Nebivolol 10 mg 67877-0391-01 | Ascend | 100 tablets | — | AB | FDA listed | — |
| nebivolol 10 mg 68462-0617-01 | Glenmark | 100 tablets | — | AB | FDA listed | — |
| Nebivolol 10 mg 71209-0060-01 | Cadila | 30 tablets | — | AB | FDA listed | — |
| Nebivolol 10 mg 71335-2443-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Nebivolol 10 mg 71335-3102-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Nebivolol 10 mg 72162-2414-03 | Bryant | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 51407-0485-30 You're viewing this | 30 TABLET in 1 BOTTLE (51407-485-30) | 2021-09-17 | Active |
| 51407-0485-90 | 90 TABLET in 1 BOTTLE (51407-485-90) | 2021-09-17 | Active |
You're viewing the smallest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 51407-0485-30?
What is the difference between NDC 51407-0485-30 and NDC 51407-0485-90?
What NDC number is used to bill for this package of Nebivolol 10 mg Tablet?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Nebivolol Tablets are a beta-adrenergic blocking agent indicated for the treatment of hypertension, to lower blood pressure. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions. ( 1.1 )
1.1Hypertension Nebivolol tablets are indicated for the treatment of hypertension, to lower blood pressure [see Clinical Studies ( 14.1 )] . Nebivolol tablets may be used alone or in combination with other antihypertensive agents [see Drug Interactions ( 7 )] . Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions.
These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologic classes, including the class to which this drug principally belongs. There are no controlled trials demonstrating risk reduction with nebivolol. Control of high blood pressure should be part of comprehensive cardiovascular risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation, exercise, and limited sodium intake.
Many patients will require more than one drug to achieve blood pressure goals. For specific advice on goals and management, see published guidelines, such as those of the National High Blood Pressure Education Program's Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC). Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce cardiovascular morbidity and mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits.
The largest and most consistent cardiovascular outcome benefit has been a reduction in the risk of stroke, but reductions in myocardial infarction and cardiovascular mortality also have been seen regularly. Elevated systolic or diastolic pressure causes increased cardiovascular risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severe hypertension can provide substantial benefit. Relative risk reduction from blood pressure reduction is similar across populations with varying absolute risk, so the absolute benefit is greater in patients who are at higher risk independent of their hypertension (for example, patients with diabetes or hyperlipidemia), and such patients would be expected to benefit from more aggressive treatment to a lower blood pressure goal.
Some antihypertensive drugs have smaller blood pressure effects (as monotherapy) in black patients, and many antihypertensive drugs have additional approved indications and effects (e.g., on angina, heart failure, or diabetic kidney disease). These considerations may guide selection of therapy.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Can be taken with and without food. Individualize to the needs of the patient and monitor during up-titration. ( 2 ) Hypertension: Most patients start at 5 mg once daily. Dose can be increased at 2-week intervals up to 40 mg. ( 2.1 )
2.1Hypertension The dose of nebivolol must be individualized to the needs of the patient. For most patients, the recommended starting dose is 5 mg once daily, with or without food, as monotherapy or in combination with other agents. For patients requiring further reduction in blood pressure, the dose can be increased at 2-week intervals up to 40 mg.
A more frequent dosing regimen is unlikely to be beneficial. Renal Impairment In patients with severe renal impairment (ClCr less than 30 mL/min) the recommended initial dose is 2.5 mg once daily; titrate up slowly if needed. Nebivolol has not been studied in patients receiving dialysis [see Clinical Pharmacology ( 12.4 )] .
Hepatic Impairment In patients with moderate hepatic impairment, the recommended initial dose is 2.5 mg once daily; titrate up slowly if needed. Nebivolol has not been studied in patients with severe hepatic impairment and therefore it is not recommended in that population [see Clinical Pharmacology ( 12.4 )] .
2.2Subpopulations Geriatric Patients It is not necessary to adjust the dose in the elderly [see Use in Specific Populations ( 8.5 )]. CYP2D6 Polymorphism No dose adjustments are necessary for patients who are CYP2D6 poor metabolizers. The clinical effect and safety profile observed in poor metabolizers were similar to those of extensive metabolizers [see Clinical Pharmacology ( 12.3 )].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Nebivolol tablets are available for oral administration containing nebivolol hydrochloride equivalent to 2.5, 5, 10, and 20 mg of nebivolol. 2.5 mg tablets: White to off-white, round, unscored tablets debossed with “A4” on one side with the other side blank. 5 mg tablets: White to off-white, round, unscored tablets debossed with “A49” on one side with the other side blank.
10 mg tablets: White to off-white, round, unscored tablets debossed with “A50” on one side with the other side blank. 20 mg tablets: White to off-white, round, unscored tablets debossed with “A51” on one side with the other side blank. Tablets: 2.5, 5, 10, 20 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Nebivolol tablets are contraindicated in the following conditions: Severe bradycardia Heart block greater than first degree Patients with cardiogenic shock Decompensated cardiac failure Sick sinus syndrome (unless a permanent pacemaker is in place) Patients with severe hepatic impairment (Child-Pugh >B) Patients who are hypersensitive to any component of this product Severe bradycardia ( 4 ) Heart block greater than first degree ( 4 ) Patients with cardiogenic shock ( 4 ) Decompensated cardiac failure ( 4 ) Sick sinus syndrome (unless a permanent pacemaker is in place) ( 4 ) Patients with severe hepatic impairment (Child-Pugh >B) ( 4 ) Hypersensitive to any component of this product ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Acute exacerbation of coronary artery disease upon cessation of therapy: Do not abruptly discontinue. ( 5.1 ) Diabetes: May mask symptoms of hypoglycemia and alter glucose levels; monitor. ( 5.5 )
5.1Abrupt Cessation of Therapy Do not abruptly discontinue nebivolol therapy in patients with coronary artery disease. Severe exacerbation of angina, myocardial infarction and ventricular arrhythmias have been reported in patients with coronary artery disease following the abrupt discontinuation of therapy with β-blockers. Myocardial infarction and ventricular arrhythmias may occur with or without preceding exacerbation of the angina pectoris.
Caution patients without overt coronary artery disease against interruption or abrupt discontinuation of therapy. As with other β-blockers, when discontinuation of nebivolol is planned, carefully observe and advise patients to minimize physical activity. Taper nebivolol over 1 to 2 weeks when possible.
If the angina worsens or acute coronary insufficiency develops, re-start nebivolol promptly, at least temporarily.
5.2Angina and Acute Myocardial Infarction Nebivolol was not studied in patients with angina pectoris or who had a recent MI.
5.3Bronchospastic Diseases In general, patients with bronchospastic diseases should not receive β-blockers.
5.4Anesthesia and Major Surgery Because beta-blocker withdrawal has been associated with an increased risk of MI and chest pain, patients already on beta-blockers should generally continue treatment throughout the perioperative period. If nebivolol is to be continued perioperatively, monitor patients closely when anesthetic agents which depress myocardial function, such as ether, cyclopropane, and trichloroethylene, are used. If β-blocking therapy is withdrawn prior to major surgery, the impaired ability of the heart to respond to reflex adrenergic stimuli may augment the risks of general anesthesia and surgical procedures.
The β-blocking effects of nebivolol can be reversed by β-agonists, e.g., dobutamine or isoproterenol. However, such patients may be subject to protracted severe hypotension. Additionally, difficulty in restarting and maintaining the heartbeat has been reported with β-blockers.
5.5Hypoglycemia Beta-blockers may prevent early warning signs of hypoglycemia, such as tachycardia, and increase the risk for severe or prolonged hypoglycemia at anytime during treatment, especially in patients with diabetes mellitus or children and patients who are fasting (i.e., surgery, not eating regularly, or are vomiting). If severe hypoglycemia occurs, patients should be instructed to seek emergency treatment.
5.6Thyrotoxicosis β-blockers may mask clinical signs of hyperthyroidism, such as tachycardia. Abrupt withdrawal of β-blockers may be followed by an exacerbation of the symptoms of hyperthyroidism or may precipitate a thyroid storm.
5.7Peripheral Vascular Disease β-blockers can precipitate or aggravate symptoms of arterial insufficiency in patients with peripheral vascular disease.
5.8Non-dihydropyridine Calcium Channel Blockers Because of significant negative inotropic and chronotropic effects in patients treated with β-blockers and calcium channel blockers of the verapamil and diltiazem type, monitor the ECG and blood pressure in patients treated concomitantly with these agents.
5.9Use with CYP2D6 Inhibitors Nebivolol exposure increases with inhibition of CYP2D6 [see Drug Interactions ( 7 )]. The dose of nebivolol may need to be reduced.
5.10Impaired Renal Function Renal clearance of nebivolol is decreased in patients with severe renal impairment. Nebivolol has not been studied in patients receiving dialysis [see Clinical Pharmacology ( 12.4 ) and Dosage and Administration ( 2.1 )].
5.11Impaired Hepatic Function Metabolism of nebivolol is decreased in patients with moderate hepatic impairment. Nebivolol has not been studied in patients with severe hepatic impairment [see Clinical Pharmacology ( 12.4 ) and Dosage…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions ( 6.1 ): Headache, fatigue To report SUSPECTED ADVERSE REACTIONS, contact ANI Pharmaceuticals, Inc. at 1-855-204-1431 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Studies Experience Nebivolol has been evaluated for safety in patients with hypertension and in patients with heart failure. The observed adverse reaction profile was consistent with the pharmacology of the drug and the health status of the patients in the clinical trials. Adverse reactions reported for each of these patient populations are provided below.
Excluded are adverse reactions considered too general to be informative and those not reasonably associated with the use of the drug because they were associated with the condition being treated or are very common in the treated population. The data described below reflect worldwide clinical trial exposure to nebivolol tablets in 6545 patients, including 5038 patients treated for hypertension and the remaining 1507 subjects treated for other cardiovascular diseases. Doses ranged from 0.5 mg to 40 mg.
Patients received nebivolol tablets for up to 24 months, with over 1900 patients treated for at least 6 months, and approximately 1300 patients for more than one year. HYPERTENSION : In placebo-controlled clinical trials comparing nebivolol tablets with placebo, discontinuation of therapy due to adverse reactions was reported in 2.8% of patients treated with nebivolol and 2.2% of patients given placebo. The most common adverse reactions that led to discontinuation of nebivolol tablets were headache (0.4%), nausea (0.2%) and bradycardia (0.2%).
Table 1 lists treatment-emergent adverse reactions that were reported in three 12-week, placebo-controlled monotherapy trials involving 1597 hypertensive patients treated with either 5 mg, 10 mg, or 20-40 mg of nebivolol and 205 patients given placebo and for which the rate of occurrence was at least 1% of patients treated with nebivolol and greater than the rate for those treated with placebo in at least one dose group. Table 1. Treatment-Emergent Adverse Reactions with an Incidence (over 6 weeks) ≥ 1% in Nebivolol-Treated Patients and at a Higher Frequency than Placebo-Treated Patients System Organ Class – Preferred Term Placebo (n = 205) (%) Nebivolol 5 mg (n = 459) (%) Nebivolol 10 mg (n = 461) (%) Nebivolol 20-40 mg (n = 677) (%) Cardiac Disorders Bradycardia 0 0 0 1 Gastrointestinal Disorders Diarrhea 2 2 2 3 Nausea 0 1 3 2 General Disorders Fatigue 1 2 2 5 Chest pain 0 0 1 1 Peripheral edema 0 1 1 1 Nervous System Disorders Headache 6 9 6 7 Dizziness 2 2 3 4 Psychiatric Disorders Insomnia 0 1 1 1 Respiratory Disorders Dyspnea 0 0 1 1 Skin and Subcutaneous Tissue Disorders Rash 0 0 1 1 Listed below are other reported adverse reactions with an incidence of at least 1% in the more than 4300 patients treated with nebivolol tablets in controlled or open-label trials except for those already appearing in Table 1 , terms too general to be informative, minor symptoms, or adverse reactions unlikely to be attributable to drug because they are common in the population.
These adverse reactions were in most cases observed at a similar frequency in placebo-treated patients in the controlled studies. Body as a Whole : asthenia Gastrointestinal System Disorders : abdominal pain Metabolic and Nutritional Disorders : hypercholesterolemia Nervous System Disorders : paraesthesia
6.2Laboratory Abnormalities In controlled monotherapy trials of hypertensive patients, nebivolol was associated with an increase in BUN, uric acid, triglycerides and a decrease in HDL cholesterol and platelet count.
6.3Postmarketing Experience The following adverse reactions have been identified from spontaneous reports of nebivolol tablets received worldwide and have not been listed elsewhere. These adverse reactions have been chosen for inclusion due to a combination of seriousness, frequency of reporting or potential causal connection to nebivolo…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS CYP2D6 enzyme inhibitors may increase nebivolol levels. ( 7.1 ) Reserpine or clonidine may produce excessive reduction of sympathetic activity. ( 7.2 ) Both digitalis glycosides and β-blockers slow atrioventricular conduction and decrease heart rate.
Concomitant use can increase the risk of bradycardia. ( 7.3 ) Verapamil- or diltiazem-type calcium channel blockers may cause excessive reductions in heart rate, blood pressure, and cardiac contractility. ( 7.4 )
7.1CYP2D6 Inhibitors Use caution when nebivolol is co-administered with CYP2D6 inhibitors (quinidine, propafenone, fluoxetine, paroxetine, etc.) [see Clinical Pharmacology ( 12.5 )].
7.2Hypotensive Agents Do not use nebivolol tablets with other β-blockers. Closely monitor patients receiving catecholamine-depleting drugs, such as reserpine or guanethidine, because the added β-blocking action of nebivolol may produce excessive reduction of sympathetic activity. In patients who are receiving nebivolol tablets and clonidine, discontinue nebivolol tablets for several days before the gradual tapering of clonidine.
7.3Digitalis Glycosides Both digitalis glycosides and β-blockers slow atrioventricular conduction and decrease heart rate. Concomitant use can increase the risk of bradycardia.
7.4Calcium Channel Blockers Nebivolol can exacerbate the effects of myocardial depressants or inhibitors of AV conduction, such as certain calcium antagonists (particularly of the phenylalkylamine [verapamil] and benzothiazepine [diltiazem] classes), or antiarrhythmic agents, such as disopyramide.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Breastfeeding is not recommended. ( 8.2 )
8.1Pregnancy Risk Summary Available data regarding use of nebivolol in pregnant women are insufficient to determine whether there are drug-associated risks of adverse developmental outcomes. There are risks to the mother and fetus associated with poorly controlled hypertension in pregnancy. The use of beta-blockers during the third trimester of pregnancy may increase the risk of hypotension, bradycardia, hypoglycemia, and respiratory depression in the neonate [see Clinical Considerations] .
Oral administration of nebivolol to pregnant rats during organogenesis resulted in embryofetal and perinatal lethality at doses approximately equivalent to the maximum recommended human dose (MRHD). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, and post-partum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly.
Fetal/Neonatal adverse reactions Neonates of women with hypertension, who are treated with beta-blockers during the third trimester of pregnancy, may be at increased risk for hypotension, bradycardia, hypoglycemia, and respiratory depression. Observe newborns for symptoms of hypotension, bradycardia, hypoglycemia and respiratory depression and manage accordingly. Data Animal Data Nebivolol was shown to increase embryo-fetal and perinatal lethality in rats at approximately 1.2 times the MRHD or 40 mg/day on a mg/m 2 basis.
Decreased pup body weights occurred at 1.25 and 2.5 mg/kg in rats, when exposed during the perinatal period (late gestation, parturition and lactation). At 5 mg/kg and higher doses (1.2 times the MRHD), prolonged gestation, dystocia and reduced maternal care were produced with corresponding increases in late fetal deaths and stillbirths and decreased birth weight, live litter size and pup survival. These events occurred only when nebivolol was given during the perinatal period (late gestation, parturition and lactation).
Insufficient numbers of pups survived at 5 mg/kg to evaluate the offspring for reproductive performance. In studies in which pregnant rats were given nebivolol during organogenesis, reduced fetal body weights were observed at maternally toxic doses of 20 and 40 mg/kg/day (5 and 10 times the MRHD), and small reversible delays in sternal and thoracic ossification associated with the reduced fetal body weights and a small increase in resorption occurred at 40 mg/kg/day (10 times the MRHD). No adverse effects on embryo-fetal viability, sex, weight or morphology were observed in studies in which nebivolol was given to pregnant rabbits at doses as high as 20 mg/kg/day (10 times the MRHD).
8.2Lactation Risk Summary There is no information regarding the presence of nebivolol in human milk, the effects on the breastfed infant, or the effects on milk production. Nebivolol is present in rat milk [see Data] . Because of the potential for β-blockers to produce serious adverse reactions in nursing infants, especially bradycardia, Nebivolol tablets are not recommended during nursing.
Data In lactating rats, maximum milk levels of unchanged nebivolol were observed at 4 hours after single and repeat doses of 2.5 mg/kg/day. The daily dose (mg/kg body weight) ingested by a rat pup is 0.3% of the dam dose for unchanged nebivolol.
8.4 Pediatric Use Safety and effectiveness in pediatric patients have not been esta…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data regarding use of nebivolol in pregnant women are insufficient to determine whether there are drug-associated risks of adverse developmental outcomes. There are risks to the mother and fetus associated with poorly controlled hypertension in pregnancy. The use of beta-blockers during the third trimester of pregnancy may increase the risk of hypotension, bradycardia, hypoglycemia, and respiratory depression in the neonate [see Clinical Considerations] .
Oral administration of nebivolol to pregnant rats during organogenesis resulted in embryofetal and perinatal lethality at doses approximately equivalent to the maximum recommended human dose (MRHD). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, and post-partum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly.
Fetal/Neonatal adverse reactions Neonates of women with hypertension, who are treated with beta-blockers during the third trimester of pregnancy, may be at increased risk for hypotension, bradycardia, hypoglycemia, and respiratory depression. Observe newborns for symptoms of hypotension, bradycardia, hypoglycemia and respiratory depression and manage accordingly. Data Animal Data Nebivolol was shown to increase embryo-fetal and perinatal lethality in rats at approximately 1.2 times the MRHD or 40 mg/day on a mg/m 2 basis.
Decreased pup body weights occurred at 1.25 and 2.5 mg/kg in rats, when exposed during the perinatal period (late gestation, parturition and lactation). At 5 mg/kg and higher doses (1.2 times the MRHD), prolonged gestation, dystocia and reduced maternal care were produced with corresponding increases in late fetal deaths and stillbirths and decreased birth weight, live litter size and pup survival. These events occurred only when nebivolol was given during the perinatal period (late gestation, parturition and lactation).
Insufficient numbers of pups survived at 5 mg/kg to evaluate the offspring for reproductive performance. In studies in which pregnant rats were given nebivolol during organogenesis, reduced fetal body weights were observed at maternally toxic doses of 20 and 40 mg/kg/day (5 and 10 times the MRHD), and small reversible delays in sternal and thoracic ossification associated with the reduced fetal body weights and a small increase in resorption occurred at 40 mg/kg/day (10 times the MRHD). No adverse effects on embryo-fetal viability, sex, weight or morphology were observed in studies in which nebivolol was given to pregnant rabbits at doses as high as 20 mg/kg/day (10 times the MRHD).
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established. Pediatric studies in ages newborn to 18 years old have not been conducted because of incomplete characterization of developmental toxicity and possible adverse effects on long-term fertility [see Nonclinical Toxicology ( 13.1 )] . Juvenile Animal Toxicity Data Daily oral doses of nebivolol to juvenile rats from post-natal day 14 to post-natal day 27 showed sudden unexplained death at exposures equal to those in human poor metabolizers given a single dose of 10 mg.
No mortality was seen at half the adult human exposure. In surviving rats, cardiomyopathy was seen at exposures greater than or equal to the human exposure. Male rat pups exposed to twice the human exposure showed decreases in total sperm count as well as decreases in the total and percentage of motile sperm.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 2800 patients in the U.S. sponsored placebo-controlled clinical hypertension studies, 478 patients were 65 years of age or older. No overall differences in efficacy or in the incidence of adverse events were observed between older and younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE In clinical trials and worldwide postmarketing experience there were reports of nebivolol overdose. The most common signs and symptoms associated with nebivolol overdosage are bradycardia and hypotension. Other important adverse reactions reported with nebivolol overdose include cardiac failure, dizziness, hypoglycemia, fatigue and vomiting.
Other adverse reactions associated with β-blocker overdose include bronchospasm and heart block. The largest known ingestion of nebivolol worldwide involved a patient who ingested up to 500 mg of nebivolol along with several 100 mg tablets of acetylsalicylic acid in a suicide attempt. The patient experienced hyperhydrosis, pallor, depressed level of consciousness, hypokinesia, hypotension, sinus bradycardia, hypoglycemia, hypokalemia, respiratory failure and vomiting.
The patient recovered. Because of extensive drug binding to plasma proteins, hemodialysis is not expected to enhance nebivolol clearance. If overdose occurs, provide general supportive and specific symptomatic treatment.
Based on expected pharmacologic actions and recommendations for other β-blockers, consider the following general measures, including stopping nebivolol, when clinically warranted: Bradycardia : Administer IV atropine. If the response is inadequate, isoproterenol or another agent with positive chronotropic properties may be given cautiously. Under some circumstances, transthoracic or transvenous pacemaker placement may be necessary.
Hypotension : Administer IV fluids and vasopressors. Intravenous glucagon may be useful. Heart Block (second or third degree) : Monitor and treat with isoproterenol infusion.
Under some circumstances, transthoracic or transvenous pacemaker placement may be necessary. Congestive Heart Failure : Initiate therapy with digitalis glycoside and diuretics. In certain cases, consider the use of inotropic and vasodilating agents.
Bronchospasm : Administer bronchodilator therapy such as a short acting inhaled β 2 -agonist and/or aminophylline. Hypoglycemia : Administer IV glucose. Repeated doses of IV glucose or possibly glucagon may be required.
Supportive measures should continue until clinical stability is achieved. The half-life of low doses of nebivolol is 12-19 hours. Call the National Poison Control Center (800-222-1222) for the most current information on β-blocker overdose treatment.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY Nebivolol is a β-adrenergic receptor blocking agent. In extensive metabolizers (most of the population) and at doses less than or equal to 10 mg, nebivolol is preferentially β 1 selective. In poor metabolizers and at higher doses, nebivolol inhibits both β 1 - and β 2 - adrenergic receptors.
Nebivolol lacks intrinsic sympathomimetic and membrane stabilizing activity at therapeutically relevant concentrations. At clinically relevant doses, nebivolol does not demonstrate α 1 -adrenergic receptor blockade activity. Various metabolites, including glucuronides, contribute to β-blocking activity.
12.1Mechanism of Action The mechanism of action of the antihypertensive response of nebivolol has not been definitively established. Possible factors that may be involved include: (1) decreased heart rate, (2) decreased myocardial contractility, (3) diminution of tonic sympathetic outflow to the periphery from cerebral vasomotor centers, (4) suppression of renin activity and (5) vasodilation and decreased peripheral vascular resistance.
12.3Pharmacokinetics Nebivolol is metabolized by a number of routes, including glucuronidation and hydroxylation by CYP2D6. The active isomer (d-nebivolol) has an effective half-life of about 12 hours in CYP2D6 extensive metabolizers (most people), and 19 hours in poor metabolizers and exposure to d-nebivolol is substantially increased in poor metabolizers. This has less importance than usual, however, because the metabolites, including the hydroxyl metabolite and glucuronides (the predominant circulating metabolites), contribute to β-blocking activity.
Plasma levels of d–nebivolol increase in proportion to dose in EMs and PMs for doses up to 20mg. Exposure to l-nebivolol is higher than to d-nebivolol but l-nebivolol contributes little to the drug's activity as d-nebivolol's beta receptor affinity is > 1000-fold higher than l-nebivolol. For the same dose, PMs attain a 5-fold higher C max and 10-fold higher AUC of d-nebivolol than do EMs. d-Nebivolol accumulates about 1.5-fold with repeated once-daily dosing in EMs.
Absorption Absorption of nebivolol is similar to an oral solution. The absolute bioavailability has not been determined. Mean peak plasma nebivolol concentrations occur approximately 1.5 to 4 hours post-dosing in EMs and PMs.
Food does not alter the pharmacokinetics of nebivolol. Under fed conditions, nebivolol glucuronides are slightly reduced. Nebivolol tablets may be administered without regard to meals.
Distribution The in vitro human plasma protein binding of nebivolol is approximately 98%, mostly to albumin, and is independent of nebivolol concentrations. Metabolism Nebivolol is predominantly metabolized via direct glucuronidation of parent and to a lesser extent via N-dealkylation and oxidation via cytochrome P450 2D6. Its stereospecific metabolites contribute to the pharmacologic activity [see Drug Interactions ( 7 )] .
Elimination After a single oral administration of 14C-nebivolol, 38% of the dose was recovered in urine and 44% in feces for EMs and 67% in urine and 13% in feces for PMs. Essentially all nebivolol was excreted as multiple oxidative metabolites or their corresponding glucuronide conjugates.
12.4Pharmacokinetics in Special Populations Hepatic Disease d-Nebivolol peak plasma concentration increased 3-fold, exposure (AUC) increased 10-fold, and the apparent clearance decreased by 86% in patients with moderate hepatic impairment (Child-Pugh Class B). No formal studies have been performed in patients with severe hepatic impairment and nebivolol should be contraindicated for these patients [see Dosage and Administration ( 2.1 )] . Renal Disease The apparent clearance of nebivolol was unchanged following a single 5 mg dose of nebivolol in patients with mild renal impairment (ClCr 50 to 80 mL/min, n=7), and it was reduced negligibly in patients with moderate (ClCr 30 to 50 mL/min, n=9), but clearance was reduced by 53% in patients with severe renal impai…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of action of the antihypertensive response of nebivolol has not been definitively established. Possible factors that may be involved include: (1) decreased heart rate, (2) decreased myocardial contractility, (3) diminution of tonic sympathetic outflow to the periphery from cerebral vasomotor centers, (4) suppression of renin activity and (5) vasodilation and decreased peripheral vascular resistance.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Nebivolol Tablets are available for oral administration containing nebivolol hydrochloride equivalent to 2.5, 5, 10, and 20 mg of nebivolol. 2.5 mg tablets: White to off-white, round, unscored tablets debossed with “A4” on one side with the other side blank, are supplied in the following package size: Bottles of 30 NDC 51407-483-30 5 mg tablets: White to off-white, round, unscored tablets debossed with “A49” on one side with the other side blank, are supplied in the following package sizes: Bottles of 30 NDC 51407-484-30 Bottles of 90 NDC 51407-484-90 10 mg tablets: White to off-white, round, unscored tablets debossed with “A50” on one side with the other side blank, are supplied in the following package sizes: Bottles of 30 NDC 51407-485-30 Bottles of 90 NDC 51407-485-90 20mg tablets: White to off-white, round, unscored tablets debossed with “A51” on one side with the other side blank, are supplied in the following package sizes: Bottles of 30 NDC 51407-486-30 Bottles of 90 NDC 51407-486-90 Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature].
Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure.
📋 Description ▾
11 DESCRIPTION The chemical name for the active ingredient in nebivolol tablets is (1RS,1'RS)-1,1'-[(2RS,2'SR)-bis(6-fluoro-3,4-dihydro-2H-1-benzopyran-2-yl)]- 2,2'-iminodiethanol hydrochloride. Nebivolol is a racemate composed of d-Nebivolol and l-Nebivolol with the stereochemical designations of [SRRR]-nebivolol and [RSSS]-nebivolol, respectively. Nebivolol's molecular formula is (C 22 H 25 F 2 NO 4 •HCl) with the following structural formula: Nebivolol hydrochloride is a white to almost white powder that is soluble in methanol, dimethylsulfoxide, and N,N-dimethylformamide, sparingly soluble in ethanol, propylene glycol, and polyethylene glycol, and very slightly soluble in hexane, dichloromethane, and methylbenzene.
Nebivolol tablets for oral administration contain nebivolol hydrochloride equivalent to 2.5, 5, 10, and 20 mg of nebivolol base. In addition, nebivolol tablets contain the following inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, hypromellose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, pregelatinized starch, polysorbate 80, and sodium lauryl sulfate. Structure-SRRR Structure-RSSS
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See FDA-approved patient labeling (Patient Information). Patient Advice Advise patients to take nebivolol tablets regularly and continuously, as directed. Nebivolol tablets can be taken with or without food.
If a dose is missed, take the next scheduled dose only (without doubling it). Do not interrupt or discontinue nebivolol tablets without consulting the physician. Patients should know how they react to this medicine before they operate automobiles, use machinery, or engage in other tasks requiring alertness.
Advise patients to consult a physician if any difficulty in breathing occurs, or if they develop signs or symptoms of worsening congestive heart failure such as weight gain or increasing shortness of breath, or excessive bradycardia. Caution patients subject to spontaneous hypoglycemia, or diabetic patients receiving insulin or oral hypoglycemic agents, that β-blockers may mask some of the manifestations of hypoglycemia, particularly tachycardia. Inform patients or caregivers that there is a risk of hypoglycemia when nebivolol tablets are given to patients who are fasting or who are vomiting.
Instruct patients or caregivers how to monitor for signs of hypoglycemia [see Warnings and Precautions ( 5.5 )] . All brand names listed are the registered trademarks of their respective owners and are not trademarks of ANI Pharmaceuticals, Inc. Manufactured by: ANI Pharmaceuticals, Inc.
Baudette, MN 56623 10465 Rev 10/25 Marketed by: GSMS, Inc. Camarillo, CA 93012 USA logo