
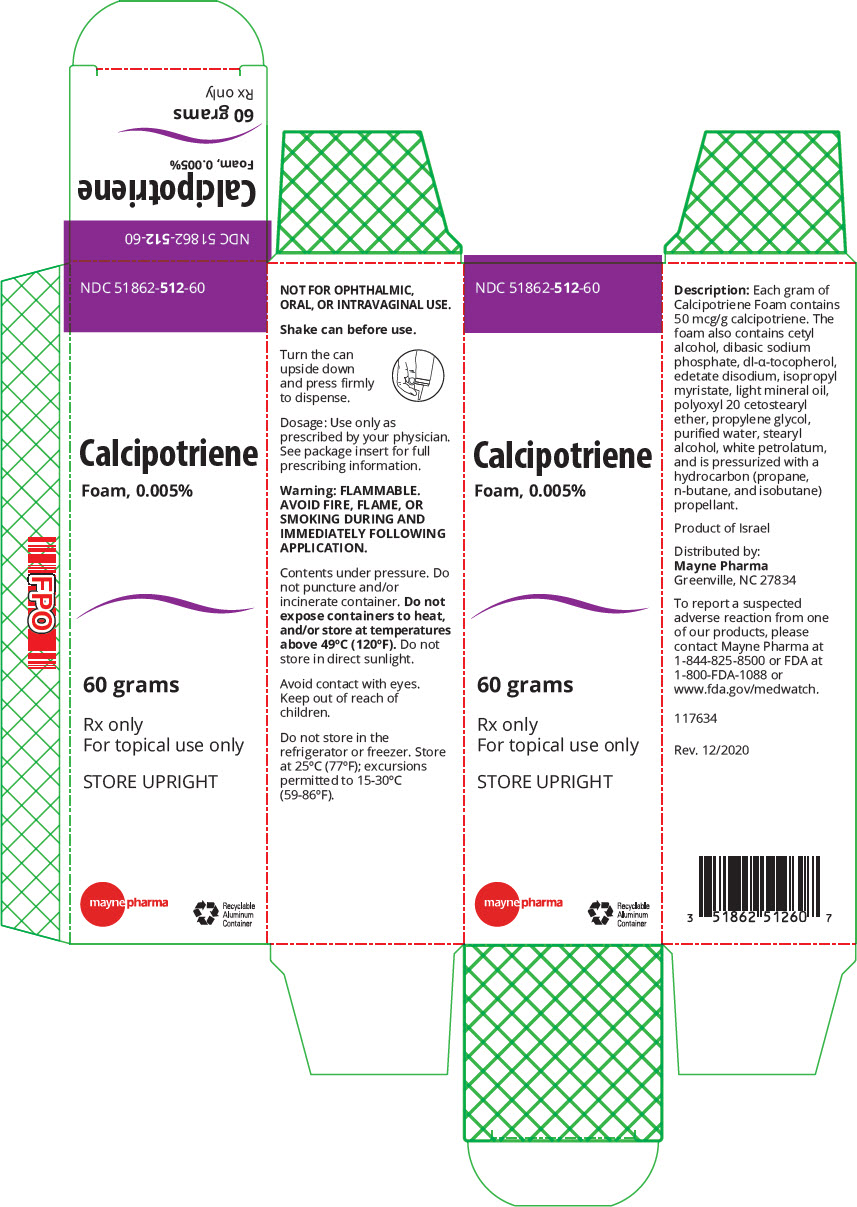
calcipotriene 50 ug/g Aerosol, Foam
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Vitamin D Analog class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Calcipotriene is used to treat psoriasis (a skin disease in which red, scaly patches form due to increased production of skin cells on some areas of the body). Calcipotriene is in a class of medications called synthetic vitamin D3 derivatives. It works by slowing the excessive production of skin cells.
Read the full MedlinePlus article ↗- Calcipotriene is not a steroid at all — it's a synthetic form of vitamin D3. While steroid creams work by suppressing inflammation, calcipotriene is thought to work by binding to v...
- What exactly is calcipotriene, and how is it different from a steroid cream?
- No — calcipotriene should not be applied to the face. The label is clear on this for all product forms. If you have psoriasis on your face, talk to your dermatologist about other o...
- Can I use this on my face if my psoriasis is there too?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Calcipotriene — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 7QWA1RIO01
A synthetic form of vitamin E used as an antioxidant in medicines. It prevents oils and fats in the formulation from breaking down, helping the drug remain stable and effective during storage.
-
UNII 936JST6JCN
Cetyl alcohol is a waxy, fatty substance derived from plant or animal sources. It acts as an emulsifier and thickener in medicines, helping blend oil and water components and giving products a smooth, creamy texture.
-
UNII 7FLD91C86K
Edetate disodium is a chemical compound that binds and removes certain metal ions. In medicines, it acts as a preservative and stabilizer by preventing metals like calcium from interfering with the product's shelf life and consistency.
-
UNII 0RE8K4LNJS
Isopropyl myristate is an oily liquid made from coconut or palm oil. It's used in medicines as an emollient and penetration enhancer to help the medicine absorb through skin or improve spreadability in topical products.
-
UNII N6K5787QVP
Light mineral oil is a clear, odorless liquid derived from petroleum. In medicines, it acts as a lubricant and emollient to help the product spread smoothly and improve texture.
-
UNII 4T6H12BN9U
Petrolatum is a purified mineral oil-based jelly derived from petroleum. In medicines, it acts as an emollient, lubricant, and moisture barrier to soften skin, reduce friction, and help prevent water loss from formulations.
-
UNII YRC528SWUY
A waxy emulsifier made from plant-derived fatty alcohols. It helps blend oil and water-based ingredients together and improves how the medicine spreads and absorbs.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII GR686LBA74
Sodium phosphate, dibasic is a salt derived from phosphoric acid. It acts as a buffer to help maintain the medicine's pH balance and may serve as a binder or filler in tablets and capsules.
-
UNII 2KR89I4H1Y
Stearyl alcohol is a waxy, fatty substance derived from natural oils or made synthetically. It acts as an emulsifier and thickener in medicines, helping mix ingredients together and give the product the right texture.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per g | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $16.10 | $966.14 / 60 g |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Sorilux 50 ug/g 51862-0376-12 | Mayne | 1 can | — | — | FDA listed | — |
| calcipotriene 50 ug/gthis 51862-0512-60 | Mayne | 1 can | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8629128 ↗ | Method of use | U-1280 | May 26, 2026 |
| US 8263580 ↗ | Method of use | U-1280 | May 7, 2028 |
| US 8629128 ↗ | Method of use | U-1767 | May 26, 2026 |
| US 8629128 ↗ | Method of use | U-2662 | May 26, 2026 |
| US 8263580 ↗ | Method of use | U-2662 | May 7, 2028 |
Is there a generic version of CALCIPOTRIENE 0.005% FOAM?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 51862-0512-60 You're viewing this | 1 CAN in 1 CARTON (51862-512-60) / 60 g in 1 CAN | 2021-02-15 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Calcipotriene foam is indicated for the topical treatment of plaque psoriasis of the scalp and body in adults and pediatric patients 4 years of age and older. Calcipotriene foam, is a vitamin D analog indicated for the topical treatment of plaque psoriasis of the scalp and body in adults and pediatric patients 4 years of age and older. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Calcipotriene foam is for topical use only. Calcipotriene foam is not for oral, ophthalmic, or intravaginal use. Apply a thin layer of calcipotriene foam twice daily to the affected areas and rub in gently and completely. Avoid contact with the face and eyes. For topical use only; not for oral, ophthalmic, or intravaginal use. ( 2 ) Apply twice daily. ( 2 )
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 0.005%, white foam. Calcipotriene foam contains calcipotriene 50 mcg/g in an aqueous-based emulsion foam vehicle. 0.005%, foam. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Calcipotriene foam should not be used by patients with known hypercalcemia. Do not use in patients with known hypercalcemia. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Flammability: Contents are flammable. Instruct the patient the avoid fire, flame, and smoking during and immediately following application. ( 5.1 ) Effects on Calcium Metabolism: If elevation of serum calcium occurs, instruct patients to discontinue treatment until normal calcium levels are restored. ( 5.2 )
5.1Flammability The propellant in calcipotriene foam is flammable. Instruct the patient to avoid fire, flame, and smoking during and immediately following application.
5.2Effects on Calcium Metabolism Elevation of serum calcium has occurred with use of calcipotriene. If elevation in serum calcium outside the normal range should occur, discontinue treatment until normal calcium levels are restored.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Adverse reactions reported in ≥ 1% of subjects treated with Calcipotriene foam and at a higher incidence than subjects treated with vehicle were application site erythema and application site pain. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Mayne Pharma at 1-844-825-8500 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch . ( 6 )
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Calcipotriene foam was studied in four vehicle-controlled trials. A total of 1094 adult subjects with plaque psoriasis, including 654 exposed to calcipotriene foam, were treated twice daily for 8 weeks.
Adverse reactions reported in ≥1% of subjects treated with calcipotriene foam and at a higher incidence than subjects treated with vehicle were application site erythema (2%) and application site pain (3%). The incidence of these adverse reactions was similar between the body and scalp. In an open-label study, 19 pediatric subjects age 12 to less than 17 years applied calcipotriene foam twice daily for 14 days and once on Day 15.
Adverse reactions included application site pain, application site pruritus and pruritus [see Clinical Pharmacology (12.2 and 12.3) and Pediatric Use (8.4) ] . In an open-label study, 36 pediatric subjects age 4 to less than 12 years applied calcipotriene foam twice daily for up to 8 weeks. Adverse reactions included application site pain and contact dermatitis [see Clinical Pharmacology (12.2 and 12.3) and Pediatric Use (8.4) ] .
6.2Postmarketing Experience The following adverse reactions have been identified during post approval use of calcipotriene foam. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Skin and Subcutaneous: application site vesicles
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Although there are no available data on the drug- associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes in pregnant women exposed to calcipotriene foam, systemic exposure to calcipotriene is likely to be low [see Clinical Pharmacology (12.2 , 12.3) ] . In animal reproduction studies, oral administration of calcipotriene to pregnant rats and rabbits during the period of organogenesis resulted in an increased incidence of minor skeletal abnormalities, including enlarged fontanelles and extra ribs in rats and an increased incidence of minor skeletal abnormalities, including incomplete ossification of pubic bones and forelimb phalanges in rabbits (see Data ) .
The available data do not allow the calculation of relevant comparisons between the systemic exposure of calcipotriene observed in animal studies to the systemic exposure that would be expected in humans after topical use of calcipotriene foam. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Embryofetal development studies were conducted with calcipotriene after oral administration in rats and rabbits. Pregnant rats received daily oral administration of calcipotriene during the period of organogenesis.
Fetuses from dams dosed with 54 mcg/kg/day (318 mcg/m 2 /day) exhibited a significantly increased incidence of minor skeletal abnormalities consisting primarily of enlarged fontanelles and extra ribs. The enlarged fontanelles are most likely due to calcipotriene's effect upon calcium metabolism. There were no effects on the incidence of major malformations in fetuses.
Pregnant rabbits received daily oral administration of calcipotriene during the period of organogenesis. Increased rabbit maternal and fetal toxicity was noted at 12 mcg/kg/day (132 mcg/m 2 /day). Fetuses from does dosed with 36 mcg/kg/day (396 mcg/m 2 /day) exhibited a significantly increased incidence of minor skeletal abnormalities including incomplete ossification of pubic bones and forelimb phalanges.
There were no effects on the incidence of major malformations in fetuses.
8.2Lactation Risk Summary There are no data on the presence of topically administered calcipotriene in human or animal milk, the effects on the breastfed infant, or the effects on milk production. After topical administration of calcipotriene foam, concentrations of calcipotriene in plasma are low, and therefore, concentrations in human milk are likely to be low [see Clinical Pharmacology (12.3) ] . The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for and any potential adverse effects on the breastfed child from calcipotriene foam or from the underlying maternal condition.
8.4Pediatric Use The safety and effectiveness of calcipotriene foam have been established in pediatric patients age 4 years and older for topical treatment of plaque psoriasis of the scalp and body. Use of calcipotriene foam in this age group is supported by two adequate and well controlled 8-week trials in adults and adolescents 12 years of age and older, with additional data from a 15-day open-label safety and pharmacokinetics (PK) study conducted in 19 subjects 12 to less than 17 years of age; and an 8-week open-label safety and PK study in 36 subjects 4 to 11 years of age with psoriasis.
Data from 19 subjects aged 12 to less than 17 years and 18 subjects aged 5 to 11 years showed no significant effects on indices of calcium metabolism. Systemic concentrations of calcipotriene were not quantifiable in the two studies in subjects aged 7 years to less than 17 years. [see Clinical Stu…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Although there are no available data on the drug- associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes in pregnant women exposed to calcipotriene foam, systemic exposure to calcipotriene is likely to be low [see Clinical Pharmacology (12.2 , 12.3) ] . In animal reproduction studies, oral administration of calcipotriene to pregnant rats and rabbits during the period of organogenesis resulted in an increased incidence of minor skeletal abnormalities, including enlarged fontanelles and extra ribs in rats and an increased incidence of minor skeletal abnormalities, including incomplete ossification of pubic bones and forelimb phalanges in rabbits (see Data ) .
The available data do not allow the calculation of relevant comparisons between the systemic exposure of calcipotriene observed in animal studies to the systemic exposure that would be expected in humans after topical use of calcipotriene foam. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Embryofetal development studies were conducted with calcipotriene after oral administration in rats and rabbits. Pregnant rats received daily oral administration of calcipotriene during the period of organogenesis.
Fetuses from dams dosed with 54 mcg/kg/day (318 mcg/m 2 /day) exhibited a significantly increased incidence of minor skeletal abnormalities consisting primarily of enlarged fontanelles and extra ribs. The enlarged fontanelles are most likely due to calcipotriene's effect upon calcium metabolism. There were no effects on the incidence of major malformations in fetuses.
Pregnant rabbits received daily oral administration of calcipotriene during the period of organogenesis. Increased rabbit maternal and fetal toxicity was noted at 12 mcg/kg/day (132 mcg/m 2 /day). Fetuses from does dosed with 36 mcg/kg/day (396 mcg/m 2 /day) exhibited a significantly increased incidence of minor skeletal abnormalities including incomplete ossification of pubic bones and forelimb phalanges.
There were no effects on the incidence of major malformations in fetuses.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of calcipotriene foam have been established in pediatric patients age 4 years and older for topical treatment of plaque psoriasis of the scalp and body. Use of calcipotriene foam in this age group is supported by two adequate and well controlled 8-week trials in adults and adolescents 12 years of age and older, with additional data from a 15-day open-label safety and pharmacokinetics (PK) study conducted in 19 subjects 12 to less than 17 years of age; and an 8-week open-label safety and PK study in 36 subjects 4 to 11 years of age with psoriasis.
Data from 19 subjects aged 12 to less than 17 years and 18 subjects aged 5 to 11 years showed no significant effects on indices of calcium metabolism. Systemic concentrations of calcipotriene were not quantifiable in the two studies in subjects aged 7 years to less than 17 years. [see Clinical Studies (14) , Clinical Pharmacology (12.2 , 12.3) and Adverse Reactions (6.1) ] . The safety and effectiveness of calcipotriene foam in pediatric patients less than 4 years of age have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of calcipotriene foam did not include sufficient numbers of subjects aged 65 years and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE Topically applied calcipotriene can be absorbed in sufficient amounts to produce systemic effects. Elevated serum calcium has been observed with use of topical calcipotriene [See Warnings and Precautions (5.2) ] .
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Calcipotriene is a synthetic vitamin D3 analog that has a similar receptor binding affinity as natural vitamin D3. However, the exact mechanism of action contributing to the clinical efficacy in the treatment of psoriasis is unknown.
12.2Pharmacodynamics Effects on Calcium Metabolism In 19 subjects with psoriasis aged 12 to less than 17 years treated with calcipotriene foam two times a day for 15 days, there was no significant effect on indices of calcium metabolism including serum albumin adjusted calcium, urine calcium/creatinine ratio, iPTH, alkaline phosphatase, magnesium and phosphorus. The effects of calcipotriene foam, 0.005%, on calcium metabolism were evaluated in 18 pediatric subjects 5 to 11 years of age receiving calcipotriene foam administered twice daily for a minimum of 14 days (mean: 56 days, range: 14 to 69 days).
These subjects had plaque psoriasis involving an average of 10% of the body surface area (BSA) (range: 0.5%-36.5%). There was no relationship between urinary calcium/creatinine ratio (comparing Week 2 to Baseline) and % BSA treated.
12.3Pharmacokinetics The systemic absorption of calcipotriene in subjects with psoriasis of the body was evaluated at steady state following application of either calcipotriene foam or calcipotriene ointment to a body surface area of 5% to 10%. In the calcipotriene foam treatment group, 15 out of 16 subjects had calcipotriene plasma concentrations below the limit of quantitation (10 pg/mL), while in the calcipotriene ointment treated group, 5 out of 16 subjects had measurable calcipotriene plasma concentrations at various time points.
All measurable plasma calcipotriene concentrations were below 25 pg/mL. The pharmacokinetics of calcipotriene foam, 0.005% was investigated when applied topically for 15 days to 17 subjects aged 12 to less than 17 years with moderate plaque psoriasis involving a mean BSA of 24%, excluding face and scalp, and a mean scalp involvement of 43%. Systemic concentration of calcipotriene were not quantifiable in any of the subjects (limit of quantification = 10 pg/mL).
In 11 pediatric subjects 7 to 11 years of age with plaque psoriasis involving a mean BSA of 10%, plasma concentration of calcipotriene was measured following 2 weeks of twice daily administration of calcipotriene foam. No subject had quantifiable calcipotriene plasma concentration (limit of quantification = 10 pg/mL). The systemic disposition of calcipotriene is expected to be similar to that of the naturally occurring vitamin D.
Absorbed calcipotriene is known to be converted to inactive metabolites within 24 hours of application and the metabolism occurs via a similar pathway to the natural hormone.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Calcipotriene is a synthetic vitamin D3 analog that has a similar receptor binding affinity as natural vitamin D3. However, the exact mechanism of action contributing to the clinical efficacy in the treatment of psoriasis is unknown.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Calcipotriene foam, 0.005%, is supplied as follows: 60 g aluminum can NDC 51862-512-60
16.2Storage and Handling Store at 20ºC to 25°C (68°F to 77°F); excursions permitted to 15°C – 30°C (59°F – 86°F). Flammable. Contents under pressure. Do not puncture or incinerate. Do not expose to heat or store at temperatures above 120°F (49°C). Keep out of reach of children.
📦 Storage and Handling ▾
16.2Storage and Handling Store at 20ºC to 25°C (68°F to 77°F); excursions permitted to 15°C – 30°C (59°F – 86°F). Flammable. Contents under pressure. Do not puncture or incinerate. Do not expose to heat or store at temperatures above 120°F (49°C). Keep out of reach of children.
📋 Description ▾
11 DESCRIPTION Calcipotriene foam contains the compound calcipotriene, a synthetic vitamin D3 analog, in an aqueous-based emulsion foam vehicle for topical dermatologic use. Chemically, calcipotriene is (5Z,7E,22E,24S)-24-cyclopropyl-9,10-secochola-5,7,10(19), 22-tetraene- 1α,3β,24-triol. The structural formula is represented below: Molecular Formula: C27H40O3 Molecular Weight: 412.6 Calcipotriene is a white or off-white crystalline substance.
Calcipotriene foam contains calcipotriene 50 mcg/g in an aqueous-based emulsion foam vehicle consisting of cetyl alcohol, dibasic sodium phosphate, dl-α-tocopherol, edetate disodium, isopropyl myristate, light mineral oil, polyoxyl 20 cetostearyl ether, propylene glycol, purified water, stearyl alcohol, and white petrolatum. Calcipotriene foam is dispensed from an aluminum can pressurized with a hydrocarbon (propane/n-butane/isobutane) propellant. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Inform the patient to adhere to the following instructions: Apply calcipotriene foam to the affected skin areas. Apply calcipotriene foam to the scalp when the hair is dry.
Avoid fire, flame, and smoking during and immediately following application since calcipotriene foam is flammable. Avoid contact with the face and eyes. If calcipotriene foam gets on the face or in or near their eyes, rinse thoroughly with water.
Talk to your doctor if your skin does not improve after treatment with calcipotriene foam for 8 weeks. Wash your hands after applying calcipotriene foam unless your hands are the affected site. Do not place calcipotriene foam in the refrigerator or freezer.