
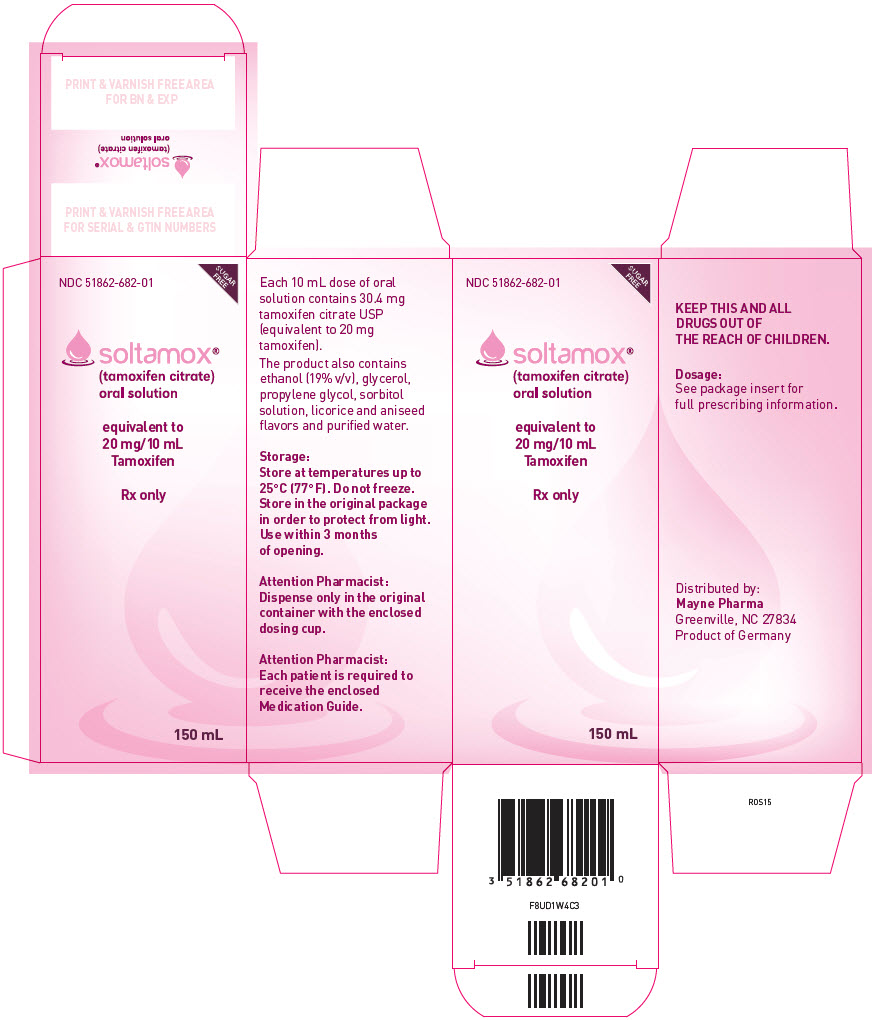
SOLTAMOX TAMOXIFEN CITRATE 20 mg/10mL Liquid, 150 mL
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Estrogen Agonist/Antagonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Tamoxifen is used to treat breast cancer that has spread to other parts of the body in men and women. It is used to treat early breast cancer in women who have already been treated with surgery, radiation, and/or chemotherapy. It is used to reduce the risk of developing a more serious type of breast cancer in women who have had ductal carcinoma in situ (DCIS; a type of breast cancer that does not spread outside of the milk duct where it forms) and who have been treated with surgery and radiation. It is used to reduce the risk of breast cancer in women who are at high risk for the disease due t...
Read the full MedlinePlus article ↗- That depends on your situation. Tamoxifen is used for a few related but different reasons: treating breast cancer that has spread, helping prevent breast cancer from coming back af...
- What exactly is tamoxifen being used for in my case?
- For most uses — including after surgery for breast cancer, after DCIS treatment, and for high-risk risk reduction — the standard course is 5 years of daily treatment. Soltamox is a...
- Hot flashes are the most common thing people notice — they can range from mild to pretty disruptive. Vaginal discharge, irregular periods, nausea, and fatigue are also common. Thes...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Tamoxifen Citrate — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII 21C2F5E8RE
Anise is a plant-derived flavoring from anise seeds with a licorice-like taste. It is added to medicines to improve flavor and make the product more pleasant to take.
-
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII 61ZBX54883
Licorice is a natural extract from the licorice plant root. It's used in medicines as a flavoring agent to mask bitter tastes and improve how the medicine tastes.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 506T60A25R
Sorbitol is a natural sugar alcohol derived from glucose. It serves as a sweetener, humectant, and bulking agent in medications to improve taste and help maintain moisture in the product.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $4.61 | $690.86 / 150 ml |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Soltamox 20 mg/10mLthis 51862-0682-00 | Mayne | 150 ml | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 51862-0682-00 You're viewing this | 1 CONTAINER in 1 CARTON (51862-682-00) / 150 mL in 1 CONTAINER | — | — | 2021-12-06 | Active |
| 51862-0682-01 | 1 CONTAINER in 1 CARTON (51862-682-01) / 150 mL in 1 CONTAINER | $4.40 / mL | $660.14 | 2021-06-18 | Active |
Pack size FAQ
What quantity is in NDC 51862-0682-00?
What is the difference between NDC 51862-0682-00 and NDC 51862-0682-01?
What NDC number is used to bill for this package of SOLTAMOX TAMOXIFEN CITRATE 20 mg/10mL Liquid?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: UTERINE MALIGNANCIES and THROMBOEMBOLIC EVENTS Serious and life-threatening events from the use of SOLTAMOX include uterine malignancies, stroke, and pulmonary embolism [see Warnings and Precautions (5.1 , 5.2) ] . Fatal cases of each type of event have occurred. Incidence rates per 1000 women-years for these events were estimated from the National Surgical Adjuvant Breast and Bowel Project (NSABP) P-1 trial in women at high risk for breast cancer [see Clinical Studies (14.4) ] : Endometrial adenocarcinoma: 2.20 for tamoxifen vs.
0.71for placebo Uterine sarcoma: 0.17 for tamoxifen vs. 0.04 for placebo Stroke: 1.43 for tamoxifen vs. 1.00 for placebo.
Pulmonary embolism: 0.75 for tamoxifen versus 0.25 for placebo. Discuss the potential benefits of tamoxifen versus the potential risks of these serious events with women at high risk for breast cancer and women with ductal carcinoma in situ (DCIS) considering tamoxifen to reduce the risk of developing breast cancer [see Warnings and Precautions (5) ]. For most patients already diagnosed with breast cancer, the benefits of tamoxifen outweigh its risks.
WARNING: UTERINE MALIGNANCIES and THROMBOEMBOLIC EVENTS See full prescribing information for complete boxed warning . Serious, life-threatening, and fatal events from use of tamoxifen include uterine malignancies, stroke, and pulmonary embolism. ( 5.1 , 5.2 ) Discuss risks and benefits of tamoxifen with women at high risk for breast cancer and women with ductal carcinoma in situ (DCIS) when considering tamoxifen use to reduce the risk of developing breast cancer.
( 5.1 , 5.2 ) For most patients already diagnosed with breast cancer, the benefits of tamoxifen outweigh its risks. ( 5.1 , 5.2 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE SOLTAMOX is an estrogen agonist/antagonist indicated: For treatment of adult patients with estrogen receptor-positive metastatic breast cancer ( 1.1 ) For adjuvant treatment of adult patients with early stage estrogen receptor- positive breast cancer ( 1.2 ) To reduce risk of invasive breast cancer following breast surgery and radiation in adult women with ductal carcinoma in situ (DCIS) ( 1.3 ) To reduce the incidence of breast cancer in adult women at high risk ( 1.4 )
1.1Metastatic Breast Cancer SOLTAMOX is indicated for the treatment of adult patients with estrogen receptor-positive metastatic breast cancer.
1.2Adjuvant Treatment of Breast Cancer SOLTAMOX is indicated: for the adjuvant treatment of adult patients with early stage estrogen receptor-positive breast cancer to reduce the occurrence of contralateral breast cancer in adult patients when used as adjuvant therapy for the treatment of breast cancer.
1.3Ductal Carcinoma in Situ In adult women with DCIS, following breast surgery and radiation, SOLTAMOX is indicated to reduce the risk of invasive breast cancer [see Boxed Warning and Clinical Studies (14.3) ] .
1.4Reduction in Breast Cancer Incidence in Women at High Risk SOLTAMOX is indicated to reduce the incidence of breast cancer in adult women at high risk for breast cancer. [see Boxed Warning and Clinical Studies (14.4) ] .
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Metastatic breast cancer: 20-40 mg per day. For doses greater than 20 mg per day, administer in divided doses (morning and evening). ( 2 ) Adjuvant treatment of breast cancer, DCIS, reduction of breast cancer incidence in women at high risk: 20 mg per day ( 2 ) Metastatic Breast Cancer For patients with breast cancer, the recommended daily dose of SOLTAMOX is 20 to 40 mg.
Doses greater than 20 mg per day should be given in divided doses (morning and evening). Adjuvant Treatment of Breast Cancer For use in the adjuvant setting, the recommended dose of SOLTAMOX is 20 mg daily for 5-10 years [see Clinical Studies (14.2) ] . Doses greater than 20 mg daily yield no additional clinical benefit.
Ductal Carcinoma in Situ For patients with DCIS, the recommended dose of SOLTAMOX is 20 mg daily for 5 years. Reduction in Breast Cancer Incidence in Women at High Risk In the risk reduction setting, the recommended dose of SOLTAMOX is 20 mg daily for 5 years .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS SOLTAMOX oral solution: Each 10 mL of solution contains 20 mg tamoxifen, equivalent to 30.4 mg tamoxifen citrate. Oral solution: Each 10 mL of solution contains 20 mg tamoxifen, equivalent to 30.4 mg tamoxifen citrate. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS SOLTAMOX is contraindicated in patients with known hypersensitivity (e.g., angioedema, serious skin reactions) to tamoxifen or any other SOLTAMOX ingredient [see Adverse Reactions (6.2) ] . SOLTAMOX is contraindicated in patients who require concomitant warfarin therapy or have a history of deep vein thrombosis or pulmonary embolus if the indication for treatment is either reduction of breast cancer incidence in high-risk patients or risk reduction of invasive breast cancer after treatment of DCIS [see Warnings and Precautions (5.2) and Drug Interactions (7.2) ].
Known hypersensitivity to tamoxifen or any other SOLTAMOX ingredient ( 4 ) In patients who require concomitant warfarin therapy or have a history of deep vein thrombosis or pulmonary embolus, if the indication for treatment is either reduction of breast cancer incidence in high-risk patients or risk reduction of invasive breast cancer after treatment of DCIS ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Uterine malignancies: Promptly evaluate abnormal vaginal bleeding in a woman with current or past tamoxifen use. ( 5.1 ) Thromboembolic events: Risk increases with coadministered chemotherapy. For treatment of breast cancer, consider risks and benefits in patients with a history of thromboembolic events.
( 5.2 ) Embryo-fetal toxicity: Can cause fetal harm. Advise females of reproductive potential of the potential risk to a fetus and to use effective contraception. ( 5.3 , 8.1 , 8.3 ) Effects on the liver: Liver cancer and liver abnormalities, some fatal, have occurred.
Perform periodic liver function testing. ( 5.4 , 5.9 )
5.1Endometrial Cancer, Uterine Sarcoma, and Other Effects on the Uterus Endometrial Cancer and Uterine Sarcoma An increased incidence of uterine malignancies (endometrial adenocarcinoma and uterine sarcoma), including fatal cases, has been reported with tamoxifen treatment. The underlying mechanism is unknown, but may be related to the estrogen-like effect of tamoxifen. Most uterine malignancies seen with tamoxifen are classified as adenocarcinoma of the endometrium; however, uterine sarcomas, including malignant mixed mullerian tumors (MMMT), have also been reported.
Uterine sarcoma was generally associated with a higher FIGO stage (III/IV) at diagnosis, poor prognosis, and short survival. Uterine sarcoma has been reported to occur more frequently among long-term users (≥2 years) of tamoxifen than non-users. Promptly evaluate any patient receiving or who has previously received tamoxifen who reports abnormal vaginal bleeding.
Patients receiving or who have previously received tamoxifen should have annual gynecological examinations. Advise patients to promptly inform a healthcare provider if they experience any abnormal gynecological symptoms (e.g., menstrual irregularities, abnormal vaginal bleeding, changes in vaginal discharge, or pelvic pain or pressure). There are no data to suggest that routine endometrial sampling in asymptomatic women taking tamoxifen is beneficial.
In a review of long-term data (median length of total follow-up was 6.9 years, including blinded follow-up) on 8,306 women with an intact uterus at randomization in the NSABP P-1 risk reduction trial, the incidence of both adenocarcinomas and uterine sarcomas was increased in women taking tamoxifen. During blinded follow-up, there were 36 cases of FIGO Stage I endometrial adenocarcinoma (22 were FIGO Stage IA, 13 IB, and 1 IC) in women receiving tamoxifen and 15 cases in women receiving placebo [14 were FIGO Stage I (9 IA and 5 IB), and 1 case was FIGO Stage IV].
During total follow-up, endometrial adenocarcinoma was reported in 53 women randomized to tamoxifen (30 cases of FIGO Stage IA, 20 were Stage IB, 1 was Stage IC, and 2 were Stage IIIC), and 17 women randomized to placebo (9 cases were FIGO Stage IA, 6 were Stage IB, 1 was Stage IIIC, and 1 was Stage IVB) (incidence per 1,000 women-years of 2.20 and 0.71, respectively). Uterine sarcomas were reported in 4 women randomized to tamoxifen (1 was FIGO IA, 1 was FIGO IB, 1 was FIGO IIA, and 1 was FIGO IIIC) and 1 patient randomized to placebo (FIGO IA); incidence per 1,000 women-years of 0.17 and 0.04, respectively.
Of the patients randomized to tamoxifen, the FIGO IA and IB cases were a MMMT and sarcoma, respectively; the FIGO II was a MMMT; and the FIGO III was a sarcoma; and the 1 patient randomized to placebo had a MMMT. A similar increased incidence in endometrial adenocarcinoma and uterine sarcoma was observed among women receiving tamoxifen in 5 other NSABP clinical trials. In the NSABP P-1 trial, endometrial sampling did not alter the endometrial cancer detection rate compared to women who did not undergo endometrial sampling (0.6% with sampling, 0.5% without sampling) for women who had not undergone hysterectomy.
Non-Malignant Effects on the Uterus An increased incidence of endometrial changes including hyperplasia and polyps has been reported with t…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed below and elsewhere in the labeling: Uterine malignancies [see Boxed Warning , Warnings and Precautions (5.1) , and Clinical Studies (14.4) ] Thromboembolic events [see Boxed Warning , Warnings and Precautions (5.2) , and Clinical Studies (14.4) ] Embryo-Fetal Toxicity [see Warnings and Precautions (5.3) , and Use in Specific Populations (8.1 , 8.3) ] Liver cancer [see Warnings and Precautions (5.4) ] Most common adverse reactions: hot flashes, mood disturbances, vaginal discharge, vaginal bleeding, nausea, and fluid retention ( 6.1 ).
To report SUSPECTED ADVERSE REACTIONS, contact Mayne Pharma at 1-844-825-8500 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse Reactions in Patients with Metastatic Breast Cancer In patients treated with tamoxifen for metastatic breast cancer, the most frequent adverse reaction was hot flashes. Other adverse reactions which were seen less commonly are hypercalcemia, peripheral edema, distaste for food, pruritus vulvae, depression, dizziness, lightheadedness, headache, hair thinning and/or partial hair loss, and vaginal dryness.
Increased bone, tumor pain and local disease flare have occurred. Patients with soft tissue disease may have sudden increases in the size of preexisting lesions, sometimes associated with marked erythema within and surrounding the lesions and/or the development of new lesions. When they occurred, the bone pain or disease flares were seen shortly after starting tamoxifen and generally subsided rapidly.
Premenopausal Women with Metastatic Breast Cancer Table 1 summarizes the incidence of adverse reactions reported at a frequency of 2% or greater from clinical trials that compared tamoxifen therapy to ovarian ablation in premenopausal patients with metastatic breast cancer. Table 1: Adverse Reactions (frequency ≥2% in either arm) from Trials Comparing Tamoxifen to Ovarian Ablation in Premenopausal Women with Metastatic Breast Cancer % of Women Tamoxifen N=104 Ovarian Ablation N=100 Adverse Reactions Some women had more than one adverse reaction.
Flush 33 46 Amenorrhea 16 69 Altered menses 13 5 Oligomenorrhea 9 1 Bone pain 6 6 Menstrual disorder 6 4 Nausea 5 4 Cough/coughing 4 1 Edema 4 1 Fatigue 4 1 Musculoskeletal pain 3 0 Pain 3 4 Ovarian cyst(s) 3 2 Depression 2 2 Abdominal cramps 1 2 Anorexia 1 2 Adverse Reactions in Adjuvant Breast Cancer In the NSABP B-14 study, women with axillary node-negative breast cancer were randomized to 5 years of tamoxifen 20 mg per day or placebo following primary surgery [see Clinical Studies (14.2) ]. Table 2 presents the most common adverse reactions (mean follow-up of approximately 6.9 years) that were more common on tamoxifen than placebo.
Table 2: Most Common Adverse Reactions in Women with Axillary Node-Negative Breast Cancer (Study NSABP B-14) % of Women Tamoxifen N=1,422 Placebo N=1,437 Hot flashes 64 48 Fluid retention 32 30 Vaginal discharge 30 15 Nausea 26 24 Irregular menses 25 19 Weight loss (>5%) 23 18 Skin changes 19 15 Increased SGOT 5 3 Increased bilirubin 2 1 Increased creatinine 2 1 Thrombocytopenia Defined as a platelet count of < 100,000/mm 3 2 1 Thrombotic events Two of the tamoxifen-treated patients who had thrombotic events died. Deep vein thrombosis 0.8
0.2Pulmonary embolism 0.5
0.2Superficial phlebitis 0.4 0 In the Eastern Cooperative Oncology Group (ECOG) adjuvant breast cancer trial [see Clinical Studies (14.2) ] , tamoxifen or placebo was administered for 2 years to women following mastectomy. When compared to placebo, tamoxifen showed a higher incidence of hot flashes (19% vs. 8% for placebo). The incidence of all other adverse reactions w…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Anastrozole and letrozole: Should not be used in combination with tamoxifen. ( 7.1 ) Warfarin: Do not use in patients taking tamoxifen for DCIS and for reduction in breast cancer incidence in women at high risk. ( 4 ) Closely monitor coagulation indices for increased anticoagulant effect when used with tamoxifen for metastatic breast cancer or as adjuvant therapy. ( 7.2 )
7.1Aromatase Inhibitors Anastrozole The combination of anastrozole and tamoxifen did not demonstrate any benefit when compared to tamoxifen alone and should be avoided in all patients [see Clinical Studies (14.2) ] . In the ATAC trial, coadministration of anastrozole and tamoxifen in breast cancer patients reduced the anastrozole plasma concentration by 27% compared to that achieved with anastrozole alone. The tamoxifen concentration was not altered [see Clinical Pharmacology (12.3) ].
Letrozole The concomitant use of letrozole with tamoxifen is not recommended because the efficacy of the combination in the adjuvant treatment of breast cancer has not been established. Tamoxifen reduced the plasma concentration of letrozole by 38% when these drugs were co-administered [see Clinical Pharmacology (12.3) ]. 7.2.
Warfarin A marked increase in anticoagulant effect may occur when tamoxifen is used in combination with warfarin. Closely monitor coagulation indices in patients who are taking tamoxifen for either the treatment of metastatic breast cancer or as adjuvant therapy who require concomitant use of warfarin [see Contraindications (4) ] .
7.3Inducers of CYP3A4 Strong CYP3A4 inducers should not be used with tamoxifen. Strong CYP3A4 inducers (e.g., rifampin) reduce tamoxifen AUC and C max [see Clinical Pharmacology (12.3) ] .
7.4Strong Inhibitors of CYP2D6 The impact on the efficacy of tamoxifen with co-administration of strong CYP2D6 inhibitors (e.g., paroxetine) is not well established. Some studies have shown that the efficacy of tamoxifen may be reduced when the drugs are co-administered as a result of reduced levels of potent active metabolites of tamoxifen . However, other studies have failed to demonstrate such an effect [see Clinical Pharmacology (12.3) ] .
7.5Drug-Laboratory Test Interactions There are postmarketing reports of T 4 elevations in postmenopausal patients taking tamoxifen that may be explained by increases in thyroid-binding globulin. These elevations were not accompanied by clinical hyperthyroidism. Variations in the karyopyknotic index on vaginal smears and various degrees of estrogen effect on Pap smears have been seen in postmenopausal patients taking tamoxifen.
🔄 Drug / Laboratory Test Interactions ▾
7.5Drug-Laboratory Test Interactions There are postmarketing reports of T 4 elevations in postmenopausal patients taking tamoxifen that may be explained by increases in thyroid-binding globulin. These elevations were not accompanied by clinical hyperthyroidism. Variations in the karyopyknotic index on vaginal smears and various degrees of estrogen effect on Pap smears have been seen in postmenopausal patients taking tamoxifen.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed. ( 8.2 ) Females and males of reproductive potential: Verify pregnancy status of females prior to initiation of tamoxifen. Advise females to use effective contraception. ( 8.3 )
8.1Pregnancy Risk Summary SOLTAMOX can cause fetal harm when administered to a pregnant woman . There are no adequate and well- controlled studies of tamoxifen in pregnant women. There are limited postmarketing reports of vaginal bleeding, spontaneous abortions, birth defects, and fetal deaths in pregnant women taking tamoxifen.
In a primate model administration of tamoxifen at doses 2 times higher than the maximum recommended human dose resulted in spontaneous abortion. In rat and rabbit studies, doses of tamoxifen less than or equal to human doses resulted in increased embryotoxicity, abortions, and altered learning behaviors. Additionally, rodent models showed reproductive tract changes often associated with DES in offspring of both sexes [ see Data ].
Advise pregnant women of the potential risk to a fetus, including the potential long-term risk of a DES-like syndrome. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Data Animal Data In embryofetal development studies in rats using doses significantly below those used in humans (0.01 to 0.03 times the recommended human dose on a mg/m 2 basis), a lower incidence of embryo implantation and a higher incidence of fetal death or delayed in utero growth occurred, along with slower learning behavior in some rat pups when compared to historical controls. When pregnant rabbits received tamoxifen during organogenesis, abortion and premature delivery occurred at doses of greater than 0.125 mg/kg/day (about 0.05 times the daily maximum recommended human dose on a mg/m 2 basis).
Although reversible nonteratogenic skeletal variations occurred in rat reproductive studies at doses less than or equal to the human dose, there were no teratogenic changes in either rats or rabbits. In pregnant marmosets, administration of 10 mg/kg/day tamoxifen (about 2 times the daily maximum recommended human dose on a mg/m 2 basis) during organogenesis or in the last half of pregnancy terminated pregnancy in some animals. In pregnancies that continued, there were no malformations or deformations in offspring.
In rodent models of fetal reproductive tract development, tamoxifen (at doses 0.002 to 2.4 times the daily maximum recommended human dose on a mg/m 2 basis) caused changes in both sexes that are similar to those caused by estradiol, ethynylestradiol and diethylstilbestrol. Although the clinical relevance of these changes is unknown, some of these changes, especially vaginal adenosis, are similar to those seen in young women who were exposed to diethylstilbestrol in utero and who have a 1 in 1,000 risk of developing clear-cell adenocarcinoma of the vagina or cervix.
To date, in utero exposure to tamoxifen has not been shown to cause vaginal adenosis, or clear-cell adenocarcinoma of the vagina or cervix, in young women; however, only a small number of young women have been exposed to tamoxifen in utero , and a smaller number have been followed long enough (to age 15 to 20) to determine whether vaginal or cervical neoplasia could occur as a result of this exposure.
8.2Lactation Risk Summary There is no information regarding the presence of tamoxifen or its metabolites in human milk or its effects on the breastfed infant. Additional information from juvenile animal studies suggests a potential for serious long- term adverse effects for breastfed infants exposed to tamoxifen through breast milk [see Use in Specific Populations (8.4) ] . Because of the potential for serious adverse reactions in breastfed infants from tamoxifen, advise a w…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary SOLTAMOX can cause fetal harm when administered to a pregnant woman . There are no adequate and well- controlled studies of tamoxifen in pregnant women. There are limited postmarketing reports of vaginal bleeding, spontaneous abortions, birth defects, and fetal deaths in pregnant women taking tamoxifen.
In a primate model administration of tamoxifen at doses 2 times higher than the maximum recommended human dose resulted in spontaneous abortion. In rat and rabbit studies, doses of tamoxifen less than or equal to human doses resulted in increased embryotoxicity, abortions, and altered learning behaviors. Additionally, rodent models showed reproductive tract changes often associated with DES in offspring of both sexes [ see Data ].
Advise pregnant women of the potential risk to a fetus, including the potential long-term risk of a DES-like syndrome. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Data Animal Data In embryofetal development studies in rats using doses significantly below those used in humans (0.01 to 0.03 times the recommended human dose on a mg/m 2 basis), a lower incidence of embryo implantation and a higher incidence of fetal death or delayed in utero growth occurred, along with slower learning behavior in some rat pups when compared to historical controls. When pregnant rabbits received tamoxifen during organogenesis, abortion and premature delivery occurred at doses of greater than 0.125 mg/kg/day (about 0.05 times the daily maximum recommended human dose on a mg/m 2 basis).
Although reversible nonteratogenic skeletal variations occurred in rat reproductive studies at doses less than or equal to the human dose, there were no teratogenic changes in either rats or rabbits. In pregnant marmosets, administration of 10 mg/kg/day tamoxifen (about 2 times the daily maximum recommended human dose on a mg/m 2 basis) during organogenesis or in the last half of pregnancy terminated pregnancy in some animals. In pregnancies that continued, there were no malformations or deformations in offspring.
In rodent models of fetal reproductive tract development, tamoxifen (at doses 0.002 to 2.4 times the daily maximum recommended human dose on a mg/m 2 basis) caused changes in both sexes that are similar to those caused by estradiol, ethynylestradiol and diethylstilbestrol. Although the clinical relevance of these changes is unknown, some of these changes, especially vaginal adenosis, are similar to those seen in young women who were exposed to diethylstilbestrol in utero and who have a 1 in 1,000 risk of developing clear-cell adenocarcinoma of the vagina or cervix.
To date, in utero exposure to tamoxifen has not been shown to cause vaginal adenosis, or clear-cell adenocarcinoma of the vagina or cervix, in young women; however, only a small number of young women have been exposed to tamoxifen in utero , and a smaller number have been followed long enough (to age 15 to 20) to determine whether vaginal or cervical neoplasia could occur as a result of this exposure.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of SOLTAMOX in pediatric patients have not been established. Tamoxifen Use in McCune-Albright Syndrome The safety and effectiveness of SOLTAMOX for the treatment of girls with McCune-Albright syndrome, including long-term effects, have not been established. A single, uncontrolled multicenter trial of tamoxifen 20 mg once a day was conducted in a heterogeneous group of girls with McCune-Albright syndrome and precocious puberty manifested by physical signs of pubertal development, episodes of vaginal bleeding, and/or advanced bone age (bone age of at least 12 months beyond chronological age).
Twenty-eight female pediatric patients, aged 2 to 10 years, were treated for up to 12 months. Effect of treatment on frequency of vaginal bleeding, bone age advancement, and linear growth rate was assessed relative to prestudy baseline. Tamoxifen treatment was associated with a 50% reduction in frequency of vaginal bleeding episodes by patient or family report (mean annualized frequency of 3.56 episodes at baseline and 1.73 episodes on-treatment).
Among the patients who reported vaginal bleeding during the prestudy period, 62% (13 out of 21 patients) reported no bleeding for a 6-month period and 33% (7 out of 21 patients) reported no vaginal bleeding for the duration of the trial. Not all patients improved on treatment and a few patients not reporting vaginal bleeding in the 6 months prior to enrollment reported menses on treatment. Tamoxifen therapy was associated with a reduction in mean rate of increase of bone age (defined as the ratio of bone age change and chronological age); individual responses with regard to this endpoint were highly heterogeneous.
Linear growth rate (height velocity) was reduced during the course of tamoxifen treatment in a majority of patients (mean change of 1.68 cm/year relative to baseline; change from 7.47 cm/year at baseline to 5.79 cm/year on study). This change was not uniformly seen across all stages of bone maturity; all recorded response failures occurred in patients with bone ages less than 7 years at screening. Mean uterine volume increased after 6 months of treatment and doubled at the end of the one-year study.
A causal relationship to tamoxifen has not been established; however, as an increase in the incidence of endometrial adenocarcinoma and uterine sarcoma has been noted in adults treated with tamoxifen, continued monitoring of McCune-Albright patients treated with tamoxifen for long-term uterine effects is recommended. Pharmacokinetics in Pediatric Patients The pharmacokinetics of tamoxifen and N-desmethyl tamoxifen were characterized using a population pharmacokinetic analysis with sparse samples per patient obtained from 27 female pediatric patients aged 2 to 10 years enrolled in a study of tamoxifen in treating McCune-Albright syndrome.
Clearance (CL/F), adjusted for body weight, in female pediatric patients was approximately 2.3-fold higher than in adult female breast cancer patients. In the youngest cohort of female pediatric patients (2 to 6 year olds), CL/F was 2.6-fold higher; in the oldest cohort (7 to 10.9 year olds), CL/F was approximately 1.9-fold higher. Exposure to N-desmethyl tamoxifen was comparable between the pediatric and adult patients.
In pediatric patients, an average steady-state peak plasma concentration (Css, max) and AUC were 187 ng/mL and 4,110 ng hr/mL, respectively, and Css, max occurred approximately 8 hours after dosing. Animal Data Direct neonatal exposure of tamoxifen to mice and rats produced: 1) reproductive tract lesions in female rodents (similar to those seen in humans after intrauterine exposure to DES) and 2) functional defects of the reproductive tract in male rodents such as testicular atrophy and arrest of spermatogenesis.
🧓 Geriatric Use ▾
8.5Geriatric Use Ductal Carcinoma in Situ In the NSABP B-24 trial, the percentage of women at least 65 years of age was 23%. Women at least 70 years of age accounted for 10% of participants. A total of 14 and 12 invasive breast cancers were seen among participants 65 and older in the placebo and tamoxifen groups, respectively.
This subset is too small to reach any conclusions on efficacy. Across all other endpoints, the results in this subset were comparable to those of younger women enrolled in this trial. No overall differences in tolerability were observed between older and younger patients.
Reduction in Breast Cancer Incidence in Women at High Risk In the NSABP P-1 trial, the percentage of women at least 65 years of age was 16%. Women at least 70 years of age accounted for 6% of the participants. A reduction in breast cancer incidence was seen among participants in each of the subsets.
A total of 28 and 10 invasive breast cancers were seen among participants 65 and older in the placebo and tamoxifen groups, respectively. Across all other outcomes, the results in this subset reflect the results observed in the subset of women at least 50 years of age. No overall differences in tolerability were observed between older and younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE No specific treatment for SOLTAMOX overdosage is recommended, other than symptomatic treatment. In a study of advanced metastatic cancer patients to determine the maximum tolerated dose of tamoxifen that could reverse multidrug resistance, the following adverse events were observed: acute neurotoxicity manifested by tremor, hyperreflexia, unsteady gait, and dizziness. These symptoms occurred within 3 to 5 days of beginning tamoxifen and cleared within 2 to 5 days after stopping therapy.
No permanent neurologic toxicity was noted. One patient experienced a seizure several days after tamoxifen was discontinued and neurotoxic symptoms had resolved. The causal relationship of the seizure to tamoxifen therapy is unknown.
Doses given in these patients were all greater than 400 mg/m 2 loading dose (at least 6-fold higher than the recommended dosage), followed by maintenance doses of 150 mg/m 2 of tamoxifen given twice a day (at least 6-fold higher than the recommended dosage). In the same study, prolongation of the QT interval on the electrocardiogram was noted when patients were given doses higher than 250 mg/m 2 loading dose (at least 6-fold higher than the recommended dose) , followed by maintenance doses of 80 mg/m 2 of tamoxifen given twice a day.
For a woman with a body surface area of 1.5 m 2 , the minimal loading dose and maintenance doses at which neurological symptoms and QT changes occurred were at least 6-fold higher in respect to the maximum recommended dose. Signs observed at the highest doses following studies to determine LD 50 in animals were respiratory difficulties and convulsions.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Tamoxifen is an estrogen agonist/antagonist. Tamoxifen competes with estrogen for binding to the estrogen receptor, which can result in a decrease in estrogen receptor signaling-dependent growth in breast tissue. Tamoxifen has demonstrated antitumor activity against human breast cancer cell lines xenografted in mice.
The drug has been shown to inhibit the induction of rat mammary carcinoma induced by dimethylbenzanthracene (DMBA) and to cause the regression of already established DMBA-induced tumors.
12.3Pharmacokinetics Absorption and Distribution Following a single oral dose of 20 mg tamoxifen, an average peak plasma concentration of 40 ng/mL (range 35 to 45 ng/mL) occurred approximately 5 hours after dosing. The decline in plasma concentrations of tamoxifen is biphasic with a terminal elimination half-life of about 5 to 7 days. The average peak plasma concentration of N- desmethyl tamoxifen, the major metabolite, is 15 ng/mL (range 10 to 20 ng/mL).
Chronic administration of 10 mg tamoxifen given twice daily for 3 months to patients results in average steady-state plasma concentrations of 120 ng/mL (range 67 to 183 ng/mL) for tamoxifen and 336 ng/mL (range 148 to 654 ng/mL) for N-desmethyl tamoxifen. The average steady-state plasma concentrations of tamoxifen and N-desmethyl tamoxifen after administration of 20 mg tamoxifen once daily for 3 months are 122 ng/mL (range 71 to 183 ng/mL) and 353 ng/mL (range 152 to 706 ng/mL), respectively. The steady-state plasma concentrations of endoxifen and 4-hydroxytamoxifen are 29.1 (95% CI 24.6 to 33.6) and 3.7 (95% CI 3.3 to 4.1) ng/mL, respectively.
After initiation of therapy, steady-state concentrations for tamoxifen are achieved in about 4 weeks and steady-state concentrations for N-desmethyl tamoxifen are achieved in about 8 weeks, suggesting a half-life of approximately 14 days for this metabolite. In a steady-state, crossover study of 10 mg tamoxifen tablets given twice a day vs. a 20 mg tamoxifen tablet given once daily, the 20 mg tamoxifen tablet was bioequivalent to the 10 mg tamoxifen tablets. A pharmacokinetic study was performed in healthy perimenopausal and postmenopausal female subjects to evaluate the bioavailability of SOLTAMOX (n=30) in comparison with the commercially available tamoxifen citrate tablets (n=33) under fasting conditions.
A third arm evaluated the effect of food on SOLTAMOX (n=16). The rate and extent of absorption of SOLTAMOX was found to be bioequivalent to that of tamoxifen citrate tablets under fasting conditions. There was no difference in bioavailability (C max and AUC) of SOLTAMOX oral solution between fed and fasting states, and therefore SOLTAMOX can be given without regard to meals.
Metabolism Tamoxifen is extensively metabolized by CYP450 enzymes, including CYP3A, CYP2D6, CYP2C9, CYP2C19, and CYP2B6. N-desmethyltamoxifen, formed predominantly by CYP3A, is the major metabolite found in plasma. The pharmacological activity of N-desmethyltamoxifen is similar to that of tamoxifen.
Endoxifen and 4-hydroxytamoxifen, identified as minor metabolites, have 100-fold greater affinity for the estrogen receptor and 30 to 100-fold greater potency in suppressing estrogen-dependent cell proliferation than tamoxifen. The polymorphic enzyme CYP2D6 is involved in the formation of endoxifen and 4-hydroxytamoxifen, and it is the key enzyme that catalyzes the formation of endoxifen from N-desmethyltamoxifen. Endoxifen concentrations may differ among patients because of various CYP2D6 genotypes [see Clinical Pharmacology (12.5) ] .
Phase 2 enzymes, such as SULT1A1, UGT2B7, and UGT1A4, are associated with tamoxifen clearance from plasma. Excretion Studies in women receiving 20 mg of 14 C tamoxifen showed that approximately 65% of the administered dose was excreted from the body over a period of 2 weeks, with fecal excretion as the primary route of elimination. The drug is excreted mainly as polar conjugates, with un…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Tamoxifen is an estrogen agonist/antagonist. Tamoxifen competes with estrogen for binding to the estrogen receptor, which can result in a decrease in estrogen receptor signaling-dependent growth in breast tissue. Tamoxifen has demonstrated antitumor activity against human breast cancer cell lines xenografted in mice.
The drug has been shown to inhibit the induction of rat mammary carcinoma induced by dimethylbenzanthracene (DMBA) and to cause the regression of already established DMBA-induced tumors.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING SOLTAMOX oral solution is a sugar-free, clear colorless liquid, with licorice and aniseed odor and taste. It is supplied in a 150 mL bottle with a dosing cup intended for the measurement of SOLTAMOX oral solution only. Each 10 mL of solution contains 20 mg tamoxifen, equivalent to 30.4 mg tamoxifen citrate.
NDC# 51862- 682 -01 Store at room temperatures 20° to 25°C (68° - 77°F); excursions permitted between 15° to 30°C (59° - 86°F) [see USP Controlled Room Temperature]. DO NOT freeze or refrigerate. Store in original packaging in order to protect from light.
Discard any unused portion after 3 months of first opening of the bottle.
📦 Storage and Handling ▾
Store at room temperatures 20° to 25°C (68° - 77°F); excursions permitted between 15° to 30°C (59° - 86°F) [see USP Controlled Room Temperature]. DO NOT freeze or refrigerate. Store in original packaging in order to protect from light. Discard any unused portion after 3 months of first opening of the bottle.
📋 Description ▾
11 DESCRIPTION SOLTAMOX (tamoxifen citrate) oral solution is for oral administration. Tamoxifen citrate is an estrogen agonist/antagonist. Chemically, tamoxifen is the trans-isomer of a triphenylethylene derivative.
The chemical name is (Z)2-[4-(1,2- diphenyl-1-butenyl)phenoxy]- N , N -dimethylethanamine 2-hydroxy-1,2,3- propanetricarboxylate (1:1). The structural formula, empirical formula, and molecular weight are as follows: C 32 H 37 NO 8 M.W. 563.62 Tamoxifen citrate has a pKa′ of 8.85.
The equilibrium solubility in water at 37°C is 0.5 mg/mL, and is 0.2 mg/mL in
0.02N HCl at 37°C. Each 10 mL of SOLTAMOX oral solution contains 20 mg tamoxifen, equivalent to 30.4 mg tamoxifen citrate. The oral solution is a sugar-free, clear colorless liquid, with licorice and aniseed odor and taste supplied in a 150 mL bottle with a dosing cup.
SOLTAMOX oral solution contains the following inactive ingredients: ethanol, glycerol, propylene glycol, sorbitol solution, licorice flavor, aniseed flavor, purified water. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Uterine Malignancies Inform women that SOLTAMOX increases the risk of uterine malignancies (endometrial carcinoma and uterine sarcoma), including fatal cases. Advise women to promptly inform a healthcare provider if they experience any abnormal gynecological symptoms (e.g., menstrual irregularities, abnormal vaginal bleeding, changes in vaginal discharge, or pelvic pain or pressure.) Advise women receiving or who have previously received tamoxifen to undergo annual gynecological examinations [see Boxed Warning and Warnings and Precautions (5.1) ] .
Thromboembolic Events Inform patients that SOLTAMOX increases the risk of thromboembolic events (deep vein thrombosis, pulmonary embolism, and stroke), including fatal cases. Advise patients to seek medical attention immediately if signs or symptoms of a thromboembolic event occur [see Boxed Warning and Warnings and Precautions (5.2) ] . Embryo-Fetal Toxicity Advise pregnant women and females of reproductive potential of the potential that exposure during pregnancy or within 2 months prior to conception can result in fetal harm, including the potential long-term risk of a DES-like syndrome.
Advise females to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.3) and Use in Specific Populations (8.1) ] . Advise females of reproductive potential to use effective nonhormonal contraception while taking SOLTAMOX and for 2 months after the last dose [see Use in Specific Populations (8.3) ] . Lactation Advise women not to breastfeed during treatment and for 3 months after the last dose of SOLTAMOX [see Use in Specific Populations (8.2) ] .
Effects on the Liver Inform patients that SOLTAMOX may increase the risk of liver cancer and liver abnormalities [see Warnings and Precautions (5.4) ] .
💬 Medication Guide ▾
MEDICATION GUIDE SOLTAMOX ® (SOL-ta-mox) (tamoxifen citrate) oral solution Before taking SOLTAMOX, you and your healthcare provider should talk about the possible benefits and risks. The benefits and risks are different for women at high risk for breast cancer and women with breast cancer that is only inside the milk ducts (ductal carcinoma in-situ or DCIS) than for women who have been diagnosed with invasive breast cancer. For most people who already have invasive breast cancer, the benefits of SOLTAMOX are greater than the risks.
Talk to your healthcare provider about which risks may affect you. What is the most important information I should know about SOLTAMOX? SOLTAMOX can cause serious side effects, including: Uterine cancer .
Cancer of the lining of the uterus (endometrial adenocarcinoma) or cancer of the body of the uterus (uterine sarcoma) may happen more often in women who take SOLTAMOX and can lead to death. People who take or have taken SOLTAMOX should have a gynecologic exam every year. SOLTAMOX can also cause other non-cancer effects on the uterus, including: overgrowth of the lining of the uterus (hyperplasia) and uterine polyps endometriosis fibroids irregular menstrual periods or no menstrual periods (amenorrhea) Tell your healthcare provider right away if you get any of the following symptoms during or after treatment with SOLTAMOX: irregular menstrual periods abnormal vaginal bleeding a change in your vaginal discharge pelvic pain or pressure Blood clots in your veins or lungs.
Blood clots in your veins or lungs may happen more often in people who take SOLTAMOX and can lead to death, especially in people who take SOLTAMOX during their treatment with chemotherapy. Tell your healthcare provider right away if you get any of the following symptoms of a blood clot during treatment with SOLTAMOX: sudden chest pain, shortness of breath, or coughing up blood pain, tenderness, or swelling in one or both of your legs Stroke. Stroke can cause serious problems and can lead to death.
Get medical help right away if you get any of these symptoms of a stroke: sudden weakness, tingling, or numbness of your face, arm or leg, especially on one side of your body sudden confusion, trouble speaking or understanding sudden trouble seeing in one or both eyes sudden trouble walking, dizziness, loss of balance or coordination sudden severe headache with no known cause What is SOLTAMOX? SOLTAMOX is a prescription medicine used: to treat adults with estrogen receptor-positive breast cancer that has spread to other parts of the body (metastatic) to treat adults with early stage estrogen receptor-positive breast cancer after surgery and radiation for breast cancer to reduce the chance of developing breast cancer in the other breast in adults after surgery and radiation for breast cancer to reduce the risk of invasive breast cancer in adult women with DCIS, after breast surgery and radiation treatment to reduce the risk of getting breast cancer in women with a high risk of getting breast cancer It is not known if SOLTAMOX is safe and effective in children.
Do not take SOLTAMOX if you: have had a serious allergic reaction to tamoxifen or any other ingredient in SOLTAMOX. Ask your healthcare provider if you are not sure. have DCIS or a high-risk of breast cancer, and you need to take the blood thinner medicine warfarin, or have a history of a blood clot in your veins or lungs Before taking SOLTAMOX, tell your healthcare provider about all of your medical conditions, including if you: have uterine cancer or other problems with your uterus. See " What is the most important information I should know about SOLTAMOX? " have irregular menstrual periods, no menstrual periods, or abnormal vaginal bleeding have or had a blood clot in your veins or lungs have had a stroke are pregnant or plan to become pregnant.
SOLTAMOX can harm your unborn baby. You should not become pregnant during treatment with SOLTAMOX or within 2 months after you stop taking i…