
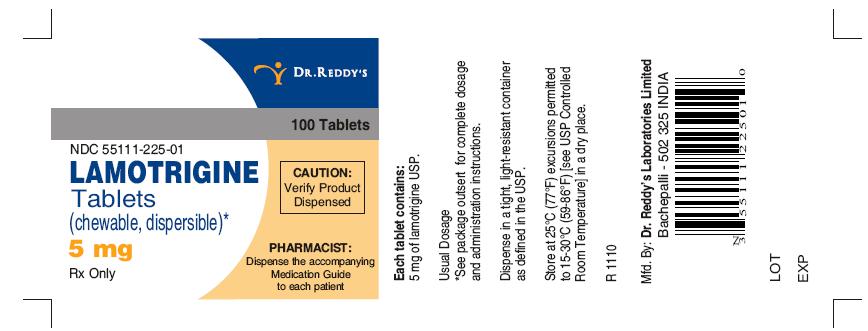
Lamotrigine 5 mg Tablet, Chewable, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Mood Stabilizer class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- I completely understand the impatience — but the slow ramp-up is one of the most important safety steps with lamotrigine. Going too fast significantly raises your risk of a serious...
- Why does my doctor keep telling me to increase my dose so slowly? Can't we just get to the right dose faster?
- That's a fair question, and the honest answer is: with lamotrigine, we can't reliably tell in advance which rashes are harmless and which are dangerous. So the rule is — call your...
- What kind of rash should I worry about? I get skin reactions from all sorts of things.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Lamotrigine — tap one for details:
Lamotrigine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 9755T40D11
Black currant is a plant-derived ingredient used as a natural flavoring and coloring agent in medications. It adds berry flavor and dark purple color to make medicines taste better and look more appealing.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 68401960MK
Crospovidone is a synthetic polymer made from polyvinylpyrrolidone. It acts as a disintegrant, helping tablets break apart quickly in the stomach so the medicine dissolves and absorbs into the body.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII SB8ZUX40TY
Saccharin sodium is an artificial sweetener made from saccharin salt. It's added to medicines to improve taste, especially in liquid formulations for children or bitter drugs.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.2940 | $29.40 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lamotrigine 5 mg 16571-0785-01 | Rising | 100 tablets | $0.161 | AB | Availability likely | — |
| Lamotrigine 5 mg 65862-0361-01 | Aurobindo | 100 tablets | $0.161 | AB | Availability likely | — |
| Lamotrigine 5 mg 68462-0228-01 | Glenmark | 100 tablets | $0.161 | AB | Availability likely | — |
| Lamictal 5 mg 00173-0526-00 | GlaxoSmithKline | 100 tablets | — | AB | FDA listed | — |
| lamotrigine 5 mg 46708-0095-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Lamotrigine 5 mgthis 55111-0225-01 | Dr.Reddy's | 100 tablets | — | AB | FDA listed | — |
| lamotrigine 5 mg 62332-0095-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Lamotrigine 5 mg 65841-0689-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Lamotrigine 5 mg 68382-0108-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 55111-0225-01 You're viewing this | 100 TABLET, CHEWABLE in 1 BOTTLE (55111-225-01) | 2009-01-29 | Active |
| 55111-0225-05 | 500 TABLET, CHEWABLE in 1 BOTTLE (55111-225-05) | 2009-01-29 | Active |
| 55111-0225-30 | 30 TABLET, CHEWABLE in 1 BOTTLE (55111-225-30) | 2009-01-29 | Active |
| 55111-0225-60 | 60 TABLET, CHEWABLE in 1 BOTTLE (55111-225-60) | 2009-01-29 | Active |
| 55111-0225-78 | 10 BLISTER PACK in 1 CARTON (55111-225-78) / 10 TABLET, CHEWABLE in 1 BLISTER PACK (55111-225-79) | 2009-01-29 | Active |
Pack size FAQ
What quantity is in NDC 55111-0225-01?
What is the difference between NDC 55111-0225-01 and NDC 55111-0225-30?
What NDC number is used to bill for this package of Lamotrigine 5 mg Tablet, Chewable?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SERIOUS SKIN RASHES Lamotrigine can cause serious rashes requiring hospitalization and discontinuation of treatment. The incidence of these rashes, which have included Stevens-Johnson syndrome, is approximately 0.3% to 0.8% in pediatric patients (aged 2 to 17 years) and 0.08% to 0.3% in adults receiving lamotrigine. One rash-related death was reported in a prospectively followed cohort of 1,983 pediatric patients (aged 2 to 16 years) with epilepsy taking lamotrigine as adjunctive therapy.
In worldwide postmarketing experience, rare cases of toxic epidermal necrolysis and/or rash-related death have been reported in adult and pediatric patients, but their numbers are too few to permit a precise estimate of the rate. Other than age, there are as yet no factors identified that are known to predict the risk of occurrence or the severity of rash caused by lamotrigine. There are suggestions, yet to be proven, that the risk of rash may also be increased by (1) coadministration of lamotrigine with valproate (includes valproic acid and divalproex sodium), (2) exceeding the recommended initial dose of lamotrigine, or (3) exceeding the recommended dose escalation for lamotrigine.
However, cases have occurred in the absence of these factors. Nearly all cases of life-threatening rashes caused by lamotrigine have occurred within 2 to 8 weeks of treatment initiation. However, isolated cases have occurred after prolonged treatment (e.g., 6 months).
Accordingly, duration of therapy cannot be relied upon as means to predict the potential risk heralded by the first appearance of a rash. Although benign rashes are also caused by lamotrigine, it is not possible to predict reliably which rashes will prove to be serious or life threatening. Accordingly, lamotrigine should ordinarily be discontinued at the first sign of rash, unless the rash is clearly not drug related.
Discontinuation of treatment may not prevent a rash from becoming life threatening or permanently disabling or disfiguring [see Warnings and Precautions (5.1 )]. W A RNING: SERIOUS SKIN RASHES See full prescribing information for complete boxed warning. Cases of life-threatening serious rashes, including Stevens-Johnson syndrome and toxic epidermal necrolysis, and/or rash-related death, havebeen caused by lamotrigine.
The rate of serious rash is greater in pediatric patients than in adults. Additional factors that may increase the risk of rash include. coadministration with valproate exceeding recommended initial dose of lamotrigine exceeding recommended dose escalation of lamotrigine. (5.1) Benign rashes are also caused by lamotrigine; however, it is not possible to predict which rashes will prove to be serious or life threatening.
Lamotrigine should be discontinued at the first sign of rash, unless the rash is clearly not drug related. (5.1)
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Lamotrigine tablet (chewable, dispersible) is indicated for: Epilepsy—adjunctive therapy in patients aged 2 years and older partial-onset seizures. primary generalized tonic-clonic seizures. generalized seizures of Lennox-Gastaut syndrome. Epilepsy—monotherapy in patients aged 16 years and older: Conversion to monotherapy in patients with partial-onset seizures who are receiving treatment with carbamazepine, phenytoin, phenobarbital, primidone, or valproate as the single AED. (1.1) Bipolar Disorder : Maintenance treatment of bipolar I disorder to delay the time to occurrence of mood episodes in patients treated for acute mood episodes with standard therapy.
(1.2) Limitations of Use: Treatment of acute manic or mixed episodes is not recommended. Effectiveness of lamotrigine in the acute treatment of mood episodes has not been established.
1.1Epilepsy Adjunctive Therapy Lamotrigine tablets (chewable, dispersible) are indicated as adjunctive therapy for the following seizure types in patients aged 2 years and older: partial seizures primary generalized tonic-clonic (PGTC) seizures generalized seizures of Lennox-Gastaut syndrome Monotherapy Lamotrigine tablets (chewable, dispersible) are indicated for conversion to monotherapy in adults (≥16 years of age) with partial-onset seizures who are receiving treatment with carbamazepine, phenytoin, phenobarbital, primidone, or valproate as the single antiepileptic drug (AED).
Safety and effectiveness of lamotrigine tablets (chewable, dispersible) are have not been established (1) as initial monotherapy; (2) for conversion to monotherapy from AEDs other than carbamazepine, phenytoin, phenobarbital, primidone, or valproate; or (3) for simultaneous conversion to monotherapy from 2 or more concomitant AEDs.
1.2Bipolar Disorder Lamotrigine tablets (chewable, dispersible) are indicated for the maintenance treatment of bipolar I disorder to delay the time to occurrence of mood episodes (depression, mania, hypomania, mixed episodes) in patients treated for acute mood episodes with standard therapy [see Clinical Studies (14.1) ]. Limitations of Use Treatment of acute manic or mixed episodes is not recommended. Effectiveness of lamotrigine in the acute treatment of mood episodes has not been established.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Dosing is based on concomitant medications, indication, and patient age. ( 2.1 , 2.2 , 2.3 , 2.4 ) To avoid an increased risk of rash, the recommended initial dose and subsequent dose escalations should not be exceeded. Do not restart lamotrigine tablets (chewable, dispersible)in patients who discontinued due to rash unless the potential benefits clearly outweigh the risks.
( 2.1 , 5.1 ) Adjustments to maintenance doses will be necessary in most patients starting or stopping estrogen-containing oral contraceptives. ( 2.1 , 5.7 ) Discontinuation: Taper over a period of at least 2 weeks (approximately 50% dose reduction per week). ( 2.1 , 5.8 ) Epilepsy Adjunctive therapy—See Table 1 for patients older than 12 years and Tables 2 and 3 for patients aged 2 to 12 years.
(2.2) Conversion to monotherapy—See Table 4. ( 2.3 ) Bipolar Disorder: See Tables 5 and 6 (2.4)
2.1General Dosing Considerations Rash There are suggestions, yet to be proven, that the risk of severe, potentially life-threatening rash may be increased by (1) coadministration of lamotrigine tablets (chewable, dispersible) with valproate, (2) exceeding the recommended initial dose of lamotrigine tablets (chewable, dispersible), or (3) exceeding the recommended dose escalation for lamotrigine tablets (chewable, dispersible). However, cases have occurred in the absence of these factors [see Boxed Warning ]. Therefore, it is important that the dosing recommendations be followed closely.
The risk of nonserious rash may be increased when the recommended initial dose and/or the rate of dose escalation for lamotrigine tablets (chewable, dispersible) is exceeded and in patients with a history of allergy or rash to other AEDs. It is recommended that lamotrigine tablets (chewable, dispersible) not be restarted in patients who discontinued due to rash associated with prior treatment with lamotrigine unless the potential benefits clearly outweigh the risks. If the decision is made to restart a patient who has discontinued lamotrigine, the need to restart with the initial dosing recommendations should be assessed.
The greater the interval of time since the previous dose, the greater consideration should be given to restarting with the initial dosing recommendations. If a patient has discontinued lamotrigine for a period of more than 5 half-lives, it is recommended that initial dosing recommendations and guidelines be followed. The half-life of lamotrigine is affected by other concomitant medications [see Clinical Pharmacology (12.3 ) ].
Lamotrigine Added to Drugs Known to Induce or Inhibit Glucuronidation Because lamotrigine is metabolized predominantly by glucuronic acid conjugation, drugs that are known to induce or inhibit glucuronidation may affect the apparent clearance of lamotrigine. Drugs that induce glucuronidation include carbamazepine, phenytoin, phenobarbital, primidone, rifampin, estrogen-containing oral contraceptives, and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir. Valproate inhibits glucuronidation.
For dosing considerations for lamotrigine in patients on estrogen-containing contraceptives and atazanavir/ritonavir, see below and Table 13. For dosing considerations for lamotrigine in patients on other drugs known to induce or inhibit glucuronidation, see Tables 1, 2, 5-6, and 13. Target Plasma Levels for Patients with Epilepsy or Bipolar Disorder A therapeutic plasma concentration range has not been established for lamotrigine.
Dosing of lamotrigine tablets (chewable, dispersible) should be based on therapeutic response [see Clinical Pharmacology (12.3) ]. Women Taking Estrogen-Containing Oral Contraceptives Starting Lamotrigine in Women Taking Estrogen-Containing Oral Contraceptives: Although estrogen-containing oral contraceptives have been shown to increase the clearance of lamotrigine [see Clinical Pharmacology (12.3) ], no adjustments to the recommended dose-escalation guidelines for lamotrigine tablets (che…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Lamotrigine tablets (chewable, dispersible): 5 mg and 25 mg . (3.1, 16)
3.2Lamotrigine Tablets (chewable, dispersible) Lamotrigine tablets (chewable, dispersible), 5 mg are white to off-white, round shaped, flat beveled edged uncoated tablets, embossed “RDY” on one side and “225” on other side. The tablets are pleasantly flavored. Lamotrigine tablets (chewable, dispersible), 25 mg are white to off-white, modified capsule shaped, flat beveled edged uncoated tablets, embossed “RDY” on one side and “226” on other side.
The tablets are pleasantly flavored.
⛔ Contraindications ▾
4 CONTRAINDICATIONS Lamotrigine tablets (chewable, dispersible) are contraindicated in patients who have demonstrated hypersensitivity to the drug or its ingredients [see Boxed Warning, Warnings and Precautions ( 5.1 ), ( 5.2 )]. Hypersensitivity to the drug or its ingredients. ( Boxed Warning , 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Life-threatening serious rash and/or rash-related death: Discontinue at the first sign of rash, unless the rash is clearly not drug related. ( Boxed Warning , 5.1 ) Fatal or life-threatening hypersensitivity reaction: Multiorgan hypersensitivity reactions, also known as drug reaction with eosinophilia and systemic symptoms, may be fatal or life threatening. Early signs may include rash, fever, and lymphadenopathy.
These reactions may be associated with other organ involvement, such as hepatitis, hepatic failure, blood dyscrasias, or acute multiorgan failure. Lamotrigine should be discontinued if alternate etiology for this reaction is not found. (5.2) Blood dyscrasias (e.g., neutropenia, thrombocytopenia, pancytopenia): May occur, either with or without an associated hypersensitivity syndrome.
Monitor for signs of anemia, unexpected infection, or bleeding. (5.3) Suicidal behavior and ideation: Monitor for suicidal thoughts or behaviors. (5.4) Aseptic meningitis: Monitor for signs of meningitis.
(5.5) Medication errors due to product name confusion: Strongly advise patients to visually inspect tablets to verify the received drug is correct. ( 5.6 , 16 , 17 )
5.1Serious Skin Rashes [see Boxed Warning ] Pediatric Population The incidence of serious rash associated with hospitalization and discontinuation of lamotrigine in a prospectively followed cohort of pediatric patients (aged 2 to 17 years) is approximately 0.3% to 0.8%. One rash-related death was reported in a prospectively followed cohort of 1,983 pediatric patients (aged 2 to 16 years) with epilepsy taking lamotrigine as adjunctive therapy. Additionally, there have been rare cases of toxic epidermal necrolysis with and without permanent sequelae and/or death in US and foreign postmarketing experience.
There is evidence that the inclusion of valproate in a multidrug regimen increases the risk of serious, potentially life-threatening rash in pediatric patients. In pediatric patients who used valproate concomitantly for epilepsy, 1.2% (6 of 482) experienced a serious rash compared with 0.6% (6 of 952) patients not taking valproate. Adult Population Serious rash associated with hospitalization and discontinuation of lamotrigine occurred in 0.3% (11 of 3,348) of adult patients who received lamotrigine in premarketing clinical trials of epilepsy.
In the bipolar and other mood disorders clinical trials, the rate of serious rash was 0.08% (1 of 1,233) of adult patients who received lamotrigine as initial monotherapy and 0.13% (2 of 1,538) of adult patients who received lamotrigine as adjunctive therapy. No fatalities occurred among these individuals. However, in worldwide postmarketing experience, rare cases of rash-related death have been reported, but their numbers are too few to permit a precise estimate of the rate.
Among the rashes leading to hospitalization were Stevens-Johnson syndrome, toxic epidermal necrolysis, angioedema, and those associated with multiorgan hypersensitivity [see Warnings and Precautions ( 5.2 )]. There is evidence that the inclusion of valproate in a multidrug regimen increases the risk of serious, potentially life-threatening rash in adults. Specifically, of 584 patients administered lamotrigine with valproate in epilepsy clinical trials, 6 (1%) were hospitalized in association with rash; in contrast, 4 (0.16%) of 2,398 clinical trial patients and volunteers administered lamotrigine in the absence of valproate were hospitalized.
Patients with History of Allergy or Rash to Other Antiepileptic Drugs The risk of nonserious rash may be increased when the recommended initial dose and/or the rate of dose escalation for lamotrigine is exceeded and in patients with a history of allergy or rash to other AEDs.
5.2Multiorgan Hypersensitivity Reactions and Organ Failure Multiorgan hypersensitivity reactions, also known as drug reaction with eosinophilia and systemic symptoms (DRESS) have occurred with lamotrigine. Some have been fata…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are described in more detail in the Warnings and Precautions section of the label: • Serious skin rashes [see Warnings and Precautions (5.1) ] • Multiorgan hypersensitivity reactions and organ failure [see Warnings and Precautions ( 5.2 )] • Blood dyscrasias [see Warnings and Precautions (5.3) ] • Suicidal behavior and ideation [see Warnings and Precautions (5.4) ] • Aseptic meningitis [see Warnings and Precautions ( 5.5) ] • Withdrawal seizures [see Warnings and Precautions (5.8) ] • Status epilepticus [see Warnings and Precautions (5.9) ] • Sudden unexplained death in epilepsy [see Warnings and Precautions (5.10) ] Epilepsy: Most common adverse reactions (incidence ≥10%) in adults were dizziness, headache, diplopia, ataxia, nausea, blurred vision, somnolence, rhinitis, pharyngitis, and rash.
Additional adverse reactions (incidence ≥10%) reported in children included vomiting, infection, fever, accidental injury, diarrhea, abdominal pain, and tremor. (6.1) Bipolar disorder: Most common adverse reactions (incidence >5%) in adults were nausea, insomnia, somnolence, back pain, fatigue, rash, rhinitis, abdominal pain, and xerostomia. (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Dr.
Reddy’s Laboratories Inc., at 1-888-375-3784 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in practice. Epilepsy Most Common Adverse Reactions in All Clinical Trials: Adjunctive Therapy in Adults with Epilepsy : The most commonly observed (≥5% for lamotrigine and more common on drug than placebo) adverse reactions seen in association with lamotrigine during adjunctive therapy in adults and not seen at an equivalent frequency among placebo-treated patients were: dizziness, ataxia, somnolence, headache, diplopia, blurred vision, nausea, vomiting, and rash.
Dizziness, diplopia, ataxia, blurred vision, nausea, and vomiting were dose related. Dizziness, diplopia, ataxia, and blurred vision occurred more commonly in patients receiving carbamazepine with lamotrigine than in patients receiving other AEDs with lamotrigine. Clinical data suggest a higher incidence of rash, including serious rash, in patients receiving concomitant valproate than in patients not receiving valproate [see Warnings and Precautions (5.1) ].
Approximately 11% of the 3,378 adult patients who received lamotrigine as adjunctive therapy in premarketing clinical trials discontinued treatment because of an adverse reaction. The adverse reactions most commonly associated with discontinuation were rash (3.0%), dizziness (2.8%), and headache (2.5%). In a dose-response trial in adults, the rate of discontinuation of lamotrigine for dizziness, ataxia, diplopia, blurred vision, nausea, and vomiting was dose related.
Monotherapy in Adults with Epilepsy: The most commonly observed (≥5% for lamotrigine and more common on drug than placebo) adverse reactions seen in association with the use of lamotrigine during the monotherapy phase of the controlled trial in adults not seen at an equivalent rate in the control group were vomiting, coordination abnormality, dyspepsia, nausea, dizziness, rhinitis, anxiety, insomnia, infection, pain, weight decrease, chest pain, and dysmenorrhea. The most commonly observed (≥5% for lamotrigine and more common on drug than placebo) adverse reactions associated with the use of lamotrigine during the conversion to monotherapy (add-on) period, not seen at an equivalent frequency among low-dose valproate-treated patients, were dizziness, headache, nausea, asthenia, coordination abnormality, vomiting, rash, somnolence, diplopia, ataxia, accidental injury, tremor, blurred vision, insomnia, nystagmus, diarrhea, lymphadenopathy, pruritus…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Significant drug interactions with lamotrigine are summarized in this section. Additional details of these drug interaction studies are provided in the Clinical Pharmacology section [see Clinical Pharmacology (12.3 ) ]. Table 13.
Established and Other Potentially Significant Drug Interactions Concomitant Drug Effect on Concentration of Lamotrigine or Concomitant Drug Clinical Comment Estrogen-containing oral contraceptive preparations containing 30 mcg ethinylestradiol and 150 mcg levonorgestrel ↓ lamotrigine ↓ levonorgestrel Decreased lamotrigine concentrations approximately 50%. Decrease in levonorgestrel component by 19%. Carbamazepine and carbamazepine epoxide ↓ lamotrigine ? carbamazepine epoxide Addition of carbamazepine decreases lamotrigine concentration approximately 40%.
May increase carbamazepine epoxide levels Lopinavir/ritonavir ↓ lamotrigine Decreased lamotrigine concentration approximately 50%. Atazanavir/ritonavir ↓ lamotrigine Decreased lamotrigine AUCapproximately 32%. Phenobarbital/primidone ↓ lamotrigine Decreased lamotrigine concentration approximately 40%.
Phenytoin ↓ lamotrigine Decreased lamotrigine concentration approximately 40%. Rifampin ↓ lamotrigine Decreased lamotrigine AUC approximately 40%. Valproate ↑ lamotrigine ? valproate Increased lamotrigine concentrations slightly more than 2-fold.
There are conflicting study results regarding effect of lamotrigine on valproate concentrations: 1) a mean 25% decrease in valproate concentrations inhealthy volunteers, 2) no change in valproate concentrations in controlled clinical trials in patients with epilepsy. ↓ =Decreased (induces lamotrigine glucuronidation). ↑ =Increased (inhibits lamotrigine glucuronidation). ?= Conflicting data. Effect of Lamotrigine on Organic Cationic Transporter 2 SubstratesLamotrigine is an inhibitor of renal tubular secretion via organic cationic transporter 2 (OCT2) proteins [see Clinical Pharmacology (12.3) ].
This may result in increased plasma levels of certain drugs that are substantially excreted via this route. Coadministration of lamotrigine with OCT2 substrates with a narrow therapeutic index (e.g., dofetilide) is not recommended Valproate increases lamotrigine concentrations more than 2-fold. ( 7 , 12.3 ) Carbamazepine, phenytoin, phenobarbital, primidone, and rifampin decrease lamotrigine concentrations by approximately 40%.
( 7 , 12.3 ) Estrogen containing oral contraceptives decrease lamotrigine concentrations by approximately 50%. ( 7 , 12.3 ) Protease inhibitors lopinavir/ritonavir and atazanavir/lopinavir decrease lamotrigine exposure by approximately 50% and 32%, respectively. ( 7 , 12.3 ) Coadministration with organic cationic transporter 2 substrates with narrow therapeutic index is not recommended ( 7 , 12.3 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data may cause fetal harm. (8.1) Hepatic impairment: Dosage adjustments required in patients with moderate and severe liver impairment. ( 2.1 , 8.6 ) Renal impairment: Reduced maintenance doses may be effective for patients with significant renal impairment. ( 2.1 , 8.7 )
8.1Pregnancy As with other AEDs, physiological changes during pregnancy may affect lamotrigine concentrations and/or therapeutic effect. There have been reports of decreased lamotrigine concentrations during pregnancy and restoration of pre-partum concentrations after delivery. Dosage adjustments may be necessary to maintain clinical response.
Pregnancy Category C There are no adequate and well-controlled studies in pregnant women. In animal studies, lamotrigine was developmentally toxic at doses lower than those administered clinically. lamotrigine should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. When lamotrigine was administered to pregnant mice, rats, or rabbits during the period of organogenesis (oral doses of up to 125, 25, and 30 mg/kg, respectively), reduced fetal body weight and increased incidences of fetal skeletal variations were seen in mice and rats at doses that were also maternally toxic.
The no-effect doses for embryofetal developmental toxicity in mice, rats, and rabbits (75, 6.25, and 30 mg/kg, respectively) are similar to (mice and rabbits) or less than (rats) the human dose of 400 mg/day on a body surface area (mg/m 2 ) basis. In a study in which pregnant rats were administered lamotrigine (oral doses of 5 or 25 mg/kg) during the period of organogenesis and offspring were evaluated postnatally, behavioral abnormalities were observed in exposed offspring at both doses. The lowest effect dose for developmental neurotoxicity in rats is less than the human dose of 400 mg/day on a mg/m 2 basis.
Maternal toxicity was observed at the higher dose tested. When pregnant rats were administered lamotrigine (oral doses of 5, 10, or 20 mg/kg) during the latter part of gestation, increased offspring mortality (including stillbirths) was seen at all doses.The lowest effect dose for peri/postnatal developmental toxicity in rats is less than the human dose of 400 mg/day on a mg/m2 basis. Maternal toxicity was observed at the 2 highest doses tested.
Lamotrigine decreases fetal folate concentrations in rat, an effect known to be associated with adverse pregnancy outcomes in animals and humans. Pregnancy RegistryTo provide information regarding the effects of in utero exposure to lamotrigine, physicians are advised to recommend that pregnant patients taking lamotrigine enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry. This can be done by calling the toll free number 1-888-233-2334, and must be done by patients themselves.
Information on the registry can also be found at the website http://www.aedpregnancyregistry.org.
8.2Labor and Delivery The effect of lamotrigine on labor and delivery in humans is unknown.
8.3Nursing Mothers Lamotrigine is present in milk from lactating women taking lamotrigine tablets (chewable, dispersible). Data from multiple small studies indicate that lamotrigine plasma levels in human milk-fed infants have been reported to be as high as 50% of the maternal serum levels. Neonates and young infants are at risk for high serum levels because maternal serum and milk levels can rise to high levels postpartum if lamotrigine dosage has been increased during pregnancy but not later reduced to the pre-pregnancy dosage.
Lamotrigine exposure is further increased due to the immaturity of the infant glucuronidation capacity needed for drug clearance. Events including apnea, drowsiness, and poor sucking have been reported in infants who have been human milk-fed by mothers using lamotrigine; whether or not these events were caused by lamotrigine is unknown. Human milk-fed infants should be closely monitored for…
🆘 Overdosage ▾
10 OVERDOSAGE
10.1Human Overdose Experience Overdoses involving quantities up to 15 g have been reported for lamotrigine, some of which have been fatal. Overdose has resulted in ataxia, nystagmus, seizures (including tonic-clonic seizures), decreased level of consciousness, coma, and intraventricular conduction delay.
10.2Management of Overdose There are no specific antidotes for lamotrigine. Following a suspected overdose, hospitalization of the patient is advised. General supportive care is indicated, including frequent monitoring of vital signs and close observation of the patient.
If indicated, emesis should be induced; usual precautions should be taken to protect the airway. It should be kept in mind that immediate-release lamotrigine is rapidly absorbed [see Clinical Pharmacology (12.3) ]. It is uncertain whether hemodialysis is an effective means of removing lamotrigine from the blood.
In 6 renal failure patients, about 20% of the amount of lamotrigine in the body was removed by hemodialysis during a 4-hour session. A Poison Control Center should be contacted for information on the management of overdosage of lamotrigine.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The precise mechanism(s) by which lamotrigine exerts its anticonvulsant action are unknown. In animal models designed to detect anticonvulsant activity, lamotrigine was effective in preventing seizure spread in the maximum electroshock (MES) and pentylenetetrazol (scMet) tests, and prevented seizures in the visually and electrically evoked after-discharge (EEAD) tests for antiepileptic activity. Lamotrigine also displayed inhibitory properties in the kindling model in rats both during kindling development and in the fully kindled state.
The relevance of these models to human epilepsy, however, is not known. One proposed mechanism of action of lamotrigine, the relevance of which remains to be established in humans, involves an effect on sodium channels. In vitro pharmacological studies suggest that lamotrigine inhibits voltage-sensitive sodium channels, thereby stabilizing neuronal membranes and consequently modulating presynaptic transmitter release of excitatory amino acids (e.g., glutamate and aspartate).
Effect of Lamotrigine on N-Methyl d-Aspartate-Receptor Mediated Activity Lamotrigine did not inhibit N-methyl d-aspartate (NMDA)-induced depolarizations in rat cortical slices or NMDA-induced cyclic GMP formation in immature rat cerebellum, nor did lamotrigine displace compounds that are either competitive or noncompetitive ligands at this glutamate receptor complex (CNQX, CGS, TCHP). The IC50 for lamotrigine effects on NMDA-induced currents (in the presence of 3 µM of glycine) in cultured hippocampal neurons exceeded 100 µM.
The mechanisms by which lamotrigine exerts its therapeutic action in bipolar disorder have not been established.
12.2Pharmacodynamics Folate Metabolism In vitro, lamotrigine inhibited dihydrofolate reductase, the enzyme that catalyzes the reduction of dihydrofolate to tetrahydrofolate. Inhibition of this enzyme may interfere with the biosynthesis of nucleic acids and proteins. When oral daily doses of lamotrigine were given to pregnant rats during organogenesis, fetal, placental, and maternal folate concentrations were reduced.
Significantly reduced concentrations of folate are associated with teratogenesis [see Use in Specific Populations (8.1) ]. Folate concentrations were also reduced in male rats given repeated oral doses of lamotrigine. Reduced concentrations were partially returned to normal when supplemented with folinic acid.
Accumulation in Kidneys: Lamotrigine accumulated in the kidney of the male rat, causing chronic progressive nephrosis, necrosis, and mineralization. These findings are attributed to α-2 microglobulin, a species- and sex-specific protein that has not been detected in humans or other animal species. Melanin Binding Lamotrigine binds to melanin-containing tissues, e.g., in the eye and pigmented skin.
It has been found in the uveal tract up to 52 weeks after a single dose in rodents. Cardiovascular In dogs, lamotrigine is extensively metabolized to a 2-N-methyl metabolite. This metabolite causes dose-dependent prolongation of the PR interval, widening of the QRS complex, and, at higher doses, complete AV conduction block.
Similar cardiovascular effects are not anticipated in humans because only trace amounts of the 2-N-methyl metabolite (<0.6% of lamotrigine dose) have been found in human urine [see Clinical Pharmacology (12.3) ]. However, it is conceivable that plasma concentrations of this metabolite could be increased in patients with a reduced capacity to glucuronidate lamotrigine (e.g., in patients with liver disease, patients taking concomitant medications that inhibit glucuronidation).
12.3Pharmacokinetics The pharmacokinetics of lamotrigine have been studied in subjects with epilepsy, healthy young and elderly volunteers, and volunteers with chronic renal failure. Lamotrigine pharmacokinetic parameters for adult and pediatric subjects and healthy normal volunteers are summarized in Tables 14 and 16. Table 14. Mean Pha…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The precise mechanism(s) by which lamotrigine exerts its anticonvulsant action are unknown. In animal models designed to detect anticonvulsant activity, lamotrigine was effective in preventing seizure spread in the maximum electroshock (MES) and pentylenetetrazol (scMet) tests, and prevented seizures in the visually and electrically evoked after-discharge (EEAD) tests for antiepileptic activity. Lamotrigine also displayed inhibitory properties in the kindling model in rats both during kindling development and in the fully kindled state.
The relevance of these models to human epilepsy, however, is not known. One proposed mechanism of action of lamotrigine, the relevance of which remains to be established in humans, involves an effect on sodium channels. In vitro pharmacological studies suggest that lamotrigine inhibits voltage-sensitive sodium channels, thereby stabilizing neuronal membranes and consequently modulating presynaptic transmitter release of excitatory amino acids (e.g., glutamate and aspartate).
Effect of Lamotrigine on N-Methyl d-Aspartate-Receptor Mediated Activity Lamotrigine did not inhibit N-methyl d-aspartate (NMDA)-induced depolarizations in rat cortical slices or NMDA-induced cyclic GMP formation in immature rat cerebellum, nor did lamotrigine displace compounds that are either competitive or noncompetitive ligands at this glutamate receptor complex (CNQX, CGS, TCHP). The IC50 for lamotrigine effects on NMDA-induced currents (in the presence of 3 µM of glycine) in cultured hippocampal neurons exceeded 100 µM.
The mechanisms by which lamotrigine exerts its therapeutic action in bipolar disorder have not been established.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Lamotrigine Tablets (chewable, dispersible) Lamotrigine tablets (chewable, dispersible), 5 mg are white to off-white, round shaped, flat beveled edged uncoated tablets, embossed “RDY” on one side and “225” on other side. The tablets are pleasantly flavored and are supplied in bottles of 30, 60, 100, 500 and unit-dose packages of 100 (10 x 10). Bottles of 30 NDC 55111-225-30 Bottles of 60 NDC 55111-225-60 Bottles of 100 NDC 55111-225-01 Bottles of 500 NDC 55111-225-05 Unit dose package of 100 (10 x 10) NDC 55111-225-78 Lamotrigine tablets (chewable, dispersible), 25 mg are white to off-white, modified capsule shaped, flat beveled edged uncoated tablets, embossed “RDY” on one side and “226” on other side.
The tablets are pleasantly flavored and are supplied in bottles of 30, 60, 100, 500 and unit-dose packages of 100 (10 x 10). Bottles of 30 NDC 55111-226-30 Bottles of 60 NDC 55111-226-60 Bottles of 100 NDC 55111-226-01 Bottles of 500 NDC 55111-226-05 Unit dose package of 100 (10 x 10) NDC 55111-226-78 Store at 25°C (77°F); excursions permitted to 15-30°C (59-86°F) [see USP Controlled Room Temperature] in a dry place.
📋 Description ▾
11 DESCRIPTION Lamotrigine, an AED of the phenyltriazine class, is chemically unrelated to existing AEDs. lamotrigine's chemical name is 3,5-diamino-6-(2,3-dichlorophenyl)-as-triazine, its molecular formula is C 9 H 7 N 5 Cl 2 , and its molecular weight is 256.09. Lamotrigine USP is a white to pale cream-colored powder and has a pKa of 5.56. Lamotrigine USP is slightly soluble in methanol.
The structural formula is: Lamotrigine tablets (chewable, dispersible) are supplied for oral administration. The tablets contain 5 mg, or 25 mg of lamotrigine USP and the following inactive ingredients: black currant flavor, colloidal silicon dioxide, crospovidone, magnesium stearate, mannitol (pearlitol SD 200), microcrystalline cellulose (Avicel pH 112), microcrystalline cellulose and guar gum (Avicel CE 15), pregelatinized starch, sodium saccharin, and talc.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Rash Prior to initiation of treatment with lamotrigine, inform patients that a rash or other signs or symptoms of hypersensitivity (e.g., fever, lymphadenopathy) may herald a serious medical event and instruct them to report any such occurrence to their healthcare providers immediately. Multiorgan Hypersensitivity Reactions, Blood Dyscrasias, and Organ Failure Inform patients that multiorgan hypersensitivity reactions and acute multiorgan failure may occur with lamotrigine. Isolated organ failure or isolated blood dyscrasias without evidence of multiorgan hypersensitivity may also occur.
Instruct patients to contact their healthcare providers immediately if they experience any signs or symptoms of these conditions [see Warnings and Precautions ( 5.2 , 5.3 ) ]. Suicidal Thinking and Behavior Inform patients, their caregivers, and families that AEDs, including lamotrigine, may increase the risk of suicidal thoughts and behavior. Instruct them to be alert for the emergence or worsening of symptoms of depression, any unusual changes in mood or behavior, or the emergence of suicidal thoughts or behavior or thoughts about self-harm.
Instruct them to immediately report behaviors of concern to their healthcare providers. Worsening of Seizures Instruct patients to notify their healthcare providers if worsening of seizure control occurs. Central Nervous System Adverse Effects Inform patients that lamotrigine may cause dizziness, somnolence, and other symptoms and signs of central nervous system depression.
Accordingly, instruct them neither to drive a car nor to operate other complex machinery until they have gained sufficient experience on lamotrigine to gauge whether or not it adversely affects their mental and/or motor performance. Pregnancy and Nursing Instruct patients to notify their healthcare providers if they become pregnant or intend to become pregnant during therapy and if they intend to breastfeed or are breastfeeding an infant. Encourage patients to enroll in the NAAED Pregnancy Registry if they become pregnant.
This registry is collecting information about the safety of antiepileptic drugs during pregnancy. To enroll, patients can call the toll-free number 1-888-233-2334 [see Use in Specific Populations (8.1) ]. Inform patients who intend to breastfeed that lamotrigine is present in breast milk and advise them to monitor their child for potential adverse effects of this drug.
Discuss the benefits and risks of continuing breastfeeding. Oral Contraceptive Use Instruct women to notify their healthcare providers if they plan to start or stop use of oral contraceptives or other female hormonal preparations. Starting estrogen-containing oral contraceptives may significantly decrease lamotrigine plasma levels and stopping estrogen- containing oral contraceptives (including the pill-free week) may significantly increase lamotrigine plasma levels [see Warnings and Precautions (5.7) , Clinical Pharmacology (12.3) ].
Also instruct women to promptly notify their healthcare providers if they experience adverse reactions or changes in menstrual pattern (e.g., break-through bleeding) while receiving lamotrigine in combination with these medications. Discontinuing Lamotrigine Instruct patients to notify their healthcare providers if they stop taking lamotrigine for any reason and not to resume lamotrigine without consulting their healthcare providers. Aseptic Meningitis Inform patients that lamotrigine may cause aseptic meningitis.
Instruct them to notify their healthcare providers immediately if they develop signs and symptoms of meningitis such as headache, fever, nausea, vomiting, stiff neck, rash, abnormal sensitivity to light, myalgia, chills, confusion, or drowsiness while taking lamotrigine. Potential Medication Errors To avoid a medication error of using the wrong drug or formulation, strongly advise patients to visually inspect their tablets to verify that they are lamotrigine, as well as the cor…
💬 Medication Guide ▾
MEDICATION GUIDE Lamotrigine Tablets (chewable, dispersible) (la moe' tri jeen) What is the most important information I should know about lamotrigine? 1. Lamotrigine may cause a serious skin rash that may cause you to be hospitalized or even cause death. any time during your treatment with lamotrigine, but is more likely to happen within the first 2 to 8 weeks of treatment.
Children and teenagers aged between 2 and 17 years have a higher chance of getting this serious skin rash while taking lamotrigine. The risk of getting a serious skin rash is higher if you: take lamotrigine while taking valproate [(valproic acid) or (divalproex sodium)] take a higher starting dose of lamotrigine than your healthcare provider prescribed increase your dose of lamotrigine faster than prescribed. Call your healthcare provider right away if you have any of the following: a skin rash blistering or peeling of your skin hives painful sores in your mouth or around your eyes These symptoms may be the first signs of a serious skin reaction.
A healthcare provider should examine you to decide if you should continue taking lamotrigine. 2. Other serious reactions, including serious blood problems or liver problems.
Lamotrigine can also cause other types of allergic reactions or serious problems that may affect organs and other parts of your body like your liver or blood cells. You may or may not have a rash with these types of reactions. Call your healthcare provider right away if you have any of these symptoms: fever frequent infections severe muscle pain swelling of your face, eyes, lips, or tongue swollen lymph glands unusual bruising or bleeding weakness, fatigue yellowing of your skin or the white part of your eyes 3.
Like other antiepileptic drugs, lamotrigine may cause suicidal thoughts or actions in a very small number of people, about 1 in 500. Call a healthcare provider right away if you have any of these symptoms, especially if they are new, worse, or worry you: thoughts about suicide or dying attempt to commit suicidenew or worse depression new or worse anxietyfeeling agitated or restless panic attacks trouble sleeping (insomnia) new or worse irritability acting aggressive, being angry, or violent acting on dangerous impulses an extreme increase in activity and talking (mania) other unusual changes in behavior or mood Do not stop lamotrigine without first talking to a healthcare provider.
Stopping lamotrigine suddenly can cause serious problems. Suicidal thoughts or actions can be caused by things other than medicines. If you have suicidal thoughts or actions, your healthcare provider may check for other causes.
How can I watch for early symptoms of suicidal thoughts and actions in myself or a family member? Pay attention to any changes, especially sudden changes, in mood, behaviors, thoughts, or feelings. Keep all follow-up visits with your healthcare provider as scheduled.
Call your healthcare provider between visits as needed, especially if you are worriedabout symptoms. 4. Lamotrigine can cause aseptic meningitis, a serious inflammation of the protective membrane that covers the brain and spinal cord.
Call your healthcare provider right away if you have any of the following symptoms: headache fever nausea vomiting stiff neck rash unusual sensitivity to light muscle pains chills confusion drowsiness Meningitis has many causes other than lamotrigine, which your doctor would check for if you developed meningitis while taking lamotrigine. Lamotrigine can cause other serious side effects. For more information ask your healthcare provider or pharmacist.
Tell your healthcare provider if you have any side effect that bothers you. Be sure to read the section below entitled “What are the possible side effects of lamotrigine ?” 5. People prescribed lamotrigine have sometimes been given the wrong medicine because many medicines have names similar to lamotrigine, so always check that you receive lamotrigine.
Taking the wrong medication can cause serio…